
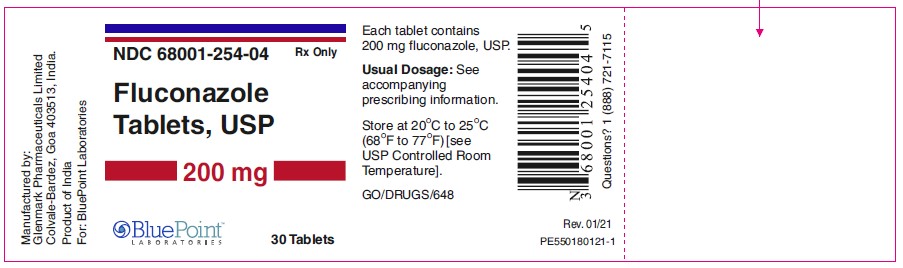
Fluconazole 200 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Azole Antifungal class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Fluconazole is used to treat fungal infections, including yeast infections of the vagina, mouth, throat, esophagus (tube leading from the mouth to the stomach), abdomen (area between the chest and waist), lungs, blood, and other organs. Fluconazole is also used to treat meningitis (infection of the membranes covering the brain and spine) caused by fungus. Fluconazole is also used to prevent yeast infections in patients who are likely to become infected because they are being treated with chemotherapy or radiation therapy before a bone marrow transplant (replacement of unhealthy spongy tissue i...
Read the full MedlinePlus article ↗- Yes, for a vaginal yeast infection, a single oral dose of fluconazole is the standard treatment with Diflucan or generic fluconazole tablets. Most people see their symptoms clear u...
- I was prescribed fluconazole for a yeast infection — do I really only need one pill?
- Good news — you can take fluconazole tablets with or without food, whichever is easier on your stomach. Studies showed that eating doesn't meaningfully change how much of the drug...
- Can I take fluconazole with food, or does it need to be on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fluconazole — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.392 | $11.77 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.12 | $33.69 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.4361 | $13.08 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fluconazole 200 mg 00904-6501-06 | Major | 50 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 16714-0693-01 | NorthStar | 30 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 50268-0339-15 | AvPAK | 50 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 55111-0146-01 | Dr. | 100 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 57237-0006-01 | Rising | 100 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 62135-0133-30 | Chartwell | 30 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 62559-0993-30 | ANI | 30 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mgthis 68001-0254-04 | BluePoint | 30 tablets | $0.392 | AB | Availability likely | — |
| Fluconazole 200 mg 68084-0735-01 | American | 100 tablets | $0.392 | AB | Availability likely | — |
| fluconazole 200 mg 70710-1140-01 | Zydus | 100 tablets | $0.392 | AB | Availability likely | — |
| fluconazole 200 mg 50090-4864-01 | A-S | 30 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 50090-6751-00 | A-S | 28 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 51407-0427-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 55154-7875-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 55289-0824-20 | PD-Rx | 20 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 61919-0493-03 | Direct | 3 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 63187-0878-01 | Proficient | 1 tablet | — | AB | FDA listed | — |
| Fluconazole 200 mg 63629-9091-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 65862-0061-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 68071-3428-02 | NuCare | 2 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 68071-3547-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 68462-0104-10 | Glenmark | 1000 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 68788-8526-00 | Preferred | 1 tablet | — | AB | FDA listed | — |
| Fluconazole 200 mg 70518-4020-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| fluconazole 200 mg 70771-1066-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| fluconazole 200 mg 71205-0283-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| fluconazole 200 mg 71335-0769-00 | Bryant | 4 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 71335-1895-00 | Bryant | 4 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 71335-2235-00 | Bryant | 4 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 72189-0516-03 | Direct_Rx | 3 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 77771-0399-01 | Radha | 100 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 82804-0030-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 82804-0146-06 | Proficient | 6 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 85766-0104-00 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 85766-0159-00 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
| Fluconazole 200 mg 87063-0206-00 | ASCLEMED | 100 tablets | — | AB | FDA listed | — |
| fluconazole 200 mg 68788-4163-00 | Preferred | 1 tablet | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68001-0254-04 You're viewing this | 30 TABLET in 1 BOTTLE (68001-254-04) | 2014-03-13 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Fluconazole tablets are indicated for the treatment of: Vaginal candidiasis (vaginal yeast infections due to Candida ). Oropharyngeal and esophageal candidiasis. In open noncomparative studies of relatively small numbers of patients, fluconazole tablets were also effective for the treatment of Candida urinary tract infections, peritonitis, and systemic Candida infections including candidemia, disseminated candidiasis, and pneumonia.
Cryptococcal meningitis. Before prescribing fluconazole tablets for AIDS patients with cryptococcal meningitis, please see CLINICAL STUDIES section. Studies comparing fluconazole tablets to amphotericin B in non-HIV infected patients have not been conducted.
Prophylaxis: Fluconazole tablets are also indicated to decrease the incidence of candidiasis in patients undergoing bone marrow transplantation who receive cytotoxic chemotherapy and/or radiation therapy. Specimens for fungal culture and other relevant laboratory studies (serology, histopathology) should be obtained prior to therapy to isolate and identify causative organisms. Therapy may be instituted before the results of the cultures and other laboratory studies are known; however, once these results become available, anti-infective therapy should be adjusted accordingly.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Dosage and Administration in Adults: Single Dose Vaginal candidiasis: The recommended dosage of fluconazole for vaginal candidiasis is 150 mg as a single oral dose. Multiple Dose SINCE ORAL ABSORPTION IS RAPID AND ALMOST COMPLETE, THE DAILY DOSE OF FLUCONAZOLE IS THE SAME FOR ORAL TABLETS AND INTRAVENOUS ADMINISTRATION. In general, a loading dose of twice the daily dose is recommended on the first day of therapy to result in plasma concentrations close to steady-state by the second day of therapy.
The daily dose of fluconazole for the treatment of infections other than vaginal candidiasis should be based on the infecting organism and the patient’s response to therapy. Treatment should be continued until clinical parameters or laboratory tests indicate that active fungal infection has subsided. An inadequate period of treatment may lead to recurrence of active infection.
Patients with AIDS and cryptococcal meningitis or recurrent oropharyngeal candidiasis usually require maintenance therapy to prevent relapse. Oropharyngeal candidiasis: The recommended dosage of fluconazole for oropharyngeal candidiasis is 200 mg on the first day, followed by 100 mg once daily. Clinical evidence of oropharyngeal candidiasis generally resolves within several days, but treatment should be continued for at least 2 weeks to decrease the likelihood of relapse.
Esophageal candidiasis: The recommended dosage of fluconazole for esophageal candidiasis is 200 mg on the first day, followed by 100 mg once daily. Doses up to 400 mg/day may be used, based on medical judgment of the patient’s response to therapy. Patients with esophageal candidiasis should be treated for a minimum of three weeks and for at least two weeks following resolution of symptoms.
Systemic Candida infections: For systemic Candida infections including candidemia , disseminated candidiasis, and pneumonia, optimal therapeutic dosage and duration of therapy have not been established. In open, noncomparative studies of small numbers of patients, doses of up to 400 mg daily have been used. Urinary tract infections and peritonitis: For the treatment of Candida urinary tract infections and peritonitis, daily doses of 50 to 200 mg have been used in open, noncomparative studies of small numbers of patients.
Cryptococcal meningitis: The recommended dosage for treatment of acute cryptococcal meningitis is 400 mg on the first day, followed by 200 mg once daily. A dosage of 400 mg once daily may be used, based on medical judgment of the patient’s response to therapy. The recommended duration of treatment for initial therapy of cryptococcal meningitis is 10 to 12 weeks after the cerebrospinal fluid becomes culture negative.
The recommended dosage of fluconazole for suppression of relapse of cryptococcal meningitis in patients with AIDS is 200 mg once daily. Prophylaxis in patients undergoing bone marrow transplantation : The recommended fluconazole daily dosage for the prevention of candidiasis in patients undergoing bone marrow transplantation is 400 mg, once daily. Patients who are anticipated to have severe granulocytopenia (less than 500 neutrophils cells/mm 3 ) should start fluconazole prophylaxis several days before the anticipated onset of neutropenia, and continue for 7 days after the neutrophil count rises above 1000 cells/mm 3 .
Dosage and Administration in Pediatric Patients: Oropharyngeal candidiasis : The recommended dosage of fluconazole for oropharyngeal candidiasis in pediatric patients 6 months and older is 6 mg/kg on the first day, followed by 3 mg/kg once daily. Treatment should be administered for at least 2 weeks to decrease the likelihood of relapse. Esophageal candidiasis : For the treatment of esophageal candidiasis, the recommended dosage of fluconazole in pediatric patients 6 months and older is 6 mg/kg on the first day, followed by 3 mg/kg once daily.
Doses up to 12 mg/kg/day may be used, based on medical judgment of the patient’s response to ther…
⛔ Contraindications ▾
CONTRAINDICATIONS Fluconazole tablets is contraindicated in patients who have shown hypersensitivity to fluconazole or to any of its excipients. There is no information regarding cross-hypersensitivity between fluconazole and other azole antifungal agents. Caution should be used in prescribing fluconazole to patients with hypersensitivity to other azoles.
Coadministration of other drugs known to prolong the QT interval and which are metabolized via the enzyme CYP3A4 such as erythromycin, pimozide, and quinidine are contraindicated in patients receiving fluconazole. (See CLINICAL PHARMACOLOGY: Drug Interaction Studies and PRECAUTIONS.)
⚠️ Warnings ▾
WARNINGS (1) Hepatic injury: Fluconazole should be administered with caution to patients with liver dysfunction. Fluconazole has been associated with rare cases of serious hepatic toxicity, including fatalities primarily in patients with serious underlying medical conditions. In cases of fluconazole-associated hepatotoxicity, no obvious relationship to total daily dose, duration of therapy, sex, or age of the patient has been observed.
Fluconazole hepatotoxicity has usually, but not always, been reversible on discontinuation of therapy. Patients who develop abnormal liver function tests during fluconazole therapy should be monitored for the development of more severe hepatic injury. Fluconazole should be discontinued if clinical signs and symptoms consistent with liver disease develop that may be attributable to fluconazole.
(2) Anaphylaxis: In rare cases, anaphylaxis has been reported. (3) Dermatologic: Exfoliative skin disorders during treatment with fluconazole have been reported. Fatal outcomes have been reported in patients with serious underlying diseases.
Patients with deep seated fungal infections who develop rashes during treatment with fluconazole should be monitored closely and the drug discontinued if lesions progress. Fluconazole should be discontinued in patients treated for superficial fungal infection who develop a rash that may be attributed to fluconazole. (4) Potential for fetal harm: There are no adequate and well-controlled clinical trials of fluconazole in pregnant women.
Case reports describe a pattern of distinct congenital anomalies in infants exposed in utero to high dose maternal fluconazole (400 to 800 mg/day) during most or all of the first trimester. These reported anomalies are similar to those seen in animal studies. If fluconazole is used during pregnancy or if the patient becomes pregnant while taking the drug, the patient should be informed of the potential hazard to the fetus.
Effective contraceptive measures should be considered in women of child-bearing potential who are being treated with fluconazole 400 to 800 mg/day and should continue throughout the treatment period and for approximately 1 week (5 to 6 half-lives) after the final dose. Epidemiological studies suggest a potential risk of spontaneous abortion and congenital abnormalities in infants whose mothers were treated with 150 mg of fluconazole as a single or repeated dose in the first trimester, but these epidemiological studies have limitations and these findings have not been confirmed in controlled clinical trials (See PRECAUTIONS: Pregnancy ).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Fluconazole is generally well tolerated. In some patients, particularly those with serious underlying diseases such as AIDS and cancer, changes in renal and hematological function test results and hepatic abnormalities have been observed during treatment with fluconazole and comparative agents, but the clinical significance and relationship to treatment is uncertain. In Patients Receiving a Single Dose for Vaginal Candidiasis: During comparative clinical studies conducted in the United States, 448 patients with vaginal candidiasis were treated with fluconazole, 150 mg single dose.
The overall incidence of side effects possibly related to fluconazole was 26%. In 422 patients receiving active comparative agents, the incidence was 16%. The most common treatment-related adverse events reported in the patients who received 150 mg single dose fluconazole for vaginitis were headache (13%), nausea (7%), and abdominal pain (6%).
Other side effects reported with an incidence equal to or greater than 1% included diarrhea (3%), dyspepsia (1%), dizziness (1%), and taste perversion (1%). Most of the reported side effects were mild to moderate in severity. Rarely, angioedema and anaphylactic reaction have been reported in marketing experience.
In Patients Receiving Multiple Doses for Other Infections: Sixteen percent of over 4000 patients treated with fluconazole in clinical trials of 7 days or more experienced adverse events. Treatment was discontinued in 1.5% of patients due to adverse clinical events and in 1.3% of patients due to laboratory test abnormalities. Clinical adverse events were reported more frequently in HIV infected patients (21%) than in non-HIV infected patients (13%); however, the patterns in HIV infected and non-HIV infected patients were similar.
The proportions of patients discontinuing therapy due to clinical adverse events were similar in the two groups (1.5%). The following treatment-related clinical adverse events occurred at an incidence of 1% or greater in 4048 patients receiving fluconazole for 7 or more days in clinical trials: nausea 3.7%, headache 1.9%, skin rash 1.8%, vomiting 1.7%, abdominal pain 1.7%, and diarrhea 1.5%. Hepato-biliary: In combined clinical trials and marketing experience, there have been rare cases of serious hepatic reactions during treatment with fluconazole (See WARNINGS ).
The spectrum of these hepatic reactions has ranged from mild transient elevations in transaminases to clinical hepatitis, cholestasis and fulminant hepatic failure, including fatalities. Instances of fatal hepatic reactions were noted to occur primarily in patients with serious underlying medical conditions (predominantly AIDS or malignancy) and often while taking multiple concomitant medications. Transient hepatic reactions, including hepatitis and jaundice, have occurred among patients with no other identifiable risk factors.
In each of these cases, liver function returned to baseline on discontinuation of fluconazole. In two comparative trials evaluating the efficacy of fluconazole for the suppression of relapse of cryptococcal meningitis, a statistically significant increase was observed in median AST (SGOT) levels from a baseline value of 30 IU/L to 41 IU/L in one trial and 34 IU/L to 66 IU/L in the other. The overall rate of serum transaminase elevations of more than 8 times the upper limit of normal was approximately 1% in fluconazole-treated patients in clinical trials.
These elevations occurred in patients with severe underlying disease, predominantly AIDS or malignancies, most of whom were receiving multiple concomitant medications, including many known to be hepatotoxic. The incidence of abnormally elevated serum transaminases was greater in patients taking fluconazole concomitantly with one or more of the following medications: rifampin, phenytoin, isoniazid, valproic acid, or oral sulfonylurea hypoglycemic agents. Post-Marketing Experience In addition, the following adverse events have…
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects. Potential for Fetal Harm: Use in pregnancy should be avoided except in patients with severe or potentially life-threatening fungal infections in whom fluconazole may be used if the anticipated benefit outweighs the possible risk to the fetus. A few published case reports describe a pattern of distinct congenital anomalies in infants exposed in utero to high dose maternal fluconazole (400 to 800 mg/day) during most or all of the first trimester.
These reported anomalies are similar to those seen in animal studies. Effective contraceptive measures should be considered in women of child-bearing potential who are being treated with fluconazole 400 to 800 mg/day and should continue throughout the treatment period and for approximately 1 week (5 to 6 half-lives) after the final dose. If fluconazole is used during pregnancy, or if the patient becomes pregnant while taking the drug, the patient should be informed of the potential hazard to the fetus.
Spontaneous abortions and congenital abnormalities have been suggested as potential risks associated with 150 mg of fluconazole as a single or repeated dose in the first trimester of pregnancy based on retrospective epidemiological studies. There are no adequate and well-controlled studies of fluconazole in pregnant women (See WARNINGS: Potential for Fetal Harm ). Human Data Case reports describe a distinctive and rare pattern of birth defects among infants whose mothers received high-dose (400 to 800 mg/day) fluconazole during most or all of the first trimester of pregnancy.
The features seen in these infants include brachycephaly, abnormal facies, abnormal calvarial development, cleft palate, femoral bowing, thin ribs and long bones, arthrogryposis, and congenital heart disease. These effects are similar to those seen in animal studies. Epidemiological studies suggest a potential risk of spontaneous abortion and congenital abnormalities in infants whose mothers were treated with 150 mg of fluconazole as a single or repeated dose in the first trimester, but these epidemiological studies have limitations and these findings have not been confirmed in controlled clinical trials.
Animal Data Fluconazole was administered orally to pregnant rabbits during organogenesis in two studies at doses of 5 mg/kg, 10 mg/kg, and 20 mg/kg and at 5 mg/kg, 25 mg/kg, and 75 mg/kg, respectively. Maternal weight gain was impaired at all dose levels (approximately 0.25 to 4 times the 400 mg clinical dose based on body surface area (BSA) comparison), and abortions occurred at 75 mg/kg (approximately 4 times the 400 mg clinical dose based on BSA); no adverse fetal effects were observed. In several studies in which pregnant rats received fluconazole orally during organogenesis, maternal weight gain was impaired and placental weights were increased at 25 mg/kg.
There were no fetal effects at 5 mg/kg or 10 mg/kg; increases in fetal anatomical variants (supernumerary ribs, renal pelvis dilation) and delays in ossification were observed at 25 mg/kg and 50 mg/kg and higher doses. At doses ranging from 80 to 320 mg/kg (approximately 2 to 8 times the 400 mg clinical dose based on BSA), embryolethality in rats was increased and fetal abnormalities included wavy ribs, cleft palate, and abnormal craniofacial ossification. These effects are consistent with the inhibition of estrogen synthesis in rats and may be a result of known effects of lowered estrogen on pregnancy, organogenesis, and parturition.
🧒 Pediatric Use ▾
Pediatric Use Use in Pediatric Patients for the Treatment of Oropharyngeal Candidiasis An open-label, randomized, controlled trial has shown fluconazole to be effective in the treatment of oropharyngeal candidiasis in pediatric patients 6 months to 13 years of age (See CLINICAL STUDIES). Use in Pediatric Patients for the Treatment of Candida Esophagitis, Systemic Candida Infections, or Cryptococcal Meningitis The use of fluconazole in pediatric patients with cryptococcal meningitis, Candida esophagitis, or systemic Candida infections is supported by the efficacy shown for these indications in adults and by the results from several small noncomparative pediatric clinical studies.
In addition, pharmacokinetic studies in pediatric patients (see CLINICAL PHARMACOLOGY ) have established a dose proportionality between pediatric patients and adults (See DOSAGE AND ADMINISTRATION ). In a noncomparative study of fluconazole administered to pediatric patients (from birth to less than 17 years) with serious systemic fungal infections, most of which were candidemia, the effectiveness of fluconazole was similar to that reported for the treatment of candidemia in adults. Of 17 subjects with culture-confirmed candidemia, 11 of 14 (79%) with baseline symptoms (3 were asymptomatic) had a clinical cure; 13/15 (87%) of evaluable patients had a mycologic cure at the end of treatment but two of these patients relapsed at 10 and 18 days, respectively, following cessation of therapy.
The efficacy of fluconazole for the suppression of cryptococcal meningitis was successful in 4 of 5 pediatric patients (4 years to 10 years of age) treated in a compassionate-use study of fluconazole for the treatment of life-threatening or serious mycosis. There are limited clinical data to support the efficacy of fluconazole for the primary treatment of cryptococcal meningitis in pediatric patients. The safety profile of fluconazole in children has been studied in 577 pediatric patients from 1 day to 17 years who received doses ranging from 1 to 15 mg/kg/day for 1 to 1,616 days (See ADVERSE REACTIONS).
Use in Pediatric Patients on Extracorporeal Membrane Oxygenation (ECMO). A prospective, open-label, single -center study was conducted to determine the PK and safety of fluconazole in pediatric patients (ages: from birth to 17 years of age) on ECMO (see CLINICAL PHARMACOLOGY). A loading dose of 35-mg/kg is recommended in pediatric patients on ECMO due to increased volume of distribution (see DOSAGE AND ADMINISTRATION).
Use in Prophylaxis of Invasive Candida Infections in Pediatric Patients (premature infants weighing less than 750 grams at birth) Safety and effectiveness of fluconazole tablets for the prophylaxis of invasive candidiasis in pediatric patients (premature infants weighing less than 750 grams at birth) have not been established. A prospective, randomized, double-blind, placebo-controlled, multicenter trail was conducted in premature infants weighing less than 750 grams at birth to evaluate the efficacy and safety of prophylactic fluconazole tablets 6-mg/kg administered twice weekly for 6 weeks versus placebo (NCT00734539).
Efficacy was assessed using the endpoint of death or candidiasis by study day 49. The results are summarized in Table 4. Table 4: Death or Candidiasis by day 49 in Premature Infants Receiving Fluconazole Prophylaxis Fluconazole (N=188) n (%) Placebo (N=173) n (%) P-value Difference (95% CI) Death or candidiasis* 33 (17.6) 38 (22.0) 0.2954 -4.4 (-12.6, 3.8) Components of endpoint** Death Candidiasis Missing 27 (14.4) 6 (3.2) 2 (1.0) 25 (14.5) 16 (9.2) 1 (0.5) *Subjects with missing data are imputed as having candidiasis or died. **Subjects may be counted more than once as two fluconazole subjects and four placebo subjects diagnosed with candidiasis subsequently died by day 49.
The most common fatal serious adverse reactions in the fluconazole tablets vs placebo arms, respectively, were necrotizing enterocolitis (NEC), 9 (5%); neonatal bact…
🧓 Geriatric Use ▾
Geriatric Use In non-AIDS patients, side effects possibly related to fluconazole treatment were reported in fewer patients aged 65 and older (9%, n =339) than for younger patients (14%, n=2240). However, there was no consistent difference between the older and younger patients with respect to individual side effects. Of the most frequently reported (>1%) side effects, rash, vomiting, and diarrhea occurred in greater proportions of older patients.
Similar proportions of older patients (2.4%) and younger patients (1.5%) discontinued fluconazole therapy because of side effects. In post-marketing experience, spontaneous reports of anemia and acute renal failure were more frequent among patients 65 years of age or older than in those between 12 and 65 years of age. Because of the voluntary nature of the reports and the natural increase in the incidence of anemia and renal failure in the elderly, it is however not possible to establish a causal relationship to drug exposure.
Controlled clinical trials of fluconazole did not include sufficient numbers of patients aged 65 and older to evaluate whether they respond differently from younger patients in each indication. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Fluconazole is primarily cleared by renal excretion as unchanged drug.
Because elderly patients are more likely to have decreased renal function, care should be taken to adjust dose based on creatinine clearance. It may be useful to monitor renal function (See CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE There have been reports of overdose with fluconazole accompanied by hallucination and paranoid behavior. In the event of overdose, symptomatic treatment (with supportive measures and gastric lavage if clinically indicated) should be instituted. Fluconazole is largely excreted in urine.
A 3-hour hemodialysis session decreases plasma levels by approximately 50%. In mice and rats receiving very high doses of fluconazole, clinical effects in both species included decreased motility and respiration, ptosis, lacrimation, salivation, urinary incontinence, loss of righting reflex, and cyanosis; death was sometimes preceded by clonic convulsions.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacokinetics and Metabolism The pharmacokinetic properties (PK) of fluconazole are similar following administration by the intravenous or oral routes. In normal volunteers, the bioavailability of orally administered fluconazole is over 90% compared with intravenous administration. Bioequivalence was established between the 100 mg tablet and both suspension strengths when administered as a single 200 mg dose.
Peak plasma concentrations (C max ) in fasted normal volunteers occur between 1 and 2 hours with a terminal plasma elimination half-life of approximately 30 hours (range: 20 to 50 hours) after oral administration. In fasted normal volunteers, administration of a single oral 400 mg dose of fluconazole leads to a mean C max of 6.72 mcg/mL (range: 4.12 to 8.08 mcg/mL) and after single or multiple oral doses of 50 to 400 mg, fluconazole plasma concentrations and area under the plasma concentration-time curve (AUC) are dose proportional (Table 1).
The C max and AUC data from a food-effect study involving administration of fluconazole tablets to healthy volunteers under fasting conditions and with a high-fat meal indicated that exposure to the drug is not affected by food. Therefore, fluconazole may be taken without regard to meals (See DOSAGE AND ADMINISTRATION ). Table 1: Mean Pharmacokinetic Parameters of Fluconazole in Adult Healthy Volunteers Following the Administration of Fluconazole Tablets.
Dose regimen C max (mcg/mL) AUC 0-24 (mcg* h/mL) Half-life (hours) 50 mg oral (once daily x 7 days) 2.21 37.6 26.6 100 mg oral (once daily x 7 days) 4.81 82.5 27.7 150 mg single oral 2.70 137* 34.1 200 mg oral (once daily x 14 days) 10.12 169.5 31 300 mg oral (once daily x 14 days) 15.98 299.4 34 400 mg oral (once daily x 14 days) 18.89 349.9 31 *AUC o-inf. C max = peak plasma concentrations, AUC – area under the plasma concentration time curve. Steady-state concentrations are reached within 5 to 10 days following oral doses of 50 to 400 mg given once daily.
Administration of a loading dose (on Day 1) of twice the usual daily dose results in plasma concentrations close to steady-state by the second day. The apparent volume of distribution of fluconazole approximates that of total body water. Plasma protein binding is low (11 to 12%).
Following either single- or multiple oral doses for up to 14 days, fluconazole penetrates into all body fluids studied (see table below). In normal volunteers, saliva concentrations of fluconazole were equal to or slightly greater than plasma concentrations regardless of dose, route, or duration of dosing. In patients with bronchiectasis, sputum concentrations of fluconazole following a single 150 mg oral dose were equal to plasma concentrations at both 4 and 24 hours post dose.
In patients with fungal meningitis, fluconazole concentrations in the cerebrospinal fluid (CSF) are approximately 80% of the corresponding plasma concentrations. A single oral 150 mg dose of fluconazole administered to 27 patients penetrated into vaginal tissue, resulting in tissue: plasma ratios ranging from 0.94 to 1.14 over the first 48 hours following dosing. A single oral 150 mg dose of fluconazole administered to 14 patients penetrated into vaginal fluid, resulting in fluid: plasma ratios ranging from 0.36 to 0.71 over the first 72 hours following dosing.
Table 2: Ratio of Fluconazole Tissue (Fluid)/ Plasma Concentration Tissue or Fluid Ratio of Fluconazole Tissue (Fluid)/Plasma Concentration* Cerebrospinal fluid† 0.5 to
0.9Saliva 1 Sputum 1 Blister fluid 1 Urine 10 Normal skin 10 Nails 1 Blister skin 2 Vaginal tissue 1 Vaginal fluid 0.4 to 0.7 * Relative to concurrent concentrations in plasma in subjects with normal renal function. † Independent of degree of meningeal inflammation. Mean body clearance in adults is reported to be 0.23 (17%) mL/min/kg. In normal volunteers, fluconazole is cleared primarily by renal excretion, with approximately 80% of the administered dose appearing in the urine as…
🧬 Mechanism of Action ▾
Mechanism of Action Fluconazole is a highly selective inhibitor of fungal cytochrome P450 dependent enzyme lanosterol 14-α-demethylase. This enzyme functions to convert lanosterol to ergosterol. The subsequent loss of normal sterols correlates with the accumulation of 14-α-methyl sterols in fungi and may be responsible for the fungistatic activity of fluconazole.
Mammalian cell demethylation is much less sensitive to fluconazole inhibition. Resistance A potential for development of resistance to fluconazole is well known. Fungal isolates exhibiting reduced susceptibility to other azoles may also show reduced susceptibility to fluconazole.
The frequency of drug resistance development for the various fungi for which this drug is indicated is not known. Fluconazole resistance may arise from a modification in the quality or quantity of the target enzyme (lanosterol 14-α-demethylase), reduced access to the drug target, or some combination of these mechanisms. Point mutations in the gene (ERG11) encoding for the target enzyme lead to an altered target with decreased affinity for azoles.
Overexpression of ERG11 results in the production of high concentrations of the target enzyme, creating the need for higher intracellular drug concentrations to inhibit all of the enzyme molecules in the cell. The second major mechanism of drug resistance involves active efflux of fluconazole out of the cell through the activation of two types of multidrug efflux transporters; the major facilitators (encoded by MDR genes) and those of the ATP-binding cassette superfamily (encoded by CDR genes). Upregulation of the MDR gene leads to fluconazole resistance, whereas, upregulation of CDR genes may lead to resistance to multiple azoles.
Resistance in Candida glabrata usually includes upregulation of CDR genes resulting in resistance to multiple azoles. For an isolate where the minimum inhibitory concentration (MIC) is categorized as Intermediate (16 to 32 mcg/mL), the highest fluconazole dose is recommended.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Fluconazole Tablets, USP, 50 mg are pink, trapezoidal shaped tablets, engraved with “50” on one side and plain on the other side, supplied as follows: NDC 68001-251-04 Bottles of 30 Fluconazole Tablets, USP 100 mg are pink, trapezoidal shaped tablets, engraved with “100” on one side and plain on the other side, supplied as follows: NDC 68001-252-04 Bottles of 30 Fluconazole Tablets, USP 150 mg are pink, oval shaped tablets, engraved with “150” on one side and plain on the other side, supplied as follows: NDC 68001-253-44 Carton of 1 blister pack of 1 tablet (1 X 1 unit-dose) NDC 68001-253-17 Carton of 12 blister packs of 1 tablet (12 X 1 unit-dose) Fluconazole Tablets, USP 200 mg are pink, trapezoidal shaped tablets, engraved with “200” on one side and plain on the other side, supplied as follows: NDC 68001-254-04 Bottles of 30 Storage: Store at 20 o C to 25 o C (68 o F to 77 o F). [see USP Controlled Room Temperature].
Manufactured by: Glenmark Pharmaceuticals Limited. Colvale-Bardez, Goa 403513, India. Manufactured for: BluePoint Laboratories Questions?
1(888)721-7115 Rev: 04/2024
📋 Description ▾
DESCRIPTION Fluconazole, USP the first of a new subclass of synthetic triazole antifungal agents, is available as tablets for oral administration. Fluconazole, USP is designated chemically as 2,4-difluoro-1’,1’-bis(1 H -1,2,4-triazol-1-ylmethyl) benzyl alcohol with an empirical formula of C 13 H 12 F 2 N 6 O and molecular weight of 306.27. The structural formula is: Fluconazole, USP is a white or almost white crystalline powder which is freely soluble in methanol; soluble in alcohol and in acetone, sparingly soluble in isopropanol and in chloroform; slightly soluble in water; very slightly soluble in toluene.
Fluconazole Tablets USP contain 50 mg, 100 mg, 150 mg, or 200 mg of fluconazole, USP and the following inactive ingredients: croscarmellose sodium, dibasic calcium phosphate anhydrous, FD&C Red No. 40, magnesium stearate, microcrystalline cellulose and povidone K-30. Formula image