
Brineura cerliponase alfa Kit — NDC 68135-811-02 (Billing 68135-0811-02)
This is a package of Brineura cerliponase alfa Kit from BioMarin Pharmaceutical Inc., marketed since Apr 2017 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 68135-811-02 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 68135 labeler · 811 product · 02 package
- Package marketed since
- Apr 27, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6813581102 2
- Medicaid fills, this package
- 72 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 077434
- GCN: 43455
- GPI-14 (Medi-Span): 30909020106420
- HICL (First Databank): 044258
- AHFS class code: 44:00.00.00
- RxCUI (RxNorm): 1922453
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Hydrolytic Lysosomal N-terminal Tripeptidyl Peptidase class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cerliponase alfa is used to slow the loss of being able to crawl or walk in children with neuronal ceroid lipofuscinosis type 2 (CLN2 disease; an inherited disease of the nervous system), also known as tripeptidyl peptidase 1 (TPP1) deficiency. Cerliponase alfa is in a class of medications called enzymes. It works by replacing the lack of TPP1 in the nervous system.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $13,391.79 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68135-0811-02 You're viewing this Main listing | 1 KIT in 1 CARTON * 5 mL in 1 VIAL, GLASS * 5 mL in 1 VIAL, GLASS | 2017-04-27 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Brineurathis 68135-0811-02 | BioMarin | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Apr 27, 2029 |
Is there a biosimilar for BRINEURA 2X150MG/5ML-ELYTE KIT?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from BioMarin Pharmaceutical Inc. labeler code 68135
- Kuvan SAPROPTERIN DIHYDROCHLORIDE 100 mg Tablet NDC 68135-300-02
- Kuvan SAPROPTERIN DIHYDROCHLORIDE 100 mg Powder, For Solution NDC 68135-301-22
- Kuvan sapropterin dihydrochloride 500 mg Powder, For Solution NDC 68135-482-11
- cerliponase alfa 150 mg/5mL Injection, Solution NDC 68135-502-00
- Palynziq pegvaliase-pqpz 20 mg/mL Injection, Solution NDC 68135-673-40
- Palynziq pegvaliase-pqpz 10 mg/.5mL Injection, Solution NDC 68135-756-20
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HYPERSENSITIVITY REACTIONS INCLUDING ANAPHYLAXIS Patients treated with enzyme replacement therapies have experienced life-threatening hypersensitivity reactions, including anaphylaxis. Anaphylaxis has occurred during the early course of enzyme replacement therapy and after extended duration of therapy. Initiate BRINEURA in a healthcare setting with appropriate medical monitoring and support measures, including access to cardiopulmonary resuscitation equipment.
If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue BRINEURA and immediately initiate appropriate medical treatment, including use of epinephrine. Inform patients of the symptoms of life-threatening hypersensitivity reactions, including anaphylaxis and to seek immediate medical care should symptoms occur [see Warnings and Precautions (5.1) ]. WARNING: HYPERSENSITIVITY REACTIONS INCLUDING ANAPHYLAXIS See full prescribing information for complete boxed warning Anaphylaxis has occurred during the early course of enzyme replacement therapy and after extended duration of therapy.
( 5.1 ) Initiate BRINEURA in a healthcare setting with appropriate medical monitoring and support measures, including access to cardiopulmonary resuscitation equipment. ( 5.1 ) If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue BRINEURA and immediately initiate appropriate medical treatment, including use of epinephrine. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BRINEURA is indicated to slow the loss of ambulation in pediatric patients with neuronal ceroid lipofuscinosis type 2 (CLN2 disease), also known as tripeptidyl peptidase 1 (TPP1) deficiency. BRINEURA is a hydrolytic lysosomal N-terminal tripeptidyl peptidase indicated to slow the loss of ambulation in pediatric patients with neuronal ceroid lipofuscinosis type 2 (CLN2 disease), also known as tripeptidyl peptidase 1 (TPP1) deficiency. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administration of BRINEURA should be supervised by a healthcare provider knowledgeable in the management of hypersensitivity reactions including anaphylaxis. ( 2.1 ) BRINEURA should be administered by or under the supervision of a physician experienced in intraventricular administration. ( 2.1 ) Premedication of patients with antihistamines with or without antipyretics or corticosteroids is recommended.
( 2.1 ) Prior to each infusion, inspect the scalp for signs of intraventricular access device reservoir leakage, failure, or potential infection. ( 2.1 ) Recommended BRINEURA dosage is 300 mg administered once every other week as an intraventricular infusion. In patients less than 2 years of age, lower doses are recommended.
( 2.2 ) Dosing is not recommended in patients less than 37 weeks post-menstrual age or those weighing less than 2.5 kg. ( 2.2 ) See the full prescribing information for dosage modifications due to hypersensitivity reactions. ( 2.3 ) See the full prescribing information for preparation and administration instructions.
( 2.4 , 2.6 )
2.1Recommendations Prior to BRINEURA Treatment Administration of BRINEURA should be supervised by a healthcare provider knowledgeable in the management of hypersensitivity reactions including anaphylaxis. Initiate BRINEURA in a healthcare setting with appropriate medical monitoring and support measures, including access to cardiopulmonary resuscitation equipment [see Warnings and Precautions (5.1) ] . BRINEURA should be administered by or under the supervision of a physician experienced in intraventricular administration via a surgically implanted intraventricular access device system which consists of the reservoir and catheter components [see Dosage and Administration (2.6) ] .
Premedication of patients with antihistamines with or without antipyretics or corticosteroids is recommended 30 to 60 minutes prior to the start of infusion [see Warnings and Precautions (5.1 , 5.5) ] . Aseptic technique must be strictly observed during preparation and administration [see Dosage and Administration (2.6) ] . Prior to each infusion of BRINEURA, inspect the scalp for signs of intraventricular access device reservoir leakage, failure or potential infection [see Warnings and Precautions (5.2 , 5.3) ] .
Prior to each infusion of BRINEURA and when clinically indicated, obtain a sample of CSF for cell count and culture [see Warnings and Precautions (5.2) ] . Replace the intraventricular access device reservoir prior to 4 years of single-puncture administrations [see Warnings and Precautions (5.3) ].
2.2Recommended Dosage and Administration The recommended dosage of BRINEURA in pediatric patients is provided in Table 1. The dose is administered once every other week by intraventricular infusion. BRINEURA is not recommended in patients less than 37 weeks post-menstrual age (gestational age at birth plus post-natal age) or those weighing less than 2.5 kg [see Use in Specific Populations (8.4) ].
Administer BRINEURA first followed by infusion of the Intraventricular Electrolytes. The complete BRINEURA infusion, including the required infusion of Intraventricular Electrolytes, is approximately 2 to 4.5 hours, depending on the dose and volume administered. See Table 1 for the appropriate volume and infusion rate.
For volumes that are not whole numbers, see Dosage and Administration (2.6) . Table 1: BRINEURA Dose, Volume, and Infusion Rate by Age Age groups BRINEURA dose administered every other week Volume of BRINEURA solution Infusion rate Birth to < 6 months 100 mg 3.3 mL 1.25 mL/hr 6 months to < 1 year 150 mg 5 mL 2.5 mL/hr 1 year to < 2 years 200 mg (first 4 doses) 6.7 mL (first 4 doses) 2.5 mL/hr 300 mg (subsequent doses) 10 mL (subsequent doses) 2 years and older 300 mg 10 mL 2.5 mL/hr Missed Dose If one or more doses are missed, restart BRINEURA treatment as soon as possible, maintaining the 2-week interval between infusions thereafter.
2.3Administration Modificati… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: BRINEURA 150 mg/5 mL (30 mg/mL) solution, two single-dose vials per carton co-packaged with Intraventricular Electrolytes Injection 5 mL in a single-dose vial. BRINEURA is a clear to slightly opalescent and colorless to pale yellow solution. Intraventricular Electrolytes is a clear to colorless solution [see How Supplied/Storage and Handling (16) ] .
Injection: BRINEURA 150 mg/5 mL (30 mg/mL) solution, two single-dose vials per carton co-packaged with Intraventricular Electrolytes Injection 5 mL in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS BRINEURA is contraindicated in patients with: any sign or symptom of acute, unresolved localized infection on or around the device insertion site (e.g., cellulitis or abscess); or suspected or confirmed CNS infection (e.g., cloudy CSF or positive CSF gram stain, or meningitis) [see Warnings and Precautions (5.2) ] . any acute intraventricular access device-related complication (e.g., leakage, extravasation of fluid, or device failure) [see Warnings and Precautions (5.3) ]. ventriculoperitoneal shunts.
Any sign or symptom of acute or unresolved localized infection on or around the device insertion site (e.g. cellulitis or abscess); or suspected or confirmed CNS infection (e.g., cloudy CSF or positive CSF gram stain, or meningitis). ( 4 ) Any acute intraventricular access device-related complication (e.g., leakage, extravasation of fluid, or device failure). ( 4 ) Patients with ventriculoperitoneal shunts.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Meningitis and Other Intraventricular Access Device-Related Infections : Monitor the device insertion site for signs of infection. ( 4 , 5.2 ) Intraventricular Access Device-Related Complications : Consult a neurosurgeon for any complications with the implanted device. In case of device-related complication, discontinue the infusion and refer to the device labeling for further instructions.
( 4 , 5.3 ) Cardiovascular Adverse Reactions : Monitor vital signs before, during, and post-infusion. Monitor Electrocardiogram (ECG) in patients with a history of bradycardia, conduction disorder, or with structural heart disease, during the infusion. In patients without cardiac abnormalities, perform regular 12-lead ECG evaluations every 6 months.
( 2.5 , 5.4 ) Infusion-Associated Reactions (IARs) : If an IAR occurs, decreasing the infusion rate, temporarily stopping the infusion, and/or administering antihistamines and/or antipyretics may ameliorate the symptoms. ( 5.5 )
5.1Hypersensitivity Reactions Including Anaphylaxis Life-threatening hypersensitivity reactions including anaphylaxis have been reported in patients treated with enzyme replacement therapies, including BRINEURA . BRINEURA-treated patients have had these reactions occur in clinical studies and postmarketing use [see Adverse Reactions (6) ] . In clinical Trial 1 and Trial 2 to 96 weeks, a total of 11 of 24 (46%) patients experienced hypersensitivity reactions during the infusion or within 24 hours of completion of the infusion.
Patients in clinical trials were routinely pre-medicated with antihistamines with or without antipyretics or corticosteroids, prior to infusion of BRINEURA. During postmarketing use, anaphylactic reactions occurred during or within several hours of BRINEURA infusion. Epinephrine was administered in these patients, and they received subsequent BRINEURA infusions without recurrence of anaphylaxis.
In Trial 3, hypersensitivity reactions were reported in 5 of 8 (63 %) patients less than 3 years of age at baseline as compared to 0 of 6 patients ≥ 3 years of age at baseline [see Adverse Reactions (6.1) ] . Of the reported hypersensitivity reactions, a single anaphylactic reaction occurred in a subject < 3 years of age. Anaphylaxis has occurred during the early course of enzyme replacement therapy and after extended duration of therapy.
Administration of BRINEURA should be supervised by a healthcare provider knowledgeable in the management of hypersensitivity reactions including anaphylaxis. Initiate BRINERUA in a healthcare setting with appropriate medical monitoring and support measures, including access to cardiopulmonary resuscitation equipment. Premedication of patients with antihistamines with or without antipyretics or corticosteroids is recommended 30 to 60 minutes prior to the start of infusion.
Observe patients closely during and after the infusion. If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue BRINEURA and immediately initiate appropriate medical treatment including use of epinephrine. Inform patients and caregivers of the symptoms of life-threatening hypersensitivity reactions, including anaphylaxis and to seek immediate medical care should symptoms occur.
The management of hypersensitivity reactions should be based on the severity of the reaction and may include temporarily interrupting the infusion, and/or treatment with antihistamines, antipyretics, and/or corticosteroids. Consider the risks and benefits of readministration of BRINEURA following an anaphylactic reaction. If the decision is made to readminister BRINEURA after the occurrence of anaphylaxis, ensure appropriately trained personnel and equipment for emergency resuscitation (including epinephrine and other emergency medicines) are readily available during infusion.
Initiate subsequent infusion at approximately one-half the initial infusion rate at which the anaphylactic reaction occurred.
5.2Meningitis and Other Intraven… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described below and elsewhere in the labeling: Hypersensitivity Reactions Including Anaphylaxis [see Warnings and Precautions (5.1) ] Meningitis and Other Intraventricular Access Device-Related Infections [see Warnings and Precautions (5.2) ] Intraventricular Access Device-Related Complications [see Warnings and Precautions (5.3) ] Cardiovascular Adverse Reactions [see Warnings and Precautions (5.4) ] Infusion-Associated Reactions [see Warnings and Precautions (5.5) ] Most common adverse reactions (≥8%) are: pyrexia, ECG abnormalities, decreased CSF protein, vomiting, seizures, device-related complications, hypersensitivity, increased CSF protein, hematoma, headache, irritability, pleocytosis, device-related infections, bradycardia, feeling jittery, and hypotension.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact BioMarin at 1-866-906-6100 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Trial 1 and Trial 2 The safety of BRINEURA was evaluated in 24 patients with CLN2 disease who received at least one 300 mg dose of BRINEURA given by intraventricular infusion in a clinical trial with extension (Trials 1 and 2) of up to 161 weeks [see Clinical Studies (14) ] .
Table 2 summarizes the most common adverse reactions that occurred in BRINEURA-treated patients through 96 weeks. Table 2: Adverse Reactions Reported in ≥ 8% of Symptomatic Pediatric Patients with CLN2 Disease in BRINEURA Trial 1 and Trial 2 at Week 96 Adverse Reaction Patients Treated with BRINEURA n=24 (%) Increased body temperature Increased body temperature includes: increased body temperature and pyrexia 17 (71) ECG abnormalities ECG abnormalities include: non-specific repolarization abnormality, notched QRS, ST segment elevation, biphasic T wave abnormality, supraventricular extrasystoles, bradycardia, sinus tachycardia, and intraventricular conduction delay 17 (71) Decreased CSF protein 17 (71) Vomiting 15 (63) Seizures Seizures include: atonic, generalized tonic-clonic, focal, and absence 12 (50) Device-related complications Device-related complications include device-related infection, delivery system-related complications (needle issues, device leakage, device malfunction, device difficult to use, medical device site irritation, device breakage, etc.) and pleocytosis.
12 (50) Hypersensitivity Hypersensitivity includes only hypersensitivity [see Warnings and Precautions (5.4) ] 9 (38) Increased CSF protein 5 (21) Hematoma 5 (21) Headache 4 (17) Irritability 4 (17) Pleocytosis 4 (17) Device-related infections Device-related infections include: Propionibacterium acnes and Staphylococcus epidermidis 2 (8) Bradycardia 2 (8) Feeling jittery 2 (8) Hypotension 2 (8) Description of Selected Adverse Reactions from Trial 1 and Trial 2 at 96 weeks Seizures Seizures were reported in 12 of 24 (50%) patients.
The seizure types reported include atonic, generalized tonic-clonic, focal, and absence. Seizures were managed with standard anti-convulsive therapies and did not result in discontinuation of BRINEURA treatment. Device-Related Complications Adverse reactions related to the device were observed in 12 of 24 (50%) of patients.
Device-related adverse reactions include infection, delivery system-related complications, and pleocytosis. Nine out of 24 patients (38%) experienced adverse reactions, which involved complications of the non-implanted delivery system components. Four out of 24 patients (16%) had device-related adverse reactions, which required medical intervention, including two patients (8%) with intraventricular access device-related CNS infections, and one patient (4%) each with leakage of the intraventricular ac… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on BRINEURA use in pregnant women to inform a drug-associated risk of pregnancy-related outcomes. Animal reproduction studies have not been conducted using cerliponase alfa. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
8.2Lactation Risk Summary There are no data on the presence of cerliponase alfa in human milk, the effects on the breastfed child, or the effects on milk production. The lack of clinical data during lactation precludes a clear determination of the risk of BRINEURA to an infant during lactation; therefore, the development and health benefits of breastfeeding should be considered along with the mother's clinical need for BRINEURA and any potential adverse effects on the breastfed infant from BRINEURA or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of BRINEURA have been established to slow the loss of ambulation in pediatric patients with CLN2 disease and the information on this use is discussed throughout the labeling. BRINEURA is not recommended for use in patients less than 37 weeks post-menstrual age (gestational age at birth plus post-natal age) or those weighing less than 2.5 kg due to physiologic immaturity which may increase risk of serious and clinically significant adverse reactions observed with BRINEURA [see Warnings and Precautions (5) ] .
Patients less than 3 years of age may be at increased risk for developing hypersensitivity reactions with BRINEURA use compared to patients 3 years of age and older [see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on BRINEURA use in pregnant women to inform a drug-associated risk of pregnancy-related outcomes. Animal reproduction studies have not been conducted using cerliponase alfa. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BRINEURA have been established to slow the loss of ambulation in pediatric patients with CLN2 disease and the information on this use is discussed throughout the labeling. BRINEURA is not recommended for use in patients less than 37 weeks post-menstrual age (gestational age at birth plus post-natal age) or those weighing less than 2.5 kg due to physiologic immaturity which may increase risk of serious and clinically significant adverse reactions observed with BRINEURA [see Warnings and Precautions (5) ] .
Patients less than 3 years of age may be at increased risk for developing hypersensitivity reactions with BRINEURA use compared to patients 3 years of age and older [see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action CLN2 disease is a neurodegenerative disease caused by deficiency of the lysosomal enzyme tripeptidyl peptidase-1 (TPP1), which catabolizes polypeptides in the CNS. TPP1 has no known substrate specificity. Deficiency in TPP1 activity results in the accumulation of lysosomal storage materials normally metabolized by this enzyme in the central nervous system (CNS), leading to progressive decline in motor function.
Cerliponase alfa (rhTTP1), a proenzyme, is taken up by target cells in the CNS and is translocated to the lysosomes through the Cation Independent Mannose-6-Phosphate Receptor (CI-MPR, also known as M6P/IGF2 receptor). Cerliponase alfa is activated in the lysosome and the activated proteolytic form of rhTPP1 cleaves tripeptides from the N-terminus of proteins.
12.2Pharmacodynamics No formal pharmacodynamic studies have been conducted with cerliponase alfa.
12.3Pharmacokinetics Patients 3 years of age and older The pharmacokinetics of cerliponase alfa were evaluated in patients with CLN2 disease who received intraventricular infusions of 30 mg (0.1 times the maximum approved recommended dosage), 100 mg (approximately 0.3 times the maximum approved recommended dosage), and 300 mg over approximately 4.5 hours once every other week. Cerliponase alfa CSF exposure following the initial single dose administration of BRINEURA increased less than proportionally across doses of 30 mg, 100 mg, and 300 mg.
There was no apparent accumulation of cerliponase alfa in CSF or plasma when BRINEURA was administered at a dose of 300 mg once every other week. Cerliponase alfa pharmacokinetics have high inter-subject and intra-subject variability. Following intraventricular infusions of 300 mg of BRINEURA at Day 1, Week 5, and Week 13, the pharmacokinetic parameters in CSF and plasma were assessed in 14 patients and are summarized in Table 4.
Table 4: Pharmacokinetic Parameters of Cerliponase Alfa Following Intraventricular Infusion (approximately 4.5 hours in duration) of BRINEURA 300 mg Every Two Weeks in Patients ≥ 3 years Parameter Median [Min, Max] Day 1 Week 5 Week 13 N 13 14 13 T max T max expressed as time since start of ~4.5 hour infusion. , hr 4.5 [4.3, 5.8] 4.3 [3.8, 4.5] 4.3 [4.0, 4.5] C max , mcg/mL 1260 [359, 4380] 1630 [376, 4670] 1390 [1110, 2340] CSF AUC 0-t , mcg-hr/mL 9290 [3660, 19000] 12400 [4620, 26200] 10500 [7000, 18200] V ss , mL 245 [78.4, 909] 196 [85.4, 665] 186 [131, 257] CL, mL/hr 32.3 [15.8, 81.9] 24.2 [11.4, 64.9] 28.7 [16.5, 42.9] t 1/2 , hr 6.2 [5.5, 16.3] 7.4 [3.3, 9.5] 7.7 [5.1, 9.4] N 12 12 9 Plasma V ss , CL, and t 1/2 were not estimated due to insufficient plasma pharmacokinetic data T max , hr 12.0 [4.3, 24.5] 12.0 [7.5, 24.2] 12.3 [4.3, 75.9] C max , mcg/mL 1.3 [0.2, 3.9] 1.9 [0.2, 4.3] 1.0 [0.03, 2.6] AUC 0-t , mcg-hr/mL 16.2 [1.1, 69.9] 40.1 [11.1, 78.9] 9.5 [0.2, 51.6] N 11 12 9 CSF/Plasma Ratio C max 1200 [305, 4530] 809 [202, 9370] 1320 [541, 51200] AUC 0-t 393 [115, 1910] 340 [126, 1780] 1330 [167, 38900] The estimated CSF volume of distribution of cerliponase alfa following intraventricular infusion of 300 mg of BRINEURA (median V ss = 245 mL) exceeds the typical CSF volume (100 mL).
Pediatric patients less than 3 years Pediatric CLN2 patients ages 1 to < 2 years (n=2) and 2 to < 3 years (n=6) were administered cerliponase alfa according to the recommended dosing regimen based on age for up to 144 weeks. CSF exposure with 300 mg cerliponase alfa was within the range characterized to be safe and effective in pivotal Trial 1. Plasma exposure in younger patients trended higher than the range characterized in the pivotal study.
The pharmacokinetic parameters summarized by age at time of visit and dose are shown in Table 5. Table 5: Pharmacokinetic Parameters of Cerliponase Alfa by Age at Visit and Dose Following Intraventricular Infusion of BRINEURA Every Two Weeks in Pediatric Patients < 3 years Age at Visit Dose (mg) Parameter Median [Min, Max] 1… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action CLN2 disease is a neurodegenerative disease caused by deficiency of the lysosomal enzyme tripeptidyl peptidase-1 (TPP1), which catabolizes polypeptides in the CNS. TPP1 has no known substrate specificity. Deficiency in TPP1 activity results in the accumulation of lysosomal storage materials normally metabolized by this enzyme in the central nervous system (CNS), leading to progressive decline in motor function.
Cerliponase alfa (rhTTP1), a proenzyme, is taken up by target cells in the CNS and is translocated to the lysosomes through the Cation Independent Mannose-6-Phosphate Receptor (CI-MPR, also known as M6P/IGF2 receptor). Cerliponase alfa is activated in the lysosome and the activated proteolytic form of rhTPP1 cleaves tripeptides from the N-terminus of proteins.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BRINEURA is supplied as a sterile, clear to slightly opalescent and colorless to pale yellow solution for intraventricular infusion and Intraventricular Electrolytes Injection is supplied as a clear to colorless solution for intraventricular infusion; both are included in package 1 of 2. The Administration Kit for use with BRINEURA is supplied separately as package 2 of 2 [see Dosage and Administration (2.4) ] . Package 1 of 2 Each BRINEURA (cerliponase alfa) Injection vial has a green flip-off cap (plastic) and contains 150 mg cerliponase alfa per 5 mL (30 mg/mL).
Each Intraventricular Electrolytes Injection vial has a yellow flip-off cap (plastic) and contains 5 mL of solution. Contents of Package 1 NDC Number BRINEURA (cerliponase alfa) Injection (2 vials of 150 mg/5 mL) Intraventricular Electrolytes Injection (1 vial, 5 mL) 68135-811-02 Package 2 of 2 The Administration Kit for use with BRINEURA is supplied separately and contains the following single-use, sterile infusion components: Two 20-mL syringes Two syringe needles (21 G, 25.4 mm) One extension line One infusion set with 0.2 micron inline filter One port needle (22 G, 16 mm) Storage BRINEURA (cerliponase alfa) Injection and Intraventricular Electrolytes Injection: Store upright in a freezer (-25°C to -15°C) in original carton to protect from light.
Administration Kit for use with BRINEURA: Store in original carton separately from BRINEURA. Do not freeze.
📦 Storage and Handling ▾
Storage BRINEURA (cerliponase alfa) Injection and Intraventricular Electrolytes Injection: Store upright in a freezer (-25°C to -15°C) in original carton to protect from light. Administration Kit for use with BRINEURA: Store in original carton separately from BRINEURA. Do not freeze.
📋 Description ▾
11 DESCRIPTION Cerliponase alfa is a purified human enzyme produced by recombinant DNA technology in a Chinese hamster ovary cell line. The active substance is a recombinant human tripeptidyl peptidase-1 (rhTPP1), a lysosomal exopeptidase. The primary activity of the mature enzyme is the cleavage of N-terminal tripeptides from a broad range of protein substrates.
Cerliponase alfa contains 544 amino acids with an average molecular mass of 59 kDa. The mature enzyme is 368 amino acids in length. There are 5 consensus N-glycosylation sites on rhTPP1 that contain high mannose, phosphorylated high mannose and complex glycosylation structures.
BRINEURA (cerliponase alfa) Injection and Intraventricular Electrolytes Injection are administered by intraventricular infusion. The solutions are sterile, nonpyrogenic, and free of foreign particulates. BRINEURA is a clear to slightly opalescent and colorless to pale yellow solution.
Intraventricular Electrolytes is a clear to colorless solution. BRINEURA and Intraventricular Electrolytes Injection are packaged in 10 mL clear Type 1 single-dose glass vials [see How Supplied/Storage and Handling (16) ]. Each vial of BRINEURA provides 5 mL of solution containing 150 mg cerliponase alfa.
Each vial of Intraventricular Electrolytes Injection provides 5 mL of solution. Both BRINEURA and Intraventricular Electrolytes Injection are formulated with the following excipients: calcium chloride dihydrate (1.05 mg); magnesium chloride hexahydrate (0.8 mg); potassium chloride (1.1 mg); sodium chloride (43.85 mg); sodium phosphate, dibasic, heptahydrate (0.55 mg); sodium phosphate, monobasic, monohydrate (0.4 mg); and Water for Injection, USP. The pH of the solution is between 6.2 to 6.8 for BRINEURA, and between 6.0 to 7.0 for Intraventricular Electrolytes Injection.
Each vial contains: sodium: 0.76 mEq, and potassium: 0.015 mEq.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Including Anaphylaxis and Infusion-Associated Reactions (IARs) Advise patients and caregivers that life-threatening hypersensitivity reactions, including anaphylaxis, and IARs may occur with BRINEURA treatment. Advise patients and caregivers that anaphylaxis has occurred during the early course of enzyme replacement therapy and after extended duration of therapy. Inform patients and caregivers of the symptoms of life-threatening hypersensitivity reactions, including anaphylaxis, and IARs and to seek immediate medical care should symptoms occur [see Warnings and Precautions (5.1 , 5.5) ] .
Intraventricular Access Device-Related Infections Advise patients and caregivers of the risk of device-related infections, including meningitis. Familiarize them with the signs and symptoms of these infections and instruct them to immediately contact their healthcare provider if an infection is suspected [see Warnings and Precautions (5.2) ] . Cardiovascular Adverse Reactions Advise patients and caregivers that hypotension and/or bradycardia may occur during and following the infusion of BRINEURA.
Instruct patients immediately to contact their healthcare provider if these reactions occur [see Warnings and Precautions (5.4) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Patients 3 years of age and older The pharmacokinetics of cerliponase alfa were evaluated in patients with CLN2 disease who received intraventricular infusions of 30 mg (0.1 times the maximum approved recommended dosage), 100 mg (approximately 0.3 times the maximum approved recommended dosage), and 300 mg over approximately 4.5 hours once every other week. Cerliponase alfa CSF exposure following the initial single dose administration of BRINEURA increased less than proportionally across doses of 30 mg, 100 mg, and 300 mg.
There was no apparent accumulation of cerliponase alfa in CSF or plasma when BRINEURA was administered at a dose of 300 mg once every other week. Cerliponase alfa pharmacokinetics have high inter-subject and intra-subject variability. Following intraventricular infusions of 300 mg of BRINEURA at Day 1, Week 5, and Week 13, the pharmacokinetic parameters in CSF and plasma were assessed in 14 patients and are summarized in Table 4.
Table 4: Pharmacokinetic Parameters of Cerliponase Alfa Following Intraventricular Infusion (approximately 4.5 hours in duration) of BRINEURA 300 mg Every Two Weeks in Patients ≥ 3 years Parameter Median [Min, Max] Day 1 Week 5 Week 13 N 13 14 13 T max T max expressed as time since start of ~4.5 hour infusion. , hr 4.5 [4.3, 5.8] 4.3 [3.8, 4.5] 4.3 [4.0, 4.5] C max , mcg/mL 1260 [359, 4380] 1630 [376, 4670] 1390 [1110, 2340] CSF AUC 0-t , mcg-hr/mL 9290 [3660, 19000] 12400 [4620, 26200] 10500 [7000, 18200] V ss , mL 245 [78.4, 909] 196 [85.4, 665] 186 [131, 257] CL, mL/hr 32.3 [15.8, 81.9] 24.2 [11.4, 64.9] 28.7 [16.5, 42.9] t 1/2 , hr 6.2 [5.5, 16.3] 7.4 [3.3, 9.5] 7.7 [5.1, 9.4] N 12 12 9 Plasma V ss , CL, and t 1/2 were not estimated due to insufficient plasma pharmacokinetic data T max , hr 12.0 [4.3, 24.5] 12.0 [7.5, 24.2] 12.3 [4.3, 75.9] C max , mcg/mL 1.3 [0.2, 3.9] 1.9 [0.2, 4.3] 1.0 [0.03, 2.6] AUC 0-t , mcg-hr/mL 16.2 [1.1, 69.9] 40.1 [11.1, 78.9] 9.5 [0.2, 51.6] N 11 12 9 CSF/Plasma Ratio C max 1200 [305, 4530] 809 [202, 9370] 1320 [541, 51200] AUC 0-t 393 [115, 1910] 340 [126, 1780] 1330 [167, 38900] The estimated CSF volume of distribution of cerliponase alfa following intraventricular infusion of 300 mg of BRINEURA (median V ss = 245 mL) exceeds the typical CSF volume (100 mL).
Pediatric patients less than 3 years Pediatric CLN2 patients ages 1 to < 2 years (n=2) and 2 to < 3 years (n=6) were administered cerliponase alfa according to the recommended dosing regimen based on age for up to 144 weeks. CSF exposure with 300 mg cerliponase alfa was within the range characterized to be safe and effective in pivotal Trial 1. Plasma exposure in younger patients trended higher than the range characterized in the pivotal study.
The pharmacokinetic parameters summarized by age at time of visit and dose are shown in Table 5. Table 5: Pharmacokinetic Parameters of Cerliponase Alfa by Age at Visit and Dose Following Intraventricular Infusion of BRINEURA Every Two Weeks in Pediatric Patients < 3 years Age at Visit Dose (mg) Parameter Median [Min, Max] 1 to < 2 years 200 CSF N 3 C max , mcg/mL 511 [163, 987] AUC 0-t , mcg-hr/mL 2720 [1100, 5050] Plasma N 2 C max , mcg/mL 10.4 [9.46, 11.3] AUC 0-t , mcg-hr/mL 91.8 [72.7, 111] 300 CSF N 2 C max , mcg/mL 566 [496, 636] AUC 0-t , mcg-hr/mL 8030 [8030, 8030] N=1 due to less than 3 evaluable datapoints for determination of AUC 0-t Plasma N 2 C max , mcg/mL 14.1 [11.2, 17.0] AUC 0-t , mcg-hr/mL 145 [82.7, 206] 2 to < 3 years 300 CSF N 6 C max , mcg/mL 896 [508, 1790] AUC 0-t , mcg-hr/mL 4100 [2380, 6720] N=5 due to less than 3 evaluable datapoints for determination of AUC 0-t Plasma N 6 C max , mcg/mL 14.9 [9.08, 35.3] AUC 0-t , mcg-hr/mL 163 [91.5, 320] Cerliponase alfa is a protein and is expected to be degraded through peptide hydrolysis.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics No formal pharmacodynamic studies have been conducted with cerliponase alfa.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of BRINEURA was assessed over 96 weeks in a non-randomized single-arm dose escalation clinical study with extension in symptomatic pediatric patients with late infantile neuronal ceroid lipofuscinosis type 2 (CLN2) disease, confirmed by TPP1 deficiency. BRINEURA-treated patients were compared to untreated patients from a natural history cohort. The Motor domain of a CLN2 Clinical Rating Scale was used to assess disease progression.
Scores ranged from 3 (grossly normal) to 0 (profoundly impaired) with unit decrements representing milestone events in the loss of motor function (ability to walk or crawl). Due to the inability to establish comparability for the CLN2 Language domain ratings between the clinical study with extension and the natural history cohort, efficacy of BRINEURA for the Language domain cannot be established. Twenty-four patients, aged 3 to 8 years were enrolled in the BRINEURA single-arm clinical study (Trial 1, NCT01907087).
Sixty-three percent of patients were female and 37% were male. Ninety-six percent of patients were White and 4% were Asian; for ethnicity, 4% identified as Hispanic/Latino, 96% as non-Hispanic/Latino. One patient withdrew after week 1 due to inability to continue with study procedures; 23 patients were treated with BRINEURA 300 mg every other week by intraventricular infusion for 48 weeks, and continued treatment during the 240-week extension period, Trial 2 (NCT02485899), for a total duration of 288 weeks, plus a 24-week safety follow-up.
In the clinical study with extension, patients were assessed for decline in the Motor domain of the CLN2 Clinical Rating Scale at 48, 72 and 96 weeks. Decline was defined as having an unreversed (sustained) 2-category decline or an unreversed score of 0 in the Motor domain of the CLN2 Clinical Rating Scale. Patients' responses to BRINEURA treatment were evaluated if at screening a combined Motor plus Language CLN2 score of less than 6 was recorded.
Two patients with a combined Motor plus Language CLN2 score of 6 were excluded from the analyses; they maintained that score throughout the study period. The patient who terminated early was analyzed as having a decline at the time of termination. Data used in the analyses from the natural history cohort began at 36 months of age or greater and at the first time a Motor plus Language CLN2 score less than 6 was recorded.
Motor scores of the 22 BRINEURA-treated patients in the clinical study with extension were compared to scores of the independent natural history cohort that included 42 untreated patients who satisfied inclusion criteria for the clinical study. The results of logistic modeling with covariates (screening age, screening motor score, genotype: 0 key mutations (yes/no)), demonstrated the odds of BRINEURA-treated patients not having a decline by 96 weeks were 13 times the odds of natural history cohort patients not having a decline (Odds Ratio (95% CI): 13.1 (1.2, 146.9)).
Descriptive non-randomized comparison In an unadjusted non-randomized comparison, of the 22 patients treated with BRINEURA and evaluated for efficacy at week 96, 21 (95%) did not decline, and only the patient who terminated early was deemed to have a decline in the Motor domain of the CLN2 Clinical Rating Scale. Results from the natural history cohort demonstrated progressive decline in motor function; of the 42 patients in the natural history cohort, 21 (50%) experienced an unreversed (sustained) 2-category decline or unreversed score of 0 in the Motor domain of the CLN2 Clinical Rating Scale over 96 weeks.
Given the non-randomized study design, a Cox Proportional Hazards Model adjusted for age, initial motor score, and genotype was used to evaluate time to unreversed 2-category decline or unreversed score of 0 in the Motor domain. This model showed a lesser decrease in motor function in the BRINEURA-treated patients when compared to the natural history cohort (see Figure 7 ). Figure 7.
Estimated… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity, genotoxicity, and fertility studies have not been performed with cerliponase alfa. Based on the mechanism of action, cerliponase alfa is not expected to be tumorigenic.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity, genotoxicity, and fertility studies have not been performed with cerliponase alfa. Based on the mechanism of action, cerliponase alfa is not expected to be tumorigenic.
📄 Recent Major Changes ▾
Boxed Warning 7/2024 Indication and Usage ( 1 ) 7/2024 Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.6 ) 7/2024 Warnings and Precautions ( 5.1 , 5.5 ) 7/2024
📄 Package Label / Principal Display Panel ▾
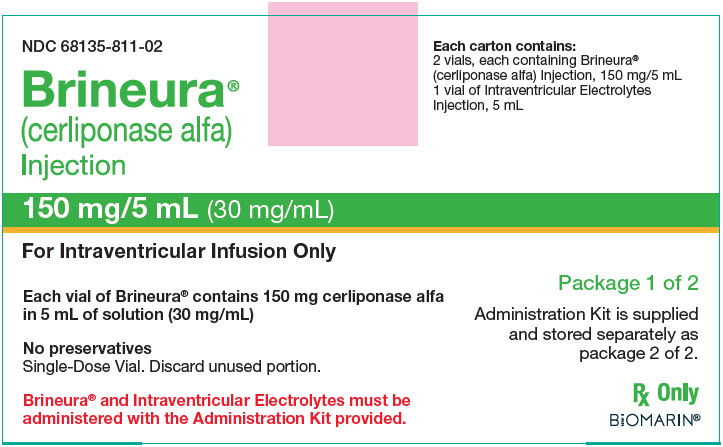
PRINCIPAL DISPLAY PANEL - Kit Carton - Package 1 NDC 68135-811-02 Brineura ® (cerliponase alfa) Injection 150 mg/5 mL (30 mg/mL) For Intraventricular Infusion Only Each vial of Brineura ® contains 150 mg cerliponase alfa in 5 mL of solution (30 mg/mL) No preservatives Single-Dose Vial. Discard unused portion. Brineura ® and Intraventricular Electrolytes must be administered with the Administration Kit provided.
Each carton contains: 2 vials, each containing Brineura ® (cerliponase alfa) Injection, 150 mg/5 mL 1 vial of Intraventricular Electrolytes Injection, 5 mL Package 1 of 2 Administration Kit is supplied and stored separately as package 2 of 2. Rx Only BIOMARIN ® PRINCIPAL DISPLAY PANEL - Kit Carton - Package 1
PRINCIPAL DISPLAY PANEL - 150 mg/5 mL Vial Label Brineura ® (cerliponase alfa) Injection 150 mg/5 mL (30 mg/mL) For Intraventricular Infusion Only Use before Intraventricular Electrolytes PRINCIPAL DISPLAY PANEL - 150 mg/5 mL Vial Label
PRINCIPAL DISPLAY PANEL - 5 mL Vial Label Intraventricular Electrolytes Injection Use after Brineura ® (cerliponase alfa) 5 mL For Intraventricular Infusion Only PRINCIPAL DISPLAY PANEL - 5 mL Vial Label
PRINCIPAL DISPLAY PANEL - Kit Carton - Package 2 Administration Kit for use with Brineura ® (cerliponase alfa) Intraventricular infusion only Recommended Dosage: See Prescribing Information Contents of Administration Kit: Two single-use 20-mL syringes Two single-use syringe needles, 21 G, 25.4 mm One single-use extension line One single-use infusion set with 0.2 micron inline filter One single-use port needle, 22 G, 16 mm Package 2 of 2 Brineura ® and Intraventricular Electrolytes Injection are separately supplied and stored frozen as package 1 of 2 Not for resale Only for use with Brineura ® Caution: - Do not use if the seals or package are damaged. - Do not resterilize. - Single use only.
Do not reuse. - Do not freeze. - Store in original package separately from Brineura ® . NOTE: - This Administration Kit has no components made of natural latex rubber. - Individual devices are provided in separate sterile packaging. - Expiration dates may vary for each device included. Manufactured for BioMarin Pharmaceutical Inc.
Novato, CA 94949 www.bmrn.com Rx Only BIOMARIN ® PRINCIPAL DISPLAY PANEL - Kit Carton - Package 2
Medicaid utilization & spend
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |