
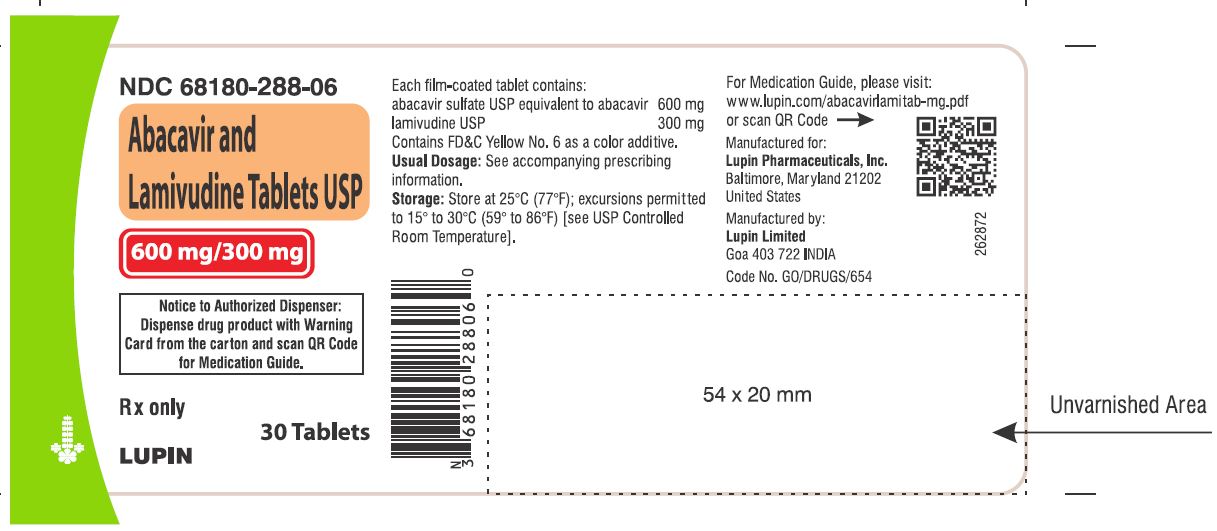
Abacavir and Lamivudine 600 mg; 300 mg Tablet, Film Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Abacavir is used to treat human immunodeficiency virus (HIV) infection. Abacavir is in a class of medications called nucleoside reverse transcriptase inhibitors (NRTIs). It works by decreasing the amount of HIV in the blood. Although abacavir does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.209 | $36.27 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Abacavir and Lamivudine 600 mg/1; 300 mgthis 68180-0288-06 | Lupin | 30 tablets | $1.209 | AB | Discontinued | — |
| ABACAVIR and LAMIVUDINE 600 mg/1; 300 mg 31722-0838-30 | Camber | 30 tablets | $1.469 | AB | Availability likely | +21% |
| Abacavir and Lamivudine 600 mg/1; 300 mg 69097-0362-02 | Cipla | 30 tablets | $1.469 | AB | Availability likely | +21% |
| Abacavir and Lamivudine 600 mg/1; 300 mg 33342-0440-07 | Macleods | 30 tablets | — | — | FDA listed | — |
| Abacavir and Lamivudine 600 mg/1; 300 mg 42385-0962-18 | Laurus | 180 tablets | — | AB | FDA listed | — |
| Abacavir and Lamivudine 600 mg/1; 300 mg 65862-0335-10 | Aurobindo | 10 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 68180-0288-06 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE (68180-288-06) | $1.21 / ea | $36.27 | 2017-03-28 | Discontinued by firm |
| 68180-0288-09 | 90 TABLET, FILM COATED in 1 BOTTLE (68180-288-09) | — | — | 2017-03-28 | Active |
| 68180-0288-33 | 750 TABLET, FILM COATED in 1 POUCH (68180-288-33) | — | — | 2017-03-28 | Active |
You're viewing the smallest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 68180-0288-06?
What is the difference between NDC 68180-0288-06 and NDC 68180-0288-09?
What NDC number is used to bill for this package of Abacavir and Lamivudine 600 mg; 300 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HYPERSENSITIVITY REACTIONS AND EXACERBATIONS OF HEPATITIS B WARNING: HYPERSENSITIVITY REACTIONS AND EXACERBATIONS OF HEPATITIS B See full prescribing information for complete boxed warning. Hypersensitivity Reactions Serious and sometimes fatal hypersensitivity reactions have occurred with abacavir-containing products. ( 5.1 ) Hypersensitivity to abacavir is a multi-organ clinical syndrome.
( 5.1 ) Patients who carry the HLA-B*5701 allele are at a higher risk of experiencing a hypersensitivity reaction to abacavir. ( 5.1 ) Abacavir and lamivudine tablets are contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients. ( 4 ) Discontinue abacavir and lamivudine tablets as soon as a hypersensitivity reaction is suspected.
Regardless of HLA-B*5701 status, permanently discontinue abacavir and lamivudine tablets if hypersensitivity cannot be ruled out, even when other diagnoses are possible. ( 5.1 ) Following a hypersensitivity reaction to abacavir and lamivudine tablets, NEVER restart abacavir and lamivudine tablets or any other abacavir-containing product. ( 5.1 ) Exacerbations of Hepatitis B Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with hepatitis B virus (HBV) and human immunodeficiency virus (HIV-1) and have discontinued lamivudine, a component of abacavir and lamivudine tablets.
Monitor hepatic function closely in these patients and, if appropriate, initiate anti-hepatitis B treatment. ( 5.2 ) Hypersensitivity Reactions Serious and sometimes fatal hypersensitivity reactions, with multiple organ involvement, have occurred with abacavir, a component of abacavir and lamivudine Tablets. Patients who carry the HLA-B*5701 allele are at a higher risk of a hypersensitivity reaction to abacavir; although, hypersensitivity reactions have occurred in patients who do not carry the HLA-B*5701 allele [see Warnings and Precautions ( 5.1 )] .
Abacavir and lamivudine tablets are contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 )] . All patients should be screened for the HLA-B*5701 allele prior to initiating therapy with abacavir and lamivudine tablets or reinitiation of therapy with abacavir and lamivudine tablets, unless patients have a previously documented HLA-B*5701 allele assessment. Discontinue Abacavir and lamivudine tablets immediately if a hypersensitivity reaction is suspected, regardless of HLA-B*5701 status and even when other diagnoses are possible [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 )] .
Following a hypersensitivity reaction to abacavir and lamivudine tablets, NEVER restart abacavir and lamivudine tablets or any other abacavir-containing product because more severe symptoms, including death, can occur within hours. Similar severe reactions have also occurred rarely following the reintroduction of abacavir-containing products in patients who have no history of abacavir hypersensitivity [see Warnings and Precautions ( 5.1 )] . Exacerbations of Hepatitis B Severe acute exacerbations of hepatitis B have been reported in patients who are co-infected with hepatitis B virus (HBV) and human immunodeficiency virus (HIV-1) and have discontinued lamivudine, which is a component of abacavir and lamivudine tablets.
Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue abacavir and lamivudine tablets and are co-infected with HIV-1 and HBV. If appropriate, initiation of anti-hepatitis B therapy may be warranted [see Warnings and Precautions ( 5.2 )] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Abacavir and lamivudine tablet, a combination of abacavir and lamivudine, both nucleoside analogue HIV-1 reverse transcriptase inhibitors, is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection. ( 1 ) Abacavir and lamivudine tablets, in combination with other antiretroviral agents, are indicated for the treatment of human immunodeficiency virus type 1 (HIV-1) infection.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Before initiating abacavir and lamivudine tablets, screen for the HLA-B*5701 allele because abacavir and lamivudine tablets contains abacavir. ( 2.1 ) Adults: One tablet orally once daily. ( 2.2 ) Pediatric patients weighing at least 25 kg: One tablet daily.
( 2.3 ) Because abacavir and lamivudine tablets is a fixed-dose tablet and cannot be dose adjusted, abacavir and lamivudine tablets is not recommended in patients with creatinine clearance less than 30 mL per minute or patients with hepatic impairment. ( 2.4 , 4 )
2.1Screening for HLA-B*5701 Allele Prior to Starting Abacavir and Lamivudine Tablets Screen for the HLA-B*5701 allele prior to initiating therapy with abacavir and lamivudine tablets [see Boxed Warning , Warnings and Precautions ( 5.1 )] .
2.2Recommended Dosage for Adult Patients The recommended dosage of abacavir and lamivudine tablets for adults is one tablet taken orally once daily, in combination with other antiretroviral agents, with or without food.
2.3Recommended Dosage for Pediatric Patients The recommended oral dose of abacavir and lamivudine tablets for pediatric patients weighing at least 25 kg is one tablet daily in combination with other antiretroviral agents [see Clinical Studies ( 14.2 )] . Before prescribing abacavir and lamivudine tablets, pediatric patients should be assessed for the ability to swallow tablets.
2.4Not Recommended Due to Lack of Dosage Adjustment Because abacavir and lamivudine tablet is a fixed-dose tablet and cannot be dose adjusted, abacavir and lamivudine tablets are not recommended for: patients with creatinine clearance less than 30 mL per minute [see Use in Specific Populations ( 8.6 )] . patients with mild hepatic impairment. Abacavir and lamivudine tablets is contraindicated in patients with moderate or severe hepatic impairment [see Contraindications ( 4 ), Use in Specific Populations ( 8.7 )] . Use of EPIVIR® (lamivudine) oral solution or tablets and ZIAGEN® (abacavir) oral solution may be considered.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 600 mg of abacavir and 300 mg of lamivudine. ( 3 ) Abacavir and lamivudine tablets USP contain 600 mg of abacavir as abacavir sulfate and 300 mg of lamivudine. The tablets are orange colored, oval shaped, biconvex, film-coated tablets debossed with "LU" on one side "C51" on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Presence of HLA-B*5701 allele. ( 4 ) Prior hypersensitivity reaction to abacavir or lamivudine. ( 4 ) Moderate or severe hepatic impairment.
( 4 , 8.7 ) Abacavir and lamivudine tablets are contraindicated in patients: who have the HLA-B*5701 allele [see Warnings and Precautions ( 5.1 )]. with prior hypersensitivity reaction to abacavir [see Warnings and Precautions ( 5.1 )] or lamivudine. with moderate or severe hepatic impairment [see Use in Specific Populations ( 8.7 )].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues. (5.3) Immune reconstitution syndrome has been reported in patients treated with combination antiretroviral therapy. ( 5.4 )
5.1Hypersensitivity Reactions Serious and sometimes fatal hypersensitivity reactions have occurred with abacavir, a component of abacavir and lamivudine tablets. These hypersensitivity reactions have included multi-organ failure and anaphylaxis and typically occurred within the first 6 weeks of treatment with abacavir (median time to onset was 9 days); although abacavir hypersensitivity reactions have occurred any time during treatment [see Adverse Reactions (6.1)] . Patients who carry the HLA-B*5701 allele are at a higher risk of abacavir hypersensitivity reactions; although, patients who do not carry the HLA-B*5701 allele have developed hypersensitivity reactions.
Hypersensitivity to abacavir was reported in approximately 206 (8%) of 2,670 patients in 9 clinical trials with abacavir-containing products where HLA-B*5701 screening was not performed. The incidence of suspected abacavir hypersensitivity reactions in clinical trials was 1% when subjects carrying the HLA-B*5701 allele were excluded. In any patient treated with abacavir, the clinical diagnosis of hypersensitivity reaction must remain the basis of clinical decision making.
Due to the potential for severe, serious, and possibly fatal hypersensitivity reactions with abacavir: All patients should be screened for the HLA-B*5701 allele prior to initiating therapy with abacavir and lamivudine tablets or reinitiation of therapy with abacavir and lamivudine tablets, unless patients have a previously documented HLA-B*5701 allele assessment. Abacavir and lamivudine tablets are contraindicated in patients with a prior hypersensitivity reaction to abacavir and in HLA-B*5701-positive patients. Before starting abacavir and lamivudine tablets, review medical history for prior exposure to any abacavir containing product.
NEVER restart abacavir and lamivudine tablets or any other abacavir-containing product following a hypersensitivity reaction to abacavir, regardless of HLA-B*5701 status. To reduce the risk of a life-threatening hypersensitivity reaction, regardless of HLA-B*5701 status, discontinue abacavir and lamivudine tablets immediately if a hypersensitivity reaction is suspected, even when other diagnoses are possible (e.g., acute onset respiratory diseases such as pneumonia, bronchitis, pharyngitis, or influenza; gastroenteritis; or reactions to other medications).
If a hypersensitivity reaction cannot be ruled out, do not restart abacavir and lamivudine tablets or any other abacavir-containing products because more severe symptoms, which may include life-threatening hypotension and death, can occur within hours. If a hypersensitivity reaction is ruled out, patients may restart abacavir and lamivudine tablets. Rarely, patients who have stopped abacavir for reasons other than symptoms of hypersensitivity have also experienced life-threatening reactions within hours of reinitiating abacavir therapy.
Therefore, reintroduction of abacavir and lamivudine tablets or any other abacavir-containing product is recommended only if medical care can be readily accessed. A Medication Guide and Warning Card that provide information about recognition of hypersensitivity reactions should be dispensed with each new prescription and refill.
5.2Patients with Hepatitis B Virus Co-infection Posttreatment Exacerbations of Hepatitis Clinical and laboratory evidence of exacerbations of hepatitis have occurred after discontinuation of lamivudine. See full prescribing information for EPIVIR (lamivudine). Patients should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment.
Emergence of Lamivudine-Resistant HBV Safety and efficacy of lamivudine have not…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most commonly reported adverse reactions of at least moderate intensity (incidence greater than 5%) in an adult HIV-1 clinical trial were drug hypersensitivity, insomnia, depression/depressed mood, headache/migraine, fatigue/malaise, dizziness/vertigo, nausea, and diarrhea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals, Inc. at 1-800-399-2561 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. The following adverse reactions are discussed in greater detail in other sections of the labeling: Serious and sometimes fatal hypersensitivity reactions [see Boxed Warning, Warnings and Precautions ( 5.1 )].
Exacerbations of hepatitis B [see Boxed Warning, Warnings and Precautions ( 5.2 )]. Lactic acidosis and severe hepatomegaly with steatosis [see Warnings and Precautions ( 5.3 )]. Immune reconstitution syndrome [see Warnings and Precautions ( 5.4 )].
Myocardial infarction [see Warnings and Precautions ( 5.5 )].
6.1Clinical Trials Experience in Adult Subjects Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Serious and Fatal Abacavir-Associated Hypersensitivity Reactions In clinical trials, serious and sometimes fatal hypersensitivity reactions have occurred with abacavir, a component of abacavir and lamivudine tablets [ see Boxed Warning, Warnings and Precautions ( 5.1 ) ].
These reactions have been characterized by 2 or more of the following signs or symptoms: (1) fever; (2) rash; (3) gastrointestinal symptoms (including nausea, vomiting, diarrhea, or abdominal pain); (4) constitutional symptoms (including generalized malaise, fatigue, or achiness); (5) respiratory symptoms (including dyspnea, cough, or pharyngitis). Almost all abacavir hypersensitivity reactions include fever and/or rash as part of the syndrome. Other signs and symptoms have included lethargy, headache, myalgia, edema, arthralgia, and paresthesia.
Anaphylaxis, liver failure, renal failure, hypotension, adult respiratory distress syndrome, respiratory failure, myolysis, and death have occurred in association with these hypersensitivity reactions. Physical findings have included lymphadenopathy, mucous membrane lesions (conjunctivitis and mouth ulcerations), and maculopapular or urticarial rash (although some patients had other types of rashes and others did not have a rash). There were reports of erythema multiforme.
Laboratory abnormalities included elevated liver chemistries, elevated creatine phosphokinase, elevated creatinine, and lymphopenia and abnormal chest x-ray findings (predominantly infiltrates, which were localized). Additional Adverse Reactions with Use of Abacavir and Lamivudine Tablets: Therapy-Naive Adults: Treatment-emergent clinical adverse reactions (rated by the investigator as moderate or severe) with greater than or equal to 5% frequency during therapy with ZIAGEN 600 mg once daily or ZIAGEN 300 mg twice daily, both in combination with lamivudine 300 mg once daily and efavirenz 600 mg once daily, are listed in Table 1.
Table 1. Treatment-Emergent (All Causality) Adverse Reactions of at Least Moderate Intensity (Grades 2 to 4, Greater than or Equal to 5% Frequency) in Therapy-Naive Adults (CNA30021) through 48 Weeks of Treatment a Subjects receiving ZIAGEN 600 mg once daily, experienced a significantly higher incidence of severe drug hypersensitivity reactions and severe diarrhea compared with subjects who received ZIAGEN 300 mg twice daily. Five percent (5%) of subjects receiving ZIAGEN 600 mg once daily had severe drug hypersensitivity reactions compared with 2% of subjects receiving ZIAGEN 300 mg twice daily.
Two percent (2%) of subjects receiving ZIAGEN 600 mg once daily had severe diarrhea while none of the subjects receiving ZIAGEN 300 mg twice daily had this even…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Methadone: An increased methadone dose may be required in a small number of patients. ( 7.1 ) Sorbitol: Coadministration of lamivudine and sorbitol may decrease lamivudine concentrations; when possible, avoid chronic coadministration. ( 7.2 ) Riociguat: The riociguat dose may need to be reduced. ( 7.3 )
7.1Methadone In a trial of 11 HIV-1-infected subjects receiving methadone-maintenance therapy with 600 mg of ZIAGEN twice daily (twice the currently recommended dose), oral methadone clearance increased [see Clinical Pharmacology ( 12.3 )] . This alteration will not result in a methadone dose modification in the majority of patients; however, an increased methadone dose may be required in a small number of patients.
7.2Sorbitol Coadministration of single doses of lamivudine and sorbitol resulted in a sorbitol dose-dependent reduction in lamivudine exposures. When possible, avoid use of sorbitol-containing medicines with lamivudine-containing medicines [see Clinical Pharmacology ( 12.3 )].
7.3Riociguat Coadministration with fixed-dose abacavir/dolutegravir/lamivudine resulted in increased riociguat exposure, which may increase the risk of riociguat adverse reactions [see Clinical Pharmacology (12.3)] . The riociguat dose may need to be reduced. See full prescribing information for ADEMPAS (riociguat).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Women infected with HIV should be instructed not to breastfeed due to potential for HIV transmession. ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to abacavir and lamivudine tablets during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the (APR) show no difference in the overall risk of birth defects for abacavir or lamivudine compared with the background rate for birth defects of 2.7% in the Metropolitan Atlanta Congenital Defects Program (MACDP) reference population (see Data) .
The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks gestation. The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. In animal reproduction studies, oral administration of abacavir to pregnant rats during organogenesis resulted in fetal malformations and other embryonic and fetal toxicities at exposures 35 times the human exposure (AUC) at the recommended clinical daily dose.
However, no adverse developmental effects were observed following oral administration of abacavir to pregnant rabbits during organogenesis, at exposures approximately 9 times the human exposure (AUC) at the recommended clinical dose. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at systemic exposure (AUC) similar to the recommended clinical dose; however, no adverse development effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (Cmax) 35 times the recommended clinical dose (see Data) .
Data Human Data: Abacavir Based on prospective reports to the APR of exposures to abacavir during pregnancy resulting in live births (including over 1,300 exposed in the first trimester and over 1,300 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for abacavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP. The prevalence of defects in live births was 3.2% (95% CI: 2.3% to 4.3%) following first trimester exposure to abacavir-containing regimens and 2.9% (95% CI: 2.1% to 4.0%) following second/third trimester exposure to abacavir-containing regimens.
Abacavir has been shown to cross the placenta and concentrations in neonatal plasma at birth were essentially equal to those in maternal plasma at delivery [see Clinical Pharmacology ( 12.3 )]. Lamivudine Based on prospective reports to the APR of exposures to lamivudine during pregnancy resulting in live births (including over 5,300 exposed in the first trimester and over 7,400 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for lamivudine compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 3.1% (95% CI: 2.7% to 3.6%) following first trimester exposure to lamivudine-containing regimens and 2.9% (95% CI: 2.5%, 3.3%) following second/third trimester exposure to lamivudine-containing regimens. Lamivudine pharmacokinetics were studied in pregnant women during 2 clinical trials conducted in South Africa. The trials assessed pharmacokinetics in 16 women at 36 weeks gestation using 150 mg lamivudine twice daily with zidovudine, 10 women at 38 weeks gestation using 150 mg lamivudine twice dail…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to abacavir and lamivudine tablets during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the (APR) show no difference in the overall risk of birth defects for abacavir or lamivudine compared with the background rate for birth defects of 2.7% in the Metropolitan Atlanta Congenital Defects Program (MACDP) reference population (see Data) .
The APR uses the MACDP as the U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occurred at less than 20 weeks gestation. The rate of miscarriage is not reported in the APR.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. The background risk for major birth defects and miscarriage for the indicated population is unknown. In animal reproduction studies, oral administration of abacavir to pregnant rats during organogenesis resulted in fetal malformations and other embryonic and fetal toxicities at exposures 35 times the human exposure (AUC) at the recommended clinical daily dose.
However, no adverse developmental effects were observed following oral administration of abacavir to pregnant rabbits during organogenesis, at exposures approximately 9 times the human exposure (AUC) at the recommended clinical dose. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at systemic exposure (AUC) similar to the recommended clinical dose; however, no adverse development effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (Cmax) 35 times the recommended clinical dose (see Data) .
Data Human Data: Abacavir Based on prospective reports to the APR of exposures to abacavir during pregnancy resulting in live births (including over 1,300 exposed in the first trimester and over 1,300 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for abacavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP. The prevalence of defects in live births was 3.2% (95% CI: 2.3% to 4.3%) following first trimester exposure to abacavir-containing regimens and 2.9% (95% CI: 2.1% to 4.0%) following second/third trimester exposure to abacavir-containing regimens.
Abacavir has been shown to cross the placenta and concentrations in neonatal plasma at birth were essentially equal to those in maternal plasma at delivery [see Clinical Pharmacology ( 12.3 )]. Lamivudine Based on prospective reports to the APR of exposures to lamivudine during pregnancy resulting in live births (including over 5,300 exposed in the first trimester and over 7,400 exposed in the second/third trimester), there was no difference between the overall risk of birth defects for lamivudine compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 3.1% (95% CI: 2.7% to 3.6%) following first trimester exposure to lamivudine-containing regimens and 2.9% (95% CI: 2.5%, 3.3%) following second/third trimester exposure to lamivudine-containing regimens. Lamivudine pharmacokinetics were studied in pregnant women during 2 clinical trials conducted in South Africa. The trials assessed pharmacokinetics in 16 women at 36 weeks gestation using 150 mg lamivudine twice daily with zidovudine, 10 women at 38 weeks gestation using 150 mg lamivudine twice daily with zidovudine, and 10 women at 38 weeks gestation using lamivudine 300 mg twice daily without other antiretrovirals.
These trials were not designed…
🧒 Pediatric Use ▾
8.4Pediatric Use The dosing recommendations in this population are based on the safety and efficacy established in a controlled trial conducted using either the combination of EPIVIR and ZIAGEN or abacavir and lamivudine tablets [see Dosage and Administration ( 2.3 ), Adverse Reactions ( 6.2 ), Clinical Studies ( 14.2 )] . In pediatric patients weighing less than 25 kg, use of abacavir and lamivudine as single products is recommended to achieve appropriate dosing.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of abacavir and lamivudine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, caution should be exercised in the administration of abacavir and lamivudine tablets in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Dosage and Administration ( 2.4 ), Use in Specific Populations ( 8.6 , 8.7 )].
🆘 Overdosage ▾
10 OVERDOSAGE There is no known specific treatment for overdose with abacavir and lamivudine tablets. If overdose occurs, the patient should be monitored, and standard supportive treatment applied as required. Abacavir It is not known whether abacavir can be removed by peritoneal dialysis or hemodialysis.
Lamivudine Because a negligible amount of lamivudine was removed via (4-hour) hemodialysis, continuous ambulatory peritoneal dialysis, and automated peritoneal dialysis, it is not known if continuous hemodialysis would provide clinical benefit in a lamivudine overdose event.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Abacavir and lamivudine tablet is an antiretroviral agent with activity against HIV-1 [see Microbiology ( 12.4 )].
12.3Pharmacokinetics Pharmacokinetics in Adults In a single-dose, 3-way crossover bioavailability trial of 1 abacavir and lamivudine tablet versus 2 ZIAGEN tablets (2 x 300 mg) and 2 EPIVIR tablets (2 x 150 mg) administered simultaneously in healthy subjects (n = 25), there was no difference in the extent of absorption, as measured by the area under the plasma concentration-time curve (AUC) and maximal peak concentration (C max ), of each component. Abacavir: Following oral administration, abacavir is rapidly absorbed and extensively distributed.
After oral administration of a single dose of 600 mg of abacavir in 20 subjects, C max was 4.26 ± 1.19 mcg per mL (mean ± SD) and AUC ∞ was 11.95 ± 2.51 mcg•hour per mL. Binding of abacavir to human plasma proteins is approximately 50% and was independent of concentration. Total blood and plasma drug-related radioactivity concentrations are identical, demonstrating that abacavir readily distributes into erythrocytes.
The primary routes of elimination of abacavir are metabolism by alcohol dehydrogenase to form the 5'-carboxylic acid and glucuronyl transferase to form the 5'-glucuronide. Lamivudine: Following oral administration, lamivudine is rapidly absorbed and extensively distributed. After multiple-dose oral administration of lamivudine 300 mg once daily for 7 days to 60 healthy subjects, steady-state C max (C max , ss ) was 2.04 ± 0.54 mcg per mL (mean ± SD) and the 24-hour steady-state AUC (AUC 24 , ss ) was 8.87 ± 1.83 mcg•hour per mL.
Binding to plasma protein is low. Approximately 70% of an intravenous dose of lamivudine is recovered as unchanged drug in the urine. Metabolism of lamivudine is a minor route of elimination.
In humans, the only known metabolite is the trans-sulfoxide metabolite (approximately 5% of an oral dose after 12 hours). In humans, abacavir and lamivudine are not significantly metabolized by cytochrome P450 (CYP) enzymes. The pharmacokinetic properties of abacavir and lamivudine in fasting subjects are summarized in Table 2.
Table 2: Pharmacokinetic Parameters Data presented as mean ± standard deviation except where noted. for Abacavir and Lamivudine in Adults Parameter Abacavir Lamivudine Oral bioavailability (%) 86 ± 25 n = 6 86 ± 16 n = 12 Apparent volume of distribution (L/kg) 0.86 ± 0.15 n = 6 1.3 ± 0.4 n = 20 Systemic clearance (L/h/kg) 0.80 ± 0.24 n = 6 0.33 ± 0.06 n = 20 Renal clearance (L/h/kg) 0.007 ± 0.008 n = 6 0.22 ± 0.06 n = 20 Elimination half-life (h) 1.45 ± 0.32 n = 20 13 to 19 Approximate range Effect of Food on Absorption of Abacavir and Lamivudine Tablets Abacavir and lamivudine tablets may be administered with or without food.
Administration with a high-fat meal in a single-dose bioavailability trial resulted in no change in AUC last , AUC ∞ , and C max for lamivudine. Food did not alter the extent of systemic exposure to abacavir (AUC ∞ ), but the rate of absorption (C max ) was decreased approximately 24% compared with fasted conditions (n = 25). These results are similar to those from previous trials of the effect of food on abacavir and lamivudine tablets administered separately.
Specific Populations Patients with Renal Impairment: The pharmacokinetics for the individual lamivudine component of abacavir and lamivudine tablets has been evaluated in patients with renal impairment (see the U.S. prescribing information for the individual lamivudine component). Patients with Hepatic Impairment: The pharmacokinetics for the individual components of abacavir and lamivudine tablets have been evaluated in patients with varying degrees of hepatic impairment (see the U.S. prescribing information for the individual abacavir and lamivudine components).
Pregnant Women: Abacavir: Abacavir pharmacokinetics were studied in 25 pregnant women during the last trimester of pregnancy receiv…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Abacavir and lamivudine tablet is an antiretroviral agent with activity against HIV-1 [see Microbiology ( 12.4 )].
Mechanism of Action Abacavir: Abacavir is a carbocyclic synthetic nucleoside analogue. Abacavir is converted by cellular enzymes to the active metabolite, carbovir triphosphate (CBV-TP), an analogue of deoxyguanosine-5'-triphosphate (dGTP). CBV-TP inhibits the activity of HIV-1 reverse transcriptase (RT) both by competing with the natural substrate dGTP and by its incorporation into viral DNA.
Lamivudine: Lamivudine is a synthetic nucleoside analogue. Intracellularly lamivudine is phosphorylated to its active 5'-triphosphate metabolite, lamivudine triphosphate (3TC-TP). The principal mode of action of 3TC-TP is inhibition of RT via DNA chain termination after incorporation of the nucleotide analogue.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Abacavir and lamivudine tablets USP are available as tablets. Each tablet contains 600 mg of abacavir as abacavir sulfate and 300 mg of lamivudine. The tablets are orange colored, oval shaped, biconvex, film-coated tablets debossed with "LU" on one side "C51" on the other side.
They are packaged as follows: Bottles (120cc) of 30 Tablets (NDC 68180-288-06). Bottles (250cc) of 90 Tablets (NDC 68180-288-09). Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Abacavir and Lamivudine Tablets USP Abacavir and lamivudine tablets USP contain the following 2 synthetic nucleoside analogues: abacavir (ZIAGEN, also a component of TRIZIVIR ® ) and lamivudine (also known as EPIVIR or 3TC) with inhibitory activity against HIV-1. Abacavir and lamivudine tablets USP are for oral administration. Each orange colored, oval shaped, biconvex, film-coated tablet contains the active ingredients 600 mg of abacavir as abacavir sulfate and 300 mg of lamivudine, and the inactive ingredients crospovidone, magnesium stearate, microcrystalline cellulose, and povidone.
The tablets are coated with a film that is made of FD&C Yellow No. 6, hypromellose, polyethylene glycol, polysorbate, and titanium dioxide. Abacavir Sulfate The chemical name of abacavir sulfate is (1S,4R)- 4-[2-Amino-6-(cyclopropylamino) -9H- purin-9-yl]-2-cyclopentene-1-methanol sulfate (2:1).
Abacavir sulfate is the enantiomer with 1S, 4R absolute configuration on the cyclopentene ring. It has a molecular formula of (C 14 H 18 N 6 O) 2 . H 2 SO 4 and a molecular weight of 670.74 g per mol.
It has the following structural formula: Abacavir sulfate is a white to off-white solid with a solubility of approximately 77 mg per mL in distilled water at 25°C. In vivo, abacavir sulfate dissociates to its free base, abacavir. Dosages are expressed in terms of abacavir.
Lamivudine The chemical name of lamivudine is (2R, cis)-4-amino-1-(2- hydroxymethyl-1,3-oxathiolan-5-yl)-(1H)-pyrimidin-2-one. Lamivudine is the (-) enantiomer of a dideoxy analogue of cytidine. Lamivudine has also been referred to as (-)2',3'-dideoxy, 3'thiacytidine.
It has a molecular formula of C 8 H 11 N 3 O 3 S and a molecular weight of 229.26 g per mol. It has the following structural formula: Lamivudine is a white to off-white solid with a solubility of approximately 68 mg per mL in water at 20°C. Image-02 image-03
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Hypersensitivity Reactions Inform patients: that a Medication Guide and Warning Card summarizing the symptoms of the abacavir hypersensitivity reaction and other product information will be dispensed by the pharmacist with each new prescription and refill of abacavir and lamivudine tablets, and instruct the patient to read the Medication Guide and Warning Card every time to obtain any new information that may be present about abacavir and lamivudine tablets.
The complete text of the Medication Guide is reprinted at the end of this document. to carry the Warning Card with them. how to identify a hypersensitivity reaction [see Warnings And Precautions ( 5.1 ), MEDICATION GUIDE]. that if they develop symptoms consistent with a hypersensitivity reaction they should call their healthcare provider right away to determine if they should stop taking abacavir and lamivudine tablets. that a hypersensitivity reaction can worsen and lead to hospitalization or death if abacavir and lamivudine tablets is not immediately discontinued. to not restart abacavir and lamivudine tablets or any other abacavir-containing product following a hypersensitivity reaction because more severe symptoms can occur within hours and may include life-threatening hypotension and death. that if they have a hypersensitivity reaction, they should dispose of any unused abacavir and lamivudine tablets to avoid restarting abacavir. that a hypersensitivity reaction is usually reversible if it is detected promptly and abacavir and lamivudine tablets is stopped right away. that if they have interrupted abacavir and lamivudine tablets for reasons other than symptoms of hypersensitivity (for example, those who have an interruption in drug supply), a serious or fatal hypersensitivity reaction may occur with reintroduction of abacavir. to not restart abacavir and lamivudine tablets or any other abacavir-containing product without medical consultation and only if medical care can be readily accessed by the patient or others.
Patients with Hepatitis B or C Co-infection Advise patients co-infected with HIV-1 and HBV that worsening of liver disease has occurred in some cases when treatment with lamivudine was discontinued. Advise patients to discuss any changes in regimen with their physician [see Warnings and Precautions ( 5.2 )]. Lactic Acidosis/Hepatomegaly with Steatosis Advise patients that lactic acidosis and severe hepatomegaly with steatosis have been reported with use of nucleoside analogues and other antiretrovirals.
Advise patients to stop taking abacavir and lamivudine tablets if they develop clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Warnings and Precautions ( 5.3 )]. Immune Reconstitution Syndrome Advise patients to inform their healthcare provider immediately of any signs and symptoms of infection as inflammation from previous infection may occur soon after combination antiretroviral therapy, including when abacavir and lamivudine tablet is started [see Warnings and Precautions ( 5.4 )] .
Redistribution/Accumulation of Body Fat Inform patients that redistribution or accumulation of body fat may occur in patients receiving antiretroviral therapy and that the cause and long-term health effects of these conditions are not known at this time [see Warnings and Precautions ( 5.6 )] . Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to abacavir and lamivudine tablets during pregnancy [see Use in Specific Populations ( 8.1 )]. Lactation Instruct women with HIV-1 infection not to breastfeed because HIV-1 can be passed to the baby in the breast milk [see Use in Specific Populations ( 8.2 )].
Missed Dose Instruct patients that if they miss a dose of abacavir and lamivudine tablets, to take it as soon as they remember. Advise patients not to doubl…
💬 Medication Guide ▾
MEDICATION GUIDE Abacavir and Lamivudine (a-BAK-a-vir and la-MIV-ue-deen) Tablets USP Rx Only What is the most important information I should know about Abacavir and Lamivudine Tablets? Abacavir and Lamivudine Tablets can cause serious side effects, including: Serious allergic reactions (hypersensitivity reaction) that can cause death have happened with abacavir and lamivudine tablets and other abacavir-containing products. Your risk of this allergic reaction is much higher if you have a gene variation called HLA-B*5701.
Your healthcare provider can determine with a blood test if you have this gene variation. If you get a symptom from 2 or more of the following groups while taking abacavir and lamivudine tablets, call your healthcare provider right away to find out if you should stop taking abacavir and lamivudine tablets . Symptom(s) Group 1 Fever Group 2 Rash Group 3 Nausea, vomiting, diarrhea, abdominal (stomach area) pain Group 4 Generally ill feeling, extreme tiredness, or achiness Group 5 Shortness of breath, cough, sore throat A list of these symptoms is on the Warning Card your pharmacist gives you.
Carry this Warning Card with you at all times. If you stop abacavir and lamivudine tablets because of an allergic reaction, never take abacavir and lamivudine tablets or any other abacavir-containing medicine (TRIUMEQ ® , TRIZIVIR ® or ZIAGEN) again. If you have an allergic reaction, dispose of any unused abacavir and lamivudine tablets.
Ask your pharmacist how to properly dispose of medicines. If you take abacavir and lamivudine tablets or any other abacavir-containing medicine again after you have had an allergic reaction, within hours you may get life-threatening symptoms that may include very low blood pressure or death . If you stop abacavir and lamivudine tablets for any other reason, even for a few days, and you are not allergic to abacavir and lamivudine tablets, talk with your healthcare provider before taking it again.
Taking abacavir and lamivudine tablets again can cause a serious allergic or life-threatening reaction, even if you never had an allergic reaction to it before. If your healthcare provider tells you that you can take abacavir and lamivudine tablets again, start taking it when you are around medical help or people who can call a healthcare provider if you need one. Worsening of hepatitis B virus (HBV) infection .
If you have HBV infection and take abacavir and lamivudine tablets, your HBV may get worse (flare-up) if you stop taking abacavir and lamivudine tablets. A "flare-up" is when your HBV infection suddenly returns in a worse way than before. Do not run out of abacavir and lamivudine tablets.
Refill your prescription or talk to your healthcare provider before your abacavir and lamivudine tablets is all gone. Do not stop abacavir and lamivudine tablets without first talking to your healthcare provider. If you stop taking abacavir and lamivudine tablets, your healthcare provider will need to check your health often and do blood tests regularly for several months to check your liver.
Resistant HBV . If you have human immunodeficiency virus-1 (HIV-1) and HBV, the HBV can change (mutate) during your treatment with abacavir and lamivudine tablets and become harder to treat (resistant). For more information about side effects, see "What are the possible side effects of abacavir and lamivudine tablets?" What is Abacavir and Lamivudine Tablet?
Abacavir and lamivudine tablet is a prescription medicine used with other HIV-1 medicines to treat HIV-1 infection. HIV-1 is the virus that causes Acquired Immune Deficiency Syndrome (AIDS). Abacavir and lamivudine tablet contains the prescription medicines, abacavir and lamivudine Abacavir and lamivudine tablets should not be used in children weighing less than 55 pounds (25 kg).
Do not take abacavir and lamivudine tablets if you: have a certain type of gene variation called the HLA-B*5701 allele. Your healthcare provider will test you for this before prescribing…