
Eszopiclone 3 mg Tablet, Film Coated, 100-count — NDC 68180-324-01 (Billing 68180-0324-01)
This is a package of 100 tablets of Eszopiclone 3 mg Tablet, Film Coated from Lupin Pharmaceuticals, Inc., marketed since Apr 2014 and currently FDA-listed; retail pharmacies pay about $0.1177 per tablet (NADAC). It is the main listing for this product, which comes in 4 package sizes.
Other active recalls for Eszopiclone (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 058482
- GCN: 23925
- GPI-14 (Medi-Span): 60204035000340
- HICL (First Databank): 026791
- AHFS class code: 28:24.44.00
- RxCUI (RxNorm): 485440
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Benzodiazepine related drugs class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats insomnia. In studies it helped people fall asleep faster and stay asleep. It is meant to be taken right at bedtime.
- Take it by mouth right before bed, when you can get a full 7 to 8 hours of sleep. Avoid taking it with or right after a heavy, high-fat meal, since that can slow it down. Follow yo...
- The most common are an unpleasant taste in your mouth, headache, sleepiness, dizziness, and dry mouth. Some people feel drowsy the next day, so be careful driving until you know ho...
- If you sleep-walk, sleep-drive, or do things like eat or make calls while not fully awake, stop it and call your doctor. Also get help right away for swelling of the tongue or thro...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Eszopiclone — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.118 | $11.77 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4456 | $44.56 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1735 | $17.35 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 21, 2024
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q3 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 68180-0324-01 You're viewing this Main listing | 100 TABLET, FILM COATED in 1 BOTTLE | $0.1177 / ea | $11.77 | 2014-04-15 | — | Active |
| 68180-0324-02 68180-324-02 | 500 TABLET, FILM COATED in 1 BOTTLE | — | — | 2014-04-15 | — | Active |
| 68180-0324-03 68180-324-03 | 1000 TABLET, FILM COATED in 1 BOTTLE | — | — | 2014-04-15 | — | Active |
| 68180-0324-13 68180-324-13 | 7 BLISTER PACK in 1 CARTON / 14 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2014-04-15 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 68180-0324-02?
What NDC number is used to bill for this package of Eszopiclone 3 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eszopiclone 3 mg 00093-5539-01 | Teva | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mg 00378-5272-01 | Mylan | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mg 31722-0857-01 | Camber | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mg 33342-0301-11 | Macleods | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mg 55111-0617-01 | Dr. | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mg 65862-0969-01 | Aurobindo | 100 tablets | $0.088 | — | Availability likely | save 25% |
| Eszopiclone 3 mg 68462-0384-01 | Glenmark | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mg 69452-0349-20 | Bionpharma | 100 tablets | $0.088 | AB | Availability likely | save 25% |
| Eszopiclone 3 mgthis 68180-0324-01 | Lupin | 100 tablets | $0.118 | — | FDA listed | — |
| Eszopiclone 3 mg 43063-0795-30 | PD-Rx | 30 tablets | — | — | FDA listed | — |
| Eszopiclone 3 mg 47335-0588-08 | Sun | 100 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 50090-3514-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 50090-7746-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 55700-0610-30 | Quality | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 60429-0634-01 | Golden | 100 tablets | — | AB | Discontinued | — |
| Eszopiclone 3 mg 63187-0843-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 68071-2403-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 68071-3376-03 | NuCarePharmaceuticals, | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 68788-7169-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 70518-3576-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 71205-0236-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 71205-0633-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 71335-0116-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 71335-2002-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 71610-0409-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 72789-0067-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 76420-0027-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 76420-0354-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 80425-0065-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 80425-0066-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 80425-0067-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Eszopiclone 3 mg 80425-0115-01 | Advanced | 30 tablets | — | — | FDA listed | — |
| Lunesta 3 mg 80725-0012-30 | Waylis | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Feb 21, 2024
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: COMPLEX SLEEP BEHAVIORS Complex sleep behaviors including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur following use of eszopiclone tablets. Some of these events may result in serious injuries, including death. Discontinue eszopiclone tablets immediately if a patient experiences a complex sleep behavior [see CONTRAINDICATIONS ( 4 ) and WARNINGS AND PRECAUTIONS ( 5.1 )].
WARNING: COMPLEX SLEEP BEHAVIORS See full prescribing information for complete boxed warning. Complex sleep behaviors including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur following use of eszopiclone tablets. Some of these events may result in serious injuries, including death.
Discontinue eszopiclone tablets immediately if a patient experiences a complex sleep behavior ( 4 , 5.1 ).
Eszopiclone tablet is a federally controlled substance (C-IV) because it can be abused or lead to dependence. Keep eszopiclone tablets in a safe place to prevent misuse and abuse. Selling or giving away eszopiclone tablets may harm others, and is against the law. Tell your doctor if you have ever abused or been dependent on alcohol, prescription medicines or street drugs.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Eszopiclone tablets are indicated for the treatment of insomnia. Eszopiclone tablet has been shown to decrease sleep latency and improve sleep maintenance ( 1 ) Eszopiclone tablet is indicated for the treatment of insomnia. In controlled outpatient and sleep laboratory studies, eszopiclone tablets administered at bedtime decreased sleep latency and improved sleep maintenance.
The clinical trials performed in support of efficacy were up to 6 months in duration. The final formal assessments of sleep latency and maintenance were performed at 4 weeks in the 6-week study (adults only), at the end of both 2-week studies (elderly only) and at the end of the 6-month study (adults only).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Use the lowest dose effective for the patient ( 2 ) Recommended initial dose is 1 mg, immediately before bedtime, with at least 7 to 8 hours remaining before the planned time of awakening. May increase dose if clinically indicated, to a maximum of 3 mg ( 2.1 ) Geriatric or debilitated patients: Dose should not exceed 2 mg ( 2.2 ) Patients with severe hepatic impairment, or taking potent CYP3A4 inhibitors: Dose should not exceed 2 mg ( 2.3 ) Do not take with or immediately after a meal ( 2.5 ) Use the lowest effective dose for the patient.
2.1Dosage in Adults The recommended starting dose is 1 mg. Dosing can be raised to 2 mg or 3 mg if clinically indicated. In some patients, the higher morning blood levels of eszopiclone following use of the 2 mg or 3 mg dose increase the risk of next day impairment of driving and other activities that require full alertness [see WARNINGS AND PRECAUTIONS (5.1) ].
The total dose of eszopiclone should not exceed 3 mg, once daily immediately before bedtime [see WARNINGS AND PRECAUTIONS (5.6) ].
2.2Geriatric or Debilitated Patients The total dose of eszopiclone tablets should not exceed 2 mg in elderly or debilitated patients.
2.3Patients with Severe Hepatic Impairment, or Taking Potent CYP3A4 Inhibitors In patients with severe hepatic impairment, or in patients coadministered eszopiclone with potent CYP3A4 inhibitors, the total dose of eszopiclone tablets should not exceed 2 mg [see WARNING AND PRECAUTIONS (5.7) ].
2.4Use with CNS Depressants Dosage adjustments may be necessary when eszopiclone tablets are combined with other central nervous system (CNS) depressant drugs because of the potentially additive effects [see WARNINGS AND PRECAUTIONS (5.1) ].
2.5Administration with Food Taking eszopiclone tablets with or immediately after a heavy, high-fat meal results in slower absorption and would be expected to reduce the effect of eszopiclone tablets on sleep latency [see CLINICAL PHARMACOLOGY (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 1 mg, 2 mg, and 3 mg ( 3 ) Eszopiclone tablets USP are available in 1 mg, 2 mg and 3 mg strengths for oral administration. Eszopiclone tablets USP, 1 mg are light blue coloured, round, biconvex, film-coated tablets, debossed with "LU" on one side and "Y21" on the other side. Eszopiclone tablets USP, 2 mg are white coloured, round, biconvex, film-coated tablets, debossed with "LU" on one side and "Y22" on the other side.
Eszopiclone tablets USP, 3 mg are dark blue coloured, round, biconvex, film-coated tablets, debossed with "LU" on one side and "Y23" on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Patients who have experienced complex sleep behaviors after taking eszopiclone tablets ( 4 ) Known hypersensitivity to eszopiclone ( 4 ) Eszopiclone is contraindicated in patients who have experienced complex sleep behaviors after taking eszopiclone [see WARNINGS AND PRECAUTIONS ( 5.1 )]. Eszopiclone is contraindicated in patients with known hypersensitivity to eszopiclone. Hypersensitivity reactions include anaphylaxis and angioedema [see WARNINGS AND PRECAUTIONS ( 5.3 )] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CNS Depressant Effects: Impaired alertness and motor coordination, including risk of morning impairment. Risk increases with dose and use with other CNS depressants and alcohol. Caution patients taking 3 mg dose against driving and against activities requiring complete mental alertness during the morning after use.
( 5.2 ) Evaluate for Comorbid Diagnoses: Reevaluate if insomnia persists after 7 to 10 days of use ( 5.3 ) Severe Anaphylactic/Anaphylactoid Reactions (angioedema and anaphylaxis have been reported): Do not rechallenge if such reactions occur ( 5.4 ) Abnormal Thinking and Behavioral Changes: Changes including decreased inhibition, bizarre behavior, agitation and depersonalization have been reported. Immediately evaluate any new onset of behavioral changes ( 5.5 ) Worsening of Depression or Suicidal Thinking may occur: Prescribe the least number of tablets feasible to avoid intentional overdose ( 5.5 , 5.8 ) Withdrawal Effects: Symptoms may occur with rapid dose reduction or discontinuation ( 5.6 , 9.3 ) Elderly Patients: Use lower dose due to impaired motor, cognitive performance and increased sensitivity ( 2.2 , 5.8 ) Patients with Hepatic Impairment, Impaired Respiratory Function, Impaired Drug Metabolism or Hemodynamic Responses: Use with caution ( 5.8 )
5.1Complex Sleep Behaviors Complex sleep behaviors including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur following the first or any subsequent use of eszopiclone. Patients can be seriously injured or injure others during complex sleep behaviors. Such injuries may result in fatal outcomes.
Other complex sleep behaviors (e.g., preparing and eating food, making phone calls, or having sex) have also been reported. Patients usually do not remember these events. Post-marketing reports have shown that complex sleep behaviors may occur with eszopiclone alone at recommended dosages, with or without the concomitant use of alcohol or other CNS depressants [see DRUG INTERACTIONS ( 7.1 )].
Discontinue eszopiclone immediately if a patient experiences a complex sleep behavior.
5.2CNS Depressant Effects and Next-Day Impairment Eszopiclone is a CNS depressant and can impair daytime function in some patients at the higher doses (2 mg or 3 mg), even when used as prescribed. Prescribers should monitor for excess depressant effects, but impairment can occur in the absence of symptoms (or even with subjective improvement), and impairment may not be reliably detected by ordinary clinical exam (i.e., less than formal psychomotor testing). While pharmacodynamic tolerance or adaptation to some adverse depressant effects of eszopiclone may develop, patients using 3 mg eszopiclone should be cautioned against driving or engaging in other hazardous activities or activities requiring complete mental alertness the day after use.
Additive effects occur with concomitant use of other CNS depressants (e.g., benzodiazepines, opioids, tricyclic antidepressants, alcohol), including daytime use. Downward dose adjustment of eszopiclone and concomitant CNS depressants should be considered [see DOSAGE AND ADMINISTRATION (2.4) ]. The use of eszopiclone with other sedative-hypnotics at bedtime or the middle of the night is not recommended.
The risk of next-day psychomotor impairment is increased if eszopiclone is taken with less than a full night of sleep remaining (7-to 8 hours); if higher than the recommended dose is taken; if coadministered with other CNS depressants; or coadministered with other drugs that increase the blood levels of eszopiclone [see DOSAGE AND ADMINISTRATION (2.3) and CLINICAL STUDIES (14.3) ]. Because eszopiclone can cause drowsiness and a decreased level of consciousness, patients, particularly the elderly, are at higher risk of falls.
5.3Need to Evaluate for Comorbid Diagnoses Because sleep disturbances may be the presenting manifestation of a physical and/or psychiatric disorder, symptomatic treatment… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most commonly observed adverse reactions (incidence ≥2%) were unpleasant taste, headache, somnolence, respiratory infection, dizziness, dry mouth, rash, anxiety, hallucinations, and viral infections ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals, Inc. at 1-800-299-2561 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. The following are described in more detail in the WARNINGS AND PRECAUTIONS section of the label: Complex Sleep Behaviors [see BOXED WARNING and WARNINGS AND PRECAUTIONS ( 5.1 )] CNS Depressant Effects and Next-Day Impairment [see WARNINGS AND PRECAUTIONS ( 5.2 )] Need to Evaluate for Comorbid Diagnoses [see WARNINGS AND PRECAUTIONS ( 5.3 )] Severe Anaphylactic and Anaphylactoid Reactions [see WARNINGS AND PRECAUTIONS ( 5.4 )] Abnormal Thinking and Behavioral Changes [see WARNINGS AND PRECAUTIONS ( 5.5 )] Withdrawal Effects [see WARNINGS AND PRECAUTIONS ( 5.6 )] Timing of Drug Administration [see WARNINGS AND PRECAUTIONS ( 5.7 )] Special Populations [see WARNINGS AND PRECAUTIONS ( 5.8 )] Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice.
The premarketing development program for eszopiclone included eszopiclone exposures in patients and/or normal subjects from two different groups of studies: approximately 400 normal subjects in clinical pharmacology/pharmacokinetic studies, and approximately 1550 patients in placebo-controlled clinical effectiveness studies, corresponding to approximately 263 patient-exposure years. The conditions and duration of treatment with eszopiclone varied greatly and included (in overlapping categories) open-label and double-blind phases of studies, inpatients and outpatients, and short-term and longer-term exposure.
Adverse reactions were assessed by collecting adverse events, results of physical examinations, vital signs, weights, laboratory analyses, and ECGs. The stated frequencies of adverse reactions represent the proportion of individuals who experienced, at least once, adverse reaction of the type listed. A reaction was considered treatment-emergent if it occurred for the first time or worsened while the patient was receiving therapy following baseline evaluation.
6.1Clinical Trials Experience Adverse Reactions Resulting in Discontinuation of Treatment In placebo-controlled, parallel-group clinical trials in the elderly, 3.8% of 208 patients who received placebo, 2.3% of 215 patients who received 2 mg eszopiclone, and 1.4% of 72 patients who received 1 mg eszopiclone discontinued treatment due to an adverse reaction. In the 6-week parallel-group study in adults, no patients in the 3 mg arm discontinued because of an adverse reaction. In the long-term 6-month study in adult insomnia patients, 7.2% of 195 patients who received placebo and 12.8% of 593 patients who received 3 mg eszopiclone discontinued due to an adverse reaction.
No reaction that resulted in discontinuation occurred at a rate of greater than 2%. Adverse Reactions Observed at an Incidence of ≥2% in Controlled Trials Table 1 shows the incidence of adverse reactions from a Phase 3 placebo-controlled study of eszopiclone at doses of 2 or 3 mg in nonelderly adults. Treatment duration in this trial was 44 days.
The table includes only reactions that occurred in 2% or more of patients treated with eszopiclone 2 mg or 3 mg in which the incidence in patients treated with eszopiclone was greater than the incidence in placebo-treated patients. Table 1: Incidence (%) of Adverse Reactions in a 6-Week Placebo-Controlled Study in Nonelderly Adults with Eszopiclone 1 1 Reactions for which the eszopiclone incidence was equal to or less than placebo are not listed on the table, but included the following: abnormal dreams, accidental injury, back pain, diarrhea, flu s… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CNS Depressants: Additive CNS-depressant effects with combination use. Use with ethanol causes additive psychomotor impairment ( 7.1 ) Rifampicin: Combination use may decrease exposure to and effects of eszopiclone ( 7.2 ) Ketoconazole: Combination use increases exposure to and effect of eszopiclone. Dose reduction of eszopiclone is needed ( 7.2 )
7.1CNS Active Drugs Ethanol An additive effect on psychomotor performance was seen with coadministration of eszopiclone and ethanol [see WARNINGS AND PRECAUTIONS ( 5.1 , 5.2 )]. Olanzapine Coadministration of eszopiclone and olanzapine produced a decrease in DSST scores. The interaction was pharmacodynamic; there was no alteration in the pharmacokinetics of either drug.
7.2Drugs that Inhibit or Induce CYP3A4 Drugs that Inhibit CYP3A4 (Ketoconazole) CYP3A4 is a major metabolic pathway for elimination of eszopiclone. The exposure of eszopiclone was increased by coadministration of ketoconazole, a potent inhibitor of CYP3A4. Other strong inhibitors of CYP3A4 (e.g., itraconazole, clarithromycin, nefazodone, troleandomycin, ritonavir, nelfinavir) would be expected to behave similarly.
Dose reduction of eszopiclone is needed for patient co-administered eszopiclone with potent CYP3A4 inhibitors [see DOSAGE AND ADMINISTRATION (2.3) ]. Drugs that Induce CYP3A4 (Rifampicin) Racemic zopiclone exposure was decreased 80% by concomitant use of rifampicin, a potent inducer of CYP3A4. A similar effect would be expected with eszopiclone.
Combination use with CYP3A4 inducer may decrease the exposure and effects of eszopiclone.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric Use: Safety and effectiveness not established. Dizziness, dysgeusia, hallucinations, suicidal ideation reported ( 8.4 )
8.1Pregnancy Risk Summary Available pharmacovigilance data with eszopiclone use in pregnant women are insufficient to identify a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies conducted in pregnant rats and rabbits throughout organogenesis, there was no evidence of teratogenicity. Administration of eszopiclone to rats throughout pregnancy and lactation resulted in offspring toxicities at all doses tested; the lowest dose was approximately 200 times the maximum recommended human dose (MRHD) of 3 mg/day based on mg/m2 body surface area (See Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data: Oral administration of eszopiclone to pregnant rats (62.5, 125, or 250 mg/kg/day) and rabbits (4, 8, or 16 mg/kg/day) throughout organogenesis showed no evidence of teratogenicity up to the highest doses tested. In rats, reduced fetal weight and increased incidences of skeletal variations and/or delayed ossification were observed at the mid and high doses. The no-observed-effect dose for adverse effects on embryofetal development is 200 times the MRHD of 3 mg/day on a mg/m 2 basis.
No effects on embryofetal development were observed in rabbits; the highest dose tested is approximately 100 times the MRHD on a mg/m 2 basis. Oral administration of eszopiclone (60, 120, or 180 mg/kg/day) to pregnant rats throughout the pregnancy and lactation resulted in increased post-implantation loss, decreased postnatal pup weights and survival, and increased pup startle response at all doses. The lowest dose tested is approximately 200 times the MRHD on a mg/m 2 basis.
Eszopiclone had no effects on other developmental measures or reproductive function in the offspring.
8.2Lactation Risk Summary There are no data on the presence of eszopiclone in either human or animal milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for eszopiclone and any potential adverse effects on the breastfed infant from eszopiclone or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness of eszopiclone have not been established in pediatric patients. Eszopiclone failed to demonstrate efficacy in controlled clinical studies of pediatric patients with Attention-Deficit/Hyperactivity (ADHD) associated insomnia. In a 12-week controlled study, 483 pediatric patients (aged 6 to 17 years) with insomnia associated with ADHD (with 65% of the patients using concomitant ADHD treatments) were treated with oral tablets of eszopiclone (1, 2 or 3 mg tablets, n=323), or placebo (n=160).
Eszopiclone did not significantly decrease latency to persistent sleep, compared to placebo, as measured by polysomnography after 12 weeks of treatment. Psychiatric and nervous system disorders comprised the most frequent treatment-emergent adverse reactions observed with eszopiclone versus placebo and included dysgeusia (9% vs. 1%), dizziness (6% vs.
2%), hallucinations (2% vs. 0%) and suicidal ideation (0.3% vs. 0%).
Nine patients on eszopiclone (3%) discontinued treatment due to an adverse reaction compared to 3 patients on placebo (2%). In studies in which eszopiclone (2 to 300 mg/kg/day) was orally administered to young rats from weaning through sexual maturity, neurobehavioral impairment (altered auditory startle response) and reproductive toxicity (adverse eff… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available pharmacovigilance data with eszopiclone use in pregnant women are insufficient to identify a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies conducted in pregnant rats and rabbits throughout organogenesis, there was no evidence of teratogenicity. Administration of eszopiclone to rats throughout pregnancy and lactation resulted in offspring toxicities at all doses tested; the lowest dose was approximately 200 times the maximum recommended human dose (MRHD) of 3 mg/day based on mg/m2 body surface area (See Data).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data: Oral administration of eszopiclone to pregnant rats (62.5, 125, or 250 mg/kg/day) and rabbits (4, 8, or 16 mg/kg/day) throughout organogenesis showed no evidence of teratogenicity up to the highest doses tested. In rats, reduced fetal weight and increased incidences of skeletal variations and/or delayed ossification were observed at the mid and high doses. The no-observed-effect dose for adverse effects on embryofetal development is 200 times the MRHD of 3 mg/day on a mg/m 2 basis.
No effects on embryofetal development were observed in rabbits; the highest dose tested is approximately 100 times the MRHD on a mg/m 2 basis. Oral administration of eszopiclone (60, 120, or 180 mg/kg/day) to pregnant rats throughout the pregnancy and lactation resulted in increased post-implantation loss, decreased postnatal pup weights and survival, and increased pup startle response at all doses. The lowest dose tested is approximately 200 times the MRHD on a mg/m 2 basis.
Eszopiclone had no effects on other developmental measures or reproductive function in the offspring.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of eszopiclone have not been established in pediatric patients. Eszopiclone failed to demonstrate efficacy in controlled clinical studies of pediatric patients with Attention-Deficit/Hyperactivity (ADHD) associated insomnia. In a 12-week controlled study, 483 pediatric patients (aged 6 to 17 years) with insomnia associated with ADHD (with 65% of the patients using concomitant ADHD treatments) were treated with oral tablets of eszopiclone (1, 2 or 3 mg tablets, n=323), or placebo (n=160).
Eszopiclone did not significantly decrease latency to persistent sleep, compared to placebo, as measured by polysomnography after 12 weeks of treatment. Psychiatric and nervous system disorders comprised the most frequent treatment-emergent adverse reactions observed with eszopiclone versus placebo and included dysgeusia (9% vs. 1%), dizziness (6% vs.
2%), hallucinations (2% vs. 0%) and suicidal ideation (0.3% vs. 0%).
Nine patients on eszopiclone (3%) discontinued treatment due to an adverse reaction compared to 3 patients on placebo (2%). In studies in which eszopiclone (2 to 300 mg/kg/day) was orally administered to young rats from weaning through sexual maturity, neurobehavioral impairment (altered auditory startle response) and reproductive toxicity (adverse effects on male reproductive organ weights and histopathology) were observed at doses ≥ 5 mg/kg/day. Delayed sexual maturation was noted in males and females at ≥10 mg/kg/day.
The no-effect dose (2 mg/kg) was associated with plasma exposures (AUC) for eszopiclone and metabolite (S)-desmethylzopiclone [(S)-DMZ] approximately 2 times plasma exposures in humans at the MRHD in adults (3 mg/day). When eszopiclone (doses from 1 to 50 mg/kg/day) was orally administered to young dogs from weaning through sexual maturity, neurotoxicity (convulsions) was observed at doses ≥ 5 mg/kg/day. Hepatotoxicity (elevated liver enzymes and hepatocellular vacuolation and degeneration) and reproductive toxicity (adverse effects on male reproductive organ weights and histopathology) were noted at doses ≥10 mg/kg/day.
The no-effect dose (1 mg/kg) was associated with plasma exposures (AUC) to eszopiclone and (S)-DMZ approximately 3 and 2 times, respectively, plasma exposures in humans at the MRHD in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use A total of 287 subjects in double-blind, parallel-group, placebo-controlled clinical trials who received eszopiclone were 65 to 86 years of age. The overall pattern of adverse events for elderly subjects (median age = 71 years) in 2-week studies with nighttime dosing of 2 mg eszopiclone was not different from that seen in younger adults [see ADVERSE REACTIONS (6) ] . Eszopiclone 2 mg exhibited significant reduction in sleep latency and improvement in sleep maintenance in the elderly population.
Compared with nonelderly adults, subjects 65 years and older had longer elimination and higher total exposure to eszopiclone. Therefore, dose reduction is recommended in elderly patients [see DOSAGE AND ADMINISTRATION (2.2) , CLINICAL PHARMACOLOGY (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE In clinical trials with eszopiclone, one case of overdose with up to 36 mg of eszopiclone was reported in which the subject fully recovered. Since commercial marketing began, spontaneous cases of eszopiclone overdoses up to 270 mg (90 times the maximum recommended dose of eszopiclone) have been reported, in which patients have recovered. Fatalities related to eszopiclone overdoses were reported only in combination with other CNS drugs or alcohol.
10.1Signs and Symptoms Signs and symptoms of overdose effects of CNS depressants can be expected to present as exaggerations of the pharmacological effects noted in preclinical testing. Impairment of consciousness ranging from somnolence to coma has been described. Rare individual instances of fatal outcomes following overdose with racemic zopiclone have been reported in European postmarketing reports, most often associated with overdose with other CNS-depressant agents.
Methemoglobinemia in association with overdoses of racemic zopiclone has been reported.
10.2Recommended Treatment General symptomatic and supportive measures should be used along with immediate gastric lavage where appropriate. Intravenous fluids should be administered as needed. Flumazenil may be useful.
As in all cases of drug overdose, respiration, pulse, blood pressure, and other appropriate signs should be monitored and general supportive measures employed. Hypotension and CNS depression should be monitored and treated by appropriate medical intervention. Consider monitoring methemoglobin in the setting of high-dose overdosage.
The value of dialysis in the treatment of overdosage has not been determined. As with the management of all overdosage, the possibility of multiple drug ingestion should be considered. The physician may wish to consider contacting a poison control center for up-to-date information on the management of hypnotic drug product overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of eszopiclone as a hypnotic is unclear; however, its effect could be related to its interaction with GABA-receptor complexes at binding domains located close to or allosterically coupled to benzodiazepine receptors.
12.3Pharmacokinetics The pharmacokinetics of eszopiclone have been investigated in healthy subjects (adult and elderly) and in patients with hepatic disease or renal disease. In healthy subjects, the pharmacokinetic profile was examined after single doses of up to 7.5 mg and after once-daily administration of 1, 3, and 6 mg for 7 days. Eszopiclone is rapidly absorbed, with a time to peak concentration (t max ) of approximately 1 hour and a terminal-phase elimination half-life (t 1/2 ) of approximately 6 hours.
In healthy adults, eszopiclone does not accumulate with once-daily administration, and its exposure is dose-proportional over the range of 1 to 6 mg. Absorption and Distribution Eszopiclone is rapidly absorbed following oral administration. Peak plasma concentrations are achieved within approximately 1 hour after oral administration.
Eszopiclone is weakly bound to plasma protein (52 to 59%). The large free fraction suggests that eszopiclone disposition should not be affected by drug-drug interactions caused by protein binding. The blood-to-plasma ratio for eszopiclone is less than one, indicating no selective uptake by red blood cells.
Metabolism Following oral administration, eszopiclone is extensively metabolized by oxidation and demethylation. The primary plasma metabolites are ( S )-zopiclone-N-oxide and ( S )-N-desmethyl zopiclone; the latter compound binds to GABA receptors with substantially lower potency than eszopiclone, and the former compound shows no significant binding to this receptor. In vitro studies have shown that CYP3A4 and CYP2E1 enzymes are involved in the metabolism of eszopiclone.
Eszopiclone did not show any inhibitory potential on CYP450 1A2, 2A6, 2C9, 2C19, 2D6, 2E1, and 3A4 in cryopreserved human hepatocytes. Elimination After oral administration, eszopiclone is eliminated with a mean t 1/2 of approximately 6 hours. Up to 75% of an oral dose of racemic zopiclone is excreted in the urine, primarily as metabolites.
A similar excretion profile would be expected for eszopiclone, the S-isomer of racemic zopiclone. Less than 10% of the orally administered eszopiclone dose is excreted in the urine as parent drug. Effect of Food In healthy adults, administration of a 3 mg dose of eszopiclone after a high-fat meal resulted in no change in AUC, a reduction in mean C max of 21%, and delayed t max by approximately 1 hour.
The half-life remained unchanged, approximately 6 hours. The effects of eszopiclone on sleep onset may be reduced if it is taken with or immediately after a high-fat/heavy meal. Specific Populations Age: Compared with nonelderly adults, subjects 65 years and older had an increase of 41% in total exposure (AUC) and a slightly prolonged elimination of eszopiclone (t 1/2 approximately 9 hours).
C max was unchanged. Therefore, in elderly patients the dose should not exceed 2 mg. Gender: The pharmacokinetics of eszopiclone in men and women are similar.
Race: In an analysis of data on all subjects participating in Phase 1 studies of eszopiclone, the pharmacokinetics for all races studied appeared similar. Hepatic Impairment: Pharmacokinetics of a 2 mg eszopiclone dose were assessed in 16 healthy volunteers and in 8 subjects with mild, moderate, and severe liver disease. Exposure was increased 2-fold in severely impaired patients compared with the healthy volunteers.
C max and t max were unchanged. No dose adjustment is necessary for patients with mild-to-moderate hepatic impairment. Dose reduction is recommended for patients with severe hepatic impairment.
Eszopiclone should be used with caution in patients with hepatic impairment [see DOSAGE AND ADMINISTRATION (2.3) ] . Renal Impairment : The pharmacokineti… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of eszopiclone as a hypnotic is unclear; however, its effect could be related to its interaction with GABA-receptor complexes at binding domains located close to or allosterically coupled to benzodiazepine receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Eszopiclone tablets USP, 1 mg are light blue coloured, round, biconvex, film-coated tablets, debossed with "LU" on one side and "Y21" on the other side. They are supplied as follows: NDC 68180-322-01 Bottles of 100's NDC 68180-322-13 7 x 14's unit dose blisters Eszopiclone tablets USP, 2 mg are white coloured, round, biconvex, film-coated tablets, debossed with "LU" on one side and "Y22" on the other side. They are supplied as follows: NDC 68180-323-01 Bottles of 100's NDC 68180-323-02 Bottles of 500's NDC 68180-323-13 7 x 14's unit dose blisters Eszopiclone tablets USP, 3 mg are dark blue coloured, round, biconvex, film-coated tablets, debossed with "LU" on one side and "Y23" on the other side.
They are supplied as follows: NDC 68180-324-01 Bottles of 100's NDC 68180-324-02 Bottles of 500's NDC 68180-324-03 Bottles of 1000's NDC 68180-324-13 7 x 14's unit dose blisters Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Eszopiclone is a nonbenzodiazepine hypnotic agent that is a pyrrolopyrazine derivative of the cyclopyrrolone class. The chemical name of eszopiclone is (+)-(5S)-6-(5-chloropyridin-2-yl)-7-oxo-6,7-dihydro-5H-pyrrolo[3,4-b] pyrazin-5-yl 4-methylpiperazine-1-carboxylate. Its molecular weight is 388.81, and its empirical formula is C 17 H 17 ClN 6 O 3 .
Eszopiclone has a single chiral center with an ( S )-configuration. It has the following chemical structure: Eszopiclone is a white to light-yellow crystalline solid. Eszopiclone is very slightly soluble in water, slightly soluble in ethanol, and soluble in phosphate buffer (pH 3.2).
Eszopiclone is formulated as film-coated tablets for oral administration. Eszopiclone tablets USP contain 1 mg, 2 mg, or 3 mg eszopiclone and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, dibasic calcium phosphate dihydrate, hypromellose, lactose monohydrate, polyethylene glycol, povidone, pregelatinized starch, magnesium stearate and titanium dioxide. In addition, both the 1 mg and 3 mg tablets contain FD&C Blue #2.
Image 1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling ( Medication Guide ). Inform patients and their families about the benefits and risks of treatment with eszopiclone tablets. Inform patients of the availability of a Medication Guide and instruct them to read the Medication Guide prior to initiating treatment with eszopiclone tablets and with each prescription refill.
Review the eszopiclone tablets Medication Guide with every patient prior to initiation of treatment. Instruct patients or caregivers that eszopiclone tablets should be taken only as prescribed. Complex Sleep Behaviors Instruct patients and their families that eszopiclone tablets may cause complex sleep behaviors, including sleep-walking, sleep-driving, preparing and eating food, making phone calls, or having sex while not being fully awake.
Serious injuries and death have occurred during complex sleep behavior episodes. Tell patients to discontinue eszopiclone tablets and notify their healthcare provider immediately if they develop any of these symptoms [see BOXED WARNING , WARNINGS AND PRECAUTIONS ( 5.1 )]. CNS Depressant Effects and Next-Day Impairment Tell patients that eszopiclone tablets can cause next-day impairment even when used as prescribed, and that this risk is increased if dosing instructions are not carefully followed.
Caution patients taking the 3 mg dose against driving and other activities requiring complete mental alertness the day after use. Inform patients that impairment can be present despite feeling fully awake. Advise patients that increased drowsiness and decreased consciousness may increase the risk of falls in some patients [see WARNINGS AND PRECAUTIONS ( 5.2 )].
Severe Anaphylactic and Anaphylactoid Reactions Inform patients that severe anaphylactic and anaphylactoid reactions have occurred with eszopiclone. Describe the signs/symptoms of these reactions and advise patients to seek medical attention immediately if any of them occur [WARNINGS AND PRECAUTIONS ( 5.2 )]. Suicide Tell patients to immediately report any suicidal thoughts.
Alcohol and Other Drugs Ask patients about alcohol consumption, medicines they are taking, and drugs they may be taking without a prescription. Advise patients not to use eszopiclone tablets if they drank alcohol that evening or before bed. Tolerance, Abuse, and Dependence Tell patients not to increase the dose of eszopiclone tablets on their own, and to inform you if they believe the drug "does not work." Administration Instructions Patients should be counseled to take eszopiclone tablets right before they get into bed and only when they are able to stay in bed a full night (7 to 8 hours) before being active again.
Eszopiclone tablets should not be taken with or immediately after a meal. Advise patients NOT to take eszopiclone tablets if they drank alcohol that evening. Manufactured for: Lupin Pharmaceuticals, Inc.
Baltimore, Maryland 21202 United States Manufactured by: Lupin Limited Goa 403 722 INDIA Revised: October 2019 ID#: 262263
💬 Medication Guide ▾
R x only Read the Medication Guide that comes with eszopiclone tablets before you start taking it and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking to your doctor about your medical condition or treatment.
What is the most important information I should know about eszopiclone tablets? Do not take more eszopiclone tablets than prescribed. Do not take eszopiclone tablets unless you are able to stay in bed a full night (7 to 8 hours) before you must be active again.
Take eszopiclone tablets right before you get in bed, not sooner. Eszopiclone tablets may cause serious side effects, including: Complex sleep behaviors that have caused serious injury and death. After taking eszopiclone tablets, you may get up out of bed while not being fully awake and do an activity that you do not know you are doing (complex sleep behaviors).
The next morning, you may not remember that you did anything during the night. These activities may occur with eszopiclone tablets whether or not you drink alcohol or take other medicines that make you sleepy. Reported activities and behaviors include: doing activities when you are asleep like: making and eating food talking on the phone having sex driving a car ("sleep-driving") sleep walking Stop taking eszopiclone tablets and call your healthcare provider right away if you find out that you have done any of the above activities after taking eszopiclone tablets.
The morning after you take eszopiclone tablets your ability to drive safely and think clearly may be decreased. Do not take eszopiclone tablets if you: have ever experienced a complex sleep behavior (such as driving a car, making and eating food, talking on the phone or having sex while not fully awake) after taking eszopiclone tablets drank alcohol that evening or before bed take other medicines that can make you sleepy. Talk to your doctor about all of your medicines.
Your doctor will tell you if you can take eszopiclone tablets with your other medicines. cannot get a full night's sleep WHAT IS ESZOPICLONE TABLET? Eszopiclone tablet is a sedative-hypnotic (sleep) medicine. Eszopiclone tablet is used in adults for the treatment of a sleep problem called insomnia.
Symptoms of insomnia include: trouble falling asleep waking up often during the night Eszopiclone tablets are not for children. Eszopiclone tablet is a federally controlled substance (C-IV) because it can be abused or lead to dependence. Keep eszopiclone tablets in a safe place to prevent misuse and abuse.
Selling or giving away eszopiclone tablets may harm others, and is against the law. Tell your doctor if you have ever abused or been dependent on alcohol, prescription medicines or street drugs. Who should not take eszopiclone tablets?
Do not take eszopiclone tablets if you have ever had a complex sleep behavior happen after taking eszopiclone tablets. Do not take eszopiclone tablets if you are allergic to anything in it. See the end of this Medication Guide for a complete list of ingredients in eszopiclone tablets.
Eszopiclone tablets may not be right for you. Before starting eszopiclone tablets, tell your doctor about all of your health conditions, including if you: have a history of depression, mental illness, or suicidal thoughts have a history of drug or alcohol abuse or addiction have liver disease are pregnant, planning to become pregnant, or breastfeeding Tell your doctor about all of the medicines you take including prescription and nonprescription medicines, vitamins and herbal supplements. Medicines can interact with each other, sometimes causing serious side effects.
Do not take eszopiclone tablets with other medicines that can make you sleepy. Know the medicines you take. Keep a list of your medicines with you to show your doctor and pharmacist each time you get a new medicine.
How should I take eszopiclone tablets? Take eszopiclone tablets exactly as prescribed. Do not take more eszopiclone tablets than pre… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary There are no data on the presence of eszopiclone in either human or animal milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for eszopiclone and any potential adverse effects on the breastfed infant from eszopiclone or from the underlying maternal condition.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of eszopiclone have been investigated in healthy subjects (adult and elderly) and in patients with hepatic disease or renal disease. In healthy subjects, the pharmacokinetic profile was examined after single doses of up to 7.5 mg and after once-daily administration of 1, 3, and 6 mg for 7 days. Eszopiclone is rapidly absorbed, with a time to peak concentration (t max ) of approximately 1 hour and a terminal-phase elimination half-life (t 1/2 ) of approximately 6 hours.
In healthy adults, eszopiclone does not accumulate with once-daily administration, and its exposure is dose-proportional over the range of 1 to 6 mg. Absorption and Distribution Eszopiclone is rapidly absorbed following oral administration. Peak plasma concentrations are achieved within approximately 1 hour after oral administration.
Eszopiclone is weakly bound to plasma protein (52 to 59%). The large free fraction suggests that eszopiclone disposition should not be affected by drug-drug interactions caused by protein binding. The blood-to-plasma ratio for eszopiclone is less than one, indicating no selective uptake by red blood cells.
Metabolism Following oral administration, eszopiclone is extensively metabolized by oxidation and demethylation. The primary plasma metabolites are ( S )-zopiclone-N-oxide and ( S )-N-desmethyl zopiclone; the latter compound binds to GABA receptors with substantially lower potency than eszopiclone, and the former compound shows no significant binding to this receptor. In vitro studies have shown that CYP3A4 and CYP2E1 enzymes are involved in the metabolism of eszopiclone.
Eszopiclone did not show any inhibitory potential on CYP450 1A2, 2A6, 2C9, 2C19, 2D6, 2E1, and 3A4 in cryopreserved human hepatocytes. Elimination After oral administration, eszopiclone is eliminated with a mean t 1/2 of approximately 6 hours. Up to 75% of an oral dose of racemic zopiclone is excreted in the urine, primarily as metabolites.
A similar excretion profile would be expected for eszopiclone, the S-isomer of racemic zopiclone. Less than 10% of the orally administered eszopiclone dose is excreted in the urine as parent drug. Effect of Food In healthy adults, administration of a 3 mg dose of eszopiclone after a high-fat meal resulted in no change in AUC, a reduction in mean C max of 21%, and delayed t max by approximately 1 hour.
The half-life remained unchanged, approximately 6 hours. The effects of eszopiclone on sleep onset may be reduced if it is taken with or immediately after a high-fat/heavy meal. Specific Populations Age: Compared with nonelderly adults, subjects 65 years and older had an increase of 41% in total exposure (AUC) and a slightly prolonged elimination of eszopiclone (t 1/2 approximately 9 hours).
C max was unchanged. Therefore, in elderly patients the dose should not exceed 2 mg. Gender: The pharmacokinetics of eszopiclone in men and women are similar.
Race: In an analysis of data on all subjects participating in Phase 1 studies of eszopiclone, the pharmacokinetics for all races studied appeared similar. Hepatic Impairment: Pharmacokinetics of a 2 mg eszopiclone dose were assessed in 16 healthy volunteers and in 8 subjects with mild, moderate, and severe liver disease. Exposure was increased 2-fold in severely impaired patients compared with the healthy volunteers.
C max and t max were unchanged. No dose adjustment is necessary for patients with mild-to-moderate hepatic impairment. Dose reduction is recommended for patients with severe hepatic impairment.
Eszopiclone should be used with caution in patients with hepatic impairment [see DOSAGE AND ADMINISTRATION (2.3) ] . Renal Impairment : The pharmacokinetics of eszopiclone were studied in 24 patients with mild, moderate, or severe renal impairment. AUC and C max were similar in the patients compared with demographically matched healthy control subjects.
No dose adjustment is necessary in patients with renal impairment, since less than 10% of… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The effect of eszopiclone on reducing sleep latency and improving sleep maintenance was established in studies with 2100 subjects (ages 18 to 86) with chronic and transient insomnia in six placebo-controlled trials of up to 6 months' duration. Two of these trials were in elderly patients (n=523). Overall, at the recommended adult dose (2 to 3 mg) and elderly dose (1 to 2 mg), eszopiclone significantly decreased sleep latency and improved measures of sleep maintenance (objectively measured as WASO and subjectively measured as total sleep time).
14.1Transient Insomnia Healthy adults were evaluated in a model of transient insomnia (n=436) in a sleep laboratory in a double-blind, parallel-group, single-night trial comparing two doses of eszopiclone and placebo. Eszopiclone 3 mg was superior to placebo on measures of sleep latency and sleep maintenance, including polysomnographic (PSG) parameters of latency to persistent sleep (LPS) and WASO.
14.2Chronic Insomnia (Adults and Elderly) The effectiveness of eszopiclone was established in five controlled studies in chronic insomnia. Three controlled studies were in adult subjects, and two controlled studies were in elderly subjects with chronic insomnia. Adults In the first study, adults with chronic insomnia (n=308) were evaluated in a double-blind, parallel-group trial of 6 weeks' duration comparing eszopiclone 2 mg and 3 mg with placebo.
Objective endpoints were measured for 4 weeks. Both 2 mg and 3 mg were superior to placebo on LPS at 4 weeks. The 3 mg dose was superior to placebo on WASO.
In the second study, adults with chronic insomnia (n=788) were evaluated using subjective measures in a double-blind, parallel-group trial comparing the safety and efficacy of eszopiclone 3 mg with placebo administered nightly for 6 months. Eszopiclone was superior to placebo on subjective measures of sleep latency, total sleep time, and WASO. In addition, a 6-period crossover PSG study evaluating eszopiclone doses of 1 to 3 mg, each given over a 2-day period, demonstrated effectiveness of all doses on LPS, and of 3 mg on WASO.
In this trial, the response was dose related. Elderly Elderly subjects (ages 65 to 86 years) with chronic insomnia were evaluated in two double-blind, parallel-group trials of 2 weeks duration. One study (n=231) compared the effects of eszopiclone with placebo on subjective outcome measures, and the other (n=292) on objective and subjective outcome measures.
The first study compared 1 mg and 2 mg of eszopiclone with placebo, while the second study compared 2 mg of eszopiclone with placebo. All doses were superior to placebo on measures of sleep latency. In both studies, 2 mg of eszopiclone was superior to placebo on measures of sleep maintenance.
14.3Studies Pertinent to Safety Concerns for Sedative Hypnotic Drugs Next Day Residual Effects In a double-blind study of 91 healthy adults age 25-to 40 years, the effects of eszopiclone 3 mg on psychomotor function were assessed between 7.5 and 11.5 hours the morning after dosing. Measures included tests of psychomotor coordination that are correlated with ability to maintain a motor vehicle in the driving lane, tests of working memory, and subjective perception of sedation and coordination. Compared with placebo, eszopiclone 3 mg was associated with next-morning psychomotor and memory impairment that was most severe at 7.5 hours, but still present and potentially clinically meaningful at 11.5 hours.
Subjective perception of sedation and coordination from eszopiclone 3 mg was not consistently different from placebo, even though subjects were objectively impaired. In a 6-month double-blind, placebo-controlled trial of nightly administered eszopiclone 3 mg, memory impairment was reported by 1.3% (8/593) of subjects treated with eszopiclone 3 mg compared to 0% (0/195) of subjects treated with placebo. In a 6-week adult study of nightly administered eszopiclone confusion was reported by 3.0% of patients treate… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Eszopiclone is a Schedule IV controlled substance under the Controlled Substances Act. Other substances under the same classification are benzodiazepines and the nonbenzodiazepine hypnotics zaleplon and zolpidem. While eszopiclone is a hypnotic agent with a chemical structure unrelated to benzodiazepines, it shares some of the pharmacologic properties of the benzodiazepines.
9.2Abuse Abuse and addiction are separate and distinct from physical dependence and tolerance. Abuse is characterized by misuse of the drug for non-medical purposes, often in combination with other psychoactive substances. Physical dependence is a state of adaptation that is manifested by a specific withdrawal syndrome that can be produced by abrupt cessation, rapid dose reduction, decreasing blood level of the drug and/or administration of an antagonist.
Tolerance is a state of adaptation in which exposure to a drug induces changes that result in a diminution of one or more of the drug's effects over time. Tolerance may occur to both the desired and undesired effects of drugs and may develop at different rates for different effects. Addiction is a primary, chronic, neurobiological disease with genetic, psychosocial, and environmental factors influencing its development and manifestations.
It is characterized by behaviors that include one or more of the following: impaired control over drug use, compulsive use, continued use despite harm, and craving. Drug addiction is a treatable disease, utilizing a multidisciplinary approach, but relapse is common. In a study of abuse liability conducted in individuals with known histories of benzodiazepine abuse, eszopiclone at doses of 6 and 12 mg produced euphoric effects similar to those of diazepam 20 mg.
In this study, at doses 2-fold or greater than the maximum recommended doses, a dose-related increase in reports of amnesia and hallucinations was observed for both eszopiclone and diazepam.
9.3Dependence The clinical trial experience with eszopiclone revealed no evidence of a serious withdrawal syndrome. Nevertheless, the following adverse events included in DSM-IV criteria for uncomplicated sedative/hypnotic withdrawal were reported during clinical trials following placebo substitution occurring within 48 hours following the last eszopiclone treatment: anxiety, abnormal dreams, nausea, and upset stomach. These reported adverse events occurred at an incidence of 2% or less.
Use of benzodiazepines and similar agents may lead to physical and psychological dependence. The risk of abuse and dependence increases with the dose and duration of treatment and concomitant use of other psychoactive drugs. The risk is also greater for patients who have a history of alcohol or drug abuse or history of psychiatric disorders.
These patients should be under careful surveillance when receiving eszopiclone or any other hypnotic.
9.4Tolerance Some loss of efficacy to the hypnotic effect of benzodiazepines and benzodiazepine-like agents may develop after repeated use of these drugs for a few weeks. No development of tolerance to any parameter of sleep measurement was observed over six months. Tolerance to the efficacy of eszopiclone 3 mg was assessed by 4-week objective and 6-week subjective measurements of time to sleep onset and sleep maintenance for eszopiclone in a placebo-controlled 44-day study, and by subjective assessments of time to sleep onset and wake time after sleep onset (WASO) in a placebo-controlled study for 6 months.
🔒 Controlled Substance ▾
9.1Controlled Substance Eszopiclone is a Schedule IV controlled substance under the Controlled Substances Act. Other substances under the same classification are benzodiazepines and the nonbenzodiazepine hypnotics zaleplon and zolpidem. While eszopiclone is a hypnotic agent with a chemical structure unrelated to benzodiazepines, it shares some of the pharmacologic properties of the benzodiazepines.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a carcinogenicity study in rats, oral administration of eszopiclone for 97 (males) or 104 (females) weeks resulted in no increases in tumors; plasma levels (AUC) of eszopiclone at the highest dose tested (16 mg/kg/day) are approximately 80 (females) and 20 (males) times those in humans at the MRHD of 3 mg/day. However, in a 2-year carcinogenicity study in rats, oral administration of racemic zopiclone (1, 10, or 100 mg/kg/day) resulted in increases in mammary gland adenocarcinomas (females) and thyroid gland follicular cell adenomas and carcinomas (males) at the highest dose tested.
Plasma levels of eszopiclone at this dose are approximately 150 (females) and 70 (males) times those in humans at the MRHD of eszopiclone. The mechanism for the increase in mammary adenocarcinomas is unknown. The increase in thyroid tumors is thought to be due to increased levels of TSH secondary to increased metabolism of circulating thyroid hormones, a mechanism not considered relevant to humans.
In a 2-year carcinogenicity study in mice, oral administration of racemic zopiclone (1, 10, or 100 mg/kg/day) produced increases in pulmonary carcinomas and carcinomas plus adenomas (females) and skin fibromas and sarcomas (males) at the highest dose tested. The skin tumors were due to skin lesions induced by aggressive behavior, a mechanism not relevant to humans. A carcinogenicity study of eszopiclone was conducted in mice at oral doses up to 100 mg/kg/day.
Although this study did not reach a maximum tolerated dose, and was thus inadequate for overall assessment of carcinogenic potential, no increases in either pulmonary or skin tumors were seen at doses producing plasma levels of eszopiclone approximately 90 times those in humans at the MRHD of eszopiclone (and 12 times the exposure in the racemate study). Eszopiclone did not increase tumors in a p53 transgenic mouse bioassay at oral doses up to 300 mg/kg/day. Mutagenesis Eszopiclone was clastogenic in in vitro (mouse lymphoma and chromosomal aberration) assays in mammalian cells.
Eszopiclone was negative in the in vitro bacterial gene mutation (Ames) assay and in an in vivo micronucleus assay. ( S )-N-desmethyl zopiclone, a metabolite of eszopiclone, was positive in in vitro chromosomal aberration assays in mammalian cells. ( S )-N-desmethyl zopiclone was negative in the in vitro bacterial gene mutation (Ames) assay and in an in vivo chromosomal aberration and micronucleus assay.
Impairment of Fertility Oral administration of eszopiclone to rats prior to and during mating, and continuing in females to day 7 of gestation (doses up to 45 mg/kg/day to males and females or up to 180 mg/kg/day to females only) resulted in decreased fertility, with no pregnancy at the highest dose tested when both males and females were treated. In females, there was an increase in abnormal estrus cycles at the highest dose tested. In males, decreases in sperm number and motility and increases in morphologically abnormal sperm were observed at the mid and high doses.
The no-effect dose for adverse effects on fertility (5 mg/kg/day) is 16 times the MRHD on a mg/m 2 basis.
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Boxed Warning 08/2019 Contraindications ( 4 ) 08/2019 Warnings and Precautions, Complex Sleep Behaviors ( 5.1 ) 08/2019 Warnings and Precautions, CNS Depressant Effects and Next-Day Impairment ( 5.2 ) 12/2018
📄 Package Label / Principal Display Panel ▾
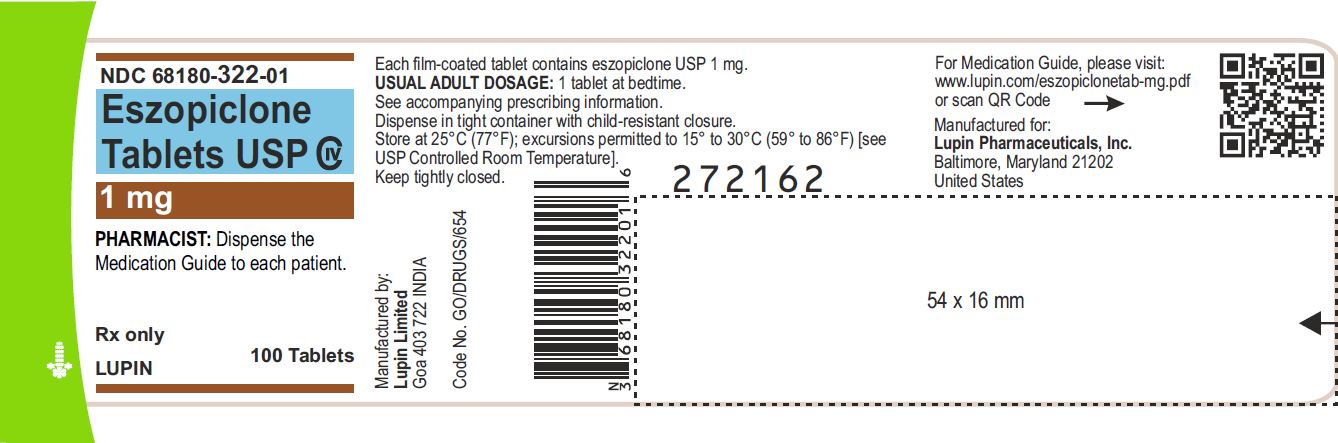
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Eszopiclone Tablets USP, 1 mg Rx Only NDC 68180-322-01 Bottle of 100 Tablets Eszopiclone Tablets USP, 2 mg Rx Only NDC 68180-323-01 Bottle of 100 Tablets Eszopiclone Tablets USP, 3 mg Rx Only NDC 68180-324-01 Bottle of 100 Tablets image 3 image 6 Figure 7