
Amlodipine and Valsartan 10 mg; 160 mg Tablet, 90-count — NDC 68180-765-09 (Billing 68180-0765-09)
This is a package of 90 tablets of Amlodipine and Valsartan 10 mg; 160 mg Tablet from Lupin Pharmaceuticals, Inc., marketed since Mar 2015 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 68180-765-09 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 68180 labeler · 765 product · 09 package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0368180765110, 0368180766117, 0368180767114, 0368180764113
- FDA record last changed
- Sep 10, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GPI-14 (Medi-Span): 36993002100330
- RxCUI (RxNorm): 722126
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Amlodipine is used to treat high blood pressure and certain types of angina (chest pain) and coronary artery disease (narrowing of the blood vessels that supply blood to the heart). Amlodipine is in a class of medications called calcium channel blockers. It lowers blood pressure by relaxing the blood vessels so the heart does not have to pump as hard. It controls chest pain by increasing the supply of blood to the heart. If taken regularly, amlodipine controls chest pain, but it does not stop chest pain once it starts. Your doctor may prescribe a different medication to take when you have ches...
Read the full MedlinePlus article ↗- It treats high blood pressure. Lowering your blood pressure reduces the risk of strokes and heart attacks. It combines two medicines that work in different ways, so it can help whe...
- Take one tablet by mouth once a day, with or without food. Most of the effect shows up within about 2 weeks. Follow your prescriber's directions and don't change the dose yourself.
- The most common are swelling in the feet or ankles, a stuffy nose or sore throat, cold-like symptoms and dizziness. These are usually mild. Call your doctor if they bother you or d...
- Get help for swelling of the face, lips or tongue, fainting, worsening chest pain or yellowing of your skin or eyes. Also call right away if you become pregnant.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 6, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 68180-0765-02 68180-765-02 | 500 TABLET in 1 BOTTLE | — | — | 2015-03-31 | — | Active |
| 68180-0765-06 68180-765-06 Main listing | 30 TABLET in 1 BOTTLE | $0.5916 / ea | $17.75 | 2015-03-31 | — | Discontinued by firm |
| 68180-0765-09 You're viewing this | 90 TABLET in 1 BOTTLE | — | — | 2015-03-31 | — | Active |
| 68180-0765-11 68180-765-11 | 10 TABLET in 1 BLISTER PACK | — | — | 2015-03-31 | — | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 68180-0765-11?
What NDC number is used to bill for this package of Amlodipine and Valsartan 10 mg; 160 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Amlodipine And Valsartan 10 mg/1; 160 mg 00378-1722-93 | Mylan | 30 tablets | $0.330 | AB | Availability likely | — |
| Amlodipine and Valsartan 10 mg/1; 160 mg 23155-0845-03 | Heritage | 30 tablets | $0.330 | AB | Availability likely | — |
| amlodipine and valsartan 10 mg/1; 160 mg 33342-0280-07 | Macleods | 30 tablets | $0.330 | AB | Availability likely | — |
| Exforge 10 mg/1; 160 mg 00078-0489-15 | Novartis | 30 tablets | $12.127 | AB | FDA listed | — |
| Amlodipine And Valsartan 10 mg/1; 160 mg 43386-0082-03 | Lupin | 30 tablets | — | AB | FDA listed | — |
| Amlodipine and Valsartan 10 mg/1; 160 mg 46708-0459-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Amlodipine and Valsartan 10 mg/1; 160 mg 51407-0773-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Amlodipine and Valsartan 10 mg/1; 160 mg 62332-0206-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Amlodipine and Valsartan 10 mg/1; 160 mg 64380-0215-01 | Strides | 30 tablets | — | AB | Discontinued | — |
| Amlodipine and valsartan 10 mg/1; 160 mg 65862-0739-03 | Aurobindo | 10 tablets | — | AB | FDA listed | — |
| Amlodipine and Valsartan 10 mg/1; 160 mgthis 68180-0765-09 | Lupin | 90 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Amlodipine / Valsartan inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Lupin Pharmaceuticals, Inc. labeler code 68180
- Amlodipine Besylate and Benazepril Hydrochloride 5 mg; 10 mg Capsule NDC 68180-756-01
- Amlodipine Besylate and Benazepril Hydrochloride 5 mg; 20 mg Capsule NDC 68180-757-01
- Amlodipine Besylate and Benazepril Hydrochloride 10 mg; 20 mg Capsule NDC 68180-758-01
- Amlodipine Besylate and Benazepril Hydrochloride 5 mg; 40 mg Capsule NDC 68180-759-01
- Amlodipine Besylate and Benazepril Hydrochloride 10 mg; 40 mg Capsule NDC 68180-760-01
- Amlodipine and Valsartan 5 mg; 160 mg Tablet NDC 68180-764-02
- Amlodipine and Valsartan 5 mg; 320 mg Tablet NDC 68180-766-02
- Amlodipine and Valsartan 10 mg; 320 mg Tablet NDC 68180-767-02
- Amlodipine, Valsartan and Hydrochlorothiazide 5 mg; 160 mg; 12.5 mg Tablet, Film Coated NDC 68180-771-02
- Amlodipine, Valsartan and Hydrochlorothiazide 10 mg; 160 mg; 12.5 mg Tablet, Film Coated NDC 68180-772-02
- Amlodipine, Valsartan and Hydrochlorothiazide 5 mg; 160 mg; 25 mg Tablet, Film Coated NDC 68180-773-02
- Amlodipine, Valsartan and Hydrochlorothiazide 10 mg; 160 mg; 25 mg Tablet, Film Coated NDC 68180-774-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue a mlodipine and valsartan tablets as soon as possible. ( 5.1 ) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 ) WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue amlodipine and valsartan tablets as soon as possible. ( 5.1 ) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 )
What is the most important information I should know about amlodipine and valsartan tablets? Amlodipine and valsartan tablets can cause harm or death to an unborn baby. Talk to your doctor about other ways to lower your blood pressure if you plan to become pregnant. If you get pregnant while taking amlodipine and valsartan tablets, tell your doctor right away.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Amlodipine and valsartan tablet is the combination tablet of amlodipine, a dihydropyridine calcium channel blocker (DHP CCB), and valsartan, an angiotensin II receptor blocker (ARB). Amlodipine and valsartan tablets are indicated for the treatment of hypertension, to lower blood pressure: In patients not adequately controlled on monotherapy ( 1 ) As initial therapy in patients likely to need multiple drugs to achieve their blood pressure goals ( 1 ). Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions.
1.1Hypertension Amlodipine and valsartan tablets are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes, including amlodipine and the angiotensin II receptor blocker (ARB) class to which valsartan principally belongs.
There are no controlled trials demonstrating risk reduction with amlodipine and valsartan tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals.
For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Amlodipine and valsartan tablets are indicated for the treatment of hypertension.
Amlodipine and valsartan tablets may be used in patients whose blood pressure is not adequately controlled on either monotherapy. Amlodipine and valsartan tablets may also be used as initial therapy in patients who are likely to need multiple drugs to achieve their blood pressure goals. The choice of amlodipine and valsartan tablets as initial therapy for hypertension should be based on an assessment of potential benefits and risks including whether the patient is likely to tolerate the lowest dose of amlodipine and valsartan tablets.
Patients with stage 2 hypertension (moderate or severe) are at a relatively higher risk for cardiovascular… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION General Considerations : Majority of effect attained within 2 weeks ( 2.1 ) May be administered with other antihypertensive agents ( 2.1 ) Hypertension: May be used as add-on therapy for patients not controlled on monotherapy ( 2.2 ) Patients who experience dose-limiting adverse reactions on monotherapy may be switched to amlodipine and valsartan tablets containing a lower dose of that component ( 2.2 ) May be substituted for titrated components ( 2.3 ) When used as initial therapy: Initiate with 5/160 mg, then titrate upwards as necessary to a maximum of 10/320 mg once daily ( 2.4 )
2.1General Considerations Dose once daily. The dosage can be increased after 1 to 2 weeks of therapy to a maximum of one 10/320 mg tablet once daily as needed to control blood pressure. The majority of the antihypertensive effect is attained within 2 weeks after initiation of therapy or a change in dose. Amlodipine and valsartan tablets may be administered with other antihypertensive agents.
2.2Add-on Therapy A patient whose blood pressure is not adequately controlled with amlodipine (or another dihydropyridine calcium-channel blocker) alone or with valsartan (or another ARB) alone may be switched to combination therapy with amlodipine and valsartan tablets. A patient who experiences dose-limiting adverse reactions on either component alone may be switched to amlodipine and valsartan tablets containing a lower dose of that component in combination with the other to achieve similar blood pressure reductions.
The clinical response to amlodipine and valsartan tablets should be subsequently evaluated and if blood pressure remains uncontrolled after 3 to 4 weeks of therapy, the dose may be titrated up to a maximum of 10/320 mg.
2.3Replacement Therapy For convenience, patients receiving amlodipine and valsartan from separate tablets may instead wish to receive tablets of amlodipine and valsartan tablets containing the same component doses.
2.4Initial Therapy A patient may be initiated on amlodipine and valsartan tablets if it is unlikely that control of blood pressure would be achieved with a single agent. The usual starting dose is amlodipine and valsartan tablets 5/160 mg once daily in patients who are not volume-depleted.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS (Amlodipine and valsartan) tablets are available as follows: 5/160 mg tablets, debossed with LU/Q12 (side 1/side 2) 10/160 mg tablets, debossed with LU/Q14 5/320 mg tablets, debossed with LU/Q13 10/320 mg tablets, debossed with LU/Q15 Tablets (amlodipine/valsartan mg): 5/160, 10/160, 5/320, 10/320 ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Do not use in patients with known hypersensitivity to any component. Do not coadminister aliskiren with amlodipine and valsartan in patients with diabetes [see Drug Interactions ( 7 )] . Known hypersensitivity to any component; Do not coadminister aliskiren with amlodipine and valsartan in patients with diabetes ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume depletion prior to initiation ( 5.2 ) Increased angina and/or myocardial infarction ( 5.3 ) Monitor renal function and potassium in susceptible patients ( 5.4 , 5.5 )
5.1Fetal Toxicity Amlodipine and valsartan tablets can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue amlodipine and valsartan tablets as soon as possible [see Use in Specific Populations ( 8.1 )] .
5.2Hypotension Excessive hypotension was seen in 0.4% of patients with uncomplicated hypertension treated with amlodipine and valsartan tablets in placebo-controlled studies. In patients with an activated renin-angiotensin system, such as volume-and/or salt-depleted patients receiving high doses of diuretics, symptomatic hypotension may occur in patients receiving angiotensin receptor blockers. Volume depletion should be corrected prior to administration of amlodipine and valsartan tablets.
Treatment with amlodipine and valsartan tablets should start under close medical supervision. Initiate therapy cautiously in patients with heart failure or recent myocardial infarction and in patients undergoing surgery or dialysis. Patients with heart failure or post-myocardial infarction patients given valsartan commonly have some reduction in blood pressure, but discontinuation of therapy because of continuing symptomatic hypotension usually is not necessary when dosing instructions are followed.
In controlled trials in heart failure patients, the incidence of hypotension in valsartan-treated patients was 5.5% compared to 1.8% in placebo-treated patients. In the Valsartan in Acute Myocardial Infarction Trial (VALIANT), hypotension in post-myocardial infarction patients led to permanent discontinuation of therapy in 1.4% of valsartan-treated patients and 0.8% of captopril-treated patients. Since the vasodilation induced by amlodipine is gradual in onset, acute hypotension has rarely been reported after oral administration.
Nonetheless, caution, as with any other peripheral vasodilator, should be exercised when administering amlodipine, particularly in patients with severe aortic stenosis. If excessive hypotension occurs with amlodipine and valsartan tablets, place the patient in a supine position and, if necessary, give intravenous normal saline. A transient hypotensive response is not a contraindication to further treatment, which usually can be continued without difficulty once the blood pressure has stabilized.
5.3Risk of Myocardial Infarction or Increased Angina Worsening angina and acute myocardial infarction can develop after starting or increasing the dose of amlodipine, particularly in patients with severe obstructive coronary artery disease.
5.4Impaired Renal Function Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on amlodipine and valsartan tablets. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on amlodipine and valsartan tablets [see Drug Interactions ( 7 )] .
5.5Hyperkalemia Drugs that inhibit the renin-angiotensin system can cause hyperkalemia. Monitor serum electrolytes periodica… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS In placebo-controlled clinical trials, discontinuation due to side effects occurred in 1.8% of patients in the amlodipine and valsartan tablets-treated patients and 2.1% in the placebo-treated group. The most common reasons for discontinuation of therapy with amlodipine and valsartan tablets were peripheral edema and vertigo. The adverse experiences that occurred in clinical trials (≥2% of patients) at a higher incidence than placebo included peripheral edema, nasopharyngitis, upper respiratory tract infection, and dizziness.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals Inc. at 1-800-399-2561 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates. Studies with Amlodipine and Valsartan Tablets Amlodipine and valsartan tablets has been evaluated for safety in over 2600 patients with hypertension; over 1440 of these patients were treated for at least 6 months and over 540 of these patients were treated for at least 1 year.
Adverse reactions have generally been mild and transient in nature and have only infrequently required discontinuation of therapy. The hazards [see Warnings and Precautions ( 5 )] of valsartan are generally independent of dose; those of amlodipine are a mixture of dose-dependent phenomena (primarily peripheral edema) and dose-independent phenomena, the former much more common than the latter. The overall frequency of adverse reactions was neither dose-related nor related to gender, age, or race.
In placebo-controlled clinical trials, discontinuation due to side effects occurred in 1.8% of patients in the amlodipine and valsartan tablets-treated patients and 2.1% in the placebo-treated group. The most common reasons for discontinuation of therapy with amlodipine and valsartan tablets were peripheral edema (0.4%), and vertigo (0.2%). The adverse reactions that occurred in placebo-controlled clinical trials in at least 2% of patients treated with amlodipine and valsartan tablets but at a higher incidence in amlodipine/valsartan patients (n=1437) than placebo (n=337) included peripheral edema (5.4% vs.
3.0%), nasopharyngitis (4.3% vs 1.8%), upper respiratory tract infection (2.9% vs 2.1%) and dizziness (2.1% vs 0.9%). Orthostatic events (orthostatic hypotension and postural dizziness) were seen in less than 1% of patients. Studies with Valsartan Diovan ®# has been evaluated for safety in more than 4000 hypertensive patients in clinical trials.
In trials in which valsartan was compared to an angiotensin-converting enzyme (ACE) inhibitor with or without placebo, the incidence of dry cough was significantly greater in the ACE inhibitor group (7.9%) than in the groups who received valsartan (2.6%) or placebo (1.5%). In a 129-patient trial limited to patients who had had dry cough when they had previously received ACE inhibitors, the incidences of cough in patients who received valsartan, HCTZ, or lisinopril were 20%, 19%, and 69% respectively (p<0.001). Clinical Lab Test Findings Creatinine: In heart failure patients, greater than 50% increases in creatinine were observed in 3.9% of valsartan-treated patients compared to 0.9% of placebo-treated patients.
In post-myocardial infarction patients, doubling of serum creatinine was observed in 4.2% of valsartan-treated patients and 3.4% of captopril-treated patients. Blood Urea Nitrogen (BUN): In hypertensive patients, greater than 50% increases in BUN were observed in 5.5% of amlodipine and valsartan tablets-treated patients compared to 4.7% of placebo-tre… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No drug interaction studies have been conducted with amlodipine and valsartan tablets and other drugs, although studies have been conducted with the individual amlodipine and valsartan components. Amlodipine Impact of Other Drugs on Amlodipine CYP3A Inhibitors : Coadministration with CYP3A inhibitors (moderate and strong) results in increased systemic exposure to amlodipine and may require dose reduction. Monitor for symptoms of hypotension and edema when amlodipine is coadministered with CYP3A inhibitors to determine the need for dose adjustment [see Clinical Pharmacology ( 12.3 )] .
CYP3A Inducers : No information is available on the quantitative effects of CYP3A inducers on amlodipine. Blood pressure should be closely monitored when amlodipine is co-administered with CYP3A inducers. (e.g. rifampicin, St.
John's Wort). Sildenafil : Monitor for hypotension when sildenafil is co-administered with amlodipine [see Clinical Pharmacology ( 12.2 )] . Impact of Amlodipine on Other Drugs Simvastatin: Co-administration of simvastatin with amlodipine increases the systemic exposure of simvastatin.
Limit the dose of simvastatin in patients on amlodipine to 20 mg daily [see Clinical Pharmacology ( 12.3 )] . Immunosuppressants: Amlodipine may increase the systemic exposure of cyclosporine or tacrolimus when co-administered. Frequent monitoring of trough blood levels of cyclosporine and tacrolimus is recommended and adjust the dose when appropriate [see Clinical Pharmacology ( 12.3 )] .
Valsartan Agents Increasing Serum Potassium: Concomitant use of valsartan with other agents that block the renin-angiotensin system, potassium-sparing diuretics (e.g., spironolactone, triamterene, amiloride), potassium supplements, salt substitutes containing potassium or other drugs that may increase potassium levels (e.g., heparin) may lead to increases in serum potassium and in heart failure patients to increases in serum creatinine. If co-medication is considered necessary, monitoring of serum potassium is advisable.
Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors): In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists, including valsartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving valsartan and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including valsartan may be attenuated by NSAIDs including selective COX-2 inhibitors. Dual Blockade of the Renin-Angiotensin System (RAS): Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of two RAS inhibitors do not obtain any additional benefit compared to monotherapy.
In general, avoid combined use of RAS inhibitors. Closely monitor blood pressure, renal function, and electrolytes in patients on valsartan and other agents that affect the RAS. Do not coadminister aliskiren with amlodipine and valsartan in patients with diabetes.
Avoid use of aliskiren with amlodipine and valsartan in patients with renal impairment (GFR <60 mL/min). Lithium: Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists. Monitor serum lithium levels during concomitant use.
If simvastatin is coadministered with amlodipine, do not exceed doses greater than 20 mg daily of simvastatin ( 7 ) Non-Steroidal Anti-Inflammatory Drug (NSAID) use may lead to increased risk of renal impairment… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended ( 8.2 ) Geriatric Patients: Not recommended for initial therapy ( 8.5 ) Hepatic Impairment: Not recommended for initial therapy ( 8.7 )
8.1Pregnancy Risk Summary Amlodipine and valsartan can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan ( see Clinical Considerations ). When pregnancy is detected, discontinue amlodipine and valsartan as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease- Associated Maternal and/or Embryo/Fetal risk: Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions: Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
If oligohydramnios is observed, consider alternative drug treatment. Closely observe neonates with histories of in utero exposure to amlodipine and valsartan for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to amlodipine and valsartan, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Data Animal Data: In rats, administered 20 mg/kg/day amlodipine plus 320 mg/kg/day valsartan, treatment-related maternal and fetal effects (developmental delays and alterations noted in the presence of significant maternal toxicity) were noted with the high dose combination. This corresponds to dose multiples of 9 and 19.5 times, respectively, the maximum recommended human dose (MRHD) of 10 mg/day for amlodipine and 320 mg/day for valsartan (based on body surface area and considering a 60 kg patient).
8.2Lactation Risk Summary There is limited information regarding the presence of amlodipine and valsartan in human milk, the effects on the breastfed infant, or the effects on milk production. Valsartan is present in rat milk. Limited published studies report that amlodipine is present in human milk.
Because of the potential for serious adverse reactions in breastfed infants, advise a nursing woman that breastfeeding is not recommended during treatment with amlodipine and valsartan tablets. Data Valsartan was detected in the milk of lactating rats 15… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Amlodipine and valsartan can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Published reports include cases of anhydramnios and oligohydramnios in pregnant women treated with valsartan ( see Clinical Considerations ). When pregnancy is detected, discontinue amlodipine and valsartan as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease- Associated Maternal and/or Embryo/Fetal risk: Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage).
Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions: Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension and death.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
If oligohydramnios is observed, consider alternative drug treatment. Closely observe neonates with histories of in utero exposure to amlodipine and valsartan for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to amlodipine and valsartan, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Data Animal Data: In rats, administered 20 mg/kg/day amlodipine plus 320 mg/kg/day valsartan, treatment-related maternal and fetal effects (developmental delays and alterations noted in the presence of significant maternal toxicity) were noted with the high dose combination. This corresponds to dose multiples of 9 and 19.5 times, respectively, the maximum recommended human dose (MRHD) of 10 mg/day for amlodipine and 320 mg/day for valsartan (based on body surface area and considering a 60 kg patient).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of amlodipine and valsartan tablets in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In controlled clinical trials, 323 (22.5%) hypertensive patients treated with amlodipine and valsartan tablets were ≥65 years and 79 (5.5%) were ≥75 years. No overall differences in the efficacy or safety of amlodipine and valsartan tablets were observed in this patient population, but greater sensitivity of some older individuals cannot be ruled out. Amlodipine The recommended starting dose of amlodipine 2.5 mg is not an available strength with amlodipine and valsartan tablets.
Clinical studies of amlodipine besylate tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
Elderly patients have decreased clearance of amlodipine with a resulting increase of area under the curve (AUC) of approximately 40% to 60%. Valsartan In the controlled clinical trials of valsartan, 1214 (36.2%) of hypertensive patients treated with valsartan were ≥65 years and 265 (7.9%) were ≥75 years. No overall difference in the efficacy or safety of valsartan was observed in this patient population, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Amlodipine Single oral doses of amlodipine maleate equivalent to 40 mg/kg and 100 mg/kg amlodipine in mice and rats, respectively, caused deaths. Single oral doses equivalent to 4 or more mg/kg amlodipine in dogs (11 or more times the maximum recommended human dose on a mg/m 2 basis) caused a marked peripheral vasodilation and hypotension. Overdosage might be expected to cause excessive peripheral vasodilation with marked hypotension.
In humans, experience with intentional overdosage of amlodipine is limited. Marked and potentially prolonged systemic hypotension up to and including shock with fatal outcome have been reported. If massive overdose should occur, initiate active cardiac and respiratory monitoring.
Frequent blood pressure measurements are essential. Should hypotension occur, cardiovascular support including elevation of the extremities and the judicious administration of fluids should be initiated. If hypotension remains unresponsive to these conservative measures, consider administration of vasopressors (such as phenylephrine) with attention to circulating volume and urine output.
As amlodipine is highly protein bound, hemodialysis is not likely to be of benefit. Administration of activated charcoal to healthy volunteers immediately or up to two hours after ingestion of amlodipine has been shown to significantly decrease amlodipine absorption. Valsartan Limited data are available related to overdosage in humans.
The most likely effect of overdose with valsartan would be peripheral vasodilation, hypotension, and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation. Depressed level of consciousness, circulatory collapse, and shock have been reported. If symptomatic hypotension should occur institute supportive treatment.
Valsartan is not removed from the plasma by hemodialysis. Valsartan was without grossly observable adverse effects at single oral doses up to 2000 mg/kg in rats and up to 1000 mg/kg in marmosets, except for the salivation and diarrhea in the rat and vomiting in the marmoset at the highest dose (60 and 37 times, respectively, the (MRHD) on a mg/m 2 basis). (Calculations assume an oral dose of 320 mg/day and a 60 kg patient.)
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Amlodipine Amlodipine is a dihydropyridine calcium channel blocker that inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. Experimental data suggest that amlodipine binds to both dihydropyridine and nondihydropyridine binding sites. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels.
Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses. Serum calcium concentration is not affected by amlodipine.
Within the physiologic pH range, amlodipine is an ionized compound (pKa=8.6), and its kinetic interaction with the calcium channel receptor is characterized by a gradual rate of association and dissociation with the receptor binding site, resulting in a gradual onset of effect. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure. Valsartan Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II).
Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland. Its action is therefore independent of the pathways for angiotensin II synthesis.
There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Valsartan has much greater affinity (about 20,000-fold) for the AT 1 receptor than for the AT 2 receptor. The increased plasma levels of angiotensin following AT 1 receptor blockade with valsartan may stimulate the unblocked AT 2 receptor.
The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one-200 th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE.
Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known. Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure.
12.2Pharmacodynamics Amlodipine Following administration of therapeutic doses to patients with hypertension, amlodipine produces vasodilation resulting in a reduction of supine and standing blood pressures. These decreases in blood pressure are not accompanied by a significant change in heart rate or plasma catecholamine levels with chronic dosing. Although the acute intravenous administration of amlodipine decreases arterial blood pressure and increases heart rate in hemodynamic studies of patients with chronic stable angina, chronic oral administration of amlodipine in clinical trials did not lead to clinically significant changes in heart rate or bloo… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Amlodipine Amlodipine is a dihydropyridine calcium channel blocker that inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. Experimental data suggest that amlodipine binds to both dihydropyridine and nondihydropyridine binding sites. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels.
Amlodipine inhibits calcium ion influx across cell membranes selectively, with a greater effect on vascular smooth muscle cells than on cardiac muscle cells. Negative inotropic effects can be detected in vitro but such effects have not been seen in intact animals at therapeutic doses. Serum calcium concentration is not affected by amlodipine.
Within the physiologic pH range, amlodipine is an ionized compound (pKa=8.6), and its kinetic interaction with the calcium channel receptor is characterized by a gradual rate of association and dissociation with the receptor binding site, resulting in a gradual onset of effect. Amlodipine is a peripheral arterial vasodilator that acts directly on vascular smooth muscle to cause a reduction in peripheral vascular resistance and reduction in blood pressure. Valsartan Angiotensin II is formed from angiotensin I in a reaction catalyzed by angiotensin-converting enzyme (ACE, kininase II).
Angiotensin II is the principal pressor agent of the renin-angiotensin system, with effects that include vasoconstriction, stimulation of synthesis and release of aldosterone, cardiac stimulation, and renal reabsorption of sodium. Valsartan blocks the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor in many tissues, such as vascular smooth muscle and the adrenal gland. Its action is therefore independent of the pathways for angiotensin II synthesis.
There is also an AT 2 receptor found in many tissues, but AT 2 is not known to be associated with cardiovascular homeostasis. Valsartan has much greater affinity (about 20,000-fold) for the AT 1 receptor than for the AT 2 receptor. The increased plasma levels of angiotensin following AT 1 receptor blockade with valsartan may stimulate the unblocked AT 2 receptor.
The primary metabolite of valsartan is essentially inactive with an affinity for the AT 1 receptor about one-200 th that of valsartan itself. Blockade of the renin-angiotensin system with ACE inhibitors, which inhibit the biosynthesis of angiotensin II from angiotensin I, is widely used in the treatment of hypertension. ACE inhibitors also inhibit the degradation of bradykinin, a reaction also catalyzed by ACE.
Because valsartan does not inhibit ACE (kininase II), it does not affect the response to bradykinin. Whether this difference has clinical relevance is not yet known. Valsartan does not bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
Blockade of the angiotensin II receptor inhibits the negative regulatory feedback of angiotensin II on renin secretion, but the resulting increased plasma renin activity and angiotensin II circulating levels do not overcome the effect of valsartan on blood pressure.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Amlodipine and Valsartan is available as tablets containing amlodipine besylate (6.9 mg or 13.9 mg, equivalent to 5 mg, or 10 mg of amlodipine respectively) with valsartan 160 mg or 320 mg, providing for the following available combinations: 5/160 mg, 10/160 mg, 5/320 mg, and 10/320 mg. All strengths are packaged in bottles of 30, 90 and 500 count, and unit dose blister packages. 5/160 mg Tablets - Mustard coloured, capsule shaped, film coated, biconvex tablets debossed 'LU' on one side and 'Q12' on the other side.
Bottles of 30 NDC # 68180-764-06 Bottles of 90 NDC # 68180-764-09 Bottles of 500 NDC # 68180-764-02 Unit Dose 100 tablets (10 X 10 tablets blister cards) NDC # 68180-764-13 10/160 mg Tablets - Yellow, capsule shaped, film coated, biconvex tablets debossed 'LU' on one side and 'Q14' on the other side. Bottles of 30 NDC # 68180-765-06 Bottles of 90 NDC # 68180-765-09 Bottles of 500 NDC # 68180-765-02 Unit Dose 100 tablets (10 X 10 tablets blister cards) NDC # 68180-765-13 5/320 mg Tablets - Mustard coloured, capsule shaped, film coated, biconvex tablets debossed 'LU' on one side and 'Q13' on the other side.
Bottles of 30 NDC # 68180-766-06 Bottles of 90 NDC # 68180-766-09 Bottles of 500 NDC # 68180-766-02 Unit Dose 100 tablets (10 X 10 tablets blister cards) NDC # 68180-766-13 10/320 mg Tablets - Yellow, capsule shaped, film coated, biconvex tablets debossed 'LU' on one side and 'Q15' on the other side Bottles of 30 NDC # 68180-767-06 Bottles of 90 NDC # 68180-767-09 Bottles of 500 NDC # 68180-767-02 Unit Dose 100 tablets (10 X 10 tablets blister cards) NDC # 68180-767-13 Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted between 15°C and 30ºC (59ºF and 86ºF) [See USP Controlled Room Temperature].
Protect from moisture.
📋 Description ▾
11 DESCRIPTION Amlodipine and valsartan tablet USP is a fixed combination of amlodipine and valsartan. Amlodipine and valsartan tablets USP contain the besylate salt of amlodipine, a dihydropyridine calcium-channel blocker (CCB). Amlodipine besylate is a white to pale yellow crystalline powder, slightly soluble in water and sparingly soluble in ethanol.
Amlodipine besylate's chemical name is 3-Ethyl-5-methyl(4RS)-2-[(2-aminoethoxy)methyl]-4-(2-chlorophenyl)-6-methyl-1,4-dihydropyridine-3,5-dicarboxylate benzenesulphonate; its structural formula is Its empirical formula is C 20 H 25 ClN 2 O 5 •C 6 H 6 O 3 S and its molecular weight is 567.1. Valsartan is a nonpeptide, orally active, and specific angiotensin II antagonist acting on the AT 1 receptor subtype. Valsartan is a white to practically white fine powder, soluble in ethanol and methanol and slightly soluble in water.
Valsartan's chemical name is N-(1-oxopentyl)-N-[[2'-(1H-tetrazol-5-yl) [1,1'-biphenyl]-4-yl]methyl]-L-valine; its structural formula is Its empirical formula is C 24 H 29 N 5 O 3 and its molecular weight is 435.5. Amlodipine and valsartan tablets USP are formulated in 4 strengths for oral administration with a combination of amlodipine besylate (6.9 mg or 13.9 mg, equivalent to 5 mg or 10 mg of amlodipine respectively), with 160 mg, or 320 mg of valsartan providing for the following available combinations: 5/160 mg, 10/160 mg, 5/320 mg, and 10/320 mg.
The inactive ingredients for all strengths of the tablets are colloidal silicon dioxide, croscarmellose sodium, crospovidone, magnesium stearate and microcrystalline cellulose. The film coating contains hypromellose, polyethylene glycol, iron oxide yellow and titanium dioxide. Additionally, the 5/160 mg and 5/320 mg strengths contain iron oxide red.
Amlodipine and valsartan tablets USP meets USP Dissolution Test 2. 05 06
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Information for Patients Advise the patient to read the FDA-approved patient labeling (Patient Information). Pregnancy Advise female patients of childbearing age about the consequences of exposure to amlodipine and valsartan tablets during pregnancy. Discuss treatment options with women planning to become pregnant.
Ask patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.1 )] . Lactation Advise women not to breastfeed during treatment with amlodipine and valsartan tablets [see Use in Specific Populations ( 8.2 )]. Symptomatic Hypotension Advise patients that lightheadedness can occur, especially during the first days of therapy, and that it should be reported to their healthcare provider.
Tell patients that if syncope occurs to discontinue amlodipine and valsartan tablets until the physician has been consulted. Caution all patients that inadequate fluid intake, excessive perspiration, diarrhea, or vomiting can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope [see Warnings and Precautions ( 5.2 )] . Hyperkalemia Advise patients not to use salt substitutes without consulting their healthcare provider [see Drug Interactions ( 7 )] .
The brands listed are trademarks of their respective owners and are not trademarks of Lupin Pharmaceuticals, Inc. The makers of these brands are not affiliated with and do not endorse Lupin Pharmaceuticals, Inc. or its products. Manufactured for: Lupin Pharmaceuticals, Inc.
Baltimore, Maryland 21202 United States Manufactured by: Lupin Limited Goa - 403722 India Revised: July 2021
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Amlodipine Peak plasma concentrations of amlodipine are reached 6 to 12 hours after administration of amlodipine alone. Absolute bioavailability has been estimated to be between 64% and 90%. The bioavailability of amlodipine is not altered by the presence of food.
The apparent volume of distribution of amlodipine is 21 L/kg. Approximately 93% of circulating amlodipine is bound to plasma proteins in hypertensive patients. Amlodipine is extensively (about 90%) converted to inactive metabolites via hepatic metabolism with 10% of the parent compound and 60% of the metabolites excreted in the urine.
Elimination of amlodipine from the plasma is biphasic with a terminal elimination half-life of about 30 to 50 hours. Steady state plasma levels of amlodipine are reached after 7 to 8 days of consecutive daily dosing. Valsartan Following oral administration of valsartan alone peak plasma concentrations of valsartan are reached in 2 to 4 hours.
Absolute bioavailability is about 25% (range 10% to 35%). Food decreases the exposure (as measured by AUC) to valsartan by about 40% and peak plasma concentration (C max ) by about 50%. The steady state volume of distribution of valsartan after intravenous administration is 17 L indicating that valsartan does not distribute into tissues extensively.
Valsartan is highly bound to serum proteins (95%), mainly serum albumin. Valsartan shows biexponential decay kinetics following intravenous administration with an average elimination half-life of about 6 hours. The recovery is mainly as unchanged drug, with only about 20% of dose recovered as metabolites.
The primary metabolite, accounting for about 9% of dose, is valeryl 4-hydroxy valsartan. In vitro metabolism studies involving recombinant CYP 450 enzymes indicated that the CYP 2C9 isoenzyme is responsible for the formation of valeryl-4-hydroxy valsartan. Valsartan does not inhibit CYP 450 isozymes at clinically relevant concentrations.
CYP 450 mediated drug interaction between valsartan and coadministered drugs are unlikely because of the low extent of metabolism. Valsartan, when administered as an oral solution, is primarily recovered in feces (about 83% of dose) and urine (about 13% of dose). Following intravenous administration, plasma clearance of valsartan is about 2 L/h and its renal clearance is
0.62L/h (about 30% of total clearance). Amlodipine and valsartan tablets Following oral administration of amlodipine and valsartan tablets in normal healthy adults, peak plasma concentrations of valsartan and amlodipine are reached in 3 and 6 to 8 hours, respectively. The rate and extent of absorption of valsartan and amlodipine from amlodipine and valsartan tablets are the same as when administered as individual tablets.
The bioavailabilities of amlodipine and valsartan are not altered by the coadministration of food. Amlodipine and valsartan may be administered with or without food. Specific Populations Geriatric: Amlodipine Elderly patients have decreased clearance of amlodipine with a resulting increase in peak plasma levels, elimination half-life and AUC.
Valsartan Exposure (measured by AUC) to valsartan is higher by 70% and the half-life is longer by 35% in the elderly than in the young. No dosage adjustment is necessary. Gender Valsartan Pharmacokinetics of valsartan does not differ significantly between males and females.
Renal Insufficiency Amlodipine The pharmacokinetics of amlodipine is not significantly influenced by renal impairment. Valsartan There is no apparent correlation between renal function (measured by creatinine clearance) and exposure (measured by AUC) to valsartan in patients with different degrees of renal impairment. Consequently, dose adjustment is not required in patients with mild-to-moderate renal dysfunction.
No studies have been performed in patients with severe impairment of renal function (creatinine clearance <10 mL/min). Valsartan is not removed from the plasma by hemodialysis. In the case of… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Amlodipine Following administration of therapeutic doses to patients with hypertension, amlodipine produces vasodilation resulting in a reduction of supine and standing blood pressures. These decreases in blood pressure are not accompanied by a significant change in heart rate or plasma catecholamine levels with chronic dosing. Although the acute intravenous administration of amlodipine decreases arterial blood pressure and increases heart rate in hemodynamic studies of patients with chronic stable angina, chronic oral administration of amlodipine in clinical trials did not lead to clinically significant changes in heart rate or blood pressures in normotensive patients with angina.
With chronic, once-daily administration, antihypertensive effectiveness is maintained for at least 24 hours. Plasma concentrations correlate with effect in both young and elderly patients. The magnitude of reduction in blood pressure with amlodipine is also correlated with the height of pretreatment elevation; thus, individuals with moderate hypertension (diastolic pressure 105 to 114 mmHg) had about a 50% greater response than patients with mild hypertension (diastolic pressure 90 to 104 mmHg).
Normotensive subjects experienced no clinically significant change in blood pressure (+1/-2 mmHg). In hypertensive patients with normal renal function, therapeutic doses of amlodipine resulted in a decrease in renal vascular resistance and an increase in glomerular filtration rate and effective renal plasma flow without change in filtration fraction or proteinuria. As with other calcium channel blockers, hemodynamic measurements of cardiac function at rest and during exercise (or pacing) in patients with normal ventricular function treated with amlodipine have generally demonstrated a small increase in cardiac index without significant influence on dP/dt or on left ventricular end diastolic pressure or volume.
In hemodynamic studies, amlodipine has not been associated with a negative inotropic effect when administered in the therapeutic dose range to intact animals and man, even when coadministered with beta-blockers to man. Similar findings, however, have been observed in normal or well-compensated patients with heart failure with agents possessing significant negative inotropic effects. Amlodipine does not change sinoatrial nodal function or atrioventricular (AV) conduction in intact animals or man.
In patients with chronic stable angina, intravenous administration of 10 mg did not significantly alter A-H and H-V conduction and sinus node recovery time after pacing. Similar results were obtained in patients receiving amlodipine and concomitant beta-blockers. In clinical studies in which amlodipine was administered in combination with beta-blockers to patients with either hypertension or angina, no adverse effects of electrocardiographic (ECG) parameters were observed.
In clinical trials with angina patients alone, amlodipine therapy did not alter electrocardiographic intervals or produce higher degrees of AV blocks. Amlodipine has indications other than hypertension which can be found in the Norvasc* package insert. Drug Interactions: Sildenafil When amlodipine and sildenafil were used in combination, each agent independently exerted its own blood pressure lowering effect [see Drug Interactions ( 7 )] .
Valsartan Valsartan inhibits the pressor effect of angiotensin II infusions. An oral dose of 80 mg inhibits the pressor effect by about 80% at peak with approximately 30% inhibition persisting for 24 hours. No information on the effect of larger doses is available.
Removal of the negative feedback of angiotensin II causes a 2- to 3-fold rise in plasma renin and consequent rise in angiotensin II plasma concentration in hypertensive patients. Minimal decreases in plasma aldosterone were observed after administration of valsartan; very little effect on serum potassium was observed. In multiple dose studies in hypertensive patients with st… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Amlodipine and valsartan tablets were studied in 2 placebo-controlled and 4 active-controlled trials in hypertensive patients. In a double-blind, placebo-controlled study, a total of 1012 patients with mild-to-moderate hypertension received treatments of 3 combinations of amlodipine and valsartan (5/80, 5/160, 5/320 mg) or amlodipine alone (5 mg), valsartan alone (80, 160, or 320 mg) or placebo. All doses with the exception of the 5/320 mg dose were initiated at the randomized dose.
The high dose was titrated to that dose after a week at a dose of 5/160 mg. At week 8, the combination treatments were statistically significantly superior to their monotherapy components in reduction of diastolic and systolic blood pressures. Table 1: Effect of Amlodipine and Valsartan Tablets on Sitting Diastolic Blood Pressure *Mean Change and Placebo-Subtracted Mean Change from Baseline (mmHg) at Week 8 in Sitting Diastolic Blood Pressure.
Mean baseline diastolic BP was 99.3 mmHg. Amlodipine dosage Valsartan dosage 0 mg 80 mg 160 mg 320 mg Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted 0 mg -6.4 --- -9.5 -3.1 -10.9 -4.5 -13.2 -6.7 5 mg -11.1 -4.7 -14.2 -7.8 -14.0 -7.6 -15.7 -9.3 Table 2: Effect of Amlodipine and Valsartan Tablets on Sitting Systolic Blood Pressure *Mean Change and Placebo-Subtracted Mean Change from Baseline (mmHg) at Week 8 in Sitting Systolic Blood Pressure.
Mean baseline systolic BP was 152.8 mmHg. Amlodipine dosage Valsartan dosage 0 mg 80 mg 160 mg 320 mg Mean Change* Placebo-subtracted Mean Change* Placebo-subtracted Mean Change* Placebo-subtracted Mean Change* Placebo-subtracted 0 mg -6.2 --- -12.9 -6.8 -14.3 -8.2 -16.3 -10.1 5 mg -14.8 -8.6 -20.7 -14.5 -19.4 -13.2 -22.4 -16.2 In a double-blind, placebo controlled study, a total of 1246 patients with mild to moderate hypertension received treatments of 2 combinations of amlodipine and valsartan (10/160, 10/320 mg) or amlodipine alone (10 mg), valsartan alone (160 or 320 mg) or placebo.
With the exception of the 10/320 mg dose, treatment was initiated at the randomized dose. The high dose was initiated at a dose of 5/160 mg and titrated to the randomized dose after 1 week. At week 8, the combination treatments were statistically significantly superior to their monotherapy components in reduction of diastolic and systolic blood pressures.
Table 3: Effect of Amlodipine and Valsartan Tablets on Sitting Diastolic Blood Pressure *Mean Change and Placebo-Subtracted Mean Change from Baseline (mmHg) at Week 8 in Sitting Diastolic Blood Pressure. Mean baseline diastolic BP was 99.1 mmHg. Amlodipine dosage Valsartan dosage 0 mg 160 mg 320 mg Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted 0 mg -8.2 --- -12.8 -4.5 -12.8 -4.5 10 mg -15.0 -6.7 -17.2 -9.0 -18.1 -9.9 Table 4: Effect of Amlodipine and Valsartan Tablets on Sitting Systolic Blood Pressure *Mean Change and Placebo-Subtracted Mean Change from Baseline (mmHg) at Week 8 in Sitting Systolic Blood Pressure.
Mean baseline systolic BP was 156.7 mmHg. Amlodipine dosage Valsartan dosage 0 mg 160 mg 320 mg Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted Mean Change* Placebo- subtracted 0 mg -11.0 --- -18.1 -7.0 -18.5 -7.5 10 mg -22.2 -11.2 -26.6 -15.5 -26.9 -15.9 In a double-blind, active-controlled study, a total of 947 patients with mild to moderate hypertension who were not adequately controlled on valsartan 160 mg received treatments of 2 combinations of amlodipine and valsartan (10/160, 5/160 mg) or valsartan alone (160 mg).
At week 8, the combination treatments were statistically significantly superior to the monotherapy component in reduction of diastolic and systolic blood pressures. Table 5: Effect of Amlodipine and Valsartan Tablets on Sitting Diastolic/Systolic Blood Pressure *Mean Change from Baseline at Week 8 in Sitting Diastolic/Systolic Blood Pres… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Amlodipine Rats and mice treated with amlodipine maleate in the diet for up to 2 years, at concentrations calculated to provide daily dosage levels of 0.5, 1.25, and 2.5 mg amlodipine/kg/day, showed no evidence of a carcinogenic effect of the drug. For the mouse, the highest dose was, on mg/m 2 basis, similar to the MRHD of 10 mg amlodipine/day. For the rat, the highest dose was, on a mg/m 2 basis, about 2.5 the MRHD (Calculations based on a 60 kg patient).
Mutagenicity studies conducted with amlodipine maleate revealed no drug-related effects at either the gene or chromosome level. There was no effect on the fertility of rats treated orally with amlodipine maleate (males for 64 days and females for 14 days prior to mating) at doses of up to 10 mg amlodipine/kg/day (about 10 times the MRHD of 10 mg/day on a mg/m 2 basis). Valsartan There was no evidence of carcinogenicity when valsartan was administered in the diet to mice and rats for up to 2 years at concentrations calculated to provide doses of up to 160 and 200 mg/kg/day, respectively.
These doses in mice and rats are about 2.4 and 6 times, respectively, the MRHD of 320 mg/day on a mg/m 2 basis. (Calculations based on a 60 kg patient.) Mutagenicity assays did not reveal any valsartan-related effects at either the gene or chromosome level. These assays included bacterial mutagenicity tests with Salmonella and E. coli , a gene mutation test with Chinese hamster V79 cells, a cytogenetic test with Chinese hamster ovary cells, and a rat micronucleus test.
Valsartan had no adverse effects on the reproductive performance of male or female rats at oral doses of up to 200 mg/kg/day. This dose is about 6 times the MRHD on a mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Amlodipine Rats and mice treated with amlodipine maleate in the diet for up to 2 years, at concentrations calculated to provide daily dosage levels of 0.5, 1.25, and 2.5 mg amlodipine/kg/day, showed no evidence of a carcinogenic effect of the drug. For the mouse, the highest dose was, on mg/m 2 basis, similar to the MRHD of 10 mg amlodipine/day. For the rat, the highest dose was, on a mg/m 2 basis, about 2.5 the MRHD (Calculations based on a 60 kg patient).
Mutagenicity studies conducted with amlodipine maleate revealed no drug-related effects at either the gene or chromosome level. There was no effect on the fertility of rats treated orally with amlodipine maleate (males for 64 days and females for 14 days prior to mating) at doses of up to 10 mg amlodipine/kg/day (about 10 times the MRHD of 10 mg/day on a mg/m 2 basis). Valsartan There was no evidence of carcinogenicity when valsartan was administered in the diet to mice and rats for up to 2 years at concentrations calculated to provide doses of up to 160 and 200 mg/kg/day, respectively.
These doses in mice and rats are about 2.4 and 6 times, respectively, the MRHD of 320 mg/day on a mg/m 2 basis. (Calculations based on a 60 kg patient.) Mutagenicity assays did not reveal any valsartan-related effects at either the gene or chromosome level. These assays included bacterial mutagenicity tests with Salmonella and E. coli , a gene mutation test with Chinese hamster V79 cells, a cytogenetic test with Chinese hamster ovary cells, and a rat micronucleus test.
Valsartan had no adverse effects on the reproductive performance of male or female rats at oral doses of up to 200 mg/kg/day. This dose is about 6 times the MRHD on a mg/m 2 basis.
📄 Patient Package Insert ▾
FDA-APPROVED PATIENT LABELING PATIENT INFORMATION Amlodipine ( am-LOE-di-peen) and Valsartan ( val-SAR-tan) Tablets USP Rx only Read the Patient Information that comes with amlodipine and valsartan tablets before you start taking it and each time you get a refill. There may be new information. This leaflet does not take the place of talking with your doctor about your medical condition or treatment.
If you have any questions about amlodipine and valsartan tablets, ask your doctor or pharmacist. What is the most important information I should know about amlodipine and valsartan tablets? Amlodipine and valsartan tablets can cause harm or death to an unborn baby.
Talk to your doctor about other ways to lower your blood pressure if you plan to become pregnant. If you get pregnant while taking amlodipine and valsartan tablets, tell your doctor right away. What are amlodipine and valsartan tablets?
Amlodipine and valsartan tablets contains 2 prescription medicines: amlodipine, a calcium channel blocker valsartan, an angiotensin receptor blocker (ARB). Amlodipine and valsartan tablets may be used to lower high blood pressure (hypertension) in adults when 1 medicine to lower your high blood pressure is not enough as the first medicine to lower high blood pressure if your doctor decides you are likely to need more than 1 medicine. Amlodipine and valsartan tablets have not been studied in children under 18 years of age.
What should I tell my doctor before taking amlodipine and valsartan tablets? Tell your doctor about all of your medical conditions, including if you: are pregnant or plan to become pregnant. See "What is the most important information I should know about amlodipine and valsartan tablets?" are breastfeeding or plan to breastfeed.
Amlodipine and valsartan tablet is present in human milk. It is not known whether amlodipine and valsartan tablets affects your breastfed baby or milk production. Do not breastfeed while you are taking amlodipine and valsartan tablets. have heart problems have liver problems have kidney problems are vomiting or having a lot of diarrhea have ever had a reaction called angioedema, to another blood pressure medicine.
Angioedema causes swelling of the face, lips, tongue, throat, and may cause difficulty breathing. Tell your doctor about all the medicines you take, including prescription and nonprescription medicines, vitamins, and herbal supplements. Some of your other medicines and amlodipine and valsartan tablets could affect each other, causing serious side effects.
Especially tell your doctor if you take: simvastatin or other cholesterol-lowering medicine other medicines for high blood pressure or a heart problem water pills (diuretics) potassium supplements. Your doctor may check the amount of potassium in your blood periodically. a salt substitute. Your doctor may check the amount of potassium in your blood periodically. nonsteroidal anti-inflammatory drugs (like ibuprofen or naproxen) medicines used to prevent and treat fungal skin infections (such as ketoconazole, itraconazole) medicines used to treat bacterial infections (such as clarithromycin, telithromycin) certain antibiotics (rifamycin group), a drug used to protect against transplant rejection (cyclosporine) or an antiretroviral drug used to treat HIV/AIDS infection (ritonavir).
These drugs may increase the effect of valsartan. lithium, a medicine used in some types of depression Know the medicines you take. Keep a list of your medicines and show it to your doctor or pharmacist when you get a new medicine. Talk to your doctor or pharmacist before you start taking any new medicine.
Your doctor or pharmacist will know what medicines are safe to take together. How should I take amlodipine and valsartan tablets? Take amlodipine and valsartan tablets exactly as your doctor tells you.
Take amlodipine and valsartan tablets once each day. Amlodipine and valsartan tablets can be taken with or without food. If you miss a dose, take it as soon as… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
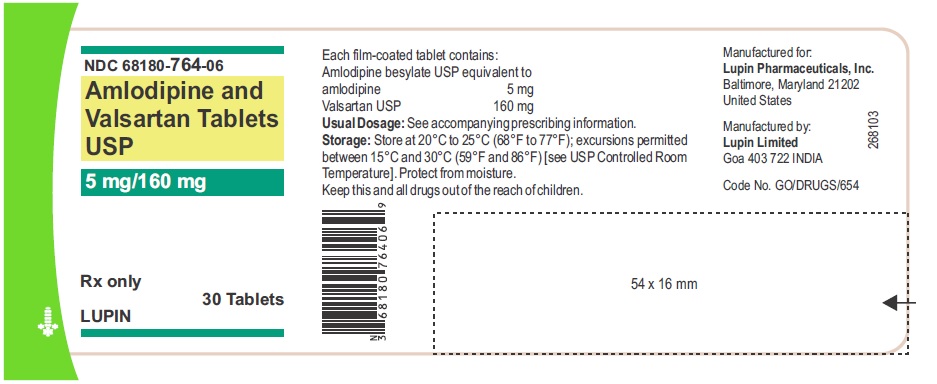
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Strength: 5/160 mg Tablets Container Label: 30s Pack NDC 68180-764-06 Strength: 5/160 mg Tablets Carton Label: 100 Tablets NDC 68180-764-13 Strength: 5/160 mg Tablets NDC 68180-764-11 Blister strip of 10's Strength: 10/160 mg Tablets Container Label: 30s Pack NDC 68180-765-06 Strength: 10/160 mg Tablets Carton Label: 100 Tablets NDC 68180-765-13 Strength: 10/160 mg Tablets NDC 68180-765-11 Blister strip of 10's Strength: 5/320 mg Tablets Container Label: 30s Pack NDC 68180-766-06 Strength: 5/320 mg Tablets Carton Label: 100 Tablets NDC 68180-766-13 Strength: 5/320 mg Tablets NDC 68180-766-11 Blister strip of 10's Strength: 10/320 mg Tablets Container Label: 30s Pack NDC 68180-767-06 Strength: 10/320 mg Tablets Carton Label: 100 Tablets NDC 68180-767-13 Strength: 10/320 mg Tablets NDC 68180-767-11 Blister strip of 10's 07 08 08 09 09 10 11 12 13 13 14 15
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |