
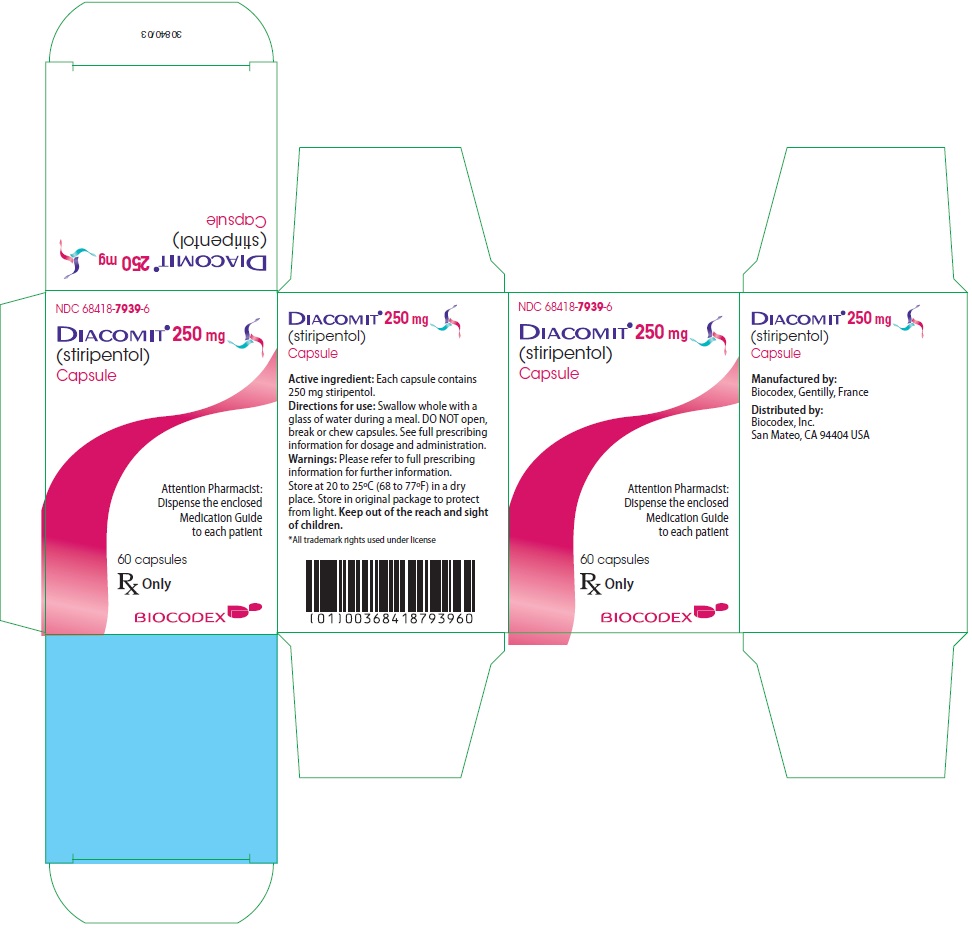
Diacomit stiripentol 500 mg Capsule, 60-count — NDC 68418-7940-6 (Billing 68418-7940-06)
This is a package of 60 capsules of Diacomit stiripentol 500 mg Capsule from BIOCODEX, INC., marketed since Aug 2018 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 063791
- GCN: 99501
- GPI-14 (Medi-Span): 72600070000130
- HICL (First Databank): 035461
- AHFS class code: 28:12.28.00
- RxCUI (RxNorm): 2054973
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Other antiepileptics class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Stiripentol (Diacomit) treats seizures from Dravet syndrome. It's used along with clobazam in children 6 months and older who weigh at least 7 kg. It isn't meant to be used alone.
- Give it by mouth with a meal, split into 2 or 3 doses a day as prescribed. Capsules go down whole with water. The powder is mixed in water and taken right away. If a dose is missed...
- Sleepiness and reduced appetite are the big ones. Weight loss, agitation, unsteadiness, nausea, tremor and trouble sleeping can also happen. Let your doctor know if sleepiness is h...
- Yes. Blood counts are checked before starting and then every 6 months, because stiripentol can lower certain blood cells. Your child's weight and growth will also be watched.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Stiripentol — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $69.86 | $4,191.60 / 60 capsules |
| Medicare drug plans payPart D · Q2 2026 | $77.68 | $4,660.72 / 60 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68418-7940-06 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 60 CAPSULE in 1 BOTTLE | 2018-08-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diacomit 500 mgthis 68418-7940-06 | BIOCODEX, | 60 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Code | What it grants | Expires |
|---|---|---|
| ODE-403 | Orphan Drug Exclusivity (7-year) | Jul 14, 2029 |
| ODE-403 | Orphan Drug Exclusivity (7-year) | Jul 14, 2029 |
Is there a generic version of DIACOMIT 500 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE DIACOMIT is indicated for the treatment of seizures associated with Dravet syndrome (DS) in patients taking clobazam who are 6 months of age and older and weighing 7 kg or more. There are no clinical data to support the use of DIACOMIT as monotherapy in Dravet syndrome. DIACOMIT is indicated for the treatment of seizures associated with Dravet syndrome in patients taking clobazam who are 6 months of age and older and weighing 7 kg or more .
There are no clinical data to support the use of DIACOMIT as monotherapy in Dravet syndrome. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The dosage of DIACOMIT is 50 mg/kg/day, administered by mouth in 2 or 3 divided doses, depending on age and weight. ( 2.2 ) Capsules must be swallowed whole with a glass of water during a meal. Capsules should not be broken or opened. ( 2.3 ) Powder for suspension should be mixed in a glass of water and should be taken immediately after mixing during a meal. ( 2.3 ) Reduce dose or discontinue dose gradually. ( 2.5 )
2.1Laboratory Tests Prior to First Dose of DIACOMIT Hematologic testing should be obtained prior to starting treatment with DIACOMIT [see Warnings and Precautions (5.3) ].
2.2Dosing Information The recommended oral dosage of DIACOMIT is 50 mg/kg/day, administered in 2 or 3 divided doses (i.e., 16.67 mg/kg three times daily or 25 mg/kg twice daily), depending on the patient’s age and body weight as shown in Table 1. If the exact dosage is not achievable given the available strengths, round to the nearest possible dosage, which is usually within 50 mg to 150 mg of the recommended 50 mg/kg/day. A combination of the two DIACOMIT strengths can be used to achieve this dosage.
The maximum recommended total dosage is 3,000 mg/day. Table 1. Recommended Dosage for Patients 6 Months of Age and Older Weighing 7 kg or More with Dravet Syndrome Age of Patient Body Weight Dosing Regimen (administered by mouth in equally divided doses) Total Daily Dose 6 months to less than 1 year 7 kg and above 25 mg/kg twice daily a,b 50 mg/kg/day 1 year and above 7 kg to less than 10 kg 25 mg/kg twice daily b 50 mg/kg/day 10 kg and above 25 mg/kg twice daily or 16.67 mg/kg three times daily 50 mg/kg/day Maximum daily dose is 3000 mg a Dosing frequency should not exceed twice daily to limit free water administration. b Dosing frequency should not exceed twice daily to avoid overexposures.
2.3Administration Instructions DIACOMIT Capsules DIACOMIT capsules must be swallowed whole with a glass of water during a meal. Capsules should not be broken or opened. DIACOMIT for Oral Suspension DIACOMIT should be mixed in a glass of water (100 mL) and should be taken immediately after mixing during a meal.
To be sure there is no medicine left in the glass, add a small amount of water (25 mL) to the drinking cup and drink all of the mixture [see Instructions for Use ] .
2.4Missed Dose A missed dose should be taken as soon as possible. If it is almost time for the next dose, the missed dose should not be taken. Instead, the next scheduled dose should be taken. Doses should not be doubled.
2.5Discontinuation of DIACOMIT As is advisable for most antiepileptic drugs, if DIACOMIT treatment is discontinued, the drug should be withdrawn gradually to minimize the risk of increased seizure frequency and status epilepticus [see Warnings and Precautions ( 5.4 )]. In situations where rapid withdrawal of DIACOMIT is medically required, appropriate monitoring is recommended.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules 250 mg: size 2, pink, and imprinted with “Diacomit” and “250mg” 500 mg: size 0, white, and imprinted with “Diacomit” and “500mg” For Oral Suspension Pale pink fruit flavored powder packaged in packets. Each packet contains either 250 mg or 500 mg of stiripentol Capsule: 250 mg or 500 mg ( 3 ) For Oral Suspension: 250 mg or 500 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Somnolence: Monitor for somnolence, particularly when DIACOMIT is used concomitantly with other CNS depressants; If somnolence occurs during co-administration with clobazam, consider an initial reduction of clobazam by 25%. ( 5.1 ) Decreased Appetite and Decreased Weight: the weight of patients and the growth rate of pediatric patients should be carefully monitored. ( 5.2 ) Neutropenia and Thrombocytopenia: Blood counts should be obtained prior to starting treatment with DIACOMIT and then every 6 months.
( 5.3 ) Withdrawal : DIACOMIT should be gradually withdrawn to minimize the risk of increased seizure frequency and status epilepticus. ( 5.4 ) Risks in Patients with Phenylketonuria (PKU) : DIACOMIT for oral suspension contains phenylalanine; consider total daily intake before prescribing to patients with PKU. ( 5.5 ) Suicidal Behavior and Ideation : Monitor for suicidal thoughts or behaviors.
( 5.6 )
5.1Somnolence DIACOMIT can cause somnolence. In controlled studies in patients with Dravet syndrome, the incidence of somnolence was 67% in DIACOMIT-treated patients, compared to 23% in patients on placebo. All patients in both groups were on concomitant clobazam, which is also known to cause somnolence.
Co-administration of DIACOMIT with clobazam results in increased levels of clobazam and its active metabolite [see Drug Interactions (7.1) ]. Other central nervous system CNS depressants, including alcohol, could potentiate the somnolence effect of DIACOMIT. Prescribers should monitor patients for somnolence.
If somnolence occurs during co-administration with clobazam, consider an initial reduction of clobazam by 25%. If somnolence persists, further clobazam reduction by an additional 25% should be considered, as should adjustment of the dosage of other concomitant anticonvulsant drugs with sedating properties. Prescribers should caution patients against engaging in hazardous activities requiring mental alertness, such as operating dangerous machinery or motor vehicles, until the effect of DIACOMIT on mental alertness is known.
5.2Decreased Appetite and Decreased Weight DIACOMIT can cause decreases in appetite and weight. In controlled studies in patients with Dravet syndrome, the incidence of decreased appetite was 46% in DIACOMIT-treated patients, compared to 10% in patients on placebo. The incidence of decreased weight was 27% in DIACOMIT-treated patients, compared to 6% in patients on placebo.
Nausea and vomiting also occurred more frequently in DIACOMIT-treated patients [see Adverse Reactions (6.1) ] . Given the frequency of these adverse reactions, the growth of pediatric patients treated with DIACOMIT should be carefully monitored. In some cases, decreasing the dose of concomitant valproate by 30% per week can reduce the decrease in appetite and weight.
5.3Neutropenia and Thrombocytopenia DIACOMIT can cause a significant decline in neutrophil count. In controlled studies in patients with Dravet syndrome, there were 31 patients treated with DIACOMIT who had both a baseline and end-of-study neutrophil count obtained. A decrease in neutrophil count from normal at baseline to less than 1500 cells/mm 3 during the trial was observed in 13% of these DIACOMIT- treated patients, but not in any placebo-treated patients.
DIACOMIT can cause a significant decline in platelet count. In controlled studies in patients with Dravet syndrome, there were 31 patients treated with DIACOMIT who had both a baseline and end-of-study platelet count. A decrease in platelet count from normal at baseline to less than 150,000/µL during the trial was observed in 13% of these DIACOMIT-treated patients, but not in any placebo-treated patients.
Hematologic testing should be obtained prior to starting treatment with DIACOMIT, and then every 6 months.
5.4Withdrawal of Antiepileptic Drugs As with most antiepileptic drugs, DIACOMIT should generally be withdrawn gradually to minimize the risk of increased seizure frequency and st… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious or otherwise clinically significant adverse reactions are described elsewhere in the labeling: Somnolence [see Warnings and Precautions (5.1) ] Decreased Appetite and Decreased Weight [see Warnings and Precautions (5.2) ] Neutropenia and Thrombocytopenia [see Warnings and Precautions (5.3) ] Withdrawal Symptoms [see Warnings and Precautions (5.4) ] Risks in Patients with Phenylketonuria [see Warnings and Precautions (5.5) ] Suicidal Behavior and Ideation [see Warnings and Precautions (5.6) ] Adverse reactions that occurred in at least 10% of DIACOMIT-treated patients and more frequently than on placebo were somnolence, decreased appetite, agitation, ataxia, weight decreased, hypotonia, nausea, tremor, dysarthria, and insomnia.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact BIOCODEX at 1-866-330-3050 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in clinical trials of another drug, and may not reflect the rates observed in practice. During its development for the treatment of seizures associated with Dravet syndrome, DIACOMIT was administered to 55 healthy male volunteers and 438 patients with Dravet syndrome, including 310 patients treated for 12 months or more.
The conditions and duration of exposure varied greatly, and included single- and multiple-dose clinical pharmacology studies in healthy male volunteers, 2 randomized, double-blind, placebo-controlled, 12-week studies in patients with Dravet syndrome (Sticlo France and Sticlo Italy), and open-label long-term studies. In Sticlo France and Sticlo Italy, 33 patients received DIACOMIT and 31 patients received placebo for a treatment duration of 8 weeks [see Clinical Studies ( 14 )] . Adverse reactions from these trials are presented below.
Approximately 53% of patients were female and the mean age was 9.2 years. All patients were taking clobazam and valproate. There were 2 patients in whom adverse reactions led to discontinuation of DIACOMIT treatment: one patient had an adverse reaction of status epilepticus; the second patient had drowsiness, balance impaired and sialorrhea.
The most common adverse reactions, occurring in at least 10% of DIACOMIT-treated patients and more frequently than on placebo, included somnolence (67%), decreased appetite (45%), agitation (27%), ataxia (27%), weight decreased (27%), hypotonia (24%), nausea (15%), tremor (15%), dysarthria (12%), and insomnia (12%). Table 3 lists the adverse reactions that occurred in 5% or more of DIACOMIT-treated patients and at a rate greater than in patients on placebo in the 2 randomized, double-blind, placebo-controlled, clinical trials in patients with Dravet syndrome (Sticlo France and Sticlo Italy).
Table 3. Adverse Reactions in 5% or More of DIACOMIT-Treated Patients and More Frequently than on Placebo in Patients with Dravet Syndrome (Sticlo France and Sticlo Italy) Sticlo France and Sticlo Italy– Pooled Total DIACOMIT (50mg/kg/day) Placebo Adverse Reactions N=33 % N=31 % Gastrointestinal disorders Nausea 15 3 Vomiting 9 0 Salivary hypersecretion 6 0 General disorders and administration site conditions Fatigue 9 3 Pyrexia 6 3 Infections and infestations Bronchitis 6 0 Nasopharyngitis 6 0 Investigations Weight decreased 27 6 Weight increased 6 3 Metabolism and nutrition disorders Decreased appetite 46 10 Nervous system disorders Somnolence 67 23 Ataxia 27 23 Hypotonia 18 13 Tremor 15 10 Dysarthria 12 0 Psychiatric disorders Agitation 27 16 Insomnia 12 7 Aggression 9 0 Adverse Reactions in Pediatric Patients 6 months to Less Than 2 Years of Age In five open-label studies including pediatric patients 6 months to less than 2 years of age with Dravet syndrome, a total of 106 patients received DIACOMIT, with 81 patients exposed for at least 6 months, and 69 pat… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS DIACOMIT increases the plasma concentration of clobazam and its metabolite through metabolic inhibition of CYP3A4 and CYP2C19. Consider dose reduction of clobazam in case of adverse reactions. ( 7.1 ) Substrates of CYP2C8, CYP2C19, P-gp and BCRP may require a dose reduction.
(7.1) Substrates of CYP1A2, CYP2B6 and CYP3A4 may require a dose adjustment. ( 7.1 ) Strong inducers of CYP1A2, CYP3A4 or CYP2C19: Consider dose increase of DIACOMIT. ( 7.2 )
7.1Effect of DIACOMIT on Other Drugs CYP1A2, CYP2B6, CYP3A4, CYP2C8, CYP2C19, P-glycoprotein (P-gp) and Breast Cancer Resistance Protein (BCRP) Substrates In vitro data show that stiripentol is both an inhibitor and inducer of CYP1A2, CYP2B6, and CYP3A4. Because of potential drug-drug interactions, consider dose adjustment of CYP1A2 substrates (e.g., theophylline, caffeine), CYP2B6 substrates (e.g., sertraline, thiotepa), and CYP3A4 substrates (e.g., midazolam, triazolam, quinidine), as clinically appropriate, when administered concomitantly with DIACOMIT.
Because of potential inhibition of enzyme/transporter activity, consider a reduction in dosage of substrates of CYP2C8, CYP2C19 (e.g., diazepam, clopidogrel), P-gp (e.g., carbamazepine), and BCRP (e.g., methotrexate, prazosin, glyburide), if adverse reactions are experienced when administered concomitantly with DIACOMIT. Clobazam Co-administration of DIACOMIT (which inhibits CYP 3A4 and 2C19) with clobazam results in increased plasma concentrations of clobazam (a substrate of CYP3A4) and norclobazam, the active metabolite of clobazam (a substrate of CYP2C19) [see Clinical Pharmacology (12.3) ] .
This may increase the risk of clobazam-related adverse reactions. Consider a reduction in dosage of clobazam if adverse reactions are experienced when co-administered with DIACOMIT [see Warnings and Precautions (5.1) ].
7.2Effect of Other Drugs on DIACOMIT Induction-based interactions leading to decreases in DIACOMIT concentrations are possible when co-administered with a potent CYP1A2, CYP3A4, or CYP2C19 inducer, such as rifampin, phenytoin, phenobarbital and carbamazepine, as these enzymes all metabolize stiripentol. Concomitant use of strong inducers with DIACOMIT should be avoided, or dosage adjustments should be made.
7.3CNS Depressants and Alcohol Concomitant use of DIACOMIT with other CNS depressants, including alcohol, may increase the risk of sedation and somnolence [see Warnings and Precautions (5.1) ].
🔄 Drug / Laboratory Test Interactions ▾
7.1Effect of DIACOMIT on Other Drugs CYP1A2, CYP2B6, CYP3A4, CYP2C8, CYP2C19, P-glycoprotein (P-gp) and Breast Cancer Resistance Protein (BCRP) Substrates In vitro data show that stiripentol is both an inhibitor and inducer of CYP1A2, CYP2B6, and CYP3A4. Because of potential drug-drug interactions, consider dose adjustment of CYP1A2 substrates (e.g., theophylline, caffeine), CYP2B6 substrates (e.g., sertraline, thiotepa), and CYP3A4 substrates (e.g., midazolam, triazolam, quinidine), as clinically appropriate, when administered concomitantly with DIACOMIT.
Because of potential inhibition of enzyme/transporter activity, consider a reduction in dosage of substrates of CYP2C8, CYP2C19 (e.g., diazepam, clopidogrel), P-gp (e.g., carbamazepine), and BCRP (e.g., methotrexate, prazosin, glyburide), if adverse reactions are experienced when administered concomitantly with DIACOMIT. Clobazam Co-administration of DIACOMIT (which inhibits CYP 3A4 and 2C19) with clobazam results in increased plasma concentrations of clobazam (a substrate of CYP3A4) and norclobazam, the active metabolite of clobazam (a substrate of CYP2C19) [see Clinical Pharmacology (12.3) ] .
This may increase the risk of clobazam-related adverse reactions. Consider a reduction in dosage of clobazam if adverse reactions are experienced when co-administered with DIACOMIT [see Warnings and Precautions (5.1) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as DIACOMIT, during pregnancy. Physicians are advised to recommend that pregnant patients taking DIACOMIT enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves or their caregiver.
Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/. Risk Summary There are no adequate data on the developmental risks associated with the use of DIACOMIT in pregnant women. Administration of stiripentol to pregnant animals produced evidence of developmental toxicity, including increased incidences of fetal malformations, increased embryofetal and pup mortality, and decreased embryofetal and pup growth, at maternal doses lower than the recommended clinical dose [see Animal Data ] .
The background risk of major birth defects and miscarriage in Dravet syndrome is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to pregnant mice throughout the period of organogenesis resulted in increased embryofetal mortality and decreased fetal body weights at all doses and an increased incidence of malformations at the high dose, with no evidence of maternal toxicity.
The lowest effect dose for developmental toxicity in mice (50 mg/kg/day) was less than the recommended human dose (RHD) of 50 mg/kg/day on a body surface area (mg/m 2 ) basis. Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to pregnant rabbits throughout organogenesis resulted in increased embryofetal mortality at the mid and high dose and decreased fetal body weights at all doses. The mid and high doses were associated with maternal toxicity.
The lowest effect dose for developmental toxicity in rabbits (50 mg/kg/day) was less than the RHD on a mg/m 2 basis. Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to rats throughout pregnancy and lactation resulted in decreased pup survival, decreased pup body weights at birth and throughout lactation, and deficits in pup reflex development at the high dose, which was also associated with maternal toxicity. The no-effect dose for pre- and postnatal developmental toxicity in rats (200 mg/kg) was less than the RHD on a mg/m 2 basis.
8.2Lactation Risk Summary There are no data on the presence of stiripentol in human milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for DIACOMIT and any potential adverse effects on the breastfed infant from DIACOMIT or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of DIACOMIT have been established for the treatment of seizures associated with Dravet syndrome in patients taking clobazam who are 6 months and older and weighing 7 kg or more. Use of DIACOMIT in this pediatric population is supported by 2 multicenter placebo-controlled, double-blind randomized studies in patients 3 to 18 years of age with additional pharmacokinetic and safety data in patients 6 months to less than 3 years of age [see Clinical Studies ( 14 )]. The safety and effectiveness of DIACOMIT have not been established in pediatric patients below the age of 6 months or who weigh less than 7 kg.
8.5Geriatric Use Clinical studies of DIACOMIT in Dravet syndrome did not include patients ≥65 years of age to determine whether they respond differently from younger patients. The possibility of age-associated hepatic and renal function… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as DIACOMIT, during pregnancy. Physicians are advised to recommend that pregnant patients taking DIACOMIT enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves or their caregiver.
Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/. Risk Summary There are no adequate data on the developmental risks associated with the use of DIACOMIT in pregnant women. Administration of stiripentol to pregnant animals produced evidence of developmental toxicity, including increased incidences of fetal malformations, increased embryofetal and pup mortality, and decreased embryofetal and pup growth, at maternal doses lower than the recommended clinical dose [see Animal Data ] .
The background risk of major birth defects and miscarriage in Dravet syndrome is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to pregnant mice throughout the period of organogenesis resulted in increased embryofetal mortality and decreased fetal body weights at all doses and an increased incidence of malformations at the high dose, with no evidence of maternal toxicity.
The lowest effect dose for developmental toxicity in mice (50 mg/kg/day) was less than the recommended human dose (RHD) of 50 mg/kg/day on a body surface area (mg/m 2 ) basis. Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to pregnant rabbits throughout organogenesis resulted in increased embryofetal mortality at the mid and high dose and decreased fetal body weights at all doses. The mid and high doses were associated with maternal toxicity.
The lowest effect dose for developmental toxicity in rabbits (50 mg/kg/day) was less than the RHD on a mg/m 2 basis. Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to rats throughout pregnancy and lactation resulted in decreased pup survival, decreased pup body weights at birth and throughout lactation, and deficits in pup reflex development at the high dose, which was also associated with maternal toxicity. The no-effect dose for pre- and postnatal developmental toxicity in rats (200 mg/kg) was less than the RHD on a mg/m 2 basis.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of DIACOMIT have been established for the treatment of seizures associated with Dravet syndrome in patients taking clobazam who are 6 months and older and weighing 7 kg or more. Use of DIACOMIT in this pediatric population is supported by 2 multicenter placebo-controlled, double-blind randomized studies in patients 3 to 18 years of age with additional pharmacokinetic and safety data in patients 6 months to less than 3 years of age [see Clinical Studies ( 14 )]. The safety and effectiveness of DIACOMIT have not been established in pediatric patients below the age of 6 months or who weigh less than 7 kg.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of DIACOMIT in Dravet syndrome did not include patients ≥65 years of age to determine whether they respond differently from younger patients. The possibility of age-associated hepatic and renal function abnormalities should be considered when using DIACOMIT in patients ≥65 years of age [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There are no data concerning overdose in humans. In mice treated with high doses of stiripentol (600 to 1800 mg/kg i.p.), decreased motor activity and decreased respiration were observed. Treatment of an overdose should be supportive (symptomatic measures in intensive care units). For management of a suspected drug overdose, contact your regional Poison Control Center.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism by which DIACOMIT exerts its anticonvulsant effect in humans is unknown. Possible mechanisms of action include direct effects mediated through the gamma-aminobutyric acid (GABA) A receptor and indirect effects involving inhibition of cytochrome P450 activity with resulting increase in blood levels of clobazam and its active metabolite.
12.2Pharmacodynamics There are no relevant data on the pharmacodynamic effects of DIACOMIT.
12.3Pharmacokinetics The following pharmacokinetic properties of stiripentol have been found in studies in adult healthy volunteers and adult patients. Systemic exposure of stiripentol increases in a greater than dose proportional manner from 500 mg to 2000 mg. Absorption : The median time to stiripentol peak plasma concentration is 2 to 3 hours.
Distribution : Protein binding of stiripentol is 99%. Elimination : The elimination half-life of stiripentol ranges from 4.5 to 13 hours, increasing with doses of 500 mg, 1000 mg and 2000 mg. Metabolism : On the basis of in vitro studies, the main liver cytochrome P450 (CYP) isoenzymes involved in metabolism are considered to be CYP1A2, CYP2C19, and CYP3A4.
Specific Populations The effect of age (≥ 65 years), race, renal and hepatic impairment on stiripentol pharmacokinetics is unknown [see Use in Specific Populations (8.5, 8.6, 8.7 )]. Sex does not have a clinically significant effect on the pharmacokinetics of DIACOMIT. Pediatric Patients : In a study of children (median age 7.3 years) with Dravet syndrome treated with DIACOMIT, valproate, and clobazam, the apparent clearance and volume of distribution of stiripentol were related to body weight.
Elimination half-life increased from 8.5 hr (for 10 kg) to 23.5 hr (for 60 kg). Drug Interaction Studies In Vitro Studies The metabolic pathway for stiripentol has not been clearly elucidated. Stiripentol is a substrate of several CYP enzymes, including CYP1A2, CYP2C19, and CYP3A4.
Stiripentol inhibits and induces CYP1A2, CYP2B6, and CYP3A4. Stiripentol also inhibits CYP2C8, CYP2C19, and drug transporters, including P-gp and BCRP, at clinically relevant concentrations [see Drug Interactions (7.1) ]. Clinical Studies Antiepileptic drugs: Co-administration of clobazam with stiripentol increased concentrations of clobazam by approximately 2-fold and norclobazam (clobazam active metabolite) by 5-fold [see Drug Interactions (7.1) ].
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism by which DIACOMIT exerts its anticonvulsant effect in humans is unknown. Possible mechanisms of action include direct effects mediated through the gamma-aminobutyric acid (GABA) A receptor and indirect effects involving inhibition of cytochrome P450 activity with resulting increase in blood levels of clobazam and its active metabolite.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied DIACOMIT Capsules 250 mg: size 2, pink, and imprinted with “Diacomit” and “250mg” are supplied as follows: Bottles of 60 NDC 68418-7939-6 500 mg: size 0, white, and imprinted with “Diacomit” and “500mg” are supplied as follows: Bottles of 60 NDC 68418-7940-6 For Oral Suspension 250 mg: pale pink fruit flavored powder packaged in packets are supplied as follows: Cartons of 60 NDC 68418-7941-6 500 mg: pale pink fruit flavored powder packaged in packets are supplied as follows: Cartons of 60 NDC 68418-7942-6
16.2Storage and Handling Store in a dry place at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store in original package to protect from light.
📋 Description ▾
11 DESCRIPTION Table 4. Description Proprietary Name DIACOMIT Established Name Stiripentol Route of Administration Oral Chemical Name 4,4-dimethyl-1-[3,4-(methylendioxyphenyl)-1-pentene-3-ol Structural Formula Stiripentol is a white to pale yellow crystalline powder with a bitter taste; it is practically insoluble in water (at 25°C), sparingly soluble in chloroform, and soluble in acetone, ethanol, ether, acetonitrile, and dichloromethane. The melting point is approximately 75°C.
The pKa is 14.2, and measurement of the partition coefficient (water-octanol) provides a Log P value of 2.94. The molecular formula is C 14 H 18 O 3 and the molecular weight is 234.3. Capsules DIACOMIT capsules contain 250 mg (size 2: pink) or 500 mg (size 0: white) of stiripentol.
Capsules also contain the following inactive ingredients: erythrosine (250 mg capsule only), gelatin, indigotine (250 mg capsule only), magnesium stearate, povidone, sodium starch glycolate, titanium dioxide. For Oral Suspension DIACOMIT for oral suspension packets contain 250 mg or 500 mg of stiripentol. DIACOMIT packets also contain the following inactive ingredients: aspartame, carmellose sodium, erythrosine, glucose, hydroxyethylcellulose, povidone, sodium starch glycolate, sorbitol, titanium dioxide, fruit flavor (acacia, Bergamot oil, hypromellose, maltodextrin, sorbitol, and vanillin).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide and Instructions for Use ). DIACOMIT Oral Capsule Administration Inform patients or caregivers that DIACOMIT capsules must be swallowed whole with a glass of water during a meal. Capsules should not be broken or opened.
DIACOMIT For Oral Suspension Administration DIACOMIT should be mixed in a glass of water and should be taken immediately after mixing during a meal [see Instructions for Use ] . Somnolence Advise patient or caregivers that somnolence may occur, and may require a decrease in the dose of clobazam [see Warnings and Precautions (5.1) ] . Also, advise the patients and their caregivers to avoid alcohol consumption during DIACOMIT treatment [see Drug Interactions (7.3) ] .
If applicable, caution patients about hazardous machinery, including automobiles, until they know how DIACOMIT affects them. Decreased Appetite and Decreased Weight Advise patients or caregivers that decreased appetite is frequent and nausea and vomiting can also occur during DIACOMIT treatment, which can cause loss of weight [see Warnings and Precautions (5.2) ] . Withdrawal Symptoms Advise patients or caregivers that abrupt withdrawal of DIACOMIT may increase their risk of seizures or status epilepticus [see Dosage and Administration (2.5) and Warnings and Precautions (5.4) ] .
Instruct patients or caregivers to not discontinue use of DIACOMIT without consulting with their healthcare provider. Neutropenia and Thrombocytopenia Advise patients or caregivers of the risk of neutropenia and thrombocytopenia and the importance of hematologic testing, which should be obtained prior to starting treatment with DIACOMIT and then every 6 months [see Warnings and Precautions (5.3) ]. Suicidal Thinking and Behavior Counsel patients, their caregivers, and their families that AEDs, including DIACOMIT, may increase the risk of suicidal thoughts and behavior and advise them of the need to be alert for the emergence of worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thought of self-harm.
Patients or caregivers should report behaviors of concern immediately to healthcare providers [see Warnings and Precautions (5.5) ]. Use in Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during DIACOMIT therapy. Encourage patients to enroll in the NAAED Pregnancy registry if they become pregnant.
This registry is collecting information about the safety of AEDs during pregnancy [see Use in Specific Populations (8.1) ] . Use in Nursing Instruct patients to notify their physician if they are breast feeding or intend to breast feed during therapy [see Use in Specific Populations (8.2) ] . DIACOMIT Capsules and DIACOMIT for Oral Suspension manufactured by: BIOCODEX 1, avenue Blaise Pascal 60000 BEAUVAIS France
💬 Medication Guide ▾
MEDICATION GUIDE Medication Guide has been approved by the U.S. Food and Drug Administration Issued: 07/2022 MEDICATION GUIDE DIACOMIT (die-uh-KA-mit) (stiripentol) capsules, for oral use for oral suspension Read this Medication Guide before you start taking DIACOMIT and each time you get a refill. There may be new information.
This information does not take the place of talking to your healthcare provider about your medical condition or treatment. What is the most important information I should know about DIACOMIT? DIACOMIT can cause serious side effects, including: Sleepiness and drowsiness.
Sleepiness and drowsiness are serious and common side effects. DIACOMIT can make you sleepy or dizzy, and slow your thinking. Your healthcare provider may decrease your dose of clobazam or other seizure medicines.
Do not drive, operate heavy machinery, or do other dangerous activities until you know how DIACOMIT affects you. Do not drink alcohol or take other medicines that may make you sleepy or dizzy while taking DIACOMIT until you talk to your healthcare provider. DIACOMIT, when taken with alcohol or medicines that cause sleepiness or dizziness, may make your sleepiness or dizziness worse.
Loss of appetite and weight loss. Loss of appetite and weight loss are serious and common side effects. DIACOMIT can cause frequent nausea and loss of appetite that can cause weight loss.
Your weight should be checked frequently during DIACOMIT treatment. Children who take DIACOMIT should have their weight and growth checked often. Low white blood cell counts (neutropenia) and low platelet counts (thrombocytopenia).
Low white blood cell counts may occur during treatment with DIACOMIT and may cause serious infections. Low platelet counts may cause serious bleeding problems. Your healthcare provider should check your white blood cell count and platelet count before and during treatment.
Do not stop taking DIACOMIT without first talking to your healthcare provider. Stopping a seizure medicine such as DIACOMIT should be done slowly to avoid having seizures more often, or seizures that do not stop (status epilepticus). Like other antiepileptic drugs, DIACOMIT may cause suicidal thoughts or actions in a very small number of people (about 1 in 500).
Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Suicidal thoughts or actions can be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes. Call your healthcare provider right away if you have any of the above side effects while taking DIACOMIT.
What is DIACOMIT? DIACOMIT is a prescription medicine used along with clobazam to treat seizures in people with Dravet syndrome who are 6 months of age and older and weighing 15 pounds (7 kg) or more. DIACOMIT has not been shown to be able to treat seizures associated with Dravet syndrome without the use of clobazam.
It is not known if DIACOMIT is safe and effective in children under 6 months of age or who weigh less than 15 pounds (7 kg). Before you take DIACOMIT, tell your healthcare provider about all of your medical conditions, including if you: have liver or kidney problems. have phenylkentonuria (PKU). DIACOMIT for or… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The following pharmacokinetic properties of stiripentol have been found in studies in adult healthy volunteers and adult patients. Systemic exposure of stiripentol increases in a greater than dose proportional manner from 500 mg to 2000 mg. Absorption : The median time to stiripentol peak plasma concentration is 2 to 3 hours.
Distribution : Protein binding of stiripentol is 99%. Elimination : The elimination half-life of stiripentol ranges from 4.5 to 13 hours, increasing with doses of 500 mg, 1000 mg and 2000 mg. Metabolism : On the basis of in vitro studies, the main liver cytochrome P450 (CYP) isoenzymes involved in metabolism are considered to be CYP1A2, CYP2C19, and CYP3A4.
Specific Populations The effect of age (≥ 65 years), race, renal and hepatic impairment on stiripentol pharmacokinetics is unknown [see Use in Specific Populations (8.5, 8.6, 8.7 )]. Sex does not have a clinically significant effect on the pharmacokinetics of DIACOMIT. Pediatric Patients : In a study of children (median age 7.3 years) with Dravet syndrome treated with DIACOMIT, valproate, and clobazam, the apparent clearance and volume of distribution of stiripentol were related to body weight.
Elimination half-life increased from 8.5 hr (for 10 kg) to 23.5 hr (for 60 kg). Drug Interaction Studies In Vitro Studies The metabolic pathway for stiripentol has not been clearly elucidated. Stiripentol is a substrate of several CYP enzymes, including CYP1A2, CYP2C19, and CYP3A4.
Stiripentol inhibits and induces CYP1A2, CYP2B6, and CYP3A4. Stiripentol also inhibits CYP2C8, CYP2C19, and drug transporters, including P-gp and BCRP, at clinically relevant concentrations [see Drug Interactions (7.1) ]. Clinical Studies Antiepileptic drugs: Co-administration of clobazam with stiripentol increased concentrations of clobazam by approximately 2-fold and norclobazam (clobazam active metabolite) by 5-fold [see Drug Interactions (7.1) ].
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics There are no relevant data on the pharmacodynamic effects of DIACOMIT.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The effectiveness of DIACOMIT for the treatment of seizures associated with Dravet syndrome was established in 2 multicenter placebo-controlled double-blind randomized studies (Sticlo France and Sticlo Italy), conducted according to similar protocols. To be enrolled in either study, patients were required to be 3 years to less than 18 years of age, to have Dravet syndrome (ILAE classification of epilepsy, 1989), and to be inadequately controlled on clobazam and valproate, with at least 4 generalized clonic or tonic-clonic seizures per month despite optimized therapy.
Eligible patients were enrolled in a 1-month baseline period during which they continued to receive their optimized antiepileptic treatment. Following this 1-month baseline, patients were randomly allocated to receive either DIACOMIT (fixed dose of 50 mg/kg/day in divided doses with no dose titration) or placebo, added to their treatment with clobazam and valproate. Duration of double-blind treatment was 2 months.
The frequency of generalized clonic or tonic-clonic seizures during the study was recorded by patients and/or their caregivers, using a diary. Although patients with Dravet syndrome have several different types of seizures, only generalized clonic or tonic-clonic seizures were recorded, as other seizure types can be difficult to recognize by patients and/or their caregivers as seizures. The primary efficacy endpoint for both studies was the responder rate.
A responder was defined as a patient who experienced a greater than 50% decrease in the frequency (per 30 days) of generalized clonic or tonic-clonic seizures during the double-blind treatment period compared to the 4-week baseline period (i.e., placebo run-in). The mean change from baseline in frequency of generalized clonic or tonic clonic seizures was also evaluated. In Sticlo France (n=41), 21 patients were randomized to DIACOMIT, and 20 patients to placebo.
In Sticlo Italy (n=23), 12 patients were randomized to DIACOMIT, and 11 patients to placebo. In both studies, the demographic and baseline clinical characteristics were similar between the treatment groups. Table5 summarizes the results of the primary endpoint for DIACOMIT in each study.
Table 5. Efficacy Results in the Intent-to-Treat Population in Sticlo France and Sticlo Italy a Responder is defined as a patient with a greater than 50% decrease in frequency of generalized tonic-clonic or clonic seizures b Fisher Exact Test c Frequency of generalized tonic-clonic or clonic seizures during month 2 d Wilcoxon Test with two-sided t-approximation e Nominal p value, as Sticlo Italy was stopped early CI=confidence interval; SD=standard deviation. Sticlo France N=41 Sticlo Italy N=23 DIACOMIT N=21 Placebo N=20 DIACOMIT N=12 Placebo N=11 Responder Analysis a No of responders/total (Responder Rate) [95% CI] 15/21 (71%) [52% – 91%] 1/20 (5%) [0.0% – 15%] 8/12 (67%) [40% – 93%] 1/11 (9.1%) [0.0%– 26%] p-value b <0.0001 0.0094 e Percentage Change from Baseline in Seizure Frequency c n Mean ± SD Median Min – Max 20 -69% ± 42% -91% -100% – 28% 16 7.6% ± 38% 7.4% -75% – 65% 11 -74% ± 27% -81% -100% – -33% 9 -13% ± 62% -27% -87% – 140% p-value d 0.0002 0.0056 e In both studies, the responder rate (primary efficacy endpoint) was significantly greater for DIACOMIT than for placebo.
DIACOMIT was also superior to placebo for the reduction in mean frequency of generalized clonic or tonic-clonic seizures. In Sticlo France and Sticlo Italy, respectively 43% and 25% of patients reported no generalized clonic or tonic-clonic seizure for the duration of the study. Figure 1 displays the percentage of patients by category of percent reduction in tonic-clonic and clonic seizure frequency during month 2 of the treatment period compared to baseline (per 30 days) in Sticlo France and Sticlo Italy (pooled).
Figure 1.: Proportion of Patients by Category of Seizure Response for DIACOMIT and Placebo in Sticlo France and Sticlo Italy Pooled, Baseline to 2nd M… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In mice, oral administration of stiripentol (0, 60, 200, or 600 mg/kg/day) for 78 weeks increased the incidences of liver tumors (hepatocellular adenoma and carcinoma) at the mid and high dose. The dose not associated with an increase in liver tumors (60 mg/kg/day) is less than the recommended human dose (RHD) of 50 mg/kg/day, based on body surface area (mg/m 2 ). In rats, oral administration of stiripentol at doses of up to 800 mg/kg/day (approximately 2.5 times the RHD on a mg/m 2 basis) for 102 weeks did not result in an increase in tumors.
Mutagenesis Stiripentol was negative for genotoxicity in in vitro (Ames, HPRT gene mutation in V79 Chinese hamster cells, and chromosomal aberration in human lymphocytes) and in vivo (mouse bone marrow micronucleus) assays. Stiripentol was clastogenic in CHO cells in vitro, but only at cytotoxic concentrations. Impairment of Fertility Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to male and female rats prior to and throughout mating and continuing in females throughout organogenesis produced no adverse effects on fertility.
The highest dose tested is approximately 2.5 times the RHD on mg/m 2 basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In mice, oral administration of stiripentol (0, 60, 200, or 600 mg/kg/day) for 78 weeks increased the incidences of liver tumors (hepatocellular adenoma and carcinoma) at the mid and high dose. The dose not associated with an increase in liver tumors (60 mg/kg/day) is less than the recommended human dose (RHD) of 50 mg/kg/day, based on body surface area (mg/m 2 ). In rats, oral administration of stiripentol at doses of up to 800 mg/kg/day (approximately 2.5 times the RHD on a mg/m 2 basis) for 102 weeks did not result in an increase in tumors.
Mutagenesis Stiripentol was negative for genotoxicity in in vitro (Ames, HPRT gene mutation in V79 Chinese hamster cells, and chromosomal aberration in human lymphocytes) and in vivo (mouse bone marrow micronucleus) assays. Stiripentol was clastogenic in CHO cells in vitro, but only at cytotoxic concentrations. Impairment of Fertility Oral administration of stiripentol (0, 50, 200, or 800 mg/kg/day) to male and female rats prior to and throughout mating and continuing in females throughout organogenesis produced no adverse effects on fertility.
The highest dose tested is approximately 2.5 times the RHD on mg/m 2 basis.
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE DIACOMIT (die-uh-KA-mit) (stiripentol) for oral suspension Be sure that you read, understand, and follow the Instructions for Use before preparing your child’s first dose of DIACOMIT for oral suspension and each time you get a refill. There may be new information. This information does not take the place of talking to your child’s healthcare provider about their medical condition or treatment.
Ask your child’s healthcare provider or pharmacist if you have questions about how to mix or give a dose of DIACOMIT for oral suspension. Important information: Your child’s healthcare provider will tell you the dose of DIACOMIT and how many packets are needed for your child’s dose. Each packet of DIACOMIT for oral suspension contains 250 mg or 500 mg of DIACOMIT as a powder.
Be sure to use the right strength to prepare your child’s dose. When you receive DIACOMIT for oral suspension prescription at the pharmacy, check to make sure that you were given the right strength of DIACOMIT for oral suspension, the carton is not damaged, and the packets are not opened. Make sure you have enough packets of DIACOMIT for oral suspension to give a full dose.
Call your healthcare provider if you need more DIACOMIT for oral suspension. Do not run out of your child’s medicine. Check that the expiration date on the carton (located on the bottom of the carton) and packet (located at the bottom right of the back side of the packet) has not passed.
Do not use if the expiration date has passed. Talk with your child’s healthcare provider to help decide the best schedule for giving your child DIACOMIT for oral suspension. DIACOMIT for oral suspension must be mixed with water and your child must eat food right after taking DIACOMIT for oral suspension.
Be sure to give the entire prepared dose of DIACOMIT for oral suspension to your child. For more information about DIACOMIT for oral suspension, see the “ Medication Guide .” Instructions for mixing DIACOMIT for oral suspension: Before you prepare a dose of DIACOMIT for oral suspension, check the prescription label on the carton for the number of packets you need to prepare a dose. Take the prescribed number of packets of DIACOMIT for oral suspension needed for the prescribed dose out of the carton.
Wash and dry your hands before and after preparing DIACOMIT for oral suspension. When preparing DIACOMIT for oral suspension, choose a clean, flat work surface, and place the supplies you will need on the work surface. Gather the following supplies: 1-spoon 1-measuring cup 1-small drinking cup water the correct number of DIACOMIT for oral suspension packets needed for the prescribed dose 1-clean pair of scissors Step 1.
Fill measuring cup with 100 mL of water. Step 2. Pour 100 mL of water into the small drinking cup.
Step 3. Tap the packet of DIACOMIT for oral suspension to settle the medicine to the bottom of the packet. Step 4.
Using a clean pair of scissors, cut off the top of the packet and make sure the packet is fully open. Step 5. Empty the packet into the small drinking cup.
Look inside the packet to make sure there is no medicine left inside. If there is medicine left inside, hold the open end of the packet over your small drinking cup and tap the packet again to get all of the medicine out. To make sure a full dose of DIACOMIT for oral suspension is given, it is important not to spill any medicine and that there is no medicine left in the packet.
Repeat Steps 3 through 5 for each packet of DIACOMIT for oral suspension needed for the total prescribed dose. Step 6. Hold the small drinking cup with one hand.
With your other hand, use the spoon to gently mix the medicine and the water until clear. Steps 7 and 8 must be completed right after mixing the medicine. Step 7.
Have your child drink all of the mixture in the small drinking cup. Step 8. To make sure there is no mixture left in the small drinking cup, add a small amount (25 mL) of water to the small drinking cup: Stir with the spoon.
R… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL NDC 68418- 7939 -6 DIACOMIT ® 250 mg (stiripentol) Capsule Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 capsules Rx Only BIOCODEX Active ingredient: Each capsule contains 250 mg stiripentol. Directions for use: Swallow whole with a glass of water during a meal. DO NOT open, break or chew capsules.
See full prescribing information for dosage and administration. Warnings: Please refer to full prescribing information for further information. Store at 20 to 25ºC (68 to 77ºF) in a dry place.
Store in original package to protect from light. Keep out of the reach and sight of children. *All trademark rights used under license Manufactured by: Biocodex, Gentilly, France Distributed by: Biocodex, Inc. Bedminster, NJ 07921 USA NDC 68418- 7939 -6 DIACOMIT ® 250 mg (stiripentol) Capsule Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 capsules BIOCODEX Rx Only NDC 68418- 7939 -6 DIACOMIT ® 250 mg (stiripentol) Capsule Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 capsules BIOCODEX Rx Only Peel here Active ingredient: Each capsule contains 250 mg stiripentol.
Directions for use: Swallow whole with a glass of water during a meal. DO NOT open, break or chew capsules. See full prescribing information for dosage and administration.
Warnings: Please refer to full prescribing information for further information. Store at 20 to 25ºC (68 to 77ºF) in a dry place. Store in original package to protect from light.
Keep out of the reach and sight of children. Manufactured by: Biocodex, Gentilly, France Distributed by: Biocodex, Inc. Bedminster, NJ 07921 USA *All trademark rights used under license NDC 68418- 7940 -6 DIACOMIT ® 500 mg (stiripentol) Capsule Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 capsules Rx Only BIOCODEX Active ingredient: Each capsule contains 500 mg stiripentol.
Directions for use: Swallow whole with a glass of water during a meal. DO NOT open, break or chew capsules. See full prescribing information for dosage and administration.
Warnings: Please refer to full prescribing information for further information. Store at 20 to 25ºC (68 to 77ºF) in a dry place. Store in original package to protect from light.
Keep out of the reach and sight of children. *All trademark rights used under license Manufactured by: Biocodex, Gentilly, France Distributed by: Biocodex, Inc. Bedminster, NJ 07921 USA NDC 68418- 7940 -6 DIACOMIT ® 500 mg (stiripentol) Capsule Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 capsules BIOCODEX Rx Only NDC 68418- 7940 -6 DIACOMIT ® 500 mg (stiripentol) Capsule Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 capsules BIOCODEX Rx Only Peel here Active ingredient: Each capsule contains 500 mg stiripentol.
Directions for use: Swallow whole with a glass of water during a meal. DO NOT open, break or chew capsules. See full prescribing information for dosage and administration.
Warnings: Please refer to full prescribing information for further information. Store at 20 to 25ºC (68 to 77ºF) in a dry place. Store in original package to protect from light.
Keep out of the reach and sight of children. Manufactured by: Biocodex, Gentilly, France Distributed by: Biocodex, Inc. Bedminster, NJ 07921 USA *All trademark rights used under license NDC 68418- 7941 -6 DIACOMIT ® 250 mg/packet (stiripentol) For oral suspension Attention Pharmacist: Dispense the enclosed Medication Guide to each patient 60 Packets Rx Only BIOCODEX Active ingredient: Each packet contains 250 mg stiripentol.
PHENYLKETONURICS: CONTAINS PHENYLALANINE - KEEP THIS AND ALL DRUGS OUT OF REACH OF CHILDREN. Preparation: The powder should be mixed in a glass of water and should be taken immediately after mixing during a meal. See full prescribing information for dosage and administration.
Warnings: Please refer to full prescribing information for further i… [Excerpted — this section continues on DailyMed.]
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |