
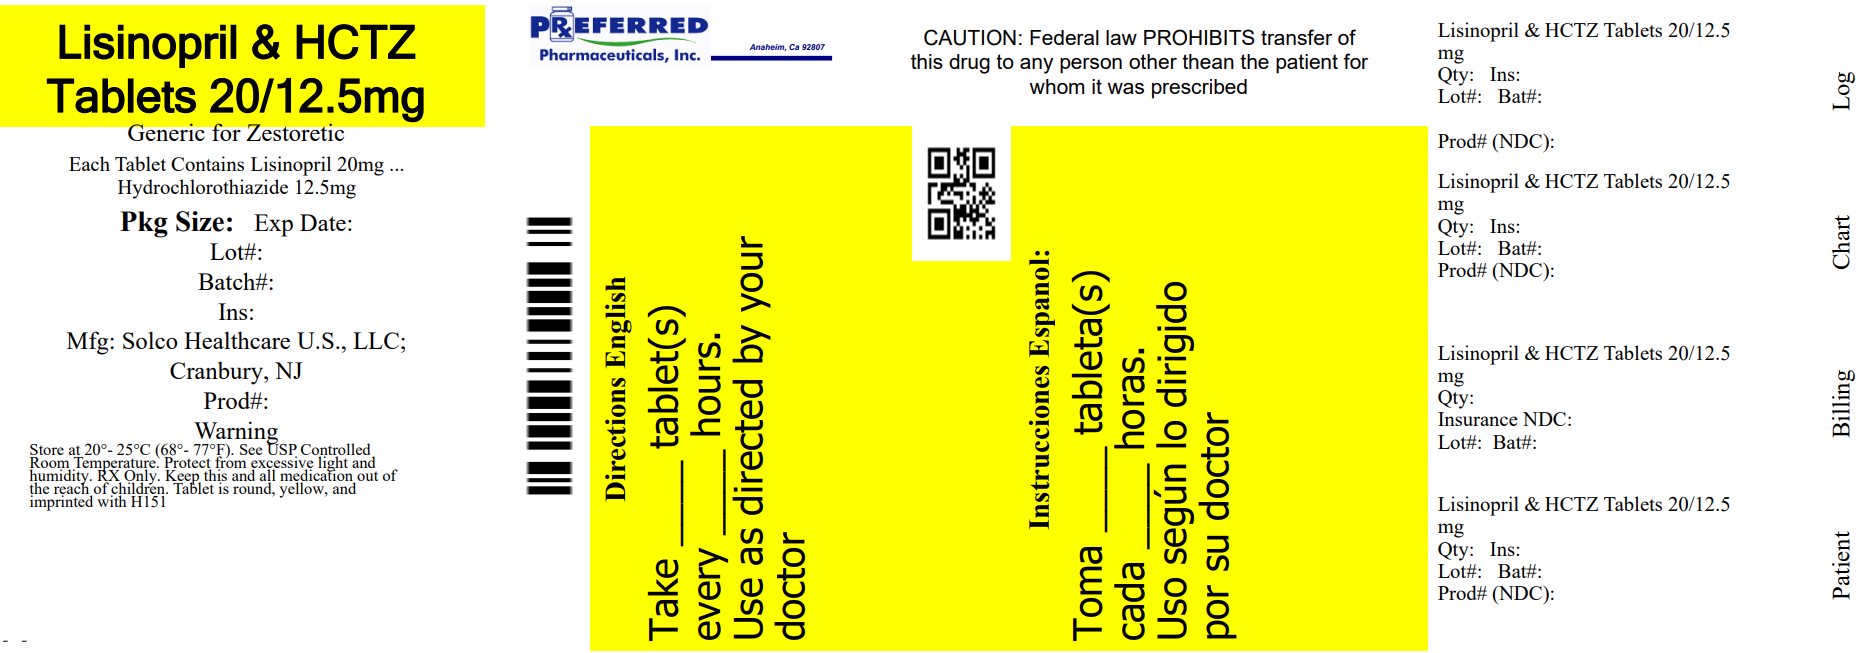
Lisinopril and Hydrochlorothiazide 20 mg; 12.5 mg Tablet, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of lisinopril and hydrochlorothiazide is used to treat high blood pressure. Lisinopril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It works by decreasing certain chemicals that tighten the blood vessels, so blood flows more smoothly. Hydrochlorothiazide is in a class of medications called diuretics ('water pills'). It works by causing the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood vessels, kidneys an...
Read the full MedlinePlus article ↗- Great question. Lisinopril is an ACE inhibitor — it relaxes your blood vessels by blocking a chemical in your body that would otherwise make them tighten up. Hydrochlorothiazide is...
- Why am I taking two medicines in one pill — what does each one do?
- You can take it either way — with or without food. Food does not affect how your body absorbs lisinopril, so just pick a time of day that's easy for you to remember and stick with...
- Can I take this pill with food, or does it have to be on an empty stomach?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII O7TSZ97GEP
A mineral compound that serves as a filler and binding agent in tablets and capsules. It adds bulk to the medicine and helps hold ingredients together during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1025 | $6.15 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lisinopril and hydrochlorothiazide 20 mg/1; 12.5 mg 00591-0861-01 | Actavis | 100 tablets | $0.037 | — | Availability likely | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 43547-0421-10 | Solco | 100 tablets | $0.037 | AB | Availability likely | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 68180-0519-01 | Lupin | 100 tablets | $0.037 | AB | Availability likely | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 68645-0557-54 | Legacy | 30 tablets | $0.037 | AB | Availability likely | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 76282-0447-01 | Exelan | 100 tablets | $0.037 | AB | Availability likely | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 43063-0458-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 50090-6204-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 50090-6752-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| LISINOPRIL and HYDROCHLOROTHIAZIDE 20 mg/1; 12.5 mg 51407-0565-05 | GSMS, | 500 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 51655-0311-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 51655-0414-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Zestoretic 20 mg/1; 12.5 mg 52427-0436-90 | Almatica | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 60760-0519-90 | St. | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and hydrochlorothiazide 20 mg/1; 12.5 mg 63187-0050-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 63629-4470-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 65862-0044-00 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 67046-0433-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 68071-2263-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 68071-3177-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 68071-4435-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mgthis 68788-8253-06 | Preferred | 60 tablets | — | AB | FDA listed | — |
| Lisinopril And Hydrochlorothiazide 12.5 mg/1; 20 mg 68788-9809-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 69097-0969-05 | Cipla | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 70518-0382-00 | REMEDYREPACK | 90 tablets | — | AB | Discontinued | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 70518-3505-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 71205-0022-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 71205-0763-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 71335-0862-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 71335-9730-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 71610-0274-80 | Aphena | 180 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 71610-0374-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 12.5 mg/1; 20 mg 71610-0838-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Lisinopril and Hydrochlorothiazide 20 mg/1; 12.5 mg 71610-0868-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Lisinopril/HCTZ 20 mg/1; 12.5 mg 72189-0651-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68788-8253-01 | 100 TABLET in 1 BOTTLE (68788-8253-1) | 2022-10-01 | Active |
| 68788-8253-03 | 30 TABLET in 1 BOTTLE (68788-8253-3) | 2022-10-01 | Active |
| 68788-8253-06 You're viewing this | 60 TABLET in 1 BOTTLE (68788-8253-6) | 2022-10-01 | Active |
| 68788-8253-09 | 90 TABLET in 1 BOTTLE (68788-8253-9) | 2022-10-01 | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 68788-8253-06?
What is the difference between NDC 68788-8253-06 and NDC 68788-8253-03?
What NDC number is used to bill for this package of Lisinopril and Hydrochlorothiazide 20 mg; 12.5 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY • When pregnancy is detected, discontinue lisinopril and hydrochlorothiazide tablets as soon as possible. • Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. See Warnings, Fetal Toxicity .
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Lisinopril and hydrochlorothiazide tablets are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure lowers the risk of fatal and non-fatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including lisinopril and hydrochlorothiazide.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. These fixed-dose combinations are not indicated for initial therapy (see DOSAGE AND ADMINISTRATION ).
In using lisinopril and hydrochlorothiazide tablets, consideration should be given to the fact that an angiotensin converting enzyme inhibitor, captopril, has caused agranulocytosis, particularly in patients with renal impairment or collagen vascular disease, and that available data are insufficient to show that lisinopril does not have a similar risk. (See WARNINGS .) In considering use of lisinopril and hydrochlorothiazide tablets, it should be noted that Black patients receiving ACE inhibitors have been reported to have a higher incidence of angioedema compared to non-Black.
(See WARNINGS, Head and Neck Angioedema .)
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Lisinopril monotherapy is an effective treatment of hypertension in once-daily doses of 10 mg to 80 mg, while hydrochlorothiazide monotherapy is effective in doses of 12.5 mg to 50 mg per day. In clinical trials of lisinopril/hydrochlorothiazide combination therapy using lisinopril doses of 10 mg to 80 mg and hydrochlorothiazide doses of 6.25 mg to 50 mg, the antihypertensive response rates generally increased with increasing dose of either component. The side effects (see WARNINGS ) of lisinopril are generally rare and apparently independent of dose; those of hydrochlorothiazide are a mixture of dose-dependent phenomena (primarily hypokalemia) and dose-independent phenomena (e.g., pancreatitis), the former much more common than the latter.
Therapy with any combination of lisinopril and hydrochlorothiazide will be associated with both sets of dose-independent side effects, but addition of lisinopril in clinical trials blunted the hypokalemia normally seen with diuretics. To minimize dose-independent side effects, it is usually appropriate to begin combination therapy only after a patient has failed to achieve the desired effect with monotherapy. Dose Titration Guided by Clinical Effect A patient whose blood pressure is not adequately controlled with either lisinopril or hydrochlorothiazide monotherapy may be switched to lisinopril and hydrochlorothiazide tablets 10 mg/12.5 mg or lisinopril and hydrochlorothiazide tablets 20 mg/12.5 mg.
Further increases of either or both components could depend on clinical response. The hydrochlorothiazide dose should generally not be increased until 2-3 weeks have elapsed. Patients whose blood pressures are adequately controlled with 25 mg of daily hydrochlorothiazide, but who experience significant potassium loss with this regimen, may achieve similar or greater blood pressure control with less potassium loss if they are switched to lisinopril and hydrochlorothiazide tablets 10 mg/12.5 mg.
Dosage higher than lisinopril 80 mg and hydrochlorothiazide 50 mg should not be used. Replacement Therapy The combination may be substituted for the titrated individual components. Use in Renal Impairment The usual regimens of therapy with lisinopril and hydrochlorothiazide tablets need not be adjusted as long as the patient's creatinine clearance is greater than 30 mL/min/1.73 m 2 (serum creatinine approximately less than or equal to 3 mg/dL or 265 μmol/L).
In patients with more severe renal impairment, loop diuretics are preferred to thiazides, so lisinopril and hydrochlorothiazide tablets are not recommended (see WARNINGS, Anaphylactoid reactions during membrane exposure ).
⛔ Contraindications ▾
CONTRAINDICATIONS Lisinopril and hydrochlorothiazide tablets are contraindicated in patients who are hypersensitive to any component of this product and in patients with a history of angioedema related to previous treatment with an angiotensin converting enzyme inhibitor and in patients with hereditary or idiopathic angioedema. Because of the hydrochlorothiazide component, this product is contraindicated in patients with anuria or hypersensitivity to other sulfonamide-derived drugs. Lisinopril and hydrochlorothiazide tablets are contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril).
Do not administer lisinopril and hydrochlorothiazide tablets within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor (see WARNINGS ). Do not coadminister aliskiren with lisinopril and hydrochlorothiazide tablets in patients with diabetes.
⚠️ Warnings ▾
WARNINGS General Lisinopril Anaphylactoid and Possibly Related Reactions: Presumably because angiotensin-converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors (including lisinopril and hydrochlorothiazide tablets) may be subject to a variety of adverse reactions, some of them serious. Head and Neck Angioedema: Angioedema of the face, extremities, lips, tongue, glottis and/or larynx has been reported rarely in patients treated with angiotensin converting enzyme inhibitors, including lisinopril.
This may occur at any time during treatment. ACE inhibitors have been associated with a higher rate of angioedema in Black than in non-Black patients. In such cases lisinopril and hydrochlorothiazide tablets should be promptly discontinued and appropriate therapy and monitoring should be provided until complete and sustained resolution of signs and symptoms has occurred.
Even in those instances where swelling of only the tongue is involved, without respiratory distress, patients may require prolonged observation since treatment with antihistamines and corticosteroids may not be sufficient. Very rarely, fatalities have been reported due to angioedema associated with laryngeal edema or tongue edema. Patients with involvement of the tongue, glottis or larynx are likely to experience airway obstruction, especially those with a history of airway surgery.
Where there is involvement of the tongue, glottis or larynx, likely to cause airway obstruction, subcutaneous epinephrine solution 1:1,000 (0.3 mL to 0.5 mL) and/or measures necessary to ensure a patent airway, should be promptly provided. (See ADVERSE REACTIONS . ) Patients with a history of angioedema unrelated to ACE-inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor (see also INDICATIONS AND USAGE and CONTRAINDICATIONS ). Patients receiving coadministration of ACE inhibitor and mTOR (mammalian target of rapamycin) inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema (see PRECAUTIONS ).
Intestinal Angioedema : Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor.
Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain. Anaphylactoid reactions during desensitization: Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions. In the same patients, these reactions were avoided when ACE inhibitors were temporarily withheld, but they reappeared upon inadvertent rechallenge.
Anaphylactoid reactions during membrane exposure: Sudden and potentially life-threatening anaphylactoid reactions have been reported in some patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor. In such patients, dialysis must be stopped immediately, and aggressive therapy for anaphylactoid reactions must be initiated. Symptoms have not been relieved by antihistamines in these situations.
In these patients, consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent. Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption. Hypotension and Related Effects Excessive hypotension was rarely seen in uncomplicated hypertensive patients but is a possible consequence of lisinopril use in salt/volume-depleted persons, su…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Lisinopril and hydrochlorothiazide tablets have been evaluated for safety in 930 patients, including 100 patients treated for 50 weeks or more. In clinical trials with lisinopril and hydrochlorothiazide tablets no adverse experiences peculiar to this combination drug have been observed. Adverse experiences that have occurred have been limited to those that have been previously reported with lisinopril or hydrochlorothiazide.
The most frequent clinical adverse experiences in controlled trials (including open label extensions) with any combination of lisinopril and hydrochlorothiazide tablets were: dizziness (7.5%), headache (5.2%), cough (3.9%), fatigue (3.7%) and orthostatic effects (3.2%) all of which were more common than in placebo-treated patients. Generally, adverse experiences were mild and transient in nature; but see WARNINGS regarding angioedema and excessive hypotension or syncope. Discontinuation of therapy due to adverse effects was required in 4.4% of patients, principally because of dizziness, cough, fatigue and muscle cramps.
Adverse experiences occurring in greater than one percent of patients treated with lisinopril plus hydrochlorothiazide in controlled clinical trials are shown below. Percent of Patients in Controlled Studies Clinical adverse experiences occurring in 0.3% to 1.0% of patients in controlled trials included: Lisinopril-Hydrochlorothiazide (n=930) Incidence (discontinuation) Placebo (n=207) Incidence Dizziness 7.5 (0.8)
1.9Headache 5.2 (0.3)
1.9Cough 3.9 (0.6)
1.0Fatigue 3.7 (0.4)
1.0Orthostatic Effects 3.2 (0.1)
1.0Diarrhea 2.5 (0.2)
2.4Nausea 2.2 (0.1)
2.4Upper Respiratory Infection 2.2 (0.0)
0.0Muscle Cramps 2.0 (0.4)
0.5Asthenia 1.8 (0.2)
1.0Paresthesia 1.5 (0.1)
0.0Hypotension 1.4 (0.3)
0.5Vomiting 1.4 (0.1)
0.5Dyspepsia 1.3 (0.0)
0.0Rash 1.2 (0.1)
0.5Impotence 1.2 (0.3)
0.0Body as a Whole: Chest pain, abdominal pain, syncope, chest discomfort, fever, trauma, virus infection. Cardiovascular: Palpitation, orthostatic hypotension. Digestive: Gastrointestinal cramps, dry mouth, constipation, heartburn.
Musculoskeletal: Back pain, shoulder pain, knee pain, back strain, myalgia, foot pain. Nervous/Psychiatric: Decreased libido, vertigo, depression, somnolence. Respiratory: Common cold, nasal congestion, influenza, bronchitis, pharyngeal pain, dyspnea, pulmonary congestion, chronic sinusitis, allergic rhinitis, pharyngeal discomfort.
Skin: Flushing, pruritus, skin inflammation, diaphoresis. Special Senses: Blurred vision, tinnitus, otalgia. Urogenital: Urinary tract infection.
Angioedema: Angioedema has been reported in patients receiving PRINZIDE, with an incidence higher in Black than in non-Black patients. Angioedema associated with laryngeal edema may be fatal. If angioedema of the face, extremities, lips, tongue, glottis and/or larynx occurs, treatment with PRINZIDE should be discontinued and appropriate therapy instituted immediately.
In rare cases, intestinal angioedema has been reported with angiotensin converting enzyme inhibitors including lisinopril. (See WARNINGS .) Hypotension: In clinical trials, adverse effects relating to hypotension occurred as follows: hypotension (1.4 percent), orthostatic hypotension (0.5 percent), other orthostatic effects (3.2 percent). In addition syncope occurred in 0.8 percent of patients.
(See WARNINGS .) Cough: See PRECAUTIONS, Cough . Clinical Laboratory Test Findings Serum Electrolytes: See PRECAUTIONS . Creatinine, Blood Urea Nitrogen: Minor reversible increases in blood urea nitrogen and serum creatinine were observed in patients with essential hypertension treated with lisinopril and hydrochlorothiazide tablets.
More marked increases have also been reported and were more likely to occur in patients with renal artery stenosis (See PRECAUTIONS ). Serum Uric Acid, Glucose, Magnesium, Cholesterol, Triglycerides and Calcium: See PRECAUTIONS . Hemoglobin and Hematocrit: Small decreases in hemoglobin and hematocrit (mean…
🔄 Drug Interactions ▾
Drug Interactions Lisinopril Hypotension - Patients on Diuretic Therapy: Patients on diuretics, and especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with lisinopril. The possibility of hypotensive effects with lisinopril can be minimized by either discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with lisinopril. If it is necessary to continue the diuretic, initiate therapy with lisinopril at a dose of 5 mg daily, and provide close medical supervision after the initial dose for at least two hours and until blood pressure has stabilized for at least an additional hour.
(See WARNINGS and DOSAGE AND ADMINISTRATION .) When a diuretic is added to the therapy of a patient receiving lisinopril, an additional antihypertensive effect is usually observed. (See DOSAGE AND ADMINISTRATION .) Non-steroidal Anti-inflammatory Agents Including Selective Cyclooxygenase-2 (COX-2) Inhibitors: In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including lisinopril, may result in deterioration of renal function, including possible acute renal failure.
These effects are usually reversible. Monitor renal function periodically in patients receiving lisinopril and NSAID therapy. The antihypertensive effect of ACE inhibitors, including lisinopril, may be attenuated by NSAIDs.
Dual Blockade of the Renin-Angiotensin System (RAS): Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or direct renin inhibitors (such as aliskiren) is associated with increased risk of hypotension, syncope, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The VA NEPHRON trial enrolled 1448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratio, and decreased estimated glomerular filtration rate (GFR 30 to 89.9 ml/min), randomized them to lisinopril or placebo on a background of losartan therapy and followed them for a median of 2.2 years.
Patients receiving the combination of losartan and lisinopril did not obtain any additional benefit compared to monotherapy for the combined endpoint of decline in GFR, end state renal disease, or death, but experienced an increased incidence of hyperkalemia and acute kidney injury compared with the monotherapy group. In general, avoid combined use of RAS inhibitors. Monitor blood pressure, renal function, and electrolytes in patients on lisinopril and hydrochlorothiazide tablets and other agents that affect the RAS.
Do not coadminister aliskiren with lisinopril and hydrochlorothiazide tablets in patients with diabetes. Avoid use of aliskiren with PRINZIDE in patients with renal impairment (GFR <60 ml/min). Other Agents: Lisinopril has been used concomitantly with nitrates and/or digoxin without evidence of clinically significant adverse interactions.
No meaningful clinically important pharmacokinetic interactions occurred when lisinopril was used concomitantly with propranolol, digoxin, or hydrochlorothiazide. The presence of food in the stomach does not alter the bioavailability of lisinopril. Agents Increasing Serum Potassium: Lisinopril attenuates potassium loss caused by thiazide-type diuretics.
Use of lisinopril with potassium-sparing diuretics (e.g., spironolactone, eplerenone, triamterene, or amiloride), potassium supplements, or potassium-containing salt substitutes may lead to significant increases in serum potassium. Therefore, if concomitant use of these agents is indicated, because of demonstrated hypokalemia, they should be used with caution and with frequent monitoring of serum potassium. Lithium: Lithium toxicity has been reported in patients receiving lithium concomitantly with drugs which cause elimination of sodium, includ…
🧒 Pediatric Use ▾
Pediatric Use Neonates with a history of in utero exposure to lisinopril and hydrochlorothiazide tablets: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Lisinopril, which crosses the placenta, has been removed from neonatal circulation by peritoneal dialysis with some clinical benefit, and theoretically may be removed by exchange transfusion, although there is no experience with the latter procedure.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of lisinopril and hydrochlorothiazide tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
In a multiple-dose pharmacokinetic study in elderly versus young hypertensive patients using the lisinopril/hydrochlorothiazide combination, area under the plasma concentration time curve (AUC) increased approximately 120% for lisinopril and approximately 80% for hydrochlorothiazide in older patients. This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection.
Evaluation of the hypertensive patient should always include assessment of renal function. (See DOSAGE AND ADMINISTRATION.)
🆘 Overdosage ▾
OVERDOSAGE No specific information is available on the treatment of overdosage with lisinopril and hydrochlorothiazide tablets. Treatment is symptomatic and supportive. Therapy with lisinopril and hydrochlorothiazide tablets should be discontinued and the patient observed closely.
Suggested measures include induction of emesis and/or gastric lavage, and correction of dehydration, electrolyte imbalance and hypotension by established procedures. Lisinopril Following a single oral dose of 20 g/kg, no lethality occurred in rats and death occurred in one of 20 mice receiving the same dose. The most likely manifestation of overdosage would be hypotension, for which the usual treatment would be intravenous infusion of normal saline solution.
Lisinopril can be removed by hemodialysis. (See WARNINGS, Anaphylactoid reaction during membrane exposure .) Hydrochlorothiazide Oral administration of a single oral dose of 10 g/kg to mice and rats was not lethal. The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis.
If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Lisinopril-Hydrochlorothiazide As a result of its diuretic effects, hydrochlorothiazide increases plasma renin activity, increases aldosterone secretion, and decreases serum potassium. Administration of lisinopril blocks the renin-angiotensin-aldosterone axis and tends to reverse the potassium loss associated with the diuretic. In clinical studies, the extent of blood pressure reduction seen with the combination of lisinopril and hydrochlorothiazide was approximately additive.
The lisinopril and hydrochlorothiazide tablets 10 mg/12.5 mg combination worked equally well in Black and Caucasian patients. The lisinopril and hydrochlorothiazide tablets 20 mg/12.5 mg and lisinopril and hydrochlorothiazide tablets 20 mg/25 mg combinations appeared somewhat less effective in Black patients, but relatively few Black patients were studied. In most patients, the antihypertensive effect of lisinopril and hydrochlorothiazide tablets was sustained for at least 24 hours.
In a randomized, controlled comparison, the mean antihypertensive effects of lisinopril and hydrochlorothiazide tablets 20 mg/12.5 mg and lisinopril and hydrochlorothiazide tablets 20 mg/25 mg were similar, suggesting that many patients who respond adequately to the latter combination may be controlled with lisinopril and hydrochlorothiazide tablets 20 mg/12.5 mg. (See DOSAGE AND ADMINISTRATION .) Concomitant administration of lisinopril and hydrochlorothiazide has little or no effect on the bioavailability of either drug.
The combination tablet is bioequivalent to concomitant administration of the separate entities. Lisinopril Mechanism of Action Lisinopril inhibits angiotensin-converting enzyme (ACE) in human subjects and animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II.
Angiotensin II also stimulates aldosterone secretion by the adrenal cortex. Inhibition of ACE results in decreased plasma angiotensin II which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium.
Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity. In hypertensive patients with normal renal function treated with lisinopril alone for up to 24 weeks, the mean increase in serum potassium was less than 0.1 mEq/L; however, approximately 15 percent of patients had increases greater than 0.5 mEq/L and approximately six percent had a decrease greater than 0.5 mEq/L. In the same study, patients treated with lisinopril plus a thiazide diuretic showed essentially no change in serum potassium.
(See PRECAUTIONS ) ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of lisinopril remains to be elucidated. While the mechanism through which lisinopril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, lisinopril is antihypertensive even in patients with low-renin hypertension.
Although lisinopril was antihypertensive in all races studied, Black hypertensive patients (usually a low-renin hypertensive population) had a smaller average response to lisinopril monotherapy than non-Black patients. Pharmacokinetics and Metabolism Following oral administration of lisinopril, peak serum concentrations occur within about 7 hours. Declining serum concentrations exhibit a prolonged terminal phase which does not contribute to drug accumulation.
This terminal phase probably represents saturable binding to ACE and is not proportional to dose. Lisinopril does not appear to be bound to other serum proteins. Lisinopril does not undergo metabolism and is excreted unchanged entirely in the urine.
Based on urinary recovery, the mean extent of absorption of lisinopril is approximately 25 percent, with large intersu…
🧬 Mechanism of Action ▾
Mechanism of Action Lisinopril inhibits angiotensin-converting enzyme (ACE) in human subjects and animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
Inhibition of ACE results in decreased plasma angiotensin II which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium. Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity.
In hypertensive patients with normal renal function treated with lisinopril alone for up to 24 weeks, the mean increase in serum potassium was less than 0.1 mEq/L; however, approximately 15 percent of patients had increases greater than 0.5 mEq/L and approximately six percent had a decrease greater than 0.5 mEq/L. In the same study, patients treated with lisinopril plus a thiazide diuretic showed essentially no change in serum potassium. (See PRECAUTIONS ) ACE is identical to kininase, an enzyme that degrades bradykinin.
Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of lisinopril remains to be elucidated. While the mechanism through which lisinopril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, lisinopril is antihypertensive even in patients with low-renin hypertension. Although lisinopril was antihypertensive in all races studied, Black hypertensive patients (usually a low-renin hypertensive population) had a smaller average response to lisinopril monotherapy than non-Black patients.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Lisinopril and hydrochlorothiazide tablets USP,20 mg/12.5 mg are yellow, round tablets, imprinted with ‘H151’ on one side and plain on the other side. NDC 68788-8253-3 Bottle of 30 tablets NDC 68788-8253-6 Bottle of 60 tablets NDC 68788-8253-9 Bottle of 90 tablets NDC 68788-8253-1 Bottle of 100 tablets Storage Store at 20°C-25°C (68°F-77°F); excursions permitted to 15°C-30°C (59°F-86°F) [see USP Controlled Room Temperature]. Protect from excessive light and humidity.
Dispense in a well-closed container, if product package is subdivided. Manufactured by: Zhejiang Huahai Pharmaceutical Co., Ltd. Xunqiao, Linhai, Zhejiang 317024, China Distributed by: Solco Healthcare US, LLC Somerset, NJ 08873, USA Revised: 07/2025 200489-0 Repackaged By: Preferred Pharmaceuticals Inc.
📋 Description ▾
DESCRIPTION Lisinopril and hydrochlorothiazide tablets combine an angiotensin converting enzyme inhibitor, lisinopril, and a diuretic, hydrochlorothiazide. Lisinopril, a synthetic peptide derivative, is an oral long-acting angiotensin converting enzyme inhibitor. It is chemically described as (S)-1-[N2-(1-carboxy-3-phenylpropyl)-L-lysyl]-L-proline dihydrate.
Its empirical formula is C 21 H 31 N 3 O 5 • 2H 2 O and its structural formula is: Lisinopril, USP is a white to off-white, crystalline powder, with a molecular weight of 441.52. It is soluble in water, sparingly soluble in methanol, and practically insoluble in ethanol. Hydrochlorothiazide is 6-chloro-3,4-dihydro-2H-1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide.
Its empirical formula is C 7 H 8 ClN 3 O 4 S 2 and its structural formula is: Hydrochlorothiazide, USP is a white, or practically white, crystalline powder with a molecular weight of 297.73, which is slightly soluble in water, but freely soluble in sodium hydroxide solution. Lisinopril and hydrochlorothiazide tablets, USP are available for oral use in three tablet combinations of lisinopril with hydrochlorothiazide: lisinopril and hydrochlorothiazide tablets 10 mg/12.5 mg containing 10 mg lisinopril and 12.5 mg hydrochlorothiazide; lisinopril and hydrochlorothiazide tablets 20 mg/12.5 mg containing 20 mg lisinopril and 12.5 mg hydrochlorothiazide; and, lisinopril and hydrochlorothiazide tablets 20 mg/25 mg containing 20 mg lisinopril and 25 mg hydrochlorothiazide.
Inactive Ingredients: 10 mg/12.5 mg Tablets - dibasic calcium phosphate dihydrate, magnesium stearate, mannitol, pregelatinized starch. 20 mg/12.5 mg Tablets - dibasic calcium phosphate dihydrate, magnesium stearate, mannitol, pregelatinized starch, yellow ferric oxide. 20 mg/25 mg Tablets - dibasic calcium phosphate dihydrate, magnesium stearate, mannitol, pregelatinized starch, red ferric oxide. picture 1 picture 2
💬 Information for Patients ▾
Information for Patients Angioedema: Angioedema, including laryngeal edema, may occur at any time during treatment with angiotensin converting enzyme inhibitors, including lisinopril. Patients should be so advised and told to report immediately any signs or symptoms suggesting angioedema (swelling of face, extremities, eyes, lips, tongue, difficulty in swallowing or breathing) and to take no more drug until they have consulted with the prescribing physician. Symptomatic Hypotension: Patients should be cautioned to report lightheadedness especially during the first few days of therapy.
If actual syncope occurs, the patients should be told to discontinue the drug until they have consulted with the prescribing physician. All patients should be cautioned that excessive perspiration and dehydration may lead to an excessive fall in blood pressure because of reduction in fluid volume. Other causes of volume depletion such as vomiting or diarrhea may also lead to a fall in blood pressure; patients should be advised to consult with their physician.
Hyperkalemia: Patients should be told not to use salt substitutes containing potassium without consulting their physician. Neutropenia: Patients should be told to report promptly any indication of infection (e.g., sore throat, fever) which may be a sign of neutropenia. Pregnancy: Female patients of childbearing age should be told about the consequences of exposure to lisinopril and hydrochlorothiazide tablets during pregnancy.
Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible. Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening.