
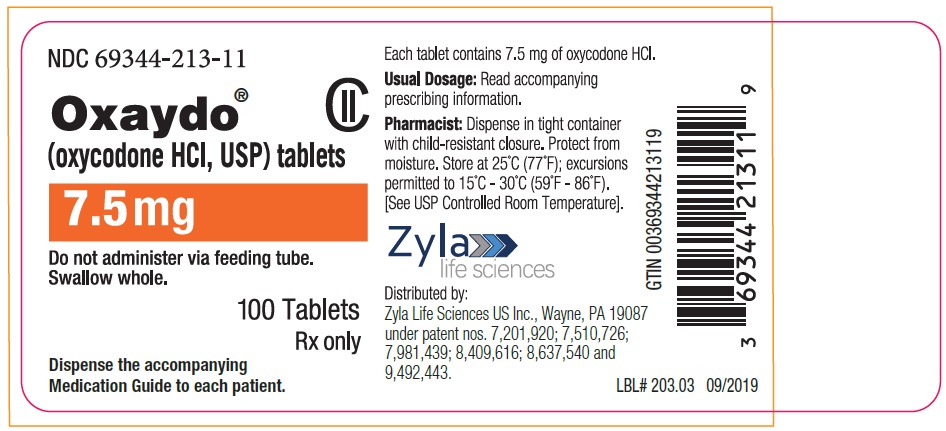
OXAYDO OXYCODONE HYDROCHLORIDE 7.5 mg Tablet, 100-count
Other active recalls for Oxycodone Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Opioid Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Oxycodone is used to relieve severe pain. Oxycodone is in a class of medications called opiate (narcotic) analgesics. It works by changing the way the brain and nervous system respond to pain.
Read the full MedlinePlus article ↗- Extended-release oxycodone is designed for pain that's severe enough to need steady, around-the-clock control — not just occasional flare-ups. The tablet releases slowly over 12 ho...
- Why has my doctor prescribed an extended-release opioid instead of regular pain pills?
- No — and this is really important. Crushing, breaking, chewing, or dissolving the tablet destroys the controlled-release mechanism. The entire dose, meant to be released slowly ove...
- Is it okay to crush or break the tablet to make it easier to swallow?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Oxycodone Hydrochloride — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $14.008 | $1,400.83 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Oxaydo 7.5 mgthis 69344-0213-11 | Zyla | 100 tablets | $14.008 | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69344-0213-11 You're viewing this | 100 TABLET in 1 BOTTLE (69344-213-11) | 2015-09-01 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF OXAYDO Addiction, Abuse, and Misuse Because the use of OXAYDO exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient’s risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [ see Warnings and Precautions ( 5.1 ) ]. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of OXAYDO, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of OXAYDO are essential [ see Warnings and Precautions ( 5.2 ) ]. Accidental Ingestion Accidental ingestion of even one dose of OXAYDO, especially by children, can result in a fatal overdose of oxycodone [ see Warnings and Precautions ( 5.2 ) ]. Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death.
Reserve concomitant prescribing of OXAYDO and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate [ see Warnings and Precautions ( 5.3 ), Drug Interactions ( 7 ) ]. Neonatal Opioid Withdrawal Syndrome (NOWS) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery [ see Warnings and Precautions ( 5.4 ) ].
Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS) Healthcare providers are strongly encouraged to complete a REMS-compliant education program and to counsel patients and caregivers on serious risks, safe use, and the importance of reading the Medication Guide with each prescription [ see Warnings and Precautions ( 5.5 ) ]. Cytochrome P450 3A4 Interaction The concomitant use of OXAYDO with all cytochrome P450 3A4 inhibitors may result in an increase in oxycodone plasma concentrations, which could increase or prolong adverse reactions and may cause potentially fatal respiratory depression.
In addition, discontinuation of a concomitantly used cytochrome P450 3A4 inducer may result in an increase in oxycodone plasma concentration. Regularly evaluate patients receiving OXAYDO and any CYP3A4 inhibitor or inducer [ see Warnings and Precautions ( 5.6 ), Drug Interactions ( 7 ), Clinical Pharmacology ( 12.3 ) ]. WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF OXAYDO See full prescribing information for complete boxed warning.
OXAYDO exposes users to risks of addiction, abuse, and misuse, which can lead to overdose and death. Assess patient’s risk before prescribing and reassess regularly for these behaviors and conditions. ( 5.1 ) Serious, life-threatening, or fatal respiratory depression may occur, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of OXAYDO are essential. ( 5.2 ) Accidental ingestion of OXAYDO, especially by children, can result in a fatal overdose of oxycodone. ( 5.2 ) Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death.
Reserve concomitant prescribing for use in patients for whom alternative treatment options are inadequate. ( 5.6 , 7 ) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery.
( 5.4 ) Healthcare providers are strongly encouraged to…
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE OXAYDO is indicated for the management of acute and chronic pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate. Limitations of Use Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy [ see Warnings and Precautions (5.1) ], reserve opioid analgesics, including OXAYDO, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
OXAYDO is an opioid agonist indicated for the management of acute and chronic pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate. ( 1 ) Limitations of Use ( 1 ) Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy, reserve opioid analgesics, including OXAYDO, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
( 1 , 5.1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION OXAYDO should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. ( 2.1 ) Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals. Reserve titration to higher doses of OXAYDO for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks.
( 2.1 , 5 ) Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic. Clinical guidelines on opioid prescribing for some acute pain conditions are available. ( 2.1 ) Initiate the dosing regimen for each patient individually, taking into account the patient’s underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse.
( 2.1 , 5.1 ) Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with OXAYDO. Consider this risk when selecting an initial dose and when making dose adjustments. ( 2.1 , 5.2 ) Discuss opioid overdose reversal agents and options for acquiring them with the patient and/or caregiver, both when initiating and renewing treatment with OXAYDO, especially if the patient has additional risk factors for overdose, or close contacts at risk for exposure and overdose.
( 2.2 , 5.1 , 5.2 , 5.3 ) For opioid naïve patients, initiate treatment with 5 mg to 15 mg every 4 to 6 hours as needed for pain, and at the lowest dose necessary to achieve adequate analgesia. Titrate the dose based upon the individual patient’s response to their initial dose of OXAYDO. ( 2.2 , 2.4 ) Must be swallowed whole and is not amenable to crushing and dissolution.
Do not use OXAYDO for administration via nasogastric, gastric, or other feeding tubes as it may cause obstruction of feeding tubes ( 2.1 , 17 ) Must take tablets one at a time, with enough water to ensure complete swallowing immediately after placing in mouth. ( 2.1 ) Periodically reassess patients receiving OXAYDO to evaluate the continued need for opioid analgesics to maintain pain control, for the signs or symptoms of adverse reactions, and for the development of addiction, abuse, or misuse. ( 2.4 ) Do not rapidly reduce or abruptly discontinue OXAYDO in a physically-dependent patient because rapid reduction or abrupt discontinuation of opioid analgesics has resulted in serious withdrawal symptoms, uncontrolled pain, and suicide.
( 2.4 , 5.14 )
2.1Important Dosage and Administration Instructions OXAYDO should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals [see Warnings and Precautions ( 5 )]. Because the risk of overdose increases as opioid doses increase, reserve titration to higher doses of OXAYDO for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks.
Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic. Clinical guidelines on opioid prescribing for some acute pain conditions are available. There is variability in the opioid analgesic dose and duration needed to adequately manage pain due both to the cause of pain and to individual patient factors.
Initiate the dosing regimen for each patient individually, taking into account the patient’s underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse [see Warnings an…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 5 mg and 7.5 mg of oxycodone HCl, USP: Strength Description 5 mg Round, convex, white tablet, debossed “5” on one side, letter “O” on other side. 7.5 mg Round, convex, white tablet, debossed “7.5” on one side, letter “O” on other side. Tablets: 5 mg and 7.5 mg oxycodone HCl ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS OXAYDO is contraindicated in patients with: Significant respiratory depression [see Warnings and Precautions ( 5.2 )] Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see Warnings and Precautions ( 5.8 )] Known or suspected gastrointestinal obstruction, including paralytic ileus [see Warnings and Precautions ( 5.12 )] Hypersensitivity to oxycodone, oxycodone salts, or any components of the product (e.g., anaphylaxis) [see Adverse Reactions ( 6.2 )] Significant respiratory depression.
( 4 ) Acute or severe bronchial asthma in an unmonitored setting or in absence of resuscitative equipment. ( 4 ) Known or suspected gastrointestinal obstruction, including paralytic ileus. ( 4 ) Hypersensitivity to oxycodone, oxycodone salts, or any components of the product.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Opioid-Induced Hyperalgesia and Allodynia: Opioid-Induced Hyperalgesia (OIH) occurs when an opioid analgesic paradoxically causes an increase in pain, or an increase in sensitivity to pain. If OIH is suspected, carefully consider appropriately decreasing the dose of the current opioid analgesic, or opioid rotation. ( 5.7 ) Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients: Regularly evaluate, particularly during initiation and titration.
( 5.8 ) Adrenal Insufficiency: If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid. ( 5.9 ) Severe Hypotension: Regularly evaluate during dosage initiation and titration. Avoid use of OXAYDO in patients with circulatory shock.
( 5.10 ) Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness: Monitor for sedation and respiratory depression. Avoid use of OXAYDO in patients with impaired consciousness or coma. ( 5.11 )
5.1Addiction, Abuse, and Misuse OXAYDO contains oxycodone, a Schedule II controlled substance. As an opioid, OXAYDO exposes users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence ( 9 )]. Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed OXAYDO.
Addiction can occur at recommended dosages and if the drug is misused or abused. The risk of opioid-related overdose or overdose-related death is increased with higher opioid doses, and this risk persists over the course of therapy. In postmarketing studies, addiction, abuse, misuse, and fatal and non-fatal opioid overdose were observed in patients with long-term opioid use [ see Adverse Reactions ( 6.2 ) ].
Assess each patient’s risk for opioid addiction, abuse, or misuse prior to prescribing OXAYDO, and reassess all patients receiving OXAYDO for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression). The potential for these risks should not, however, prevent the proper management of pain in any given patient.
Patients at increased risk may be prescribed opioids such as OXAYDO but use in such patients necessitates intensive counseling about the risks and proper use of OXAYDO along with frequent reevaluation for signs of addiction, abuse, and misuse. Consider recommending or prescribing an opioid overdose reversal agent [ see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.2 ) ]. Opioids are sought for nonmedical use and are subject to diversion from legitimate prescribed use.
Consider these risks when prescribing or dispensing OXAYDO. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity and advising the patient on careful storage of the drug during the course of treatment and on the proper disposal of unused drug. Contact the local state professional licensing board or state-controlled substances authority for information on how to prevent and detect abuse or diversion of this product.
5.2Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid overdose reversal agents, depending on the patient’s clinical status [see Overdosage ( 10 )] .
Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids. While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of OXAYDO, the risk i…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described, or described in greater detail, in other sections: Addiction, Abuse, and Misuse [see Warnings and Precautions ( 5.1 )] Life-Threatening Respiratory Depression [see Warnings and Precautions ( 5.2 )] Interactions with Benzodiazepines or Other CNS Depressants [see Warnings and Precautions ( 5.3 )] Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions ( 5.4 )] Opioid-Induced Hyperalgesia and Allodynia [ see Warnings and Precautions ( 5.7 )] Adrenal Insufficiency [see Warnings and Precautions ( 5.9 )] Severe Hypotension [see Warnings and Precautions ( 5.10 )] Gastrointestinal Adverse Reactions [see Warnings and Precautions ( 5.12 )] Seizures [see Warnings and Precautions ( 5.13 )] Withdrawal [see Warnings and Precautions ( 5.14 )] Most common adverse reactions (incidence ≥3%) were nausea, constipation, vomiting, headache, pruritus, insomnia, dizziness, asthenia, and somnolence.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Zyla Life Sciences US Inc. at 1-800-518-1084 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, the adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Serious adverse reactions that may be associated with OXAYDO include: respiratory depression, respiratory arrest, circulatory depression, cardiac arrest, hypotension, and/or shock [see Warnings and Precautions ( 5 ) and Overdosage ( 10 )] .
The common adverse reactions seen on initiation of therapy with OXAYDO are dose-dependent, and their frequency depends on the clinical setting, the patient’s level of opioid tolerance, and host factors specific to the individual. They should be expected and managed as a part of opioid therapy. The most frequent of the adverse reactions include nausea, constipation, vomiting, headache, and pruritus.
The frequency of adverse reactions during initiation of opioid therapy may be minimized by careful individualization of starting dosage, slow titration and the avoidance of large rapid swings in plasma concentration of the opioid. Many of these adverse reactions will abate as therapy is continued and some degree of tolerance is developed, but others may be expected to remain throughout therapy. In all patients for whom dosing information was available (n=191) from open-label and double-blind studies involving oxycodone, the following adverse reactions were recorded in oxycodone-treated patients with an incidence of ≥3%.
In descending order of frequency they were: nausea, constipation, vomiting, headache, pruritus, insomnia, dizziness, asthenia, and somnolence. The following adverse reactions occurred in less than 3% of patients involved in clinical trials with oxycodone: Body as a Whole: abdominal pain, accidental injury, allergic reaction, back pain, chills and fever, fever, flu syndrome, infection, neck pain, pain, photosensitivity reaction, and sepsis. Cardiovascular: deep vein thrombophlebitis, heart failure, hemorrhage, hypotension, migraine, palpitation, and tachycardia.
Digestive: anorexia, diarrhea, dyspepsia, dysphagia, gingivitis, glossitis, and nausea and vomiting. Hematopoietic and Lymphatic: anemia and leukopenia. Metabolism and Nutrition: edema, gout, hyperglycemia, iron deficiency anemia, and peripheral edema.
Musculoskeletal: arthralgia, arthritis, bone pain, myalgia, and pathological fracture. Nervous System: agitation, anxiety, confusion, dry mouth, hypertonia, hypesthesia, nervousness, neuralgia, personality disorder, tremor, and vasodilation. Respiratory: bronchitis, cough increased, dyspnea, epistaxis, laryngismus, lung disorder, pharyngitis, rhinitis, and sinusitis.
Skin and Appendages: herpes simplex, rash, sweating, and urticaria. Special Senses: amblyopia. Urogenital:…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 1 includes clinically significant drug interactions with OXAYDO. Table 1: Clinically Significant Drug Interactions with OXAYDO Inhibitors of CYP3A4 and CYP2D6 Clinical Impact: The concomitant use of OXAYDO and CYP3A4 inhibitors can increase the plasma concentration of oxycodone, resulting in increased or prolonged opioid effects. These effects could be more pronounced with concomitant use of OXAYDO and CYP2D6 and CYP3A4 inhibitors, particularly when an inhibitor is added after a stable dose of OXAYDO is achieved [ see Warnings and Precautions ( 5.6 ) ].
After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the oxycodone plasma concentration will decrease [ see Clinical Pharmacology ( 12.3 ) ], resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to oxycodone. Intervention: If concomitant use is necessary, consider dosage reduction of OXAYDO until stable drug effects are achieved. Evaluate patients for respiratory depression and sedation at frequent intervals.
If a CYP3A4 inhibitor is discontinued, consider increasing the OXAYDO dosage until stable drug effects are achieved. Evaluate for signs of opioid withdrawal. Examples Macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g., ketoconazole), protease inhibitors (e.g., ritonavir) CYP3A4 Inducers Clinical Impact: The concomitant use of OXAYDO and CYP3A4 inducers can decrease the plasma concentration of oxycodone [see Clinical Pharmacology ( 12.3 )] , resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence to oxycodone [see Warnings and Precautions ( 5.6 )] .
After stopping a CYP3A4 inducer, as the effects of the inducer decline, the oxycodone plasma concentration will increase [see Clinical Pharmacology ( 12.3 )] , which could increase or prolong both the therapeutic effects and adverse reactions, and may cause serious respiratory depression. Intervention: If concomitant use is necessary, consider increasing the OXAYDO dosage until stable drug effects are achieved [see Dosage and Administration ( 2.3 )] . Evaluate patients for signs of opioid withdrawal.
If a CYP3A4 inducer is discontinued, consider OXAYDO dosage reduction and evaluate patients at frequent intervals for signs of respiratory depression and sedation. Examples Rifampin, carbamazepine, phenytoin Benzodiazepines and other Central Nervous System (CNS) Depressants Clinical Impact: Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants including alcohol, increases the risk of respiratory depression, profound sedation, coma, and death [see Warnings and Precautions ( 5.3 )].
Intervention: Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required. Inform patients and caregivers of this potential interaction and educate them on the for signs and symptoms of respiratory depression (including sedation).
If concomitant use is warranted, consider recommending or prescribing an opioid overdose reversal agent [ see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 , 5.2 , 5.3 ) ]. Examples: Benzodiazepines and other sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids (gabapentin or pregabalin), other opioids, alcohol. Serotonergic Drugs Clinical Impact: The concomitant use of opioids with other drugs that affect the serotonergic neurotransmitter system has resulted in serotonin syndrome.
Intervention: If concomitant use is warranted, frequently evaluate the patient, particularly during treatment initiation and dose adjustment. Discontinue OXAYDO if serotonin syndrome is suspected. Examples: Selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyc…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : May cause fetal harm. ( 8.1 )
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions ( 5.4 )] . There are no available data with OXAYDO in pregnant women to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies with oral administrations of oxycodone HCl in rats and rabbits during the period of organogenesis at doses 2.6 and 8.1 times, respectively, the human dose of 60 mg/day did not reveal evidence of teratogenicity or embryo-fetal toxicity.
In several published studies, treatment of pregnant rats with oxycodone at clinically relevant doses and below resulted in neurobehavioral effects in offspring [ see Data ] . Based on animal data, advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.4 )] .
Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate. OXAYDO is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including OXAYDO, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of oxycodone HCl administered during the period of organogenesis up to 16 mg/kg/day and up 25 mg/kg/day, respectively. These studies revealed no evidence of teratogenicity or embryo-fetal toxicity due to oxycodone. The highest doses tested in rats and rabbits were equivalent to approximately 2.6 and 8.1 times an adult human dose of 60 mg/day, respectively, on a mg/m 2 basis.
In published studies, offspring of pregnant rats administered oxycodone during gestation have been reported to exhibit neurobehavioral effects including altered stress responses, increased anxiety-like behavior (2 mg/kg/day IV from Gestation Day 8 to 21 and Postnatal Day 1, 3, and 5; 0.3-times an adult human dose of 60 mg/day, on a mg/m 2 basis) and altered learning and memory (15 mg/kg/day orally from breeding through parturition; 2.4 times an adult human dose of 60 mg/day, on a mg/m 2 basis).
8.2Lactation Risk Summary Available data from lactation studies indicate that oxycodone is pr…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions ( 5.4 )] . There are no available data with OXAYDO in pregnant women to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies with oral administrations of oxycodone HCl in rats and rabbits during the period of organogenesis at doses 2.6 and 8.1 times, respectively, the human dose of 60 mg/day did not reveal evidence of teratogenicity or embryo-fetal toxicity.
In several published studies, treatment of pregnant rats with oxycodone at clinically relevant doses and below resulted in neurobehavioral effects in offspring [ see Data ] . Based on animal data, advise pregnant women of the potential risk to a fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions ( 5.4 )] .
Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agent, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate. OXAYDO is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including OXAYDO, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Data Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of oxycodone HCl administered during the period of organogenesis up to 16 mg/kg/day and up 25 mg/kg/day, respectively. These studies revealed no evidence of teratogenicity or embryo-fetal toxicity due to oxycodone. The highest doses tested in rats and rabbits were equivalent to approximately 2.6 and 8.1 times an adult human dose of 60 mg/day, respectively, on a mg/m 2 basis.
In published studies, offspring of pregnant rats administered oxycodone during gestation have been reported to exhibit neurobehavioral effects including altered stress responses, increased anxiety-like behavior (2 mg/kg/day IV from Gestation Day 8 to 21 and Postnatal Day 1, 3, and 5; 0.3-times an adult human dose of 60 mg/day, on a mg/m 2 basis) and altered learning and memory (15 mg/kg/day orally from breeding through parturition; 2.4 times an adult human dose of 60 mg/day, on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety, effectiveness, and pharmacokinetics of OXAYDO in pediatric patients below the age of 18 have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Elderly patients (aged 65 years or older) may have increased sensitivity to oxycodone. In general, use caution when selecting a dosage for an elderly patient, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Respiratory depression is the chief risk for elderly patients treated with opioids and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of OXAYDO slowly in geriatric patients frequently reevaluate the patient for signs of central nervous system and respiratory depression [see Warnings and Precautions ( 5.2 )] . Oxycodone is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to regularly evaluate renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute overdose with oxycodone can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see Clinical Pharmacology ( 12.2 )] . Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias may require advanced life-support measures.
For clinically significant respiratory or circulatory depression secondary to opioid overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene. Because the duration of opioid reversal is expected to be less than the duration of action of oxycodone in OXAYDO, carefully monitor the patient until spontaneous respiration is reliably reestablished. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product’s prescribing information.
In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be initiated with care and by titration with smaller than usual doses of the reversal agent.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Oxycodone is a full opioid agonist and is relatively selective for the mu-opioid receptor, although it can bind to other opioid receptors at higher doses. The principal therapeutic action of oxycodone is analgesia. Like all full opioid agonists, there is no ceiling effect for analgesia with oxycodone.
Clinically, dosage is titrated to provide adequate analgesia and may be limited by adverse reactions, including respiratory and CNS depression. The precise mechanism of the analgesic action is unknown. However, specific CNS opioid receptors for endogenous compounds with opioid-like activity have been identified throughout the brain and spinal cord and are thought to play a role in the analgesic effects of this drug.
12.2Pharmacodynamics Effects on the Central Nervous System Oxycodone produces respiratory depression by direct action on brainstem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Oxycodone causes miosis, even in total darkness.
Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Oxycodone causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum.
Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System Oxycodone produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes and sweating, and/or orthostatic hypotension. Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans [see Adverse Reactions ( 6.2 )] .
They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions ( 6.2 )] .
Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of oxycodone for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome, and/or the development of analgesic tolerance [see Dosage and Administration ( 2.1 , 2.4 )] . Concentration–Adverse Reaction Relationships There is a relationship between increasing oxycodone plasma…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Oxycodone is a full opioid agonist and is relatively selective for the mu-opioid receptor, although it can bind to other opioid receptors at higher doses. The principal therapeutic action of oxycodone is analgesia. Like all full opioid agonists, there is no ceiling effect for analgesia with oxycodone.
Clinically, dosage is titrated to provide adequate analgesia and may be limited by adverse reactions, including respiratory and CNS depression. The precise mechanism of the analgesic action is unknown. However, specific CNS opioid receptors for endogenous compounds with opioid-like activity have been identified throughout the brain and spinal cord and are thought to play a role in the analgesic effects of this drug.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING OXAYDO (oxycodone HCl) 5 mg tablets are round, convex, white tablets debossed with the strength “5” on one side and the letter “O” on the other side and supplied as: NDC 69344-113-11 Bottles of 100 tablets OXAYDO 7.5 mg tablets are round, convex, white tablets debossed with the strength “7.5” on one side and the letter “O” on the other side and supplied as: NDC 69344-213-11 Bottles of 100 tablets Dispense in tight container as defined in the USP, with a child-resistant closure. Store at 25°C (77°F); with excursions permitted to 15°-30°C (59°-86°F) [See USP Controlled Room Temperature].
Protect from moisture. Store OXAYDO securely and dispose of properly.
📋 Description ▾
11 DESCRIPTION OXAYDO (oxycodone HCl) 5 mg and 7.5 mg tablets are an immediate-release opioid agonist intended for oral administration only. Chemically, oxycodone HCl is 4,5α-epoxy-14-hydroxy-3-methoxy-17-methylmorphinan-6-one HCl, a white, odorless crystalline powder. Oxycodone HCl is soluble in water (1 g in 6 to 7 mL).
The molecular weight of oxycodone HCl is 351.82. The molecular formula for oxycodone HCl is C 18 H 21 NO 4 •HCl, and the structure is: The inactive ingredients in OXAYDO include: colloidal silicon dioxide NF; crospovidone NF; magnesium stearate NF; microcrystalline cellulose NF; polyethylene oxide NF; and sodium lauryl sulfate NF. The tablets are round, convex, white and debossed with the strength (5 or 7.5) on one side and the letter “O” on the other side.
Oxado Chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Storage and Disposal: Because of the risks associated with accidental ingestion, misuse, and abuse, advise patients to store OXAYDO securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. Inform patients that leaving OXAYDO unsecured can pose a deadly risk to others in the home [ see Warnings and Precautions ( 5.1 , 5.2 ), Drug Abuse and Dependence ( 9.2 ) ].
Advise patients and caregivers that when medicines are no longer needed, they should be disposed of promptly. Expired, unwanted, or unused OXAYDO should be disposed of by flushing the unused medication down the toilet if a drug take-back option is not readily available. Inform patients that they can visit www.fda.gov/drugdisposal for a complete list of medicines recommended for disposal by flushing, as well as additional information on disposal of unused medicines.
Addiction, Abuse, and Misuse Inform patients that the use of OXAYDO, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions ( 5.1 )]. Instruct patients not to share OXAYDO with others and to take steps to protect OXAYDO from theft or misuse. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting OXAYDO or when the dosage is increased, and that it can occur even at recommended dosages.
Educate patients and caregivers on how to recognize respiratory depression and emphasize the importance of calling 911 or getting emergency medical help right away in the event of a known or suspected overdose [ see Warnings and Precautions ( 5.2 ) ]. Accidental Ingestion Inform patients that accidental ingestion, especially by children, may result in respiratory depression or death [see Warnings and Precautions ( 5.2 )] . Interactions with Benzodiazepines and Other CNS Depressants Inform patients and caregivers that potentially fatal additive effects may occur if OXAYDO is used with benzodiazepines or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedative/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids), and not to use these concomitantly unless supervised by a healthcare provider [see Warnings and Precautions ( 5.3 ), Drug Interactions ( 7 )].
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose.
Discuss with the patient the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program) [ see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.3 ) ]. Educate patients and caregivers on how to recognize the signs and symptoms of an overdose. Explain to patients and caregivers that effects of opioid overdose reversal agents like naloxone and nalmefene are temporary and that they must call 911 or get emergency medical help right away in all cases of known or suspected opioid overdose, even if an opioid overdose reversal agent is administered [ see Overdosage (10) ].
Advise patients and caregivers: how to treat with the overdose reversal agent in the event of an opioid overdose to tell family and friends about their opioid overdose reversal…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Issued: 12/2025 Medication Guide OXAYDO (ox Ā doe) (oxycodone HCl, USP) Tablets for oral use only, CII OXAYDO is: A strong prescription pain medicine that contains an opioid (narcotic) that is used to manage short-term (acute) and long term (chronic) pain severe enough to require an opioid pain medicine, when other pain treatments such as non-opioid pain medicines do not treat your pain well enough or you cannot tolerate them.
An opioid pain medicine that can put you at risk for overdose and death. Even if you take your dose correctly as prescribed you are at risk for opioid addiction, abuse, and misuse that can lead to death. Important information about OXAYDO: Get emergency help right away or call 911 right away if you take too much OXAYDO (overdose) .
When you first start taking OXAYDO, when your dose is changed, or if you take too much (overdose), serious or life-threatening breathing problems that can lead to death may occur. Ask your healthcare provider about medicines like naloxone or nalmefene that can be used in an emergency to reverse an opioid overdose. Taking OXAYDO with other opioid medicines, benzodiazepines, gabapentinoids (gabapentin or pregabalin), alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems, coma, and death.
Never give anyone else your OXAYDO. They could die from taking it. Selling or giving away OXAYDO is against the law.
Store OXAYDO securely, out of sight and reach of children, and in a location not accessible by others, including visitors to the home. Do not take OXAYDO if you have: severe asthma, trouble breathing, or other lung problems. a bowel blockage or have narrowing of the stomach or intestines. Before taking OXAYDO, tell your healthcare provider if you have a history of: head injury, seizures problems urinating abuse of street or prescription drugs, alcohol addiction, opioid overdose, or mental health problems. liver, kidney, thyroid problems pancreas or gallbladder problems Tell your healthcare provider if you are: noticing your pain getting worse.
If your pain gets worse after you take OXAYDO, do not take more of OXAYDO without first talking to your healthcare provider. Talk to your healthcare provider if the pain that you have increases, if you feel more sensitive to pain, or if you have new pain after taking OXAYDO. pregnant or planning to become pregnant. Use of OXAYDO for an extended period of time during pregnancy can cause withdrawal symptoms in your newborn baby that could be life-threatening if not recognized and treated. breastfeeding.
OXAYDO passes into breastmilk and may harm your baby. Carefully observe infants for increased sleepiness (more than usual), breathing difficulties, or limpness. Seek immediate medical care if you notice these signs. living in a household where there are small children or someone who has abused street or prescription drugs. taking prescription or over-the-counter medicines, vitamins, or herbal supplements.
Taking OXAYDO with certain other medicines can cause serious side effects that could lead to death. When taking OXAYDO: Do not change your dose. Take OXAYDO exactly as prescribed by your healthcare provider.
Use the lowest dose possible for the shortest time needed. For acute (short-term) pain, you may only need to take OXAYDO for a few days. You may have some OXAYDO left over that you did not use.
See disposal information at the bottom of this section for directions on how to safely throw away (dispose of) your unused OXAYDO. Take your prescribed dose exactly as instructed by your healthcare provider. Your healthcare provider may adjust the dose until it is right for you.
Do not take more than your prescribed dose. If you miss a dose, take your next dose at your usual time. Call your healthcare provider if the dose you are taking does not control your pain.
If you have b…