
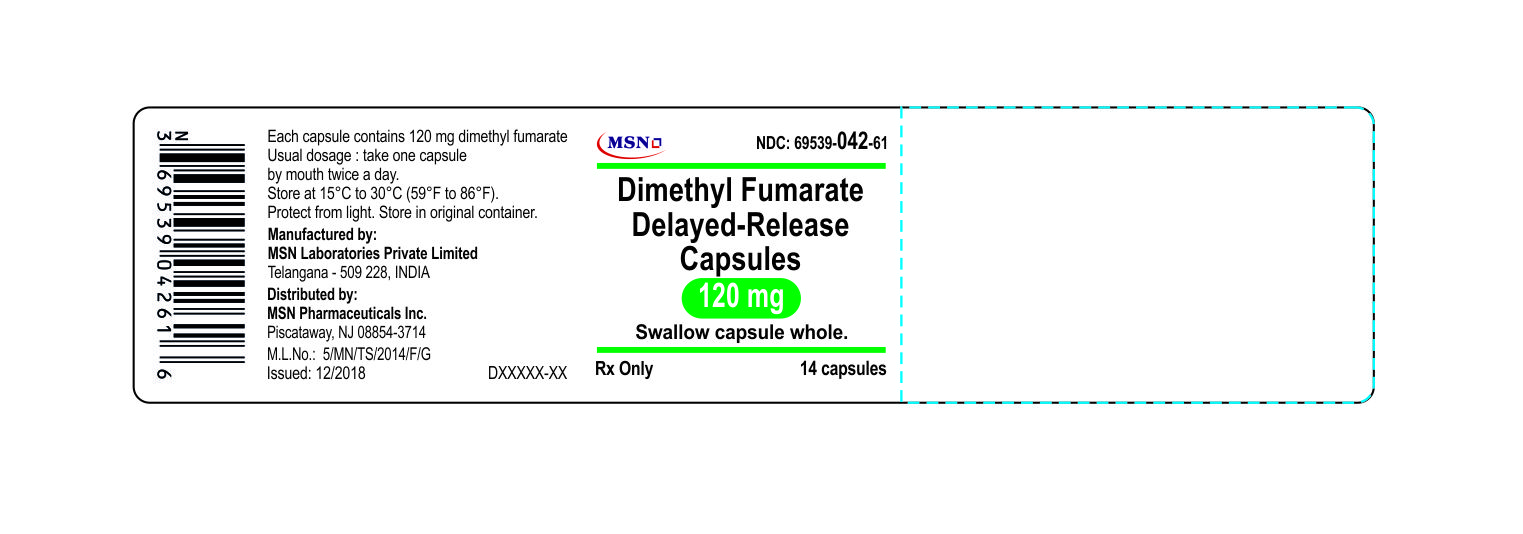
Dimethyl Fumarate 120 mg Capsule, Delayed Release, 14-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Other immunosuppressants class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Dimethyl fumarate (brand name Tecfidera, also available as a generic) is a prescription medicine for adults with relapsing forms of multiple sclerosis — meaning MS that comes and g...
- What exactly is dimethyl fumarate used for?
- The two most common things people notice early on are flushing — a sensation of warmth, redness, or tingling, usually in the face and chest — and stomach upset like belly pain, nau...
- What side effects should I expect, especially when I first start?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Dimethyl Fumarate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII 74G4R6TH13
A synthetic polymer made by combining two plastic-like chemicals. It forms a coating on tablets or capsules that dissolves at a specific point in the digestive tract, controlling where and when the medicine releases.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII MB5IUD6JUA
Shellac is a natural resin secreted by lac beetles, purified and processed into a coating material. It seals and protects tablets and capsules, controls how quickly the medicine dissolves, and gives pills their glossy finish.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
16 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.89 | $26.39 / 14 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dimethyl Fumarate 120 mg 31722-0657-31 | Camber | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 43547-0024-14 | Solco | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 43598-0429-52 | Dr. | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 59651-0083-14 | Aurobindo | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 69097-0322-89 | Cipla | 14 capsules | $0.447 | — | Availability likely | — |
| Dimethyl Fumarate 120 mg 69238-1318-04 | Amneal | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 70512-0852-14 | SOLA | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl fumarate 120 mg 82249-0745-14 | CivicaScript | 14 capsules | $0.447 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 16729-0416-04 | Accord | 14 capsules | $0.617 | AB | Availability likely | — |
| dimethyl fumarate 120 mg 24979-0127-02 | Upsher-Smith | 500 capsules | — | AB | FDA listed | — |
| Dimethyl Fumarate 120 mg 33342-0349-09 | Macleods | 60 capsules | — | AB | FDA listed | — |
| dimethyl fumarate 120 mg 51407-0442-14 | Golden | 14 capsules | — | AB | FDA listed | — |
| Tecfidera 120 mg 64406-0005-01 | Biogen | 14 capsules | — | AB | FDA listed | — |
| Dimethyl fumarate 120 mg 67877-0555-10 | Ascend | 1000 capsules | — | AB | FDA listed | — |
| Dimethyl Fumarate 120 mg 68462-0307-05 | Glenmark | 500 capsules | — | AB | FDA listed | — |
| Dimethyl Fumarate 120 mgthis 69539-0042-61 | MSN | 14 capsules | — | AB | FDA listed | — |
| dimethyl fumarate 120 mg 70710-1204-07 | Zydus | 14 capsules | — | — | FDA listed | — |
| dimethyl fumarate 120 mg 70771-1530-07 | Zydus | 14 capsules | — | — | FDA listed | — |
| Dimethyl Fumarate 120 mg 84677-0029-14 | Golden | 14 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69539-0042-05 | 1 BOTTLE in 1 CARTON (69539-042-05) / 500 CAPSULE, DELAYED RELEASE in 1 BOTTLE | 2020-09-28 | Active |
| 69539-0042-61 You're viewing this | 1 BOTTLE in 1 CARTON (69539-042-61) / 14 CAPSULE, DELAYED RELEASE in 1 BOTTLE | 2020-09-28 | Active |
Pack size FAQ
What quantity is in NDC 69539-0042-61?
What is the difference between NDC 69539-0042-61 and NDC 69539-0042-05?
What NDC number is used to bill for this package of Dimethyl Fumarate 120 mg Capsule, Delayed Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Dimethyl fumarate delayed-release capsules are indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. Dimethyl fumarate is indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting dose: 120 mg twice a day, orally, for 7 days ( 2.1 ) Maintenance dose after 7 days: 240 mg twice a day, orally ( 2.1 ) Swallow dimethyl fumarate delayed-release capsules whole and intact. Do not crush, chew, or sprinkle capsule contents on food ( 2.1 ) Take dimethyl fumarate delayed-release capsule with or without food ( 2.1 )
2.1Dosing Information The starting dose for dimethyl fumarate delayed-release capsules are 120 mg twice a day orally. After 7 days, the dose should be increased to the maintenance dose of 240 mg twice a day orally. Temporary dose reductions to 120 mg twice a day may be considered for individuals who do not tolerate the maintenance dose.
Within 4 weeks, the recommended dose of 240 mg twice a day should be resumed. Discontinuation of dimethyl fumarate delayed-release capsules should be considered for patients unable to tolerate return to the maintenance dose. The incidence of flushing may be reduced by administration of dimethyl fumarate delayed-release capsules with food.
Alternatively, administration of non-enteric coated aspirin (up to a dose of 325 mg) 30 minutes prior to dimethyl fumarate delayed-release capsule dosing may reduce the incidence or severity of flushing [see Clinical Pharmacology (12.3) ]. Dimethyl fumarate delayed-release capsules should be swallowed whole and intact. Dimethyl fumarate delayed-release capsules should not be crushed or chewed and the capsule contents should not be sprinkled on food.
Dimethyl fumarate delayed-release capsules can be taken with or without food.
2.2Blood Tests Prior to Initiation of Therapy Obtain a complete blood cell count (CBC) including lymphocyte count before initiation of therapy [ see Warnings and Precautions (5.4) ] . Obtain serum aminotransferase, alkaline phosphatase, and total bilirubin levels prior to treatment with dimethyl fumarate delayed-release capsules [ see Warnings and Precautions (5.5) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Dimethyl fumarate is available as hard gelatin delayed-release capsules containing 120 mg or 240 mg of dimethyl fumarate. The 120 mg capsules are white to off white colored enteric coated mini tablets filled in size "0" empty hard gelatin capsule shell with white opaque cap and white opaque body imprinted with "120 mg" with black ink. The 240 mg capsules are white to off white colored enteric coated mini tablets filled in size "0" empty hard gelatin capsule shell with white opaque cap and white opaque body imprinted with "240 mg" with black ink.
Delayed-release capsules: 120 mg and 240 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Dimethyl fumarate is contraindicated in patients with known hypersensitivity to dimethyl fumarate or to any of the excipients of dimethyl fumarate. Reactions have included anaphylaxis and angioedema [see Warnings and Precautions (5.1) ]. Known hypersensitivity to dimethyl fumarate or any of the excipients of dimethyl fumarate. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Anaphylaxis and angioedema: Discontinue and do not restart dimethyl fumarate if these occur. ( 5.1 ) Progressive multifocal leukoencephalopathy (PML): Withhold dimethyl fumarate at the first sign or symptom suggestive of PML. ( 5.2 ) Herpes zoster and other serious opportunistic infections: Consider withholding dimethyl fumarate in cases of serious infection until the infection has resolved.
( 5.3 ) Lymphopenia: Obtain a CBC including lymphocyte count before initiating dimethyl fumarate, after 6 months, and every 6 to 12 months thereafter. Consider interruption of dimethyl fumarate if lymphocyte counts <0.5 x 10 9 /L persist for more than six months. ( 5.4 ) Liver injury: Obtain serum aminotransferase, alkaline phosphatase, and total bilirubin levels before initiating dimethyl fumarate and during treatment, as clinically indicated.
Discontinue dimethyl fumarate if clinically significant liver injury induced by dimethyl fumarate is suspected. ( 5.5 )
5.1Anaphylaxis and Angioedema Dimethyl fumarate can cause anaphylaxis and angioedema after the first dose or at any time during treatment. Signs and symptoms have included difficulty breathing, urticaria, and swelling of the throat and tongue. Patients should be instructed to discontinue dimethyl fumarate and seek immediate medical care should they experience signs and symptoms of anaphylaxis or angioedema.
5.2Progressive Multifocal Leukoencephalopathy Progressive multifocal leukoencephalopathy (PML) has occurred in patients with MS treated with dimethyl fumarate. PML is an opportunistic viral infection of the brain caused by the JC virus (JCV) that typically only occurs in patients who are immunocompromised, and that usually leads to death or severe disability. A fatal case of PML occurred in a patient who received dimethyl fumarate for 4 years while enrolled in a clinical trial.
During the clinical trial, the patient experienced prolonged lymphopenia (lymphocyte counts predominantly <0.5 x 10 9 /L for 3.5 years) while taking dimethyl fumarate [ see Warnings and Precautions (5.4) ] . The patient had no other identified systemic medical conditions resulting in compromised immune system function and had not previously been treated with natalizumab, which has a known association with PML. The patient was also not taking any immunosuppressive or immunomodulatory medications concomitantly.
PML has also occurred in the postmarketing setting in the presence of lymphopenia (<0.9x10 9 /L). While the role of lymphopenia in these cases is uncertain, the PML cases have occurred predominantly in patients with lymphocyte counts <0.8 x 10 9 /L persisting for more than 6 months. At the first sign or symptom suggestive of PML, withhold dimethyl fumarate and perform an appropriate diagnostic evaluation.
Typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes. MRI findings may be apparent before clinical signs or symptoms. Cases of PML, diagnosed based on MRI findings and the detection of JCV DNA in the cerebrospinal fluid in the absence of clinical signs or symptoms specific to PML, have been reported in patients treated with other MS medications associated with PML.
Many of these patients subsequently became symptomatic with PML. Therefore, monitoring with MRI for signs that may be consistent with PML may be useful, and any suspicious findings should lead to further investigation to allow for an early diagnosis of PML, if present. Lower PML-related mortality and morbidity have been reported following discontinuation of another MS medication associated with PML in patients with PML who were initially asymptomatic compared to patients with PML who had characteristic clinical signs and symptoms at diagnosis.
It is not known whether these differences are d…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described elsewhere in labeling: Anaphylaxis and Angioedema [see Warnings and Precautions (5.1) ]. Progressive multifocal leukoencephalopathy [see Warnings and Precautions (5.2) ]. Herpes Zoster and Other Serious Opportunistic Infections [ see Warnings and Precautions (5.3) ].
Lymphopenia [ see Warnings and Precautions (5.4) ]. Liver Injury [ see Warnings and Precautions (5.5) ]. Flushing [ see Warnings and Precautions (5.6) ].
Most common adverse reactions (incidence ≥10% and ≥2% placebo) were flushing, abdominal pain, diarrhea, and nausea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact MSN pharmaceuticals Inc. at 1-855-668-2369 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The most common adverse reactions (incidence ≥10% and ≥2% more than placebo) for dimethyl fumarate were flushing, abdominal pain, diarrhea, and nausea. Adverse Reactions in Placebo-Controlled Trials In the two well-controlled studies demonstrating effectiveness, 1529 patients received dimethyl fumarate with an overall exposure of 2244 person-years [ see Clinical Studies (14) ].
The adverse reactions presented in the table below are based on safety information from 769 patients treated with dimethyl fumarate 240 mg twice a day and 771 placebo-treated patients. Table 1:Adverse Reactions in Study 1 and 2 reported for dimethyl fumarate 240 mg BID at ≥ 2% higher incidence than placebo Dimethyl Fumarate N=769 % Placebo N=771 % Flushing 40 6 Abdominal pain 18 10 Diarrhea 14 11 Nausea 12 9 Vomiting 9 5 Pruritus 8 4 Rash 8 3 Albumin urine present 6 4 Erythema 5 1 Dyspepsia 5 3 Aspartate aminotransferase increased 4 2 Lymphophenia 2 <1 Gastrointestinal Dimethyl fumarate caused GI events (e.g., nausea, vomiting, diarrhea, abdominal pain, and dyspepsia).
The incidence of GI events was higher early in the course of treatment (primarily in month 1) and usually decreased over time in patients treated with dimethyl fumarate compared with placebo. Four percent (4%) of patients treated with dimethyl fumarate and less than 1% of placebo patients discontinued due to gastrointestinal events. The incidence of serious GI events was 1% in patients treated with dimethyl fumarate.
Hepatic Transaminases An increased incidence of elevations of hepatic transaminases in patients treated with dimethyl fumarate was seen primarily during the first six months of treatment, and most patients with elevations had levels < 3 times the upper limit of normal (ULN) during controlled trials. Elevations of alanine aminotransferase and aspartate aminotransferase to ≥ 3 times the ULN occurred in a small number of patients treated with both dimethyl fumarate and placebo and were balanced between groups. There were no elevations in transaminases ≥ 3 times the ULN with concomitant elevations in total bilirubin > 2 times the ULN.
Discontinuations due to elevated hepatic transaminases were < 1% and were similar in patients treated with dimethyl fumarate or placebo. Eosinophilia A transient increase in mean eosinophil counts was seen during the first 2 months of therapy. Adverse Reactions in Placebo-Controlled and Uncontrolled Studies In placebo-controlled and uncontrolled clinical studies, a total of 2513 patients have received dimethyl fumarate and been followed for periods up to 4 years with an overall exposure of 4603 person-years.
Approximately 1162 patients have received more than 2 years of treatment with dimethyl fumarate. The adverse reaction profile of dimethyl fumarate in the uncontrolled clinical studies was consistent with the experience in the placebo-controlled clinical trials.
6.2 Post Marketing Experience The followin…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 )
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of dimethyl fumarate in pregnant women. In animals, adverse effects on offspring survival, growth, sexual maturation, and neurobehavioral function were observed when dimethyl fumarate (DMF) was administered during pregnancy and lactation at clinically relevant doses. [see Data] In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data In rats administered DMF orally (25, 100, 250 mg/kg/day) throughout organogenesis, embryofetal toxicity (reduced fetal body weight and delayed ossification) were observed at the highest dose tested. This dose also produced evidence of maternal toxicity (reduced body weight).
Plasma exposure (AUC) for monomethyl fumarate (MMF), the major circulating metabolite, at the no-effect dose is approximately three times that in humans at the recommended human dose (RHD) of 480 mg/day. In rabbits administered DMF orally (25, 75, and 150 mg/kg/day) throughout organogenesis, embryolethality and decreased maternal body weight were observed at the highest dose tested. The plasma AUC for MMF at the no-effect dose is approximately 5 times that in humans at the RHD.
Oral administration of DMF (25, 100, and 250 mg/kg/day) to rats throughout organogenesis and lactation resulted in increased lethality, persistent reductions in body weight, delayed sexual maturation (male and female pups), and reduced testicular weight at the highest dose tested. Neurobehavioral impairment was observed at all doses. A no-effect dose for developmental toxicity was not identified.
The lowest dose tested was associated with plasma AUC for MMF lower than that in humans at the RHD.
8.2Lactation Risk Summary There are no data on the presence of DMF or MMF in human milk. The effects on the breastfed infant and on milk production are unknown. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for dimethyl fumarate and any potential adverse effects on the breastfed infant from the drug or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of dimethyl fumarate did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of dimethyl fumarate in pregnant women. In animals, adverse effects on offspring survival, growth, sexual maturation, and neurobehavioral function were observed when dimethyl fumarate (DMF) was administered during pregnancy and lactation at clinically relevant doses. [see Data] In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data In rats administered DMF orally (25, 100, 250 mg/kg/day) throughout organogenesis, embryofetal toxicity (reduced fetal body weight and delayed ossification) were observed at the highest dose tested. This dose also produced evidence of maternal toxicity (reduced body weight).
Plasma exposure (AUC) for monomethyl fumarate (MMF), the major circulating metabolite, at the no-effect dose is approximately three times that in humans at the recommended human dose (RHD) of 480 mg/day. In rabbits administered DMF orally (25, 75, and 150 mg/kg/day) throughout organogenesis, embryolethality and decreased maternal body weight were observed at the highest dose tested. The plasma AUC for MMF at the no-effect dose is approximately 5 times that in humans at the RHD.
Oral administration of DMF (25, 100, and 250 mg/kg/day) to rats throughout organogenesis and lactation resulted in increased lethality, persistent reductions in body weight, delayed sexual maturation (male and female pups), and reduced testicular weight at the highest dose tested. Neurobehavioral impairment was observed at all doses. A no-effect dose for developmental toxicity was not identified.
The lowest dose tested was associated with plasma AUC for MMF lower than that in humans at the RHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of dimethyl fumarate did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Cases of overdose with dimethyl fumarate have been reported. The symptoms described in these cases were consistent with the known adverse event profile of dimethyl fumarate. There are no known therapeutic interventions to enhance elimination of dimethyl fumarate nor is there a known antidote. In the event of overdose, initiate symptomatic supportive treatment as clinically indicated.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism by which dimethyl fumarate (DMF) exerts its therapeutic effect in multiple sclerosis is unknown. DMF and the metabolite, monomethyl fumarate (MMF), have been shown to activate the Nuclear factor (erythroid-derived 2)-like 2 (Nrf2) pathway in vitro and in vivo in animals and humans. The Nrf2 pathway is involved in the cellular response to oxidative stress.
MMF has been identified as a nicotinic acid receptor agonist in vitro .
12.2Pharmacodynamics Potential to prolong the QT interval In a placebo controlled thorough QT study performed in healthy subjects, there was no evidence that dimethyl fumarate caused QT interval prolongation of clinical significance (i.e., the upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 ms).
12.3Pharmacokinetics After oral administration of dimethyl fumarate, dimethyl fumarate undergoes rapid presystemic hydrolysis by esterases and is converted to its active metabolite, monomethyl fumarate (MMF). Dimethyl fumarate is not quantifiable in plasma following oral administration of dimethyl fumarate. Therefore all pharmacokinetic analyses related to dimethyl fumarate were performed with plasma MMF concentrations.
Pharmacokinetic data were obtained in subjects with multiple sclerosis and healthy volunteers. Absorption The median T max of MMF is 2-2.5 hours. The peak plasma concentration (C max ) and overall exposure (AUC) increased approximately dose proportionally in the dose range studied (120 mg to 360 mg).
Following administration of dimethyl fumarate 240 mg twice a day with food, the mean C max of MMF was 1.87 mg/L and AUC was 8.21 mg.hr/L in MS patients. A high-fat, high-calorie meal did not affect the AUC of MMF but decreased its C max by 40%. The T max was delayed from 2.0 hours to 5.5 hours.
In this study, the incidence of flushing was reduced by approximately 25% in the fed state. Distribution The apparent volume of distribution of MMF varies between 53 and 73 L in healthy subjects. Human plasma protein binding of MMF is 27 to 45% and independent of concentration.
Metabolism In humans, dimethyl fumarate is extensively metabolized by esterases, which are ubiquitous in the gastrointestinal tract, blood, and tissues, before it reaches the systemic circulation. Further metabolism of MMF occurs through the tricarboxylic acid (TCA) cycle, with no involvement of the cytochrome P450 (CYP) system. MMF, fumaric and citric acid, and glucose are the major metabolites in plasma.
Elimination Exhalation of CO 2 is the primary route of elimination, accounting for approximately 60% of the dimethyl fumarate dose. Renal and fecal elimination are minor routes of elimination, accounting for 16% and 1% of the dose respectively.Trace amounts of unchanged MMF were present in urine. The terminal half-life of MMF is approximately 1 hour and no circulating MMF is present at 24 hours in the majority of individuals.
Accumulation of MMF does not occur with multiple doses of dimethyl fumarate. Specific Populations Body weight, gender, and age do not require dosage adjustment. No studies have been conducted in subjects with hepatic or renal impairment.
However, neither condition would be expected to affect exposure to MMF and therefore no dosage adjustment is necessary. Drug Interaction Studies No potential drug interactions with dimethyl fumarate or MMF were identified in in vitro CYP inhibition and induction studies, or in P-glycoprotein studies. Single doses of interferon beta-1a or glatiramer acetate did not alter the pharmacokinetics of MMF.
Aspirin, when administered approximately 30 minutes before dimethyl fumarate, did not alter the pharmacokinetics of MMF. Oral Contraceptives The coadministration of dimethyl fumarate with a combined oral contraceptive (norelgestromin and ethinyl estradiol) did not elicit any relevant effects in oral contraceptives exposure. No interaction studies have been pe…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism by which dimethyl fumarate (DMF) exerts its therapeutic effect in multiple sclerosis is unknown. DMF and the metabolite, monomethyl fumarate (MMF), have been shown to activate the Nuclear factor (erythroid-derived 2)-like 2 (Nrf2) pathway in vitro and in vivo in animals and humans. The Nrf2 pathway is involved in the cellular response to oxidative stress.
MMF has been identified as a nicotinic acid receptor agonist in vitro .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Dimethyl fumarate is available as hard gelatin delayed-release capsules in two strengths containing either 120 mg or 240 mg of dimethyl fumarate. The 120 mg capsules are white to off white colored enteric coated mini tablets filled in size "0" empty hard gelatin capsule shell with white opaque cap and white opaque body imprinted with "120 mg" with black ink. The 240 mg capsules are white to off white colored enteric coated mini tablets filled in size "0" empty hard gelatin capsule shell with white opaque cap and white opaque body imprinted with "240 mg" with black ink.
Dimethyl fumarate delayed-release capsules are available as follows: 30-day Starter Pack, (NDC 69539-240-18): 120 mg (7-day bottle): bottle of 14 capsules (NDC 69539-042-55) 240 mg (23-day bottle): bottle of 46 capsules (NDC 69539-043-46) 120 mg capsules: bottle of 14 capsules (NDC 69539-042-61)Store in original container bottle of 500 capsules (NDC 69539-042-05) 240 mg capsules: bottle of 60 capsules (NDC 69539-043-60)Store in original container bottle of 500 capsules (NDC 69539-043-05) Store at 15°C to 30°C (59 to 86°F).
Protect the capsules from light.
📋 Description ▾
11 DESCRIPTION Dimethyl fumarate delayed-release capsule contains dimethyl fumarate which is also known by its chemical name, dimethyl (E) butenedioate, (C 6 H 8 O 4 ). It has the following structure: Dimethyl fumarate is a white to off-white powder that is freely soluble in dichloromethane and very slightly soluble in water with a molecular mass of 144.13. Dimethyl fumarate is provided as hard gelatin delayed-release capsules for oral administration, containing 120 mg or 240 mg of dimethyl fumarate consisting of the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, methacrylic acid-ethyl acrylate copolymer, methacrylic acid methyl methacrylate copolymer, microcrystalline cellulose, polysorbate 80, sodium lauryl sulfate, talc and triethyl citrate.
The capsule shell contains the following inactive ingredients: gelatin and titanium dioxide and is imprinted with black ink, Black imprinting ink contains shellac, propylene glycol, black iron oxide and potassium hydroxide. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information) Dosage Inform patients that they will be provided two strengths of dimethyl fumarate when starting treatment: 120 mg capsules for the 7 day starter dose and 240 mg capsules for the maintenance dose, both to be taken twice daily. Inform patients to swallow dimethyl fumarate capsules whole and intact. Inform patients to not crush, chew, or sprinkle capsule contents on food.
Inform patients that dimethyl fumarate can be taken with or without food [see Dosage and Administration (2.1) ]. Anaphylaxis and Angioedema Advise patients to discontinue dimethyl fumarate and seek medical care if they develop signs and symptoms of anaphylaxis or angioedema [see Warnings and Precautions (5.1) ]. Progressive Multifocal Leukoencephalopathy Inform patients that progressive multifocal leukoencephalopathy (PML) has occurred in patients who received dimethyl fumarate.
Inform the patient that PML is characterized by a progression of deficits and usually leads to death or severe disability over weeks or months. Instruct the patient of the importance of contacting their doctor if they develop any symptoms suggestive of PML. Inform the patient that typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes [see Warnings and Precautions (5.2) ].
Herpes Zoster and Other Serious Opportunistic Infections Inform patients that herpes zoster and other serious opportunistic infections have occurred in patients who received dimethyl fumarate. Instruct the patient of the importance of contacting their doctor if they develop any signs or symptoms associated with herpes zoster or other serious opportunistic infections [ see Warnings and Precautions (5.3) ] . Lymphocyte Counts Inform patients that dimethyl fumarate may decrease lymphocyte counts.
A blood test should be obtained before they start therapy. Blood tests are also recommended after 6 months of treatment, every 6 to 12 months thereafter, and as clinically indicated [ see Warnings and Precautions (5.4) , Adverse Reactions (6.1) ]. Liver Injury Inform patients that dimethyl fumarate may cause liver injury.
Instruct patients treated with dimethyl fumarate to report promptly any symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice. A blood test should be obtained before patients start therapy and during treatment, as clinically indicated [ see Warnings and Precautions (5.5) ]. Flushing and Gastrointestinal (GI) Reactions Flushing and GI reactions (abdominal pain, diarrhea, and nausea) are the most common reactions, especially at the initiation of therapy, and may decrease over time.
Advise patients to contact their healthcare provider if they experience persistent and/or severe flushing or GI reactions. Advise patients experiencing flushing that taking dimethyl fumarate with food or taking a non-enteric coated aspirin prior to taking dimethyl fumarate may help [see Adverse Reactions (6.1) ]. Pregnancy Instruct patients that if they are pregnant or plan to become pregnant while taking dimethyl fumarate they should inform their physician.
Manufactured by: MSN Laboratories Private Limited Telangana – 509 228, INDIA Distributed by: MSN Pharmaceuticals Inc. Piscataway, NJ 08854-3714 Issued on: May 2021