
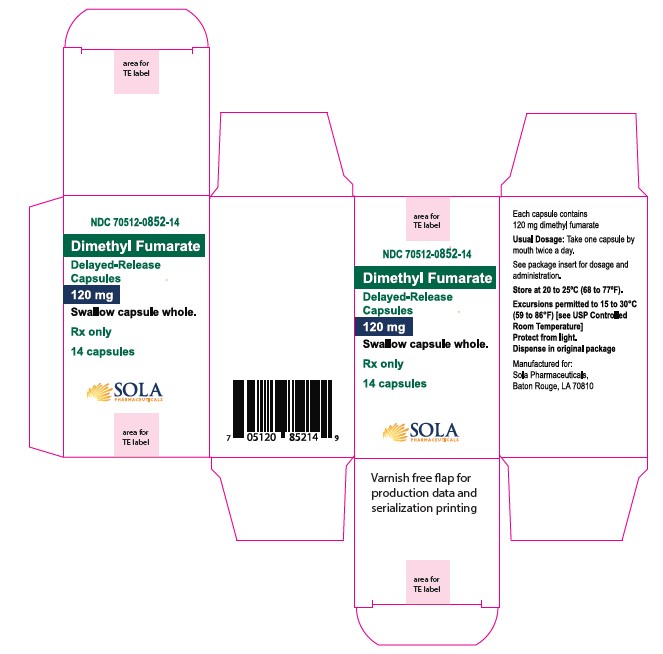
Dimethyl Fumarate 120 mg Capsule, Delayed Release, 14-count — NDC 70512-852-14 (Billing 70512-0852-14)
This is a package of 14 capsules of Dimethyl Fumarate 120 mg Capsule, Delayed Release from SOLA Pharmaceuticals, LLC, marketed since Jan 2023 and currently FDA-listed; retail pharmacies pay about $0.4284 per capsule (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 070786
- GCN: 34434
- GPI-14 (Medi-Span): 62405525006520
- HICL (First Databank): 040168
- AHFS class code: 90:04.08.00
- RxCUI (RxNorm): 1373483
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Other immunosuppressants class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Dimethyl fumarate is used to treat adults with relapsing forms of multiple sclerosis (MS; a disease in which the nerves do not function properly and people may experience weakness, numbness, loss of muscle coordination, and problems with vision, speech, and bladder control) including clinically isolated syndrome (CIS; nerve symptom episodes that last at least 24 hours), relapsing-remitting forms (course of disease where symptoms flare up from time to time), or secondary progressive forms (course of disease where relapses occur more often). Dimethyl fumarate is in a class of medications called...
Read the full MedlinePlus article ↗- The oral capsules are for relapsing forms of multiple sclerosis in adults. That includes clinically isolated syndrome, relapsing-remitting disease and active secondary progressive...
- You take them by mouth twice a day. Most people start on a lower dose for the first week and then move up. Swallow them whole, and do not crush, chew or sprinkle them on food. Take...
- Flushing is the most common, along with stomach pain, diarrhea and nausea. Taking the capsules with food can help the flushing. Your doctor may also suggest a non-enteric coated as...
- Get emergency help for swelling of the face, lips or throat or trouble breathing, and do not take another dose. Call right away for new neurologic symptoms, signs of a serious infe...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Dimethyl Fumarate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.428 | $6.00 / 14 capsules |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.89 | $26.39 / 14 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70512-0852-14 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 14 CAPSULE, DELAYED RELEASE in 1 BOTTLE | 2023-03-12 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dimethyl Fumarate 120 mg 31722-0657-31 | Camber | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 43547-0024-14 | Solco | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 43598-0429-52 | Dr. | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 59651-0083-14 | Aurobindo | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 69097-0322-89 | Cipla | 14 capsules | $0.428 | — | Availability likely | — |
| Dimethyl Fumarate 120 mg 69238-1318-04 | Amneal | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mgthis 70512-0852-14 | SOLA | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl fumarate 120 mg 82249-0745-14 | CivicaScript | 14 capsules | $0.428 | AB | Availability likely | — |
| Dimethyl Fumarate 120 mg 16729-0416-04 | Accord | 14 capsules | $0.617 | AB | Availability likely | +44% |
| dimethyl fumarate 120 mg 24979-0127-02 | Upsher-Smith | 500 capsules | — | AB | FDA listed | — |
| Dimethyl Fumarate 120 mg 33342-0349-09 | Macleods | 60 capsules | — | AB | FDA listed | — |
| dimethyl fumarate 120 mg 51407-0442-14 | Golden | 14 capsules | — | AB | FDA listed | — |
| Tecfidera 120 mg 64406-0005-01 | Biogen | 14 capsules | — | AB | FDA listed | — |
| Dimethyl fumarate 120 mg 67877-0555-10 | Ascend | 1000 capsules | — | AB | FDA listed | — |
| Dimethyl Fumarate 120 mg 68462-0307-05 | Glenmark | 500 capsules | — | AB | FDA listed | — |
| Dimethyl Fumarate 120 mg 69539-0042-05 | MSN | 500 capsules | — | AB | FDA listed | — |
| dimethyl fumarate 120 mg 70710-1204-07 | Zydus | 14 capsules | — | — | FDA listed | — |
| dimethyl fumarate 120 mg 70771-1530-07 | Zydus | 14 capsules | — | — | FDA listed | — |
| Dimethyl Fumarate 120 mg 84677-0029-14 | Golden | 14 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII T967IEU43C
A synthetic polymer made from methacrylic acid and ethyl acrylate. It forms a protective coating on tablets and capsules to control how and where the medicine dissolves in the digestive system.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Dimethyl fumarate delayed-release capsules are indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. Dimethyl fumarate delayed-release capsules are indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. ( 1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting dose: 120 mg twice a day, orally, for 7 days. (2.1) Maintenance dose after 7 days: 240 mg twice a day, orally. (2.1) Swallow dimethyl fumarate delayed-release capsules whole and intact. Do not crush, chew, or sprinkle capsule contents on food. (2.1) Take dimethyl fumarate delayed-release capsules with or without food. (2.1)
2.1Dosing Information The starting dose for dimethyl fumarate delayed-release capsules are 120 mg twice a day orally. After 7 days, the dose should be increased to the maintenance dose of 240 mg twice a day orally. Temporary dose reductions to 120 mg twice a day may be considered for individuals who do not tolerate the maintenance dose.
Within 4 weeks, the recommended dose of 240 mg twice a day should be resumed. Discontinuation of dimethyl fumarate delayed-release capsules should be considered for patients unable to tolerate return to the maintenance dose. The incidence of flushing may be reduced by administration of dimethyl fumarate delayed-release capsules with food.
Alternatively, administration of non-enteric coated aspirin (up to a dose of 325 mg) 30 minutes prior to dimethyl fumarate delayed-release capsules dosing may reduce the incidence or severity of flushing [see Clinical Pharmacology ( 12.3 ) ] . Dimethyl fumarate delayed-release capsules should be swallowed whole and intact. Dimethyl fumarate delayed-release capsules should not be crushed or chewed and the capsule contents should not be sprinkled on food.
Dimethyl fumarate delayed-release capsules can be taken with or without food.
2.2Blood Tests Prior to Initiation of Therapy Obtain a complete blood cell count (CBC) including lymphocyte count before initiation of therapy [ see Warnings and Precautions ( 5.4 ) ] . Obtain serum aminotransferase, alkaline phosphatase, and total bilirubin levels prior to treatment with dimethyl fumarate delayed-release capsules [ see Warnings and Precautions ( 5.5 ) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Dimethyl fumarate delayed-release capsules are available as hard gelatin delayed-release capsules containing 120 mg or 240 mg of dimethyl fumarate. The 120 mg capsules have a green cap and white body, printed with “120” in black ink on the body. The 240 mg capsules have a green cap and a green body, printed with “240” in black ink on the body.
Delayed-release capsules: 120 mg and 240 mg (3) Delayed-release capsules: 120 mg and 240 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Dimethyl fumarate delayed-release capsule are contraindicated in patients with known hypersensitivity to dimethyl fumarate or to any of the excipients of dimethyl fumarate delayed-release capsule. Reactions have included anaphylaxis and angioedema [ see Warnings and Precautions ( 5.1 ) ] . Known hypersensitivity to dimethyl fumarate or any of the excipients of dimethyl fumarate delayed-release capsules. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Anaphylaxis and angioedema: Discontinue and do not restart dimethyl fumarate delayed-release capsules if these occur. (5.1) Progressive multifocal leukoencephalopathy (PML): Withhold dimethyl fumarate delayed-release capsules at the first sign or symptom suggestive of PML. (5.2) Herpes zoster and other serious opportunistic infections: Consider withholding dimethyl fumarate delayed-release capsules in cases of serious infection until the infection has resolved.
(5.3) Lymphopenia: Obtain a CBC including lymphocyte count before initiating dimethyl fumarate delayed-release capsules, after 6 months, and every 6 to 12 months thereafter. Consider interruption of dimethyl fumarate delayed- release capsules if lymphocyte counts <0.5 x 10 9 /L persist for more than 6 months. (5.4) Liver injury: Obtain serum aminotransferase, alkaline phosphatase, and total bilirubin levels before initiating dimethyl fumarate delayed-release capsules and during treatment, as clinically indicated.
Discontinue dimethyl fumarate delayed-release capsules if clinically significant liver injury induced by dimethyl fumarate delayed-release capsules is suspected. (5.5)
5.1Anaphylaxis and Angioedema Dimethyl fumarate delayed-release capsules can cause anaphylaxis and angioedema after the first dose or at any time during treatment. Signs and symptoms have included difficulty breathing, urticaria, and swelling of the throat and tongue. Patients should be instructed to discontinue dimethyl fumarate delayed-release capsules and seek immediate medical care should they experience signs and symptoms of anaphylaxis or angioedema.
5.2Progressive Multifocal Leukoencephalopathy Progressive multifocal leukoencephalopathy (PML) has occurred in patients with MS treated with dimethyl fumarate delayed-release capsules. PML is an opportunistic viral infection of the brain caused by the JC virus (JCV) that typically only occurs in patients who are immunocompromised, and that usually leads to death or severe disability. A fatal case of PML occurred in a patient who received dimethyl fumarate delayed-release capsules for 4 years while enrolled in a clinical trial.
During the clinical trial, the patient experienced prolonged lymphopenia (lymphocyte counts predominantly <0.5x10 9 /L for 3.5 years) while taking dimethyl fumarate delayed-release capsules [ see Warnings and Precautions ( 5.4 ) ]. The patient had no other identified systemic medical conditions resulting in compromised immune system function and had not previously been treated with natalizumab, which has a known association with PML. The patient was also not taking any immunosuppressive or immunomodulatory medications concomitantly.
PML has also occurred in the postmarketing setting in the presence of lymphopenia (<0.9x10 9 /L). While the role of lymphopenia in these cases is uncertain, the PML cases have occurred predominantly in patients with lymphocyte counts <0.8x10 9 /L persisting for more than 6 months. At the first sign or symptom suggestive of PML, withhold dimethyl fumarate delayed-release capsules and perform an appropriate diagnostic evaluation.
Typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes. MRI findings may be apparent before clinical signs or symptoms. Cases of PML, diagnosed based on MRI findings and the detection of JCV DNA in the cerebrospinal fluid in the absence of clinical signs or symptoms specific to PML, have been reported in patients treated with other MS medications associated with PML.
Many of these patients subsequently became symptomatic with PML. Therefore, monitoring with MRI for signs that may be consistent with PML may be useful, and any suspicious findings should lead to further investigation to allow for an early diagnosis of PML, if… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described elsewhere in labeling: Anaphylaxis and Angioedema [ see Warnings and Precautions ( 5.1 ) Progressive multifocal leukoencephalopathy [ see Warnings and Precautions ( 5.2 ) ] Herpes Zoster and Other Serious Opportunistic Infections [ see Warnings and Precautions ( 5.3 ) ] Lymphopenia [ see Warnings and Precautions ( 5.4 ) ] Liver Injury [ see Warnings and Precautions ( 5.5 ) ] Flushing [ see Warnings and Precautions ( 5.6 ) ] Most common adverse reactions (incidence ≥ 10% and ≥ 2% placebo) were flushing, abdominal pain, diarrhea, and nausea.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Sola Pharmaceuticals at 1- 866-747-7365 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In placebo-controlled and uncontrolled clinical studies, a total of 2513 patients have received dimethyl fumarate delayed-release capsules and been followed for periods up to 13 years with an overall exposure of 11,318 person-years.
Approximately 1169 patients have received more than 5 years treatment with dimethyl fumarate delayed-release capsules, and 426 patients have received at least 10 years of treatment with dimethyl fumarate delayed-release capsules. Adverse Reactions in Placebo-Controlled Trials In the two well-controlled studies demonstrating effectiveness, 1,529 patients received dimethyl fumarate delayed-release capsules with an overall exposure of 2,244 person-years [ see Clinical Studies ( 14 ) ]. The adverse reactions presented in the table below are based on safety information from 769 patients treated with dimethyl fumarate delayed-release capsules 240 mg twice a day and 771 placebo-treated patients.
The most common adverse reactions (incidence ≥10% and ≥2% more than placebo) for dimethyl fumarate delayed-release capsules were flushing, abdominal pain, diarrhea, and nausea. Table 1: Adverse Reactions in Study 1 and 2 reported for Dimethyl Fumarate240 mg BID at ≥ 2% higher incidence than placebo Dimethyl Fumarate N=769% Placebo N=771% Flushing 40 6 Abdominal pain 18 10 Diarrhea 14 11 Nausea 12 9 Vomiting 9 5 Pruritus 8 4 Rash 8 3 Albumin urine present 6 4 Erythema 5 1 Dyspepsia 5 3 Aspartate aminotransferase increased 4 2 Lymphopenia 2 < 1 Gastrointestinal Dimethyl fumarate delayed-release capsules caused GI events (e.g., nausea, vomiting, diarrhea, abdominal pain, and dyspepsia).
The incidence of GI events was higher early in the course of treatment (primarily in month 1) and usually decreased over time in patients treated with dimethyl fumarate delayed-release capsules compared with placebo. Four percent (4%) of patients treated with dimethyl fumarate delayed-release capsules and less than 1% of placebo patients discontinued due to gastrointestinal events. The incidence of serious GI events was 1% in patients treated with dimethyl fumarate delayed-release capsules.
Hepatic Transaminases An increased incidence of elevations of hepatic transaminases in patients treated with dimethyl fumarate delayed-release capsules was seen primarily during the first six months of treatment, and most patients with elevations had levels < 3 times the upper limit of normal (ULN) during controlled trials. Elevations of alanine aminotransferase and aspartate aminotransferase to ≥ 3 times the ULN occurred in a small number of patients treated with both dimethyl fumarate delayed-release capsules and placebo and were balanced between groups.
There were no elevations in transaminases ≥ 3 times the ULN with concomitant elevations in total bilirubin > 2 times the ULN. Discontinuations due to elevated hepatic transaminases were < 1% and were similar in patients treated with dimethyl fumarate d… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. (8.1)
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of dimethyl fumarate delayed-release capsules in pregnant women. In animals, adverse effects on offspring survival, growth, sexual maturation, and neurobehavioral function were observed when dimethyl fumarate (DMF) was administered during pregnancy and lactation at clinically relevant doses [ see Data ]. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data In rats administered DMF orally (25, 100, 250 mg/kg/day) throughout organogenesis, embryofetal toxicity (reduced fetal body weight and delayed ossification) were observed at the highest dose tested. This dose also produced evidence of maternal toxicity (reduced body weight).
Plasma exposure (AUC) for monomethyl fumarate (MMF), the major circulating metabolite, at the no-effect dose is approximately three times that in humans at the recommended human dose (RHD) of 480 mg/day. In rabbits administered DMF orally (25, 75, and 150 mg/kg/day) throughout organogenesis, embryolethality and decreased maternal body weight were observed at the highest dose tested. The plasma AUC for MMF at the no-effect dose is approximately 5 times that in humans at the RHD.
Oral administration of DMF (25, 100, and 250 mg/kg/day) to rats throughout organogenesis and lactation resulted in increased lethality, persistent reductions in body weight, delayed sexual maturation (male and female pups), and reduced testicular weight at the highest dose tested. Neurobehavioral impairment was observed at all doses. A no-effect dose for developmental toxicity was not identified.
The lowest dose tested was associated with plasma AUC for MMF lower than that in humans at the RHD.
8.2Lactation Risk Summary There are no data on the presence of DMF or MMF in human milk. The effects on the breastfed infant and on milk production are unknown. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for dimethyl fumarate delayed-release capsules and any potential adverse effects on the breastfed infant from the drug or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of dimethyl fumarate delayed-release capsules did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of dimethyl fumarate delayed-release capsules in pregnant women. In animals, adverse effects on offspring survival, growth, sexual maturation, and neurobehavioral function were observed when dimethyl fumarate (DMF) was administered during pregnancy and lactation at clinically relevant doses [ see Data ]. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data In rats administered DMF orally (25, 100, 250 mg/kg/day) throughout organogenesis, embryofetal toxicity (reduced fetal body weight and delayed ossification) were observed at the highest dose tested. This dose also produced evidence of maternal toxicity (reduced body weight).
Plasma exposure (AUC) for monomethyl fumarate (MMF), the major circulating metabolite, at the no-effect dose is approximately three times that in humans at the recommended human dose (RHD) of 480 mg/day. In rabbits administered DMF orally (25, 75, and 150 mg/kg/day) throughout organogenesis, embryolethality and decreased maternal body weight were observed at the highest dose tested. The plasma AUC for MMF at the no-effect dose is approximately 5 times that in humans at the RHD.
Oral administration of DMF (25, 100, and 250 mg/kg/day) to rats throughout organogenesis and lactation resulted in increased lethality, persistent reductions in body weight, delayed sexual maturation (male and female pups), and reduced testicular weight at the highest dose tested. Neurobehavioral impairment was observed at all doses. A no-effect dose for developmental toxicity was not identified.
The lowest dose tested was associated with plasma AUC for MMF lower than that in humans at the RHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of dimethyl fumarate delayed-release capsules did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients.
🆘 Overdosage ▾
10 OVERDOSE Cases of overdose with dimethyl fumarate delayed-release capsules have been reported. The symptoms described in these cases were consistent with the known adverse event profile of dimethyl fumarate delayed-release capsules. There are no known therapeutic interventions to enhance elimination of dimethyl fumarate delayed-release capsules nor is there a known antidote.
In the event of overdose, initiate symptomatic supportive treatment as clinically indicated.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism by which dimethyl fumarate (DMF) exerts its therapeutic effect in multiple sclerosis is unknown. DMF and the metabolite, monomethyl fumarate (MMF), have been shown to activate the Nuclear factor (erythroid-derived 2)-like 2 (Nrf2) pathway in vitro and in vivo in animals and humans. The Nrf2 pathway is involved in the cellular response to oxidative stress.
MMF has been identified as a nicotinic acid receptor agonist in vitro .
12.2Pharmacodynamics Potential to prolong the QT interval In a placebo controlled thorough QT study performed in healthy subjects, there was no evidence that dimethyl fumarate caused QT interval prolongation of clinical significance (i.e., the upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 ms).
12.3Pharmacokinetics After oral administration of dimethyl fumarate delayed-release capsules, dimethyl fumarate undergoes rapid presystemic hydrolysis by esterases and is converted to its active metabolite, monomethyl fumarate (MMF). Dimethyl fumarate is not quantifiable in plasma following oral administration of dimethyl fumarate delayed-release capsules. Therefore all pharmacokinetic analyses related to dimethyl fumarate delayed-release capsules were performed with plasma MMF concentrations.
Pharmacokinetic data were obtained in subjects with multiple sclerosis and healthy volunteers. Absorption The median T max of MMF is 2 to 2.5 hours. The peak plasma concentration (C max ) and overall exposure (AUC) increased approximately dose proportionally in the dose range studied (120 mg to 360 mg).
Following administration of dimethyl fumarate delayed-release capsules, 240 mg twice a day with food, the mean C max of MMF was 1.87 mg/L and AUC was 8.21 mg.hr/L in MS patients. A high-fat, high-calorie meal did not affect the AUC of MMF but decreased its C max by 40%. The T max was delayed from 2.0 hours to 5.5 hours.
In this study, the incidence of flushing was reduced by approximately 25% in the fed state. Distribution The apparent volume of distribution of MMF varies between 53 L and 73 L in healthy subjects. Human plasma protein binding of MMF is 27% to 45% and independent of concentration.
Metabolism In humans, dimethyl fumarate is extensively metabolized by esterases, which are ubiquitous in the gastrointestinal tract, blood, and tissues, before it reaches the systemic circulation. Further metabolism of MMF occurs through the tricarboxylic acid (TCA) cycle, with no involvement of the cytochrome P450 (CYP) system. MMF, fumaric and citric acid, and glucose are the major metabolites in plasma.
Elimination Exhalation of CO2 is the primary route of elimination, accounting for approximately 60% of the dimethyl fumarate delayed-release capsules dose. Renal and fecal elimination are minor routes of elimination, accounting for 16% and 1% of the dose respectively. Trace amounts of unchanged MMF were present in urine.
The terminal half-life of MMF is approximately 1 hour and no circulating MMF is present at 24 hours in the majority of individuals. Accumulation of MMF does not occur with multiple doses of dimethyl fumarate delayed-release capsules. Specific Populations Body weight, gender, and age do not require dosage adjustment.
No studies have been conducted in subjects with hepatic or renal impairment. However, neither condition would be expected to affect exposure to MMF and therefore no dosage adjustment is necessary. Drug Interaction Studies No potential drug interactions with dimethyl fumarate or MMF were identified in in vitro CYP inhibition and induction studies, or in P-glycoprotein studies.
Single doses of interferon beta-1a or glatiramer acetate did not alter the pharmacokinetics of MMF. Aspirin, when administered approximately 30 minutes before dimethyl fumarate delayed-release capsules, did not alter the pharmacokinetics of MMF. Oral Contraceptives The co-administration of dimethyl fuma… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism by which dimethyl fumarate (DMF) exerts its therapeutic effect in multiple sclerosis is unknown. DMF and the metabolite, monomethyl fumarate (MMF), have been shown to activate the Nuclear factor (erythroid-derived 2)-like 2 (Nrf2) pathway in vitro and in vivo in animals and humans. The Nrf2 pathway is involved in the cellular response to oxidative stress.
MMF has been identified as a nicotinic acid receptor agonist in vitro .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGEAND HANDLING Dimethyl fumarate delayed-release capsules are available as hard gelatin delayed-release capsules in two strengths containing either 120 mg or 240 mg of dimethyl fumarate. The green and white 120 mg capsules are printed with “120” in black ink. The green 240 mg capsules are printed with “240” in black ink.
Dimethyl fumarate delayed-release capsules are available as follows: 30-day Starter Pack, (NDC 70512-858-60): 7-day bottle 120 mg capsules, quantity 14 23-day bottle 240 mg capsules, quantity 46 120 mg capsules: 7-day bottle of 14 capsules (NDC 70512-852-14) 240 mg capsules: 30-day bottle of 60 capsules (NDC 70512-853-60) Store at 20°C to 25°C (68°F to 77°F). Excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Protect the capsules from light.
Store in original container.
📋 Description ▾
11 DESCRIPTION Dimethyl fumarate delayed-released capsules contain dimethyl fumarate which is also known by its chemical name, dimethyl (E) butenedioate, (C 6 H 8 O 4 ). It has the following structure: Dimethyl fumarate is a white to off-white powder that is highly soluble in water with a molecular mass of 144.13. Dimethyl fumarate delayed-release capsules are provided as hard gelatin delayed-release capsules for oral administration, containing 120 mg or 240 mg of dimethyl fumarate consisting of the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, ethyl alcohol 96%, magnesium stearate, methacrylic acid and ethyl acrylate copolymer dispersion, methacrylic acid and methyl methacrylate copolymer (1:1), microcrystalline cellulose, purified water, talc, and triethyl citrate.
The capsule shell, printed with black ink, contains the following inactive ingredients: FD&C Blue No. 1, gelatin, iron oxide black, iron oxide yellow, and titanium dioxide. 10
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Dosage Inform patients that they will be provided two strengths of dimethyl fumarate delayed-release capsules when starting treatment: 120 mg capsules for the 7-day starter dose and 240 mg capsules for the maintenance dose, both to be taken twice daily. Inform patients to swallow dimethyl fumarate delayed-release capsules whole and intact.
Inform patients to not crush, chew, or sprinkle capsule contents on food. Inform patients that dimethyl fumarate delayed-release capsules can be taken with or without food [ see Dosage and Administration ( 2.1 ) ]. Anaphylaxis and Angioedema Advise patients to discontinue dimethyl fumarate delayed-release capsules and seek medical care if they develop signs and symptoms of anaphylaxis or angioedema [ see Warnings and Precautions ( 5.1 ) ].
Progressive Multifocal Leukoencephalopathy Inform patients that progressive multifocal leukoencephalopathy (PML) has occurred in patients who received dimethyl fumarate delayed-release capsules. Inform the patient that PML is characterized by a progression of deficits and usually leads to death or severe disability over weeks or months. Instruct the patient of the importance of contacting their doctor if they develop any symptoms suggestive of PML.
Inform the patient that typical symptoms associated with PML are diverse, progress over days to weeks, and include progressive weakness on one side of the body or clumsiness of limbs, disturbance of vision, and changes in thinking, memory, and orientation leading to confusion and personality changes [ see Warnings and Precautions ( 5.2 ) ]. Herpes Zoster and Other Serious Opportunistic Infections Inform patients that herpes zoster and other serious opportunistic infections have occurred in patients who received dimethyl fumarate delayed-release capsules.
Instruct the patient of the importance of contacting their doctor if they develop any signs or symptoms associated with herpes zoster or other serious opportunistic infections [ see Warnings and Precautions ( 5.3 ) ]. Lymphocyte Counts Inform patients that dimethyl fumarate delayed-release capsules may decrease lymphocyte counts. A blood test should be obtained before they start therapy.
Blood tests are also recommended after 6 months of treatment, every 6 to 12 months thereafter, and as clinically indicated [ see Warnings and Precautions ( 5.4 ), Adverse Reactions ( 6.1 ) ]. Liver Injury Inform patients that dimethyl fumarate delayed-release capsules may cause liver injury. Instruct patients treated with dimethyl fumarate delayed-release capsules to report promptly any symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine, or jaundice.
A blood test should be obtained before patients start therapy and during treatment, as clinically indicated [ see Warnings and Precautions ( 5.5 ) ]. Flushing and Gastrointestinal (GI) Reactions Flushing and GI reactions (abdominal pain, diarrhea, and nausea) are the most common reactions, especially at the initiation of therapy, and may decrease over time. Advise patients to contact their healthcare provider if they experience persistent and/or severe flushing or GI reactions.
Advise patients experiencing flushing that taking dimethyl fumarate delayed-release capsules with food or taking a non-enteric coated aspirin prior to taking dimethyl fumarate delayed-release capsules may help [ see Adverse Reactions ( 6.1 ) ]. Pregnancy Instruct patients that if they are pregnant or plan to become pregnant while taking dimethyl fumarate delayed-release capsules they should inform their physician. Manufactured for: Sola Pharmaceuticals Baton Rouge, LA 70810
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics After oral administration of dimethyl fumarate delayed-release capsules, dimethyl fumarate undergoes rapid presystemic hydrolysis by esterases and is converted to its active metabolite, monomethyl fumarate (MMF). Dimethyl fumarate is not quantifiable in plasma following oral administration of dimethyl fumarate delayed-release capsules. Therefore all pharmacokinetic analyses related to dimethyl fumarate delayed-release capsules were performed with plasma MMF concentrations.
Pharmacokinetic data were obtained in subjects with multiple sclerosis and healthy volunteers. Absorption The median T max of MMF is 2 to 2.5 hours. The peak plasma concentration (C max ) and overall exposure (AUC) increased approximately dose proportionally in the dose range studied (120 mg to 360 mg).
Following administration of dimethyl fumarate delayed-release capsules, 240 mg twice a day with food, the mean C max of MMF was 1.87 mg/L and AUC was 8.21 mg.hr/L in MS patients. A high-fat, high-calorie meal did not affect the AUC of MMF but decreased its C max by 40%. The T max was delayed from 2.0 hours to 5.5 hours.
In this study, the incidence of flushing was reduced by approximately 25% in the fed state. Distribution The apparent volume of distribution of MMF varies between 53 L and 73 L in healthy subjects. Human plasma protein binding of MMF is 27% to 45% and independent of concentration.
Metabolism In humans, dimethyl fumarate is extensively metabolized by esterases, which are ubiquitous in the gastrointestinal tract, blood, and tissues, before it reaches the systemic circulation. Further metabolism of MMF occurs through the tricarboxylic acid (TCA) cycle, with no involvement of the cytochrome P450 (CYP) system. MMF, fumaric and citric acid, and glucose are the major metabolites in plasma.
Elimination Exhalation of CO2 is the primary route of elimination, accounting for approximately 60% of the dimethyl fumarate delayed-release capsules dose. Renal and fecal elimination are minor routes of elimination, accounting for 16% and 1% of the dose respectively. Trace amounts of unchanged MMF were present in urine.
The terminal half-life of MMF is approximately 1 hour and no circulating MMF is present at 24 hours in the majority of individuals. Accumulation of MMF does not occur with multiple doses of dimethyl fumarate delayed-release capsules. Specific Populations Body weight, gender, and age do not require dosage adjustment.
No studies have been conducted in subjects with hepatic or renal impairment. However, neither condition would be expected to affect exposure to MMF and therefore no dosage adjustment is necessary. Drug Interaction Studies No potential drug interactions with dimethyl fumarate or MMF were identified in in vitro CYP inhibition and induction studies, or in P-glycoprotein studies.
Single doses of interferon beta-1a or glatiramer acetate did not alter the pharmacokinetics of MMF. Aspirin, when administered approximately 30 minutes before dimethyl fumarate delayed-release capsules, did not alter the pharmacokinetics of MMF. Oral Contraceptives The co-administration of dimethyl fumarate with a combined oral contraceptive (norelgestromin and ethinyl estradiol) did not elicit any relevant effects in oral contraceptives exposure.
No interaction studies have been performed with oral contraceptives containing other progestogens. Vaccines A randomized, open-label study examined the concomitant use of dimethyl fumarate delayed-release capsules and several non-live vaccines in adults 27-55 years of age with relapsing forms if MS (38 subjects undergoing treatment with dimethyl fumarate delayed-release capsules at the time of vaccination and 33 subjects undergoing treatment with non-pegylated interferon at the time of vaccination). Concomitant exposure to dimethyl fumarate delayed-release capsules did not attenuate antibody responses to tetanus toxoid-containing vaccine, pneumococcal polysaccharide, and meningococcal vaccines relati… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Potential to prolong the QT interval In a placebo controlled thorough QT study performed in healthy subjects, there was no evidence that dimethyl fumarate caused QT interval prolongation of clinical significance (i.e., the upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 ms).
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy and safety of dimethyl fumarate delayed-release capsules were demonstrated in two studies (Studies 1 and 2) that evaluated dimethyl fumarate delayed-release capsules taken either twice or three times a day in patients with relapsing-remitting multiple sclerosis (RRMS). The starting dose for dimethyl fumarate delayed-release capsules was 120 mg twice or three times a day for the first 7 days, followed by an increase to 240 mg twice or three times a day. Both studies included patients who had experienced at least 1 relapse over the year preceding the trial or had a brain Magnetic Resonance Imaging (MRI) scan demonstrating at least one gadolinium- enhancing (Gd+) lesion within 6 weeks of randomization.
The Expanded Disability Status Scale (EDSS) was also assessed and patients could have scores ranging from 0 to 5. Neurological evaluations were performed at baseline, every 3 months, and at the time of suspected relapse. MRI evaluations were performed at baseline, month 6, and year 1 and 2 in a subset of patients (44% in Study 1 and 48% in Study 2).
Study 1: Placebo-Controlled Trial in RRMS Study 1 was a 2-year randomized, double-blind, placebo-controlled study in 1,234 patients with RRMS. The primary endpoint was the proportion of patients relapsed at 2 years. Additional endpoints at 2 years included the number of new or newly enlarging T2 hyperintense lesions, number of new T1 hypointense lesions, number of Gd+ lesions, annualized relapse rate (ARR), and time to confirmed disability progression.
Confirmed disability progression was defined as at least a 1 point increase from baseline EDSS (1.5 point increase for patients with baseline EDSS of 0) sustained for 12 weeks. Patients were randomized to receive dimethyl fumarate delayed-release capsules 240 mg twice a day (n=410), dimethyl fumarate delayed-release capsules 240 mg three times a day (n=416), or placebo (n=408) for up to 2 years. The median age was 39 years, median time since diagnosis was 4 years, and median EDSS score at baseline was 2.
The median time on study drug for all treatment arms was 96 weeks. The percentages of patients who completed 96 weeks on study drug per treatment group were 69% for patients assigned to dimethyl fumarate delayed-release capsules 240 mg twice a day, 69% for patients assigned to dimethyl fumarate delayed-release capsules 240 mg three times a day and 65% for patients assigned to placebo groups. Dimethyl fumarate delayed-release capsules had a statistically significant effect on all of the endpoints described above and the 240 mg three times daily dose showed no additional benefit over the dimethyl fumarate delayed-release capsules 240 mg twice daily dose.
The results for this study (240 mg twice a day vs. placebo) are shown in Table 2 and Figure 1 . Table 2: Clinical and MRI Results of Study 1 Dimethyl Fumarate 240 mg BID Placebo P-value Clinical Endpoints N=410 N=408 Proportion relapsing (primary endpoint) 27% 46% <0.0001 Relative risk reduction 49% Annualized relapse rate 0.172 0.364 <0.0001 Relative reduction 53% Proportion with disability progression 16% 27% 0.0050 Relative risk reduction 38% MRI Endpoints N=152 N=165 Mean number of new or newly enlarging T2 lesions over 2 years 2.6 17 <0.0001 Percentage of subjects with no new or newly enlarging lesions 45% 27% Number of Gd+ lesions at 2 years Mean (median) 0.1 (0) 1.8 (0) Percentage of subjects with 0 lesions 1 lesion 2 lesions 3 to 4 lesions 5 or more lesions 93% 5% <1% 0 <1% 62% 10% 8% 9% 11% Relative odds reduction (percentage) 90% <0.0001 Mean number of new T1 hypointense lesions over 2 years 1.5 5.6 <0.0001 Figure 1: Time to 12-Week Confirmed Progression of Disability (Study 1) Study 2: Placebo-Controlled Trial in RRMS Study 2 was a 2-year multicenter, randomized, double-blind, placebo-controlled study that also included an open-label comparator arm in patients with RRMS.
The primary endpoint was the annualized relapse rate at 2 years. Additional e… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Carcinogenicity studies of dimethyl fumarate (DMF) were conducted in mice and rats. In mice, oral administration of DMF (25, 75, 200, and 400 mg/kg/day) for up to two years resulted in an increase in nonglandular stomach (forestomach) and kidney tumors: squamous cell carcinomas and papillomas of the forestomach in males and females at 200 and 400 mg/kg/day; leiomyosarcomas of the forestomach at 400 mg/kg/day in males and females; renal tubular adenomas and carcinomas at 200 and 400 mg/kg/day in males; and renal tubule adenomas at 400 mg/kg/day in females.
Plasma MMF exposure (AUC) at the highest dose not associated with tumors in mice (75 mg/kg/day) was similar to that in humans at the recommended human dose (RHD) of 480 mg/day. In rats, oral administration of DMF (25, 50, 100, and 150 mg/kg/day) for up to two years resulted in increases in squamous cell carcinomas and papillomas of the forestomach at all doses tested in males and females, and in testicular interstitial (Leydig) cell adenomas at 100 and 150mg/kg/day. Plasma MMF AUC at the lowest dose tested was lower than that in humans at the RHD.
Mutagenesis Dimethyl fumarate (DMF) and monomethyl fumarate (MMF) were not mutagenic in the in vitro bacterial reverse mutation (Ames) assay. DMF and MMF were clastogenic in the in vitro chromosomal aberration assay in human peripheral blood lymphocytes in the absence of metabolic activation. DMF was not clastogenic in the in vivo micronucleus assay in the rat.
Impairment of Fertility In male rats, oral administration of DMF (75, 250, and 375 mg/kg/day) prior to and throughout the mating period had no effect on fertility; however, increases in non-motile sperm were observed at the mid and high doses. The no-effect dose for adverse effects on sperm is similar to the recommended human dose (RHD) of 480 mg/day on a body surface area (mg/m 2 ) basis. In female rats, oral administration of DMF (20, 100, and 250 mg/kg/day) prior to and during mating and continuing to gestation day 7 caused disruption of the estrous cycle and increases in embryolethality at the highest dose tested.
The highest dose not associated with adverse effects (100 mg/kg/day) is twice the RHD on a mg/m 2 basis. Testicular toxicity (germinal epithelial degeneration, atrophy, hypospermia, and/or hyperplasia) was observed at clinically relevant doses in mice, rats, and dogs in subchronic and chronic oral toxicity studies of DMF, and in a chronic oral toxicity study evaluating a combination of four fumaric acid esters (including DMF) in rats.
13.2Animal Toxicology and/or Pharmacology Kidney toxicity was observed after repeated oral administration of dimethyl fumarate (DMF) in mice, rats, dogs, and monkeys. Renal tubule epithelia regeneration, suggestive of tubule epithelial injury, was observed in all species. Renal tubular hyperplasia was observed in rats with dosing for up to two years.
Cortical atrophy and interstitial fibrosis were observed in dogs and monkeys at doses above 5 mg/kg/day. In monkeys, the highest dose tested (75 mg/kg/day) was associated with single cell necrosis and multifocal and diffuse interstitial fibrosis, indicating irreversible loss of renal tissue and function. In dogs and monkeys, the 5 mg/kg/day dose was associated with plasma MMF exposures less than or similar to that in humans at the recommended human dose (RHD).
A dose-related increase in incidence and severity of retinal degeneration was observed in mice following oral administration of DMF for up to two years at doses above 75 mg/kg/day, a dose associated with plasma MMF exposure (AUC) similar to that in humans at the RHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Carcinogenicity studies of dimethyl fumarate (DMF) were conducted in mice and rats. In mice, oral administration of DMF (25, 75, 200, and 400 mg/kg/day) for up to two years resulted in an increase in nonglandular stomach (forestomach) and kidney tumors: squamous cell carcinomas and papillomas of the forestomach in males and females at 200 and 400 mg/kg/day; leiomyosarcomas of the forestomach at 400 mg/kg/day in males and females; renal tubular adenomas and carcinomas at 200 and 400 mg/kg/day in males; and renal tubule adenomas at 400 mg/kg/day in females.
Plasma MMF exposure (AUC) at the highest dose not associated with tumors in mice (75 mg/kg/day) was similar to that in humans at the recommended human dose (RHD) of 480 mg/day. In rats, oral administration of DMF (25, 50, 100, and 150 mg/kg/day) for up to two years resulted in increases in squamous cell carcinomas and papillomas of the forestomach at all doses tested in males and females, and in testicular interstitial (Leydig) cell adenomas at 100 and 150mg/kg/day. Plasma MMF AUC at the lowest dose tested was lower than that in humans at the RHD.
Mutagenesis Dimethyl fumarate (DMF) and monomethyl fumarate (MMF) were not mutagenic in the in vitro bacterial reverse mutation (Ames) assay. DMF and MMF were clastogenic in the in vitro chromosomal aberration assay in human peripheral blood lymphocytes in the absence of metabolic activation. DMF was not clastogenic in the in vivo micronucleus assay in the rat.
Impairment of Fertility In male rats, oral administration of DMF (75, 250, and 375 mg/kg/day) prior to and throughout the mating period had no effect on fertility; however, increases in non-motile sperm were observed at the mid and high doses. The no-effect dose for adverse effects on sperm is similar to the recommended human dose (RHD) of 480 mg/day on a body surface area (mg/m 2 ) basis. In female rats, oral administration of DMF (20, 100, and 250 mg/kg/day) prior to and during mating and continuing to gestation day 7 caused disruption of the estrous cycle and increases in embryolethality at the highest dose tested.
The highest dose not associated with adverse effects (100 mg/kg/day) is twice the RHD on a mg/m 2 basis. Testicular toxicity (germinal epithelial degeneration, atrophy, hypospermia, and/or hyperplasia) was observed at clinically relevant doses in mice, rats, and dogs in subchronic and chronic oral toxicity studies of DMF, and in a chronic oral toxicity study evaluating a combination of four fumaric acid esters (including DMF) in rats.
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 10/2022.
Patient Information Dimethyl Fumarate (dye METH il FUE ma rate) Delayed-Release Capsules What are dimethyl fumarate delayed-release capsules? Dimethyl fumarate delayed-release capsules are a prescription medicine used to treat relapsing forms of multiple sclerosis (MS), to include clinically isolated syndrome, relapsing-remitting disease, and active secondary progressive disease, in adults. It is not known if dimethyl fumarate delayed-release capsules are safe and effective in children under 18 years of age.
Who should not take dimethyl fumarate delayed-release capsules? Do not use dimethyl fumarate delayed-release capsules if you have had an allergic reaction (such as welts, hives, swelling of the face, lips, mouth or tongue, or difficulty breathing) to dimethyl fumarate delayed-release capsules or any of their ingredients. See below for a complete list of ingredients.
Before taking and while you take dimethyl fumarate delayed-release capsules, tell your doctor if you have or have had: low white blood cell counts or an infection any other medical conditions Tell your doctor if you are: pregnant or plan to become pregnant. It is not known if dimethyl fumarate delayed-release capsules will harm your unborn baby. breastfeeding or plan to breastfeed. It is not known if dimethyl fumarate delayed-release capsules pass into your breast milk.
You and your doctor should decide if you will take dimethyl fumarate delayed-release capsules or breastfeed. taking prescription or over-the-counter medicines, vitamins, or herbal supplements. How should I take dimethyl fumarate delayed-release capsules? Take dimethyl fumarate delayed-release capsules exactly as your doctor tells you to take them.
The recommended starting dose is one 120 mg capsule taken by mouth 2 times a day for 7 days. The recommended dose after 7 days is one 240 mg capsule taken by mouth 2 times a day Dimethyl fumarate delayed-release capsules can be taken with or without food. Swallow dimethyl fumarate delayed-release capsules whole.
Do not crush, chew, or sprinkle capsule contents on food. Protect dimethyl fumarate delayed-release capsules from light. You can do this by storing the capsules in their original container.
If you take too many dimethyl fumarate delayed-release capsules, call your doctor or go to the nearest hospital emergency room right away. What are the possible side effects of dimethyl fumarate delayed-release capsules? Dimethyl fumarate delayed-release capsules may cause serious side effects including: allergic reaction (such as welts, hives, swelling of the face, lips, mouth or tongue, or difficulty breathing).
PML a rare brain infection that usually leads to death or severe disability. decreases in your white blood cell count Your doctor should do a blood test before you start treatment with dimethyl fumarate delayed-release capsules and while on therapy. liver problems. YYour doctor should do blood tests to check your liver function before you start taking dimethyl fumarate delayed-release capsules and during treatment if needed. Tell your doctor right away if you get any of these symptoms of a liver problem during treatment. severe tiredness loss of appetite pain on the right side of your stomach have dark or brown (tea color) urine yellowing of your skin or the white part of your eyes herpes zoster infections (shingles), including central nervous system infections. other serious infections.
The most common side effects of dimethyl fumarate delayed-release capsules include : flushing, redness, itching, or rash nausea, vomiting, diarrhea, stomach pain, or indigestion Flushing and stomach problems are the most common reactions, especially at the start of therapy, and may decrease over time. Taking dimethyl fumarate delayed-release capsules with food may help reduce flushing. Call your doctor if you have any of these symptoms and they bother you or do no… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 70512-852-14 Dimethyl Fumarate Delayed-Release Capsules 120 mg Swallow capsule whole. Rx only 14 capsules SOLA PHARMACEUTICALS Each capsule contains 120 mg dimethyl fumarate Usual Dosage: Take one capsule by mouth twice a day. See package insert for dosage and administration.
Store at 20 to 25ºC (68 to 77ºF) Excursions permitted to 15 to 30ºC (59 to 86ºF) [see USP Controlled Room Temperature] Protect from light. Dispense in original package Manufactured for: Sola Pharmaceuticals, Baton Rouge, LA 70810 NDC 70512-852-14 Dimethyl Fumarate Delayed-Release Capsules 120 mg Swallow capsule whole. Rx only • 14 capsules SOLA PHARMACEUTICALS Each capsule contains 120 mg dimethyl fumarate Usual Dosage: Take one capsule by mouth twice a day.
See package insert for dosage and administration. Store at 20 to 25ºC (68 to 77ºF) Excursions permitted to 15 to 30ºC (59 to 86ºF) [see USP Controlled Room Temperature] Protect from light. Dispense in original package.
Manufactured for: Sola Pharmaceuticals, Baton Rouge, LA 70810 Lot: Exp: NDC 70512-853-60 Dimethyl Fumarate Delayed-Release Capsules 240 mg Swallow capsule whole. Rx only 60 capsules SOLA PHARMACEUTICALS Each capsule contains 240 mg dimethyl fumarate Usual Dosage: Take one capsule by mouth twice a day. See package insert for dosage and administration.
Store at 20 to 25ºC (68 to 77ºF) Excursions permitted to 15 to 30ºC (59 to 86ºF) [see USP Controlled Room Temperature] Protect from light. Dispense in original package. Manufactured for: Sola Pharmaceuticals, Baton Rouge, LA 70810 NDC 70512-853-60 Dimethyl Fumarate Delayed-Release Capsules 240 mg Swallow capsule whole.
Rx only 60 capsules SOLA PHARMACEUTICALS Each capsule contains 240 mg dimethyl fumarate Usual Dosage: Take one capsule by mouth twice a day. See package insert for dosage and administration. Store at 20 to 25ºC (68 to 77ºF).
Excursions permitted to 15 to 30ºC (59 to 86ºF) [see USP Controlled Room Temperature] Protect from Light. Dispense in original package. Manufactured for: Sola Pharmaceuticals, Baton Rouge, LA 70810 Lot: Exp: 70512-852-14 120 mg carton 70512-852-14 120 mg label 70512-853-carton 240 mg 70512-853-label 240 mg