
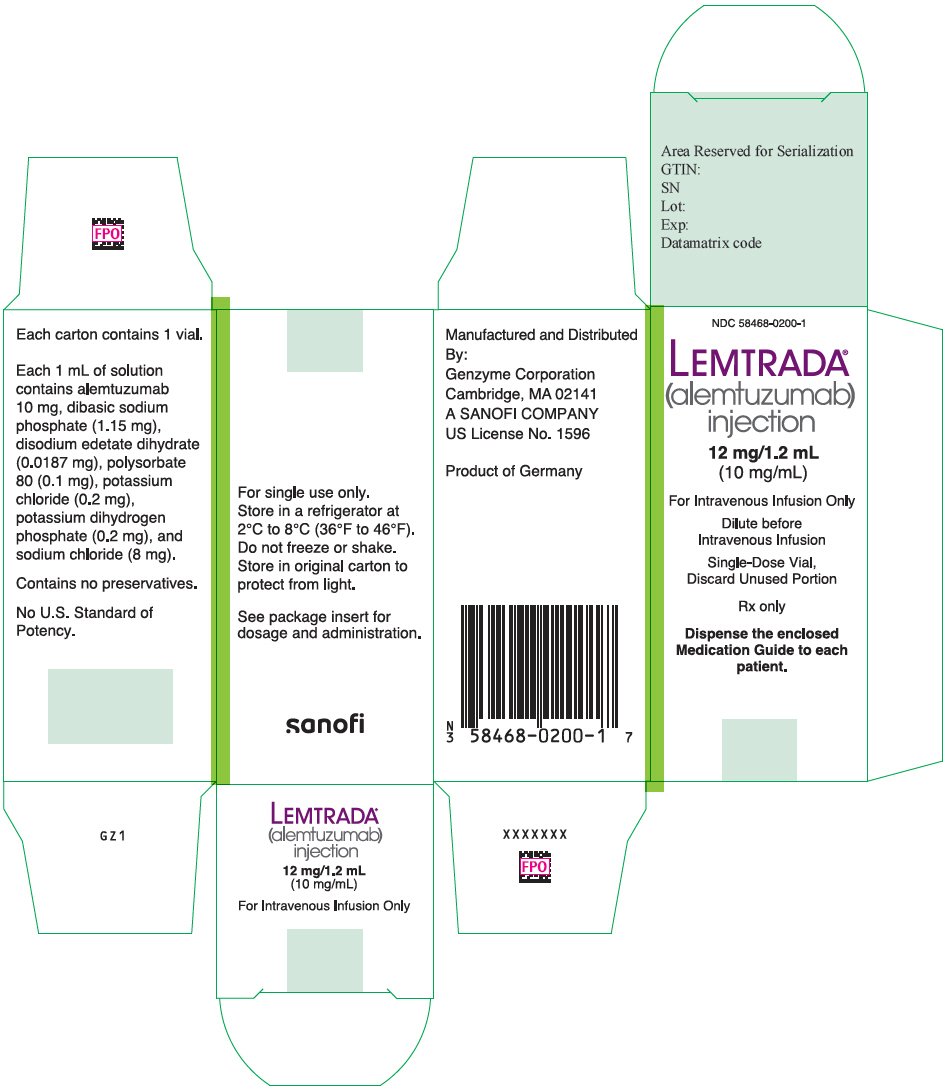
LEMTRADA ALEMTUZUMAB 12 mg/1.2mL Injection, Solution, Concentrate, 1 vial — NDC 58468-0200-1 (Billing 58468-0200-01)
This is a package of 1 vial of LEMTRADA ALEMTUZUMAB 12 mg/1.2mL Injection, Solution, Concentrate from Genzyme Corporation, marketed since Nov 2014 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 58468-0200-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 58468 labeler · 0200 product · 1 package
- Package marketed since
- Nov 18, 2014
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5846802001 7
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 072082
- GCN: 36182
- GPI-14 (Medi-Span): 62405010002020
- HICL (First Databank): 022112
- AHFS class code: 90:04.04.00
- RxCUI (RxNorm): 1594658
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the CD52-directed Cytolytic Antibody class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Alemtuzumab injection is used to treat B-cell chronic lymphocytic leukemia (B-CLL; a slowly developing cancer in which too many of a certain type of white blood cell accumulate in the body). Alemtuzumab is in a class of medications called monoclonal antibodies. It works by activating the immune system to destroy cancer cells. Alemtuzumab is also available as an injection (Lemtrada) that is used to treat multiple sclerosis (a disease in which the nerves do not function properly; you may experience weakness, numbness, loss of muscle coordination and problems with vision, speech, and bladder cont...
Read the full MedlinePlus article ↗- Alemtuzumab is generally reserved for people whose MS hasn't responded well enough to at least two other medications. It's a more aggressive treatment that can make a real differen...
- Why is my doctor recommending this medication when there are other MS treatments out there?
- Each infusion takes about 4 hours, and you'll need to stay for at least 2 more hours of monitoring afterward. Before the infusion, you'll receive a corticosteroid medication to hel...
- What should I expect on the days I get the infusion?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Alemtuzumab — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0202 | $2,544.937 / J0202 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 58468-0200-01 You're viewing this Main listing | 1 VIAL, SINGLE-USE in 1 CARTON / 1.2 mL in 1 VIAL, SINGLE-USE | 2014-11-18 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lemtrada 12 mg/1.2mLthis 58468-0200-01 | Genzyme | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.0224 mg / 1.2 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
0.24 mg / 1.2 mL
UNII 4J9FJ0HL51
Potassium phosphate, monobasic is a salt compound used in medicines as a pH buffer and electrolyte source. It helps stabilize the acidity level of liquid and powdered formulations.
-
0.12 mg / 1.2 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
0.24 mg / 1.2 mL
UNII 660YQ98I10
Potassium chloride is a mineral salt used in medicines as a buffer and to help maintain the proper pH balance and stability of the formulation during storage and use.
-
9.6 mg / 1.2 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
1.38 mg / 1.2 mL
UNII GR686LBA74
Sodium phosphate, dibasic is a salt derived from phosphoric acid. It acts as a buffer to help maintain the medicine's pH balance and may serve as a binder or filler in tablets and capsules.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Genzyme Corporation labeler code 58468
- ALDURAZYME laronidase 2.9 mg/5mL Injection, Solution, Concentrate NDC 58468-0070-1
- Thymoglobulin Anti-thymocyte Globulin (Rabbit) 5 mg/mL Injection, Powder, Lyophilized, For Solution NDC 58468-0080-1
- Renvela SEVELAMER CARBONATE 2400 mg Powder, For Suspension NDC 58468-0131-2
- Renvela SEVELAMER CARBONATE 800 mg Powder, For Suspension NDC 58468-0132-2
- Renvela SEVELAMER CARBONATE 800 mg Tablet, Film Coated NDC 58468-0133-1
- Lumizyme ALGLUCOSIDASE ALFA 5 mg/mL Injection, Powder, For Solution NDC 58468-0160-1
- Aubagio teriflunomide 14 mg Tablet, Film Coated NDC 58468-0210-1
- Aubagio teriflunomide 7 mg Tablet, Film Coated NDC 58468-0211-2
- Cerdelga eliglustat 84 mg Capsule NDC 58468-0220-1
- Cablivi caplacizumab Kit NDC 58468-0225-1
- Wayrilz rilzabrutinib 400 mg Tablet, Film Coated NDC 58468-0251-5
- Qfitlia fitusiran 20 mg/.2mL Injection, Solution NDC 58468-0347-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: AUTOIMMUNITY, INFUSION REACTIONS, STROKE, AND MALIGNANCIES LEMTRADA causes serious, sometimes fatal, autoimmune conditions such as immune thrombocytopenia and anti-glomerular basement membrane disease. Monitor complete blood counts with differential, serum creatinine levels, and urinalysis with urine cell counts before starting treatment and then at monthly intervals until 48 months after the last dose of LEMTRADA [see Warnings and Precautions (5.1) ] . LEMTRADA causes serious and life-threatening infusion reactions.
LEMTRADA must be administered in a setting with appropriate equipment and personnel to manage anaphylaxis or serious infusion reactions. Monitor patients for two hours after each infusion. Make patients aware that serious infusion reactions can also occur after the 2-hour monitoring period [see Warnings and Precautions (5.2) ] .
Serious and life-threatening stroke (including ischemic and hemorrhagic stroke) has been reported within 3 days of LEMTRADA administration. Instruct patients to seek immediate medical attention if symptoms of stroke occur [see Warnings and Precautions (5.3) ]. LEMTRADA may cause an increased risk of malignancies, including thyroid cancer, melanoma, and lymphoproliferative disorders.
Perform baseline and yearly skin exams [see Warnings and Precautions (5.4) ] . Because of the risk of autoimmunity, infusion reactions, and malignancies, LEMTRADA is available only through restricted distribution under a Risk Evaluation Mitigation Strategy (REMS) Program. Call 1-855-676-6326 to enroll in the LEMTRADA REMS program [see Warnings and Precautions (5.5) ] .
WARNING: AUTOIMMUNITY, INFUSION REACTIONS, STROKE, AND MALIGNANCIES See full prescribing information for complete boxed warning. LEMTRADA causes serious, sometimes fatal, autoimmune conditions such as immune thrombocytopenia and anti-glomerular basement membrane disease. Monitor complete blood counts with differential, serum creatinine levels, and urinalysis with urine cell counts monthly until 48 months after the last dose.
( 5.1 ) LEMTRADA causes serious and life-threatening infusion reactions. LEMTRADA must be administered in a setting with appropriate equipment and personnel to manage anaphylaxis or serious infusion reactions. Monitor patients for two hours after each infusion.
Make patients aware that serious infusion reactions can also occur after the 2-hour monitoring period. ( 5.2 ) Serious and life-threatening stroke has been reported within 3 days of LEMTRADA administration. Instruct patients to seek immediate medical attention if symptoms of stroke occur.
( 5.3 ) LEMTRADA may cause an increased risk of malignancies, including thyroid cancer, melanoma, and lymphoproliferative disorders. Perform baseline and yearly skin exams. ( 5.4 ) LEMTRADA is available only through a restricted distribution program.
( 5.5 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE LEMTRADA is indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include relapsing-remitting disease and active secondary progressive disease, in adults. Because of its safety profile, the use of LEMTRADA should generally be reserved for patients who have had an inadequate response to two or more drugs indicated for the treatment of MS [see Warnings and Precautions (5) ] . LEMTRADA is a CD52-directed cytolytic monoclonal antibody indicated for the treatment of relapsing forms of multiple sclerosis (MS), to include relapsing-remitting disease and active secondary progressive disease, in adults.
Because of its safety profile, the use of LEMTRADA should generally be reserved for patients who have had an inadequate response to two or more drugs indicated for the treatment of MS. (1.5) Limitations of Use : LEMTRADA is not recommended for use in patients with clinically isolated syndrome (CIS) because of its safety profile. (1.5) Limitations of Use LEMTRADA is not recommended for use in patients with clinically isolated syndrome (CIS) because of its safety profile [see Warnings and Precautions (5) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Baseline laboratory tests are required prior to treatment. ( 2.1 ) Administer LEMTRADA by intravenous infusion over 4 hours for 2 or more treatment courses: Initial treatment of 2 courses: First course: 12 mg/day on 5 consecutive days. ( 2.3 ) Second course: 12 mg/day on 3 consecutive days 12 months after first treatment course.
( 2.3 ) Subsequent treatment courses of 12 mg per day on 3 consecutive days (36 mg total dose) may be administered, as needed, at least 12 months after the last dose of any prior treatment course. ( 2.3 ) Premedicate with corticosteroids prior to LEMTRADA infusion for the first 3 days of each treatment course. ( 2.2 ) Administer antiviral agents for herpetic prophylaxis starting on the first day of LEMTRADA dosing and continuing for a minimum of two months after completion of LEMTRADA dosing or until CD4+ lymphocyte count is more than 200 cells per microliter, whichever occurs later.
( 2.2 ) Must be diluted prior to administration. ( 2.4 )
2.1Testing and Procedures Prior to Treatment Baseline laboratory tests are required prior to treatment with LEMTRADA [see Dosage and Administration (2.6) ] . In addition, prior to starting treatment with LEMTRADA [see Warnings and Precautions (5.15) ] : complete any necessary immunizations at least 6 weeks prior to treatment. determine whether patients have a history of varicella or have been vaccinated for varicella zoster virus (VZV). If not, test the patient for antibodies to VZV and consider vaccination for those who are antibody-negative.
Postpone treatment with LEMTRADA until 6 weeks after VZV vaccination. perform tuberculosis screening according to local guidelines. instruct patients to avoid potential sources of Listeria monocytogenes.
2.2Recommended Premedication and Concomitant Medication Corticosteroids Premedicate patients with high dose corticosteroids (1,000 mg methylprednisolone or equivalent) immediately prior to LEMTRADA infusion and for the first 3 days of each treatment course [see Warnings and Precautions (5.2) ] . Herpes Prophylaxis Administer antiviral prophylaxis for herpetic viral infections starting on the first day of each treatment course and continue for a minimum of two months following treatment with LEMTRADA or until the CD4+ lymphocyte count is at least 200 cells per microliter, whichever occurs later [see Warnings and Precautions (5.15) ] .
2.3Recommended Dosage The recommended dosage of LEMTRADA is 12 mg/day administered by intravenous infusion for 2 treatment courses: First Treatment Course: 12 mg/day on 5 consecutive days (60 mg total dose). Second Treatment Course: 12 mg/day on 3 consecutive days (36 mg total dose) administered 12 months after the first treatment course. Following the second treatment course, subsequent treatment courses of 12 mg per day on 3 consecutive days (36 mg total dose) may be administered, as needed, at least 12 months after the last dose of any prior treatment courses.
2.4Preparation Instructions Follow the steps below to prepare the diluted solution of LEMTRADA for intravenous infusion: Inspect LEMTRADA visually for particulate matter and discoloration prior to administration. Do not use if particulate matter is present or the solution is discolored. Do not freeze or shake vials prior to use.
Withdraw 1.2 mL of LEMTRADA from the vial into a syringe using aseptic technique and inject into a 100 mL bag of sterile 0.9% Sodium Chloride, USP or 5% Dextrose in Water, USP. Gently invert the bag to mix the solution. Ensure the sterility of the prepared solution because it contains no antimicrobial preservatives.
Each vial is for single use only. Prior to administration, protect diluted LEMTRADA solution from light and store for as long as 8 hours either at room temperature 15°C to 25°C (59°F to 77°F) or keep refrigerated at conditions 2°C to 8°C (36°F to 46°F).
2.5Infusion Instructions Infuse LEMTRADA over 4 hours starting within 8 hours after dilution. Extend the duration of th… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 12 mg/1.2 mL (10 mg/mL) in a single-dose vial. LEMTRADA is a clear and colorless to slightly yellow solution that requires dilution prior to intravenous infusion. Injection: 12 mg/1.2 mL (10 mg/mL) in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS LEMTRADA is contraindicated in patients: with known hypersensitivity or anaphylactic reactions to alemtuzumab or any of the excipients in LEMTRADA who are infected with human immunodeficiency virus (HIV) because LEMTRADA causes prolonged reductions of CD4+ lymphocyte counts with active infection Known hypersensitivity or anaphylactic reactions to alemtuzumab or any of the excipients in LEMTRADA ( 4 ) Infection with Human Immunodeficiency Virus ( 4 ) Active infection ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Immune Thrombocytopenia: Obtain complete blood counts (CBCs) with differential prior to initiation of treatment and at monthly intervals thereafter until 48 months after the last infusion. ( 5.6 ) Glomerular Nephropathies: Obtain serum creatinine levels, urinalysis with cell counts and urine protein to creatinine ratio prior to initiation of treatment. Monitor serum creatinine levels and urinalysis with cell counts at monthly intervals thereafter until 48 months after the last infusion.
( 5.7 ) Thyroid Disorders: Obtain thyroid function tests prior to initiation of treatment and every 3 months until 48 months after the last infusion. ( 5.8 ) Other Autoimmune Cytopenias: Monitor CBCs monthly until 48 months after the last infusion. ( 2.6 , 5.9 ) Autoimmune Hepatitis: If signs of hepatic dysfunction occur, promptly measure serum transaminases and total bilirubin and interrupt or discontinue treatment.
( 5.10 ) Hemophagocytic Lymphohistiocytosis : Consider this diagnosis and evaluate patients immediately if they develop signs or symptoms of systemic inflammation. Discontinue LEMTRADA if an alternative etiology is not established. ( 5.11 ) Adult Onset Still's Disease (AOSD): If a patient develops AOSD, they require prompt evaluation and treatment.
( 5.12 ) Thrombotic Thrombocytopenic Purpura (TTP): Evaluate patients immediately if they develop clinical symptoms or laboratory findings consistent with TTP. Discontinue LEMTRADA if TTP is confirmed or if an alternative etiology is not established. ( 5.13 ) Autoimmune Encephalitis (AIE): Evaluate patients if they develop signs and symptoms suggestive of AIE, such as subacute onset of memory impairment, altered mental status, psychiatric symptoms, neurological findings, and seizures.
( 5.14 ) Acquired Hemophilia A: Obtain a coagulopathy panel including aPTT in patients who present with signs such as spontaneous subcutaneous hematomas, extensive bruising, hematuria, epistaxis, or gastrointestinal or other types of bleeding. ( 5.15 ) Immune-Mediated Colitis: Immune-mediated colitis has been reported in the postmarketing setting. Monitor patients for new or persistent diarrhea or other gastrointestinal symptoms, and evaluate promptly if colitis is suspected.
( 5.16 ) Infections: Administration is contraindicated in patients with active infection. Do not administer live viral vaccines following a course of LEMTRADA. ( 4 , 5.17 ) Progressive Multifocal Leukoencephalopathy (PML): Withhold LEMTRADA at the first sign or symptom suggestive of PML.
( 5.18 )
5.1Autoimmunity Treatment with LEMTRADA can result in the formation of autoantibodies and increase the risk of serious autoimmune conditions, which may be life threatening. In clinical studies (controlled and open-label extension), the following serious autoimmune conditions were reported in LEMTRADA-treated patients, which are described in separate warnings: thyroid disorders (36.8%) [see Warnings and Precautions (5.8) ] immune thrombocytopenia (2%) [see Warnings and Precautions (5.6) ] glomerular nephropathies (0.3%) [see Warnings and Precautions 5.7 ] autoimmune hemolytic anemia (0.3%), autoimmune pancytopenia (0.2%), and autoimmune neutropenia (0.1%) [see Warnings and Precautions (5.9) ] acquired hemophilia A (anti-Factor VIII antibodies) (0.1%) [see Warnings and Precautions (5.15) ] In clinical studies (controlled and open-label extension), vitiligo (0.3%), undifferentiated connective tissue disorders (0.2%), type 1 diabetes (0.2%), rheumatoid arthritis (0.1%), and retinal pigment epitheliopathy (0.1%) were also reported in LEMTRADA-treated patients.
In the postmarketing setting, cases of autoimmune hepatitis [see Warnings and Precautions (5.10) ] , hemophagocytic lymphohistiocytosis [ see Warnings and Precautions (5.11) ] , Adult Onset Still's Disease [see Warnings and Precautions (5.12) ] , thrombotic thrombocytopenic purpura [see Warnings and Precautions (5.13) ] , autoimmune encephalitis [see Warnings and P… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: Autoimmunity [see Boxed Warning and Warnings and Precautions (5.1) ] Infusion Reactions [see Boxed Warning and Warnings and Precautions (5.2) ] Stroke and Cervicocephalic Arterial Dissection [see Warnings and Precautions (5.3) ] Malignancies [see Warnings and Precautions (5.4) ] Immune Thrombocytopenia [see Warnings and Precautions (5.6) ] Glomerular Nephropathies Including Anti-glomerular Basement Membrane Disease [see Warnings and Precautions (5.7) ] Thyroid Disorders [see Warnings and Precautions (5.8) ] Other Autoimmune Cytopenias [see Warnings and Precautions (5.9) ] Autoimmune Hepatitis [see Warnings and Precautions (5.10) ] Hemophagocytic Lymphohistiocytosis [see Warnings and Precautions (5.11) ] Adult Onset Still's Disease [see Warnings and Precautions (5.12) ] Thrombotic Thrombocytopenic Purpura (TTP) [see Warnings and Precautions (5.13) ] Autoimmune Encephalitis (AIE) [see Warnings and Precautions (5.14) ] Acquired Hemophilia A [see Warnings and Precautions (5.15) ] Immune-Mediated Colitis [see Warnings and Precautions (5.16) ] Infections [see Warnings and Precautions (5.17) ] Progressive Multifocal Leukoencephalopathy (PML) [see Warnings and Precautions (5.18) ] Acute Acalculous Cholecystitis [see Warnings and Precautions (5.19) ] Pneumonitis [see Warnings and Precautions (5.20) ] Most common adverse reactions (incidence ≥10% and > interferon beta-1a): rash, headache, pyrexia, nasopharyngitis, nausea, urinary tract infection, fatigue, insomnia, upper respiratory tract infection, herpes viral infection, urticaria, pruritus, thyroid gland disorders, fungal infection, arthralgia, pain in extremity, back pain, diarrhea, sinusitis, oropharyngeal pain, paresthesia, dizziness, abdominal pain, flushing, and vomiting.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Genzyme Corporation at 1-800-745-4447, option 2 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In controlled clinical trials (Study 1 and Study 2), a total of 811 patients with relapsing forms of MS received LEMTRADA. The population was 18 to 55 years of age, 65% were female, and 92% were Caucasian.
A total of 811 patients received 1 course of therapy, and 789 patients received a second course of therapy at 12 months. The overall follow-up in the controlled trials was equivalent to 1622 patient years. In MS clinical studies (controlled and open-label extension), overall, a total of 1217 patients received LEMTRADA.
Approximately 60% of patients received a total of 2 treatment courses and approximately 24% of patients received a total of 3 treatment courses; others received a total of 4 or more treatment courses, although data beyond 3 treatment courses are limited. The overall follow-up was 6858 person-years. Patients had a median of 6 years of follow-up from the first LEMTRADA dose, with approximately 14% having at least 7 years of follow-up.
Most Common Adverse Reactions In controlled clinical trials, the most common adverse reactions with LEMTRADA (in at least 10% of patients and more frequently than in interferon beta-1a) were rash, headache, pyrexia, nasopharyngitis, nausea, urinary tract infection, fatigue, insomnia, upper respiratory tract infection, herpes viral infection, urticaria, pruritus, thyroid gland disorders, fungal infection, arthralgia, pain in extremity, back pain, diarrhea, sinusitis, oropharyngeal pain, paresthesia, dizziness, abdominal pain, flushing, and vomiting.
Table 1 lists adverse reactions occurring in ≥5% of LEMTRADA-treated patients in Study 1 and 2 and at the same or at a higher rate than interferon beta-1a. Table 1: Advers… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm. ( 8.1 ) Women of childbearing potential should use effective contraception during and for 4 months after a course of treatment with LEMTRADA. ( 8.3 )
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of LEMTRADA in pregnant women. LEMTRADA was embryolethal in pregnant huCD52 transgenic mice when administered during organogenesis [see Animal data ] . Auto-antibodies may develop after administration of LEMTRADA.
Placental transfer of anti-thyroid antibodies resulting in neonatal Graves' disease has been reported. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
There is a pregnancy surveillance program for LEMTRADA. If LEMTRADA exposure occurs during pregnancy, healthcare providers and patients are encouraged to report pregnancies by calling 1-800-745-4447, option 2. Clinical Considerations LEMTRADA induces persistent thyroid disorders [see Warnings and Precautions (5.8) ] .
Untreated hypothyroidism in pregnant women increases the risk for miscarriage and may have effects on the fetus including mental retardation and dwarfism. In mothers with Graves' disease, maternal thyroid stimulating hormone receptor antibodies can be transferred to a developing fetus and can cause neonatal Graves' disease. In a patient who developed Graves' disease after treatment with alemtuzumab, placental transfer of anti-thyrotropin receptor antibodies resulted in neonatal Graves' disease with thyroid storm in her infant who was born 1 year after alemtuzumab dosing [see Warnings and Precautions (5.1) ] .
Data Animal data When LEMTRADA was administered to pregnant huCD52 transgenic mice during organogenesis (gestation days [GD] 6–10 or GD 11–15) at doses of 3 or 10 mg/kg IV, no teratogenic effects were observed. However, there was an increase in embryolethality (increased postimplantation loss and the number of dams with all fetuses dead or resorbed) in pregnant animals dosed during GD 11–15. In a separate study in pregnant huCD52 transgenic mice, administration of LEMTRADA during organogenesis (GD 6–10 or GD 11–15) at doses of 3 or 10 mg/kg IV, decreases in B- and T-lymphocyte populations were observed in the offspring at both doses tested.
In pregnant huCD52 transgenic mice administered LEMTRADA at doses of 3 or 10 mg/kg/day IV throughout gestation and lactation, there was an increase in pup deaths during the lactation period at 10 mg/kg. Decreases in T- and B-lymphocyte populations and in antibody response were observed in offspring at both doses tested.
8.2Lactation Risk Summary There are no data on the presence of alemtuzumab in human milk, the effects on the breastfed infant, or the effects of the drug on milk production. Alemtuzumab was detected in the milk of lactating huCD52 transgenic mice administered LEMTRADA [see Animal data ]. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for LEMTRADA and any potential adverse effects on the breastfed child from LEMTRADA or from the underlying maternal conditions.
Data Animal data Alemtuzumab was detected in the milk of lactating huCD52 transgenic mice following intravenous administration of LEMTRADA at a dose of 10 mg/kg on postpartum days 8–12. Serum levels of alemtuzumab were similar in lactating mice and offspring on postpartum Day 13 and were associated with evidence of pharmacological activity (decrease in lymphocyte counts) in the offspring.
8.3Females and Males of Reproductive Potential Contraception Before initiation of LEMTRADA treatment, women of childbearing potential should be counselled on the potential for a serious risk to the fetus. To avoid in utero exposure to LEMTRADA, women of… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of LEMTRADA in pregnant women. LEMTRADA was embryolethal in pregnant huCD52 transgenic mice when administered during organogenesis [see Animal data ] . Auto-antibodies may develop after administration of LEMTRADA.
Placental transfer of anti-thyroid antibodies resulting in neonatal Graves' disease has been reported. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
There is a pregnancy surveillance program for LEMTRADA. If LEMTRADA exposure occurs during pregnancy, healthcare providers and patients are encouraged to report pregnancies by calling 1-800-745-4447, option 2. Clinical Considerations LEMTRADA induces persistent thyroid disorders [see Warnings and Precautions (5.8) ] .
Untreated hypothyroidism in pregnant women increases the risk for miscarriage and may have effects on the fetus including mental retardation and dwarfism. In mothers with Graves' disease, maternal thyroid stimulating hormone receptor antibodies can be transferred to a developing fetus and can cause neonatal Graves' disease. In a patient who developed Graves' disease after treatment with alemtuzumab, placental transfer of anti-thyrotropin receptor antibodies resulted in neonatal Graves' disease with thyroid storm in her infant who was born 1 year after alemtuzumab dosing [see Warnings and Precautions (5.1) ] .
Data Animal data When LEMTRADA was administered to pregnant huCD52 transgenic mice during organogenesis (gestation days [GD] 6–10 or GD 11–15) at doses of 3 or 10 mg/kg IV, no teratogenic effects were observed. However, there was an increase in embryolethality (increased postimplantation loss and the number of dams with all fetuses dead or resorbed) in pregnant animals dosed during GD 11–15. In a separate study in pregnant huCD52 transgenic mice, administration of LEMTRADA during organogenesis (GD 6–10 or GD 11–15) at doses of 3 or 10 mg/kg IV, decreases in B- and T-lymphocyte populations were observed in the offspring at both doses tested.
In pregnant huCD52 transgenic mice administered LEMTRADA at doses of 3 or 10 mg/kg/day IV throughout gestation and lactation, there was an increase in pup deaths during the lactation period at 10 mg/kg. Decreases in T- and B-lymphocyte populations and in antibody response were observed in offspring at both doses tested.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients less than 17 years of age have not been established. Use of LEMTRADA is not recommended in pediatric patients due to the risks of autoimmunity, infusion reactions, and stroke, and because it may increase the risk of malignancies (thyroid, melanoma, lymphoproliferative disorders, and lymphoma) [see Warnings and Precautions (5.1 , 5.2 , 5.3 , 5.4 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of LEMTRADA did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently than younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Two MS patients experienced serious reactions (headache, rash, and either hypotension or sinus tachycardia) after a single accidental infusion up to 60 mg of LEMTRADA. Doses of LEMTRADA greater than those recommended may increase the intensity and/or duration of infusion reactions or its immune effects. There is no known antidote for alemtuzumab overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism by which alemtuzumab exerts its therapeutic effects in multiple sclerosis is unknown but is presumed to involve binding to CD52, a cell surface antigen present on T and B lymphocytes, and on natural killer cells, monocytes, and macrophages. Following cell surface binding to T and B lymphocytes, alemtuzumab results in antibody-dependent cellular cytolysis and complement-mediated lysis.
12.2Pharmacodynamics Effects of LEMTRADA on the Lymphocyte Population LEMTRADA depletes circulating T and B lymphocytes after each treatment course. In clinical trials, the lowest cell counts occurred 1 month after a course of treatment at the time of the first post-treatment blood count. Lymphocyte counts then increased over time: B cell counts usually recovered within 6 months; T cell counts increased more slowly and usually remained below baseline 12 months after treatment.
Approximately 60% of patients had total lymphocyte counts below the lower limit of normal 6 months after each treatment course and 20% had counts below the lower limit of normal after 12 months. Reconstitution of the lymphocyte population varies for the different lymphocyte subtypes. At Month 1 in clinical trials, the mean CD4+ lymphocyte count was 40 cells per microliter, and, at Month 12, 270 cells per microliter.
At 30 months, approximately half of patients had CD4+ lymphocyte counts that remained below the lower limit of normal. Cardiac Electrophysiology In a study of 53 MS patients, alemtuzumab 12 mg per day for 5 days caused no changes in the QTc interval greater than 20 ms. An average 22 to 26 beats-per-minute increase in heart rate was observed for at least 2 hours after the first but not subsequent infusions.
12.3Pharmacokinetics The pharmacokinetics of LEMTRADA were evaluated in a total of 148 patients with relapsing forms of MS who received 12 mg/day on 5 consecutive days, followed by 12 mg/day on 3 consecutive days 12 months following the first treatment course. Absorption Serum concentrations increased with each consecutive dose within a treatment course, with the highest observed concentrations occurring following the last infusion of a treatment course. The mean maximum concentration was 3014 ng/mL on Day 5 of the first treatment course, and 2276 ng/mL on Day 3 of the second treatment course.
Distribution LEMTRADA is largely confined to the blood and interstitial space with a central volume of distribution of
14.1L. Elimination The elimination half-life was approximately 2 weeks and was comparable between courses. The serum concentrations were generally undetectable (<60 ng/mL) within approximately 30 days following each treatment course. Specific Populations Age, race, or gender had no effect on the pharmacokinetics of LEMTRADA.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism by which alemtuzumab exerts its therapeutic effects in multiple sclerosis is unknown but is presumed to involve binding to CD52, a cell surface antigen present on T and B lymphocytes, and on natural killer cells, monocytes, and macrophages. Following cell surface binding to T and B lymphocytes, alemtuzumab results in antibody-dependent cellular cytolysis and complement-mediated lysis.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied LEMTRADA (alemtuzumab) injection is a sterile, clear and colorless to slightly yellow solution for intravenous infusion, containing no antimicrobial preservatives. Each LEMTRADA carton (NDC: 58468-0200-1) contains one single-dose vial that delivers 12 mg/1.2 mL (10 mg/mL). The vial stopper is not made with natural rubber latex.
16.2Storage and Handling Store LEMTRADA vials at 2°C to 8°C (36°F to 46°F). Do not freeze or shake. Store in original carton to protect from light.
16.1How Supplied LEMTRADA (alemtuzumab) injection is a sterile, clear and colorless to slightly yellow solution for intravenous infusion, containing no antimicrobial preservatives. Each LEMTRADA carton (NDC: 58468-0200-1) contains one single-dose vial that delivers 12 mg/1.2 mL (10 mg/mL). The vial stopper is not made with natural rubber latex.
📦 Storage and Handling ▾
16.2Storage and Handling Store LEMTRADA vials at 2°C to 8°C (36°F to 46°F). Do not freeze or shake. Store in original carton to protect from light.
📋 Description ▾
11 DESCRIPTION Alemtuzumab is a recombinant humanized IgG1 kappa monoclonal antibody directed against the cell surface glycoprotein, CD52. Alemtuzumab has an approximate molecular weight of 150 kD. Alemtuzumab is produced in mammalian cell (Chinese hamster ovary) suspension culture in a nutrient medium containing neomycin.
Neomycin is not detectable in the final product. LEMTRADA (alemtuzumab) injection is a sterile, clear and colorless to slightly yellow, solution (pH 7.2 ± 0.2) for intravenous infusion. Each 1 mL of solution contains 10 mg alemtuzumab, dibasic sodium phosphate (1.15 mg), disodium edetate dihydrate (0.0187 mg), polysorbate 80 (0.1 mg), potassium chloride (0.2 mg), potassium dihydrogen phosphate (0.2 mg), sodium chloride (8 mg), and Water for Injection, USP.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Autoimmunity Advise patients to contact their healthcare provider promptly if they experience any symptoms of potential autoimmune disease. Give examples of important symptoms such as bleeding, easy bruising, petechiae, purpura, hematuria, edema, jaundice, or hemoptysis [see Warnings and Precautions (5.1) ] .
Advise patients of the importance of monthly blood and urine tests for 48 months following the last course of LEMTRADA to monitor for signs of autoimmunity because early detection and prompt treatment can help prevent serious and potentially fatal outcomes associated with these events. Advise patients that monitoring may need to continue past 48 months if they have signs or symptoms of autoimmunity. Advise patients that LEMTRADA may cause hyperthyroid or hypothyroid disorders.
Advise patients to contact their healthcare provider if they experience symptoms reflective of a potential thyroid disorder such as unexplained weight loss or gain, fast heartbeat or palpitations, nervousness, worsening tiredness, eye swelling, constipation, or feeling cold. Advise women of childbearing potential of the risks of pregnancy with concomitant thyroid disease. Advise women of childbearing potential to discuss pregnancy planning with their doctor.
Cases of autoimmune hepatitis have been reported in patients treated with LEMTRADA. Advise patients to contact their healthcare provider right away if they develop signs or symptoms suggestive of hepatic dysfunction such as unexplained nausea, vomiting, abdominal pain, fatigue, anorexia, jaundice and/or dark urine, or bleeding or bruising more easily than normal. Advise patients to contact their healthcare provider if they experience symptoms of acquired hemophilia A such as spontaneous bruising, nose bleeds, painful or swollen joints, other types of bleeding, or bleeding from a cut that may take longer than usual to stop.
Advise patients that cases of autoimmune encephalitis can occur after receiving LEMTRADA. This condition may include symptoms such as behavior and psychiatric changes, movement disorders, short-term memory loss or seizures, as well as other symptoms that may resemble an MS relapse. Infusion Reactions Advise patients that infusion reactions can occur at the time of infusion or after they leave the infusion center [see Warnings and Precautions (5.2) ] .
Instruct the patient to remain at the infusion center for at least 2 hours after each LEMTRADA infusion, or longer at the discretion of the healthcare provider. Advise patients that symptoms of infusion reactions may occur after they leave the infusion center and to report these symptoms to their healthcare provider. Advise patients that their healthcare provider will monitor vital signs, including blood pressure, before and during the infusion and to contact their healthcare provider promptly if they experience infusion reactions, which include swelling in the mouth or throat, difficulty breathing, weakness, abnormal heart rate (fast, slow, or irregular), chest pain, rash, facial drooping, sudden severe headache, weakness on one side of the body, difficulty with speech, or neck pain.
Instruct patients that there have also been reports of rare but serious infusion reactions, including bleeding in the lung, chest tightness/pain or discomfort, heart attack, and stroke or tears in blood vessels supplying the brain, which should be reported to your healthcare provider. Advise patients that reactions may occur following any of the doses during the treatment course. In the majority of cases, reactions occurred within 1–3 days of the infusion.
Stroke and Cervicocephalic Arterial Dissection Educate patients on the symptoms and instruct patients to seek immediate medical attention if symptoms of stroke or cervicocephalic arterial dissection occur (e.g., neck pain, weakness on one side, facial droop, difficulty with speech, su… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration Revised: x 2024 MEDICATION GUIDE LEMTRADA ® (lem-TRA-da) (alemtuzumab), injection for intravenous infusion Read this Medication Guide before you start receiving LEMTRADA and before you begin each treatment course. There may be new information.
This information does not take the place of talking to your healthcare provider about your medical condition or treatment. What is the most important information I should know about LEMTRADA? LEMTRADA can cause serious side effects, including: 1.
Serious autoimmune problems. Some people receiving LEMTRADA develop a condition where the immune cells in your body attack other cells or organs in the body (autoimmunity) which can be serious and may cause death. Serious autoimmune problems may include: immune thrombocytopenic purpura (ITP).
LEMTRADA may cause the number of platelets in your blood to be reduced (ITP). ITP can cause severe bleeding that may cause life-threatening problems. Call your healthcare provider right away if you have any of the following symptoms: easy bruising bleeding from a cut that is hard to stop coughing up blood heavier menstrual periods than normal bleeding from your gums or nose that is new or takes longer than usual to stop small, scattered spots on your skin that are red, pink, or purple kidney problems.
LEMTRADA may cause a serious kidney problem called anti-glomerular basement membrane disease. If this happens and you do not get treated, anti-glomerular basement membrane disease can lead to severe kidney damage, kidney failure that needs dialysis, a kidney transplant, or death. Call your healthcare provider right away if you have any of the following symptoms: swelling of your legs or feet blood in the urine (red or tea-colored urine) decrease in urine fatigue coughing up blood Side effects may happen while you receive LEMTRADA and for 4 years after you stop receiving LEMTRADA.
Your healthcare provider will order blood and urine tests before you receive, while you are receiving, and every month for 4 years after you receive your last LEMTRADA infusion. You may need to continue these blood and urine tests after 4 years if you have any autoimmune signs or symptoms. The blood and urine tests will help your healthcare provider watch for signs and symptoms of serious autoimmune problems.
It is important to have your blood and urine tested, even if you are feeling well and do not have any symptoms from LEMTRADA and your multiple sclerosis. This may help your healthcare provider find any problems early. 2.
Serious infusion reactions. LEMTRADA can cause serious infusion reactions that may cause death. Serious infusion reactions may happen while you receive, or up to 24 hours or longer after you receive LEMTRADA.
You will receive your infusion at a healthcare facility with equipment and staff trained to manage infusion reactions. You will be watched while you receive and for at least 2 hours after you receive LEMTRADA. It is important that you stay at the infusion center for at least 2 hours after your infusion is finished or longer if your healthcare provider decides you need to stay longer.
If a serious infusion reaction happens while you are receiving LEMTRADA, your infusion may be stopped. Tell your healthcare provider right away if you have any of the following symptoms of a serious infusion reaction during the infusion, and after you have left the healthcare facility: swelling in your mouth or throat trouble breathing weakness fast, slow, or irregular heartbeat chest pain rash To lower your chances of getting a serious infusion reaction, your healthcare provider will give you a medicine called corticosteroids before your first 3 infusions of a treatment course.
You may also be given other medicines before or after the infusion to try to reduce your chances of these reactions or to treat them after they happen. 3. Stroke and tears in your arteries that supply blood to your brain (ca… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of LEMTRADA were evaluated in a total of 148 patients with relapsing forms of MS who received 12 mg/day on 5 consecutive days, followed by 12 mg/day on 3 consecutive days 12 months following the first treatment course. Absorption Serum concentrations increased with each consecutive dose within a treatment course, with the highest observed concentrations occurring following the last infusion of a treatment course. The mean maximum concentration was 3014 ng/mL on Day 5 of the first treatment course, and 2276 ng/mL on Day 3 of the second treatment course.
Distribution LEMTRADA is largely confined to the blood and interstitial space with a central volume of distribution of
14.1L. Elimination The elimination half-life was approximately 2 weeks and was comparable between courses. The serum concentrations were generally undetectable (<60 ng/mL) within approximately 30 days following each treatment course. Specific Populations Age, race, or gender had no effect on the pharmacokinetics of LEMTRADA.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effects of LEMTRADA on the Lymphocyte Population LEMTRADA depletes circulating T and B lymphocytes after each treatment course. In clinical trials, the lowest cell counts occurred 1 month after a course of treatment at the time of the first post-treatment blood count. Lymphocyte counts then increased over time: B cell counts usually recovered within 6 months; T cell counts increased more slowly and usually remained below baseline 12 months after treatment.
Approximately 60% of patients had total lymphocyte counts below the lower limit of normal 6 months after each treatment course and 20% had counts below the lower limit of normal after 12 months. Reconstitution of the lymphocyte population varies for the different lymphocyte subtypes. At Month 1 in clinical trials, the mean CD4+ lymphocyte count was 40 cells per microliter, and, at Month 12, 270 cells per microliter.
At 30 months, approximately half of patients had CD4+ lymphocyte counts that remained below the lower limit of normal. Cardiac Electrophysiology In a study of 53 MS patients, alemtuzumab 12 mg per day for 5 days caused no changes in the QTc interval greater than 20 ms. An average 22 to 26 beats-per-minute increase in heart rate was observed for at least 2 hours after the first but not subsequent infusions.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of LEMTRADA was demonstrated in two studies (Study 1 and 2) that evaluated LEMTRADA 12 mg in patients with relapsing-remitting multiple sclerosis (RRMS). LEMTRADA was administered by intravenous infusion once daily over a 5-day course, followed one year later by intravenous infusion once daily over a 3-day course. Both studies included patients who had experienced at least 2 relapses during the 2 years prior to trial entry and at least 1 relapse during the year prior to trial entry.
Neurological examinations were performed every 12 weeks and at the time of suspected relapse. Magnetic resonance imaging (MRI) evaluations were performed annually. Study 1 Study 1 was a 2-year randomized, open-label, rater-blinded, active comparator (interferon beta-1a 44 micrograms administered subcutaneously three times a week) controlled study in patients with RRMS.
Patients entering Study 1 had Expanded Disability Status Scale (EDSS) scores of 5 or less and had to have experienced at least one relapse while on interferon beta or glatiramer acetate therapy. Patients were randomized to receive LEMTRADA (n=426) or interferon beta-1a (n=202). At baseline, the mean age was 35 years, the mean disease duration was 4.5 years, and the mean EDSS score was 2.7.
The clinical outcome measures were the annualized relapse rate (ARR) over 2 years and the time to confirmed disability progression. Confirmed disability progression was defined as at least a 1 point increase above baseline EDSS (1.5 point increase for patients with baseline EDSS of 0) sustained for 6 months. The MRI outcome measure was the change in T2 lesion volume.
The annualized relapse rate was significantly lower in patients treated with LEMTRADA than in patients who received interferon beta-1a. Time to onset of 6-month confirmed disability progression was significantly delayed with LEMTRADA treatment compared to interferon beta-1a. There was no significant difference between the treatment groups for the change in T2 lesion volume.
The results of Study 1 are shown in Table 2 and Figure 1. Table 2: Clinical and MRI Results of Study 1 LEMTRADA interferon beta-1a 44 mcg p-value (N=426) (N=202) Clinical Outcomes Annualized relapse rate 0.26 0.52 <0.0001 Relative reduction 49% Proportion of patients with disability progression at Year 2 13% 21% 0.0084 Relative risk reduction 42% Percent of patients remaining relapse-free at Year 2 65% 47% <0.0001 MRI Outcomes Percent change in T2 lesion volume from baseline -1.3 -1.2
0.14Figure 1: Time to 6-month Confirmed Disability Progression (Study 1) Figure 1 Study 2 Study 2 was a 2-year randomized, open-label, rater-blinded, active comparator (interferon beta-1a 44 micrograms administered subcutaneously three times a week) controlled study in patients with RRMS. Patients entering Study 2 had EDSS scores of 3 or less and no prior treatment for multiple sclerosis. Patients were randomized to receive LEMTRADA (n=376) or interferon beta-1a (n=187).
At baseline, the mean age was 33 years, the mean disease duration was 2 years, and the mean EDSS score was 2. The clinical outcome measures were the annualized relapse rate (ARR) over 2 years and the time to confirmed disability progression, as defined in Study 1. The MRI outcome measure was the change in T2 lesion volume.
The annualized relapse rate was significantly lower in patients treated with LEMTRADA than in patients who received interferon beta-1a. There was no significant difference between the treatment groups for the time to confirmed disability progression and for the primary MRI endpoint (change in T2 lesion volume). The results for Study 2 are shown in Table 3.
Table 3: Clinical and MRI Results of Study 2 LEMTRADA interferon beta-1a 44 mcg p-value (N=376) (N=187) Clinical Outcomes Annualized relapse rate Relative reduction 0.18 55% 0.39 <0.0001 Proportion of patients with disability progression at Year 2 Relative risk reduction 8% 30% 11%
0.22Percent of patients remainin… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Studies to assess the carcinogenic or genotoxic potential of LEMTRADA have not been conducted. When LEMTRADA (3 or 10 mg/kg IV) was administered to huCD52 transgenic male mice on 5 consecutive days prior to cohabitation with untreated wild-type females, no effect on fertility or reproductive performance was observed. However, adverse effects on sperm parameters (including abnormal morphology [detached/no head] and reduced total count and motility) were observed at both doses tested.
When LEMTRADA (3 or 10 mg/kg IV) was administered to huCD52 transgenic female mice for 5 consecutive days prior to cohabitation with untreated wild-type males, there was a decrease in the average number of corpora lutea and implantation sites and an increase in postimplantation loss, resulting in fewer viable embryos at the higher dose tested.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Studies to assess the carcinogenic or genotoxic potential of LEMTRADA have not been conducted. When LEMTRADA (3 or 10 mg/kg IV) was administered to huCD52 transgenic male mice on 5 consecutive days prior to cohabitation with untreated wild-type females, no effect on fertility or reproductive performance was observed. However, adverse effects on sperm parameters (including abnormal morphology [detached/no head] and reduced total count and motility) were observed at both doses tested.
When LEMTRADA (3 or 10 mg/kg IV) was administered to huCD52 transgenic female mice for 5 consecutive days prior to cohabitation with untreated wild-type males, there was a decrease in the average number of corpora lutea and implantation sites and an increase in postimplantation loss, resulting in fewer viable embryos at the higher dose tested.
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.1 , 5.16 ) x/202x
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 12 mg/1.2 mL Vial Carton NDC 58468-0200-1 LEMTRADA ® (alemtuzumab) injection 12 mg/1.2 mL (10 mg/mL) For Intravenous Infusion Only Dilute before Intravenous Infusion Single-Dose Vial, Discard Unused Portion Rx only Dispense the enclosed Medication Guide to each patient. PRINCIPAL DISPLAY PANEL - 12 mg/1.2 mL Vial Carton
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |