
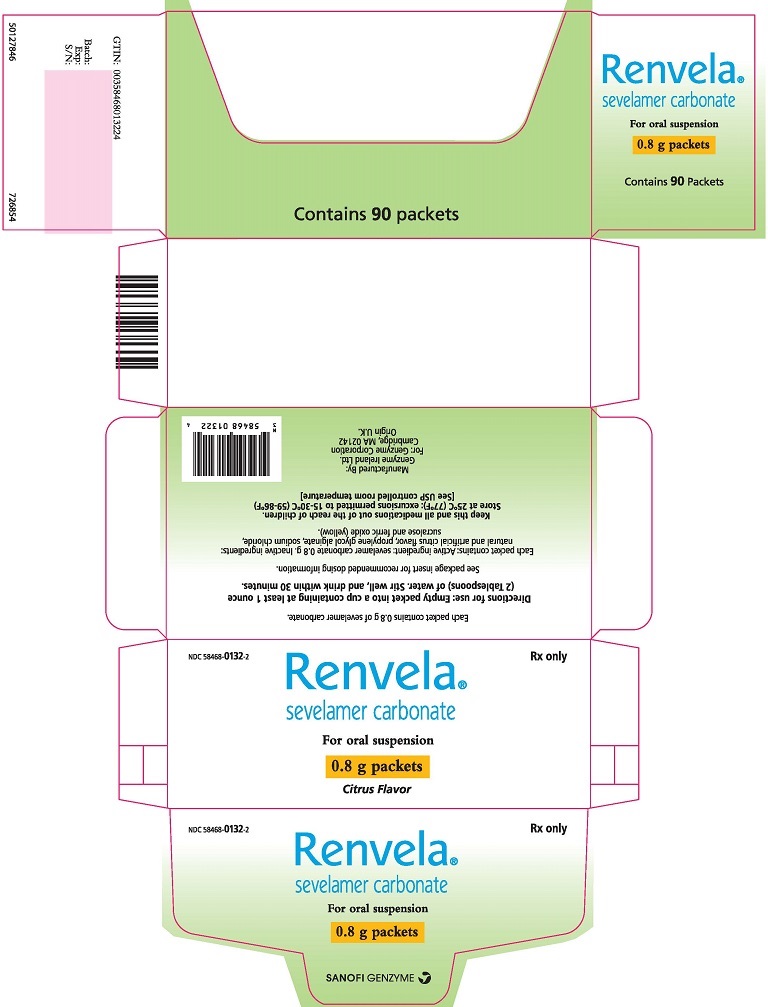
Renvela SEVELAMER CARBONATE 800 mg Powder, For Suspension, 90 packets
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phosphate Binder class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Sevelamer is used to control high blood levels of phosphorus in people with chronic kidney disease who are on dialysis (medical treatment to clean the blood when the kidneys are not working properly). Sevelamer is in a class of medications called phosphate binders. It binds phosphorus that you get from foods in your diet and prevents it from being absorbed into your blood stream.
Read the full MedlinePlus article ↗- When your kidneys aren't working properly, they can't remove phosphorus from your blood the way they normally would. Dialysis helps, but it doesn't always bring phosphorus down eno...
- What exactly does sevelamer do, and why do I need it if I'm on dialysis?
- Yes, timing really matters here. Sevelamer needs to be taken with each meal because it works by binding to phosphate in the food you're eating right then. If you take it without fo...
- Does it matter when I take it — can I just take all my doses at once?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 26CD3J2R0C
Propylene glycol alginate is a thickening agent made from seaweed extract. It stabilizes and thickens liquid medicines, helping them achieve the right consistency and preventing ingredients from separating.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 96K6UQ3ZD4
Sucralose is a synthetic sweetener made from sugar. It's added to medicines to improve taste without adding calories, helping make bitter or unpleasant-tasting drugs easier to take.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $17.156 | $1,544.02 / 90 powder |
| Medicaid paysCMS SDUD · 12 mo | $17.29 | $1,556.12 / 90 powder |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| sevelamer carbonate 800 mg 00115-1365-29 | Amneal | 90 packets | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate .8 g 33342-0288-68 | Macleods | 90 packets | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate for Oral Suspension 800 mg 43598-0478-90 | Dr. | 90 packets | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate 800 mg/930mg 64380-0880-80 | Strides | 90 packets | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate 800 mg 65862-0930-90 | Aurobindo | 90 pouches | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate 800 mg 69452-0126-19 | Bionpharma | 90 packets | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate .8 g 72603-0398-02 | NorthStar | 90 packets | $0.971 | AB | Availability likely | save 94% |
| Sevelamer Carbonate .8 g 00955-1052-90 | Sanofi-Aventis | 90 packets | $2.715 | — | FDA listed | save 84% |
| Renvela 800 mgthis 58468-0132-02 | Genzyme | 90 packets | $17.156 | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9095509 ↗ | Drug product | — | Dec 6, 2030 |
| US 9095509 ↗ | Drug product | — | Dec 6, 2030 |
Is there a generic version of RENVELA 0.8 GM POWDER PACKET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 58468-0132-02 You're viewing this | 90 PACKET in 1 CARTON (58468-0132-2) / 1 POWDER, FOR SUSPENSION in 1 PACKET (58468-0132-1) | 2009-08-12 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Renvela ® (sevelamer carbonate) is indicated for the control of serum phosphorus in adults and children 6 years of age and older with chronic kidney disease (CKD) on dialysis. Renvela ® is a phosphate binder indicated for the control of serum phosphorus in adults and children 6 years of age and older with chronic kidney disease on dialysis. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting dose of Renvela is 0.8 or 1.6 grams administered orally three times per day with meals based on serum phosphorus levels for adult patients and based on body surface area (BSA) category for pediatric patients. ( 2.1 ) Titrate by 0.8 g per meal in two-week intervals for adult patients as needed to obtain serum phosphorus target. ( 2.1 ) Titrate based on BSA category for pediatric patients in two-week intervals for 6 weeks and then every 4 weeks as needed to obtain serum phosphorus target.
( 2.1 )
2.1General Dosing Information Starting Dose for Adult Patients Not Taking a Phosphate Binder. The recommended starting dose of Renvela is 0.8 to 1.6 g taken orally with meals based on serum phosphorus level. Table 1 provides recommended starting doses of Renvela for adult patients not taking a phosphate binder.
Table 1: Starting Dose for Adult Dialysis Patients Not Taking a Phosphate Binder Serum Phosphorus Renvela >5.5 and <7.5 mg/dL 0.8 g three times daily with meals ≥7.5 mg/dL 1.6 g three times daily with meals Dose Titration for Adult Patients Taking Renvela . Titrate the Renvela dose by 0.8 g three times per day with meals at two-week intervals as necessary to achieve target serum phosphorus levels. Based on clinical studies, the average prescribed adult daily dose of sevelamer carbonate is approximately 7.2 g per day.
The highest daily adult dose of sevelamer carbonate studied was 14 grams in CKD patients on dialysis. Starting Dose for Pediatric Patients Not Taking a Phosphate Binder. The recommended starting dose for pediatric patients 6 years of age and older is 0.8 to 1.6 g taken three times per day with meals based on the patient's body surface area (BSA) category; see Table 2 .
Table 2: Recommended Starting Dosage and Titration Increment Based on Pediatric Patient's Body Surface Area (m 2 ) BSA (m 2 ) Starting Dose Per Meal/Snack Titration Increases/Decreases Per Dose ≥0.75 to <1.2 0.8 g Titrate by 0.4 g ≥1.2 1.6 g Titrate by 0.8 g Dose Titration for Pediatric Patients Taking Renvela. Titrate the Renvela dose as needed to achieve target levels at two-week intervals based on BSA category, as shown in Table 2. Switching from Sevelamer Hydrochloride Tablets.
For adult patients switching from sevelamer hydrochloride tablets to sevelamer carbonate tablets or powder, use the same dose in grams. Switching between Sevelamer Carbonate Tablets and Powder. Use the same dose in grams.
Switching from Calcium Acetate . Table 3 gives recommended starting doses of Renvela based on a patient's current calcium acetate dose. Table 3: Starting Dose for Dialysis Patients Switching from Calcium Acetate to Renvela Calcium Acetate 667 mg (Tablets per meal) Renvela 1 tablet 0.8 g 2 tablets 1.6 g 3 tablets 2.4 g
2.2Sevelamer Carbonate Powder Preparation Instructions Sevelamer carbonate powder is available in 0.8 or 2.4 g packets. For dose increments of 0.4 g, use one half of a 0.8 g packet. Place the sevelamer carbonate powder in a cup and suspend in the amount of water described in Table 4.
Table 4: Sevelamer Carbonate Powder Preparation Instructions Amount of Renvela Powder Minimum Amount of Water for Dose Preparation (either ounces, mL, or tablespoon) Ounces mL Tablespoons 0.4 g 1 30 2 0.8 g 1 30 2 2.4 g 2 60 4 Instruct patients to stir the mixture vigorously (it does not dissolve), resuspend, if necessary, right before administration, and drink the entire preparation within 30 minutes. As an alternative to water, the entire contents of the packet may be pre-mixed with a small amount of food or beverage and consumed immediately (within 30 minutes) as part of the meal.
Do not heat Renvela powder (e.g., microwave) or add to heated foods or liquids.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 800 mg white oval, film-coated, compressed tablets, engraved with RV800 on one side Powder: 0.8 g and 2.4 g pale-yellow powder packaged in an opaque, foil-lined, heat-sealed packets Tablets: 800 mg ( 3 ) Powder: 0.8 g and 2.4 g packets ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Renvela is contraindicated in patients with bowel obstruction. Renvela is contraindicated in patients with known hypersensitivity to sevelamer carbonate, sevelamer hydrochloride, or to any of the excipients. Bowel obstruction. ( 4 ) Known hypersensitivity to sevelamer carbonate, sevelamer hydrochloride, or to any of the excipients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serious cases of dysphagia, bowel obstruction, bleeding gastrointestinal ulcers, colitis, ulceration, necrosis, and perforation have been associated with sevelamer use, some requiring hospitalization and surgery. ( 5.1 )
5.1Gastrointestinal Adverse Events Patients with dysphagia, swallowing disorders, severe gastrointestinal (GI) motility disorders, including severe constipation, or major GI tract surgery were not included in the Renvela clinical studies. Cases of dysphagia and esophageal tablet retention have been reported in association with use of the tablet formulation of sevelamer, some requiring hospitalization and intervention. Consider using sevelamer suspension in patients with a history of swallowing disorders.
Cases of bowel obstruction, bleeding gastrointestinal ulcers, colitis, ulceration, necrosis, and perforation have also been reported with sevelamer use [see Adverse Reactions (6.2) ] . Inflammatory disorders may resolve upon Renvela discontinuation. Treatment with Renvela should be re-evaluated in patients who develop severe gastrointestinal symptoms.
5.2Reductions in Vitamins D, E, K (clotting factors) and Folic Acid Levels In preclinical studies in rats and dogs, sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, reduced vitamins D, E, and K (coagulation parameters) and folic acid levels at doses of 6–10 times the recommended human dose. In short-term clinical trials, there was no evidence of reduction in serum levels of vitamins. However, in a one-year clinical trial, 25-hydroxyvitamin D (normal range 10 to 55 ng/mL) fell from 39 ± 22 ng/mL to 34 ± 22 ng/mL (p<0.01) with sevelamer hydrochloride treatment.
Most (approximately 75%) patients in sevelamer hydrochloride clinical trials were receiving vitamin supplements.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most of the safety experience is with sevelamer carbonate tablets and sevelamer hydrochloride. In long-term studies with sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, the most common adverse events included: vomiting (22%), nausea (20%), diarrhea (19%), dyspepsia (16%), abdominal pain (9%), flatulence (8%), and constipation (8%). ( 6.1) To report SUSPECTED ADVERSE REACTIONS, contact Genzyme Corporation at 1-800-847-0069 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. There are limited clinical trial data on the safety of Renvela. However, because it contains the same active ingredient as the hydrochloride salt, the adverse event profiles of the two salts are expected to be similar.
In a cross-over study in hemodialysis patients with treatment durations of eight weeks each and no washout, and another cross-over study in hemodialysis patients with treatment durations of four weeks each and no washout between treatment periods, the adverse reactions on sevelamer carbonate powder were similar to those reported for sevelamer hydrochloride. In a parallel design study of sevelamer hydrochloride with treatment duration of 52 weeks, adverse reactions reported for sevelamer hydrochloride (n=99) were similar to those reported for the active-comparator group (n=101).
Overall adverse reactions among those treated with sevelamer hydrochloride occurring in >5% of patients included: vomiting (22%), nausea (20%), diarrhea (19%), dyspepsia (16%), abdominal pain (9%), flatulence (8%), and constipation (8%). A total of 27 patients treated with sevelamer and 10 patients treated with comparator withdrew from the study due to adverse reactions. Based on studies of 8–52 weeks, the most common reason for withdrawal from sevelamer hydrochloride was gastrointestinal adverse reactions (3%–16%).
In 143 peritoneal dialysis patients studied for 12 weeks using sevelamer hydrochloride, most common adverse reactions were similar to adverse reactions observed in hemodialysis patients. The most frequently occurring treatment emergent serious adverse reaction was peritonitis (8 reactions in 8 patients [8%] in the sevelamer group and 2 reactions in 2 patients [4%] on active control). Thirteen patients (14%) in the sevelamer group and 9 patients (20%) in the active-control group discontinued, mostly for gastrointestinal adverse reactions.
6.2Postmarketing Experience Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or to establish a causal relationship to drug exposure. The following adverse reactions have been identified during postapproval use of sevelamer hydrochloride or sevelamer carbonate: hypersensitivity, pruritus, rash, abdominal pain, bleeding gastrointestinal ulcers, colitis, ulceration, necrosis, fecal impaction, and uncommon cases of ileus, intestinal obstruction, and intestinal perforation.
Appropriate medical management should be given to patients who develop constipation or have worsening of existing constipation to avoid severe complications.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS There are no empirical data on avoiding drug interactions between Renvela and most concomitant oral drugs. For oral medication where a reduction in the bioavailability of that medication would have a clinically significant effect on its safety or efficacy (e.g., cyclosporine, tacrolimus, levothyroxine), consider separation of the timing of the administration of the two drugs [see Clinical Pharmacology (12.3) ] . The duration of separation depends upon the absorption characteristics of the medication concomitantly administered, such as the time to reach peak systemic levels and whether the drug is an immediate-release or an extended-release product.
Where possible consider monitoring clinical responses and/or blood levels of concomitant drugs that have a narrow therapeutic range. Table 5: Sevelamer Drug Interactions Oral drugs for which sevelamer did not alter the pharmacokinetics when administered concomitantly Digoxin Enalapril Iron Metoprolol Warfarin Oral drugs that have demonstrated interaction with sevelamer and are to be dosed separately from Renvela Dosing Recommendations Ciprofloxacin Take at least 2 hours before or 6 hours after sevelamer Mycophenolate mofetil Take at least 2 hours before sevelamer For oral medication where a reduction in the bioavailability of that medication would have a clinically significant effect on its safety or efficacy, consider separation of the timing of administration and/or monitor clinical responses or blood levels of the concomitant medication.
( 7 ) Sevelamer did not alter the pharmacokinetics of digoxin, enalapril, iron, metoprolol and warfarin. ( 7 ) Sevelamer has demonstrated interaction with ciprofloxacin, mycophenolate mofetil, and therefore, these drugs should be dosed separately from Renvela. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Sevelamer carbonate is not absorbed systemically following oral administration and maternal use is not expected to result in fetal exposure to the drug. Clinical Considerations Sevelamer carbonate may decrease serum levels of fat-soluble vitamins and folic acid in pregnant women [see Clinical Pharmacology (12.2) ] . Consider supplementation.
Data Animal data In pregnant rats given dietary doses of 0.5, 1.5, or 4.5 g/kg/day of sevelamer hydrochloride during organogenesis, reduced or irregular ossification of fetal bones, probably due to a reduced absorption of fat-soluble vitamin D, occurred in mid and high-dose groups (human equivalent doses approximately equal to 3–4 times the maximum clinical trial dose of 13 g). In pregnant rabbits given oral doses of 100, 500, or 1000 mg/kg/day of sevelamer hydrochloride by gavage during organogenesis, an increase of early resorptions occurred in the high-dose group (human equivalent dose twice the maximum clinical trial dose).
8.2Lactation Risk Summary Renvela is not absorbed systemically by the mother following oral administration, and breastfeeding is not expected to result in exposure of the child to Renvela. Clinical Considerations Sevelamer carbonate may decrease serum levels of fat-soluble vitamins and folic acid in pregnant women [see Clinical Pharmacology (12.2) ] . Consider supplementation.
8.4Pediatric Use The safety and efficacy of Renvela in lowering serum phosphorus levels was studied in patients 6 years of age and older with CKD. In this study, Renvela was apparently less effective in children with a low baseline serum phosphorus, which described children <13 years of age and children not on dialysis. Given its mechanism of action, Renvela is expected to be effective in lowering serum phosphorus levels in pediatric patients with CKD.
Most adverse events that were reported as related, or possibly related, to sevelamer carbonate were gastrointestinal in nature. No new risks or safety signals were identified with the use of sevelamer carbonate in the trial. Renvela has not been studied in pediatric patients below 6 years of age.
8.5Geriatric Use Clinical studies of Renvela did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Sevelamer carbonate is not absorbed systemically following oral administration and maternal use is not expected to result in fetal exposure to the drug. Clinical Considerations Sevelamer carbonate may decrease serum levels of fat-soluble vitamins and folic acid in pregnant women [see Clinical Pharmacology (12.2) ] . Consider supplementation.
Data Animal data In pregnant rats given dietary doses of 0.5, 1.5, or 4.5 g/kg/day of sevelamer hydrochloride during organogenesis, reduced or irregular ossification of fetal bones, probably due to a reduced absorption of fat-soluble vitamin D, occurred in mid and high-dose groups (human equivalent doses approximately equal to 3–4 times the maximum clinical trial dose of 13 g). In pregnant rabbits given oral doses of 100, 500, or 1000 mg/kg/day of sevelamer hydrochloride by gavage during organogenesis, an increase of early resorptions occurred in the high-dose group (human equivalent dose twice the maximum clinical trial dose).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of Renvela in lowering serum phosphorus levels was studied in patients 6 years of age and older with CKD. In this study, Renvela was apparently less effective in children with a low baseline serum phosphorus, which described children <13 years of age and children not on dialysis. Given its mechanism of action, Renvela is expected to be effective in lowering serum phosphorus levels in pediatric patients with CKD.
Most adverse events that were reported as related, or possibly related, to sevelamer carbonate were gastrointestinal in nature. No new risks or safety signals were identified with the use of sevelamer carbonate in the trial. Renvela has not been studied in pediatric patients below 6 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Renvela did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range.
🆘 Overdosage ▾
10 OVERDOSAGE In CKD patients on dialysis, the maximum dose studied was 14 grams of sevelamer carbonate and 13 grams of sevelamer hydrochloride. There are no reports of overdosage with sevelamer carbonate or sevelamer hydrochloride in patients. Since sevelamer is not absorbed, the risk of systemic toxicity is low.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Renvela contains sevelamer carbonate, a non-absorbed phosphate-binding cross-linked polymer, free of metal and calcium. It contains multiple amines separated by one carbon from the polymer backbone. These amines exist in a protonated form in the intestine and interact with phosphate molecules through ionic and hydrogen bonding.
By binding phosphate in the gastrointestinal tract and decreasing absorption, sevelamer carbonate lowers the phosphate concentration in the serum (serum phosphorus).
12.2Pharmacodynamics In addition to effects on serum phosphorus levels, sevelamer hydrochloride has been shown to bind bile acids in vitro and in vivo in experimental animal models. Because sevelamer binds bile acids, it may interfere with normal fat absorption and thus may reduce absorption of fat-soluble vitamins such as A, D and K. In clinical trials of sevelamer hydrochloride, both the mean total and LDL cholesterol declined by 15%–31%; the clinical significance of this finding, which was observed after 2 weeks, is unclear.
Triglycerides, HDL cholesterol, and albumin did not change.
12.3Pharmacokinetics A mass balance study using 14 C-sevelamer hydrochloride, in 16 healthy male and female volunteers showed that sevelamer hydrochloride is not systemically absorbed. No absorption studies have been performed in patients with renal disease. Drug Interactions In vivo Sevelamer carbonate has been studied in human drug-drug interaction studies (9.6 grams once daily with a meal) with warfarin and digoxin.
Sevelamer hydrochloride, which contains the same active moiety as sevelamer carbonate, has been studied in human drug-drug interaction studies (2.4–2.8 grams single dose or three times daily with meals or two times daily without meals) with ciprofloxacin, digoxin, enalapril, iron, metoprolol, mycophenolate mofetil, and warfarin. Coadministered single dose of 2.8 grams of sevelamer hydrochloride in fasted state decreased the bioavailability of ciprofloxacin by approximately 50% in healthy subjects. Concomitant administration of sevelamer and mycophenolate mofetil in adult and pediatric patients decreased the mean MPA C max and AUC 0–12h by 36% and 26%, respectively.
Sevelamer carbonate or sevelamer hydrochloride did not alter the pharmacokinetics of enalapril, digoxin, iron, metoprolol, and warfarin when coadministered. During postmarketing experience, cases of increased thyroid stimulating hormone (TSH) levels have been reported in patients coadministered sevelamer hydrochloride and levothyroxine. Reduction in concentrations of cyclosporine and tacrolimus leading to dose increases has also been reported in transplant patients when coadministered with sevelamer hydrochloride without any clinical consequences (for example, graft rejection).
The possibility of an interaction cannot be excluded with these drugs.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Renvela contains sevelamer carbonate, a non-absorbed phosphate-binding cross-linked polymer, free of metal and calcium. It contains multiple amines separated by one carbon from the polymer backbone. These amines exist in a protonated form in the intestine and interact with phosphate molecules through ionic and hydrogen bonding.
By binding phosphate in the gastrointestinal tract and decreasing absorption, sevelamer carbonate lowers the phosphate concentration in the serum (serum phosphorus).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Tablets: Renvela ® (sevelamer carbonate) tablets, for oral use is supplied as white oval, film-coated, compressed tablets, engraved with RV800 on one side, containing 800 mg of sevelamer carbonate on an anhydrous basis. 1 Bottle of 270 ct 800 mg tablets (NDC 58468-0133-1) Powder: Renvela ® (sevelamer carbonate) for oral suspension is supplied as opaque, foil-lined, heat-sealed, packets containing 0.8 g or 2.4 g of sevelamer carbonate on an anhydrous basis. 1 Box (NDC 58468-0131-2) of 90 ct 2.4 g packets (NDC 58468-0131-1) 1 Box (NDC 58468-0132-2) of 90 ct 0.8 g packets (NDC 58468-0132-1) Storage: Store at 25°C (77°F): excursions permitted to 15°C–30°C (59°F–86°F). [See USP controlled room temperature] Protect from moisture.
📦 Storage and Handling ▾
Storage: Store at 25°C (77°F): excursions permitted to 15°C–30°C (59°F–86°F). [See USP controlled room temperature] Protect from moisture.
📋 Description ▾
11 DESCRIPTION The active ingredient in Renvela is sevelamer carbonate, a polymeric amine that binds phosphate and is meant for oral administration. It was developed as a pharmaceutical alternative to sevelamer hydrochloride (Renagel ® ). Sevelamer carbonate is an anion exchange resin, with the same polymeric structure as sevelamer hydrochloride, in which carbonate replaces chloride as the counterion.
While the counterions differ for the two salts, the polymer itself, the active moiety involved in phosphate binding, is the same. Renvela (sevelamer carbonate) is known chemically as poly(allylamine- co -N,N′-diallyl-1,3-diamino-2-hydroxypropane) carbonate salt. Sevelamer carbonate is hygroscopic, but insoluble in water.
The structure is represented in Figure 1. Figure 1: Chemical Structure of Sevelamer Carbonate a, b = number of primary amine groups a + b = 9 c = number of cross-linking groups c = 1 m = large number to indicate extended polymer network Chemical Structure Renvela Tablets: Each film-coated tablet of Renvela contains 800 mg of sevelamer carbonate on an anhydrous basis. The inactive ingredients are hypromellose, diacetylated monoglycerides, microcrystalline cellulose, sodium chloride, and zinc stearate.
Renvela Powder: Each packet of Renvela powder contains 0.8 or 2.4 g of sevelamer carbonate on an anhydrous basis. The inactive ingredients are natural and artificial citrus flavor, propylene glycol alginate, sodium chloride, sucralose, and ferric oxide (yellow).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients to take Renvela with meals and adhere to their prescribed diets. For patients using an oral medication where a reduction in the bioavailability of that medication would have a clinically significant effect on its safety or efficacy, advise the patient to take the oral medication at least one hour before or three hours after Renvela. For Renvela powder, brief the patient on preparation of the powder in water.
Advise patients to report new onset or worsening of existing constipation or bloody stools promptly to their physician [see Warnings and Precautions (5.1) ] .