
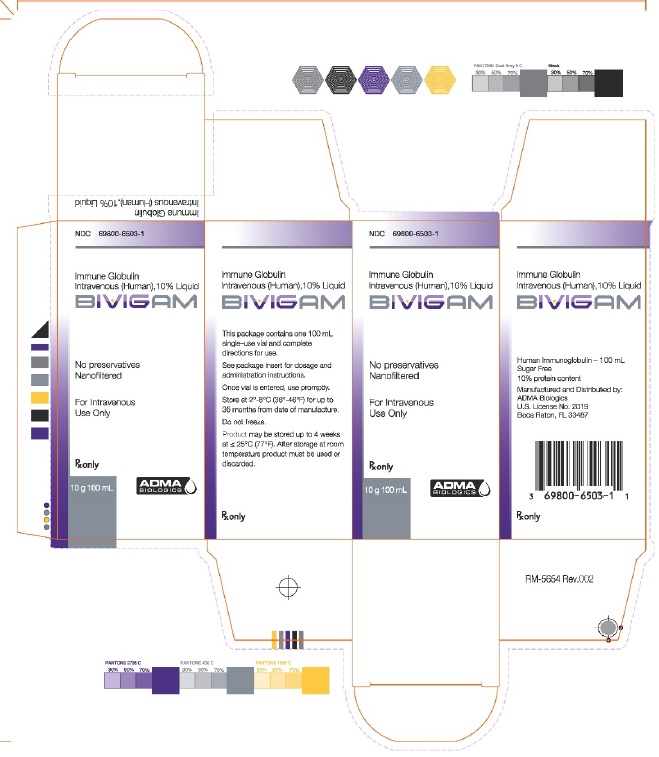
BIVIGAM Immune Globulin Intravenous (Human) 10% 10 g/100mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunoglobulin G class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Your immune system normally makes antibodies called IgG to fight off infections from bacteria, viruses, and other germs. If you have a condition like primary humoral immunodeficien...
- What exactly is this medicine doing for me — why do I need it?
- Most intravenous products are given every 3 to 4 weeks, and your doctor will adjust the timing based on your IgG blood levels and how you're doing clinically. Each infusion takes a...
- How often will I need to get this infusion, and how long does each one take?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $11.92 | $1,192.41 / 100 ml |
| Medicare drug plans payPart D · Q2 2026 | $15.69 | $1,568.84 / 100 ml |
| Medicare Part B allowsASP · J1556 | $81.241 / J1556 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bivigam 10 g/100mLthis 69800-6503-01 | ADMA | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Dec 19, 2024 |
Is there a biosimilar for BIVIGAM 10 GM/100 ML (10%) VL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 69800-6503-01 You're viewing this | 1 VIAL, SINGLE-USE in 1 CARTON (69800-6503-1) / 100 mL in 1 VIAL, SINGLE-USE (69800-6503-2) | 2013-01-21 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: THROMBOSIS, RENAL DYSFUNCTION AND ACUTE RENAL FAILURE Thrombosis may occur with immune globulin (IGIV) products, including BIVIGAM. Risk factors may include: advanced age, prolonged immobilization, hypercoagulable conditions, history of venous or arterial thrombosis, use of estrogens, indwelling central vascular catheters, hyperviscosity and cardiovascular risk factors. Thrombosis may occur in the absence of known risk factors.
(see Warnings and Precautions [5.1] , Patient Counseling Information [17.2] ). Use of Immune Globulin Intravenous (IGIV) products, particularly those containing sucrose, has been reported to be associated with renal dysfunction, acute renal failure, osmotic nephrosis, and death 1,2 . Patients at risk of acute renal failure include those with any degree of pre-existing renal insufficiency, diabetes mellitus, advanced age (above 65 years of age), volume depletion, sepsis, paraproteinemia, or receiving known nephrotoxic drugs ( see Warnings and Precautions [5.3] ) .
Renal dysfunction and acute renal failure occur more commonly in patients receiving IGIV products containing sucrose. BIVIGAM does not contain sucrose. For patients at risk of thrombosis, renal dysfunction or renal failure, administer BIVIGAM at the minimum dose and infusion rate practicable.
Ensure adequate hydration in patients before administration. Monitor for signs and symptoms of thrombosis and assess blood viscosity in patients at risk for hyperviscosity ( see Dosage and Administration [2.2 , 2.3] , Warnings and Precautions [5.3] ). WARNING: THROMBOSIS, RENAL DYSFUNCTION AND ACUTE RENAL FAILURE See full prescribing information for complete boxed warning.
Thrombosis may occur with immune globulin intravenous (IGIV) products, including BIVIGAM. Risk factors may include: advanced age, prolonged immobilization, hypercoagulable conditions, a history of venous or arterial thrombosis, use of estrogens, indwelling vascular catheters, hyperviscosity and cardiovascular risk factors. Renal dysfunction, acute renal failure, osmotic nephrosis, and death may occur with the administration of Immune Globulin Intravenous (Human) (IGIV) products in predisposed patients. [ 5.3 ] Renal dysfunction and acute renal failure occur more commonly in patients receiving IGIV products containing sucrose.
BIVIGAM does not contain sucrose. For patients at risk of thrombosis, renal dysfunction or renal failure, administer BIVIGAM at the minimum dose and infusion rate practicable. Ensure adequate hydration in patients before administration.
Monitor for signs and symptoms of thrombosis and assess blood viscosity in patients at risk for hyperviscosity. [ 2.3 , 5.3 ]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BIVIGAM is an Immune Globulin Intravenous (Human), 10% Liquid, indicated for the treatment of adults and pediatric patients 2 years of age and older with primary humoral immunodeficiency (PI). [1]
1.1Primary Humoral Immunodeficiency BIVIGAM is an Immune Globulin Intravenous (Human), 10% Liquid, indicated for the treatment of adults and pediatric patients 2 years of age and older with primary humoral immunodeficiency (PI). This includes, but is not limited to, the humoral immune defect in common variable immunodeficiency (CVID), X-linked agammaglobulinemia, congenital agammaglobulinemia, Wiskott-Aldrich syndrome, and severe combined immunodeficiencies.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For Intravenous Use Only Intravenous Use Only Indication Dose Initial Infusion Rate Maintenance Infusion Rate (if tolerated) PI 300-800 mg/kg every 3-4 weeks 0.5 mg/kg/min for first 10 minutes Increase every 20 minutes (if tolerated) by 0.8 mg/kg/min up to 6 mg/kg/min. Ensure that patients with pre-existing renal insufficiency are not volume depleted; discontinue BIVIGAM if renal function deteriorates. [5.3] For patients at risk of renal dysfunction or thrombotic events, administer BIVIGAM at the minimum infusion rate practicable. [5.1 , 5.3]
2.1Preparation and Handling BIVIGAM is a clear or slightly opalescent, colorless to pale yellow solution. Inspect BIVIGAM visually for particulate matter and discoloration prior to administration. Do not use if the solution is cloudy or turbid, or contains particulate matter.
Allow refrigerated product to come to room temperature before use. Do not freeze or heat. Do not use any solution that has been frozen or heated.
DO NOT SHAKE. Do not mix BIVIGAM with other IGIV products or other intravenous medications. If large doses of BIVIGAM are to be administered, several vials may be pooled using aseptic technique into sterile infusion bags and infused.
Do not dilute BIVIGAM. BIVIGAM contains no preservatives. BIVIGAM vial is for single use only.
Any vial of BIVIGAM that has been entered should be used promptly and any unused portion should be discarded immediately. Do not reuse or save for future use. Maintain BIVIGAM at room temperature during administration.
Do not use after expiration date.
2.2Recommended Dose As there are significant differences in the half-life of IgG among patients with primary humoral immunodeficiency, the frequency and amount of immunoglobulin therapy may vary from patient to patient. The proper amount can be determined by monitoring clinical response. The recommended dose of BIVIGAM for replacement therapy in primary humoral immunodeficiency in adults and children 2 years of age and older, is 300 to 800 mg/kg body weight administered every 3 to 4 weeks.
The dosage may be adjusted over time to achieve the desired trough levels and clinical response. BIVIGAM dose adjustments may be required in patients who fail to maintain trough total IgG concentrations of at least 500 mg/dL with a target of 600 mg/dL. Starting with the second infusion, the dose will be adjusted proportionally, targeting a trough of ≥ 600 mg/dL, based on the previous trough and the associated dose.
2.3Administration It has been reported that the frequency of adverse drug reactions to IGIV increases with the infusion rate. Initial infusion rates should be slow. If there are no adverse drug reactions, the infusion rate for subsequent infusions can be slowly increased to the maximum rate.
For patients experiencing adverse drug reactions, it is advisable to reduce the infusion rate in subsequent infusions. Table 1: Recommended Infusion Rates for BIVIGAM Indication Initial Infusion Rate (for first 10 minutes) Maintenance Infusion Rate (if tolerated) PI 0.5 mg/kg/min (0.005 mL/kg/min) Increase every 20 minutes (if tolerated) by 0.8 mg/kg/min up to 6 mg/kg/min. Monitor patient vital signs throughout the infusion.
Slow or stop the infusion if adverse reactions occur. If symptoms subside promptly, the infusion may be resumed at a lower rate that is comfortable for the patient. Ensure that patients with pre-existing renal insufficiency are not volume depleted.
For patients judged to be at risk for renal dysfunction or thrombotic events, administer BIVIGAM at the minimum infusion rate practicable, and consider discontinuation of administration if renal function deteriorates ( see Boxed Warning, Warnings and Precautions [5.1 , 5.3] ).
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS BIVIGAM is a liquid solution containing 10% IgG (100 mg/mL) for intravenous infusion. BIVIGAM is a liquid solution containing 10% IgG (100mg/mL) for intravenous infusion; (5g in 50mL solution, 10g in 100mL solution). [3]
⛔ Contraindications ▾
4 CONTRAINDICATIONS BIVIGAM is contraindicated in patients who have had an anaphylactic or severe systemic reaction to the administration of human immune globulin. BIVIGAM is contraindicated in IgA deficiency patients with antibodies to IgA and a history of hypersensitivity. History of anaphylactic or severe systemic reactions to human immunoglobulin. [4] IgA deficient patients with antibodies to IgA and a history of hypersensitivity. [4 , 5.2]
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Thrombotic events have occurred in patients receiving IGIV therapy. Monitor patients with known risk factors for thrombotic events; consider baseline assessment of blood viscosity for those at risk of hyperviscosity. [5.1 , 5.4] IgA deficient patients with antibodies against IgA are at greater risk of developing severe hypersensitivity and anaphylactic reactions. Have medications such as epinephrine available immediately to treat any acute severe hypersensitivity reactions. [4 , 5.2] Monitor renal function, including blood urea nitrogen (BUN), serum creatinine, and urine output in patients at risk of developing acute renal failure. [5.3 , 5.9] Hyperproteinemia, increased serum viscosity, and hyponatremia or pseudohyponatremia can occur in patients receiving IGIV therapy. [5.4] Aseptic meningitis syndrome (AMS) has been reported with IGIV treatments, especially with high doses or rapid infusion. [5.5] Hemolytic anemia can develop subsequent to treatment with IGIV products.
Monitor patients for hemolysis and hemolytic anemia. [5.6] Monitor patients for pulmonary adverse reactions (Transfusion-related acute lung injury [TRALI]). If transfusion-related acute lung injury is suspected, test the product and patient for antineutrophil antibodies. [5.7] Because this product is made from human blood, it may carry a risk of transmitting infectious agents, e.g., viruses, and theoretically, the Creutzfeldt-Jakob disease (CJD) agent. [5.8]
5.1Thrombosis Thrombosis may occur following treatment with immune globulin products (IGIV), including BIVIGAM. 4,5,6 Risk factors may include: advanced age, prolonged immobilization, hypercoagulable conditions, history of venous or arterial thrombosis, use of estrogens, indwelling central vascular catheters, hyperviscosity and cardiovascular risk factors. Thrombosis may occur in the absence of known risk factors Consider baseline assessment of blood viscosity in patients at risk for hyperviscosity, including those with cryoglobulins, fasting chylomicronemia/markedly high triacylglycerols (triglycerides), or monoclonal gammopathies.
For patients at risk of thrombosis, administer BIVIGAM at the minimum dose and infusion rate practicable. Ensure adequate hydration in patients before administration. Monitor for signs and symptoms of thrombosis and assess blood viscosity in patients at risk for hyperviscosity ( see Boxed Warning , Dosage and Administration [2.3] , Patient Counseling Information [17.2] ).
5.2Hypersensitivity Severe hypersensitivity reactions may occur with IGIV products, including BIVIGAM. In case of hypersensitivity, discontinue BIVIGAM infusion immediately and institute appropriate treatment. Medications such as epinephrine should be available for immediate treatment of acute hypersensitivity reactions.
BIVIGAM contains trace amounts of IgA (≤ 200 micrograms per milliliter) ( see Description [11] ). Patients with known antibodies to IgA may have a greater risk of developing potentially severe hypersensitivity and anaphylactic reactions. BIVIGAM is contraindicated in IgA deficient patients with antibodies against IgA and a history of hypersensitivity reaction ( see Contraindications [4] ).
5.3Acute Renal Dysfunction and Acute Renal Failure Acute renal dysfunction/failure, osmotic nephrosis, and death 1,2 may occur upon use of human IGIV products. Ensure that patients are not volume depleted before administering BIVIGAM. Periodic monitoring of renal function and urine output is particularly important in patients judged to be at increased risk of developing acute renal failure 2 .
Assess renal function, including measurement of blood urea nitrogen (BUN) and serum creatinine, before the initial infusion of BIVIGAM and at appropriate intervals thereafter. If renal function deteriorates, consider discontinuing BIVIGAM ( see Patient Counseling Information [17.1] ). In patients who are at risk of developing renal dysfunction, because of pre-existing renal insufficiency…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Serious adverse reactions observed in clinical trial subjects receiving BIVIGAM were vomiting and dehydration in one subject. The most common adverse reactions to BIVIGAM (reported in ≥5% of clinical study subjects) were headache, fatigue, infusion site reaction, nausea, sinusitis, blood pressure increased, diarrhea, dizziness, and lethargy. The most common adverse reactions to BIVIGAM (reported in ≥5% of clinical study subjects) were headache, fatigue, infusion site reaction, nausea, sinusitis, blood pressure increased, diarrhea, dizziness, and lethargy. [6] To report SUSPECTED ADVERSE REACTIONS, contact ADMA Biologics at (800) 458-4244 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials cannot be directly compared to rates in the clinical trials of another product and may not reflect the rates observed in clinical practice. In a multicenter, open-label, non-randomized clinical trial, 63 subjects with PI, on regular IGIV replacement therapy, received doses of BIVIGAM ranging from 254 to 1029 mg/kg (median dose 462.8 mg/kg) every 3 weeks or 4 weeks for up to 12 months (mean 317.3 days; range 66 – 386 days) ( see Clinical Studies [ 14 ] ).
The use of pre-medication was discouraged; however, if subjects required pre-medication (antipyretic, antihistamine, or antiemetic agent) for recurrent reactions to immune globulins, they were allowed to continue those medications for this trial. Of the 746 infusions administered, 41 (65%) subjects received premedication prior to 415 (56%) infusions. Fifty-nine subjects (94%) had an adverse reaction at some time during the study.
The proportion of subjects who had at least one adverse reaction was the same for both the 3- and 4-week cycles. The most common adverse reactions observed in this clinical trial were headache (32 subjects, 51%), sinusitis (24 subjects, 38%), fatigue (18 subjects, 29%), upper respiratory tract infection (16 subjects, 25%), diarrhea (13 subjects, 21%), cough (14 subjects, 22%), bronchitis (12 subjects, 19%), pyrexia (12 subjects, 19%), and nausea (9 subjects, 14%). Adverse reactions (ARs) are those occurring during or within 72 hours after the end of an infusion.
In this study, the upper bound of the 1-sided 95% confidence interval for the proportion of BIVIGAM infusions with one or more temporally associated adverse reactions was 31%. The total number of adverse reactions was 431 (a rate of
0.58ARs per infusion). Table 2: Adverse Reactions (ARs) (within 72 hours after the end of a BIVIGAM infusion) in ≥5% of Subjects ARs No. Subjects Reporting ARs (% of Subjects) [n=63] No.
Infusions With ARs (% of Infusions) [n=746] Headache 27 (43%) 115 (15.4%) Fatigue 15 (24%) 59 (7.9%) Infusion Site Reaction 5 (8%) 5 (0.7%) Nausea 5 (8%) 8 (1.1%) Sinusitis 5 (8%) 5 (0.7%) Blood Pressure Increased 4 (6%) 5 (0.7%) Diarrhea 4 (6%) 4 (0.5%) Dizziness 4 (6%) 4 (0.5%) Lethargy 4 (6%) 4 (0.5%) Back Pain 3 (5%) 3 (0.4%) Blood Pressure Diastolic Decreased 3 (5%) 5 (0.7%) Fibromyalgia a 3 (5%) 17 (2.3%) Migraine 3 (5%) 8 (1.1%) Myalgia 3 (5%) 4 (0.5%) Pharyngolaryngeal Pain 3 (5%) 3 (0.4%) a Symptoms occurring under pre-existing fibromyalgia Seven subjects (11.1%) experienced 11 serious ARs.
Two of these were related serious ARs (vomiting and dehydration) that occurred in one subject. One subject withdrew from the study due to ARs related to BIVIGAM (lethargy, headache, tachycardia and pruritus). All 63 subjects enrolled in this study had a negative direct antiglobulin (Coombs’) test at baseline.
During the study, no subjects showed clinical evidence of hemolytic anemia. No cases of transmission of viral diseases or CJD have been associated with the use of BIVIGAM. During the clinical trial no subjects tested positive for infection due to human immunodeficiency virus (HIV), hepatitis B virus (HBV), or hepatitis C virus (…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Passive transfer of antibodies may transiently interfere with the immune response to live virus vaccines, such as measles, mumps, rubella, and varicella. [7] Passive transfer of antibodies may confound the results of serological testing. [5.10]
7.1Live Virus Vaccines Immunoglobulin administration may transiently impair the efficacy of live attenuated virus vaccines such as measles, mumps, rubella, and varicella because the continued presence of high levels of passively acquired antibody may interfere with an active antibody response. 15,16 The immunizing physician should be informed of recent therapy with BIVIGAM so that appropriate measures may be taken (see Patient Counseling Information [17.7] ).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Use in pregnant women has not been evaluated. Use BIVIGAM in pregnant women only if clearly needed. [8.1] Geriatric Use: In patients over age 65 or in any patient at risk of developing renal insufficiency, do not exceed the recommended dose, and infuse BIVIGAM at the minimum infusion rate practicable. [8.5]
8.1Pregnancy No human data are available to indicate the presence or absence of drug-associated risk. Animal reproductive studies have not been conducted with BIVIGAM. It is not known whether BIVIGAM can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity.
Immune globulins cross the placenta from maternal circulation increasingly after 30 weeks of gestation. BIVIGAM should be given to pregnant women only if clearly needed. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
8.2Lactation No human data are available to indicate the presence or absence of drug-associated risk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for BIVIGAM and any potential adverse effects on the breastfed infant from BIVIGAM or from the underlying maternal condition.
8.4Pediatric Use BIVIGAM was evaluated in 25 pediatric patients (3 children ages 2 to <6, 9 children ages 6 to <12, and 13 adolescents ages 12 to 16 years) with PI. The safety and effectiveness of BIVIGAM for the treatment of PI has been established in pediatric patients 2 years of age and older, based on data from 2 prospective, open-label, single-arm, multi-center studies, supported by evidence from a population PK analysis of adult and pediatric PK data ( see Adverse Reactions [ 6.1 ], Clinical Pharmacology [ 12.3 ], and Clinical Studies [ 14.1 ] ).
PK, safety and efficacy were similar to those in adults. No specific dose requirements were necessary to achieve the targeted serum IgG levels in the pediatric subjects. The safety and effectiveness of BIVIGAM has not been established in pediatric patients with PI who are under the age of 2 ( see Clinical Studies [ 14 ] ).
8.5Geriatric Use BIVIGAM should be used with caution in patients age 65 and over who are judged to be at increased risk of developing renal insufficiency or thrombotic events (see Boxed Warning, Warnings and Precautions [5.1 , 5.3] ). Do not exceed recommended doses and administer BIVIGAM at the minimum infusion rate practicable. BIVIGAM was evaluated in 9 patients age 65 and older with PI.
This number of geriatric patients is not sufficient to determine whether they respond differently from younger patients ( see Clinical Studies [14] ).
🤰 Pregnancy ▾
8.1Pregnancy No human data are available to indicate the presence or absence of drug-associated risk. Animal reproductive studies have not been conducted with BIVIGAM. It is not known whether BIVIGAM can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity.
Immune globulins cross the placenta from maternal circulation increasingly after 30 weeks of gestation. BIVIGAM should be given to pregnant women only if clearly needed. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use BIVIGAM was evaluated in 25 pediatric patients (3 children ages 2 to <6, 9 children ages 6 to <12, and 13 adolescents ages 12 to 16 years) with PI. The safety and effectiveness of BIVIGAM for the treatment of PI has been established in pediatric patients 2 years of age and older, based on data from 2 prospective, open-label, single-arm, multi-center studies, supported by evidence from a population PK analysis of adult and pediatric PK data ( see Adverse Reactions [ 6.1 ], Clinical Pharmacology [ 12.3 ], and Clinical Studies [ 14.1 ] ).
PK, safety and efficacy were similar to those in adults. No specific dose requirements were necessary to achieve the targeted serum IgG levels in the pediatric subjects. The safety and effectiveness of BIVIGAM has not been established in pediatric patients with PI who are under the age of 2 ( see Clinical Studies [ 14 ] ).
🧓 Geriatric Use ▾
8.5Geriatric Use BIVIGAM should be used with caution in patients age 65 and over who are judged to be at increased risk of developing renal insufficiency or thrombotic events (see Boxed Warning, Warnings and Precautions [5.1 , 5.3] ). Do not exceed recommended doses and administer BIVIGAM at the minimum infusion rate practicable. BIVIGAM was evaluated in 9 patients age 65 and older with PI.
This number of geriatric patients is not sufficient to determine whether they respond differently from younger patients ( see Clinical Studies [14] ).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action BIVIGAM is a replacement therapy in patients with primary humoral immunodeficiency (PI) (e.g. agammaglobulinaemia, hypogammaglobulinaemia, CVID, SCID). The broad spectrum of neutralizing IgG antibodies against bacterial and viral pathogens and their toxins helps to avoid recurrent serious opportunistic infections. IgG antibodies are opsonins that increase phagocytosis and elimination of pathogens from the circulation.
The mechanism of action has not been fully elucidated in PI.
12.2Pharmacodynamics BIVIGAM contains mainly immunoglobulin G (IgG) with a broad spectrum of antibodies against various infectious agents, reflecting the IgG activity found in the donor population. BIVIGAM, which is prepared from pooled plasma from not less than 1,000 donors, has an IgG subclass distribution similar to that of native human plasma. Adequate doses of IGIV can restore an abnormally low IgG level to the normal range.
Standard pharmacodynamics studies were not performed.
12.3Pharmacokinetics In the clinical study assessing the efficacy and safety of BIVIGAM in 63 subjects with PI ( see Clinical Studies [ 14.1 ] ), serum concentrations of total IgG and IgG subclasses were measured in 21 subjects (ages 18 to 75) following the 4th infusion for the 5 subjects on the 3-week dosing interval and following the 5th infusion for the 16 subjects on the 4-week dosing interval. The dose of BIVIGAM used in these subjects ranged from 300 mg/kg to 800 mg/kg. After the infusion, blood samples were taken until Day 21 and Day 28 for the 3-week and 4-week dosing intervals, respectively.
Table 5 summarizes the Total IgG Pharmacokinetic Parameters of BIVIGAM, based on serum concentrations of total IgG. Table 5: Total IgG Pharmacokinetic Parameter Estimates (PK Population) in Adults Statistic 3-week cycle Mean (CV%) [n=5] 4-week cycle Mean (CV%) [n=16] Total Mean (CV%) [n=21] C max (mg/dL) 2184 (13.4) 2122 (20.0) 2137 (18.3) C min (mg/dL) 996 (17.6) 1106 (35.8) 1080 (32.9) T max (h) a 4.05 (NA) 3.47 (NA) 3.50 (NA) AUC tau (day*mg/dL) 27841 (17.7) 35509 (18.2) 33592 (20.5) t ½ (d) 19.6 (21.1) 33.5 (32.0) 30.0 (37.5) CL (dL/d/kg) 0.02 (11.3) 0.01 (32.8) 0.02 (31.0) V ss (dL/kg) 0.584 (22.6) 0.640 (22.1) 0.626 (22.0) AUC tau = steady-state area under the plasma concentration versus time curve with tau = dosing interval; CL = total body clearance; C max = maximum concentration; C min = minimum concentration; CV = coefficient of variation; n = number of subjects; NA = not applicable; SD = standard deviation; T max = time of maximum concentration; t ½ = terminal half-life; V ss = Volume of distribution steady-state; a Median and Range.
The median terminal half-life of BIVIGAM was 30 days for the 21 subjects. Mean trough IgG subclass levels were consistent with physiological values. In a pediatric-only clinical study in 16 children and adolescents ≥2 to ≤16 years of age with PI, 10 subjects in the PK population contributed sufficient samples for the non-compartmental analysis of serum concentrations of total IgG and IgG subclasses after the 5 th infusion (4-week regimen) or 7 th infusion (3-week regimen).
A population pharmacokinetic analysis was conducted using data pooled from the pediatric only clinical study together with the prior study conducted in adult and pediatric subjects with PI. Based on the pooled population pharmacokinetic analysis in 79 subjects using all evaluable total IgG PK concentrations, the clearance of BIVIGAM was similar across age groups (Table 6). After correcting for body weight no other patient-specific factors were found to affect BIVIGAM pharmacokinetics.
Trough concentrations were maintained throughout the study and mean trough concentrations were well above the target trough concentration of 500 mg/dL for both treatment cycles in pediatric (≥ 2 years old) as well as adult subjects at all time points. Table 6 Summary of Total IgG Clearance By Age Group Age group Number of Subjects Mean Ig…
🧬 Mechanism of Action ▾
12.1Mechanism of Action BIVIGAM is a replacement therapy in patients with primary humoral immunodeficiency (PI) (e.g. agammaglobulinaemia, hypogammaglobulinaemia, CVID, SCID). The broad spectrum of neutralizing IgG antibodies against bacterial and viral pathogens and their toxins helps to avoid recurrent serious opportunistic infections. IgG antibodies are opsonins that increase phagocytosis and elimination of pathogens from the circulation.
The mechanism of action has not been fully elucidated in PI.
12.3Pharmacokinetics In the clinical study assessing the efficacy and safety of BIVIGAM in 63 subjects with PI ( see Clinical Studies [ 14.1 ] ), serum concentrations of total IgG and IgG subclasses were measured in 21 subjects (ages 18 to 75) following the 4th infusion for the 5 subjects on the 3-week dosing interval and following the 5th infusion for the 16 subjects on the 4-week dosing interval. The dose of BIVIGAM used in these subjects ranged from 300 mg/kg to 800 mg/kg. After the infusion, blood samples were taken until Day 21 and Day 28 for the 3-week and 4-week dosing intervals, respectively.
Table 5 summarizes the Total IgG Pharmacokinetic Parameters of BIVIGAM, based on serum concentrations of total IgG. Table 5: Total IgG Pharmacokinetic Parameter Estimates (PK Population) in Adults Statistic 3-week cycle Mean (CV%) [n=5] 4-week cycle Mean (CV%) [n=16] Total Mean (CV%) [n=21] C max (mg/dL) 2184 (13.4) 2122 (20.0) 2137 (18.3) C min (mg/dL) 996 (17.6) 1106 (35.8) 1080 (32.9) T max (h) a 4.05 (NA) 3.47 (NA) 3.50 (NA) AUC tau (day*mg/dL) 27841 (17.7) 35509 (18.2) 33592 (20.5) t ½ (d) 19.6 (21.1) 33.5 (32.0) 30.0 (37.5) CL (dL/d/kg) 0.02 (11.3) 0.01 (32.8) 0.02 (31.0) V ss (dL/kg) 0.584 (22.6) 0.640 (22.1) 0.626 (22.0) AUC tau = steady-state area under the plasma concentration versus time curve with tau = dosing interval; CL = total body clearance; C max = maximum concentration; C min = minimum concentration; CV = coefficient of variation; n = number of subjects; NA = not applicable; SD = standard deviation; T max = time of maximum concentration; t ½ = terminal half-life; V ss = Volume of distribution steady-state; a Median and Range.
The median terminal half-life of BIVIGAM was 30 days for the 21 subjects. Mean trough IgG subclass levels were consistent with physiological values. In a pediatric-only clinical study in 16 children and adolescents ≥2 to ≤16 years of age with PI, 10 subjects in the PK population contributed sufficient samples for the non-compartmental analysis of serum concentrations of total IgG and IgG subclasses after the 5 th infusion (4-week regimen) or 7 th infusion (3-week regimen).
A population pharmacokinetic analysis was conducted using data pooled from the pediatric only clinical study together with the prior study conducted in adult and pediatric subjects with PI. Based on the pooled population pharmacokinetic analysis in 79 subjects using all evaluable total IgG PK concentrations, the clearance of BIVIGAM was similar across age groups (Table 6). After correcting for body weight no other patient-specific factors were found to affect BIVIGAM pharmacokinetics.
Trough concentrations were maintained throughout the study and mean trough concentrations were well above the target trough concentration of 500 mg/dL for both treatment cycles in pediatric (≥ 2 years old) as well as adult subjects at all time points. Table 6 Summary of Total IgG Clearance By Age Group Age group Number of Subjects Mean IgG Clearance (dL/day/kg) CV(%) 2 to <6 years 3 0.01 6.9 6 to <12 years 9 0.01 15.9 12 to ≤16 years 13 0.01 21.3 >16 years 54 0.01
24.8CV=coefficient of variation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BIVIGAM is supplied in a single-use, tamper-evident vial. The components used in the packaging for BIVIGAM are not made with natural rubber latex. BIVIGAM is supplied in the following sizes: NDC Number Size Grams Protein 69800-6502-1 50mL 5 69800-6503-1 100mL 10 Storage Store at 2 to 8°C (36 to 46°F) for up to 36 months from date of manufacture.
Do not freeze. Product may be stored up to 4 weeks at ≤ 25°C (77°C). After storage at room temperature product must be used or discarded.
Special Precautions for Storage Do not freeze or heat. Do not use any solutions that have been frozen or heated. Allow refrigerated product to come to room temperature before use.
Do not use after expiration date. Shelf-life BIVIGAM may be stored until expiration date on vial packaging at 2 to 8°C (36 to 46°F). Product may be stored up to 4 weeks at ≤ 25°C (77°C).
After storage at room temperature product must be used or discarded. Incompatibilities Do not dilute. BIVIGAM should be infused using a separate line by itself, without mixing with other intravenous fluids or medications the patient may be receiving.
📦 Storage and Handling ▾
Storage Store at 2 to 8°C (36 to 46°F) for up to 36 months from date of manufacture. Do not freeze. Product may be stored up to 4 weeks at ≤ 25°C (77°C).
After storage at room temperature product must be used or discarded. Special Precautions for Storage Do not freeze or heat. Do not use any solutions that have been frozen or heated.
Allow refrigerated product to come to room temperature before use. Do not use after expiration date. Shelf-life BIVIGAM may be stored until expiration date on vial packaging at 2 to 8°C (36 to 46°F).
Product may be stored up to 4 weeks at ≤ 25°C (77°C). After storage at room temperature product must be used or discarded. Incompatibilities Do not dilute.
BIVIGAM should be infused using a separate line by itself, without mixing with other intravenous fluids or medications the patient may be receiving.
📋 Description ▾
11 DESCRIPTION BIVIGAM is a purified, sterile, ready-to-use preparation of concentrated human immunoglobulin G (IgG) antibodies. The distribution of IgG subclasses is similar to that of normal plasma. 19,20 The active ingredient is human immunoglobulin purified from source human plasma and processed using a modified classical Cohn Method 6 / Oncley Method 9 fractionation process as well as anion and cation exchange steps for added purification.
BIVIGAM contains 100 ± 10 mg/mL protein, of which not less than 96% is human immunoglobulin obtained from source human plasma. It is formulated in water for injection containing 0.100-0.140 M sodium chloride, 0.20-0.29 M glycine, 0.15–0.25% polysorbate 80, and pH 4.0–4.6. BIVIGAM contains ≤ 200 µg/mL of IgA.
Each plasma donation used for the manufacture of BIVIGAM is collected from FDA licensed facilities and undergoes rigorous testing. Plasma donations must test negative for hepatitis B virus (HBV) surface antigen (HBsAg), antibodies to human immunodeficiency virus (HIV) strains 1 and 2 (anti-HIV-1/2), and antibodies to the hepatitis C virus (anti-HCV) as determined by enzyme immuno assay (EIA). In addition, each plasma unit must test negative and/or non-reactive for HIV RNA, HCV RNA, HBV DNA, Hepatitis A Virus (HAV) RNA, and Parvovirus B19 (B19 virus) DNA as determined by Nucleic Acid Amplification Testing (NAT) of plasma minipools.
NAT is also performed on a sample of the manufacturing pool and must be negative and/or non-reactive for HIV RNA, HCV RNA, HBV DNA, and Hepatitis A Virus (HAV) RNA, and the limit for B19 virus DNA in a manufacturing pool is set not to exceed 10 4 IU/mL. The manufacturing process of BIVIGAM employs six steps to remove/inactivate adventitious viruses to minimize the risk of virus transmission. The steps are "Precipitation and removal of fraction III" during cold ethanol fractionation, “Q-membrane filtration”, "Solvent/detergent treatment" (TnBP/ Triton X-100), “Anion exchange chromatography” and “virus filtration”.
In compliance with current guidelines, the steps have been separately validated in a series of in vitro experiments for their capacity to inactivate or remove both enveloped and non-enveloped viruses. Precipitation and removal of fraction III and Q-membrane filtration removes non-enveloped viruses, solvent/detergent treatment represents a virus inactivation step for enveloped viruses, Anion exchange chromatography binds enveloped and non-enveloped viruses, and virus filtration removes both enveloped and non-enveloped viruses by size exclusion.
In addition to the steps above, low pH during several steps of the production process contributes to virus inactivation. The results of virus validation studies for the BIVIGAM process are shown in Table 4, expressed as log 10 reduction factors. Table 4: Virus Removal/Inactivation (log 10 ) Step/Virus HIV BVDV SinV WNV PRV MEV EMC BPV PPV SV40 Virus Type Enveloped Enveloped Enveloped Enveloped Enveloped Non-enveloped Non-enveloped Non-enveloped Non-enveloped Non-enveloped Virus Family Retro Flavi Flavi Flavi Herpes Picorna Picorna Parvo Parvo Polyoma Precipitation and Removal of Fraction III and Depth Filtration - - - - - 5.29 ≥5.70 - ≥5.78 2.00* Q-Membrane Filtration 1 - - - - - - - - 2.02 - Solvent - DetergentTNBP/Triton X- 100 Treatment ≥3.92 ≥5.32 >7.11 >4.96 ≥4.88 - - - - - Anion Exchange Chromatography 1.04 - - - - - - - 1.09 - Virus Nanofiltration ≥4.72 ≥4.67 - - ≥4.15 - ≥6.24 6.18 4.66 >5.02 Low pH Treatment 2 2.43 - - - 3.20 2 - - - - - Total Clearance ≥9.68 ≥9.99 >7.11 >4.96 ≥12.23 5.29 ≥5.70 3 6.18 11.49 >7.02 * without depth filtration HIV , human immunodeficiency virus; BVDV , Bovine viral diarrhea virus, model virus for HCV; SinV , Sindbis virus, model virus for HCV; WNV , West Nile virus; PRV , Pseudorabies virus, model virus for herpes viruses and Hepatitis B virus; MEV , Murine encephalomyelitis virus, model virus for hepatitis A virus; BPV , Bovine parvovirus, model virus for human B19 viru…
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Acute Renal Dysfunction and Acute Renal Failure Instruct patients to immediately report symptoms of decreased urine output, sudden weight gain, fluid retention/edema, and/or shortness of breath. Such symptoms may suggest kidney damage ( see Boxed Warning, Warnings and Precautions [5.3] ).
17.2Thrombosis Instruct patients to immediately report symptoms of thrombosis. These symptoms may include: pain and/or swelling of an arm or legs/feet with warmth over the affected area, discoloration of an arm or leg, unexplained shortness of breath, acute chest pain or discomfort that worsens on deep breathing, unexplained rapid pulse, numbness or weakness on one side of the body. ( see Warnings and Precautions [5.1] ).
17.3Aseptic Meningitis Syndrome (AMS) Instruct patients to immediately report signs and symptoms of AMS. These symptoms include severe headache, neck stiffness, drowsiness, fever, sensitivity to light, painful eye movements, nausea and vomiting ( see Warnings and Precautions [5.5] ).
17.4Hemolysis Instruct patients to immediately report signs and symptoms of hemolysis. These symptoms include fatigue, increased heart rate, yellowing of skin or eyes, dark-colored urine ( see Warnings and Precautions [5.6] ).
17.5Transfusion-Related Acute Lung Injury (TRALI) Instruct patients to immediately report signs and symptoms of TRALI. These symptoms include trouble breathing, chest pain, blue lips or extremities, fever ( see Warnings and Precautions [5.7] ).
17.6Transmissible Infectious Agents Inform patients that BIVIGAM is made from human plasma and may contain infectious agents that can cause disease. While the risk that BIVIGAM can transmit an infection has been reduced by screening plasma donors for prior exposure, testing donated plasma, and inactivating or removing certain viruses during manufacturing, patients should report any symptoms that concern them (see Description [11] and Warnings and Precautions [5.8] ).
17.7Live Virus Vaccines Inform patients that BIVIGAM can interfere with their immune response to live viral vaccines (e.g., measles, mumps, rubella, and varicella), and instruct patients to notify their healthcare professional of this potential interaction when they are receiving vaccinations ( see Drug Interactions [7] ).