
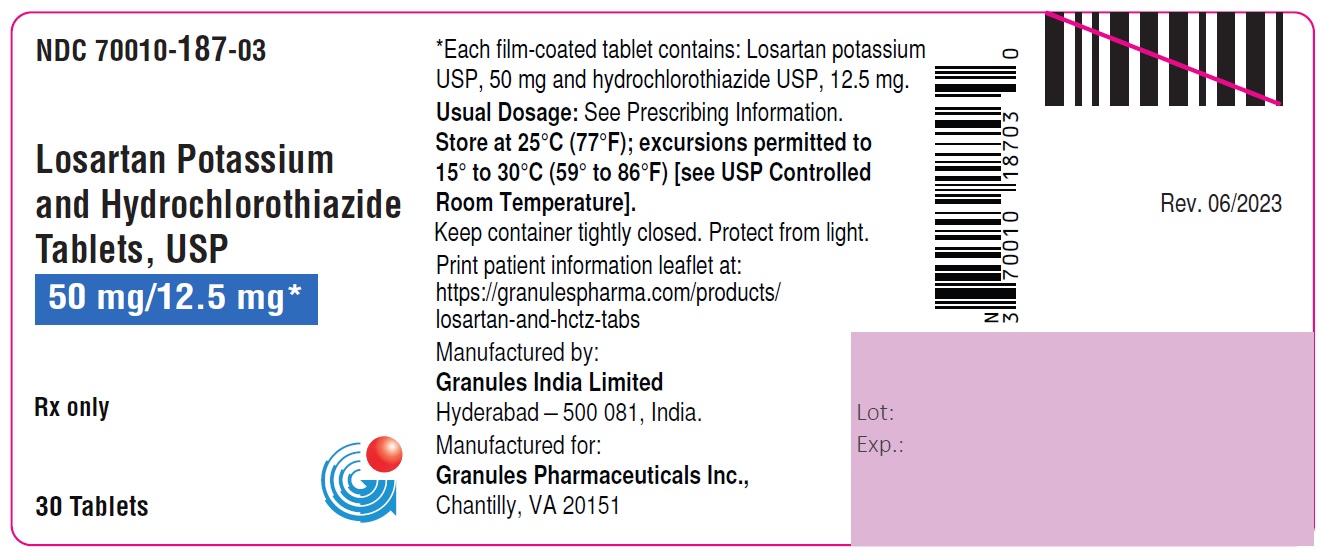
Losartan Potassium and Hydrochlorothiazide 50 mg; 12.5 mg Tablet, Film Coated, 30-count — NDC 70010-187-03 (Billing 70010-0187-03)
This is a package of 30 tablets of Losartan Potassium and Hydrochlorothiazide 50 mg; 12.5 mg Tablet, Film Coated from Granules Pharmaceuticals Inc., marketed since Sep 2023 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Losartan Potassium And Hydrochlorothiazide (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 979464
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Angiotensin 2 Receptor Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats high blood pressure and helps lower the risk of heart attack and stroke. It also reduces stroke risk in people with high blood pressure and a thickened heart wall (left v...
- It is a tablet taken by mouth, usually once a day. Your prescriber may adjust the strength after about 3 weeks. Follow your label and keep taking it even if you feel fine.
- Most people tolerate it well. Dizziness, cough, back pain, stomach pain, a cold-like infection, palpitations or a rash can happen. Call your doctor if they bother you.
- Seek emergency help for swelling of your face, lips, tongue or throat, or trouble breathing. Call your doctor promptly for fainting, sudden eye pain or vision changes, severe skin...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1658 | $4.97 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70010-0187-03 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | 2023-09-29 | — | Active |
| 70010-0187-10 70010-187-10 | 1000 TABLET, FILM COATED in 1 BOTTLE | 2023-09-29 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70010-0187-10?
What NDC number is used to bill for this package of Losartan Potassium and Hydrochlorothiazide 50 mg; 12.5 mg Tablet, Film Coated?
Therapeutic equivalents
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 7773C1ROEU
Low-substituted hydroxypropyl cellulose is a plant-derived thickener and binder made from cellulose. In medicines, it helps bind tablet ingredients together, controls how quickly the medicine dissolves, and improves texture in liquids and semi-solid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue losartan potassium and hydrochlorothiazide tablets as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions (5.1)] . WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue losartan potassium and hydrochlorothiazide tablets as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Losartan potassium and hydrochlorothiazide tablet is a combination of losartan, an angiotensin II receptor blocker (ARB) and hydrochlorothiazide, a diuretic indicated for: • Treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. (1.1) • Reduction of the risk of stroke in patients with hypertension and left ventricular hypertrophy.
There is evidence that this benefit does not apply to Black patients. (1.2)
1.1Hypertension Losartan potassium and hydrochlorothiazide tablets are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure lowers the risk of fatal and non-fatal cardiovascular (CV) events, primarily strokes and myocardial infarction. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including losartan and hydrochlorothiazide.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in Black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. This fixed dose combination is not indicated for initial therapy of hypertension, except when the hypertension is severe enough that the value of achieving prompt blood pressure control exceeds the risk of initiating combination therapy in these patients [see Clinical Studies (14) and Dosage and Administration (2.1)].
Losartan potassium and hydrochlorothiazide tablets may be administered with other antihypertensive agents.
1.2Hypertensive Patients with Left Ventricular Hypertrophy Losartan potassium and hydrochlorothiazide tablets are indicated to reduce the risk of stroke in patients with hypertension and left ventricular hypertrophy, but there is evidence that this benefit does not apply to Black patients. [See Use in Specific Populations (8.6) , Clinical Pharmacology (12.3), and Dosage and Administration (2.2).]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension Usual starting dose: 50/12.5 mg once daily. (2.1) Titrate as needed to a maximum dose of 100/25 mg. (2.1) Hypertensive Patients with Left Ventricular Hypertrophy Not controlled on monotherapy: Initiate with 50/12.5 mg. Titrate as needed to a maximum of 100/25 mg. (2.2)
2.1Hypertension The usual starting dose of losartan potassium and hydrochlorothiazide tablet is 50/12.5 (losartan 50 mg/hydrochlorothiazide 12.5 mg) once daily. The dosage can be increased after 3 weeks of therapy to a maximum of 100/25 (losartan 100 mg/hydrochlorothiazide 25 mg) once daily as needed to control blood pressure [see Clinical Studies (14.2) ]. Initiate a patient whose blood pressure is not adequately controlled with losartan 50 mg monotherapy with losartan potassium and hydrochlorothiazide tablet 50/12.5 once daily.
If blood pressure remains uncontrolled after about 3 weeks of therapy, the dosage may be increased to two tablets of losartan potassium and hydrochlorothiazide 50/12.5 once daily or one tablet of losartan potassium and hydrochlorothiazide 100/25 once daily. Initiate a patient whose blood pressure is not adequately controlled with losartan 100 mg monotherapy with losartan potassium and hydrochlorothiazide tablet 100/12.5 (losartan 100 mg/hydrochlorothiazide 12.5 mg) once daily. If blood pressure remains uncontrolled after about 3 weeks of therapy, increase the dose to two tablets of losartan potassium and hydrochlorothiazide 50/12.5 once daily or one tablet of losartan potassium and hydrochlorothiazide 100/25 once daily.
Initiate a patient whose blood pressure is inadequately controlled with hydrochlorothiazide 25 mg once daily, or is controlled but who experiences hypokalemia with this regimen, on losartan potassium and hydrochlorothiazide tablet 50/12.5 once daily, reducing the dose of hydrochlorothiazide without reducing the overall expected antihypertensive response. Evaluate the clinical response to losartan potassium and hydrochlorothiazide tablet 50/12.5 and, if blood pressure remains uncontrolled after about 3 weeks of therapy, increase the dose to two tablets of losartan potassium and hydrochlorothiazide 50/12.5 once daily or one tablet of losartan potassium and hydrochlorothiazide 100/25 once daily.
2.2Hypertensive Patients with Left Ventricular Hypertrophy In patients whose blood pressure is not adequately controlled on 50 mg losartan potassium, initiate treatment with losartan potassium and hydrochlorothiazide tablets 50/12.5. If additional blood pressure reduction is needed, increase the dose to losartan potassium and hydrochlorothiazide tablet 100/12.5, followed by losartan potassium and hydrochlorothiazide tablet 100/25. For further blood pressure reduction add other antihypertensives [see Clinical Studies (14)] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • 50 mg/12.5 mg: yellow color film-coated, oval shaped tablets debossed with "I23" on one side and plain on other side. • 100 mg/12.5 mg: white to off white, film-coated, oval shaped tablets debossed with "I24" on one side and plain on other side. • 100 mg/25 mg: yellow color film-coated, oval shaped tablets debossed with "I27" on one side and plain on other side. Tablets (losartan potassium/hydrochlorothiazide content): 50/12.5 mg; 100/12.5 mg; and 100/25 mg. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Losartan potassium and hydrochlorothiazide tablets are contraindicated: • In patients who are hypersensitive to any component of this product. • In patients with anuria • For coadministration with aliskiren in patients with diabetes Hypersensitivity to any component of losartan potassium and hydrochlorothiazide tablets. (4) Anuria. (4) Coadministration with aliskiren in patients with diabetes. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypotension: Correct volume or salt depletion prior to administration of losartan potassium and hydrochlorothiazide. (5.2) • Monitor renal function and potassium in susceptible patients. (5.3) • Observe for clinical signs of fluid or electrolyte imbalance. (5.5) • Acute angle-closure glaucoma. (5.6) • Exacerbation of systemic lupus erythematosus. (5.7)
5.1Fetal Toxicity Losartan potassium and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue losartan potassium and hydrochlorothiazide as soon as possible. Thiazides cross the placental barrier and appear in cord blood.
Adverse reactions include fetal or neonatal jaundice, thrombocytopenia [see Use in Specific Populations (8.1)] .
5.2Hypotension in Volume- or Salt-Depleted Patients In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients (e.g., those being treated with high doses of diuretics), symptomatic hypotension may occur after initiation of treatment with losartan potassium and hydrochlorothiazide. Correct volume or salt depletion prior to administration of losartan potassium and hydrochlorothiazide. Do not use losartan potassium and hydrochlorothiazide as initial therapy in patients with intravascular volume depletion.
5.3Impaired Renal Function Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on losartan potassium and hydrochlorothiazide. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on losartan potassium and hydrochlorothiazide [see Drug Interactions (7.3) and Use in Specific Populations (8.8)] .
5.4Hypersensitivity Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma but are more likely in patients with such a history [ see Adverse Reactions (6.2) ] .
5.5Electrolyte and Metabolic Effects In double-blind clinical trials of various doses of losartan potassium and hydrochlorothiazide, the incidence of hypertensive patients who developed hypokalemia (serum potassium <3.5 mEq/L) was 6.7% versus 3.5% for placebo; the incidence of hyperkalemia (serum potassium >5.7 mEq/L) was 0.4% versus 0% for placebo. Losartan potassium and hydrochlorothiazide tablet contains hydrochlorothiazide which can cause hypokalemia, hyponatremia and hypomagnesemia. Hypomagnesemia can result in hypokalemia which may be difficult to treat despite potassium repletion.
Losartan potassium and hydrochlorothiazide tablet also contains losartan which can cause hyperkalemia. Monitor serum electrolytes periodically [see Drug Interactions (7.1)] . Concomitant use of other drugs that may increase serum potassium may lead to hyperkalemia [see Drug Interactions (7.1)] .
Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides. Hyperuricemia may occur or frank gout may be precipitated in patients receiving thiazide therapy. Because losartan decreases uric acid, losartan in combination with hydrochlorothiazide attenuates the diuretic-induced hyperuricemia.
Hydrochlorothiazid… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥2% and greater than placebo) are dizziness, upper respiratory infection, cough, and back pain. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Granules Pharmaceuticals Inc., at 1-877-770-3183 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Losartan potassium-hydrochlorothiazide has been evaluated for safety in 858 patients treated for essential hypertension and 3,889 patients treated for hypertension and left ventricular hypertrophy. Most adverse reactions have been mild and transient in nature and have not required discontinuation of therapy.
In controlled clinical trials, discontinuation of therapy due to clinical adverse events was required in only 2.8% and 2.3% of patients treated with the combination and placebo, respectively. In these double-blind controlled clinical trials, adverse reactions occurring in greater than 2% of subjects treated with losartan-hydrochlorothiazide and at a greater rate than placebo were: back pain (2.1% vs 0.6%), dizziness (5.7% vs 2.9%), and upper respiratory infection (6.1% vs 4.6%). The following additional adverse reactions have been reported in clinical trials with losartan potassium and hydrochlorothiazide and/or the individual components: Blood and the lymphatic system disorders: Anemia, aplastic anemia, hemolytic anemia, leukopenia, agranulocytosis.
Metabolism and nutrition disorders: Anorexia, hyperglycemia, hyperuricemia, electrolyte imbalance including hyponatremia and hypokalemia. Psychiatric disorders: Insomnia, restlessness. Nervous system disorders: Dysgeusia, headache, migraine, paraesthesias.
Eye disorders: Xanthopsia, transient blurred vision. Cardiac disorders: Palpitation, tachycardia. Vascular disorders: Dose-related orthostatic effects, necrotizing angiitis (vasculitis, cutaneous vasculitis).
Respiratory, thoracic and mediastinal disorders: Nasal congestion. Gastrointestinal disorders: Dyspepsia, abdominal pain, gastric irritation, cramping, nausea, vomiting, pancreatitis, sialoadenitis. Hepato-biliary disorders: Jaundice (intrahepatic cholestatic jaundice).
Skin and subcutaneous tissue disorders: Rash, pruritus, purpura, toxic epidermal necrolysis, urticaria, photosensitivity, cutaneous lupus erythematosus. Musculoskeletal and connective tissue disorders: Muscle cramps, muscle spasm. Renal and urinary disorders: Glycosuria, renal dysfunction, interstitial nephritis, renal failure.
Reproductive system and breast disorders: Erectile dysfunction/impotence. General disorders and administration site conditions: Chest pain, malaise, weakness. Investigations: Liver function abnormalities.
Cough Persistent dry cough has been associated with ACE-inhibitor use and in practice can be a cause of discontinuation of ACE-inhibitor therapy. Two prospective, parallel-group, double-blind, randomized, controlled trials were conducted to assess the effects of losartan on the incidence of cough in hypertensive patients who had experienced cough while receiving ACE-inhibitor therapy. Patients who had typical ACE-inhibitor cough when challenged with lisinopril, whose cough disappeared on placebo, were randomized to losartan 50 mg, lisinopril 20 mg, or either placebo (one study, n=97) or 25 mg hydrochlorothiazide (n=135).
The double-blind treatment period lasted up to 8 weeks. The incidence of cough is shown in Table 1 below. Table 1: Study 1* HCTZ Losartan Lisinopril Cough 25% 17% 69% Study 2 † Placebo Losartan Lisinopril Cough 35% 29% 62% * Demographics = (89% Caucasian, 64% female) † Demographics = (90% Caucasian, 51% female) These studies demonstrate that the incidence of cough associated with losartan therapy, in a population that al… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Agents increasing serum potassium: Risk of hyperkalemia. (7.1) • Lithium: Risk of lithium toxicity. (7.2) • Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): increased risk of renal impairment and reduced diuretic, natriuretic, and antihypertensive effects.
(7.3) • Dual inhibition of the renin-angiotensin system: increased risk of renal impairment, hypotension, syncope, and hyperkalemia. (7.4) • Antidiabetic drugs: dosage adjustment of antidiabetic may be required. (7.5) • Cholestyramine and colestipol: Reduced absorption of thiazides.
(7.5)
7.1Agents Increasing Serum Potassium Coadministration of losartan with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
7.2Lithium Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of angiotensin II receptor antagonists or thiazide diuretics. Monitor lithium levels in patients receiving losartan potassium and hydrochlorothiazide and lithium.
7.3Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors Losartan Potassium In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists (including losartan) may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving losartan and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including losartan, may be attenuated by NSAIDs, including selective COX-2 inhibitors. Hydrochlorothiazide The administration of a non-steroidal anti-inflammatory agent including a selective COX-2 inhibitor can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics. Therefore, when losartan potassium and hydrochlorothiazide and non-steroidal anti-inflammatory agents including selective COX-2 inhibitors are used concomitantly, observe closely to determine if the desired effect of the diuretic is obtained.
In patients receiving diuretic therapy, coadministration of NSAIDs with angiotensin receptor blockers, including losartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving hydrochlorothiazide, losartan, and NSAID therapy.
7.4Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, syncope, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The Veterans Affairs Nephropathy in Diabetes (VA NEPHRON-D) trial enrolled 1,448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratio, and decreased estimated glomerular filtration rate (GFR 30 to 89.9 mL/min), randomized them to lisinopril or placebo on a background of losartan therapy and followed them for a median of 2.2 years.
Patients receiving the combination of losartan and lisinopril did not obtain any additional benefit compared to monotherapy for the combined endpoint of decline in GFR, end-stage renal disease, or death, but experienced an increased incidence of hyperkalemia and acute kidney injury compared with the monotherapy group. Closely monitor blood pressure, renal function, and electrolytes in patients on losartan potassium and hydrochlorothiazide and other agents that affect the RAS. Do not coadminister aliskiren with losartan potassium and hydrochlorothiazide in patients with diabetes.
Avoid use of aliskiren with losartan potassium and hydrochlorothiazide in patients with renal impairment (GFR <60 mL/min).
7.5The Use of Hydrochlorothiazid… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic Impairment: Losartan potassium and hydrochlorothiazide is not recommended for initial therapy, because the recommended starting dose is not available. (8.7)
8.1Pregnancy Risk Summary Losartan potassium and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue losartan potassium and hydrochlorothiazide as soon as possible (see Clinical Considerations). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Losartan: Use of drugs that act on the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: oligohydramnios, reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue losartan potassium and hydrochlorothiazide, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of gestation.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to losartan potassium and hydrochlorothiazide for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to losartan potassium and hydrochlorothiazide, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide: Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not alter the course of pre-eclampsia, these drugs should not be used to treat hypertension in pregnant women.
The use of hydrochlorothiazide for other indications in pregnancy should be avoided. Data Animal Data There was no evidence of teratogenicity in rats or rabbits treated with a maximum losartan potassium dose of 10 mg/kg/day in combination with 2.5 mg/kg/day of hydrochlorothiazide… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Losartan potassium and hydrochlorothiazide can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue losartan potassium and hydrochlorothiazide as soon as possible (see Clinical Considerations). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Losartan: Use of drugs that act on the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: oligohydramnios, reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue losartan potassium and hydrochlorothiazide, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of gestation.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to losartan potassium and hydrochlorothiazide for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to losartan potassium and hydrochlorothiazide, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide: Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not alter the course of pre-eclampsia, these drugs should not be used to treat hypertension in pregnant women.
The use of hydrochlorothiazide for other indications in pregnancy should be avoided. Data Animal Data There was no evidence of teratogenicity in rats or rabbits treated with a maximum losartan potassium dose of 10 mg/kg/day in combination with 2.5 mg/kg/day of hydrochlorothiazide. At these dosages, respective exposures (AUCs) of losartan, its active metabolite, and hydrochlorothiazide in rabbits were approximately 5, 1.5, and 1 times those achieved in humans with 100 mg… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of losartan potassium and hydrochlorothiazide in pediatric patients have not been established. Neonates with a history of in utero exposure to losartan potassium and hydrochlorothiazide: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as means of reversing hypotension and/or substituting for disordered renal function.
🧓 Geriatric Use ▾
8.5Geriatric Use In a controlled clinical study for the reduction in the combined risk of cardiovascular death, stroke and myocardial infarction in hypertensive patients with left ventricular hypertrophy, 2,857 patients (62%) were 65 years and over, while 808 patients (18%) were 75 years and over. In an effort to control blood pressure in this study, patients were coadministered losartan and hydrochlorothiazide 74% of the total time they were on study drug. No overall differences in effectiveness were observed between these patients and younger patients.
Adverse events were somewhat more frequent in the elderly compared to non-elderly patients for both the losartan-hydrochlorothiazide and the control groups [see Clinical Pharmacology (12.3)] .
🆘 Overdosage ▾
10 OVERDOSAGE Losartan Potassium Significant lethality was observed in mice and rats after oral administration of 1000 mg/kg and 2000 mg/kg, respectively, about 44 and 170 times the maximum recommended human dose on a mg/m 2 basis. Limited data are available in regard to overdosage in humans. The most likely manifestation of overdosage would be hypotension and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation.
If symptomatic hypotension should occur, supportive treatment should be instituted. Neither losartan nor its active metabolite can be removed by hemodialysis. Hydrochlorothiazide The oral LD 50 of hydrochlorothiazide is greater than 10 g/kg in both mice and rats.
The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Losartan Potassium Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)], is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis. Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1,000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor.
The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor. Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic.
Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is unknown.
12.2Pharmacodynamics Losartan Potassium Losartan inhibits the pressor effect of angiotensin II (as well as angiotensin I) infusions. A dose of 100 mg inhibits the pressor effect by about 85% at peak with 25 to 40% inhibition persisting for 24 hours. Removal of the negative feedback of angiotensin II causes a doubling to tripling in plasma renin activity and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Losartan does not affect the response to bradykinin, whereas ACE inhibitors increase the response to bradykinin. Aldosterone plasma concentrations fall following losartan administration. In spite of the effect of losartan on aldosterone secretion, very little effect on serum potassium was observed.
The effect of losartan is substantially present within one week but in some studies the maximal effect occurred in 3 to 6 weeks. In long-term follow-up studies (without placebo control) the effect of losartan appeared to be maintained for up to a year. There is no apparent rebound effect after abrupt withdrawal of losartan.
There was essentially no change in average heart rate in losartan-treated patients in controlled trials. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours, and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics — potentiation of orthostatic hypotension may occur.
Other antihypertensive drugs — additive effect or potentiation. Skeletal muscle relaxants, nondepolarizing (e.g., tubocurarine) — possible increased responsiveness to the muscle relaxant. Corticosteroids, ACTH, or glycyrrhizin (found in liquorice) — intensifie… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Losartan Potassium Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)], is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis. Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1,000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor.
The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor. Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic.
Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Losartan potassium and hydrochlorothiazide tablets, USP are supplied as a film-coated tablet. 50 mg/12.5 mg: yellow color film coated, oval shaped tablets debossed with "I23" on one side and plain on other side. Bottles of 30 NDC 70010-187-03 Bottles of 1000 NDC 70010-187-10 100 mg/12.5 mg: white to off white, film coated, oval shaped tablets debossed with "I24" on one side and plain on other side.
Bottles of 30 NDC 70010-188-03 Bottles of 1000 NDC 70010-188-10 100 mg/25 mg: yellow color film coated, oval shaped tablets debossed with "I27" on one side and plain on other side. Bottles of 30 NDC 70010-189-03 Bottles of 1000 NDC 70010-189-10 Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature]. Keep container tightly closed.
Protect from light.
📋 Description ▾
11 DESCRIPTION Losartan potassium and hydrochlorothiazide tablets USP, 50 mg/12.5 mg, losartan potassium and hydrochlorothiazide tablets USP, 100 mg/12.5 mg and losartan potassium and hydrochlorothiazide tablets USP, 100 mg/25 mg combine an angiotensin II receptor blocker acting on the AT 1 receptor subtype and a diuretic, hydrochlorothiazide. Losartan potassium, USP a non-peptide molecule, is chemically described as 2-butyl-4-chloro-1-[ p- ( o -1 H - tetrazol-5-ylphenyl)benzyl]imidazole-5-methanol monopotassium salt.
Its empirical formula is C 22 H 22 ClKN 6 O, and its structural formula is: Losartan potassium, USP is a white to off-white powder with a molecular weight of 461.00. It is freely soluble in water, sparingly soluble in isopropyl alcohol, and slightly soluble in acetonitrile. Oxidation of the 5-hydroxymethyl group on the imidazole ring results in the active metabolite of losartan.
Hydrochlorothiazide, USP is 6-chloro-3,4-dihydro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide. Its empirical formula is C 7 H 8 ClN 3 O 4 S 2 and its structural formula is: Hydrochlorothiazide, USP is a white, or practically white crystalline powder, practically odorless with a molecular weight of 297.74, which is very slightly soluble in methanol, sparingly soluble in Acetonitrile, soluble in 1% NaOH solution, practically insoluble or insoluble in water, ethanol and buffer solution with pH value range from 4.5 to 8.0.
Losartan potassium and hydrochlorothiazide tablets are available for oral administration in three tablet combinations of losartan and hydrochlorothiazide. Losartan potassium and hydrochlorothiazide tablets USP, 50 mg/12.5 mg contains 50 mg of losartan potassium USP and 12.5 mg of hydrochlorothiazide, USP. Losartan potassium and hydrochlorothiazide tablets USP, 100 mg/12.5 mg contains 100 mg of losartan potassium USP, and 12.5 mg of hydrochlorothiazide USP.
Losartan potassium and hydrochlorothiazide tablets USP, 100 mg/25 mg contains 100 mg of losartan potassium, USP and 25 mg of hydrochlorothiazide USP. Inactive ingredients are hydroxypropyl cellulose, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch, and titanium dioxide. Losartan potassium and hydrochlorothiazide tablets USP, 50 mg/12.5 mg and 100 mg/25 mg also contain iron oxide yellow.
Losartan potassium and hydrochlorothiazide tablets USP, 50 mg/12.5 mg contains 4.24 mg (0.108 mEq) of potassium, losartan potassium and hydrochlorothiazide tablets USP, 100 mg/12.5 mg contains 8.48 mg (0.216 mEq) of potassium, and losartan potassium and hydrochlorothiazide tablets USP, 100 mg/25 mg contains 8.48 mg (0.216 mEq) of potassium. figure-1 figure-2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Pregnancy: Advise female patients of childbearing age about the consequences of exposure to losartan potassium and hydrochlorothiazide during pregnancy. Discuss treatment options with women planning to become pregnant.
Tell patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1)]. Symptomatic Hypotension: Advise patients that lightheadedness can occur, especially during the first days of therapy, and to report this symptom to a healthcare provider. Inform patients that dehydration from inadequate fluid intake, excessive perspiration, vomiting, or diarrhea may lead to an excessive fall in blood pressure.
If syncope occurs, advise patients to contact their healthcare provider [see Warnings and Precautions (5.2)] . Potassium Supplements: Advise patients not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider [see Drug Interactions (7.1)] . Acute Myopia and Secondary Angle-closure Glaucoma: Advise patients to discontinue losartan potassium and hydrochlorothiazide and seek immediate medical attention if they experience symptoms of acute myopia or secondary angle-closure glaucoma [see Warnings and Precautions (5.6)].
Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening. For patent information: https://granulespharma.com/products/losartan-and-hctz-tabs Manufactured by: Granules India Limited Hyderabad-500 084, India MADE IN INDIA Manufactured for: Granules Pharmaceuticals Inc. Chantilly, VA 20151 Rev.
07/2025
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Losartan Potassium Absorption : Following oral administration, losartan is well absorbed and undergoes substantial first-pass metabolism. The systemic bioavailability of losartan is approximately 33%. Mean peak concentrations of losartan and its active metabolite are reached in 1 hour and in 3 to 4 hours, respectively.
While maximum plasma concentrations of losartan and its active metabolite are approximately equal, the AUC (area under the curve) of the metabolite is about 4 times as great as that of losartan. A meal slows absorption of losartan and decreases its C max but has only minor effects on losartan AUC or on the AUC of the metabolite (~10% decrease). The pharmacokinetics of losartan and its active metabolite are linear with oral losartan doses up to 200 mg and do not change over time.
Distribution: The volume of distribution of losartan and the active metabolite is about 34 liters and 12 liters, respectively. Both losartan and its active metabolite are highly bound to plasma proteins, primarily albumin, with plasma free fractions of 1.3% and 0.2%, respectively. Plasma protein binding is constant over the concentration range achieved with recommended doses.
Studies in rats indicate that losartan crosses the blood-brain barrier poorly, if at all. Metabolism: Losartan is an orally active agent that undergoes substantial first-pass metabolism by cytochrome P450 enzymes. It is converted, in part, to an active carboxylic acid metabolite that is responsible for most of the angiotensin II receptor antagonism that follows losartan treatment.
About 14% of an orally-administered dose of losartan is converted to the active metabolite. In addition to the active carboxylic acid metabolite, several inactive metabolites are formed. In vitro studies indicate that cytochrome P450 2C9 and 3A4 are involved in the biotransformation of losartan to its metabolites.
Elimination: Total plasma clearance of losartan and the active metabolite is about 600 mL/min and 50 mL/min, respectively, with renal clearance of about 75 mL/min and 25 mL/min, respectively. The terminal half-life of losartan is about 2 hours and of the metabolite is about 6 to 9 hours. After single doses of losartan administered orally, about 4% of the dose is excreted unchanged in the urine and about 6% is excreted in urine as active metabolite.
Biliary excretion contributes to the elimination of losartan and its metabolites. Following oral 14 C-labeled losartan, about 35% of radioactivity is recovered in the urine and about 60% in the feces. Following an intravenous dose of 14 C-labeled losartan, about 45% of radioactivity is recovered in the urine and 50% in the feces.
Neither losartan nor its metabolite accumulate in plasma upon repeated once-daily dosing. Hydrochlorothiazide Hydrochlorothiazide is not metabolized but is eliminated rapidly by the kidney. When plasma levels have been followed for at least 24 hours, the plasma half-life has been observed to vary between 5.6 and 14.8 hours.
At least 61 percent of the oral dose is eliminated unchanged within 24 hours. Hydrochlorothiazide crosses the placental but not the blood-brain barrier and is excreted in breast milk. Specific Populations Geriatric and Gender Losartan pharmacokinetics have been investigated in the elderly (65 to 75 years) and in both genders.
Plasma concentrations of losartan and its active metabolite are similar in elderly and young hypertensives. Plasma concentrations of losartan were about twice as high in female hypertensives as male hypertensives, but concentrations of the active metabolite were similar in males and females. Race Pharmacokinetic differences due to race have not been studied [see also Use in Specific Populations (8.6)].
Hepatic Insufficiency Following oral administration in patients with mild to moderate alcoholic cirrhosis of the liver, plasma concentrations of losartan and its active metabolite were, respectively, 5 times and about 1.7 times those in young male v… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Losartan Potassium Losartan inhibits the pressor effect of angiotensin II (as well as angiotensin I) infusions. A dose of 100 mg inhibits the pressor effect by about 85% at peak with 25 to 40% inhibition persisting for 24 hours. Removal of the negative feedback of angiotensin II causes a doubling to tripling in plasma renin activity and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Losartan does not affect the response to bradykinin, whereas ACE inhibitors increase the response to bradykinin. Aldosterone plasma concentrations fall following losartan administration. In spite of the effect of losartan on aldosterone secretion, very little effect on serum potassium was observed.
The effect of losartan is substantially present within one week but in some studies the maximal effect occurred in 3 to 6 weeks. In long-term follow-up studies (without placebo control) the effect of losartan appeared to be maintained for up to a year. There is no apparent rebound effect after abrupt withdrawal of losartan.
There was essentially no change in average heart rate in losartan-treated patients in controlled trials. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours, and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics — potentiation of orthostatic hypotension may occur.
Other antihypertensive drugs — additive effect or potentiation. Skeletal muscle relaxants, nondepolarizing (e.g., tubocurarine) — possible increased responsiveness to the muscle relaxant. Corticosteroids, ACTH, or glycyrrhizin (found in liquorice) — intensified electrolyte depletion, particularly hypokalemia.
Pressor amines (e.g., norepinephrine) — possible decreased response to pressor amines but not sufficient to preclude their use.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Losartan Monotherapy Reduction in the Risk of Stroke: The LIFE study was a multinational, double-blind study comparing losartan and atenolol in 9,193 hypertensive patients with ECG-documented left ventricular hypertrophy. Patients with myocardial infarction or stroke within six months prior to randomization were excluded. Patients were randomized to receive once daily losartan 50 mg or atenolol 50 mg.
If goal blood pressure (<140/90 mmHg) was not reached, hydrochlorothiazide (12.5 mg) was added first and, if needed, the dose of losartan or atenolol was then increased to 100 mg once daily. If necessary, other antihypertensive treatments (e.g., increase in dose of hydrochlorothiazide therapy to 25 mg or addition of other diuretic therapy, calcium channel blockers, alpha-blockers, or centrally acting agents, but not ACE inhibitors, angiotensin II antagonists, or beta-blockers) were added to the treatment regimen to reach the goal blood pressure.
In efforts to control blood pressure, the patients in both arms of the LIFE study were coadministered hydrochlorothiazide the majority of time they were on study drug (73.9% and 72.4% of days in the losartan and atenolol arms, respectively). Of the randomized patients, 4,963 (54%) were female and 533 (6%) were Black. The mean age was 67 with 5,704 (62%) age ≥65.
At baseline, 1,195 (13%) had diabetes, 1,326 (14%) had isolated systolic hypertension, 1,469 (16%) had coronary heart disease, and 728 (8%) had cerebrovascular disease. Baseline mean blood pressure was 174/98 mmHg in both treatment groups. The mean length of follow-up was 4.8 years.
At the end of study or at the last visit before a primary endpoint, 77% of the group treated with losartan and 73% of the group treated with atenolol were still taking study medication. Of the patients still taking study medication, the mean doses of losartan and atenolol were both about 80 mg/day, and 15% were taking atenolol or losartan as monotherapy, while 77% were also receiving hydrochlorothiazide (at a mean dose of 20 mg/day in each group). Blood pressure reduction measured at trough was similar for both treatment groups but blood pressure was not measured at any other time of the day.
At the end of study or at the last visit before a primary endpoint, the mean blood pressures were 144.1/81.3 mmHg for the group treated with losartan and 145.4/80.9 mmHg for the group treated with atenolol [the difference in SBP of 1.3 mmHg was significant (p<0.001), while the difference of 0.4 mmHg in DBP was not significant (p=0.098)]. The primary endpoint was the first occurrence of cardiovascular death, nonfatal stroke, or nonfatal myocardial infarction. Patients with nonfatal events remained in the trial, so that there was also an examination of the first event of each type even if it was not the first event (e.g., a stroke following an initial myocardial infarction would be counted in the analysis of stroke).
Treatment with losartan resulted in a 13% reduction (p=0.021) in risk of the primary endpoint compared to the atenolol group; this difference was primarily the result of an effect on fatal and nonfatal stroke. Treatment with losartan reduced the risk of stroke by 25% relative to atenolol (p=0.001).
14.2Losartan Potassium-Hydrochlorothiazide The 3 controlled studies of losartan and hydrochlorothiazide included over 1,300 patients assessing the antihypertensive efficacy of various doses of losartan (25, 50 and 100 mg) and concomitant hydrochlorothiazide (6.25, 12.5 and 25 mg). A factorial study compared the combination of losartan/hydrochlorothiazide 50/12.5 mg with its components and placebo. The combination of losartan/hydrochlorothiazide 50/12.5 mg resulted in an approximately additive placebo-adjusted systolic/diastolic response (15.5/9 mmHg for the combination compared to 8.5/5 mmHg for losartan alone and 7/3 mmHg for hydrochlorothiazide alone).
Another study investigated the dose-response relationship of various doses of hy… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Losartan Potassium-Hydrochlorothiazide No carcinogenicity studies have been conducted with the losartan potassium-hydrochlorothiazide combination. Losartan potassium-hydrochlorothiazide when tested at a weight ratio of 4:1, was negative in the Ames microbial mutagenesis assay and the V-79 Chinese hamster lung cell mutagenesis assay. In addition, there was no evidence of direct genotoxicity in the in vitro alkaline elution assay in rat hepatocytes and in vitro chromosomal aberration assay in Chinese hamster ovary cells at noncytotoxic concentrations.
Losartan potassium, coadministered with hydrochlorothiazide, had no effect on the fertility or mating behavior of male rats at dosages up to 135 mg/kg/day of losartan and 33.75 mg/kg/day of hydrochlorothiazide. These dosages have been shown to provide respective systemic exposures (AUCs) for losartan, its active metabolite and hydrochlorothiazide that are approximately 60, 60 and 30 times greater than those achieved in humans with 100 mg of losartan potassium in combination with 25 mg of hydrochlorothiazide. In female rats, however, the coadministration of doses as low as 10 mg/kg/day of losartan and 2.5 mg/kg/day of hydrochlorothiazide was associated with slight but statistically significant decreases in fecundity and fertility indices.
AUC values for losartan, its active metabolite and hydrochlorothiazide, extrapolated from data obtained with losartan administered to rats at a dose of 50 mg/kg/day in combination with 12.5 mg/kg/day of hydrochlorothiazide, were approximately 6, 2, and 2 times greater than those achieved in humans with 100 mg of losartan in combination with 25 mg of hydrochlorothiazide. Losartan Potassium Losartan potassium was not carcinogenic when administered at maximally tolerated dosages to rats and mice for 105 and 92 weeks, respectively.
Female rats given the highest dose (270 mg/kg/day) had a slightly higher incidence of pancreatic acinar adenoma. The maximally tolerated dosages (270 mg/kg/day in rats, 200 mg/kg/day in mice) provided systemic exposures for losartan and its pharmacologically active metabolite that were approximately 160 and 90 times (rats) and 30 and 15 times (mice) the exposure of a 50 kg human given 100 mg per day. Losartan potassium was negative in the microbial mutagenesis and V-79 mammalian cell mutagenesis assays and in the in vitro alkaline elution and in vitro and in vivo chromosomal aberration assays.
In addition, the active metabolite showed no evidence of genotoxicity in the microbial mutagenesis, in vitro alkaline elution, and in vitro chromosomal aberration assays. Fertility and reproductive performance were not affected in studies with male rats given oral doses of losartan potassium up to approximately 150 mg/kg/day. The administration of toxic dosage levels in females (300/200 mg/kg/day) was associated with a significant (p<0.05) decrease in the number of corpora lutea/female, implants/female, and live fetuses/female at C-section.
At 100 mg/kg/day only a decrease in the number of corpora lutea/female was observed. The relationship of these findings to drug- treatment is uncertain since there was no effect at these dosage levels on implants/pregnant female, percent post-implantation loss, or live animals/litter at parturition. In nonpregnant rats dosed at 135 mg/kg/day for 7 days, systemic exposure (AUCs) for losartan and its active metabolite were approximately 66 and 26 times the exposure achieved in man at the maximum recommended human daily dosage (100 mg).
Hydrochlorothiazide Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day). The NTP, however, found equivocal evidence for… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Losartan Potassium-Hydrochlorothiazide No carcinogenicity studies have been conducted with the losartan potassium-hydrochlorothiazide combination. Losartan potassium-hydrochlorothiazide when tested at a weight ratio of 4:1, was negative in the Ames microbial mutagenesis assay and the V-79 Chinese hamster lung cell mutagenesis assay. In addition, there was no evidence of direct genotoxicity in the in vitro alkaline elution assay in rat hepatocytes and in vitro chromosomal aberration assay in Chinese hamster ovary cells at noncytotoxic concentrations.
Losartan potassium, coadministered with hydrochlorothiazide, had no effect on the fertility or mating behavior of male rats at dosages up to 135 mg/kg/day of losartan and 33.75 mg/kg/day of hydrochlorothiazide. These dosages have been shown to provide respective systemic exposures (AUCs) for losartan, its active metabolite and hydrochlorothiazide that are approximately 60, 60 and 30 times greater than those achieved in humans with 100 mg of losartan potassium in combination with 25 mg of hydrochlorothiazide. In female rats, however, the coadministration of doses as low as 10 mg/kg/day of losartan and 2.5 mg/kg/day of hydrochlorothiazide was associated with slight but statistically significant decreases in fecundity and fertility indices.
AUC values for losartan, its active metabolite and hydrochlorothiazide, extrapolated from data obtained with losartan administered to rats at a dose of 50 mg/kg/day in combination with 12.5 mg/kg/day of hydrochlorothiazide, were approximately 6, 2, and 2 times greater than those achieved in humans with 100 mg of losartan in combination with 25 mg of hydrochlorothiazide. Losartan Potassium Losartan potassium was not carcinogenic when administered at maximally tolerated dosages to rats and mice for 105 and 92 weeks, respectively.
Female rats given the highest dose (270 mg/kg/day) had a slightly higher incidence of pancreatic acinar adenoma. The maximally tolerated dosages (270 mg/kg/day in rats, 200 mg/kg/day in mice) provided systemic exposures for losartan and its pharmacologically active metabolite that were approximately 160 and 90 times (rats) and 30 and 15 times (mice) the exposure of a 50 kg human given 100 mg per day. Losartan potassium was negative in the microbial mutagenesis and V-79 mammalian cell mutagenesis assays and in the in vitro alkaline elution and in vitro and in vivo chromosomal aberration assays.
In addition, the active metabolite showed no evidence of genotoxicity in the microbial mutagenesis, in vitro alkaline elution, and in vitro chromosomal aberration assays. Fertility and reproductive performance were not affected in studies with male rats given oral doses of losartan potassium up to approximately 150 mg/kg/day. The administration of toxic dosage levels in females (300/200 mg/kg/day) was associated with a significant (p<0.05) decrease in the number of corpora lutea/female, implants/female, and live fetuses/female at C-section.
At 100 mg/kg/day only a decrease in the number of corpora lutea/female was observed. The relationship of these findings to drug- treatment is uncertain since there was no effect at these dosage levels on implants/pregnant female, percent post-implantation loss, or live animals/litter at parturition. In nonpregnant rats dosed at 135 mg/kg/day for 7 days, systemic exposure (AUCs) for losartan and its active metabolite were approximately 66 and 26 times the exposure achieved in man at the maximum recommended human daily dosage (100 mg).
Hydrochlorothiazide Two-year feeding studies in mice and rats conducted under the auspices of the National Toxicology Program (NTP) uncovered no evidence of a carcinogenic potential of hydrochlorothiazide in female mice (at doses of up to approximately 600 mg/kg/day) or in male and female rats (at doses of up to approximately 100 mg/kg/day). The NTP, however, found equivocal evidence for hepatocarcinogenicity in… [Excerpted — this section continues on DailyMed.]
📄 Patient Package Insert ▾
Patient Information Patient Information Losartan potassium and hydrochlorothiazide tablets, USP 50 mg/12.5 mg, 100 mg/12.5 mg and 100 mg/25 mg (loe sar' tan poe tas' ee um and hye'' droe klor'' oh thye' a zide) Rx only Read the Patient Information that comes with losartan potassium and hydrochlorothiazide tablets before you start taking it and each time you get a refill. There may be new information. This leaflet does not take the place of talking with your doctor about your condition and treatment.
What is the most important information I should know about losartan potassium and hydrochlorothiazide tablets? Losartan potassium and hydrochlorothiazide tablets can cause harm or death to an unborn baby. Talk to your doctor about other ways to lower your blood pressure if you plan to become pregnant.
If you get pregnant while taking losartan potassium and hydrochlorothiazide tablets tell your doctor right away. What are losartan potassium and hydrochlorothiazide tablets? Losartan potassium and hydrochlorothiazide tablet contains 2 prescription medicines, an angiotensin receptor blocker (ARB) and a diuretic (water pill).
It is used to: lower high blood pressure (hypertension). Losartan potassium and hydrochlorothiazide tablets are not usually the first medicine used to treat high blood pressure. lower the chance of stroke in patients with high blood pressure and a heart problem called left ventricular hypertrophy (LVH). Losartan potassium and hydrochlorothiazide tablets may not help Black patients with this problem.
Losartan potassium and hydrochlorothiazide tablets have not been studied in children less than 18 years old. High Blood Pressure (hypertension). Blood pressure is the force in your blood vessels when your heart beats and when your heart rests.
You have high blood pressure when the force is too much. The losartan ingredient in losartan potassium and hydrochlorothiazide tablets can help your blood vessels relax so your blood pressure is lower. The hydrochlorothiazide ingredient in losartan potassium and hydrochlorothiazide tablets works by making your kidneys pass more water and salt.
Left Ventricular Hypertrophy (LVH) is an enlargement of the walls of the left chamber of the heart (the heart’s main pumping chamber). LVH can happen from several things. High blood pressure is the most common cause of LVH.
Who should not take losartan potassium and hydrochlorothiazide tablets? Do not take losartan potassium and hydrochlorothiazide tablets if you: are allergic to any ingredients in losartan potassium and hydrochlorothiazide tablets. See a complete list of ingredients in losartan potassium and hydrochlorothiazide tablets at the end of this leaflet. are not passing urine. have diabetes and are taking a medicine called aliskiren to reduce blood pressure.
What should I tell my doctor before taking losartan potassium and hydrochlorothiazide tablets? Tell your doctor about all your medical conditions including if you: are pregnant or planning to become pregnant. See "What is the most important information I should know about losartan potassium and hydrochlorothiazide tablets?" are breastfeeding or plan to breastfeed.
Losartan potassium and hydrochlorothiazide can pass into your milk and may harm your baby. You and your doctor should decide if you will take losartan potassium and hydrochlorothiazide tablets or breastfeed. You should not do both. have been vomiting (throwing up), having diarrhea, sweating a lot, or not drinking enough fluids.
These could cause you to have low blood pressure. have liver problems have kidney problems have systemic lupus erythematosus (Lupus; SLE) have diabetes have gout have any allergies have had skin cancer or if you develop a new skin lesion during the treatment. Treatment with hydrochlorothiazide may increase the risk of some types of skin cancer (non-melanoma skin cancer). Discuss with your doctor how to protect your skin from sun exposure and how often you should undergo skin cancer screening.
T… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL losahctz-50mg-30s losahctz-100mg-30s losahctz-25mg-30s
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |