
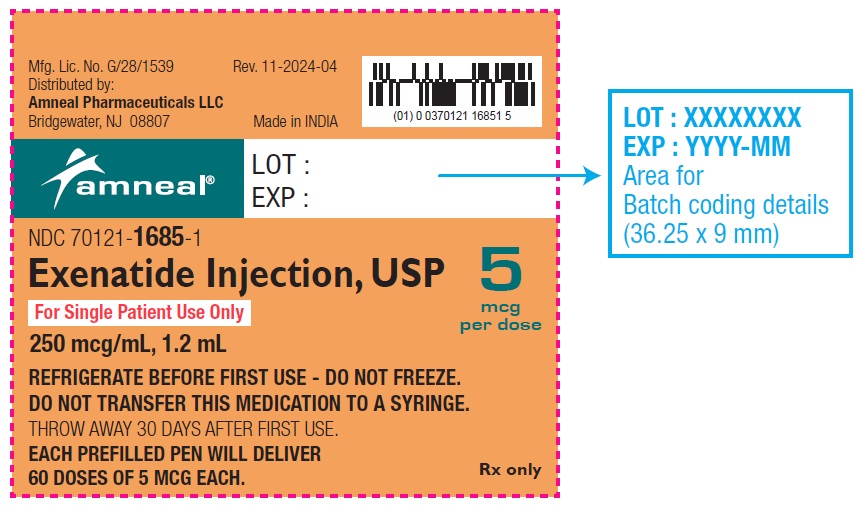
Exenatide 250 ug/mL Injection, 1 cartridge — NDC 70121-1685-1 (Billing 70121-1685-01)
This is a package of 1 cartridge of Exenatide 250 ug/mL Injection from Amneal Pharmaceuticals LLC, marketed since Nov 2024 and currently FDA-listed, this package's marketing is listed to end Jun 2027. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 70121-1685-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70121 labeler · 1685 product · 1 package
- Package marketed since
- Nov 22, 2024
- Package marketing ended
- Jun 30, 2027
- Sample package
- No — commercial package
- Barcode (UPC-A, from the NDC)
- 3 7012116851 5
- Medicaid fills, this package
- 346 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059072
- GCN: 24613
- HICL (First Databank): 032893
- AHFS class code: 68:20.06.00
- RxCUI (RxNorm): 847910
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the GLP-1 Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It helps improve blood sugar control in adults with type 2 diabetes, along with diet and exercise. It mimics a gut hormone that helps your body release insulin when your blood suga...
- With Byetta, inject it under the skin within 60 minutes before your morning and evening meals. Never inject it after a meal. If you miss a dose, just take your next scheduled one.
- Nausea is the most common side effect, but it usually gets better with time. Vomiting and diarrhea can happen too. If they are severe or persistent, call your doctor because dehydr...
- Get help for severe, lasting stomach pain (sometimes going to your back), swelling of the face or throat, trouble breathing, or unusual bleeding. Stop the medicine if you have thes...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Exenatide — tap one for details:
Exenatide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $615.81 | $615.81 / 1 cartridge |
| Medicare drug plans payPart D · Q2 2026 | $451.64 | $451.64 / 1 cartridge |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70121-1685-01 You're viewing this Main listing | 1 CARTRIDGE in 1 CARTON / 1.2 mL in 1 CARTRIDGE | 2024-11-22 | Jun 30, 2027 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Exenatide 250 ug/mL 70121-1686-01 | Amneal | 1 cartridge | $300.168 | — | Availability likely | — |
| Byetta 250 ug/mL 00310-6524-01 | AstraZeneca | 1 cartridge | $340.101 | — | FDA listed | — |
| Byetta 250 ug/mL 00310-6512-01 | AstraZeneca | 1 cartridge | $681.263 | — | FDA listed | — |
| Exenatide 250 ug/mLthis 70121-1685-01 | Amneal | 1 cartridge | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Exenatide Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Q40Q9N063P
Acetic acid is a weak organic acid commonly used in medicines as a buffer and pH adjuster. It helps maintain the proper acidity level to ensure the drug remains stable and effective in its formulation.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
2.2 mg / 1 mL
UNII GGO4Y809LO
Metacresol is a preservative derived from coal tar or petroleum. It prevents bacterial and fungal growth in liquid medicines, helping keep the product safe and stable during storage.
-
UNII 4550K0SC9B
Sodium acetate is a salt derived from acetic acid. It acts as a buffer to help maintain the medicine's pH stability and may serve as a preservative or solubilizer in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Amneal Pharmaceuticals LLC labeler code 70121
- Triamcinolone Acetonide 400 mg/10mL Injection, Suspension NDC 70121-1655-1
- Triamcinolone Acetonide 40 mg/mL Injection, Suspension NDC 70121-1657-1
- Arsenic Trioxide 2 mg/mL Injection, Solution NDC 70121-1658-1
- epinephrine 1 mg/mL Injection NDC 70121-1660-2
- carboprost tromethamine 250 ug/mL Injection, Solution NDC 70121-1680-1
- phytonadione 1 mg/.5mL Injection, Emulsion NDC 70121-1682-7
- Exenatide 250 ug/mL Injection NDC 70121-1686-1
- Tepadina thiotepa 400 mg Injection, Powder, Lyophilized, For Solution NDC 70121-1687-1
- plerixafor 24 mg/1.2mL Injection, Solution NDC 70121-1694-2
- glycopyrrolate .2 mg/mL Injection, Solution NDC 70121-1698-2
- glycopyrrolate .2 mg/mL Injection, Solution NDC 70121-1699-2
- atropine sulfate .1 mg/mL Injection, Solution NDC 70121-1705-7
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Exenatide injection is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. Exenatide injection is a glucagon-like peptide-1 (GLP-1) receptor agonist indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. ( 1 , 14 ) Limitations of Use Co-administration with other exenatide-containing products is not recommended.
( 1 ) Limitations of Use Exenatide injection contains exenatide. Co-administration with other exenatide-containing products is not recommended.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Inject subcutaneously within 60 minutes prior to morning and evening meals (or before the two main meals of the day, approximately 6 hours or more apart). ( 2.1 ) Initiate at 5 mcg per dose twice daily; increase to 10 mcg twice daily after 1 month based on clinical response. ( 2.1 )
2.1Recommended Dosing Initiate exenatide injection at 5 mcg administered subcutaneously twice daily at any time within the 60-minute period before the morning and evening meals (or before the two main meals of the day, approximately 6 hours or more apart). Do not administer after a meal. Based on clinical response, the dose of exenatide injection can be increased to 10 mcg twice daily which is recommended after 1 month of therapy, in order to reduce the risk of gastrointestinal adverse reactions [see Warnings and Precautions (5.5) and Adverse Reactions (6.1) ] .
Administer as a subcutaneous injection in the thigh, abdomen, or upper arm. Rotate injections sites with each dose. Do not use the same site for each injection.
Inspect visually for particulate matter and discoloration. Only use exenatide injection if the solution appears clear, colorless and contains no particles. When using exenatide injection with insulin, administer as separate injections and never mix.
It is acceptable to inject exenatide injection and insulin in the same body region, but the injections should not be adjacent to each other. If a dose is missed, resume the treatment regimen as prescribed with the next scheduled dose.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Exenatide Injection, USP is a clear, colorless sterile solution for subcutaneous injection containing 250 mcg/mL exenatide, USP supplied as follows: 5 mcg per dose in a single-patient-use prefilled pen containing 300 mcg/1.2 mL (250mcg/mL), 60 doses. 10 mcg per dose in a single-patient-use prefilled pen containing 600 mcg/2.4 mL (250mcg/mL), 60 doses. Exenatide injection is supplied as: 5 mcg per dose, in a single-patient-use prefilled pen containing 300 mcg/1.2 mL (250 mcg/mL), 60 doses.
10 mcg per dose, in a single-patient-use prefilled pen containing 600 mcg/2.4 mL (250 mcg/mL), 60 doses.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Exenatide injection is contraindicated in patients with: A prior severe hypersensitivity reaction to exenatide or to any of the excipients in exenatide injection. Serious hypersensitivity reactions including anaphylaxis and angioedema have been reported with exenatide injection [see Warnings and Precautions (5.7) ] . A history of drug-induced immune-mediated thrombocytopenia from exenatide products.
Serious bleeding, which may be fatal, from drug-induced immune-mediated thrombocytopenia has been reported with exenatide use [see Warnings and Precautions (5.8) ]. History of severe hypersensitivity to exenatide or any of the excipients in exenatide injection. ( 4 ) History of drug-induced immune-mediated thrombocytopenia from exenatide products.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute Pancreatitis : Has been observed in patients treated with GLP-1 receptor agonists, including exenatide. Discontinue if pancreatitis is suspected. ( 5.1 ) Never share an exenatide injection pen between patients, even if the needle is changed.
( 5.2 ) Hypoglycemia with Concomitant Use of Insulin Secretagogues or Insulin : Patients taking an insulin secretagogue or insulin may have an increased risk of hypoglycemia, including severe hypoglycemia. Reduction in the dose of insulin secretagogues or insulin may be necessary. ( 5.3 ) Acute Kidney Injury Due to Volume Depletion : Monitor renal function in patients reporting adverse reactions that could lead to volume depletion.
( 5.4 ) Severe Gastrointestinal Adverse Reactions : Use has been associated with gastrointestinal adverse reactions, sometimes severe. Exenatide is not recommended in patients with severe gastroparesis. ( 5.5 ) Immunogenicity : Patients may develop antibodies to exenatide.
If there is worsening glycemic control or failure to achieve target glycemic control, consider alternative antidiabetic therapy. ( 5.6 ) Hypersensitivity : Serious hypersensitivity reactions (e.g., anaphylaxis and angioedema) have been reported. Discontinue exenatide and promptly seek medical advice.
( 5.7 ) Drug-induced Immune-mediated Thrombocytopenia : Serious bleeding which may be fatal has been reported. Discontinue exenatide promptly and avoid re-exposure to exenatide. ( 5.8 ) Acute Gallbladder Disease: If cholelithiasis or cholecystitis are suspected, gallbladder studies are indicated.
( 5.9 ) Pulmonary Aspiration During General Anesthesia or Deep Sedation: Has been reported in patients receiving GLP-1 receptor agonists undergoing elective surgeries or procedures. Instruct patients to inform healthcare providers of any planned surgeries or procedures. ( 5.10 )
5.1Acute Pancreatitis Acute pancreatitis, including fatal and non-fatal hemorrhagic or necrotizing pancreatitis, has been observed in patients treated with glucagon-like peptide-1 (GLP-1) receptor agonists, including exenatide [see Adverse Reactions (6.2) ]. After initiation of exenatide, observe patients carefully for signs and symptoms of acute pancreatitis which may include persistent or severe abdominal pain (sometimes radiating to the back) and which may or may not be accompanied by nausea or vomiting. If pancreatitis is suspected, discontinue exenatide and initiate appropriate management.
5.2Never Share an Exenatide Injection Pen Between Patients Exenatide injection pens must never be shared between patients, even if the needle is changed. Pen-sharing poses a risk for transmission of blood-borne pathogens.
5.3Hypoglycemia with Concomitant Use of Insulin Secretagogues or Insulin Patients receiving exenatide in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin may have an increased risk of hypoglycemia including severe hypoglycemia [see Adverse Reactions (6) and Drug Interactions (7) ] . The risk of hypoglycemia may be lowered by a reduction in the dose of sulfonylurea (or other concomitantly administered insulin secretagogue) or insulin. Inform patients using these concomitant medications of the risk of hypoglycemia and educate them on the signs and symptoms of hypoglycemia.
5.4Acute Kidney Injury Due to Volume Depletion There have been post-marketing reports of acute kidney injury, in some cases requiring hemodialysis, in patients treated with GLP-1 receptor agonists, exenatide [see Adverse Reactions (6.2) ]. The majority of the reported events occurred in patients who experienced gastrointestinal reactions leading to dehydration such as nausea, vomiting, or diarrhea [see Adverse Reactions (6) ]. Monitor renal function in patients reporting adverse reactions to exenatide that could lead to volume depletion, especially during dosage initiation and escalation of exenatide.
Exenatide is not recommended in patients with severe renal impairment (creatinine clearance <30… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below or elsewhere in the prescribing information: Acute Pancreatitis [see Warnings and Precautions (5.1) ] Never Share an Exenatide Pen Between Patients [see Warnings and Precautions (5.2) ] Hypoglycemia with Concomitant Use of Insulin Secretagogues or Insulin [see Warnings and Precautions (5.3) ] Acute Kidney Injury Due to Volume Depletion [see Warnings and Precautions (5.4) ] Severe Gastrointestinal Adverse Reactions [see Warnings and Precautions (5.5) ] Immunogenicity [see Warnings and Precautions (5.6) ] Hypersensitivity [see Warnings and Precautions (5.7) ] Drug-Induced Thrombocytopenia [see Warnings and Precautions (5.8) ] Acute Gallbladder Disease [see Warnings and Precautions (5.9) ] Pulmonary Aspiration During General Anesthesia or Deep Sedation [see Warnings and Precautions (5.10) ] Most common (≥ 5%) and occurring more frequently than placebo in clinical trials: nausea, hypoglycemia, vomiting, diarrhea, feeling jittery, dizziness, headache, dyspepsia, constipation, asthenia.
Nausea usually decreases over time. ( 5.3 , 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals LLC at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Hypoglycemia Table 1 summarizes the incidence and rate of hypoglycemia with exenatide in six placebo-controlled clinical trials. Table 1: Incidence (%) and Rate of Hypoglycemia when Exenatide was used as Monotherapy or with Concomitant Antidiabetic Therapy in Six Placebo-Controlled Clinical Trials * Placebo BID Exenatide 5 mcg BID Exenatide 10 mcg BID Monotherapy (24 Weeks) N 77 77 78 % Overall 1.3% 5.2% 3.8% Rate (episodes/patient-year) 0.03 0.21 0.52 % Severe 0.0% 0.0% 0.0% With Metformin (30 Weeks) N 113 110 113 % Overall 5.3% 4.5% 5.3% Rate (episodes/patient-year) 0.12 0.13 0.12 % Severe 0.0% 0.0% 0.0% With a Sulfonylurea (30 Weeks) N 123 125 129 % Overall 3.3% 14.4% 35.7% Rate (episodes/patient-year) 0.07 0.64 1.61 % Severe 0.0% 0.0% 0.0% With Metformin and a Sulfonylurea (30 Weeks) N 247 245 241 % Overall 12.6% 19.2% 27.8% Rate (episodes/patient-year) 0.58 0.78 1.71 % Severe 0.0% 0.4% 0.0% With a Thiazolidinedione (16 Weeks) N 112 not evaluated 121 % Overall 7.1% not evaluated 10.7% Rate (episodes/patient-years) 0.56 not evaluated 0.98 % Severe 0.0% not evaluated 0.0% With Insulin Glargine with or without Metformin and/or Thiazolidinedione (30 Weeks) † N 122 not evaluated 137 % Overall 29.5% not evaluated 24.8% Rate (episodes/patient-years) 1.58 not evaluated 1.61 % Severe 0.8% not evaluated 0.0% * A hypoglycemic episode was recorded if a patient reported symptoms of hypoglycemia with or without a blood glucose value consistent with hypoglycemia.
Severe hypoglycemia was defined as an event with symptoms consistent with hypoglycemia requiring the assistance of another person and associated with either a documented blood glucose value < 54 mg/dL or prompt recovery after treatment for hypoglycemia. † When exenatide was initiated in combination with insulin glargine, the dose of insulin glargine was decreased by 20% in patients with an HbA 1c ≤ 8.0% to minimize the risk of hypoglycemia. See Table 10 for insulin dose titration algorithm. N = number of Intent-to-Treat subjects in each treatment group.
Immunogenicity Antibodies were assessed in 90% of subjects in the 30-week, 24-week, and 16-week studies of exenatide. In the 30-week controlled trials of exenatide add-on to metformin and/or sulfonylurea, antibodies were assessed at 2- to 6-week intervals. The mean antibody titer peaked at Week 6 and was reduced by 55% by Week 30.
Three hundred and sixty patients (38%) had low titer antibodies (< 625… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 6: Clinically Relevant Interactions with Exenatide Concomitant Use of Insulin Secretagogues or Insulin Clinical Impact Exenatide promotes insulin release from pancreatic beta-cells in the presence of elevated glucose concentrations. The risk of hypoglycemia is increased when exenatide is used in combination with insulin secretagogues (e.g., sulfonylureas) or insulin [see Warnings and Precautions (5.3) and Adverse Reactions (6) ] . Intervention When initiating exenatide, consider reducing the dose of concomitantly administered insulin secretagogue or insulin to reduce the risk of hypoglycemia.
Warfarin Clinical Impact In a drug interaction study, exenatide did not have a significant effect on INR [see Clinical Pharmacology (12.3) ] . There have been post-marketing reports for exenatide of increased INR with concomitant use of warfarin, sometimes associated with bleeding [see Adverse Reactions (6.2) ] . Intervention In patients taking warfarin, the prothrombin time should be monitored more frequently after initiation or alteration of exenatide therapy.
Once a stable prothrombin time has been documented, the prothrombin time can be monitored at the intervals recommended for patients taking warfarin. Orally Administered Drugs (e.g., acetaminophen) Clinical Impact Exenatide slows gastric emptying. Therefore, exenatide has the potential to reduce the rate of absorption of orally administered drugs [see Clinical Pharmacology (12.3) ].
Intervention Use caution when administering oral medications with exenatide where a slower rate of oral absorption may be clinically meaningful. For oral medications that are dependent on threshold concentrations for efficacy, such as contraceptives and antibiotics, patients should be advised to take those drugs at least 1 hour before exenatide injection. If such drugs are to be administered with food, patients should be advised to take them with a meal or snack when exenatide is not administered [see Clinical Pharmacology (12.3) ] .
May impact absorption of orally administered medications. ( 7 ) Warfarin: Post-marketing reports of increased INR sometimes associated with bleeding. Monitor INR frequently until stable upon initiation or alteration of exenatide therapy.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Use during pregnancy only if the potential benefit justifies the risk to the fetus. ( 8.1 )
8.1Pregnancy Risk Summary Limited data with exenatide in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations) . Based on animal reproduction studies, there may be risks to the fetus from exposure to exenatide during pregnancy.
Exenatide should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Animal reproduction studies identified increased adverse fetal and neonatal outcomes from exposure to exenatide during pregnancy and lactation in association with maternal effects. In mice, exenatide administered during gestation and lactation caused increased neonatal deaths at systemic exposure 3-times the human exposure resulting from the maximum recommended human dose (MRHD) of 20 mcg/day for exenatide (see Data) .
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with an HbA 1c > 7 and has been reported to be as high as 20% to 25% in women with HbA 1c > 10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryofetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data In studies evaluating reproduction and development in pregnant mice and rabbits, maternal animals were administered exenatide, the active ingredient in exenatide injection, by subcutaneous injection twice a day.
In pregnant mice given 6, 68, 460, or 760 mcg/kg/day exenatide during fetal organogenesis, skeletal variations associated with slowed fetal growth, including changes in number of rib pairs or vertebral ossifications sites, and wavy ribs were observed at 760 mcg/kg/day, a dose that produced maternal toxicity and yielded systemic exposure 390-times the human exposure resulting from the MRHD of exenatide based on AUC comparison. In pregnant rabbits given 0.2, 2, 22, 156, or 260 mcg/kg/day exenatide during fetal organogenesis, irregular fetal skeletal ossifications were observed at 2 mcg/kg/day, a dose yielding systemic exposure up to 12-times the human exposure from the MRHD of exenatide based on AUC comparison.
In maternal mice given 6, 68, or 760 mcg/kg/day exenatide from gestation day 6 through lactation day 20 (weaning), an increased number of neonatal deaths was observed on postpartum days 2 to 4 in dams given 6 mcg/kg/day, a dose yielding a systemic exposure 3-times the human exposure from the MRHD of exenatide based on AUC comparison.
8.2Lactation Risk Summary There is no information regarding the presence of exenatide, in human milk, the effects of exenatide on the breastfed infant, or the effects of exenatide on milk production. Exenatide was present in the milk of lactating mice. However, due to species-specific differences in lactation physiology, the clinical relevance of these data is not clear (see Data) .
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for exenatide and any potential adverse effects on the breastfed child from exenatide or from the underlying maternal condition. Data In lactating mice subcutaneously injected twice a day with exenatide, the concentration of exenatide in milk was up to 2.5% of the concentration in materna… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited data with exenatide in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations) . Based on animal reproduction studies, there may be risks to the fetus from exposure to exenatide during pregnancy.
Exenatide should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Animal reproduction studies identified increased adverse fetal and neonatal outcomes from exposure to exenatide during pregnancy and lactation in association with maternal effects. In mice, exenatide administered during gestation and lactation caused increased neonatal deaths at systemic exposure 3-times the human exposure resulting from the maximum recommended human dose (MRHD) of 20 mcg/day for exenatide (see Data) .
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with an HbA 1c > 7 and has been reported to be as high as 20% to 25% in women with HbA 1c > 10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryofetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data In studies evaluating reproduction and development in pregnant mice and rabbits, maternal animals were administered exenatide, the active ingredient in exenatide injection, by subcutaneous injection twice a day.
In pregnant mice given 6, 68, 460, or 760 mcg/kg/day exenatide during fetal organogenesis, skeletal variations associated with slowed fetal growth, including changes in number of rib pairs or vertebral ossifications sites, and wavy ribs were observed at 760 mcg/kg/day, a dose that produced maternal toxicity and yielded systemic exposure 390-times the human exposure resulting from the MRHD of exenatide based on AUC comparison. In pregnant rabbits given 0.2, 2, 22, 156, or 260 mcg/kg/day exenatide during fetal organogenesis, irregular fetal skeletal ossifications were observed at 2 mcg/kg/day, a dose yielding systemic exposure up to 12-times the human exposure from the MRHD of exenatide based on AUC comparison.
In maternal mice given 6, 68, or 760 mcg/kg/day exenatide from gestation day 6 through lactation day 20 (weaning), an increased number of neonatal deaths was observed on postpartum days 2 to 4 in dams given 6 mcg/kg/day, a dose yielding a systemic exposure 3-times the human exposure from the MRHD of exenatide based on AUC comparison.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of exenatide have not been established in pediatric patients. Effectiveness of exenatide was not demonstrated in a randomized, double-blind, placebo-controlled study conducted in 120 pediatric patients (78 received exenatide and 42 received placebo) aged 10 to 17 years with type 2 diabetes mellitus.
🧓 Geriatric Use ▾
8.5Geriatric Use Population pharmacokinetic analysis of patients ranging from 22 to 73 years of age suggests that age does not influence the pharmacokinetic properties of exenatide [see Clinical Pharmacology (12.3) ] . Exenatide was studied in 282 patients 65 years of age or older and in 16 patients 75 years of age or older. No differences in safety or effectiveness were observed between these patients and younger patients.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection in the elderly based on renal function.
🆘 Overdosage ▾
10 OVERDOSAGE In a clinical study of exenatide, three patients with type 2 diabetes each experienced a single overdose of 100 mcg SC (10-times the maximum recommended dose). Effects of the overdoses included severe nausea, severe vomiting and rapidly declining blood glucose concentrations. One of the three patients experienced severe hypoglycemia requiring parenteral glucose administration.
The three patients recovered without complication. In the event of overdose, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Initiate appropriate supportive treatment according to the patient’s clinical signs and symptoms.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Incretins, such as glucagon-like peptide-1 (GLP-1), enhance glucose-dependent insulin secretion and exhibit other antihyperglycemic actions following their release into the circulation from the gut. Exenatide is a GLP-1 receptor agonist that enhances glucose-dependent insulin secretion by the pancreatic beta-cell, suppresses inappropriately elevated glucagon secretion, and slows gastric emptying. The amino acid sequence of exenatide partially overlaps that of human GLP-1.
Exenatide has been shown to bind and activate the human GLP-1 receptor in vitro . This leads to an increase in both glucose-dependent synthesis of insulin, and in vivo secretion of insulin from pancreatic beta cells, by mechanisms involving cyclic AMP and/or other intracellular signaling pathways. Exenatide improves glycemic control by reducing fasting and postprandial glucose concentrations in patients with type 2 diabetes through the actions described below.
12.2Pharmacodynamics Glucose-Dependent Insulin Secretion Exenatide has acute effects on pancreatic beta-cell responsiveness to glucose leading to insulin release predominantly in the presence of elevated glucose concentrations. This insulin secretion subsides as blood glucose concentrations decrease and approach euglycemia. However, exenatide does not impair the normal glucagon response to hypoglycemia.
First-Phase Insulin Response In healthy individuals, robust insulin secretion occurs during the first 10 minutes following intravenous (IV) glucose administration. This secretion, known as the “first-phase insulin response,” is characteristically absent in patients with type 2 diabetes. The loss of the first-phase insulin response is an early beta-cell defect in type 2 diabetes.
Administration of exenatide at therapeutic plasma concentrations restored first-phase insulin response to an IV bolus of glucose in patients with type 2 diabetes (Figure 1). Both first-phase insulin secretion and second-phase insulin secretion were significantly increased in patients with type 2 diabetes treated with exenatide compared with saline (p < 0.001 for both). Figure 1: Mean (+SEM) Insulin Secretion Rate during Infusion of Exenatide or Saline in Patients with Type 2 Diabetes and during Infusion of Saline in Healthy Subjects Glucagon Secretion In patients with type 2 diabetes, exenatide moderates glucagon secretion and lowers serum glucagon concentrations during periods of hyperglycemia.
Lower glucagon concentrations lead to decreased hepatic glucose output and decreased insulin demand. Gastric Emptying Exenatide slows gastric emptying, thereby reducing the rate at which meal-derived glucose appears in the circulation. Food Intake In both animals and humans, administration of exenatide has been shown to reduce food intake.
Postprandial Glucose In patients with type 2 diabetes, exenatide reduces postprandial plasma glucose concentrations (Figure 2). Figure 2: Mean (+SEM) Postprandial Plasma Glucose Concentrations on Day 1 of Exenatide a Treatment in Patients with Type 2 Diabetes Treated with Metformin, a Sulfonylurea, or Both (N = 54) Fasting Glucose In a single-dose crossover study in patients with type 2 diabetes and fasting hyperglycemia, immediate insulin release followed injection of exenatide. Plasma glucose concentrations were significantly reduced with exenatide compared with placebo (Figure 3).
Figure 3: Mean (+SEM) Serum Insulin and Plasma Glucose Concentrations Following a One-Time Injection of Exenatide a or Placebo in Fasting Patients with Type 2 Diabetes (N = 12) Cardiac Electrophysiology The effect of exenatide 10 mcg subcutaneously on QTc interval was evaluated in a randomized, placebo-, and active-controlled (moxifloxacin 400 mg) crossover thorough QTc study in 62 healthy subjects. In this study with demonstrated ability to detect small effects, the upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was belo… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Incretins, such as glucagon-like peptide-1 (GLP-1), enhance glucose-dependent insulin secretion and exhibit other antihyperglycemic actions following their release into the circulation from the gut. Exenatide is a GLP-1 receptor agonist that enhances glucose-dependent insulin secretion by the pancreatic beta-cell, suppresses inappropriately elevated glucagon secretion, and slows gastric emptying. The amino acid sequence of exenatide partially overlaps that of human GLP-1.
Exenatide has been shown to bind and activate the human GLP-1 receptor in vitro . This leads to an increase in both glucose-dependent synthesis of insulin, and in vivo secretion of insulin from pancreatic beta cells, by mechanisms involving cyclic AMP and/or other intracellular signaling pathways. Exenatide improves glycemic control by reducing fasting and postprandial glucose concentrations in patients with type 2 diabetes through the actions described below.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Exenatide Injection, USP is supplied as a clear, colorless sterile solution for subcutaneous injection containing 250 mcg/mL exenatide, USP. The following packages are available: 5 mcg per dose, in a single-patient-use prefilled pen containing 300 mcg/1.2 mL (250mcg/mL), 60 doses: NDC 70121-1685-1 10 mcg per dose, in a single-patient-use prefilled pen containing 600 mcg/2.4 mL (250mcg/mL), 60 doses: NDC 70121-1686-1
16.2Storage and Handling Store exenatide injection in the refrigerator at 36 ○ to 46 ○ F (2 ○ to 8 ○ C). After first use, exenatide injection can be kept at a temperature not to exceed 77 ○ F (25 ○ C). Do not freeze.
Do not use exenatide injection if it has been frozen. Protect exenatide injection from light. Discard the pen 30 days after first use, even if some drug remains in the pen.
Use a puncture-resistant container to discard the needles. Do not reuse or share needles.
📋 Description ▾
11 DESCRIPTION Exenatide is a synthetic peptide, GLP-1 receptor agonist, that was originally identified in the lizard Heloderma suspectum . Exenatide is a 39-amino acid peptide amide. Exenatide has the empirical formula C 184 H 282 N 50 O 60 S and molecular weight of 4186.6 Daltons.
The amino acid sequence for exenatide is shown below. H-His-Gly-Glu-Gly-Thr-Phe-Thr-Ser-Asp-Leu-Ser-Lys-Gln-Met-Glu-Glu-Glu-Ala-Val-Arg-Leu-Phe-Ile-Glu-Trp-Leu-Lys-Asn-Gly-Gly-Pro-Ser-Ser-Gly-Ala-Pro-Pro-Pro-Ser-NH 2 Exenatide injection, USP is supplied for subcutaneous administration as a sterile, preserved isotonic solution in a glass cartridge that has been assembled in a pen-injector (pen). Each milliliter (mL) contains 250 micrograms (mcg) synthetic exenatide, USP; 2.2 mg metacresol as an antimicrobial preservative; mannitol as a tonicity-adjusting agent; and glacial acetic acid and sodium acetate trihydrate in water for injection as a buffering solution at pH 4.5.
Two prefilled pens are available to deliver unit doses of 5 mcg per dose or 10 mcg per dose. Each prefilled pen will deliver 60 doses to provide for 30 days of twice daily administration (BID). Each prefilled device is filled with volume to allow delivery of 1.2 mL or 2.4 mL.
Each device contains additional volume to allow for troubleshooting the device 4 times.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide and Instructions for Use). Acute Pancreatitis Inform patients of the potential risk for acute pancreatitis and its symptoms: severe abdominal pain that may radiate to the back and which may or may not be accompanied by nausea or vomiting. Instruct patients to discontinue exenatide promptly and contact their physician if pancreatitis is suspected [see Warnings and Precautions (5.1) ] .
Never Share an Exenatide Injection Pen Between Patients Advise patients that they must never share an exenatide injection pen with another person, even if the needle is changed, because doing so carries a risk for transmission of blood-borne pathogens [see Warnings and Precautions (5.2) ] . Hypoglycemia with Concomitant Use of Insulin Secretagogues or Insulin Inform patients that the risk of hypoglycemia is increased when exenatide is used in combination with an agent that induces hypoglycemia, such as a sulfonylurea or insulin.
Educate patients on the signs and symptoms of hypoglycemia [see Warnings and Precautions (5.3) ] . Acute Kidney Injury Due to Volume Depletion Inform patients of the potential risk of acute kidney injury due to dehydration associated with gastrointestinal adverse reactions. Advise patients to take precautions to avoid fluid depletion.
Inform patients of the signs and symptoms of acute kidney injury and instruct them to promptly report any of these signs or symptoms or persistent (or extended) nausea, vomiting, and diarrhea to their healthcare provider [see Warnings and Precautions (5.4) ] . Severe Gastrointestinal Adverse Reactions Inform patients of the potential risk of severe gastrointestinal adverse reactions. Instruct patients to contact their healthcare provider if they have severe or persistent gastrointestinal symptoms [see Warnings and Precautions (5.5) ].
Drug-Induced Thrombocytopenia Inform patients that drug-induced immune-mediated thrombocytopenia has been reported during use of exenatide. Inform patients that if symptoms of thrombocytopenia occur, stop taking exenatide and seek medical advice promptly [see Warnings and Precautions (5.8) ] . Hypersensitivity Reactions Inform patients that serious hypersensitivity reactions have been reported during post-marketing use of exenatide.
If symptoms of hypersensitivity reactions occur, instruct patients to stop taking exenatide and seek medical advice promptly [see Warnings and Precautions (5.7) ] . Acute Gallbladder Disease Inform patients of the potential risk for cholelithiasis or cholecystitis. Instruct patients to contact their physician if cholelithiasis or cholecystitis is suspected for appropriate clinical follow-up [see Warnings and Precautions (5.9) ] .
Pulmonary Aspiration During General Anesthesia or Deep Sedation Inform patients that exenatide may cause their stomach to empty more slowly which may lead to complications with anesthesia or deep sedation during planned surgeries or procedures. Instruct patients to inform healthcare providers prior to any planned surgeries or procedures if they are taking exenatide [see Warnings and Precautions (5.10)] . Pregnancy Advise patients to inform their physicians if they are pregnant or intend to become pregnant.
Instructions Instruct patients to administer exenatide as a subcutaneous injection in the thigh, abdomen, or upper arm at any time within the 60-minute period before the morning and evening meals (or before the two main meals of the day, approximately 6 hours or more apart). Do not administer exenatide injection after a meal. If a dose is missed, resume the treatment regimen as prescribed with the next scheduled dose.
Manufactured by: Amneal Pharmaceuticals Pvt. Ltd. Ahmedabad 382213, INDIA Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev.
05-2026-09
💬 Medication Guide ▾
Medication Guide Exenatide (ex en’ a tide) Injection, USP for subcutaneous use Read this Medication Guide and the Instructions for Use that comes with exenatide injection before you start using it and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your healthcare provider about your medical condition or your treatment.
If you have questions about exenatide injection after reading this information, ask your healthcare provider or pharmacist. What is the most important information I should know about exenatide injection? Serious side effects can happen in people who take exenatide injection, including inflammation of your pancreas (pancreatitis) .
Stop using exenatide injection and call your healthcare provider right away if you have severe pain in your stomach area (abdomen) that will not go away, with or without nausea or vomiting. Sometimes you may feel the pain from your abdomen to your back. What is exenatide injection?
Exenatide is an injectable prescription medicine that is used along with diet and exercise to improve blood sugar (glucose) in adults with type 2 diabetes mellitus. Exenatide is not recommended for people who take exenatide or other medicines called glucagon-like peptide-1 (GLP-1) receptor agonist. It is not known if exenatide injection is safe and effective in children.
Who should not use exenatide injection? Do not use exenatide injection if: you have had a severe allergic reaction to exenatide or any of the other ingredients in exenatide injection. See the end of this Medication Guide for a complete list of ingredients in exenatide injection.
See “What are the possible side effects of exenatide injection?” for symptoms of a serious allergic reaction. you have a history of low blood platelet count from using exenatide medicines (drug-induced thrombocytopenia). Before taking exenatide injection, tell your healthcare provider about all of your medical conditions, including if you: have or have had problems with your pancreas. have severe problems with your stomach, such as delayed emptying of your stomach (gastroparesis) or problems with digesting food. are scheduled to have surgery or other procedures that use anesthesia or deep sleepiness (deep sedation). are pregnant or plan to become pregnant.
It is not known if exenatide injection will harm your unborn baby. Tell your healthcare provider if you become pregnant while taking exenatide injection. Talk to your healthcare provider about the best way to control your blood sugar if you plan to become pregnant or while you are pregnant. are breastfeeding or plan to breastfeed.
It is not known if exenatide passes into your breast milk. You should talk with your healthcare provider about the best way to feed your baby while taking exenatide injection. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins and herbal supplements.
Exenatide injection may affect the way some medicines work and some other medicines may affect the way exenatide injection works. Before using exenatide injection, talk to your healthcare provider about low blood sugar and how to manage it. Tell your healthcare provider if you are taking other medicines to treat diabetes, including insulin or sulfonylureas.
Especially tell your healthcare provider if you take: birth control pills that are taken by mouth (oral contraceptives). Exenatide injection may lower the amount of the medicine in your blood from your birth control pills and they may not work as well to prevent pregnancy. Take your birth control pills at least one hour before your injection of exenatide.
If you must take your birth control pills with food, take it with a meal or snack at a time when you do not also take exenatide injection. antibiotics. Take antibiotic medicines at least one hour before taking exenatide injection. If you must take your antibiotic with food, take it with a me… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following SC administration to patients with type 2 diabetes, exenatide reaches median peak plasma concentrations in 2.1 hours. The mean peak exenatide concentration (C max ) was 211 pg/mL and overall mean area under the time-concentration curve (AUC 0-inf ) was 1,036 pg•h/mL following SC administration of a 10-mcg dose of exenatide. Exenatide exposure (AUC) increased proportionally over the therapeutic dose range of 5 mcg to 10 mcg.
The C max values increased less than proportionally over the same range. Similar exposure is achieved with SC administration of exenatide in the abdomen, thigh, or upper arm. Distribution The mean apparent volume of distribution of exenatide following SC administration of a single-dose of exenatide is
28.3L. Metabolism and Elimination Nonclinical studies have shown that exenatide is predominantly eliminated by glomerular filtration with subsequent proteolytic degradation. The mean apparent clearance of exenatide in humans is
9.1L/hour and the mean terminal half-life is 2.4 hours. These pharmacokinetic characteristics of exenatide are independent of the dose. In most individuals, exenatide concentrations are measurable for approximately 10 hours post-dose.
Drug Interactions Acetaminophen When 1,000 mg acetaminophen elixir was given with 10 mcg exenatide (0 hour) and 1 hour, 2 hours and 4 hours after exenatide injection, acetaminophen AUCs were decreased by 21%, 23%, 24% and 14%, respectively; C max was decreased by 37%, 56%, 54% and 41%, respectively; T max was increased from 0.6 hour in the control period to 0.9 hour, 4.2 hours, 3.3 hours and 1.6 hours, respectively. Acetaminophen AUC, C max and T max were not significantly changed when acetaminophen was given 1 hour before exenatide injection.
Digoxin Administration of repeated doses of exenatide (10 mcg BID) 30 minutes before oral digoxin (0.25 mg once daily) decreased the C max of digoxin by 17% and delayed the T max of digoxin by approximately 2.5 hours; however, the overall steady-state pharmacokinetic exposure (e.g., AUC) of digoxin was not changed. Lovastatin Administration of exenatide (10 mcg BID) 30 minutes before a single oral dose of lovastatin (40 mg) decreased the AUC and C max of lovastatin by approximately 40% and 28%, respectively, and delayed the T max by about 4 hours compared with lovastatin administered alone.
In the 30-week controlled clinical trials of exenatide, the use of exenatide in patients already receiving HMG CoA reductase inhibitors was not associated with consistent changes in lipid profiles compared to baseline. Lisinopril In patients with mild to moderate hypertension stabilized on lisinopril (5 mg/day to 20 mg/day), exenatide (10 mcg BID) did not alter steady-state C max or AUC of lisinopril. Lisinopril steady-state T max was delayed by 2 hours.
There were no changes in 24-hour mean systolic and diastolic blood pressure. Oral Contraceptives The effect of exenatide (10 mcg BID) on single and on multiple-doses of a combination oral contraceptive (30 mcg ethinyl estradiol plus 150 mcg levonorgestrel) was studied in healthy female subjects. Repeated daily doses of the oral contraceptive (OC) given 30 minutes after exenatide administration decreased the C max of ethinyl estradiol and levonorgestrel by 45% and 27%, respectively and delayed the T max of ethinyl estradiol and levonorgestrel by 3.0 hours and 3.5 hours, respectively, as compared to the oral contraceptive administered alone.
Administration of repeated daily doses of the OC one hour prior to exenatide administration decreased the mean C max of ethinyl estradiol by 15% but the mean C max of levonorgestrel was not significantly changed as compared to when the OC was given alone. Exenatide did not alter the mean trough concentrations of levonorgestrel after repeated daily dosing of the oral contraceptive for both regimens. However, the mean trough concentration of ethinyl estradiol was increased by 20% when the OC was adminis… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Glucose-Dependent Insulin Secretion Exenatide has acute effects on pancreatic beta-cell responsiveness to glucose leading to insulin release predominantly in the presence of elevated glucose concentrations. This insulin secretion subsides as blood glucose concentrations decrease and approach euglycemia. However, exenatide does not impair the normal glucagon response to hypoglycemia.
First-Phase Insulin Response In healthy individuals, robust insulin secretion occurs during the first 10 minutes following intravenous (IV) glucose administration. This secretion, known as the “first-phase insulin response,” is characteristically absent in patients with type 2 diabetes. The loss of the first-phase insulin response is an early beta-cell defect in type 2 diabetes.
Administration of exenatide at therapeutic plasma concentrations restored first-phase insulin response to an IV bolus of glucose in patients with type 2 diabetes (Figure 1). Both first-phase insulin secretion and second-phase insulin secretion were significantly increased in patients with type 2 diabetes treated with exenatide compared with saline (p < 0.001 for both). Figure 1: Mean (+SEM) Insulin Secretion Rate during Infusion of Exenatide or Saline in Patients with Type 2 Diabetes and during Infusion of Saline in Healthy Subjects Glucagon Secretion In patients with type 2 diabetes, exenatide moderates glucagon secretion and lowers serum glucagon concentrations during periods of hyperglycemia.
Lower glucagon concentrations lead to decreased hepatic glucose output and decreased insulin demand. Gastric Emptying Exenatide slows gastric emptying, thereby reducing the rate at which meal-derived glucose appears in the circulation. Food Intake In both animals and humans, administration of exenatide has been shown to reduce food intake.
Postprandial Glucose In patients with type 2 diabetes, exenatide reduces postprandial plasma glucose concentrations (Figure 2). Figure 2: Mean (+SEM) Postprandial Plasma Glucose Concentrations on Day 1 of Exenatide a Treatment in Patients with Type 2 Diabetes Treated with Metformin, a Sulfonylurea, or Both (N = 54) Fasting Glucose In a single-dose crossover study in patients with type 2 diabetes and fasting hyperglycemia, immediate insulin release followed injection of exenatide. Plasma glucose concentrations were significantly reduced with exenatide compared with placebo (Figure 3).
Figure 3: Mean (+SEM) Serum Insulin and Plasma Glucose Concentrations Following a One-Time Injection of Exenatide a or Placebo in Fasting Patients with Type 2 Diabetes (N = 12) Cardiac Electrophysiology The effect of exenatide 10 mcg subcutaneously on QTc interval was evaluated in a randomized, placebo-, and active-controlled (moxifloxacin 400 mg) crossover thorough QTc study in 62 healthy subjects. In this study with demonstrated ability to detect small effects, the upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 msec.
Thus, exenatide (10 mcg single-dose) was not associated with clinically meaningful prolongation of the QTc interval. 10 10 10
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Exenatide has been studied as monotherapy and in combination with metformin, a sulfonylurea, a thiazolidinedione, a combination of metformin and a sulfonylurea, a combination of metformin and a thiazolidinedione, or in combination with insulin glargine with or without metformin and/or thiazolidinedione.
14.1Monotherapy In a randomized, double-blind, placebo-controlled trial of 24 weeks duration, exenatide 5 mcg BID (n=77), exenatide 10 mcg BID (n=78), or placebo BID (n=77) was used as monotherapy in patients with entry HbA 1c ranging from 6.5% to 10%. All patients assigned to exenatide initially received 5 mcg BID for 4 weeks. After 4 weeks, those patients either continued to receive exenatide 5 mcg BID or had their dose increased to 10 mcg BID.
Patients assigned to placebo received placebo BID throughout the trial. Exenatide or placebo was injected subcutaneously before the morning and evening meals. The majority of patients (68%) were White, 26% were West Asian, 3% were Hispanic or Latino ethnicity, 3% were Black or African American and 0.4% were of East Asian ethnicity.
The primary endpoint was the change in HbA 1c from baseline to Week 24 (or the last value at time of early discontinuation). Compared to placebo, exenatide 5 mcg BID and 10 mcg BID resulted in statistically significant reductions in HbA 1c from baseline at Week 24 (Table 7). Table 7: Results of 24-Week Placebo-Controlled Trial of Exenatide used as Monotherapy Placebo BID Exenatide 5 mcg BID Exenatide 10 mcg * BID Intent-to-Treat Population (N) 77 77 78 HbA 1c (%), Mean Baseline 7.8 7.9
7.8Change at Week 24 † -0.2 -0.7 -0.9 Difference from placebo † (95% CI) -0.5 [-0.9, -0.2] ‡ -0.7 [-1.0, -0.3] Proportion Achieving HbA 1c < 7% 38% 48% 53% Body Weight (kg), Mean Baseline 86.1 85.1
86.2Change at Week 24 † -1.5 -2.7 -2.9 Difference from placebo † (95% CI) -1.3 [-2.3, -0.2] -1.5 [-2.5, -0.4] Fasting Serum Glucose § (mg/dL), Mean Baseline 159 166 155 Change at Week 24 † -5 -17 -19 Difference from placebo † (95% CI) -12 [-23.2, -1.3] -14 [-24.5, -2.5] * Exenatide 5 mcg twice daily (BID) for 1 month followed by 10 mcg BID for 5 months before the morning and evening meals. † Least squares means are adjusted for screening HbA 1c strata and baseline value of the dependent variable. ‡ p < 0.01, treatment vs. placebo. § Measured using the hexokinase-based glucose method.
BID = twice daily. On average, there were no adverse effects of exenatide on blood pressure or lipids.
14.2Combination Therapy with Oral Antihyperglycemic Medicines Three 30-week, double-blind, placebo-controlled trials were conducted to evaluate the safety and efficacy of exenatide in patients with type 2 diabetes whose glycemic control was inadequate with metformin alone, a sulfonylurea alone, or metformin in combination with a sulfonylurea. In addition, a 16-week, placebo-controlled trial was conducted where exenatide was added to existing thiazolidinedione (pioglitazone or rosiglitazone) treatment, with or without metformin, in patients with type 2 diabetes with inadequate glycemic control.
In the 30-week trials, after a 4-week placebo lead-in period, patients were randomly assigned to receive exenatide 5 mcg BID, exenatide 10 mcg BID, or placebo BID before the morning and evening meals, in addition to their existing oral antidiabetic agent. All patients assigned to exenatide initially received 5 mcg BID for 4 weeks. After 4 weeks, those patients either continued to receive exenatide 5 mcg BID or had their dose increased to 10 mcg BID.
Patients assigned to placebo received placebo BID throughout the study. A total of 1,446 patients were randomized in the three 30-week trials: 991 (69%) were White, 224 (16%) were Hispanic or Latino and 174 (12%) were of Black of African American ethnicity. Mean HbA 1c values at baseline for the trials ranged from 8.2% to 8.7%.
In the placebo-controlled trial of 16 weeks duration, exenatide (n=121) or placebo (n=112) was added to existing thiaz… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility A 104-week carcinogenicity study was conducted in male and female rats at doses of 18, 70, or 250 mcg/kg/day administered by bolus SC injection. Benign thyroid C-cell adenomas were observed in female rats at all exenatide doses. The incidences in female rats were 8% and 5% in the two control groups and 14%, 11% and 23% in the low-, medium- and high-dose groups with systemic exposures of 5-, 22-, and 130-times, respectively, the human exposure resulting from the maximum recommended dose of 20 mcg/day, based on plasma area under the curve (AUC).
In a 104-week carcinogenicity study in mice at doses of 18, 70, or 250 mcg/kg/day administered by bolus SC injection, no evidence of tumors was observed at doses up to 250 mcg/kg/day, a systemic exposure up to 95-times the human exposure resulting from the maximum recommended dose of 20 mcg/day, based on AUC. Exenatide was not mutagenic or clastogenic, with or without metabolic activation, in the Ames bacterial mutagenicity assay or chromosomal aberration assay in Chinese hamster ovary cells. Exenatide was negative in the in vivo mouse micronucleus assay.
In mouse fertility studies with SC doses of 6, 68, or 760 mcg/kg/day, males were treated for 4 weeks prior to and throughout mating, and females were treated 2 weeks prior to mating and throughout mating until gestation day 7. No adverse effect on fertility was observed at 760 mcg/kg/day, a systemic exposure 390-times the human exposure resulting from the maximum recommended dose of 20 mcg/day, based on AUC.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility A 104-week carcinogenicity study was conducted in male and female rats at doses of 18, 70, or 250 mcg/kg/day administered by bolus SC injection. Benign thyroid C-cell adenomas were observed in female rats at all exenatide doses. The incidences in female rats were 8% and 5% in the two control groups and 14%, 11% and 23% in the low-, medium- and high-dose groups with systemic exposures of 5-, 22-, and 130-times, respectively, the human exposure resulting from the maximum recommended dose of 20 mcg/day, based on plasma area under the curve (AUC).
In a 104-week carcinogenicity study in mice at doses of 18, 70, or 250 mcg/kg/day administered by bolus SC injection, no evidence of tumors was observed at doses up to 250 mcg/kg/day, a systemic exposure up to 95-times the human exposure resulting from the maximum recommended dose of 20 mcg/day, based on AUC. Exenatide was not mutagenic or clastogenic, with or without metabolic activation, in the Ames bacterial mutagenicity assay or chromosomal aberration assay in Chinese hamster ovary cells. Exenatide was negative in the in vivo mouse micronucleus assay.
In mouse fertility studies with SC doses of 6, 68, or 760 mcg/kg/day, males were treated for 4 weeks prior to and throughout mating, and females were treated 2 weeks prior to mating and throughout mating until gestation day 7. No adverse effect on fertility was observed at 760 mcg/kg/day, a systemic exposure 390-times the human exposure resulting from the maximum recommended dose of 20 mcg/day, based on AUC.
📄 Patient Package Insert ▾
INSTRUCTIONS FOR USE Exenatide (ex en’ a tide) Injection, USP for subcutaneous use 5 mcg/dose 300 mcg/1.2 mL ( 250 mcg/mL) Do not share your Exenatide Injection Pen with other people, even if the needle has been changed. You may give other people a serious infection or get a serious infection from them. Section 1 Read this section completely before you begin.
Then, move on to Section 2−Getting Started. WHAT YOU NEED TO KNOW ABOUT YOUR EXENATIDE INJECTION PEN INSTRUCTIONS FOR USE Read these instructions carefully BEFORE using your Exenatide Injection Pen. For complete dosing and safety information, also read the Exenatide Injection Medication Guide that comes with the Exenatide Injection Pen carton.
It is important that you use your pen correctly. Failure to follow these instructions completely may result in a wrong dose, a broken pen or an infection. These instructions do not take the place of talking with your healthcare provider about your medical condition or your treatment.
If you are having problems using your Exenatide Injection Pen, call toll free 1-877-835-5472. IMPORTANT INFORMATION ABOUT YOUR EXENATIDE INJECTION PEN Each Exenatide Injection Pen contains enough medicine for injection two times each day for 30 days. You do not have to measure any doses, the pen measures each dose for you.
Do not mix Exenatide Injection and insulin in the same syringe or vial even if you take them at the same time. If any part of your pen appears broken or damaged, do not use the pen. This Exenatide Injection Pen is not recommended for use by people who are blind or have vision problems without the help of a person trained in the proper use of the pen.
Follow the injection method explained to you by your healthcare provider. Follow Section 2 only to set up a new pen before first use. Section 3 of these Instructions for Use should be used for every injection.
ABOUT PEN NEEDLES What kinds of needles can be used with my Exenatide Injection Pen? Pen needles are not included with your pen. You may need a prescription to get them from your pharmacist.
Use 29 (thin), 30, or 31 (thinner) gauge disposable pen needles with your Exenatide Injection Pen. Ask your healthcare provider which needle gauge and length is best for you. Do I use a new needle for each injection?
Yes. Do not reuse or share your needles with other people. You may give other people a serious infection or get a serious infection from them.
Remove the needle from the pen immediately after you complete each injection. This will help prevent leakage of Exenatide Injection, keep out air bubbles, reduce needle clogs, and decrease the risk of infection. Do not push the injection button on your pen unless a needle is attached to the pen.
How do I throw away my needles? Put your used needles in a FDA-cleared sharps disposal container right away after use. Do not throw away (dispose of) loose needles and syringes in your household trash.
If you do not have a FDA-cleared sharps disposal container, you may use a household container that is: Made of a heavy-duty plastic, Can be closed with a tight-fitting, puncture-resistant lid, without sharps being able to come out, Upright and stable during use, Leak-resistant, and Properly labeled to warn of hazardous waste inside the container. When your sharps disposal container is almost full, you will need to follow your community guidelines for the right way to dispose of your sharps disposal container. There may be state or local laws about how you should throw away used needles and syringes.
Do not share your Exenatide Injection Pen with other people, even if the needle has been changed. You may give other people a serious infection or get a serious infection from them. STORING YOUR EXENATIDE INJECTION PEN How do I store my Exenatide Injection Pen?
Prior to first use, store your unused Exenatide Injection Pen in the original carton in a refrigerator at 36° to 46°F (2° to 8°C). After first use, your Exenatide Injection Pen can be kept at a temper… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 70121-1685-1 Exenatide Injection, 250 mcg/mL (1.2 mL) Rx only Amneal Pharmaceuticals LLC NDC 70121-1686-1 Exenatide Injection, 250 mcg/mL (2.4 mL) Rx only Amneal Pharmaceuticals LLC 1 1 1 1
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |