
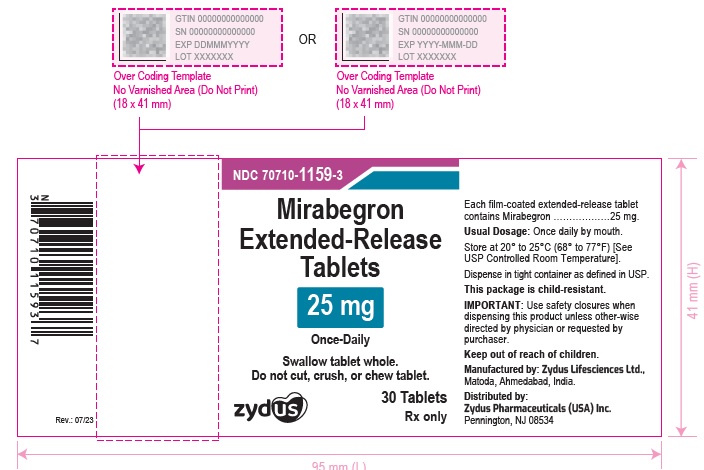
Mirabegron 50 mg Tablet, Extended Release, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta3-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Mirabegron is used alone or in combination with solifenacin (Vesicare) to treat overactive bladder (a condition in which the bladder muscles contract uncontrollably and cause frequent urination, urgent need to urinate, and inability to control urination) in adults. It is also used to treat neurogenic detrusor overactivity (a bladder control condition caused by brain, spinal cord or nerve problem) in children 3 years of age and older. Mirabegron is in a class of medications called beta-3 adrenergic agonists. It works by relaxing the bladder muscles to prevent urgent, frequent, or uncontrolled u...
Read the full MedlinePlus article ↗- Mirabegron helps your bladder muscle relax so it can hold more urine before you feel a sudden urge to go. If you're dealing with overactive bladder — the urgency, the leaks, the co...
- What is mirabegron actually supposed to do for me?
- For adults taking the tablet, it doesn't matter — you can take it with or without food. But if a child is taking either the tablet or the oral suspension (granules), it should alwa...
- Does it matter if I take it with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mirabegron — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII 11628IH70O
Polyethylene oxide is a synthetic polymer derived from ethylene. In medicines, it acts as a binder to hold ingredients together, a thickener to adjust texture, and a disintegrant to help the tablet or capsule break apart for absorption.
-
UNII 5K3991GVWI
A synthetic polymer derived from ethylene that acts as a thickener, binder, and film-former in medications. It helps control how quickly the drug dissolves and improves the texture and consistency of tablets, capsules, and liquid formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.596 | $287.88 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $9.79 | $293.67 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $7.35 | $220.56 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mirabegron 50 mg 68180-0152-06 | Lupin | 30 tablets | $9.596 | AB | Availability likely | — |
| Mirabegron 50 mg 69238-2861-01 | Amneal | 30 tablets | $9.596 | AB | Availability likely | — |
| Mirabegron 50 mgthis 70710-1160-03 | Zydus | 30 tablets | $9.596 | AB | Availability likely | — |
| Myrbetriq 50 mg 00469-2602-07 | Astellas | 7 tablets | — | AB | FDA listed | — |
| Mirabgeorn 50 mg 67184-0572-01 | Qilu | 30 tablets | — | AB | FDA listed | — |
| Mirabegron 50 mg 70518-4304-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Mirabegron 50 mg 70518-4665-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Mirabegron 50 mg 70771-1753-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Mirabegron 50 mg 71335-2808-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Mirabegron 50 mg 71335-2810-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 70710-1160-01 | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (70710-1160-1) | — | — | 2024-01-23 | Active |
| 70710-1160-03 You're viewing this | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (70710-1160-3) | $9.60 / ea | $287.88 | 2024-01-23 | Active |
| 70710-1160-09 | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (70710-1160-9) | $9.60 / ea | $863.64 | 2024-01-23 | Active |
You're viewing the smallest of 3 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($9.60 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 91% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 70710-1160-03?
What is the difference between NDC 70710-1160-03 and NDC 70710-1160-09?
What NDC number is used to bill for this package of Mirabegron 50 mg Tablet, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mirabegron extended-release tablets are a beta-3 adrenergic agonist indicated for the treatment of: Overactive bladder (OAB) in adult patients with symptoms of urge urinary incontinence, urgency, and urinary frequency. ( 1.1 ) Neurogenic detrusor overactivity (NDO) in pediatric patients aged 3 years and older and weighing 35 kg or more. ( 1.2 )
1.1Adult Overactive Bladder (OAB) Mirabegron Monotherapy Mirabegron extended-release tablets are indicated for the treatment of OAB in adult patients with symptoms of urge urinary incontinence, urgency, and urinary frequency.
1.2Pediatric Neurogenic Detrusor Overactivity (NDO) Mirabegron extended-release tablets are indicated for the treatment of NDO in pediatric patients aged 3 years and older and weighing 35 kg or more.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Mirabegron extended-release tablets and Mirabegron Granules are two different products and they are not substitutable on a milligram-per-milligram basis. Select the recommended product (Mirabegron extended-release tablets and Mirabegron Granules) based on the indication and patient's weight. OAB in Adults The recommended starting dose of mirabegron extended-release tablets is 25 mg orally once daily.
( 2.2 ) After 4 to 8 weeks, the mirabegron extended-release tablets dose may be increased to 50 mg orally once daily. ( 2.2 ) NDO in Pediatric Patients 3 Years and Older Pediatric Patients weighing 35 kg or more: Use mirabegron extended-release tablets: The recommended starting dosage of mirabegron extended-release tablets is 25 mg orally once daily. After 4 to 8 weeks, the mirabegron extended-release tablets dose may be increased to 50 mg orally once daily.
( 2.3 ) Adult or Pediatric Patients Patients with Renal or Hepatic Impairment : Refer to the full prescribing information for recommended dosage. ( 2.4 , 2.5 ) Administration Mirabegron extended-release tablets: Adult patients: Swallow mirabegron extended-release tablets whole with water. Do not chew, divide, or crush.
Take with or without food. ( 2.7 ) Pediatric patients: Swallow mirabegron extended-release tablets whole with water. Do not chew, divide, or crush.
Take with food. ( 2.7 )
2.1Important Dosage Information Mirabegron extended-release tablets and Mirabegron Granules are two different products and they are not substitutable on a milligram-per-milligram basis. Select the recommended product (Mirabegron extended-release tablets and Mirabegron Granules) based on the indication and patient's weight [see Indications and Usage ( 1 ) and Dosage and Administration ( 2.2 , 2.3 , 2.4 , 2.5 )].
2.2Recommended Dosage for Adult Patients with OAB Mirabegron Monotherapy The recommended starting dosage of mirabegron extended-release tablets is 25 mg orally once daily. If needed, increase to the maximum dosage of mirabegron extended-release tablets 50 mg orally once daily after 4 to 8 weeks. For administration instructions, see Dosage and Administration ( 2.7 ).
2.3Recommended Dosage for Pediatric Patients Aged 3 Years and Older with NDO For pediatric patients 3 years of age and older, select the appropriate product (Mirabegron extended-release tablets and Mirabegron Granules) based on the patient's weight. Pediatric Patients weighing 35 kg or more: Use mirabegron extended-release tablets The recommended starting dosage of mirabegron extended-release tablets is 25 mg orally once daily. If needed, increase to a maximum dosage of mirabegron extended-release tablets 50 mg orally once daily after 4 to 8 weeks.
For administration instructions, see Dosage and Administration (2.7) .
2.4Recommended Dosage in Adult Patients with Renal or Hepatic Impairment Dosage in Adults with Renal Impairment The recommended dosage of mirabegron extended-release tablets (administered orally once daily) in adult patients with renal impairment is described in Table 1 [see Use in Specific Populations ( 8.6 )]. For administration instructions, see Dosage and Administration ( 2.7 ). Table 1: Mirabegron Extended-Release Tablets Recommended Dosage in Adult Patients with Renal Impairment (Administered Orally Once Daily) Estimated GFR 1 Starting Dose Maximum Dose eGFR 30 to 89 mL/min/1.73 m 2 25 mg 50 mg eGFR 15 to 29 mL/min/1.73 m 2 25 mg 25 mg eGFR < 15 mL/min/1.73 m 2 or requiring dialysis Not Recommended 1.
Estimated GFR using the modification of diet in renal disease (MDRD) formula Dosage in Adults with Hepatic Impairment The recommended dosage of mirabegron extended-release tablets (administered orally once daily) in adult patients with hepatic impairment is described in Table 2 [see Use in Specific Populations ( 8.7 )]. For administration instructions, see Dosage and Administration ( 2.7 ). Table 2: Mirabegron Recommended Dosage in Adult Patients with Hepatic Impairment (Admin…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Extended-release tablets: 25 mg and 50 mg ( 3 ) Mirabegron extended-release tablets are supplied in two different strengths as described below: 25 mg peach colored, oval shaped, biconvex, film-coated tablets debossed with "1159" on one side and plain on other side 50 mg yellow colored, oval shaped, biconvex, film-coated tablets debossed with "1160" on one side and plain on other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Mirabegron extended-release tablets are contraindicated in patients with known hypersensitivity reactions to mirabegron or any inactive ingredients of the tablet [see Adverse Reactions ( 6.1 , 6.2 )]. Hypersensitivity to mirabegron or any inactive ingredients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Increases in Blood Pressure: Can increase blood pressure in adult or pediatric patients. Periodically monitor blood pressure, especially in hypertensive patients. Mirabegron extended-release tablets are not recommended in patients with severe uncontrolled hypertension.
( 5.1 ) Urinary Retention in Patients with Bladder Outlet Obstruction and in Patients Taking Muscarinic Antagonist Drugs for Overactive Bladder: Administer with caution in these patients because of risk of urinary retention. ( 5.2 ) Angioedema: Angioedema of the face, lips, tongue and/or larynx has been reported with mirabegron. ( 5.3 , 6.2 )
5.1Increases in Blood Pressure Increases in Blood Pressure in Adults Mirabegron can increase blood pressure. Periodic blood pressure determinations are recommended, especially in hypertensive patients. Mirabegron is not recommended for use in patients with severe uncontrolled hypertension (defined as systolic blood pressure greater than or equal to 180 mm Hg and/or diastolic blood pressure greater than or equal to 110 mm Hg) [see Clinical Pharmacology ( 12.2 )] .
In two, randomized, placebo-controlled, healthy adult volunteer studies, mirabegron was associated with dose-related increases in supine blood pressure. In these studies, at the maximum recommended dose of 50 mg, the mean maximum increase in systolic/diastolic blood pressure was approximately 3.5/1.5 mm Hg greater than placebo. In contrast, in adult OAB patients in clinical trials, mirabegron, taken as monotherapy, the mean increase in systolic and diastolic blood pressure at the maximum recommended mirabegron dose of 50 mg was approximately 0.5 to 1 mm Hg greater than placebo.
Worsening of pre-existing hypertension was reported infrequently in patients taking mirabegron. Increases in Blood Pressure in Pediatric Patients 3 Years and Older Mirabegron can increase blood pressure in pediatric patients. Blood pressure increases may be larger in children (3 to less than 12 years of age) than in adolescents (12 to less than 18 years of age).
Periodic blood pressure determinations are recommended. Mirabegron is not recommended for use in pediatric patients with severe uncontrolled hypertension, defined as a systolic and/or diastolic blood pressure above the 99 th percentile plus 5 mm Hg for age, sex, and stature using appropriate reference values [see Adverse Reactions (6.1) ] .
5.2Urinary Retention in Patients with Bladder Outlet Obstruction and in Patients Taking Muscarinic Antagonist Medications for OAB In patients taking mirabegron, urinary retention has been reported to occur in patients with bladder outlet obstruction (BOO) and in patients taking muscarinic antagonist medications for the treatment of OAB. A controlled clinical safety study in patients with BOO did not demonstrate increased urinary retention in patients treated with mirabegron; however, mirabegron should still be administered with caution to patients with clinically significant BOO.
For example, monitor these patients for signs and symptoms of urinary retention. Mirabegron should also be administered with caution to patients taking muscarinic antagonist medications for the treatment of OAB [see Clinical Pharmacology ( 12.2 )] .
5.3Angioedema Angioedema of the face, lips, tongue, and/or larynx has been reported with mirabegron. In some cases, angioedema occurred after the first dose, however, cases have been reported to occur hours after the first dose or after multiple doses. Angioedema, associated with upper airway swelling, may be life-threatening.
If involvement of the tongue, hypopharynx, or larynx occurs, promptly discontinue mirabegron and provide appropriate therapy and/or measures necessary to ensure a patent airway [see Adverse Reactions ( 6.2 )].
5.4Patients Taking Drugs Metabolized by CYP2D6 Since mirabegron is a moderate CYP2D6 inhibitor, the systemic exposure to CYP2D6 substrates is increased when coadministered with mirabegron. Therefore, appropriate monit…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling. Hypertension [see Warnings and Precautions ( 5.1 )] Urinary Retention [see Warnings and Precautions ( 5.2 )] Angioedema [see Warnings and Precautions ( 5.3 )] Most commonly reported adverse reactions with mirabegron monotherapy in adult patients with OAB (> 2% and > placebo) were hypertension, nasopharyngitis, urinary tract infection, and headache. ( 6.1 ) Most commonly reported adverse reactions with mirabegron in pediatric patients with NDO (≥ 3%) were UTI, nasopharyngitis, constipation, and headache.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Zydus Pharmaceuticals (USA) Inc. at 1-877-993-8779 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Mirabegron Monotherapy for Adult OAB In three, 12-week, double-blind, placebo-controlled, safety and efficacy studies in patients with OAB (Studies 1, 2, and 3), mirabegron was evaluated for safety in 2,736 patients [see Clinical Studies ( 14.1 )].
Study 1 also included an active control. For the combined Studies 1, 2, and 3,432 patients received mirabegron 25 mg, 1,375 received mirabegron 50 mg, and 929 received mirabegron 100 mg once daily. In these studies, the majority of the patients were Caucasian (94%), and female (72%) with a mean age of 59 years (range 18 to 95 years).
Mirabegron was also evaluated for safety in 1,632 patients who received mirabegron 50 mg once daily (n=812 patients) or mirabegron 100 mg (n=820 patients) in a 1-year, randomized, fixed- dose, double-blind, active-controlled, safety study in patients with OAB (Study 4). Of these patients, 731 received mirabegron in a previous 12-week study. In Study 4, 1385 patients received mirabegron continuously for at least 6 months, 1,311 patients received mirabegron for at least 9 months, and 564 patients received mirabegron for at least 1 year.
The most frequent adverse events (0.2%) leading to discontinuation in Studies 1, 2 and 3 for the 25 mg or 50 mg dose were nausea, headache, hypertension, diarrhea, constipation, dizziness, and tachycardia. Atrial fibrillation (0.2%) and prostate cancer (0.1%) were reported as serious adverse events by more than 1 patient and at a rate greater than placebo. Table 3 the lists adverse reactions, derived from all adverse events that were reported in Studies 1, 2 and 3 at an incidence greater than placebo and in 1% or more of patients treated with mirabegron 25 mg or 50 mg once daily for up to 12 weeks.
The most commonly reported adverse reactions (greater than 2% of mirabegron patients and greater than placebo) were hypertension, nasopharyngitis, urinary tract infection, and headache. Table 3: Percentages of Patients with Adverse Reactions, Derived from All Adverse Events, Exceeding Placebo Rate and Reported in ≥ 1% of OAB Patients Treated with mirabegron 25 mg or 50 mg Once Daily in Studies 1, 2, and 3 Adverse Reaction Placebo (%) Mirabegron 25 mg (%) Mirabegron 50 mg (%) Number of Patients 1380 432 1375 Hypertension * 7.6 11.3
7.5Nasopharyngitis 2.5 3.5
3.9Urinary Tract Infection 1.8 4.2
2.9Headache 3.0 2.1
3.2Constipation 1.4 1.6
1.6Upper Respiratory Tract Infection 1.7 2.1
1.5Arthralgia 1.1 1.6
1.3Diarrhea 1.3 1.2
1.5Tachycardia 0.6 1.6
1.2Abdominal Pain 0.7 1.4
0.6Fatigue 1.0 1.4 1.2 * Includes reports of blood pressure above the normal range, and BP increased from baseline, occurring predominantly in subjects with baseline hypertension. Other adverse reactions reported by less than 1% of patients treated with mirabegron in Studies 1, 2, or 3 included: Cardiac disorders: palpitations, blood pressure increased [see Clinical Pharmacology ( 12.2 )] Eye…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drug interaction studies were conducted in adult patients to investigate the effect of coadministered drugs on the pharmacokinetics of mirabegron and the effect of mirabegron on the pharmacokinetics of coadministered drugs (e.g., ketoconazole, rifampin, solifenacin succinate, tamsulosin, and oral contraceptives) [see Clinical Pharmacology ( 12.3 )] . No dose adjustment is recommended when these drugs are coadministered with mirabegron. The following are drug interactions for which monitoring is recommended: Drugs Metabolized by CYP2D6: Mirabegron is a CYP2D6 inhibitor and, when used concomitantly with drugs metabolized by CYP2D6, especially narrow therapeutic index drugs, appropriate monitoring and possible dose adjustment of those drugs may be necessary.
( 5.4 , 7.1 , 12.3 ) Digoxin: When initiating a combination of mirabegron and digoxin, use the lowest dose of digoxin; monitor serum digoxin concentrations to titrate digoxin dose to desired clinical effect. ( 7.2 , 12.3 )
7.1Drugs Metabolized by CYP2D6 Since mirabegron is a moderate CYP2D6 inhibitor, the systemic exposure of drugs metabolized by CYP2D6 enzyme is increased when coadministered with mirabegron. Therefore, appropriate monitoring and dose adjustment may be necessary when mirabegron is coadministered with these drugs, especially with narrow therapeutic index CYP2D6 substrates [see Warnings and Precautions ( 5.4 ) and Clinical Pharmacology ( 12.3 )] .
7.2Digoxin When given in combination, 100 mg mirabegron increased mean digoxin C max from 1.01 ng/mL to 1.3 ng/mL (29%) and AUC from 16.7 ng.h/mL to 19.3 ng.h/mL (27%). For patients who are initiating a combination of mirabegron and digoxin, the lowest dose for digoxin should initially be considered. Serum digoxin concentrations should be monitored and used for titration of the digoxin dose to obtain the desired clinical effect [see Clinical Pharmacology ( 12.3 )] .
7.3Warfarin The mean C max of S- and R- warfarin was increased by approximately 4% and AUC by approximately 9% when administered as a single dose of 25 mg after multiple doses of 100 mg mirabegron. Following a single dose administration of 25 mg warfarin, mirabegron had no effect on the warfarin pharmacodynamic endpoints such as International Normalized Ratio (INR) and prothrombin time. However, the effect of mirabegron on multiple doses of warfarin and on warfarin pharmacodynamic end points such as INR and prothrombin time has not been fully investigated [see Clinical Pharmacology ( 12.3 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no studies with the use of mirabegron in pregnant women or adolescents to inform a drug-associated risk of major birth defects, miscarriages, or adverse maternal or fetal outcomes. Mirabegron administration to pregnant animals during organogenesis resulted in reversible skeletal variations (in rats) at 22-fold (via AUC) the maximum recommended human dose (MRHD) of 50 mg/day and decreased fetal body weights (in rabbits) at 14-fold the MRHD. At maternally-toxic exposures in rats (96-fold), decreased fetal weight and increased fetal mortality were observed and, in rabbits (36-fold), cardiac findings (fetal cardiomegaly and fetal dilated aortae) were observed [see Data].
The estimated background risks of major birth defects and miscarriage for the indicated populations are unknown. In the U.S. general population, the estimated background risks of major birth defects or miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively. Data Animal Data No embryo-fetal lethality or morphological fetal developmental abnormalities were produced in pregnant rats following daily oral administration of mirabegron during the period of organogenesis (Days 7 to 17 of gestation) at 0, 10, 30, 100, or 300 mg/kg, doses which were associated with systemic exposures (AUC) 0, 1, 6, 22, and 96-fold the MRHD.
Skeletal variations (wavy ribs, delayed ossification) were observed in fetuses at doses 22-fold the systemic exposure at the MRHD and were reversible during development. Exposures 96-fold the MRHD were maternally-toxic (mortality, decreased body weight gain) and associated with fetal growth reduction. Pregnant rabbits were treated with daily oral doses of mirabegron at 0, 3, 10, or 30 mg/kg/day during the period of organogenesis (Days 6 to 20 of gestation), which resulted in plasma exposures that were 0, 1, 14, or 36-fold the MRHD based on AUC.
At 10 mg/kg/day (14-fold the MRHD) and higher, fetal body weights were reduced. At 30 mg/kg/day, maternal toxicity (increased heart rate, mortality, reduced body weight gain, reduced food consumption) occurred, and fetal deaths, fetal cardiomegaly and fetal dilated aortae were observed at systemic exposure levels (AUC) 36-fold the MRHD. In a pre-and postnatal developmental study, rats were treated with daily oral doses of mirabegron at 0, 10, 30, or 100 mg/kg/day (0, 1, 6, or 22-fold the MRHD) from day 7 of gestation until day 20 after birth.
Decreased maternal body weight was observed along with decreased pup survival in the first few days after birth (92.7% survival) compared to the control group (98.8% survival), at 100 mg/kg/day (22-fold the MRHD). Pup body weight gain was reduced until postnatal day 7 but not further affected throughout the remainder of the lactation period. In utero and lactational exposure did not affect developmental milestones, behavior or fertility of offspring.
No effects were observed at 30 mg/kg/day.
8.2Lactation Risk Summary There are no data on the presence of mirabegron in human milk, the effects on the breastfed child, or the effects on milk production. Mirabegron-related material was present in rat milk and in the stomach of nursing pups following administrations of a single 10 mg/kg oral dose of 14 C-labeled mirabegron to lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for mirabegron and any potential adverse effects on the breastfed child from mirabegron or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness have been established only for the following pediatric indications: Mirabegron: Treatment of neurogenic detrusor overactivity (NDO) in pediatric patients 3years of age and older and weighing 35 kg or more. The safety and effectiveness of mirabegron in pediatric…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no studies with the use of mirabegron in pregnant women or adolescents to inform a drug-associated risk of major birth defects, miscarriages, or adverse maternal or fetal outcomes. Mirabegron administration to pregnant animals during organogenesis resulted in reversible skeletal variations (in rats) at 22-fold (via AUC) the maximum recommended human dose (MRHD) of 50 mg/day and decreased fetal body weights (in rabbits) at 14-fold the MRHD. At maternally-toxic exposures in rats (96-fold), decreased fetal weight and increased fetal mortality were observed and, in rabbits (36-fold), cardiac findings (fetal cardiomegaly and fetal dilated aortae) were observed [see Data].
The estimated background risks of major birth defects and miscarriage for the indicated populations are unknown. In the U.S. general population, the estimated background risks of major birth defects or miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively. Data Animal Data No embryo-fetal lethality or morphological fetal developmental abnormalities were produced in pregnant rats following daily oral administration of mirabegron during the period of organogenesis (Days 7 to 17 of gestation) at 0, 10, 30, 100, or 300 mg/kg, doses which were associated with systemic exposures (AUC) 0, 1, 6, 22, and 96-fold the MRHD.
Skeletal variations (wavy ribs, delayed ossification) were observed in fetuses at doses 22-fold the systemic exposure at the MRHD and were reversible during development. Exposures 96-fold the MRHD were maternally-toxic (mortality, decreased body weight gain) and associated with fetal growth reduction. Pregnant rabbits were treated with daily oral doses of mirabegron at 0, 3, 10, or 30 mg/kg/day during the period of organogenesis (Days 6 to 20 of gestation), which resulted in plasma exposures that were 0, 1, 14, or 36-fold the MRHD based on AUC.
At 10 mg/kg/day (14-fold the MRHD) and higher, fetal body weights were reduced. At 30 mg/kg/day, maternal toxicity (increased heart rate, mortality, reduced body weight gain, reduced food consumption) occurred, and fetal deaths, fetal cardiomegaly and fetal dilated aortae were observed at systemic exposure levels (AUC) 36-fold the MRHD. In a pre-and postnatal developmental study, rats were treated with daily oral doses of mirabegron at 0, 10, 30, or 100 mg/kg/day (0, 1, 6, or 22-fold the MRHD) from day 7 of gestation until day 20 after birth.
Decreased maternal body weight was observed along with decreased pup survival in the first few days after birth (92.7% survival) compared to the control group (98.8% survival), at 100 mg/kg/day (22-fold the MRHD). Pup body weight gain was reduced until postnatal day 7 but not further affected throughout the remainder of the lactation period. In utero and lactational exposure did not affect developmental milestones, behavior or fertility of offspring.
No effects were observed at 30 mg/kg/day.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness have been established only for the following pediatric indications: Mirabegron: Treatment of neurogenic detrusor overactivity (NDO) in pediatric patients 3years of age and older and weighing 35 kg or more. The safety and effectiveness of mirabegron in pediatric patients aged 3 years and older have been established for the treatment of neurogenic detrusor overactivity (NDO) and the information on this use is discussed throughout the labeling. Use of mirabegron for this indication is supported by evidence from a 52-week, open-label, baseline-controlled, multicenter, dose titration trial in pediatric patients 3 years of age and older with NDO (Study 9) [see Adverse Reactions (6.1), Clinical Studies (14.3)] .
Results showed an improvement from baseline in maximum cystometric (bladder) capacity (MCC) with mirabegron use [see Clinical Studies (14.3)] . The most commonly reported adverse reactions in Study 9 (≥3%) were UTI, nasopharyngitis, constipation, and headache. Increased mean systolic and diastolic blood pressures with use of mirabegron occurred in patients less than 12 years of age with larger increases in patients younger than 8 years of age [see Adverse Reactions (6.1)] .
Take mirabegron with food to reduce potential exposure-related risks, such as increased heart rate, as predicted by modeling of vital signs data in Study 9 [see Clinical Pharmacology (12.3)] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of 5,648 patients who received mirabegron monotherapy in the phase 2 and 3 studies for OAB, 2,029 (35.9%) were 65 years of age or older, and 557 (9.9%) were 75 years of age or older. No overall differences in safety or effectiveness were observed between patients younger than 65 years of age and those 65 years of age or older in these studies.
🆘 Overdosage ▾
10 OVERDOSAGE Mirabegron has been administered to healthy volunteers at single doses up to 400 mg. At this dose, adverse events reported included palpitations (1 of 6 subjects) and increased pulse rate exceeding 100 beats per minute (bpm) (3 of 6 subjects). Multiple doses of mirabegron up to 300 mg daily for 10 days showed increases in pulse rate and systolic blood pressure when administered to healthy volunteers.
Treatment for overdosage should be symptomatic and supportive. In the event of overdosage, pulse rate, blood pressure and ECG monitoring is recommended.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Mirabegron is an agonist of the human beta-3 adrenergic receptor (AR) as demonstrated by in vitro laboratory experiments using the cloned human beta-3 AR. Mirabegron relaxes the detrusor smooth muscle during the storage phase of the urinary bladder fill-void cycle by activation of beta-3 AR which increases bladder capacity. Although mirabegron showed very low intrinsic activity for cloned human beta-1 AR and beta-2 AR, results in humans indicate that beta-1 AR stimulation occurred at a mirabegron dose of 200 mg.
12.2Pharmacodynamics Urodynamics The effects of mirabegron on maximum urinary flow rate and detrusor pressure at maximum flow rate were assessed in a urodynamic study consisting of 200 male patients with lower urinary tract symptoms (LUTS) and BOO. Administration of mirabegron once daily for 12 weeks did not adversely affect the mean maximum flow rate or mean detrusor pressure at maximum flow rate in this study. Nonetheless, mirabegron should be administered with caution to patients with clinically significant BOO [see Warnings and Precautions ( 5.2 )] .
Cardiac Electrophysiology The effect of multiple doses of mirabegron 50 mg, 100 mg, and 200 mg (four times the maximum recommended dose) once daily on QTc interval was evaluated in a randomized, placebo- and active-controlled (moxifloxacin 400 mg), four-treatment arm, parallel crossover study in 352 healthy subjects. In a study with demonstrated ability to detect small effects, the upper bound of the one-sided 95% confidence interval for the largest placebo-adjusted, baseline-corrected QTc based on individual correction method (QTcI) was below 10 msec.
For the 50 mg mirabegron dose group (the maximum approved dosage), the mean difference from placebo on QTcI interval at 4 to 5 hours post-dose was 3.7 msec (upper bound of the 95% CI 5.1 msec). For the mirabegron 100 mg and 200 mg dose groups (dosages greater than the maximum approved dose and resulting in substantial multiples of the anticipated maximum blood levels at 50 mg), the mean differences from placebo in QTcI interval at 4 to 5 hours post-dose were 6.1 msec (upper bound of the 95% CI 7.6 msec) and 8.1 msec (upper bound of the 95% CI 9.8 msec), respectively.
At the mirabegron 200 mg dose, in females, the mean effect was 10.4 msec (upper bound of the 95% CI 13.4 msec). In this thorough QT study, mirabegron increased heart rate on ECG in a dose-dependent manner. Maximum mean increases from baseline in heart rate for the 50 mg, 100 mg, and 200 mg dose groups compared to placebo were 6.7 bpm, 11 bpm, and 17 bpm, respectively.
In the clinical efficacy and safety studies, the change from baseline in mean pulse rate for mirabegron 50 mg was approximately 1 bpm. In this thorough QT study, mirabegron also increased blood pressure in a dose-dependent manner (see Effects on Blood Pressure) . Effects on Blood Pressure In a study of 352 healthy subjects assessing the effect of multiple daily doses of 50 mg, 100 mg, and 200 mg (four times the maximum recommended dose) of mirabegron for 10 days on the QTc interval, the maximum mean increase in supine systolic blood pressure (SBP)/diastolic blood pressure (DBP) at the maximum recommended dose of 50 mg was approximately 4.0/1.6 mm Hg greater than placebo [see Warnings and Precautions ( 5.1 )].
The 24-hour average increases in SBP compared to placebo were 3.0, 5.5, and 9.7 mm Hg at mirabegron doses of 50 mg, 100 mg, and 200 mg, respectively. Increases in DBP were also dose-dependent, but were smaller than SBP. In another study in 96 healthy subjects to assess the impact of age on pharmacokinetics of multiple daily doses of 50 mg, 100 mg, 200 mg, and 300 mg (six times the maximum recommended dose) of mirabegron for 10 days, SBP also increased in a dose-dependent manner.
The mean maximum increases in SBP were approximately 2.5, 4.5, 5.5, and 6.5 mm Hg for mirabegron exposures associated with doses of 50 mg, 100 mg, 200 mg and 300 m…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Mirabegron is an agonist of the human beta-3 adrenergic receptor (AR) as demonstrated by in vitro laboratory experiments using the cloned human beta-3 AR. Mirabegron relaxes the detrusor smooth muscle during the storage phase of the urinary bladder fill-void cycle by activation of beta-3 AR which increases bladder capacity. Although mirabegron showed very low intrinsic activity for cloned human beta-1 AR and beta-2 AR, results in humans indicate that beta-1 AR stimulation occurred at a mirabegron dose of 200 mg.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1Mirabegron extended-release tablets Mirabegron extended-release tablets, 25mg are peach colored, oval shaped, biconvex, film-coated tablets debossed with "1159" on one side and plain on other side and are supplied as follows: NDC 70710-1159-3 in bottles of 30 tablets with child-resistant closure NDC 70710-1159-9 in bottles of 90 tablets with child-resistant closure NDC 70710-1159-1 in bottles of 100 tablets with child-resistant closure Mirabegron extended-release tablets, 50mg are yellow colored, oval shaped, biconvex, film-coated tablets debossed with "1160" on one side and plain on other side and are supplied as follows: NDC 70710-1160-3 in bottles of 30 tablets with child-resistant closure NDC 70710-1160-9 in bottles of 90 tablets with child-resistant closure NDC 70710-1160-1 in bottles of 100 tablets with child-resistant closure Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Mirabegron extended-release tablets for oral use is a beta-3 adrenergic agonist. The chemical name is 2-(2-Amonothiazol-4-yl)-N-(4-(2-(2R)-hydroxy-2-phenylethylamino)ethyl)phenyl)acetamide having an empirical formula of C 21 H 24 N 4 O 2 S and a molecular weight of 396.51. The structural formula of mirabegron is: Mirabegron is a white powder.
It is practically insoluble in water. It is soluble in methanol and dimethyl sulfoxide. Each mirabegron extended-release tablet for oral use contains either 25 mg or 50 mg of mirabegron and the following inactive ingredients: polyethylene oxide, polyethylene glycol, magnesium stearate, hypromellose, ferrosoferric oxide, yellow iron oxide, and red iron oxide (25 mg tablet only). structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and/or caregiver to read the FDA-approved patient labeling ( Patient Information ). Increases in Blood Pressure Inform patients and/or their caregivers that mirabegron extended-release tablets may increase blood pressure. Advise patients, especially patients with hypertension, to periodically monitor their blood pressure and report increased measurement to their health care provider [see Warnings and Precautions ( 5.1 )].
Urinary Retention Inform patients and/or their caregivers that mirabegron may cause urinary retention in adult patients with bladder outlet obstruction and in patients taking muscarinic antagonist medications for the treatment of OAB. Advise patients to contact their physician if they experience these effects while taking mirabegron [see Warnings and Precautions ( 5.2 )]. Angioedema Inform patients and/or their caregivers that mirabegron may cause angioedema.
Advise patients and/or their caregivers to promptly discontinue mirabegron and seek medical attention if angioedema associated with the upper airway swelling occurs as this may be life-threatening [see Warnings and Precautions ( 5.3 )]. Drug Interactions Advise patients to report their use of any other prescription or nonprescription medications or dietary supplements because co-administration with mirabegron may require a dose adjustment and/or increased monitoring of these drugs [see Drug Interactions ( 7 )]. Administration Instructions Mirabegron extended-release tablets Advise adult patients to swallow mirabegron whole with water and not to chew, divide, or crush.
Advise adult patients to take mirabegron with or without food. Advise pediatric patients and/or their caregivers to swallow mirabegron extended-release tablets whole with water and not to chew, divide, or crush. Advise pediatric patients to take mirabegron extended-release tablets with food.
Missed Dose Instruct patients and/or their caregivers to take any missed doses as soon as they remember, unless more than 12 hours have passed since the missed dose. If more than 12 hours have passed, the missed dose can be skipped and the next dose should be taken at the usual time. Manufactured by: Zydus Lifesciences Ltd., Matoda, Ahmedabad, India Distributed by: Zydus Pharmaceuticals (USA) Inc.
Pennington, NJ 08534 Revised: 10/2024