
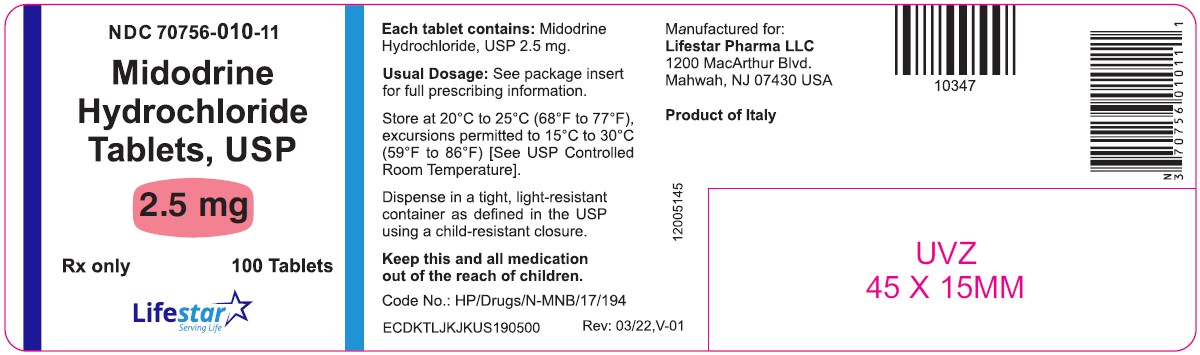
Midodrine Hydrochloride 2.5 mg Tablet, 100-count
Other active recalls for Midodrine Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the alpha-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Midodrine is used to treat orthostatic hypotension (sudden fall in blood pressure that occurs when a person assumes a standing position). Midodrine is in a class of medications called alpha-adrenergic agonists. It works by causing blood vessels to tighten, which increases blood pressure.
Read the full MedlinePlus article ↗- Midodrine raises your blood pressure in all positions — including when you're lying down. If you take it too late in the day and then lie flat to sleep, your blood pressure can sho...
- Why do I have to take this medication so early in the day and not close to bedtime?
- If you feel a severe headache, vision changes, chest discomfort, or just feel like something is off while lying or sitting down, take your blood pressure right away if you can. A v...
- What should I do if my blood pressure feels too high while I'm resting?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.073 | $7.28 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.1904 | $19.04 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2074 | $20.74 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Midodrine Hydrochloride 2.5 mg 00378-1901-01 | Mylan | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 00904-6817-06 | Major | 50 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 49884-0814-01 | Par | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 50268-0561-15 | AvPAK | 50 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 52817-0323-10 | TruPharma, | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 59651-0246-01 | Aurobindo | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 60505-1320-01 | Apotex | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 60687-0387-01 | American | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 62332-0338-31 | Alembic | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 64980-0433-01 | Rising | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine hydrochloride 2.5 mg 68382-0737-01 | Zydus | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 70700-0157-01 | Xiromed, | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mgthis 70756-0010-11 | Lifestar | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 72603-0605-01 | NorthStar | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 72888-0112-01 | Advagen | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 82293-0003-10 | Novugen | 100 tablets | $0.073 | AB | Availability likely | — |
| Midodrine Hydrochloride 2.5 mg 00245-0211-01 | Upsher-Smith | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 00615-8382-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 23155-0969-01 | Avet | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 42291-0560-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 46708-0338-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 51407-0388-90 | Golden | 90 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 63629-2227-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 63629-2348-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Midodrine hydrochloride 2.5 mg 70771-1595-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 71205-0904-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 71335-3037-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 72162-1517-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 72162-1973-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 72162-2560-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 72603-0906-05 | NorthStar | 50 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 72789-0465-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 81469-0139-90 | First | 90 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 85293-0005-01 | Umasuto, | 100 tablets | — | AB | FDA listed | — |
| Midodrine Hydrochloride 2.5 mg 00904-7640-06 | Major | 50 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70756-0010-11 You're viewing this | 100 TABLET in 1 BOTTLE (70756-010-11) | 2023-11-01 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING Warning: Because midodrine hydrochloride can cause marked elevation of supine blood pressure, it should be used in patients whose lives are considerably impaired despite standard clinical care. The indication for use of midodrine hydrochloride in the treatment of symptomatic orthostatic hypotension is based primarily on a change in a surrogate marker of effectiveness, an increase in systolic blood pressure measured one minute after standing, a surrogate marker considered likely to correspond to a clinical benefit.
At present, however, clinical benefits of midodrine hydrochloride, principally improved ability to carry out activities of daily living, have not been verified.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Midodrine hydrochloride tablets are indicated for the treatment of symptomatic orthostatic hypotension (OH). Because midodrine hydrochloride tablets can cause marked elevation of supine blood pressure (BP>200 mmHg systolic), it should be used in patients whose lives are considerably impaired despite standard clinical care, including non-pharmacologic treatment (such as support stockings), fluid expansion, and lifestyle alterations. The indication is based on midodrine hydrochloride tablets's effect on increases in 1-minute standing systolic blood pressure, a surrogate marker considered likely to correspond to a clinical benefit.
At present, however, clinical benefits of midodrine hydrochloride tablets, principally improved ability to perform life activities, have not been established. Further clinical trials are underway to verify and describe the clinical benefits of midodrine hydrochloride tablets. After initiation of treatment, midodrine hydrochloride tablets should be continued only for patients who report significant symptomatic improvement.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The recommended dose of midodrine hydrochloride tablets is 10 mg, 3 times daily. Dosing should take place during the daytime hours when the patient needs to be upright, pursuing the activities of daily living. A suggested dosing schedule of approximately 4-hour intervals is as follows: shortly before, or upon arising in the morning, midday and late afternoon (not later than 6 P.M.).
Doses may be given in 3-hour intervals, if required, to control symptoms, but not more frequently. Single doses as high as 20 mg have been given to patients, but severe and persistent systolic supine hypertension occurs at a high rate (about 45%) at this dose. In order to reduce the potential for supine hypertension during sleep, midodrine hydrochloride tablets should not be given after the evening meal or less than 4 hours before bedtime.
Total daily doses greater than 30 mg have been tolerated by some patients, but their safety and usefulness have not been studied systematically or established. Because of the risk of supine hypertension, midodrine hydrochloride tablets should be continued only in patients who appear to attain symptomatic improvement during initial treatment. The supine and standing blood pressure should be monitored regularly, and the administration of midodrine hydrochloride tablets should be stopped if supine blood pressure increases excessively.
Because desglymidodrine is excreted renally, dosing in patients with abnormal renal function should be cautious; although this has not been systematically studied, it is recommended that treatment of these patients be initiated using 2.5 mg doses. Dosing in children has not been adequately studied. Blood levels of midodrine and desglymidodrine were similar when comparing levels in patients 65 or older vs. younger than 65 and when comparing males vs. females, suggesting dose modifications for these groups are not necessary.
⛔ Contraindications ▾
CONTRAINDICATIONS Midodrine hydrochloride is contraindicated in patients with severe organic heart disease, acute renal disease, urinary retention, pheochromocytoma or thyrotoxicosis. Midodrine hydrochloride should not be used in patients with persistent and excessive supine hypertension.
⚠️ Warnings ▾
WARNINGS Supine Hypertension: The most potentially serious adverse reaction associated with midodrine hydrochloride therapy is marked elevation of supine arterial blood pressure (supine hypertension). Systolic pressure of about 200 mmHg were seen overall in about 13.4% of patients given 10 mg of midodrine hydrochloride. Systolic elevations of this degree were most likely to be observed in patients with relatively elevated pre-treatment systolic blood pressures (mean 170 mmHg).
There is no experience in patients with initial supine systolic pressure above 180 mmHg, as those patients were excluded from the clinical trials. Use of midodrine hydrochloride in such patients is not recommended. Sitting blood pressures were also elevated by midodrine hydrochloride therapy.
It is essential to monitor supine and sitting blood pressures in patients maintained on midodrine hydrochloride. Uncontrolled hypertension increases the risk of cardiovascular events, particularly stroke.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The most frequent adverse reactions seen in controlled trials were supine and sitting hypertension; paresthesia and pruritus, mainly of the scalp; goosebumps; chills; urinary urge; urinary retention and urinary frequency. The frequency of these events in a 3-week placebo-controlled trial is shown in the following table: Adverse Events Placebo n=88 Midodrine n=82 Event # of reports % of patients # of reports % of patients Total # of reports 22 77 Paresthesia 1 4 4.5 15
18.3 Piloerection 0 0 11
13.4 Dysuria 2 0 0 11
13.4Pruritis 3 2 2.3 10
12.2 Supine hypertension 4 0 0 6
7.3 Chills 0 0 4
4.9 Pain 5 0 0 4
4.9Rash 1 1.1 2 2.4 1 Includes hyperesthesia and scalp paresthesia 2 Includes dysuria (1), increased urinary frequency (2), impaired urination (1), urinary retention (5), urinary urgency (2) 3 Includes scalp pruritus 4 Includes patients who experienced an increase in supine hypertension 5 Includes abdominal pain and pain increase Less frequent adverse reactions were headache; feeling of pressure/fullness in the head; vasodilation/flushing face; confusion/thinking abnormality; dry mouth; nervousness/anxiety and rash.
Other adverse reactions that occurred rarely were visual field defect; dizziness; skin hyperesthesia; insomnia; somnolence; erythema multiforme; canker sore; dry skin; dysuria; impaired urination; asthenia; backache; pyrosis; nausea; gastrointestinal distress; flatulence and leg cramps. The most potentially serious adverse reaction associated with midodrine hydrochloride therapy is supine hypertension. The feelings of paresthesia, pruritus, piloerection and chills are pilomotor reactions associated with the action of midodrine on the alpha-adrenergic receptors of the hair follicles.
Feelings of urinary urgency, retention and frequency are associated with the action of midodrine on the alpha-receptors of the bladder neck. To report SUSPECTED ADVERSE REACTIONS, contact Lifestar Pharma LLC at 1-888-995-4337 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🆘 Overdosage ▾
OVERDOSAGE Symptoms of overdose could include hypertension, piloerection (goosebumps), a sensation of coldness and urinary retention. There are 2 reported cases of overdosage with midodrine hydrochloride, both in young males. One patient ingested midodrine hydrochloride drops, 250 mg, experienced systolic blood pressure greater than 200 mmHg, was treated with an IV injection of 20 mg of phentolamine, and was discharged the same night without any complaints.
The other patient ingested 205 mg of midodrine hydrochloride (41 5 mg tablets), and was found lethargic and unable to talk, unresponsive to voice but responsive to painful stimuli, hypertensive and bradycardic. Gastric lavage was performed, and the patient recovered fully by the next day without sequelae. The single doses that would be associated with symptoms of overdosage or would be potentially life-threatening are unknown.
The oral LD 50 is approximately 30 to 50 mg/kg in rats, 675 mg/kg in mice, and 125 to 160 mg/kg in dogs. Desglymidodrine is dialyzable. Recommended general treatment, based on the pharmacology of the drug, includes induced emesis and administration of alpha-sympatholytic drugs (e.g., phentolamine).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Midodrine hydrochloride forms an active metabolite, desglymidodrine, that is an alpha 1 -agonist, and exerts its actions via activation of the alpha-adrenergic receptors of the arteriolar and venous vasculature, producing an increase in vascular tone and elevation of blood pressure. Desglymidodrine does not stimulate cardiac beta-adrenergic receptors. Desglymidodrine diffuses poorly across the blood-brain barrier, and is therefore not associated with effects on the central nervous system.
Administration of midodrine hydrochloride results in a rise in standing, sitting, and supine systolic and diastolic blood pressure in patients with orthostatic hypotension of various etiologies. Standing systolic blood pressure is elevated by approximately 15 to 30 mmHg at 1 hour after a 10 mg dose of midodrine, with some effect persisting for 2 to 3 hours. Midodrine hydrochloride has no clinically significant effect on standing or supine pulse rates in patients with autonomic failure.
Pharmacokinetics Midodrine hydrochloride is a prodrug, i.e., the therapeutic effect of orally administered midodrine is due to the major metabolite desglymidodrine, formed by deglycination of midodrine. After oral administration, midodrine hydrochloride is rapidly absorbed. The plasma levels of the prodrug peak after about half an hour, and decline with a half- life of approximately 25 minutes, while the metabolite reaches peak blood concentrations about 1 to 2 hours after a dose of midodrine and has a half-life of about 3 to 4 hours.
The absolute bioavailability of midodrine (measured as desglymidodrine) is 93%. The bioavailability of desglymidodrine is not affected by food. Approximately the same amount of desglymidodrine is formed after intravenous and oral administration of midodrine.
Neither midodrine nor desglymidodrine is bound to plasma proteins to any significant extent. Metabolism and Excretion Thorough metabolic studies have not been conducted, but it appears that deglycination of midodrine to desglymidodrine takes place in many tissues, and both compounds are metabolized in part by the liver. Neither midodrine nor desglymidodrine is a substrate for monoamine oxidase.
Renal elimination of midodrine is insignificant. The renal clearance of desglymidodrine is of the order of 385 mL/minute, most, about 80%, by active renal secretion. The actual mechanism of active secretion has not been studied, but it is possible that it occurs by the base-secreting pathway responsible for the secretion of several other drugs that are bases (see also Potential for Drug Interactions ).
Clinical Studies Midodrine has been studied in 3 principal controlled trials, one of 3-weeks duration and 2 of 1 to 2 days duration. All studies were randomized, double-blind and parallel-design trials in patients with orthostatic hypotension of any etiology and supine-to-standing fall of systolic blood pressure of at least 15 mmHg accompanied by at least moderate dizziness/lightheadedness. Patients with pre-existing sustained supine hypertension above 180/110 mmHg were routinely excluded.
In a 3-week study in 170 patients, most previously untreated with midodrine, the midodrine-treated patients (10 mg t.i.d., with the last dose not later than 6 P.M.) had significantly higher (by about 20 mmHg) 1-minute standing systolic pressure 1 hour after dosing (blood pressures were not measured at other times) for all 3 weeks. After week 1, midodrine-treated patients had small improvements in dizziness/lightheadedness/unsteadiness scores and global evaluations, but these effects were made difficult to interpret by a high early drop-out rate (about 25% vs 5% on placebo).
Supine and sitting blood pressure rose 16/8 and 20/10 mmHg, respectively, on average. In a 2-day study, after open-label midodrine, known midodrine responders received midodrine 10 mg or placebo at 0, 3, and 6 hours. One-minute standing systolic blood pressures were increased 1 hour after eac…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Midodrine hydrochloride tablets, USP are supplied as 2.5 mg, 5 mg and 10 mg tablets for oral administration. 2.5 mg tablets are white to off white, round tablets, scored on one side and debossed with 'LS' on the other side. NDC 70756-010-11 Bottle of 100 tablets with child-resistant closure.
5 mg tablets are white to off white, round tablets, scored on one side and debossed with 'L49' on the other side. NDC 70756-049-11 Bottle of 100 tablets with child-resistant closure. 10 mg tablets are white to off white, round tablets, scored on one side and debossed with 'L50' on the other side.
NDC 70756-050-11 Bottle of 100 tablets with child-resistant closure. Store at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
Manufactured for: Lifestar Pharma LLC 1200 MacArthur Blvd. Mahwah, NJ 07430 USA Product of Italy Revised: November 2023, V-04
📋 Description ▾
DESCRIPTION Name: Midodrine hydrochloride tablets, USP Dosage Form: 2.5 mg, 5 mg and 10 mg tablets for oral administration Active Ingredient: Midodrine hydrochloride, USP 2.5 mg, 5 mg and 10 mg Inactive Ingredients: colloidal silicon dioxide, magnesium stearate, microcrystalline cellulose, pregelatinized starch (corn), and talc. Pharmacological Classification: Vasopressor/Antihypotensive Chemical Names (USAN: Midodrine Hydrochloride): (1) Acetamide, 2-amino-N-[2-(2,5 dimethoxyphenyl)-2-hydroxyethyl]-monohydrochloride, (±)-; (2) (±)-2-amino-N-(ß-hydroxy-2,5-dimethoxyphenethyl)acetamide monohydrochloride BAN, INN, JAN: Midodrine Structural formula: Molecular formula: C 12 H 18 N 2 O 4 HCl; Molecular Weight: 290.75 Organoleptic Properties: White to off-white crystalline powder Solubility: Water: Soluble pKa: 7.8 (0.3% aqueous solution) pH: 4.0 to