
tizanidine 4 mg Tablet, 1,000-count — NDC 70771-1336-0 (Billing 70771-1336-00)
This is a package of 1,000 tablets of tizanidine 4 mg Tablet from Zydus Lifesciences Limited, marketed since Sep 2018 and currently FDA-listed. It is the main listing for this product, which comes in 4 package sizes.
Other active recalls for Tizanidine (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 313412
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Tizanidine is used to relieve muscle spasms, cramping, and tightness caused by certain conditions including multiple sclerosis (MS, a disease in which the nerves do not function properly and patients may experience weakness, numbness, loss of muscle coordination and problems with vision, speech, and bladder control) and spinal injury. Tizanidine is in a class of medications called skeletal muscle relaxants. It works by slowing action in the brain and nervous system to allow the muscles to relax.
Read the full MedlinePlus article ↗- It helps manage spasticity, meaning stiff, tight muscles that are hard to control. It wears off quickly, so it is meant for the times and activities when you most need relief.
- Food changes how much tizanidine you absorb, and tablets and capsules react differently. The key is to be consistent, either always with food or always without. Tell me or your pre...
- Dry mouth, sleepiness, tiredness or weakness, and dizziness are the most common. Many people find them mild to moderate. Call your doctor if you faint, see things that are not ther...
- It is best to avoid it. Alcohol raises the amount of tizanidine in your blood and adds to drowsiness and side effects. The same goes for other sedating medicines, so check with me...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tizanidine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1130 | $113.00 / 1000 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70771-1336-00 You're viewing this Main listing | 1000 TABLET in 1 BOTTLE | 2018-09-13 | — | Active |
| 70771-1336-03 70771-1336-3 | 30 TABLET in 1 BOTTLE | 2018-09-13 | — | Active |
| 70771-1336-04 70771-1336-4 | 10 BLISTER PACK in 1 CARTON / 10 TABLET in 1 BLISTER PACK | 2018-09-13 | — | Active |
| 70771-1336-08 70771-1336-8 | 150 TABLET in 1 BOTTLE | 2018-09-13 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70771-1336-03?
What NDC number is used to bill for this package of tizanidine 4 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| tizanidine 4 mg 00904-6418-61 | Major | 100 tablets | $0.033 | AB | Availability likely | — |
| Tizanidine 4 mg 16714-0172-01 | NorthStar | 150 tablets | $0.033 | AB | Availability likely | — |
| Tizanidine 4 mg 29300-0169-03 | Unichem | 300 tablets | $0.033 | AB | Availability likely | — |
| Tizanidine 4 mg 50268-0760-15 | AvPAK | 50 tablets | $0.033 | AB | Availability likely | — |
| Tizanidine 4 mg 57664-0503-18 | Sun | 1000 tablets | $0.033 | AB | Availability likely | — |
| Tizanidine 4 mg 68084-0645-01 | American | 100 tablets | $0.033 | AB | Availability likely | — |
| tizanidine 4 mg 00615-8469-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 43063-0455-15 | PD-Rx | 15 tablets | — | AB | FDA listed | — |
| Tizanidine Hydrochloride 4 mg 49999-0347-01 | Quality | 120 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 50090-0840-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 50090-5767-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 50090-6756-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 50090-6757-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 50090-7889-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 51655-0603-20 | Northwind | 20 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 51655-0740-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 55111-0180-03 | Dr. | 300 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 55154-7287-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 60505-0252-01 | Apotex | 100 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 60760-0505-04 | St. | 4 tablets | — | AB | FDA listed | — |
| Tizanidine Hydrochloride 4 mg 61919-0196-30 | TIZANIDINE | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 63187-0009-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 63187-0145-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 63187-0493-15 | Proficient | 15 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 63187-0673-14 | Proficient | 14 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 63629-1673-00 | Bryant | 112 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 63629-2371-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 64980-0659-03 | Rising | 30 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 67046-1444-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 67296-2263-02 | Redpharm | 15 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 67877-0614-05 | Ascend | 500 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 68071-3719-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 68071-4463-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 68071-5268-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 68788-7781-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 68788-8741-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 68788-8802-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Zanaflex 4 mg 70515-0594-15 | Covis | 150 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 70518-0133-00 | REMEDYREPACK | 60 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 70518-1598-01 | REMEDYREPACK | 60 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 70518-3658-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 70518-4181-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| tizanidine 4 mgthis 70771-1336-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 71335-0914-00 | Bryant | 112 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 71335-1016-00 | Bryant | 112 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 71335-2325-00 | Bryant | 112 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 71335-3016-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 71610-0228-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 71610-0776-16 | Aphena | 6000 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 71610-0864-16 | Aphena | 6000 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 72162-1642-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 72189-0602-30 | Direct_rx | 30 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 72578-0097-06 | Viona | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 72789-0325-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 72789-0327-20 | PD-Rx | 20 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 76420-0229-30 | Asclemed | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 76420-0339-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 76420-0866-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 76420-0886-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Tizanidine HCL 4 mg 80425-0022-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Tizanidine HCl 4 mg 80425-0023-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Tizanidine HCL 4 mg 80425-0024-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 80425-0453-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 80425-0454-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 82461-0721-60 | Medcore | 60 tablets | — | AB | FDA listed | — |
| Zanaflex 4 mg 83107-0004-15 | Legacy | 150 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 85509-1180-01 | PHOENIX | 120 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 85534-0030-00 | HAWAII | 10 tablets | — | AB | FDA listed | — |
| tizanidine 4 mg 68788-4159-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Tizanidine 4 mg 84386-0024-77 | Aurobindo | 150 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tizanidine tablets are a central alpha-2-adrenergic agonist indicated for the treatment of spasticity. ( 1 ) Tizanidine tablets are indicated for the treatment of spasticity in adults.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Monitoring of aminotransferase levels is recommended at baseline and 1 month after maximum dose is achieved. ( 2.1 ) Recommended starting dose: 2 mg by mouth every 6 to 8 hours, as needed, up to a maximum of 3 doses in 24 hours ( 2.2 ) Dosage can be increased by 2 mg to 4 mg per dose every 1 to 4 days; maximum total daily dosage is 36 mg ( 2.2 ) Tizanidine pharmacokinetics differs between tablets and capsules, and when taken with or without food. These differences could result in a change in tolerability and control of symptoms.
Consistent administration with respect to food is recommended. If substitution between dosage forms is necessary, take into consideration these pharmacokinetic differences. ( 2.2 , 2.6 , 12.3 ) Patients with renal impairment (creatinine clearance <25 mL/min) or hepatic impairment: use lower individual doses during titration.
If higher doses are required, individual doses rather than dosing frequency should be increased. ( 2.3 , 2.4 ) To discontinue tizanidine tablets, decrease dose slowly to minimize the risk of withdrawal adverse reactions ( 2.5 )
2.1Recommended Evaluation and Testing Before and After Initiating Tizanidine Tablets Monitoring of aminotransferase levels is recommended at baseline and 1 month after maximum dose is achieved [see Warnings and Precautions (5.2) ].
2.2Recommended Dosage The recommended starting dose is 2 mg by mouth every 6 to 8 hours, as needed, to a maximum of three doses in 24 hours. Dosage can be gradually increased every 1 to 4 days by 2 mg to 4 mg at each dose based on clinical response and tolerability. The maximum total daily dosage is 36 mg.
Single doses greater than 16 mg have not been studied. There are pharmacokinetic differences when administering tizanidine between the fed or fasted state [see Clinical Pharmacology (12.3) ]. Tizanidine tablets may be taken with or without food; however, consistent administration with respect to food is recommended to reduce variability in tizanidine plasma exposure .
Because of the short duration of therapeutic effect, treatment with tizanidine tablets should be reserved for those daily activities and times when relief of spasticity is most important.
2.3Recommended Dosage in Patients with Renal Impairment In patients with creatinine clearance < 25 mL/min, use lower individual doses during titration. If higher doses are required, the individual doses rather than dosing frequency should be increased [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
2.4Recommended Dosage in Patients with Hepatic Impairment In patients with hepatic impairment, use lower individual doses during titration. If higher doses are required, individual doses rather than dosing frequency should be increased [see Use in Specific Populations (8.7) and Clinical Pharmacology (12.3) ].
2.5Discontinuation of Tizanidine Tablets When discontinuing tizanidine tablets, particularly in patients who have been receiving high doses for long periods or who may be on concomitant treatment with narcotics, decrease the dosage by 2 mg to 4 mg per day to minimize the risk of withdrawal adverse reactions [see Drug Abuse and Dependence (9.3) ].
2.6Switching Between with/without Food and Different Tizanidine Dosage Forms There are pharmacokinetic differences when: 1) switching between administration of tizanidine tablets with or without food 2) switching between dosage forms if being administered with food . If these situations occur, monitor patients for therapeutic effect or adverse reactions [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 2 mg and 4 mg ( 3 ) Tablets The 2 mg tablets are white to off-white, round, uncoated tablet debossed with '1' & '1' on either side of bisecting score on one side and debossed with '04' on the other side. The 4 mg tablets are white to off-white, round, uncoated tablet with quadrisecting score on one side and debossed with '1105' on the other side.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Concomitant use with strong CYP1A2 inhibitors ( 4 , 7.1 ) Patients with a history of hypersensitivity to tizanidine or the ingredients in tizanidine tablets ( 4 , 5.5 ) Tizanidine tablets are contraindicated in patients: taking strong CYP1A2 inhibitors [see Drug Interactions (7.1) ]. with a history of hypersensitivity to tizanidine or the ingredients in tizanidine tablets. Symptoms have included anaphylaxis and angioedema [see Warnings and Precautions (5.5) ].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: monitor for signs and symptoms of hypotension, in particular in patients receiving concurrent antihypertensives;tizanidine should not be used with other α 2 -adrenergic agonists ( 5.1 , 7.5 ) Risk of liver injury: monitor ALTs; discontinue tizanidine if liver injury occurs ( 5.2 ) Sedation: Tizanidine may interfere with everyday activities; sedative effects of tizanidine, alcohol, and other central nervous system (CNS) depressants are additive ( 5.3 , 7.4 ) Hallucinations: consider discontinuation of tizanidine ( 5.4 )
5.1Hypotension Tizanidine is an α 2 -adrenergic agonist that can produce hypotension [see Adverse Reactions (6.1) and Drug Interactions (7.5) ] . Syncope has been reported in patients treated with tizanidine in the postmarketing setting. The risk of hypotension may be minimized by dose titration; monitoring for signs and symptoms of hypotension prior to dosage increase may minimize the risks associated with hypotension.
In addition, patients moving from a supine to fixed upright position may be at increased risk for hypotension and orthostatic effects. Monitor for hypotension when tizanidine is used in patients receiving concurrent antihypertensive therapy. It is not recommended that tizanidine be used with other α 2 -adrenergic agonists.
Clinically significant hypotension (decreases in both systolic and diastolic pressure) has been reported with concomitant administration of tizanidine and strong CYP1A2 inhibitors [see Clinical Pharmacology (12.3) ]. Therefore, concomitant use of tizanidine with strong CYP1A2 inhibitors is contraindicated [see Contraindications (4) and Drug Interactions (7.1) ] .
5.2Liver Injury Tizanidine may cause hepatocellular liver injury. Liver function test abnormality and hepatotoxicity have been observed with tizanidine [see Adverse Reactions ( 6.1 , 6.2 )]. Monitoring of aminotransferase levels is recommended at baseline and 1 month after maximum dose is achieved, or if hepatic injury is suspected [see Dosage and Administration (2.1) and Use in Specific Populations (8.7 )] .
5.3Sedation Tizanidine can cause sedation, which may interfere with everyday activity. In the multiple dose studies of tizanidine, the prevalence of patients with sedation peaked following the first week of titration and then remained stable for the duration of the maintenance phase of the study [see Adverse Reactions (6.1) ] . The CNS depressant effects of tizanidine with alcohol and other CNS depressants (e.g., benzodiazepines, opioids, tricyclic antidepressants) may be additive [see Drug Interactions (7.4 )] .
Monitor patients who take tizanidine with another CNS depressant for symptoms of excess sedation.
5.4Hallucinosis/Psychotic-Like Symptoms Tizanidine use has been associated with hallucinations. Formed, visual hallucinations or delusions were reported in 5 of 170 patients (3%) in two North American controlled clinical studies. Most of the patients were aware that the events were unreal.
One patient developed psychosis in association with the hallucinations. One patient among these 5 continued to have problems for at least 2 weeks following discontinuation of tizanidine. Hallucinations have also been reported with tizanidine use in the postmarketing setting.
Consider discontinuing tizanidine in patients who develop hallucinations.
5.5Hypersensitivity Reactions Tizanidine can cause anaphylaxis. Signs and symptoms of hypersensitivity, including respiratory compromise, urticaria, and angioedema of the throat and tongue, have been reported. Tizanidine is contraindicated in patients with a history of hypersensitivity reactions to tizanidine [see Contraindications (4)]
5.6Withdrawal Adverse Reactions Tizanidine can cause withdrawal adverse reactions, which include rebound hypertension, tachycardia, and hypertonia. To minimize the risk of these reactions, particularly in patients who have been receiving high doses of tizanidine (20 mg to 28 mg daily) for long periods o… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (greater than 10% of patients taking tizanidine and greater than in patients taking placebo) were dry mouth, somnolence, asthenia, and dizziness. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Zydus Pharmaceuticals USA Inc. at 1-877-993-8779 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. The following clinically significant adverse reactions are described elsewhere in other sections of the prescribing information: Hypotension [ see Warnings and Precautions (5.1) ] Liver Injury [ see Warnings and Precautions (5.2) ] Sedation [ see Warnings and Precautions (5.3) ] Hallucinosis/Psychotic-Like Symptoms [ see Warnings and Precautions (5.4) ] Hypersensitivity Reactions [see Warnings and Precautions (5.5)] Withdrawal Adverse Reactions [see Warnings and Precautions (5.6)]
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in clinical practice. The safety of tizanidine has been evaluated in three double-blind, randomized, placebo-controlled clinical studies [see Clinical Studies (14)] . Two studies were conducted in patients with multiple sclerosis and one in patients with spinal cord injury.
Each study had a 13-week active treatment period which included a 3-week titration phase to the maximum tolerated dose up to 36 mg/day in three divided doses, a 9-week plateau phase where the dose of tizanidine was held constant and a 1-week dose tapering period. In all, 264 patients received tizanidine and 261 patients received placebo. Across the three studies approximately 51% of patients were women, and the median dose during the plateau phase ranged from 20 mg/day to 28 mg/day.
The most common adverse reactions (>10% of patients treated with tizanidine) reported in multiple dose, placebo-controlled clinical studies involving 264 patients with spasticity were dry mouth, somnolence/sedation, asthenia (weakness, fatigue and/or tiredness), and dizziness. Three-quarters of the patients rated the reactions as mild to moderate and one-quarter of the patients rated the reactions as being severe. These adverse reactions appeared to be dose related.
Table 1 lists adverse reactions that were reported in greater than 2% of patients in three multiple dose, placebo-controlled studies who received tizanidine where the frequency in the tizanidine group was greater than the placebo group. Table1:Multiple Dose, Placebo-Controlled Studies—Adverse Reactions Reported for in >2% of Patients Treated with Tizanidine Tablets and Incidence Greater than Placebo Adverse Reaction Placebo N = 261 % Tizanidine Tablet N = 264 % Dry mouth 10 49 Somnolence 10 48 Asthenia * 16 41 Dizziness 4 16 UTI 7 10 Infection 5 6 Constipation 1 4 Liver test abnormality 2 6 Vomiting 0 3 Speech disorder 0 3 Amblyopia (blurred vision) <1 3 Urinary frequency 2 3 Flu syndrome 2 3 Dyskinesia 0 3 Nervousness <1 3 Pharyngitis 1 3 Rhinitis 2 3 * includes weakness, fatigue, and/or tiredness In the single dose, placebo-controlled study involving 142 patients with spasticity due to multiple sclerosis (Study 1) [ see Clinical Studies (14) ] , the patients were specifically asked if they had experienced any of the four most common adverse reactions: dry mouth, somnolence (drowsiness), asthenia (weakness, fatigue and/or tiredness), and dizziness.
In addition, hypotension and bradycardia were observed. The occurrence of these reactions is summarized in Table 2. Other events were, in general, reported at a rate of 2% or less.
Table2:SingleDose , Placebo-ControlledStudy—CommonAdverseReactionsReported Adverse Reaction Placebo N = 48 % Tizanidine Tablet , 8mg , N = 45 % Tizanidine Tablet , 16 mg , N = 49 % Somnolence 31 78 92 Dry mouth 35 76 88 Asthenia * 40 67 78 Dizziness 4 22 45 Hypotension 0 16 33 Bradycardia 0… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Moderate or weak CYP1A2 inhibitors: avoid concomitant use; may cause hypotension, bradycardia, or excessive drowsiness; if concomitant use is necessary and adverse reactions occur, reduce tizanidine dosage or discontinue. ( 7.2 , 12.3 )
7.1Strong CYP1A2 Inhibitors Concomitant use of tizanidine with strong cytochrome P450 1A2 (CYP1A2) inhibitors (e.g., fluvoxamine, ciprofloxacin) is contraindicated. Changes in pharmacokinetics of tizanidine when administered with a strong CYP1A2 inhibitor resulted in significantly decreased blood pressure, increased drowsiness, and increased psychomotor impairment [see Contraindications (4) and Clinical Pharmacology (12.3)].
7.2Moderate or Weak CYP1A2 Inhibitors Concomitant use of tizanidine with moderate or weak CYP1A2 inhibitors (e.g., zileuton, antiarrhythmics [amiodarone, mexiletine, propafenone, and verapamil], cimetidine, famotidine, oral contraceptives, acyclovir, and ticlopidine) should be avoided. If concomitant use is clinically necessary, and adverse reactions such as hypotension, bradycardia, or excessive drowsiness occur, reduce tizanidine dosage or discontinue tizanidine therapy [see Clinical Pharmacology (12.3)].
7.3Oral Contraceptives Concomitant use of tizanidine with oral contraceptives is not recommended. However, if concomitant use is clinically necessary and adverse reactions such as hypotension, bradycardia, or excessive drowsiness occur, reduce or discontinue tizanidine therapy [ see Clinical Pharmacology (12.3) ] .
7.4Alcohol and Other CNS Depressants Alcohol increases the exposure of tizanidine after administration of tizanidine. This was associated with an increase in adverse reactions of tizanidine. Concomitant use of tizanidine with CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) may cause additive CNS depressant effects, including sedation.
Monitor patients who take tizanidine with another CNS depressant for symptoms of excess sedation [ see Clinical Pharmacology (12.3) ] . 7.5 a2-Adrenergic Agonists Concomitant use of tizanidine with other α 2 -adrenergic agonists is not recommended because hypotensive effects may be cumulative [ see Warnings and Precautions (5.1) ] .
7.6Antihypertensive Medications Concomitant use of tizanidine with antihypertensive medications may cause additive hypotensive effects [see Warnings and Precautions (5.1) ]. Monitor patients who take tizanidine with antihypertensive medications for hypotension.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm ( 8.1 ) Geriatric use: Tizanidine should be used with caution in elderly patients because clearance is decreased four-fold ( 8.5 )
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with use of tizanidine in pregnant women. In animal studies, administration of tizanidine during pregnancy resulted in developmental toxicity (embryofetal and postnatal offspring mortality and growth deficits) at doses less than those used clinically, which were not associated with maternal toxicity (see Animal Data ). In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Oral administration of tizanidine (0.3 mg/kg/day to 100 mg/kg/day) to pregnant rats during the period of organogenesis resulted in embryofetal and postnatal offspring mortality and reductions in body weight at doses of 30 mg/kg/day and above. Maternal toxicity was observed at the highest dose tested.
The no-effect dose for embryofetal developmental toxicity in rats (3 mg/kg/day) is similar to the maximum recommended human dose (MRHD) of 36 mg/day on a body surface area (mg/m 2 ) basis. Oral administration of tizanidine (1 mg/kg/day to 100 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in embryofetal and postnatal offspring mortality at all doses. Maternal toxicity was observed at the highest dose tested.
Oral administration of tizanidine (10 mg/kg/day and 30 mg/kg/day) during the perinatal period of pregnancy (2 to 6 days prior to delivery) resulted in increased postnatal offspring mortality at both doses. A no-effect dose for embryofetal developmental toxicity in rabbit was not identified. The lowest dose tested (1 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
In a pre- and postnatal development study in rats, oral administration of tizanidine (3 mg/kg/day to 30 mg/kg/day) resulted in increased postnatal offspring mortality. A no-effect dose for pre- and postnatal developmental toxicity was not identified. The lowest dose tested (3 mg/kg/day) is similar to the MRHD on a mg/m 2 basis, respectively.
8.2Lactation Risk Summary There are no data on the presence of tizanidine in human milk, the effects on the breastfed infant, or the effects on human milk production. Animal studies have reported the presence of tizanidine in the milk of lactating animals. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for tizanidine and any potential adverse effects on the breastfed infant from tizanidine or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential There are no adequate and well-controlled studies in humans on the effect of tizanidine on female or male reproductive potential. Oral administration of tizanidine to male and female rats resulted in adverse effects on fertility [see Nonclinical Toxicology (13.1) ].
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Juvenile Animal Toxicity Data Oral administration of tizanidine (0, 1, 3, and 10 mg/kg/day) to juvenile rats from postnatal day (PND) 7 through PND 70 resulted in delayed sexual maturation in males at all doses, reduced body weight gain, delayed sexual maturation in females, and bilateral corneal crystals at the mid and high doses. Corneal crystals were still observed at the mid and high doses after a three-week recovery period.
Neurobehavioral deficits were observed on a learning and memory task at the high dose. A no-effect dose for adverse effects on postnatal development not identified.
8.5Geriatric Use Tizanidine is known to be substantially excreted by the kidney, and the risk of adverse react… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with use of tizanidine in pregnant women. In animal studies, administration of tizanidine during pregnancy resulted in developmental toxicity (embryofetal and postnatal offspring mortality and growth deficits) at doses less than those used clinically, which were not associated with maternal toxicity (see Animal Data ). In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Oral administration of tizanidine (0.3 mg/kg/day to 100 mg/kg/day) to pregnant rats during the period of organogenesis resulted in embryofetal and postnatal offspring mortality and reductions in body weight at doses of 30 mg/kg/day and above. Maternal toxicity was observed at the highest dose tested.
The no-effect dose for embryofetal developmental toxicity in rats (3 mg/kg/day) is similar to the maximum recommended human dose (MRHD) of 36 mg/day on a body surface area (mg/m 2 ) basis. Oral administration of tizanidine (1 mg/kg/day to 100 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in embryofetal and postnatal offspring mortality at all doses. Maternal toxicity was observed at the highest dose tested.
Oral administration of tizanidine (10 mg/kg/day and 30 mg/kg/day) during the perinatal period of pregnancy (2 to 6 days prior to delivery) resulted in increased postnatal offspring mortality at both doses. A no-effect dose for embryofetal developmental toxicity in rabbit was not identified. The lowest dose tested (1 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
In a pre- and postnatal development study in rats, oral administration of tizanidine (3 mg/kg/day to 30 mg/kg/day) resulted in increased postnatal offspring mortality. A no-effect dose for pre- and postnatal developmental toxicity was not identified. The lowest dose tested (3 mg/kg/day) is similar to the MRHD on a mg/m 2 basis, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Juvenile Animal Toxicity Data Oral administration of tizanidine (0, 1, 3, and 10 mg/kg/day) to juvenile rats from postnatal day (PND) 7 through PND 70 resulted in delayed sexual maturation in males at all doses, reduced body weight gain, delayed sexual maturation in females, and bilateral corneal crystals at the mid and high doses. Corneal crystals were still observed at the mid and high doses after a three-week recovery period.
Neurobehavioral deficits were observed on a learning and memory task at the high dose. A no-effect dose for adverse effects on postnatal development not identified.
🧓 Geriatric Use ▾
8.5Geriatric Use Tizanidine is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. Clinical studies of tizanidine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently than younger subjects.
Pharmacokinetic data showed that younger subjects cleared tizanidine faster than the elderly subjects [see Clinical Pharmacology (12.3) ] . In elderly patients with renal insufficiency (creatinine clearance <25 mL/min), tizanidine clearance is reduced compared to healthy elderly subjects; this would be expected to lead to a longer duration of clinical effect. During titration, the individual doses should be reduced.
If higher doses are required, individual doses rather than dosing frequency should be increased. Monitor elderly patients because they may have an increased risk for adverse reactions associated with tizanidine.
🆘 Overdosage ▾
10 OVERDOSAGE A review of the safety surveillance database revealed cases of intentional and accidental tizanidine overdose. Some of the cases resulted in fatality and many of the intentional overdoses were with multiple drugs including CNS depressants. The clinical manifestations of tizanidine overdose were consistent with its known pharmacology.
In the majority of cases a decrease in sensorium was observed including lethargy, somnolence, confusion and coma. Depressed cardiac function is also observed including most often bradycardia and hypotension. Respiratory depression is another common feature of tizanidine overdose.
Should overdose occur, ensure the adequacy of an airway and monitor cardiovascular and respiratory function. Dialysis is not likely to be an efficient method of removing tizanidine from the body [see Description (11) ] . In general, symptoms resolve within one to three days following discontinuation of tizanidine and administration of appropriate therapy.
Because of the similar mechanism of action, symptoms and management of tizanidine overdose are similar to that following clonidine overdose. For the most recent information concerning the management of overdose, contact a poison control center.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tizanidine is a central alpha-2-adrenergic receptor agonist and presumably reduces spasticity by increasing presynaptic inhibition of motor neurons. The effects of tizanidine are greatest on polysynaptic pathways. The overall effect of these actions is thought to reduce facilitation of spinal motor neurons.
12.2Pharmacodynamics The CNS depressant effects of tizanidine and alcohol are additive [see Warnings and Precautions (5.3) and Drug Interactions (7.4) ] .
12.3Pharmacokinetics Tizanidine has linear pharmacokinetics over the doses studied in clinical development [1 mg (half the recommended dosage) to 20 mg]. Tizanidine capsules and tablets are bioequivalent to each other under fasting conditions, but not under fed conditions (see Absorption, Effect of Food). Absorption Following oral administration, tizanidine is essentially completely absorbed.
The absolute oral bioavailability of tizanidine is approximately 40% (CV = 24%), due to extensive first-pass hepatic metabolism. Effect of Food There are pharmacokinetic differences between tizanidine capsules and tizanidine tablets with respect to administration with food. A single dose of either two 4 mg tablets or two 4 mg capsules was administered under fed and fasting conditions in an open-label, four-period, randomized crossover study in 96 volunteers, of whom 81 were eligible for the statistical analysis.
Pharmacokinetics under fed conditions were different than under fasting conditions and vary by dosage form. Tablets or Capsules -Fasting T max was 1 hours after dosing T ½ was approximately 2 hours. Tablets -Fed Mean C max was increased by approximately 30% Median T max was increased by 25 minutes, to 1 hour and 25 minutes.
Extent of absorption was increased approximately 30% Capsules -Fed Mean C max was decreased by 20% (consequently, approximately 66% the C max for the tablet when administered with food) Median T max was increased 2 to 3 hours Extent of absorption was increased approximately 10% (consequently, approximately 80% of the amount absorbed from the tablet administered with food) Capsule Content Sprinkled on Applesauce Compared to administration of an intact capsule while fasting: C max and AUC was increased 15% to 20% T max was decreased 15 minutes Figure 1: Mean Tizanidine Concentration vs.
Time Profiles For Tizanidine Tablets and Tizanidine Capsules (2 mg x 4 mg) Under Fasted and Fed Conditions Distribution Tizanidine is extensively distributed throughout the body with a mean steady state volume of distribution of
2.4L/kg (CV = 21%) following intravenous administration in healthy adult volunteers. Tizanidine is approximately 30% bound to plasma proteins. Elimination Metabolism Tizanidine has a half-life of approximately 2.5 hours (CV=33%).
Approximately 95% of an administered dose is metabolized. The primary cytochrome P450 isoenzyme involved in tizanidine metabolism is CYP1A2. Tizanidine metabolites are not known to be active; their half-lives range from 20 to 40 hours.
Excretion Following single and multiple oral dosing of 14 C-tizanidine, an average of 60% and 20% of total radioactivity was recovered in the urine and feces, respectively. Specific Populations Geriatric Patients No specific pharmacokinetic study was conducted to investigate age effects. Cross study comparison of pharmacokinetic data following single dose administration of 6 mg tizanidine showed that younger subjects cleared the drug four times faster than the elderly subjects [see Use in Specific Populations (8.5) ] .
Patients with Hepatic Impairment The influence of hepatic impairment on the pharmacokinetics of tizanidine has not been evaluated. Because tizanidine is extensively metabolized in the liver, hepatic impairment would be expected to have significant effects on pharmacokinetics of tizanidine [see Use in Specific Populations (8.7) ]. Patients with Renal Impairment Tizanidine clearance is reduced by more than 50% in elderly patients… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tizanidine is a central alpha-2-adrenergic receptor agonist and presumably reduces spasticity by increasing presynaptic inhibition of motor neurons. The effects of tizanidine are greatest on polysynaptic pathways. The overall effect of these actions is thought to reduce facilitation of spinal motor neurons.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Tizanidine Tablets USP, 2 mg are white to off-white, round, uncoated tablet debossed with '1' & '1' on either side of bisecting score on one side and debossed with '04' on the other side and are supplied as follows: NDC 72578-096-06 in bottles of 30 tablets with child-resistant closure. NDC 72578-096-21 in bottles of 150 tablets with child-resistant closure. NDC 72578-096-10 in bottles of 1000 tablets NDC 72578-096-77 in unit-dose blister cartons of 100 (10 x 10) unit-dose tablets Tizanidine Tablets USP, 4 mg are white to off-white, round, uncoated tablet with quadrisecting score on one side and debossed with '1105' on the other side and are supplied as follows: NDC 72578-097-06 in bottles of 30 tablets with child-resistant closure.
NDC 72578-097-21 in bottles of 150 tablets with child-resistant closure. NDC 72578-097-76 in bottles of 300 tablets with child-resistant closure. NDC 72578-097-10 in bottles of 1000 tablets NDC 72578-097-77 in unit-dose blister cartons of 100 (10 x 10) unit-dose tablets
16.2Storage and Handling Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Dispense in a tight container as defined in the USP with a child-resistant closure.
📋 Description ▾
11 DESCRIPTION Should overdose occur, ensure the adequacy of an airway and monitor cardiovascular and respiratory function. Dialysis is not likely to be an efficient method of removing tizanidine from the body [see Description (11) ] . In general, symptoms resolve within one to three days following discontinuation of tizanidine and administration of appropriate therapy.
Because of the similar mechanism of action, symptoms and management of tizanidine overdose are similar to that following clonidine overdose. For the most recent information concerning the management of overdose, contact a poison control center. Tizanidine Hydrochloride is a white to slightly yellow crystalline powder.
Tizanidine is slightly soluble in water and methanol. Each tizanidine tablet intended for oral administration contains 2.29 mg or 4.58 mg of tizanidine hydrochloride USP, which is equivalent to 2 mg or 4 mg of tizanidine base. In addition, each tablet contains the following inactive ingredients: anhydrous lactose, colloidal silicon dioxide, croscarmellose sodium, microcrystalline cellulose and stearic acid.
Meets USP Dissolution Test 2. figure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Serious Drug Interactions Advise patients they should not take tizanidine if they are taking fluvoxamine or ciprofloxacin because of the increased risk of serious adverse reactions including severe lowering of blood pressure and sedation. Instruct patients to inform their healthcare providers when they start or stop taking any medication because of the risks associated with interaction between tizanidine and other medicines [see Contraindications (4) and Drug Interactions (7) ] . Tizanidine Dosing and Administration Tell patients to take tizanidine exactly as prescribed (consistently either with or without food) and not to switch between tablets and capsules [see Dosage and Administration (2) ] .
Inform patients that they should not take more tizanidine than prescribed because of the risk of adverse events at single doses greater than 8 mg or total daily doses greater than 36 mg. Tell patients that they should not suddenly discontinue tizanidine, because rebound hypertension and tachycardia may occur [see Warnings and Precautions (5.6) ] . Hypotension Warn patients that they may experience hypotension and to be careful when changing from a lying or sitting to a standing position [see Warnings and Precautions (5.1) ] .
Sedation Tell patients that tizanidine may cause them to become sedated or somnolent and they should be careful when performing activities that require alertness, such as driving a vehicle or operating machinery [see Warnings and Precautions (5.3) ] . Tell patients that the sedation may be additive when tizanidine is taken in conjunction with drugs (baclofen, benzodiazepines) or substances (e.g., alcohol) that act as CNS depressants. Remind patients that if they depend on their spasticity to sustain posture and balance in locomotion, or whenever spasticity is utilized to obtain increased function, that tizanidine decreases spasticity and caution should be used.
Hypersensitivity Reactions Inform patients of the signs and symptoms of severe allergic reactions and instruct them to discontinue tizanidine and seek immediate medical care should these signs and symptoms occur [see Warnings and Precautions (5.5) ]. Manufactured by: Zydus Lifesciences Ltd., Matoda, Ahmedabad, India Rev.: 12/24
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential There are no adequate and well-controlled studies in humans on the effect of tizanidine on female or male reproductive potential. Oral administration of tizanidine to male and female rats resulted in adverse effects on fertility [see Nonclinical Toxicology (13.1) ].
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Tizanidine has linear pharmacokinetics over the doses studied in clinical development [1 mg (half the recommended dosage) to 20 mg]. Tizanidine capsules and tablets are bioequivalent to each other under fasting conditions, but not under fed conditions (see Absorption, Effect of Food). Absorption Following oral administration, tizanidine is essentially completely absorbed.
The absolute oral bioavailability of tizanidine is approximately 40% (CV = 24%), due to extensive first-pass hepatic metabolism. Effect of Food There are pharmacokinetic differences between tizanidine capsules and tizanidine tablets with respect to administration with food. A single dose of either two 4 mg tablets or two 4 mg capsules was administered under fed and fasting conditions in an open-label, four-period, randomized crossover study in 96 volunteers, of whom 81 were eligible for the statistical analysis.
Pharmacokinetics under fed conditions were different than under fasting conditions and vary by dosage form. Tablets or Capsules -Fasting T max was 1 hours after dosing T ½ was approximately 2 hours. Tablets -Fed Mean C max was increased by approximately 30% Median T max was increased by 25 minutes, to 1 hour and 25 minutes.
Extent of absorption was increased approximately 30% Capsules -Fed Mean C max was decreased by 20% (consequently, approximately 66% the C max for the tablet when administered with food) Median T max was increased 2 to 3 hours Extent of absorption was increased approximately 10% (consequently, approximately 80% of the amount absorbed from the tablet administered with food) Capsule Content Sprinkled on Applesauce Compared to administration of an intact capsule while fasting: C max and AUC was increased 15% to 20% T max was decreased 15 minutes Figure 1: Mean Tizanidine Concentration vs.
Time Profiles For Tizanidine Tablets and Tizanidine Capsules (2 mg x 4 mg) Under Fasted and Fed Conditions Distribution Tizanidine is extensively distributed throughout the body with a mean steady state volume of distribution of
2.4L/kg (CV = 21%) following intravenous administration in healthy adult volunteers. Tizanidine is approximately 30% bound to plasma proteins. Elimination Metabolism Tizanidine has a half-life of approximately 2.5 hours (CV=33%).
Approximately 95% of an administered dose is metabolized. The primary cytochrome P450 isoenzyme involved in tizanidine metabolism is CYP1A2. Tizanidine metabolites are not known to be active; their half-lives range from 20 to 40 hours.
Excretion Following single and multiple oral dosing of 14 C-tizanidine, an average of 60% and 20% of total radioactivity was recovered in the urine and feces, respectively. Specific Populations Geriatric Patients No specific pharmacokinetic study was conducted to investigate age effects. Cross study comparison of pharmacokinetic data following single dose administration of 6 mg tizanidine showed that younger subjects cleared the drug four times faster than the elderly subjects [see Use in Specific Populations (8.5) ] .
Patients with Hepatic Impairment The influence of hepatic impairment on the pharmacokinetics of tizanidine has not been evaluated. Because tizanidine is extensively metabolized in the liver, hepatic impairment would be expected to have significant effects on pharmacokinetics of tizanidine [see Use in Specific Populations (8.7) ]. Patients with Renal Impairment Tizanidine clearance is reduced by more than 50% in elderly patients with renal insufficiency (creatinine clearance < 25 mL/min) compared to healthy elderly subjects; this would be expected to lead to a longer duration of clinical effect [see Use in Specific Populations (8.6) ].
Gender Effects No specific pharmacokinetic study was conducted to investigate gender effects. Retrospective analysis of pharmacokinetic data following single and multiple dose administration of 4 mg tizanidine, however, showed that gender had no effect on the pharmacokinetics of tizanidine. Drug Intera… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of tizanidine for the treatment of spasticity was demonstrated in two adequate and well-controlled studies in patients with multiple sclerosis or spinal cord injury (Studies 1 and 2). Single-Dose Study in Patients with Multiple Sclerosis with Spasticity In Study 1, 140 patients with spasticity caused by multiple sclerosis were randomized to receive single oral doses of 8 mg or 16 mg of tizanidine, or placebo. Patients and assessors were blinded to treatment assignment and efforts were made to reduce the likelihood that assessors would become aware indirectly of treatment assignment (e.g., they did not provide direct care to patients and were prohibited from asking questions about side effects).
Response was assessed by physical examination; muscle tone was rated on a 5-point scale (Ashworth score) as follows: 0 = normal muscle tone 1 = slight spastic catch 2 = more marked muscle resistance 3 = considerable increase in tone, making passive movement difficult 4 = a muscle immobilized by spasticity Spasm counts were also collected. Assessments were made at 1, 2, 3 and 6 hours after treatment. A statistically significant reduction of the Ashworth score for tizanidine compared to placebo was detected at 1, 2, and 3 hours after treatment.
Figure 2 below shows a comparison of the mean change in muscle tone from baseline as measured by the Ashworth scale. The greatest reduction in muscle tone was 1 to 2 hours after treatment. By 6 hours after treatment, muscle tone in the 8 mg and 16 mg tizanidine groups was indistinguishable from muscle tone in patients who received placebo.
Within a given patient, improvement in muscle tone was correlated with plasma concentration. Plasma concentrations were variable from patient to patient at a given dose. Although 16 mg produced a larger effect, adverse reactions including hypotension were more common and more severe than in the 8 mg group.
There were no differences in the number of spasms occurring in each group. Figure 2: Single Dose Study—Mean Change in Muscle Tone from Baseline as Measured by the Ashworth Scale ± 95% Confidence Interval (A Negative Ashworth Score Signifies an Improvement in Muscle Tone from Baseline) Seven-Week Study in Patients with Spinal Cord Injury with Spasticity In a 7-week study (Study 2), 118 patients with spasticity secondary to spinal cord injury were randomized to either placebo or tizanidine. Steps similar to those taken in the first study were employed to ensure the integrity of blinding.
Patients were titrated over 3 weeks up to a maximum tolerated dose or 36 mg daily given in three unequal doses (e.g., 10 mg given in the morning and afternoon and 16 mg given at night). Patients were then maintained on their maximally tolerated dose for 4 additional weeks (i.e., maintenance phase). Throughout the maintenance phase, muscle tone was assessed on the Ashworth scale within a period of 2.5 hours following either the morning or afternoon dose.
The number of daytime spasms was recorded daily by patients. At endpoint (the protocol-specified time of outcome assessment), there was a statistically significant reduction in muscle tone and frequency of spasms in the tizanidine treated group compared to placebo. The reduction in muscle tone was not associated with a reduction in muscle strength (a desirable outcome), but also did not lead to any consistent advantage of tizanidine treated patients on measures of activities of daily living.
Figure 3 below shows a comparison of the mean change in muscle tone from baseline as measured by the Ashworth scale. Figure 3: Seven Week Study-Mean Change in Muscle Tone 0.5 to
2.5Hours After Dosing as Measured by the Ashworth Scale ± 95% Confidence Interval (A Negative Ashworth Score Signifies an Improvement in Muscle Tone from Baseline) figure figure
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Tizanidine tablets contains tizanidine, which is not a controlled substance.
9.2Abuse Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects. Abuse potential was not evaluated in human studies. Rats were able to distinguish tizanidine from saline in a standard discrimination paradigm, after training, but failed to generalize the effects of morphine, cocaine, diazepam, or phenobarbital to tizanidine.
9.3Dependence Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Tizanidine is closely related to clonidine, which is often abused in combination with narcotics and is known to cause symptoms of rebound upon abrupt withdrawal. Cases of rebound symptoms on sudden withdrawal of tizanidine have been reported.
The case reports suggest that these patients were also misusing narcotics. Withdrawal symptoms included hypertension, tachycardia, hypertonia, tremor, and anxiety. Withdrawal symptoms are more likely to occur in cases where high doses are used, especially for prolonged periods, or with concomitant use of narcotics.
If therapy needs to be discontinued, the dose should be decreased slowly to minimize the risk of withdrawal symptoms [see Dosage and Administration (2.5 )]. Monkeys were shown to self-administer tizanidine in a dose-dependent manner, and abrupt cessation of tizanidine produced transient signs of withdrawal at doses > 35 times the maximum recommended human dose on a mg/m 2 basis. These transient withdrawal signs (increased locomotion, body twitching, and aversive behavior toward the observer) were not reversed by naloxone administration.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Tizanidine was administered to mice for 78 weeks at oral doses up to 16 mg/kg/day, which is 2 times the maximum recommended human dose (MRHD) of 36 mg/day on a body surface area (mg/m 2 ) basis. Tizanidine was administered to rats for 104 weeks at oral doses up to 9 mg/kg/day, which is 2.5 times the MRHD on a mg/m 2 basis. There was no increase in tumors in either species.
Mutagenesis Tizanidine was negative in in vitro (bacterial reverse mutation [Ames], mammalian gene mutation, and chromosomal aberration test in mammalian cells) and in vivo (bone marrow micronucleus, and cytogenetics) assay. Impairment of Fertility Oral administration of tizanidine to rats prior to and during mating and continuing during early pregnancy in females resulted in reduced fertility in male and female rats at doses of 30 mg/kg/day and 10 mg/kg/day, respectively. No effect on fertility was observed at doses of 10 (male) and 3 (female) mg/kg/day, which are approximately 3 times and similar to the MRHD, respectively, on a mg/m 2 basis.
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Indications and Usage ( 1 ) 11/2024 Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.4 , 2.5 , 2.6 ) 11/2024 Contraindications ( 4 ) 11/2024 Warnings and Precautions ( 5.1 , 5.2 , 5.4 , 5.5 ) 11/2024
📄 Package Label / Principal Display Panel ▾
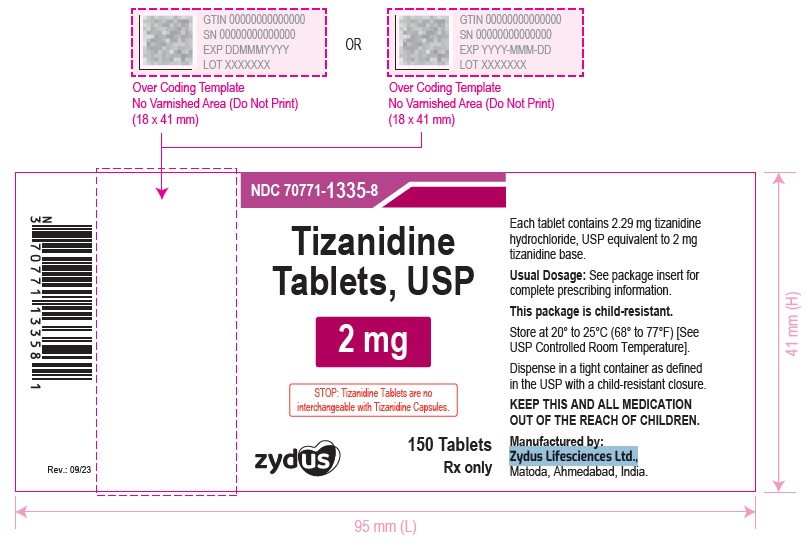
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 70771-1335-8 in bottles of 150 tablets Tizanidine Tablets USP, 2 mg 150 Tablets Rx only NDC 70771-1336-8 in bottles of 150 tablets Tizanidine Tablets USP, 4 mg 150 Tablets Rx only figure figure
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |