
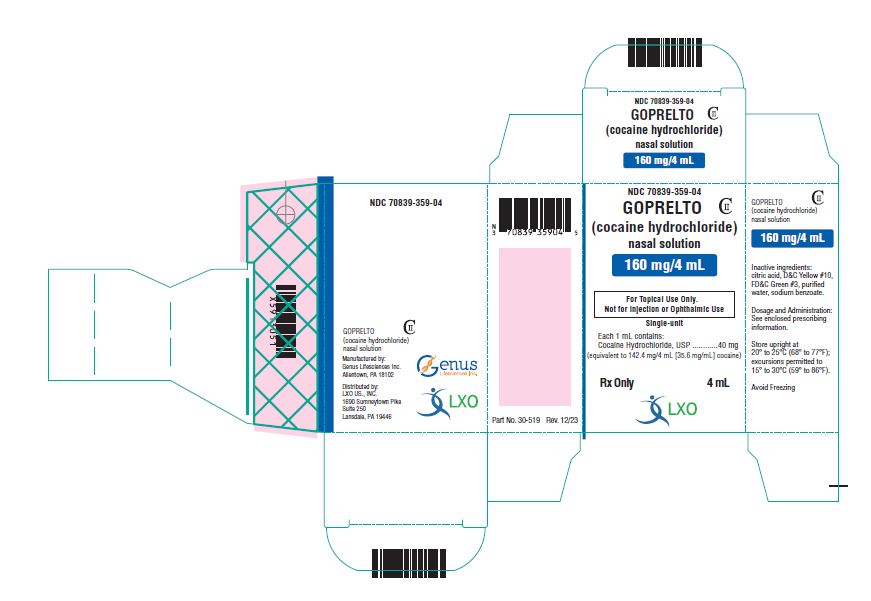
Goprelto cocaine hydrochloride 40 mg/mL Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Esters of benzoic acid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cocaine Hydrochloride (prescription drug) — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 3P3ONR6O1S
A synthetic green dye approved by the FDA for use in medicines and foods. It serves as a colorant to make the pill or liquid visually distinctive and help with product identification.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Goprelto 40 mg/mLthis 70839-0359-04 | LXO | 1 bottle | — | — | FDA listed | — |
| Cocaine Hydrochloride 40 mg/mL 70839-0362-04 | LXO | 1 bottle | — | — | FDA listed | — |
| Numbrino 40 mg/mL 81665-0300-02 | OMNIVIUM | 1 bottle | — | — | FDA listed | — |
| cocaine hydrochloride nasal 40 mg/mL 81665-0301-02 | OMNIVIUM | 1 bottle | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10016407 ↗ | Method of use | U-2329 | Feb 7, 2037 |
| US 9867815 ↗ | Method of use | U-2225 | Feb 7, 2037 |
| US 9867815 ↗ | Method of use | U-2226 | Feb 7, 2037 |
| US 9867815 ↗ | Method of use | U-2227 | Feb 7, 2037 |
| US 10413505 ↗ | Method of use | U-2479 | Feb 7, 2037 |
| US 10420760 ↗ | Method of use | U-2478 | Feb 7, 2037 |
| US 10149843 ↗ | Method of use | U-2479 | Feb 7, 2037 |
| US 10149843 ↗ | Method of use | U-2478 | Feb 7, 2037 |
| US 10933060 ↗ | Method of use | U-3014 | Feb 7, 2037 |
| US 10973811 ↗ | Method of use | U-2226 | Feb 7, 2037 |
| US 10987347 ↗ | Method of use | U-2225 | Feb 7, 2037 |
| US 10894012 ↗ | Method of use | U-3014 | Feb 7, 2037 |
| US 10857095 ↗ | Method of use | U-3014 | Feb 7, 2037 |
| US 10231961 ↗ | Drug product | — | Feb 7, 2037 |
| US 11040032 ↗ | Drug product | — | Feb 7, 2037 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70839-0359-04 You're viewing this | 1 BOTTLE, GLASS in 1 CARTON (70839-359-04) / 4 mL in 1 BOTTLE, GLASS | 2024-02-09 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE AND DEPENDENCE CNS stimulants, including cocaine hydrochloride, have a high potential for abuse and dependence [see Warning and Precautions (5.1) . ] WARNING: ABUSE AND DEPENDENCE See full prescribing information for complete boxed warning. CNS stimulants, including cocaine hydrochloride, have a high potential for abuse and dependence. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE GOPRELTO (cocaine hydrochloride) nasal solution is indicated for the induction of local anesthesia of the mucous membranes when performing diagnostic procedures and surgeries on or through the nasal cavities in adults. GOPRELTO (cocaine hydrochloride) nasal solution is an ester local anesthetic indicated for the induction of local anesthesia of the mucous membranes when performing diagnostic procedures and surgeries on or through the nasal cavities in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • For intranasal use only. ( 2.1 ) • Recommended dose: two pledgets, each containing 40 mg of cocaine hydrochloride,applied to each nasal cavity. ( 2.2 ) • Do not apply to damaged nasal mucosa.
( 2.1 ) • Preparation and Application: – In a small container, soak four pledgets in the full contents (4 mL) of one bottle of GOPRELTO until the solution is fully absorbed. Each pledget absorbs 1 mL of solution, equivalent to 40 mg cocaine hydrochloride. ( 2.2 , 2.3 ) – Following soaking, place two pledgets in each nasal cavity against the septum.
( 2.3 ) – Leave pledgets in p lace for up to 20 minutes. ( 2.3 )
2.1Important Dosage and Administration Instructions • GOPRELTO is for intranasal use only. • Do not apply GOPRELTO to damaged nasal mucosa.
2.2Dosing Recommendation for Adults The recommended dose of GOPRELTO is two soaked cottonoid pledgets placed in each nasal cavity, equivalent to 40 mg cocaine hydrochloride per pledget, for a total dose of 160 mg for four pledgets. The total dose for any one procedure or surgery should not exceed 160 mg, or 3 mg/kg, cocaine hydrochloride. The recommended size of cottonoid pledgets for use with GOPRELTO measure 1.3 cm x 4 cm (sold separately).
2.3Preparation and Administration of GOPRELTO Pledgets Pour the full contents of one 4 mL (160 mg) bottle of GOPRELTO into a small container. Soak four cottonoid pledgets until the solution is fully absorbed. Following soaking, place two pledgets in each nasal cavity against the septum.
Leave pledgets in place for up to twenty minutes. Remove pledgets and continue with the procedure.Discard pledgets and dispose of any unused portion of solution in accordance with institutional procedures for CII products.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS GOPRELTO (cocaine hydrochloride) nasal solution is provided as a 4% solution, 160 mg/4 mL (40 mg/mL), equivalent to 142.4 mg/4 mL (35.6 mg/mL) cocaine, and is a clear, greencolored solution in a single-unit bottle. Nasal solution: 160 mg/4 mL (40 mg/mL or 4%) cocaine hydrochloride, equivalent to 142.4 mg/4 mL (35.6 mg/mL) cocaine, in a single-unit bottle. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS GOPRELTO is contraindicated in patients with a known history of hypersensitivity to cocaine hydrochloride, other ester-based anesthetics, or any other component of the product. Known hypersensitivity to cocaine hydrochloride, other ester-based anesthetics, or any other component of GOPRELTO. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Seizures : GOPRELTO may lower the convulsive threshold. Monitor patients for development of seizures. ( 5.2 ) • Blood Pressure and Heart Rate Increases : Monitor vital signs, including heart rate and rhythm, in patients after receiving GOPRELTO.
Avoid use of GOPRELTO in patients with a recent or active history of uncontrolled hypertension, unstable angina, myocardial infarction, coronary artery disease, or congestive heart failure. ( 5.3 )
5.1Potential for Abuse and Dependence Central nervous system (CNS) stimulants, including cocaine hydrochloride, have a high potential for abuse and dependence [ see Drug Abuse and Dependence ( 9.2 , 9.3 )].
5.2Seizures It has been reported in the literature that cocaine hydrochloride may lower the convulsive threshold. The risk may be higher in patients with a history of seizures or in patients with prior electroencephalogram (EEG) abnormalities without seizures, but has been reported in patients with no prior history or EEG evidence of seizures. Monitor patients for development of seizures.
5.3Blood Pressure and Heart Rate Increases As reported in the literature, cocaine hydrochloride causes an increase in observed blood pressure and heart rate. In the Phase 3 clinical study with GOPRELTO, increases in blood pressure and heart rate were observed for 60 minutes or longer following pledget removal. Monitor for vital sign changes, including heart rate and rhythm, after administration of GOPRELTO.
Avoid use of GOPRELTO in patients with a recent or active history of uncontrolled hypertension, unstable angina, myocardial infarction, coronary artery disease, or congestive heart failure. Avoid use of additional vasoconstrictor agents such as epinephrine or phenylephrine with GOPRELTO. If concomitant use is unavoidable, prolonged vital sign and ECG monitoring may be required [see Drug Interactions ( 7 )].
5.4Toxicology Screening The cocaine hydrochloride in GOPRELTO may be detected in plasma for up to one week after administration. Cocaine hydrochloride and its metabolites may be detected in urine toxicology screening for longer than one week after administration.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (>0.5%) occurring in patients treated with GOPRELTO (cocaine hydrochloride) nasal solution 4% were headache and epistaxis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact LXO US., INC. at 1-844-800-8007 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. GOPRELTO has been evaluated in four Phase 1 studies and one Phase 3 study, which included 647 adult subjects who received a single topical intranasal 160 mg dose (four pledgets), of GOPRELTO. The randomized, double-blind, controlled Phase 3 study was conducted in adult patients undergoing diagnostic procedures and surgeries on or through the mucous membranes of the nasal cavities, of which 278 received GOPRELTO (4% solution), 275 received cocaine hydrochloride solution 8%, and 95 received placebo.
Safety was evaluated for up to 7 days after dosing. The most commonly reported adverse reactions (>1 patient) to occur in the Phase 3 study with GOPRELTO (4% solution) were headache and epistaxis. Two adverse reactions of headache were severe (Table 1).
No premature discontinuations due to an adverse event, serious adverse events, or deaths were reported in the Phase 3 clinical study. Table 1: Common Adverse Reactions with GOPRELTO in >1 Patient System Organ Class / Preferred Term GOPRELTO 4% (N=278) Cocaine Hydrochloride Solution 8% (N=275) Placebo (N=95) Nervous System Disorders Headache 7 (3%) 4 (2%) 1 (1%) Respiratory, Thoracic, and Mediastinal Disorders Epistaxis 3 (1%) 2 (1%) 0 Psychiatric Disorders Anxiety 0 2 (1%) 0
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Disulfiram : Increases plasma cocaine exposure. Avoid using GOPRELTO in patients taking disulfiram. ( 7 ) • Epinephrine, Phenylephrine : There have been reports of myocardial ischemia, myocardial infarction, and ventricular arrhythmias with concomitant use during nasal surgery.
Avoid use of additional vasoconstrictor agents with GOPRELTO. If concomitant use is unavoidable, prolonged vital sign and ECG monitoring may be required. ( 5.3 , 7 )
7.1Disulfiram Published literature reported that disulfiram treatment increased plasma cocaine exposure, including both AUC and C max , by several fold after acute intranasal cocaine administration. Other literature reported that co-administration of disulfiram increased AUC of plasma cocaine by several fold after intravenous cocaine administration [see Clinical Pharmacology ( 12.3 )]. Avoid using GOPRELTO in patients taking disulfiram.
Consider using other local anesthetic agents.
7.2Epinephrine, Phenylephrine There are reports in the published literature of myocardial ischemia, myocardial infarction, and ventricular arrhythmias after concomitant administration of topical intranasal cocaine with epinephrine and phenylephrine during nasal and sinus surgery. Avoid use of additional vasoconstrictor agents such as epinephrine and phenylephrine with GOPRELTO during nasal and sinus surgery. If concomitant use is unavoidable, prolonged vital sign and ECG monitoring may be required [see Warnings and Precautions ( 5.3 ) ].
7.3Inhibitors of plasma cholinesterase (pseudocholinesterase) Cocaine has been described in literature to be primarily metabolized and inactivated by nonenzymatic ester hydrolysis and hepatic carboxylesterase, and also by plasma cholinesterase, hepatic carboxylesterase, and CYP3A4 [see Clinical Pharmacology ( 12.3 )]. The pharmacokinetics of GOPRELTO in patients with reduced plasma cholinesterase activity has not been studied. Plasma cholinesterase activity may be decreased by chronic administration of certain monoamine oxidase inhibitors, oral contraceptives, or glucocorticoids.
It may also be diminished by administration of irreversible plasma cholinesterase inhibitors such as echothiophate, organophosphate insecticides, and certain antineoplastic agents. Patients with reduced plasma cholinesterase (pseudocholinesterase) activity may have reduced clearance and increased exposure of plasma cocaine after administration of GOPRELTO. Since cocaine is metabolized by multiple enzymes, the effect of reduced plasma cholinesterase activity on cocaine exposure may be limited.
No dosage adjustment of GOPRELTO is needed in patients with reduced plasma cholinesterase. Monitor patients with reduced plasma cholinesterase activity for adverse reactions such as headache, epistaxis, and clinically-relevant increases in heart rate or blood pressure.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy : May cause fetal harm. ( 8.1 ) • Lactation : Avoid breastfeeding for 48 hours after treatment. ( 8.2 ) • Hepatic Impairment : Monitor for adverse reactions such as headache, epistaxis, and clinically- relevant increases in heart rate or blood pressure. Do not administer a second dose within 24 hours of the first dose. ( 8.7 )
8.1Pregnancy Risk Summary In animal studies conducted in accordance with good laboratory practices, malformations including vertebral and rib abnormalities were reported when pregnant rabbits were treated with 16 mg/kg cocaine hydrochloride during organogenesis (8 times the adult human exposure following administration of pledgets containing 160 mg of cocaine) and increased pup mortality was noted when pregnant rats were exposed to cocaine hydrochloride during pregnancy at 47 times the adult human AUC exposures. Published rodent studies testing high exposures to cocaine during organogenesis report various malformations at 17 to 34 times the adult human AUC exposures following administration of pledgets containing 160 mg of cocaine.
Data Human Data There are no available data on the use of intranasal cocaine hydrochloride solution in pregnant women to inform a drug-associated risk adverse developmental outcomes. There are published data describing adverse developmental outcomes in women with chronic cocaine abuse during pregnancy. The published case-control and observational studies examining the effect of in utero cocaine exposure on fetal growth parameters, after controlling for confounding variables, found exposure was associated with reduced fetal growth compared with non-drugabuse populations.
Published data from a large number of studies of women with chronic cocaine abuse during pregnancy are inconsistent in their findings with regard to other developmental outcomes. Prospective studies controlling for polydrug use (marijuana, alcohol, tobacco) and lifestyle factors, have not demonstrated any association between cocaine abuse and specific major or minor fetal anomalies or other forms of fetal harm (premature birth, stillbirth, miscarriage, low birth weight, reduced head circumference, or placental abruption).
The applicability of the findings from these studies of chronic abuse in pregnancy to a single topical exposure is limited. Animal Data No clear evidence of fetal malformations was noted in a study where pregnant rats were treated subcutaneously with up to 30 mg/kg cocaine hydrochloride (48 times the human adult exposure based on AUC following administration of pledgets containing 160 mg of cocaine) from Gestation Day 7 through 17 in the absence of overt maternal rat toxicity. However, a single high-dose fetus was reported with both meningoencephalocele and anophthalmia (unilateral).
Malformations, including vertebral and rib anomalies, were observed when pregnant rabbits were treated subcutaneously with 16 mg/kg cocaine hydrochloride (8 times the human adult exposure based on AUC exposures following administration of pledgets containing 160 mg of cocaine) from Gestation Day 7 through 20. This dose level was associated with evidence of maternal toxicity (convulsions, decreased body weight gain). No adverse effects were noted in animals treated with 8 mg/kg (1.5 times the adult human AUC following administration of pledgets containing 160 mg of cocaine).
An increased incidence of pup mortality between Postnatal Day (PND) 0 to PND 4 and decreased pup body weights from PND 1 to PND 21 were noted when pregnant rats were treated from GD 6 through Lactation Day 20 with 20 mg/kg cocaine hydrochloride (47 times the adult human AUC following administration of pledgets containing 160 mg of cocaine) in the absence of overt maternal toxicity. There was no adverse effect on pre- or postnatal development at 6 mg/kg (7 times the human adult AUC exposure following administration of pledgets containing 160 mg cocaine).
Published studies in pregnant mice suggest that h…
🆘 Overdosage ▾
10 OVERDOSAGE No cases of overdose with GOPRELTO were reported in clinical trials. Blood pressure and heart rate increases were greater with cocaine hydrochloride solution 8% than with GOPRELTO. In the case of an overdose, consult with a certified poison control center (1-800-222-1222) for up-to-date guidance and advice for treatment of overdosage.
Individual patient response to cocaine varies widely. Toxic symptoms may occur idiosyncratically at low doses. Manifestations of cocaine overdose associated with illicit use of cocaine reported in literature and based on reports in FDA’s Adverse Events Reporting System (AERS) database include death, cardio-respiratory arrest, cardiac arrest, respiratory arrest, tachycardia, myocardial infarction, agitation, aggression, restlessness, tremor, hyperreflexia, rapid respiration, confusion, assaultiveness, hallucinations, panic states, hyperpyrexia, and rhabdomyolysis.
Fatigue and depression usually follow the central nervous system stimulation. Other reactions include arrhythmias, hypertension or hypotension, circulatory collapse, nausea, vomiting, diarrhea, and abdominal cramps. Fatal poisoning is usually preceded by convulsions and coma.
Because cocaine is significantly distributed to tissues and rapidly metabolized, dialysis and hemoperfusion are not effective. Acidification of the urine does not significantly enhance cocaine elimination.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Cocaine hydrochloride is a local anesthetic of the ester type. Cocaine hydrochloride prevents conduction in nerve fibers by reversibly blocking sodium channels and preventing the transient rise in sodium conductance necessary for generation of an action potential.
12.2Pharmacodynamics Cardiac Electrophysiology The effect of GOPRELTO (cocaine hydrochloride) nasal solution on the QTc interval was evaluated in a randomized, positive- and placebo-controlled four-period crossover thorough QTc study in 24 healthy subjects. No clinically relevant QTc prolongation was observed at the highest clinically relevant concentrations with a single therapeutic dose.
12.3Pharmacokinetics Absorption The pharmacokinetics of GOPRELTO (cocaine hydrochloride) nasal solution have been assessed in 74 healthy adult subjects across 4 studies. Following intranasal application of two 40 mg pledgets applied to each nasal cavity (160 mg cocaine hydrochloride total dose) for 20 minutes, the geometric mean (SD) cocaine C max was 43.2 (1.73) ng/mL. The median (range) time to peak plasma concentration (t max ) was 0.42 (0.25 – 1.75) hours after pledget application.
Distribution Cocaine has been described in literature as approximately 84 – 92% bound to human plasma proteins, binding primarily to alpha-1-acid glycoprotein (AAG) and albumin. In studies with GOPRELTO, the apparent volume of distribution (Vd/F) of cocaine after intranasal administration is 3,877 ± 1,266 L. Elimination Metabolism Cocaine has been described in literature to be primarily metabolized and inactivated by nonenzymatic ester hydrolysis and hepatic carboxylesterase 1 to form benzoylecgonine (BE), and by plasma cholinesterase and hepatic carboxylesterase 2 to form ecgonine methyl ester (EME).
In human liver microsomes, cocaine undergoes CYP3A4 mediated N-demethylation to produce a minor metabolite, norcocaine, which is pharmacologically active. Excretion Cocaine has been described in literature to be primarily eliminated by biotransformation to inactive metabolites, BE and EME. Less than 10% of the administered dose is excreted unchanged in the urine.
BE and EME are both predominantly excreted by the kidneys. In studies with GOPRELTO, 0-32 hour urinary recoveries of cocaine, BE, and EME as a percentage of dose were approximately 0.1%, 2.0%, and 1.0%, respectively. The mean elimination half-life of cocaine was 1.0 to 1.7 hours; with longer plasma sampling (32 hours) and a highly sensitive assay, mean half-life values of 5.0 to 8.0 hours were observed at very low plasma concentrations.
The apparent clearance of cocaine after intranasal administration of GOPRELTO (CL/F) is 3096 ± 1276 L/h. Specific Populations In studies with GOPRELTO, cocaine exposure (i.e., C max , AUC last , and AUC inf ) was slightly higher in females than males whereas tmax and half-life were similar in males and females. GOPRELTO pharmacokinetics are not affected by age or weight.
Renal Impairment In a pharmacokinetic study of GOPRELTO in subjects with normal and severe renal impairment (eGFR 15-29 mL/min/1.73 m2), mean AUC and Cmax were slightly higher in subjects with severe renal impairment compared to those with normal renal function and clearance was slightly lower [see Use in Specific Populations ( 8.6 )]. Hepatic Impairment In a pharmacokinetic study of GOPRELTO in subjects with normal, Child-Pugh Class B, and Child-Pugh Grade C hepatic impairment, there was a minimal effect of hepatic impairment on cocaine C max .
In moderately impaired subjects (n=9) there was a higher than two-fold increase in AUC (79.2 ng.h/mL in normal subjects to 225 ng.h/mL in Child-Pugh Grade B subjects) and the clearance was reduced by more than half (1735 L/h in normal 629 L/h in Child-Pugh Grade B subjects). In severely impaired subjects (n=3) there was an eighty percent increase in AUC (79.2 ng.h/mL in normal subjects to 142 ng.h/mL in Child-Pugh Grade C subjects) and the clearance was…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING GOPRELTO (cocaine hydrochloride) nasal solution is a clear, green colored liquid available as one dosage strength: 160 mg/4 mL (40 mg/mL or 4%) cocaine hydrochloride, equivalent to 142.4 mg/4 mL (35.6 mg/mL) cocaine NDC # 70839-359-04: Single-unit 4 mL bottle Store upright at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [ see USP, Controlled Room Temperature (CRT )]. Avoid freezing.
📋 Description ▾
11 DESCRIPTION GOPRELTO (cocaine hydrochloride) nasal solution for intranasal use contains a 4% solution, 160 mg/4 mL (40 mg/mL), equivalent to 142.4 mg/4 mL (35.6 mg/mL) cocaine, an ester local anesthetic. The chemical name for cocaine hydrochloride is (1R,2R,3S,5S) methyl 3-(benzoyloxy)-8- methyl-8-azabicyclo[3.2.1]octane-2-carboxylate hydrochloride. The molecular formula is C17H21NO4•HCl and the molecular weight is 339.81.
The structural formula is: Inactive ingredients are anhydrous citric acid, D&C Yellow No. 10, FD&C Green No. 3, sodium benzoate, and purified water. structure