
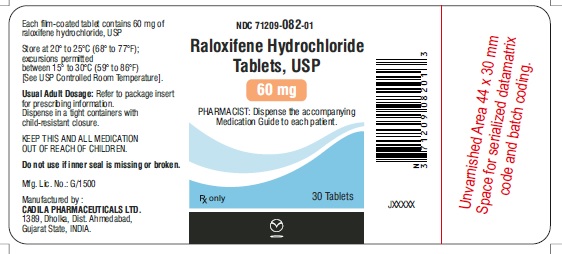
Raloxifene hydrochloride 60 mg Tablet, Coated, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Estrogen Agonist/Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Raloxifene is used to prevent and treat osteoporosis (condition in which the bones become thin and weak and break easily) in postmenopausal (women who have experienced a change of life; end of menstrual periods) women. Raloxifene is also used to decrease the risk of developing invasive breast cancer (breast cancer that has spread outside of the milk ducts or lobules into the surrounding breast tissue) in postmenopausal women who are at high risk of developing this type of cancer or who have osteoporosis. Raloxifene cannot be used to treat invasive breast cancer or to prevent invasive breast ca...
Read the full MedlinePlus article ↗- It's related to estrogen but it's not the same thing. Raloxifene is what's called a SERM — it selectively acts like estrogen in your bones, which helps slow bone loss and keep your...
- What is raloxifene actually doing for me — is it like taking estrogen?
- You have a lot of flexibility here. Raloxifene can be taken at any time of day — morning, afternoon, or evening — whatever fits your routine best. You don't need to take it with fo...
- Can I take this with or without food, and does the time of day matter?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.4465 | $446.50 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Raloxifene Hydrochloride 60 mg 00093-7290-01 | Teva | 100 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene hydrochloride 60 mg 00904-6902-04 | Major | 1 tablet | $0.236 | AB | Availability likely | — |
| Raloxifene Hydrochloride 60 mg 16714-0213-01 | NorthStar | 30 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene hydrochloride 60 mg 43598-0505-01 | Dr.Reddys | 100 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene Hydrochloride 60 mg 50268-0694-15 | AvPAK | 1 tablet | $0.236 | AB | Availability likely | — |
| Raloxifene Hydrochloride 60 mg 60687-0266-21 | American | 30 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene Hydrochloride 60 mg 65162-0057-03 | Amneal | 30 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene Hydrochloride 60 mg 65862-0709-01 | Aurobindo | 100 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene Hydrochloride 60 mg 69097-0825-02 | Cipla | 30 tablets | $0.236 | AB | Availability likely | — |
| Raloxifene hydrochloride 60 mg 72241-0010-05 | Modavar | 100 tablets | $0.236 | AB | Availability likely | — |
| Evista 60 mg 00002-4184-02 | Eli | 100 tablets | — | AB | FDA listed | — |
| Raloxifene hydrochloride 60 mg 50090-6177-01 | A-S | 90 tablets | — | AB | FDA listed | — |
| Raloxifene Hydrochloride 60 mg 50090-7073-01 | A-S | 90 tablets | — | AB | FDA listed | — |
| Raloxifene hydrochloride 60 mg 50228-0306-20 | ScieGen | 2000 tablets | — | AB | FDA listed | — |
| raloxifene hydrochloride 60 mg 68462-0393-01 | Glenmark | 100 tablets | — | AB | FDA listed | — |
| Raloxifene hydrochloride 60 mgthis 71209-0082-11 | Cadila | 1000 tablets | — | AB | FDA listed | — |
| Raloxifene hydrochloride 60 mg 71335-1460-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Raloxifene Hydrochloride 60 mg 71335-1715-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Raloxifene Hydrochloride 60 mg 71335-2059-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Raloxifene hydrochloride 60 mg 71610-0053-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Raloxifene Hydrochloride 60 mg 71610-0524-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Raloxifene hydrochloride 60 mg 72162-2418-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Raloxifene Hydrochloride 60 mg 76282-0256-01 | Exelan | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71209-0082-01 | 30 TABLET, COATED in 1 BOTTLE (71209-082-01) | 2017-12-30 | Active |
| 71209-0082-05 | 100 TABLET, COATED in 1 BOTTLE (71209-082-05) | 2017-12-30 | Active |
| 71209-0082-11 You're viewing this | 1000 TABLET, COATED in 1 BOTTLE (71209-082-11) | 2021-12-13 | Active |
| 71209-0082-13 | 2000 TABLET, COATED in 1 BOTTLE (71209-082-13) | 2017-12-30 | Active |
You're viewing one of 4 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71209-0082-11?
What is the difference between NDC 71209-0082-11 and NDC 71209-0082-01?
What NDC number is used to bill for this package of Raloxifene hydrochloride 60 mg Tablet, Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: INCREASED RISK OF VENOUS THROMBOEMBOLISM AND DEATH FROM STROKE Increased risk of deep vein thrombosis and pulmonary embolism have been reported with raloxifene hydrochloride tablets [see Warnings and Precautions ( 5.1) ] . Women with active or past history of venous thromboembolism should not take raloxifene hydrochloride tablets [see Contraindications ( 4.1) ] . Increased risk of death due to stroke occurred in a trial in postmenopausal women with documented coronary heart disease or at increased risk for major coronary events.
Consider risk-benefit balance in women at risk for stroke [see Warnings and Precautions ( 5.2 ) and Clinical Studies ( 14.5) ] . WARNING: INCREASED RISK OF VENOUS THROMBOEMBOLISM AND DEATH FROM STROKE See full prescribing information for complete boxed warning. Increased risk of deep vein thrombosis and pulmonary embolism have been reported with raloxifene hydrochloride tablets ( 5.1 ).
Women with active or past history of venous thromboembolism should not take raloxifene hydrochloride tablets ( 4.1 ). Increased risk of death due to stroke occurred in a trial in postmenopausal women with documented coronary heart disease or at increased risk for major coronary events. Consider risk-benefit balance in women at risk for stroke ( 5.2 , 14.5 ).
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Raloxifene hydrochloride is an estrogen agonist/antagonist indicated for: Treatment and prevention of osteoporosis in postmenopausal women. ( 1.1 ) Reduction in risk of invasive breast cancer in postmenopausal women with osteoporosis. ( 1.2 ) Reduction in risk of invasive breast cancer in postmenopausal women at high risk for invasive breast cancer.
( 1.3 ) Important Limitations: Raloxifene hydrochloride is not indicated for the treatment of invasive breast cancer, reduction of the risk of recurrence of breast cancer, or reduction of risk of noninvasive breast cancer. ( 1.3 )
1.1Treatment and Prevention of Osteoporosis in Postmenopausal Women Raloxifene hydrochloride is indicated for the treatment and prevention of osteoporosis in postmenopausal women [see Clinical Studies ( 14.1 , 14.2 )] .
1.2Reduction in the Risk of Invasive Breast Cancer in Postmenopausal Women with Osteoporosis Raloxifene hydrochloride is indicated for the reduction in risk of invasive breast cancer in postmenopausal women with osteoporosis [see Clinical Studies ( 14.3) ] .
1.3Reduction in the Risk of Invasive Breast Cancer in Postmenopausal Women at High Risk of Invasive Breast Cancer Raloxifene hydrochloride is indicated for the reduction in risk of invasive breast cancer in postmenopausal women at high risk of invasive breast cancer [see Clinical Studies ( 14.4 )] . The effect in the reduction in the incidence of breast cancer was shown in a study of postmenopausal women at high risk for breast cancer with a 5-year planned duration with a median follow-up of 4.3 years [see Clinical Studies ( 14.4 )] .
Twenty-seven percent of the participants received drug for 5 years. The long-term effects and the recommended length of treatment are not known. High risk of breast cancer is defined as at least one breast biopsy showing lobular carcinoma in situ (LCIS) or atypical hyperplasia, one or more first-degree relatives with breast cancer, or a 5-year predicted risk of breast cancer ≥1.66% (based on the modified Gail model).
Among the factors included in the modified Gail model are the following: current age, number of first-degree relatives with breast cancer, number of breast biopsies, age at menarche, nulliparity or age of first live birth. Healthcare professionals can obtain a Gail Model Risk Assessment Tool by dialing 1-800-545-5979. Currently, no single clinical finding or test result can quantify risk of breast cancer with certainty.
After an assessment of the risk of developing breast cancer, the decision regarding therapy with raloxifene hydrochloride tablets should be based upon an individual assessment of the benefits and risks. Raloxifene hydrochloride tablets does not eliminate the risk of breast cancer. Patients should have breast exams and mammograms before starting raloxifene hydrochloride tablets and should continue regular breast exams and mammograms in keeping with good medical practice after beginning treatment with raloxifene hydrochloride tablets.
Important Limitations of Use for Breast Cancer Risk Reduction There are no data available regarding the effect of raloxifene hydrochloride tablets on invasive breast cancer incidence in women with inherited mutations (BRCA1, BRCA2) to be able to make specific recommendations on the effectiveness of raloxifene hydrochloride tablets. Raloxifene hydrochloride tablets are not indicated for the treatment of invasive breast cancer or reduction of the risk of recurrence. Raloxifene hydrochloride tablets are not indicated for the reduction in the risk of noninvasive breast cancer.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION 60 mg tablet orally once daily. ( 2.1 )
2.1Recommended Dosing The recommended dosage is one 60 mg raloxifene hydrochloride tablet daily, which may be administered any time of day without regard to meals [see Clinical Pharmacology ( 12.3 )] . For the indications in risk of invasive breast cancer the optimum duration of treatment is not known [see Clinical Studies ( 14.3 , 14.4) ] .
2.2Recommendations for Calcium and Vitamin D Supplementation For either osteoporosis treatment or prevention, supplemental calcium and/or vitamin D should be added to the diet if daily intake is inadequate. Postmenopausal women require an average of 1,500 mg/day of elemental calcium. Total daily intake of calcium above 1,500 mg has not demonstrated additional bone benefits while daily intake above 2,000 mg has been associated with increased risk of adverse effects, including hypercalcemia and kidney stones.
The recommended intake of vitamin D is 400 to 800 IU daily. Patients at increased risk for vitamin D insufficiency (e.g., over the age of 70 years, nursing home bound, or chronically ill) may need additional vitamin D supplements. Patients with gastrointestinal malabsorption syndromes may require higher doses of vitamin D supplementation and measurement of 25-hydroxyvitamin D should be considered.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS 60 mg, white to off-white, oval shaped film coated tablet debossed with “C79” on one side and plain on the other side. Tablets (not scored): 60 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Active or past history of venous thromboembolism, including deep vein thrombosis, pulmonary embolism, and retinal vein thrombosis. ( 4.1 ) Pregnancy. ( 4.2 , 8.1 )
4.1Venous Thromboembolism Raloxifene hydrochloride tablets are contraindicated in women with active or past history of venous thromboembolism (VTE), including deep vein thrombosis, pulmonary embolism, and retinal vein thrombosis [see Warnings and Precautions ( 5.1) ] .
4.2Pregnancy Raloxifene hydrochloride tablets are contraindicated for use in pregnancy, as it may cause fetal harm [see Use in Specific Populations ( 8.1 )] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Venous Thromboembolism : Increased risk of deep vein thrombosis, pulmonary embolism, and retinal vein thrombosis. Discontinue use 72 hours prior to and during prolonged immobilization. ( 5.1 , 6.1 ) Death Due to Stroke : Increased risk of death due to stroke occurred in a trial in postmenopausal women with documented coronary heart disease or at increased risk for major coronary events.
No increased risk of stroke was seen in this trial. Consider risk-benefit balance in women at risk for stroke. ( 5.2 , 14.5 ) Cardiovascular Disease : Raloxifene hydrochloride tablets should not be used for the primary or secondary prevention of cardiovascular disease.
( 5.3 , 14.5 ) Premenopausal Women : Use is not recommended. ( 5.4 ) Hepatic Impairment : Use with caution. ( 5.5 ) Concomitant Use with Systemic Estrogens : Not recommended.
( 5.6 ) Hypertriglyceridemia : If previous treatment with estrogen resulted in hypertriglyceridemia, monitor serum triglycerides. ( 5.7 )
5.1Venous Thromboembolism In clinical trials, raloxifene hydrochloride tablets-treated women had an increased risk of venous thromboembolism (deep vein thrombosis and pulmonary embolism). Other venous thromboembolic events also could occur. A less serious event, superficial thrombophlebitis, also has been reported more frequently with raloxifene hydrochloride than with placebo.
The greatest risk for deep vein thrombosis and pulmonary embolism occurs during the first 4 months of treatment, and the magnitude of risk appears to be similar to the reported risk associated with use of hormone therapy. Because immobilization increases the risk for venous thromboembolic events independent of therapy, raloxifene hydrochloride tablets should be discontinued at least 72 hours prior to and during prolonged immobilization (e.g., post-surgical recovery, prolonged bed rest), and raloxifene hydrochloride tablets therapy should be resumed only after the patient is fully ambulatory.
In addition, women taking raloxifene hydrochloride tablets should be advised to move about periodically during prolonged travel. The risk-benefit balance should be considered in women at risk of thromboembolic disease for other reasons, such as congestive heart failure, superficial thrombophlebitis, and active malignancy [see Contraindications ( 4.1 ) and Adverse Reactions ( 6.1 )] .
5.2Death Due to Stroke In a clinical trial of postmenopausal women with documented coronary heart disease or at increased risk for coronary events, an increased risk of death due to stroke was observed after treatment with raloxifene hydrochloride tablets. During an average follow-up of 5.6 years, 59 (1.2%) raloxifene hydrochloride tablets-treated women died due to a stroke compared to 39 (0.8%) placebo-treated women (22 versus 15 per 10,000 women-years; hazard ratio 1.49; 95% confidence interval, 1.00 to 2.24; p=0.0499).
There was no statistically significant difference between treatment groups in the incidence of stroke (249 in raloxifene hydrochloride tablets [4.9%] versus 224 placebo [4.4%]). Raloxifene hydrochloride tablets had no significant effect on all-cause mortality. The risk-benefit balance should be considered in women at risk for stroke, such as prior stroke or transient ischemic attack (TIA), atrial fibrillation, hypertension, or cigarette smoking [see Clinical Studies ( 14.5 )] .
5.3Cardiovascular Disease Raloxifene hydrochloride tablets should not be used for the primary or secondary prevention of cardiovascular disease. In a clinical trial of postmenopausal women with documented coronary heart disease or at increased risk for coronary events, no cardiovascular benefit was demonstrated after treatment with raloxifene for 5 years [see Clinical Studies ( 14.5 )] .
5.4Premenopausal Use There is no indication for premenopausal use of raloxifene hydrochloride tablets. Safety of raloxifene hydrochloride tablets in premenopausal women has not been established and its use is not recommended. A…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Adverse reactions (>2% and more common than with placebo) include: hot flashes, leg cramps, peripheral edema, flu syndrome, arthralgia, sweating. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Cadila Pharmaceuticals Limited at 1-202-355-9785 (Fax 1-202-355-9784), or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to raloxifene hydrochloride tablets in 8,429 patients who were enrolled in placebo-controlled trials, including 6,666 exposed for 1 year and 5,685 for at least 3 years. Osteoporosis Treatment Clinical Trial (MORE) — The safety of raloxifene in the treatment of osteoporosis was assessed in a large (7,705 patients) multinational, placebo-controlled trial.
Duration of treatment was 36 months, and 5,129 postmenopausal women were exposed to raloxifene hydrochloride (2,557 received 60 mg/day, and 2,572 received 120 mg/day). The incidence of all-cause mortality was similar among groups: 23 (0.9%) placebo, 13 (0.5%) raloxifene hydrochloride tablets-treated (raloxifene HCl 60 mg), and 28 (1.1%) raloxifene HCl 120 mg women died. Therapy was discontinued due to an adverse reaction in 10.9% of raloxifene hydrochloride tablets-treated women and 8.8% of placebo-treated women.
Venous Thromboembolism : The most serious adverse reaction related to raloxifene hydrochloride tablets was VTE (deep venous thrombosis, pulmonary embolism, and retinal vein thrombosis). During an average of study-drug exposure of 2.6 years, VTE occurred in about 1 out of 100 patients treated with raloxifene hydrochloride tablets. Twenty-six raloxifene hydrochloride tablets-treated women had a VTE compared to 11 placebo-treated women, the hazard ratio was 2.4 (95% confidence interval, 1.2, 4.5), and the highest VTE risk was during the initial months of treatment.
Common adverse reactions considered to be related to raloxifene hydrochloride tablets therapy were hot flashes and leg cramps. Hot flashes occurred in about one in 10 patients on raloxifene hydrochloride tablets and were most commonly reported during the first 6 months of treatment and were not different from placebo thereafter. Leg cramps occurred in about one in 14 patients on raloxifene hydrochloride tablets.
Placebo-Controlled Osteoporosis Prevention Clinical Trials — The safety of raloxifene has been assessed primarily in 12 Phase 2 and Phase 3 studies with placebo, estrogen, and estrogen-progestin therapy control groups. The duration of treatment ranged from 2 to 30 months, and 2,036 women were exposed to raloxifene HCl (371 patients received 10 to 50 mg/day, 828 received 60 mg/day, and 837 received from 120 to 600 mg/day). Therapy was discontinued due to an adverse reaction in 11.4% of 581 raloxifene hydrochloride tablets-treated women and 12.2% of 584 placebo-treated women.
Discontinuation rates due to hot flashes did not differ significantly between raloxifene hydrochloride tablets and placebo groups (1.7% and 2.2%, respectively). Common adverse reactions considered to be drug-related were hot flashes and leg cramps. Hot flashes occurred in about one in four patients on raloxifene hydrochloride tablets versus about one in six on placebo.
The first occurrence of hot flashes was most commonly reported during the first 6 months of treatment. Table 1 lists adverse reactions occurring in either the osteoporosis treatment or in five prevention placebo-controlled clinical trials at a frequency ≥2.0% in either group and in more raloxifene hydrochloride tablets-treated women than in placebo-treated women. Adverse reactions are shown without attribution of causality.
The majority of adverse reactions occurring during the studies were mild and ge…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Cholestyramine : Use with raloxifene hydrochloride tablet is not recommended. Reduces the absorption and enterohepatic cycling of raloxifene. ( 7.1 , 12.3 ) Warfarin : Monitor prothrombin time when starting or stopping raloxifene hydrochloride tablets.
( 7.2 , 12.3 ) Highly Protein-Bound Drugs : Use with raloxifene hydrochloride tablets with caution. Highly protein-bound drugs include diazepam, diazoxide, and lidocaine. Raloxifene hydrochloride tablets are more than 95% bound to plasma proteins.
(7.3 , 12.3 )
7.1Cholestyramine Concomitant administration of cholestyramine with raloxifene hydrochloride tablet is not recommended. Although not specifically studied, it is anticipated that other anion exchange resins would have a similar effect. Raloxifene hydrochloride tablets should not be co-administered with other anion exchange resins [see Clinical Pharmacology ( 12.3 )] .
7.2Warfarin If raloxifene hydrochloride tablets are given concomitantly with warfarin or other warfarin derivatives, prothrombin time should be monitored more closely when starting or stopping therapy with raloxifene hydrochloride tablets. [see Clinical Pharmacology ( 12.3 )] .
7.3Other Highly Protein-Bound Drugs Raloxifene hydrochloride tablets should be used with caution with certain other highly protein-bound drugs such as diazepam, diazoxide, and lidocaine. Although not examined, raloxifene hydrochloride tablets might affect the protein binding of other drugs. Raloxifene is more than 95% bound to plasma proteins [see Clinical Pharmacology ( 12.3 )] .
7.4Systemic Estrogens The safety of concomitant use of raloxifene hydrochloride with systemic estrogens has not been established and its use is not recommended.
7.5Other Concomitant Medications Raloxifene hydrochloride tablets can be concomitantly administered with ampicillin, amoxicillin, antacids, corticosteroids, and digoxin [see Clinical Pharmacology ( 12.3 )] . The concomitant use of raloxifene hydrochloride tablets and lipid-lowering agents has not been studied.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric Use: Safety and effectiveness not established. ( 8.4 )
8.1Pregnancy Risk Summary Raloxifene hydrochloride tablets are contraindicated for use in pregnant women, and is not indicated for use in females of reproductive potential. Based on mechanism of action, raloxifene hydrochloride tablets may block the important functions that estrogen has during all stages of pregnancy [see Clinical Pharmacology ( 12.1 )] . Limited data with raloxifene hydrochloride tablets use in pregnant women are insufficient to inform any drug associated risks for births defects or miscarriage.
In rabbits and rats dosed during organogenesis or during gestation and lactation, raloxifene hydrochloride tablets produced multiple adverse reproductive and developmental effects, including abortion; fetal anomalies; and delayed or disrupted parturition leading to maternal and neonatal mortality, at doses less than or similar to the maximum recommended human dose (based on human body surface area comparison). Data Animal Data In the developmental and reproductive toxicity studies conducted with raloxifene hydrochloride tablets, numerous adverse effects were observed in multiple animal species.
In rabbits dosed during organogenesis, abortion and a low rate of fetal heart anomalies (ventricular septal defects) occurred at doses ≥0.1 mg/kg (≥0.04 times the human dose based on surface area, mg/m 2 ). In rats dosed during organogenesis, retardation of fetal growth and developmental abnormalities (wavy ribs, kidney cavitation) occurred at doses ≥1 mg/kg (≥0.2 times the human dose based on surface area, mg/m 2 ). Treatment of rats during gestation and lactation with doses of 0.1 to 10 mg/kg (0.02 to 1.6 times the human dose based on surface area, mg/m 2 ) produced effects that included delayed and disrupted parturition, decreased neonatal survival and altered physical development, sex- and age-specific reductions in growth and changes in pituitary hormone content, and decreased lymphoid compartment size in offspring.
At 10 mg/kg, the disruption of parturition resulted in maternal and progeny morbidity and death. Effects in adult offspring (4 months of age) included uterine hypoplasia and reduced fertility; however, no ovarian or vaginal pathology was observed.
8.2Lactation Risk Summary Raloxifene hydrochloride tablets are not indicated for use in females of reproductive potential. There is no information on the presence of raloxifene in human milk, the effects on the breastfed child, or the effects on milk production. However, based on mechanism of action, raloxifene hydrochloride tablets may block the important functions that estrogen has in mammary tissue during lactation [see Clinical Pharmacology ( 12.1 )] .
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Of the total number of patients in placebo-controlled clinical studies of raloxifene hydrochloride tablets, 61% were 65 and over, while 15.5% were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Based on clinical trials, there is no need for dose adjustment for geriatric patients [see Clinical Pharmacology ( 12.3 )] .
8.6Renal Impairment Raloxifene hydrochloride tablets should be used with caution in patients with moderate or severe renal impairment [see Warnings and Precautions ( 5.8 ) and Clinical Pharmacology ( 12.3 )] .
8.7Hepatic Impairment Raloxifene hydrochloride tablets should be used with caution in patients with hepatic impairment [see Warnings and Precautions ( 5.5 ) and Clinical Pharmacology ( 12.3 )] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Raloxifene hydrochloride tablets are contraindicated for use in pregnant women, and is not indicated for use in females of reproductive potential. Based on mechanism of action, raloxifene hydrochloride tablets may block the important functions that estrogen has during all stages of pregnancy [see Clinical Pharmacology ( 12.1 )] . Limited data with raloxifene hydrochloride tablets use in pregnant women are insufficient to inform any drug associated risks for births defects or miscarriage.
In rabbits and rats dosed during organogenesis or during gestation and lactation, raloxifene hydrochloride tablets produced multiple adverse reproductive and developmental effects, including abortion; fetal anomalies; and delayed or disrupted parturition leading to maternal and neonatal mortality, at doses less than or similar to the maximum recommended human dose (based on human body surface area comparison). Data Animal Data In the developmental and reproductive toxicity studies conducted with raloxifene hydrochloride tablets, numerous adverse effects were observed in multiple animal species.
In rabbits dosed during organogenesis, abortion and a low rate of fetal heart anomalies (ventricular septal defects) occurred at doses ≥0.1 mg/kg (≥0.04 times the human dose based on surface area, mg/m 2 ). In rats dosed during organogenesis, retardation of fetal growth and developmental abnormalities (wavy ribs, kidney cavitation) occurred at doses ≥1 mg/kg (≥0.2 times the human dose based on surface area, mg/m 2 ). Treatment of rats during gestation and lactation with doses of 0.1 to 10 mg/kg (0.02 to 1.6 times the human dose based on surface area, mg/m 2 ) produced effects that included delayed and disrupted parturition, decreased neonatal survival and altered physical development, sex- and age-specific reductions in growth and changes in pituitary hormone content, and decreased lymphoid compartment size in offspring.
At 10 mg/kg, the disruption of parturition resulted in maternal and progeny morbidity and death. Effects in adult offspring (4 months of age) included uterine hypoplasia and reduced fertility; however, no ovarian or vaginal pathology was observed.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients in placebo-controlled clinical studies of raloxifene hydrochloride tablets, 61% were 65 and over, while 15.5% were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Based on clinical trials, there is no need for dose adjustment for geriatric patients [see Clinical Pharmacology ( 12.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE In an 8-week study of 63 postmenopausal women, a dose of raloxifene hydrochloride (HCl) 600 mg/day was safely tolerated. In clinical trials, no raloxifene overdose has been reported. In postmarketing spontaneous reports, raloxifene overdose has been reported very rarely (less than 1 out of 10,000 [<0.01%] patients treated).
The highest overdose has been approximately 1.5 grams. No fatalities associated with raloxifene overdose have been reported. Adverse reactions were reported in approximately half of the adults who took ≥180 mg raloxifene HCl and included leg cramps and dizziness.
Two 18-month-old children each ingested raloxifene HCl 180 mg. In these two children, symptoms reported included ataxia, dizziness, vomiting, rash, diarrhea, tremor, and flushing, as well as elevation in alkaline phosphatase. There is no specific antidote for raloxifene.
No mortality was seen after a single oral dose in rats or mice at 5,000 mg/kg (810 times the human dose for rats and 405 times the human dose for mice based on surface area, mg/m 2 ) or in monkeys at 1,000 mg/kg (80 times the AUC in humans).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Raloxifene is an estrogen agonist/antagonist, commonly referred to as a selective estrogen receptor modulator (SERM). The biological actions of raloxifene are largely mediated through binding to estrogen receptors. This binding results in activation of estrogenic pathways in some tissues (agonism) and blockade of estrogenic pathways in others (antagonism).
The agonistic or antagonistic action of raloxifene depends on the extent of recruitment of coactivators and corepressors to estrogen receptor (ER) target gene promoters. Raloxifene appears to act as an estrogen agonist in bone. It decreases bone resorption and bone turnover, increases bone mineral density (BMD) and decreases fracture incidence.
Preclinical data demonstrate that raloxifene is an estrogen antagonist in uterine and breast tissues. These results are consistent with findings in clinical trials, which suggest that raloxifene hydrochloride tablets lacks estrogen-like effects on the uterus and breast tissue.
12.2Pharmacodynamics Decreases in estrogen levels after oophorectomy or menopause lead to increases in bone resorption and accelerated bone loss. Bone is initially lost rapidly because the compensatory increase in bone formation is inadequate to offset resorptive losses. In addition to loss of estrogen, this imbalance between resorption and formation may be due to age-related impairment of osteoblasts or their precursors.
In some women, these changes will eventually lead to decreased bone mass, osteoporosis, and increased risk for fractures, particularly of the spine, hip, and wrist. Vertebral fractures are the most common type of osteoporotic fracture in postmenopausal women. In both the osteoporosis treatment and prevention trials, raloxifene hydrochloride tablets therapy resulted in consistent, statistically significant suppression of bone resorption and bone formation, as reflected by changes in serum and urine markers of bone turnover (e.g., bone-specific alkaline phosphatase, osteocalcin, and collagen breakdown products).
The suppression of bone turnover markers was evident by 3 months and persisted throughout the 36-month and 24-month observation periods. In a 31-week, open-label, radiocalcium kinetics study, 33 early postmenopausal women were randomized to treatment with once-daily raloxifene hydrochloride tablet 60 mg, cyclic estrogen/progestin (0.625 mg conjugated estrogens daily with 5 mg medroxyprogesterone acetate daily for the first 2 weeks of each month [hormone therapy]), or no treatment. Treatment with either raloxifene hydrochloride tablets or hormone therapy was associated with reduced bone resorption and a positive shift in calcium balance (-82 mg Ca/day and +60 mg Ca/day, respectively, for raloxifene hydrochloride tablets and -162 mg Ca/day and +91 mg Ca/day, respectively, for hormone therapy).
There were small decreases in serum total calcium, inorganic phosphate, total protein, and albumin, which were generally of lesser magnitude than decreases observed during estrogen or hormone therapy. Platelet count was also decreased slightly and was not different from estrogen therapy.
12.3Pharmacokinetics The disposition of raloxifene has been evaluated in more than 3,000 postmenopausal women in selected raloxifene osteoporosis treatment and prevention clinical trials, using a population approach. Pharmacokinetic data also were obtained in conventional pharmacology studies in 292 postmenopausal women. Raloxifene exhibits high within-subject variability (approximately 30% coefficient of variation) of most pharmacokinetic parameters.
Table 3 summarizes the pharmacokinetic parameters of raloxifene. Absorption — Raloxifene is absorbed rapidly after oral administration. Approximately 60% of an oral dose is absorbed, but presystemic glucuronide conjugation is extensive.
Absolute bioavailability of raloxifene is 2%. The time to reach average maximum plasma concentration and bioavailability are functions…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Raloxifene is an estrogen agonist/antagonist, commonly referred to as a selective estrogen receptor modulator (SERM). The biological actions of raloxifene are largely mediated through binding to estrogen receptors. This binding results in activation of estrogenic pathways in some tissues (agonism) and blockade of estrogenic pathways in others (antagonism).
The agonistic or antagonistic action of raloxifene depends on the extent of recruitment of coactivators and corepressors to estrogen receptor (ER) target gene promoters. Raloxifene appears to act as an estrogen agonist in bone. It decreases bone resorption and bone turnover, increases bone mineral density (BMD) and decreases fracture incidence.
Preclinical data demonstrate that raloxifene is an estrogen antagonist in uterine and breast tissues. These results are consistent with findings in clinical trials, which suggest that raloxifene hydrochloride tablets lacks estrogen-like effects on the uterus and breast tissue.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Raloxifene hydrochloride tablets, USP are white to off-white, oval shaped film coated tablet debossed with “C79” on one side and plain on the other side. They are available as follows: Tablet Imprint C79 Presentations and NDCs Bottles of 30 71209-082-01 Bottles of 100 71209-082-05 Bottles of 1000 71209-082-11 Bottles of 2000 71209-082-13
16.2Storage and Handling Store at 20° to 25°C (68° to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. The USP defines controlled room temperature as a temperature maintained thermostatically that encompasses the usual and customary working environment of 20° to 25°C (68° to 77°F); that results in a mean kinetic temperature calculated to be not more than 25°C; and that allows for excursions between 15° and 30°C (59° and 86°F) that are experienced in pharmacies, hospitals, and warehouses.
📋 Description ▾
11 DESCRIPTION Raloxifene hydrochloride, USP is an estrogen agonist/antagonist, commonly referred to as a selective estrogen receptor modulator (SERM) that belongs to the benzothiophene class of compounds. The chemical structure is: The chemical designation is methanone, [6-hydroxy-2-(4-hydroxyphenyl) benzo[b]thien-3-yl]-[4-[2-(1-piperidinyl)ethoxy]phenyl]-, hydrochloride. Raloxifene hydrochloride (HCl), USP has the empirical formula C 28 H 27 NO 4 S•HCl, which corresponds to a molecular weight of 510.05.
Raloxifene HCl, USP is an off-white to pale-yellow solid that is very slightly soluble in water. Raloxifene hydrochloride, USP is supplied in a tablet dosage form for oral administration. Each raloxifene hydrochloride tablet, USP contains 60 mg of raloxifene HCl, which is the molar equivalent of 55.71 mg of free base.
Inactive ingredients include crospovidone, hypromellose, lactose monohydrate, lactose anhydrous, magnesium stearate, polyethylene glycol 400, polysorbate 80, povidone and titanium dioxide. raloxifene-spl-strc.jpg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved Medication Guide. Physicians should instruct their patients to read the Medication Guide before starting therapy with raloxifene hydrochloride tablets and to reread it each time the prescription is renewed.
17.1Osteoporosis Recommendations, Including Calcium and Vitamin D Supplementation For osteoporosis treatment or prevention, patients should be instructed to take supplemental calcium and/or vitamin D if intake is inadequate. Patients at increased risk for vitamin D insufficiency (e.g., over the age of 70 years, nursing home bound, chronically ill, or with gastrointestinal malabsorption syndromes) should be instructed to take additional vitamin D if needed. Weight-bearing exercises should be considered along with the modification of certain behavioral factors, such as cigarette smoking and/or excessive alcohol consumption, if these factors exist.
17.2Patient Immobilization Raloxifene hydrochloride tablets should be discontinued at least 72 hours prior to and during prolonged immobilization (e.g., post-surgical recovery, prolonged bed rest), and patients should be advised to avoid prolonged restrictions of movement during travel because of the increased risk of venous thromboembolic events [see Warnings and Precautions (5.1)] .
17.3Hot Flashes or Flushes Raloxifene hydrochloride tablets may increase the incidence of hot flashes and is not effective in reducing hot flashes or flushes associated with estrogen deficiency. In some asymptomatic patients, hot flashes may occur upon beginning raloxifene hydrochloride tablets therapy.
17.4Reduction in Risk of Invasive Breast Cancer in Postmenopausal Women with Osteoporosis or at High Risk of Invasive Breast Cancer Use of raloxifene hydrochloride tablets are associated with the reduction of the risk of invasive breast cancer in postmenopausal women. Raloxifene hydrochloride tablets has not been shown to reduce the risk of noninvasive breast cancer. When considering treatment, physicians need to discuss the potential benefits and risks of raloxifene hydrochloride tablets treatment with the patient.
Raloxifene hydrochloride tablets are not indicated for the treatment of invasive breast cancer or reduction of the risk of recurrence. Patients should have breast exams and mammograms before starting raloxifene hydrochloride tablets and should continue regular breast exams and mammograms in keeping with good medical practice after beginning treatment with raloxifene hydrochloride tablets. Literature revised December 13, 2021 Manufactured by: Cadila Pharmaceuticals Limited 1389, Dholka, District - Ahmedabad, Gujarat State, INDIA.
Medication Guide Raloxifene Hydrochloride Tablets for Oral Use (ral ox’ i feen hye’’ droe klor’ ide) Read the Medication Guide that comes with raloxifene hydrochloride tablets before you start taking it and each time you refill your prescription. The information may have changed. This Medication Guide does not take the place of talking with your doctor about your medical condition or treatment.
Talk with your doctor about raloxifene hydrochloride tablets when you start taking it and at regular checkups. What is the most important information I should know about raloxifene hydrochloride tablets? Serious and life-threatening side effects can occur while taking raloxifene hydrochloride tablets.
These include blood clots and dying from stroke: Increased risk of blood clots in the legs (deep vein thrombosis) and lungs (pulmonary embolism) have been reported with raloxifene hydrochloride tablets. Women who have or have had blood clots in the legs, lungs, or eyes should not take raloxifene hydrochloride tablets. Women who have had a heart attack or are at risk for a heart attack may have an increased risk of dying from stroke when taking raloxifene hydrochloride tablets.
Before starting raloxifene hydrochloride tablets, tell your doctor if you have had blood clots in your legs, lungs, or eyes, a stroke, mini-stroke (tra…