
Cytarabine 20 mg/mL Injection, Solution — NDC 71288-168-50 (Billing 71288-0168-50)
This is a package of Cytarabine 20 mg/mL Injection, Solution from Meitheal Pharmaceuticals Inc., marketed since Nov 2017 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 240416
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Nucleoside Metabolic Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cytarabine is used to treat certain types of leukemia (cancer of the white blood cells). Cytarabine is in a class of medications called antimetabolites. It works by slowing or stopping the growth of cancer cells in your body.
Read the full MedlinePlus article ↗- It is used with other cancer drugs to treat acute non-lymphocytic leukemia in adults and children. Some products also list acute lymphocytic leukemia and the blast phase of chronic...
- Your care team gives it, since it does not work by mouth. It may go into a vein, under the skin, or into the spinal fluid, depending on the product and your plan. Your schedule dep...
- Nausea, vomiting, poor appetite, diarrhea, mouth sores, rash, fever and low blood counts are common. Nausea is most likely after a rapid IV injection. Your team will check your blo...
- Call right away for fever, sore throat, unusual bleeding, trouble breathing, swelling, severe belly pain, yellow skin or eyes, or numbness, weakness or confusion. Fever with muscle...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cytarabine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 71288-0168-50 You're viewing this Main listing | 1 VIAL, MULTI-DOSE in 1 CARTON / 50 mL in 1 VIAL, MULTI-DOSE | 2017-11-09 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cytarabine 20 mg/mL 61703-0303-46 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Cytarabine 20 mg/mL 61703-0304-36 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Cytarabine 20 mg/mLthis 71288-0168-50 | Meitheal | 1 vial | — | — | FDA listed | — |
| Cytarabine 20 mg/mL 71288-0169-25 | Meitheal | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Only physicians experienced in cancer chemotherapy should use cytarabine. For induction therapy patients should be treated in a facility with laboratory and supportive resources sufficient to monitor drug tolerance and protect and maintain a patient compromised by drug toxicity. The main toxic effect of cytarabine is bone marrow suppression with leukopenia, thrombocytopenia and anemia.
Less serious toxicity includes nausea, vomiting, diarrhea and abdominal pain, oral ulceration, and hepatic dysfunction. The physician must judge possible benefit to the patient against known toxic effects of this drug in considering the advisability of therapy with cytarabine. Before making this judgment or beginning treatment, the physician should be familiar with the following text.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Cytarabine Injection in combination with other approved anticancer drugs is indicated for remission induction in acute non-lymphocytic leukemia of adults and children. It has also been found useful in the treatment of acute lymphocytic leukemia and the blast phase of chronic myelocytic leukemia. Intrathecal administration of Cytarabine Injection is indicated in the prophylaxis and treatment of meningeal leukemia.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Cytarabine injection (non-preserved) can be administered by intravenous injection or infusion, subcutaneously, or intrathecally. However, the intent of this Pharmacy Bulk Package is for the preparation of solutions for intravenous infusion only. Intrathecal use of cytarabine injection requires the use of single-dose, unpreserved solutions only.
Cytarabine injection is not active orally. The schedule and method of administration varies with the program of therapy to be used. While cytarabine injection may be given by intravenous infusion or injection, or subcutaneously or intrathecally, THE PURPOSE OF THE PHARMACY BULK PACKAGE IS FOR THE PREPARATION OF INTRAVENOUS INFUSIONS.
Thrombophlebitis has occurred at the site of drug injection or infusion in some patients, and rarely patients have noted pain and inflammation at subcutaneous injection sites. In most instances, however, the drug has been well tolerated. Patients can tolerate higher total doses when they receive the drug by rapid intravenous injection as compared with slow infusion.
This phenomenon is related to the drug's rapid inactivation and brief exposure of susceptible normal and neoplastic cells to significant levels after rapid injection. Normal and neoplastic cells seem to respond in somewhat parallel fashion to these different modes of administration and no clear-cut clinical advantage has been demonstrated for either. In the induction therapy of acute non-lymphocytic leukemia, the usual cytarabine injection dose in combination with other anti-cancer drugs is 100 mg/m 2 /day by continuous intravenous infusion (Days 1 to 7) or 100 mg/m 2 intravenously every 12 hours (Days 1 to 7).
The literature should be consulted for the current recommendations for use in acute lymphocytic leukemia. Intrathecal Use in Meningeal Leukemia Cytarabine injection has been used intrathecally in acute leukemia in doses ranging from 5 mg/m 2 to 75 mg/m 2 of body surface area. The frequency of administration varied from once a day for 4 days to once every 4 days.
The most frequently used dose was 30 mg/m 2 every 4 days until cerebrospinal fluid findings were normal, followed by one additional treatment. The dosage schedule is usually governed by the type and severity of central nervous system manifestations and the response to previous therapy. If used intrathecally, do not use a solution containing benzyl alcohol.
This pharmacy bulk package is not intended to be used for the preparation of intrathecal doses. Cytarabine injection given intrathecally may cause systemic toxicity and careful monitoring of the hemopoietic system is indicated. Modification of other anti-leukemia therapy may be necessary.
Major toxicity is rare. The most frequently reported reactions after intrathecal administration were nausea, vomiting and fever; these reactions are mild and self-limiting. Paraplegia has been reported.
Necrotizing leukoencephalopathy occurred in 5 children; these patients had also been treated with intrathecal methotrexate and hydrocortisone, as well as by central nervous system radiation. Isolated neurotoxicity has been reported. Blindness occurred in two patients in remission whose treatment had consisted of combination systemic chemotherapy, prophylactic central nervous system radiation and intrathecal cytarabine injection.
When cytarabine injection is administered both intrathecally and intravenously within a few days, there is an increased risk of spinal cord toxicity, however, in serious life-threatening disease, concurrent use of intravenous and intrathecal cytarabine injection is left to the discretion of the treating physician. Focal leukemic involvement of the central nervous system may not respond to intrathecal cytarabine injection and may better be treated with radiotherapy. Chemical Stability of Infusion Solutions Chemical stability studies were performed by a stability indicating HPLC assay on cytarabine injection in infusion solutions.
These studies sh… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Cytarabine is contraindicated in those patients who are hypersensitive to the drug.
⚠️ Warnings ▾
WARNINGS ( See boxed WARNING ) Cytarabine is a potent bone marrow suppressant. Therapy should be started cautiously in patients with pre-existing drug-induced bone marrow suppression. Patients receiving this drug must be under close medical supervision and, during induction therapy, should have leucocyte and platelet counts performed daily.
Bone marrow examinations should be performed frequently after blasts have disappeared from the peripheral blood. Facilities should be available for management of complications, possibly fatal, of bone marrow suppression (infection resulting from granulocytopenia and other impaired body defenses, and hemorrhage secondary to thrombocytopenia). One case of anaphylaxis that resulted in acute cardiopulmonary arrest and required resuscitation has been reported.
This occurred immediately after the intravenous administration of cytarabine. Severe and at times fatal CNS, GI and pulmonary toxicity (different from that seen with conventional therapy regimens of cytarabine) has been reported following some experimental cytarabine dose schedules. These reactions include reversible corneal toxicity, and hemorrhagic conjunctivitis, which may be prevented or diminished by prophylaxis with a local corticosteroid eye drop; cerebral and cerebellar dysfunction, including personality changes, somnolence and coma, usually reversible; severe gastrointestinal ulceration, including pneumatosis cystoides intestinalis leading to peritonitis; sepsis and liver abscess; pulmonary edema, liver damage with increased hyperbilirubinemia; bowel necrosis; and necrotizing colitis.
Rarely, severe skin rash, leading to desquamation has been reported. Complete alopecia is more commonly seen with experimental high dose therapy than with standard cytarabine treatment programs. If experimental high dose therapy is used, do not use a diluent containing benzyl alcohol.
Cases of cardiomyopathy with subsequent death has been reported following experimental high dose therapy with cytarabine in combination with cyclophosphamide when used for bone marrow transplant preparation. A syndrome of sudden respiratory distress, rapidly progressing to pulmonary edema and radiographically pronounced cardiomegaly has been reported following experimental high dose therapy with cytarabine used for the treatment of relapsed leukemia from one institution in 16/72 patients. The outcome of this syndrome can be fatal.
Two patients with childhood acute myelogenous leukemia who received intrathecal and intravenous cytarabine at conventional doses (in addition to a number of other concomitantly administered drugs) developed delayed progressive ascending paralysis resulting in death in one of the two patients. Use in Pregnancy Cytarabine can cause fetal harm when administered to a pregnant woman. Cytarabine causes abnormal cerebellar development in the neonatal hamster and is teratogenic to the rat fetus.
There are no adequate and well-controlled studies in pregnant women. Women of childbearing potential should be advised to avoid becoming pregnant.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Expected Reactions Because cytarabine is a bone marrow suppressant, anemia, leukopenia, thrombocytopenia, megaloblastosis and reduced reticulocytes can be expected as a result of administration with cytarabine. The severity of these reactions are dose and schedule dependent. Cellular changes in the morphology of bone marrow and peripheral smears can be expected.
Following 5-day constant infusions or acute injections of 50 mg/m 2 to 600 mg/m 2 , white cell depression follows a biphasic course. Regardless of initial count, dosage level, or schedule, there is an initial fall starting the first 24 hours with a nadir at days 7 to 9. This is followed by a brief rise which peaks around the twelfth day.
A second and deeper fall reaches nadir at days 15 to 24. Then there is a rapid rise to above baseline in the next 10 days. Platelet depression is noticeable at 5 days with a peak depression occurring between days 12 to 15.
Thereupon, a rapid rise to above baseline occurs in the next 10 days. Infectious Complications Infection Viral, bacterial, fungal, parasitic, or saprophytic infections, in any location in the body may be associated with the use of cytarabine alone or in combination with other immunosuppressive agents following immunosuppressant doses that affect cellular or humoral immunity. These infections may be mild, but can be severe and at times fatal.
The Cytarabine (Ara-C) Syndrome A cytarabine syndrome has been described by Castleberry. It is characterized by fever, myalgia, bone pain, occasionally chest pain, maculopapular rash, conjunctivitis and malaise. It usually occurs 6 to 12 hours following drug administration.
Corticosteroids have been shown to be beneficial in treating or preventing this syndrome. If the symptoms of the syndrome are deemed treatable, corticosteroids should be contemplated as well as continuation of therapy with cytarabine. Most Frequent Adverse Reactions Anorexia, hepatic dysfunction, nausea, fever, vomiting, rash, diarrhea, thrombophlebitis, oral and anal inflammation or ulceration, bleeding (all sites).
Nausea and vomiting are most frequent following rapid intravenous injection. Less Frequent Adverse Reactions Sepsis, abdominal pain, pneumonia, freckling, cellulitis at injection site, jaundice, skin ulceration, conjunctivitis (may occur with rash), urinary retention, dizziness, renal dysfunction, alopecia, neuritis, anaphylaxis (see WARNINGS ), neural toxicity, allergic edema, sore throat, pruritus, esophageal ulceration, shortness of breath, esophagitis, urticaria, chest pain, pericarditis, headache, bowel necrosis, pancreatitis, sinus bradycardia.
Experimental Doses Severe and at times fatal CNS, GI and pulmonary toxicity (different from that seen with conventional therapy regimens of cytarabine) has been reported following some experimental dose schedules of cytarabine. These reactions include reversible corneal toxicity and hemorrhagic conjunctivitis, which may be prevented or diminished by prophylaxis with a local corticosteroid eye drop; cerebral and cerebellar dysfunction, including personality changes, somnolence and coma, usually reversible; severe gastrointestinal ulceration, including pneumatosis cystoides intestinalis leading to peritonitis; sepsis and liver abscess; pulmonary edema, liver damage with increased hyperbilirubinemia; bowel necrosis; and necrotizing colitis.
Rarely, severe skin rash, leading to desquamation has been reported. Complete alopecia is more commonly seen with experimental high dose therapy than with standard cytarabine treatment programs. If experimental high dose therapy is used, do not use a diluent containing benzyl alcohol.
Cases of cardiomyopathy with subsequent death has been reported following experimental high dose therapy with cytarabine in combination with cyclophosphamide when used for bone marrow transplant preparation. This cardiac toxicity may be schedule dependent. A syndrome of sudden respiratory distress, rapidly progressing t… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Reversible decreases in steady-state plasma digoxin concentrations and renal glycoside excretion were observed in patients receiving beta-acetyldigoxin and chemotherapy regimens containing cyclophosphamide, vincristine and prednisone with or without cytarabine or procarbazine. Steady-state plasma digitoxin concentrations did not appear to change. Therefore, monitoring of plasma digoxin levels may be indicated in patients receiving similar combination chemotherapy regimens.
The utilization of digitoxin for such patients may be considered as an alternative. An in vitro interaction study between gentamicin and cytarabine showed a cytarabine related antagonism for the susceptibility of K. pneumoniae strains. This study suggests that in patients on cytarabine being treated with gentamicin for a K. pneumoniae infection, the lack of a prompt therapeutic response may indicate the need for reevaluation of antibacterial therapy.
Clinical evidence in one patient showed possible inhibition of fluorocytosine efficacy during therapy with cytarabine. This may be due to potential competitive inhibition of its uptake.
🤰 Pregnancy ▾
Pregnancy See WARNINGS . A review of the literature has shown 32 reported cases where cytarabine was given during pregnancy, either alone or in combination with other cytotoxic agents. Eighteen normal infants were delivered.
Four of these had first trimester exposure. Five infants were premature or of low birth weight. Twelve of the 18 normal infants were followed up at ages ranging from six weeks to seven years, and showed no abnormalities.
One apparently normal infant died at 90 days of gastroenteritis. Two cases of congenital abnormalities have been reported, one with upper and lower distal limb defects, and the other with extremity and ear deformities. Both of these cases had first trimester exposure.
There were seven infants with various problems in the neonatal period, including pancytopenia; transient depression of the WBC, hematocrit or platelets; electrolyte abnormalities; transient eosinophilia; and one case of increased IgM levels and hyperpyrexia possibly due to sepsis. Six of the seven infants were also premature. The child with pancytopenia died at 21 days of sepsis.
Therapeutic abortions were done in five cases. Four fetuses were grossly normal, but one had an enlarged spleen and another showed Trisomy C chromosome abnormality in the chorionic tissue. Because of the potential for abnormalities with cytotoxic therapy, particularly during the first trimester, a patient who is or who may become pregnant while on cytarabine should be apprised of the potential risk to the fetus and the advisability of pregnancy continuation.
There is a definite, but considerably reduced risk if therapy is initiated during the second or third trimester. Although normal infants have been delivered to patients treated in all three trimesters of pregnancy, follow-up of such infants would be advisable.
🧒 Pediatric Use ▾
Pediatric use See INDICATIONS AND USAGE .
🆘 Overdosage ▾
OVERDOSAGE There is no antidote for cytarabine overdosage. Doses of 4.5 g/m 2 by intravenous infusion over 1 hour every 12 hours for 12 doses has caused an unacceptable increase in irreversible CNS toxicity and death. Single doses as high as 3 g/m 2 have been administered by rapid intravenous infusion without apparent toxicity.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Cell Culture Studies Cytarabine is cytotoxic to a wide variety of proliferating mammalian cells in culture. It exhibits cell phase specificity, primarily killing cells undergoing DNA synthesis (S-phase) and under certain conditions blocking the progression of cells from the G 1 phase to the S-phase. Although the mechanism of action is not completely understood, it appears that cytarabine acts through the inhibition of DNA polymerase.
A limited, but significant, incorporation of cytarabine into both DNA and RNA has also been reported. Extensive chromosomal damage, including chromatoid breaks, have been produced by cytarabine and malignant transformation of rodent cells in culture has been reported. Deoxycytidine prevents or delays (but does not reverse) the cytotoxic activity.
Cellular Resistance and Sensitivity Cytarabine is metabolized by deoxycytidine kinase and other nucleotide kinases to the nucleotide triphosphate, an effective inhibitor of DNA polymerase; it is inactivated by a pyrimidine nucleoside deaminase which converts it to the nontoxic uracil derivative. It appears that the balance of kinase and deaminase levels may be an important factor in determining sensitivity or resistance of the cell to cytarabine. Human Pharmacology Cytarabine is rapidly metabolized and is not effective orally; less than 20 percent of the orally administered dose is absorbed from the gastrointestinal tract.
Following rapid intravenous injection of cytarabine, labeled with tritium, the disappearance from plasma is biphasic. There is an initial distributive phase with a half-life of about 10 minutes, followed by a second elimination phase with a half-life of about 1 to 3 hours. After the distributive phase, more than 80 percent of plasma radioactivity can be accounted for by the inactive metabolite 1-β-D-arabinofuranosyluracil (ara-U).
Within 24 hours about 80 percent of the administered radioactivity can be recovered in the urine, approximately 90 percent of which is excreted as ara-U. Relatively constant plasma levels can be achieved by continuous intravenous infusion. After subcutaneous or intramuscular administration of cytarabine labeled with tritium, peak-plasma levels of radioactivity are achieved about 20 to 60 minutes after injection and are considerably lower than those after intravenous administration.
Cerebrospinal fluid levels of cytarabine are low in comparison to plasma levels after single intravenous injection. However, in one patient in whom cerebrospinal levels were examined after 2 hours of constant intravenous infusion, levels approached 40 percent of the steady state plasma level. With intrathecal administration, levels of cytarabine in the cerebrospinal fluid declined with a first order half-life of about 2 hours.
Because cerebrospinal fluid levels of deaminase are low, little conversion to ara-U was observed. Immunosuppressive Action Cytarabine is capable of obliterating immune responses in man during administration with little or no accompanying toxicity. Suppression of antibody responses to E. coli-VI antigen and tetanus toxoid have been demonstrated.
This suppression was obtained during both primary and secondary antibody responses. Cytarabine also suppressed the development of cell-mediated responses such as delayed hypersensitivity skin reaction to dinitrochlorobenzene. However, it had no effect on already established delayed hypersensitivity reactions.
Following 5-day courses of intensive therapy with cytarabine, the immune response was suppressed, as indicated by the following parameters: macrophage ingress into skin windows; circulating antibody response following primary antigenic stimulation; lymphocyte blastogenesis with phytohemagglutinin. A few days after termination of therapy there was a rapid return to normal.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cytarabine Injection is available in a Pharmacy Bulk Package supplied as follows: NDC Cytarabine Injection (20 mg per mL) Package Factor 71288- 168 -50 1,000 mg per 50 mL Pharmacy Bulk Bottle 1 bottle per carton Storage Conditions Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° and 30°C (59° and 86°F). [See USP Controlled Room Temperature.] Protect from light. Retain in carton until time of use. Isotonic Solution Sterile, Nonpyrogenic, Preservative-free.
The container closure is not made with natural rubber latex.
📦 Storage and Handling ▾
Storage Conditions Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° and 30°C (59° and 86°F). [See USP Controlled Room Temperature.] Protect from light. Retain in carton until time of use. Isotonic Solution Sterile, Nonpyrogenic, Preservative-free. The container closure is not made with natural rubber latex.
📋 Description ▾
DESCRIPTION Cytarabine Injection, an antineoplastic, is a sterile isotonic solution for intravenous and subcutaneous use, which contains no preservative and is available in 20 mg per mL (1,000 mg per 50 mL) Pharmacy Bulk Package. A Pharmacy Bulk Package is a container of a sterile preparation for parenteral use that contains many single doses. The contents are intended for use in a pharmacy admixture program and are restricted to the preparation of admixtures for intravenous infusion.
Each mL contains 20 mg Cytarabine, USP and the following inactive ingredients: sodium chloride 0.68% and Water for Injection q.s. When necessary, the pH is adjusted with hydrochloric acid and/or sodium hydroxide to a target pH of 7.4. Each bottle contains approximately 5.82 mEq sodium.
Cytarabine is chemically 4-amino-1-β-D-arabinofuranosyl-2(1H)-pyrimidinone. The structural formula is: Cytarabine is an odorless, white to off-white, crystalline powder which is freely soluble in water and slightly soluble in alcohol and in chloroform. structural formula
💬 Information for Patients ▾
Information for patient Not applicable.
⚠️ Precautions ▾
PRECAUTIONS General Precautions Patients receiving cytarabine must be monitored closely. Frequent platelet and leukocyte counts and bone marrow examinations are mandatory. Consider suspending or modifying therapy when drug-induced marrow depression has resulted in a platelet count under 50,000 or a polymorphonuclear granulocyte count under 1,000/mm 3 .
Counts of formed elements in the peripheral blood may continue to fall after the drug is stopped and reach lowest values after drug-free intervals of 12 to 24 days. When indicated, restart therapy when definite signs of marrow recovery appear (on successive bone marrow studies). Patients whose drug is withheld until “normal” peripheral blood values are attained may escape from control.
When large intravenous doses are given quickly, patients are frequently nauseated and may vomit for several hours post-injection. This problem tends to be less severe when the drug is infused. The human liver apparently detoxifies a substantial fraction of an administered dose.
In particular, patients with renal or hepatic function impairment may have a higher likelihood of CNS toxicity after high-dose cytarabine treatment. Use the drug with caution and possibly at reduced dose in patients whose liver or kidney function is poor. Periodic checks of bone marrow, liver and kidney functions should be performed in patients receiving cytarabine.
Like other cytotoxic drugs, cytarabine may induce hyperuricemia secondary to rapid lysis of neoplastic cells. The clinician should monitor the patient's blood uric acid level and be prepared to use such supportive and pharmacologic measures as might be necessary to control this problem. Acute pancreatitis has been reported to occur in a patient receiving cytarabine by continuous infusion and in patients being treated with cytarabine who have had prior treatment with L-asparaginase.
Information for patient Not applicable. Laboratory tests See General Precautions . Drug Interactions Reversible decreases in steady-state plasma digoxin concentrations and renal glycoside excretion were observed in patients receiving beta-acetyldigoxin and chemotherapy regimens containing cyclophosphamide, vincristine and prednisone with or without cytarabine or procarbazine.
Steady-state plasma digitoxin concentrations did not appear to change. Therefore, monitoring of plasma digoxin levels may be indicated in patients receiving similar combination chemotherapy regimens. The utilization of digitoxin for such patients may be considered as an alternative.
An in vitro interaction study between gentamicin and cytarabine showed a cytarabine related antagonism for the susceptibility of K. pneumoniae strains. This study suggests that in patients on cytarabine being treated with gentamicin for a K. pneumoniae infection, the lack of a prompt therapeutic response may indicate the need for reevaluation of antibacterial therapy. Clinical evidence in one patient showed possible inhibition of fluorocytosine efficacy during therapy with cytarabine.
This may be due to potential competitive inhibition of its uptake. Carcinogenesis, mutagenesis, impairment of fertility Extensive chromosomal damage, including chromatoid breaks have been produced by cytarabine and malignant transformation of rodent cells in culture has been reported. Pregnancy See WARNINGS .
A review of the literature has shown 32 reported cases where cytarabine was given during pregnancy, either alone or in combination with other cytotoxic agents. Eighteen normal infants were delivered. Four of these had first trimester exposure.
Five infants were premature or of low birth weight. Twelve of the 18 normal infants were followed up at ages ranging from six weeks to seven years, and showed no abnormalities. One apparently normal infant died at 90 days of gastroenteritis.
Two cases of congenital abnormalities have been reported, one with upper and lower distal limb defects, and the other with extremity and ear deformities. Both of these cas… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing mothers It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in nursing infants from cytarabine, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, mutagenesis, impairment of fertility Extensive chromosomal damage, including chromatoid breaks have been produced by cytarabine and malignant transformation of rodent cells in culture has been reported.
📚 References ▾
REFERENCES Recommendations for the Safe handling of Parenteral Antineoplastic Drugs, NIH Publications No. 83-2621. For sale by the Superintendent of Documents, U.S.
Government Printing Office, Washington, D.C. 20402. AMA Council Report, Guidelines for Handling Parenteral Antineoplastics, JAMA, 1985; 2.53 (11): 1590-1592.
National Study Commission on Cytotoxic Exposure - Recommendations for Handling Cytotoxic Agents. Available from Louis P. Jeffrey, ScD., Chairman, National Study Commission on Cytotoxic Exposure, Massachusetts College of Pharmacy and Allied Health Sciences, 179 Longwood Avenue, Boston, Massachusetts 02115.
Clinical Oncological Society of Australia, Guidelines and Recommendations for Safe handling of Antineoplastic Agents. Med J Australia, 1983; 1:426-428. Jones RB, et al: Safe Handling of Chemotherapeutic Agents: A Report from the Mount Sinai Medical Center.
CA-A Cancer Journal of Clinicians, 1983; (Sept/Oct) 258-263. American Society of Hospital Pharmacists Technical Assistance Bulletin on Handling Cytotoxic and Hazardous Drugs. Am J.
Hosp. Pharm, 1990; 47:1033-1049. Controlling Occupational Exposure to Hazardous Drugs.
(OSHA Work Practice Guidelines), Am J. Health- Syst Pharm, 1996; 53: 1669-1685. meitheal ® Mfd. for Meitheal Pharmaceuticals Chicago, IL 60631 (USA) ©2021 Meitheal Pharmaceuticals Inc. Mfd. by Kindos Pharmaceuticals Co., Ltd.
Chengdu, China 611731 Revised: August 2021
📄 Package Label / Principal Display Panel ▾
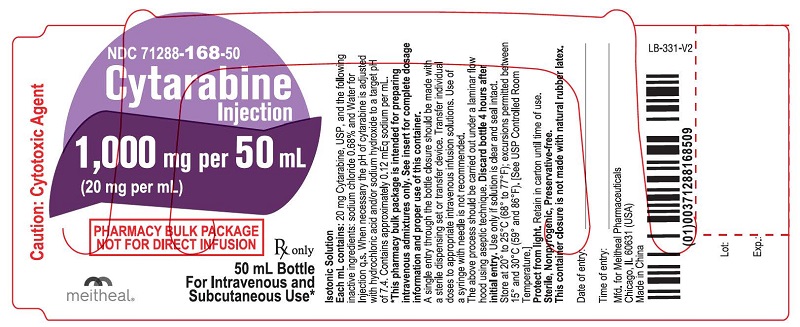
PRINCIPAL DISPLAY PANEL – Cytarabine Injection, 50 mL Bottle Label Caution: Cytotoxic Agent NDC 71288- 168 -50 Cytarabine Injection 1,000 mg per 50 mL (20 mg per mL) PHARMACY BULK PACKAGE NOT FOR DIRECT INFUSION Rx only 50 mL Bottle For Intravenous and Subcutaneous Use* 50 mL bottle label
PRINCIPAL DISPLAY PANEL – Cytarabine Injection, 50 mL Carton NDC 71288- 168 -50 1 x 50 mL Bottle Rx only Cytarabine Injection 1,000 mg per 50 mL (20 mg per mL) PHARMACY BULK PACKAGE NOT FOR DIRECT INFUSION For Intravenous and Subcutaneous Use* Caution: Cytotoxic Agent 50 mL carton
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |