
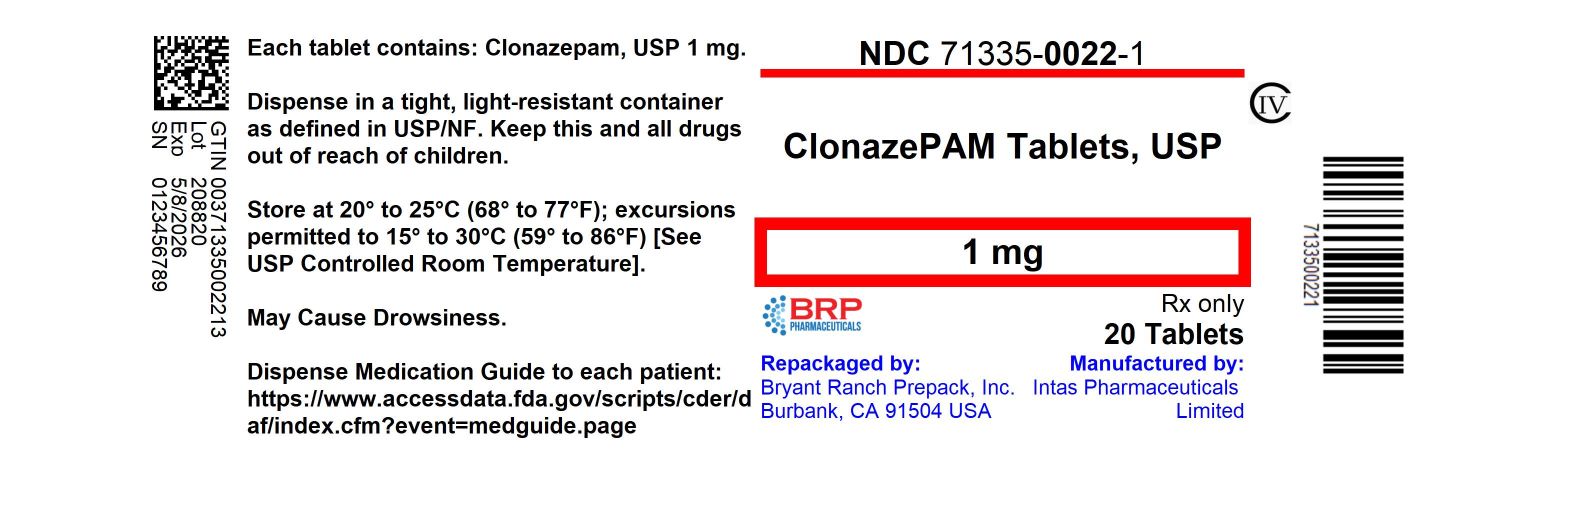
Clonazepam 1 mg Tablet, 56-count
Other active recalls for Clonazepam (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Clonazepam is used for two main things: certain types of seizures and panic disorder. On the seizure side, it's approved for Lennox-Gastaut syndrome, akinetic seizures, myoclonic s...
- It's a fair concern, and the honest answer is yes — clonazepam can cause physical dependence with regular use, and there is a real risk of misuse and addiction. This doesn't mean e...
- Is it true clonazepam is addictive? Should I be worried?
- Drowsiness is the big one — about half of people taking it for seizures experience it. Problems with balance or coordination (called ataxia) are also common. You might also notice...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Clonazepam — tap one for details:
Clonazepam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.0628 | $3.52 / 56 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clonazepam 1 mg 00093-3212-01 | Teva | 100 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 00904-7728-61 | Major | 100 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 16729-0137-00 | Accord | 100 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 43547-0407-10 | Solco | 100 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 50268-0174-15 | AvPAK | 50 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 59651-0723-01 | Aurobindo | 100 tablets | $0.025 | — | Availability likely | — |
| Clonazepam 1 mg 60687-0872-01 | American | 100 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 62135-0770-90 | Chartwell | 90 tablets | $0.025 | AB | Availability likely | — |
| Clonazepam 1 mg 72603-0308-01 | Northstar | 100 tablets | $0.025 | — | Availability likely | — |
| Clonazepam 1 mg 72888-0153-00 | Advagen | 1000 tablets | $0.025 | — | Availability likely | — |
| Klonopin 1 mg 61269-0610-10 | H2-Pharma, | 100 tablets | $3.050 | AB | Availability likely | — |
| Clonazepam 1 mg 43063-0794-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 50090-2022-00 | A-S | 60 tablets | — | AB | Discontinued | — |
| Clonazepam 1 mg 55154-4319-00 | Cardinal | 100 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 58118-0153-08 | Clinical | 30 tablets | — | — | FDA listed | — |
| Clonazepam 1 mg 60760-0300-30 | St | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 63187-0888-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 63629-1116-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 63629-1204-01 | Bryant | 500 tablets | — | AB | Discontinued | — |
| Clonazepam 1 mg 63629-1205-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 63629-8988-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 67046-0493-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 67046-0794-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 68071-5247-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 68788-8401-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 68788-8473-02 | Preferred | 20 tablets | — | — | FDA listed | — |
| Clonazepam 1 mg 70518-1521-01 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 70518-2334-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 70518-2533-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Clonazepam 1 mg 70518-3144-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 70518-4074-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 71205-0529-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mgthis 71335-0022-09 | Bryant | 56 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 71335-1843-00 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 71335-2414-00 | Bryant | 100 tablets | — | — | FDA listed | — |
| Clonazepam 1 mg 71610-0040-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 71610-0771-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 71610-0852-12 | Aphena | 12 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 72189-0475-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 72789-0314-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 80425-0135-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 80425-0357-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 82804-0272-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Clonazepam 1 mg 87441-0022-01 | Unit | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0022-00 | 100 TABLET in 1 BOTTLE (71335-0022-0) | 2021-12-27 | Active |
| 71335-0022-01 | 20 TABLET in 1 BOTTLE (71335-0022-1) | 2021-12-27 | Active |
| 71335-0022-02 | 30 TABLET in 1 BOTTLE (71335-0022-2) | 2018-02-13 | Active |
| 71335-0022-03 | 60 TABLET in 1 BOTTLE (71335-0022-3) | 2018-03-06 | Active |
| 71335-0022-04 | 90 TABLET in 1 BOTTLE (71335-0022-4) | 2018-02-13 | Active |
| 71335-0022-05 | 120 TABLET in 1 BOTTLE (71335-0022-5) | 2018-04-23 | Active |
| 71335-0022-06 | 180 TABLET in 1 BOTTLE (71335-0022-6) | 2021-12-27 | Active |
| 71335-0022-07 | 84 TABLET in 1 BOTTLE (71335-0022-7) | 2018-02-14 | Active |
| 71335-0022-08 | 28 TABLET in 1 BOTTLE (71335-0022-8) | 2018-03-28 | Active |
| 71335-0022-09 You're viewing this | 56 TABLET in 1 BOTTLE (71335-0022-9) | 2018-02-15 | Active |
You're viewing one of 10 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0022-09?
What is the difference between NDC 71335-0022-09 and NDC 71335-0022-01?
What NDC number is used to bill for this package of Clonazepam 1 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of these drugs for patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation (see WARNINGS and PRECAUTIONS ). The use of benzodiazepines, including clonazepam tablets, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes.
Before prescribing clonazepam tablets and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (see WARNINGS ). The continued use of benzodiazepines, including clonazepam tablets, may lead to clinically significant physical dependence. The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose.
Abrupt discontinuation or rapid dosage reduction of clonazepam tablets after continued use may precipitate acute withdrawal reactions, which can be life-threatening. To reduce the risk of withdrawal reactions, use a gradual taper to discontinue clonazepam tablets or reduce the dosage (see DOSAGE AND ADMINISTRATION and WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Seizure Disorders: Clonazepam tablets are useful alone or as an adjunct in the treatment of the Lennox-Gastaut syndrome (petit mal variant), akinetic, and myoclonic seizures. In patients with absence seizures (petit mal) who have failed to respond to succinimides, clonazepam tablets may be useful. Some loss of effect may occur during the course of clonazepam treatment (see PRECAUTIONS : Loss of Effect ).
Panic Disorder: Clonazepam tablets are indicated for the treatment of panic disorder, with or without agoraphobia, as defined in DSM-V. Panic disorder is characterized by the occurrence of unexpected panic attacks and associated concern about having additional attacks, worry about the implications or consequences of the attacks, and/or a significant change in behavior related to the attacks. The efficacy of clonazepam tablets was established in two 6- to 9-week trials in panic disorder patients whose diagnoses corresponded to the DSM-IIIR category of panic disorder (see CLINICAL PHARMACOLOGY: Clinical Trials) .
Panic disorder (DSM-V) is characterized by recurrent unexpected panic attacks, i.e., a discrete period of intense fear or discomfort in which four (or more) of the following symptoms develop abruptly and reach a peak within 10 minutes: (1) palpitations, pounding heart or accelerated heart rate; (2) sweating; (3) trembling or shaking; (4) sensations of shortness of breath or smothering; (5) feeling of choking; (6) chest pain or discomfort; (7) nausea or abdominal distress; (8) feeling dizzy, unsteady, lightheaded or faint; (9) derealization (feelings of unreality) or depersonalization (being detached from oneself); (10) fear of losing control; (11) fear of dying; (12) paresthesias (numbness or tingling sensations); (13) chills or hot flushes.
The effectiveness of clonazepam tablets in long-term use, that is, for more than 9 weeks, has not been systematically studied in controlled clinical trials. The physician who elects to use clonazepam tablets for extended periods should periodically reevaluate the long-term usefulness of the drug for the individual patient (see DOSAGE AND ADMINISTRATION ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Clonazepam is available as a tablet. The tablets should be administered with water by swallowing the tablet whole. Seizure Disorders: The use of multiple anticonvulsants may result in an increase of CNS depressant adverse effects.
This should be considered before adding clonazepam tablets to an existing anticonvulsant regimen. Adults: The initial dose for adults with seizure disorders should not exceed 1.5 mg/day divided into three doses. Dosage may be increased in increments of 0.5 mg to 1 mg every 3 days until seizures are adequately controlled or until side effects preclude any further increase.
Maintenance dosage must be individualized for each patient depending upon response. Maximum recommended daily dose is 20 mg. Pediatric Patients: Clonazepam tablets are administered orally.
In order to minimize drowsiness, the initial dose for infants and children (up to 10 years of age or 30 kg of body weight) should be between 0.01 and 0.03 mg/kg/day but not to exceed 0.05 mg/kg/day given in two or three divided doses. Dosage should be increased by no more than 0.25 mg to 0.5 mg every third day until a daily maintenance dose of 0.1 to 0.2 mg/kg of body weight has been reached, unless seizures are controlled or side effects preclude further increase. Whenever possible, the daily dose should be divided into three equal doses.
If doses are not equally divided, the largest dose should be given before retiring. Geriatric Patients: There is no clinical trial experience with clonazepam tablets in seizure disorder patients 65 years of age and older. In general, elderly patients should be started on low doses of clonazepam tablets and observed closely (see PRECAUTIONS: Geriatric Use ).
Panic Disorder: Adults: The initial dose for adults with panic disorder is 0.25 mg twice daily. An increase to the target dose for most patients of 1 mg/day may be made after 3 days. The recommended dose of 1 mg/day is based on the results from a fixed dose study in which the optimal effect was seen at 1 mg/day.
Higher doses of 2, 3 and 4 mg/day in that study were less effective than the 1 mg/day dose and were associated with more adverse effects. Nevertheless, it is possible that some individual patients may benefit from doses of up to a maximum dose of 4 mg/day, and in those instances, the dose may be increased in increments of 0.125 mg to 0.25 mg twice daily every 3 days until panic disorder is controlled or until side effects make further increases undesired. To reduce the inconvenience of somnolence, administration of one dose at bedtime may be desirable.
Treatment should be discontinued gradually, with a decrease of 0.125 mg twice daily every 3 days, until the drug is completely withdrawn. There is no body of evidence available to answer the question of how long the patient treated with clonazepam should remain on it. Therefore, the physician who elects to use clonazepam tablets for extended periods should periodically reevaluate the long-term usefulness of the drug for the individual patient.
Pediatric Patients: There is no clinical trial experience with clonazepam tablets in panic disorder patients under 18 years of age. Geriatric Patients: There is no clinical trial experience with clonazepam tablets in panic disorder patients 65 years of age and older. In general, elderly patients should be started on low doses of clonazepam tablets and observed closely (see PRECAUTIONS: Geriatric Use ).
Discontinuation or Dosage Reduction of Clonazepam Tablets: To reduce the risk of withdrawal reactions, increased seizure frequency, and status epilepticus, use a gradual taper to discontinue clonazepam tablets or reduce the dosage. If a patient develops withdrawal reactions, consider pausing the taper or increasing the dosage to the previous tapered dosage level. Subsequently decrease the dosage more slowly (see WARNINGS: Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE: Dependence ).
⛔ Contraindications ▾
CONTRAINDICATIONS Clonazepam tablets are contraindicated in patients with the following conditions: History of sensitivity to benzodiazepines Clinical or biochemical evidence of significant liver disease Acute narrow angle glaucoma (it may be used in patients with open angle glaucoma who are receiving appropriate therapy).
⚠️ Warnings ▾
WARNINGS Risks from Concomitant Use with Opioids: Concomitant use of benzodiazepines, including clonazepam tablets, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of benzodiazepines and opioids for patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe clonazepam tablets concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. Advise both patients and caregivers about the risks of respiratory depression and sedation when clonazepam tablets are used with opioids (see PRECAUTIONS: Information for Patients and PRECAUTIONS: Drug Interactions ). Abuse, Misuse, and Addiction: The use of benzodiazepines, including clonazepam tablets, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death (see DRUG ABUSE AND DEPENDENCE: Abuse ). Before prescribing clonazepam tablets and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (e.g., using a standardized screening tool).
Use of clonazepam tablets, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of clonazepam tablets along with monitoring for signs and symptoms of abuse, misuse, and addiction. Prescribe the lowest effective dosage; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug. If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
Dependence and Withdrawal Reactions: To reduce the risk of withdrawal reactions, use a gradual taper to discontinue clonazepam tablets or reduce the dosage (a patient-specific plan should be used to taper the dose) (see DOSAGE AND ADMINISTRATION: Discontinuation or Dosage Reduction of clonazepam tablets). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines, including clonazepam tablets, may lead to clinically significant physical dependence.
Abrupt discontinuation or rapid dosage reduction of clonazepam tablets after continued use, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures) (see DRUG ABUSE AND DEPENDENCE: Dependence ). Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months (see DRUG ABUSE AND DEPENDENCE: Dependence ). Interference with Cognitive and Motor Performance: Since clonazepam tablets produces CNS depression, patients receiving this drug should be cautioned against engaging in hazardous occupations requiring mental alertness, such as operating machinery or driving a motor vehicle.
They should also be warned about the concomitant use of alcohol or other CNS-depressant drugs during clonazepam therapy (see PRECAUTIONS: Drug Interactions and PRECAUTIONS…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The adverse experiences for clonazepam tablets are provided separately for patients with seizure disorders and with panic disorder. Seizure Disorders: The most frequently occurring side effects of clonazepam tablets are referable to CNS depression. Experience in treatment of seizures has shown that drowsiness has occurred in approximately 50% of patients and ataxia in approximately 30%.
In some cases, these may diminish with time; behavior problems have been noted in approximately 25% of patients. Others, listed by system, including those identified during postapproval use of clonazepam tablets are: Cardiovascular: Palpitations Dermatologic: Hair loss, hirsutism, skin rash, ankle and facial edema Gastrointestinal: Anorexia, coated tongue, constipation, diarrhea, dry mouth, encopresis, gastritis, increased appetite, nausea, sore gums Genitourinary: Dysuria, enuresis, nocturia, urinary retention Hematopoietic: Anemia, leukopenia, thrombocytopenia, eosinophilia Hepatic: Hepatomegaly, transient elevations of serum transaminases and alkaline phosphatase Musculoskeletal: Muscle weakness, pains Miscellaneous: Dehydration, general deterioration, fever, lymphadenopathy, weight loss or gain Neurologic: Abnormal eye movements, aphonia, choreiform movements, coma, diplopia, dysarthria, dysdiadochokinesis, ‘‘glassy-eyed’’ appearance, headache, hemiparesis, hypotonia, nystagmus, respiratory depression, slurred speech, tremor, vertigo Psychiatric: Confusion, depression, amnesia, hysteria, increased libido, insomnia, psychosis (the behavior effects are more likely to occur in patients with a history of psychiatric disturbances).
The following paradoxical reactions have been observed: irritability, aggression, agitation, nervousness, hostility, anxiety, sleep disturbances, nightmares, abnormal dreams, hallucinations. Respiratory: Chest congestion, rhinorrhea, shortness of breath, hypersecretion in upper respiratory passages Panic Disorder: Adverse events during exposure to clonazepam tablets were obtained by spontaneous report and recorded by clinical investigators using terminology of their own choosing. Consequently, it is not possible to provide a meaningful estimate of the proportion of individuals experiencing adverse events without first grouping similar types of events into a smaller number of standardized event categories.
In the tables and tabulations that follow, CIGY dictionary terminology has been used to classify reported adverse events, except in certain cases in which redundant terms were collapsed into more meaningful terms, as noted below. The stated frequencies of adverse events represent the proportion of individuals who experienced, at least once, a treatment-emergent adverse event of the type listed. An event was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
Adverse Findings Observed in Short-Term, Placebo-Controlled Trials: Adverse Events Associated with Discontinuation of Treatment: Overall, the incidence of discontinuation due to adverse events was 17% in clonazepam tablets compared to 9% for placebo in the combined data of two 6- to 9-week trials. The most common events (≥ 1%) associated with discontinuation and a dropout rate twice or greater for clonazepam tablets than that of placebo included the following: Table 2 Most Common Adverse Events (≥ 1%) Associated with Discontinuation of Treatment Adverse Event Clonazepam Tablets (N = 574) Placebo (N = 294) Somnolence 7% 1% Depression 4% 1% Dizziness 1% < 1% Nervousness 1% 0% Ataxia 1% 0% Intellectual Ability Reduced 1% 0% Adverse Events Occurring at an Incidence of 1% or More among Clonazepam Tablets-Treated Patients: Table 3 enumerates the incidence, rounded to the nearest percent, of treatment-emergent adverse events that occurred during acute therapy of panic disorder from a pool of two 6- to 9-week trials.
Events reported in 1% or more of patients treated with clon…
🔄 Drug Interactions ▾
Drug Interactions: Effect of Concomitant Use of Benzodiazepines and Opioids: The concomitant use of benzodiazepines and opioids increases the risk of respiratory depression because of actions at different receptor sites in the CNS that control respiration. Benzodiazepines interact at GABAA sites, and opioids interact primarily at mu receptors. When benzodiazepines and opioids are combined, the potential for benzodiazepines to significantly worsen opioid-related respiratory depression exists.
Limit dosage and duration of concomitant use of benzodiazepines and opioids, and follow patients closely for respiratory depression and sedation. Effect of Clonazepam on the Pharmacokinetics of Other Drugs: Clonazepam does not appear to alter the pharmacokinetics of carbamazepine or phenobarbital. Clonazepam has the potential to influence concentrations of phenytoin.
Monitoring of phenytoin concentration is recommended when clonazepam is co-administrated with phenytoin. The effect of clonazepam on the metabolism of other drugs has not been investigated. Effect of Other Drugs on the Pharmacokinetics of Clonazepam: Literature reports suggest that ranitidine, an agent that decreases stomach acidity, does not greatly alter clonazepam pharmacokinetics.
In a study in which the 2 mg clonazepam orally disintegrating tablet was administered with and without propantheline (an anticholinergic agent with multiple effects on the GI tract) to healthy volunteers, the AUC of clonazepam was 10% lower and the C max of clonazepam was 20% lower when the orally disintegrating tablet was given with propantheline compared to when it was given alone. The selective serotonin reuptake inhibitors sertraline (weak CYP3A4 inducer) and fluoxetine (CYP2D6 inhibitor), and the anti-epileptic drug felbamate (CYP2C19 inhibitor and CYP3A4 inducer) do not affect the pharmacokinetics of clonazepam.
Cytochrome P450 inducers, such as phenytoin, carbamazepine, lamotrigine, and phenobarbital induce clonazepam metabolism, causing an approximately 38% decrease in plasma clonazepam levels. Although clinical studies have not been performed, based on the involvement of the cytochrome P-450 3A family in clonazepam metabolism, inhibitors of this enzyme system, notably oral antifungal agents (e.g., fluconazole), should be used cautiously in patients receiving clonazepam because they may impair the metabolism of clonazepam leading to exaggerated concentrations and effects.
Pharmacodynamic Interactions: The CNS-depressant action of the benzodiazepine class of drugs may be potentiated by alcohol, narcotics, barbiturates, nonbarbiturate hypnotics, antianxiety agents, the phenothiazines, thioxanthene and butyrophenone classes of antipsychotic agents, monoamine oxidase inhibitors and the tricyclic antidepressants, and by other anticonvulsant drugs.
🤰 Pregnancy ▾
Pregnancy: Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as clonazepam tablets, during pregnancy. Healthcare providers are encouraged to recommend that pregnant women taking clonazepam tablets enroll in the NAAED Pregnancy Registry by calling 1-888-233-2334 or online at http://www.aedpregnancyregistry.org/. Risk Summary Neonates born to mothers using benzodiazepines late in pregnancy have been reported to experience symptoms of sedation and/or neonatal withdrawal (see WARNINGS: Neonatal Sedation and Withdrawal Syndrome, and Clinical Considerations ).
Available data from published observational studies of pregnant women exposed to benzodiazepines do not report a clear association with benzodiazepines and major birth defects (see Data ). Administration of clonazepam to pregnant rabbits during the period of organogenesis resulted in developmental toxicity, including increased incidences of fetal malformations, at doses similar to or below therapeutic doses in patients (see Animal Data). Data for other benzodiazepines suggest the possibility of long-term effects on neurobehavioral and immunological function in animals following prenatal exposure to benzodiazepines at clinically relevant doses.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated risk of major birth defects and of miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Fetal/Neonatal Adverse Reactions Benzodiazepines cross the placenta and may produce respiratory depression, hypotonia and sedation in neonates. Monitor neonates exposed to clonazepam tablets during pregnancy or labor for signs of sedation, respiratory depression, hypotonia, and feeding problems. Monitor neonates exposed to clonazepam tablets during pregnancy for signs of withdrawal.
Manage these neonates accordingly (see WARNINGS: Neonatal Sedation and Withdrawal Syndrome ). Data Human Data Published data from observational studies on the use of benzodiazepines during pregnancy do not report a clear association with benzodiazepines and major birth defects. Although early studies reported an increased risk of congenital malformations with diazepam and chlordiazepoxide, there was no consistent pattern noted.
In addition, the majority of more recent case-control and cohort studies of benzodiazepine use during pregnancy, which were adjusted for confounding exposures to alcohol, tobacco and other medications, have not confirmed these findings. Animal Data In three studies in which clonazepam was administered orally to pregnant rabbits at doses of 0.2, 1, 5, or 10 mg/kg/day during the period of organogenesis, a similar pattern of malformations (cleft palate, open eyelid, fused sternebrae and limb defects) was observed at all doses, in a low, non-dose-related incidence.
The lowest dose tested is less than the maximum recommended human dose (MRHD) of 20 mg/day for seizure disorders and similar to the MRHD of 4 mg/day for panic disorder, on a mg/m 2 basis. Reductions in maternal weight gain occurred at doses of 5 mg/kg/day or greater and reduction in embryofetal growth occurred in one study at a dose of 10 mg/kg/day. No adverse maternal or embryofetal effects were observed in mice or rats following oral administration of clonazepam during organogenesis of doses up to 15 or 40 mg/kg/day, respectively (4 and 20 times the MRHD of 20 mg/day for seizure disorders and 20 and 100 times the MRHD of 4 mg/day for panic disorder, respectively, on a mg/m 2 basis).
Data for other benzodiazepines suggest the possibility of adverse developmental effects (long-term effects on neurobehavioral and immunological function) in animals following prenatal exposure to benzodiazepines.
🧒 Pediatric Use ▾
Pediatric Use: Because of the possibility that adverse effects on physical or mental development could become apparent only after many years, a benefit-risk consideration of the long-term use of clonazepam tablets is important in pediatric patients being treated for seizure disorder (see INDICATIONS AND USAGE and DOSAGE AND ADMINISTRATION ). Safety and effectiveness in pediatric patients with panic disorder below the age of 18 have not been established.
🧓 Geriatric Use ▾
Geriatric Use: Clinical studies of clonazepam tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
Because clonazepam undergoes hepatic metabolism, it is possible that liver disease will impair clonazepam elimination. Metabolites of clonazepam tablets are excreted by the kidneys; to avoid their excess accumulation, caution should be exercised in the administration of the drug to patients with impaired renal function. Because elderly patients are more likely to have decreased hepatic and/or renal function, care should be taken in dose selection, and it may be useful to assess hepatic and/or renal function at the time of dose selection.
Sedating drugs may cause confusion and over-sedation in the elderly; elderly patients generally should be started on low doses of clonazepam tablets and observed closely.
🆘 Overdosage ▾
OVERDOSAGE Overdosage of benzodiazepines is characterized by central nervous system depression ranging from drowsiness to coma. In mild to moderate cases, symptoms can include drowsiness, confusion, dysarthria, lethargy, hypnotic state, diminished reflexes, ataxia, and hypotonia. Rarely, paradoxical or disinhibitory reactions (including agitation, irritability, impulsivity, violent behavior, confusion, restlessness, excitement, and talkativeness) may occur.
In severe overdosage cases, patients may develop respiratory depression and coma. Overdosage of benzodiazepines in combination with other CNS depressants (including alcohol and opioids) may be fatal (see WARNINGS: Abuse, Misuse, and Addiction ). Markedly abnormal (lowered or elevated) blood pressure, heart rate, or respiratory rate raise the concern that additional drugs and/or alcohol are involved in the overdosage.
In managing benzodiazepine overdosage, employ general supportive measures, including intravenous fluids and airway maintenance. Flumazenil, a specific benzodiazepine receptor antagonist indicated for the complete or partial reversal of the sedative effects of benzodiazepines in the management of benzodiazepine overdosage, can lead to withdrawal and adverse reactions, including seizures, particularly in the context of mixed overdosage with drugs that increase seizure risk (e.g., tricyclic and tetracyclic antidepressants) and in patients with long-term benzodiazepine use and physical dependency.
The risk of withdrawal seizures with flumazenil use may be increased in patients with epilepsy. Flumazenil is contraindicated in patients who have received a benzodiazepine for control of a potentially life-threatening condition (e.g., status epilepticus). If the decision is made to use flumazenil, it should be used as an adjunct to, not as a substitute for, supportive management of benzodiazepine overdosage.
See the flumazenil injection Prescribing Information. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics: The precise mechanism by which clonazepam exerts its antiseizure and antipanic effects is unknown, although it is believed to be related to its ability to enhance the activity of gamma aminobutyric acid (GABA), the major inhibitory neurotransmitter in the central nervous system. Pharmacokinetics: Clonazepam is rapidly and completely absorbed after oral administration. The absolute bioavailability of clonazepam is about 90%.
Maximum plasma concentrations of clonazepam are reached within 1 to 4 hours after oral administration. Clonazepam is approximately 85% bound to plasma proteins. Clonazepam is highly metabolized, with less than 2% unchanged clonazepam being excreted in the urine.
Biotransformation occurs mainly by reduction of the 7-nitro group to the 4-amino derivative. This derivative can be acetylated, hydroxylated and glucuronidated. Cytochrome P-450 including CYP3A, may play an important role in clonazepam reduction and oxidation.
The elimination half-life of clonazepam is typically 30 to 40 hours. Clonazepam pharmacokinetics are dose-independent throughout the dosing range. There is no evidence that clonazepam induces its own metabolism or that of other drugs in humans.
Pharmacokinetics in Demographic Subpopulations and in Disease States: Controlled studies examining the influence of gender and age on clonazepam pharmacokinetics have not been conducted, nor have the effects of renal or liver disease on clonazepam pharmacokinetics been studied. Because clonazepam undergoes hepatic metabolism, it is possible that liver disease will impair clonazepam elimination. Thus, caution should be exercised when administering clonazepam to these patients (see CONTRAINDICATIONS ).
In children, clearance values of 0.42 ± 0.32 mL/min/kg (ages 2 to 18 years) and 0.88 ± 0.4 mL/min/kg (ages 7 to 12 years) were reported; these values decreased with increasing body weight. Ketogenic diet in children does not affect clonazepam concentrations. Clinical Trials: Panic Disorder: The effectiveness of clonazepam in the treatment of panic disorder was demonstrated in two double-blind, placebo-controlled studies of adult outpatients who had a primary diagnosis of panic disorder (DSM-IIIR) with or without agoraphobia.
In these studies, clonazepam was shown to be significantly more effective than placebo in treating panic disorder on change from baseline in panic attack frequency, the Clinician’s Global Impression Severity of Illness Score and the Clinician’s Global Impression Improvement Score. Study 1 was a 9-week, fixed-dose study involving clonazepam doses of 0.5, 1, 2, 3 or 4 mg/day or placebo. This study was conducted in four phases: a 1-week placebo lead-in, a 3-week upward titration, a 6-week fixed dose, and a 7-week discontinuance phase.
A significant difference from placebo was observed consistently only for the 1 mg/day group. The difference between the 1 mg dose group and placebo in reduction from baseline in the number of full panic attacks was approximately 1 panic attack per week. At endpoint, 74% of patients receiving clonazepam 1 mg/day were free of full panic attacks, compared to 56% of placebo-treated patients.
Study 2 was a 6-week, flexible-dose study involving clonazepam in a dose range of 0.5 to 4 mg/day or placebo. This study was conducted in three phases: a 1-week placebo lead-in, a 6-week optimal-dose, and a 6-week discontinuance phase. The mean clonazepam dose during the optimal dosing period was 2.3 mg/day.
The difference between clonazepam and placebo in reduction from baseline in the number of full panic attacks was approximately 1 panic attack per week. At endpoint, 62% of patients receiving clonazepam were free of full panic attacks, compared to 37% of placebo-treated patients. Subgroup analyses did not indicate that there were any differences in treatment outcomes as a function of race or gender.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED NDC: 71335-0022-1: 20 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-2: 30 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-3: 60 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-4: 90 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-5: 120 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-6: 180 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-7: 84 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-8: 28 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-9: 56 Tablets in a BOTTLE, PLASTIC NDC: 71335-0022-0: 100 Tablets in a BOTTLE, PLASTIC
📋 Description ▾
DESCRIPTION Clonazepam tablets USP, a benzodiazepine, is available as scored tablets debossed with “1” and “2” containing 0.5 mg of clonazepam and unscored tablets debossed with “C 1” on 1 mg tablets and “C 2” on 2 mg tablets containing 1 mg or 2 mg of clonazepam. Each tablet contains anhydrous lactose, lactose monohydrate, magnesium stearate, microcrystalline cellulose and starch (corn), with the following colorants: 0.5 mg-FD&C Yellow No. 6 Lake and 1 mg- FD&C Blue No.2 Lake.
Chemically, clonazepam is 5-(2-chlorophenyl)-1,3-dihydro-7-nitro-2 H -1,4-benzodiazepin-2-one. It is a light yellow crystalline powder. It has a molecular weight of 315.72 and the following structural formula:
💬 Medication Guide ▾
MEDICATION GUIDE Clonazepam Tablets USP (kloe-NA-za-pam) for oral use This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 10/2023 What is the most important information I should know about Clonazepam tablets?
Clonazepam tablets are a benzodiazepine medicine. Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system (CNS) depressants (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma, and death. Get emergency help right away if any of the following happens: shallow or slowed breathing breathing stops (which may lead to the heart stopping) excessive sleepiness (sedation) Do not drive or operate heavy machinery until you know how taking clonazepam tablets and opioids affects you.
Risk of abuse, misuse, and addiction. There is a risk of abuse, misuse, and addiction with benzodiazepines, including clonazepam tablets, which can lead to overdose and serious side effects including coma and death. Serious side effects including coma and death have happened in people who have abused or misused benzodiazepines, including clonazepam tablets.
These serious side effects may also include delirium, paranoia, suicidal thoughts or actions, seizures, and difficulty breathing. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these serious side effects. You can develop an addiction even if you take clonazepam tablets as prescribed by your healthcare provider.
Take clonazepam tablets exactly as your healthcare provider prescribed. Do not share your clonazepam tablets with other people. Keep clonazepam tablets in a safe place and away from children.
Physical dependence and withdrawal reactions. Clonazepam tablets can cause physical dependence and withdrawal reactions. Do not suddenly stop taking clonazepam tablets.
Stopping clonazepam tablets suddenly can cause serious and life-threatening side effects, including, unusual movements, responses, or expressions, seizures, sudden and severe mental or nervous system changes, depression, seeing or hearing things that others do not see or hear, an extreme increase in activity or talking, losing touch with reality, and suicidal thoughts or actions. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these symptoms. Some people who suddenly stop benzodiazepines have symptoms that can last for several weeks to more than 12 months, including, anxiety, trouble remembering, learning, or concentrating, depression, problems sleeping, feeling like insects are crawling under your skin, weakness, shaking, muscle twitching, burning or prickling feeling in your hands, arms, legs or feet, and ringing in your ears.
Physical dependence is not the same as drug addiction. Your healthcare provider can tell you more about the differences between physical dependence and drug addiction. Do not take more clonazepam tablets than prescribed or take clonazepam tablets for longer than prescribed.
Clonazepam tablets can make you sleepy or dizzy and can slow your thinking and motor skills. This may get better over time. Do not drive, operate heavy machinery, or do other dangerous activities until you know how clonazepam tablets affect you.
Clonazepam tablets may cause problems with your coordination, especially when you are walking or picking things up. Do not drink alcohol or take other drugs that may make you sleepy or dizzy while taking clonazepam tablets until you talk to your healthcare provider. When taken with alcohol or drugs that cause sleepiness or dizziness, clonazepam tablets may make your sleepiness or dizziness worse.
Like other antiepileptic medicines, clonazepam tablets may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about…