
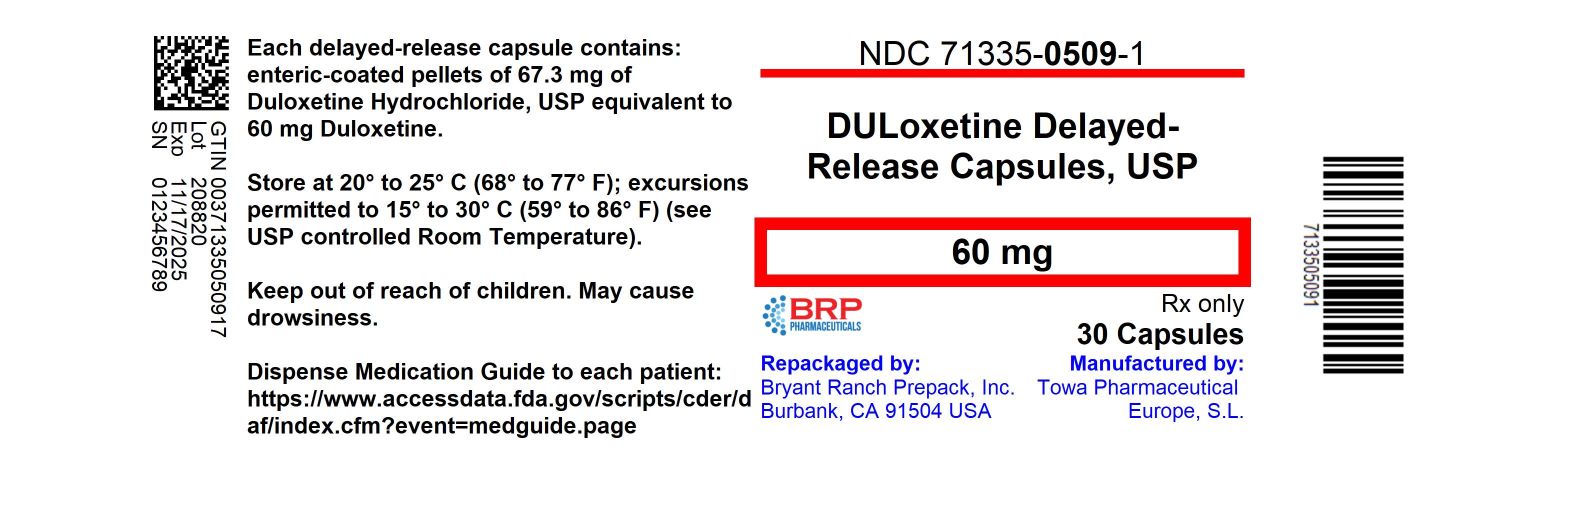
Duloxetine Delayed-Release DULOXETINE HYDROCHLORIDE 60 mg Capsule, Delayed Release Pellets, 60-count
Other active recalls for Duloxetine Hydrochloride (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin and Norepinephrine Reuptake Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- You're right to ask — duloxetine does a lot more than treat depression. It's also approved for generalized anxiety disorder, diabetic nerve pain, fibromyalgia, and chronic musculos...
- What is duloxetine actually used for? My doctor prescribed it but I wasn't sure it was just for depression.
- It depends on which product you have. Most duloxetine delayed-release capsules — including Cymbalta — must be swallowed whole. Crushing, chewing, or opening them damages the specia...
- Can I open the capsule or crush it if I have trouble swallowing pills?
Patient education
Supplement & herbal interactions
Duloxetine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
19 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3495 | $20.97 / 60 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Duloxetine Hydrochloride 60 mg 33342-0162-07 | Macleods | 30 capsules | $0.115 | AB | FDA listed | — |
| Duloxetine 60 mg 00228-2892-03 | Actavis | 30 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine 60 mg 27241-0099-03 | Ajanta | 30 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine 60 mg 43547-0381-03 | Solco | 30 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine Delayed-Release 60 mg 51991-0748-10 | Breckenridge | 1000 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine 60 mg 68001-0596-04 | BluePoint | 30 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine 60 mg 68180-0296-03 | Lupin | 1000 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine 60 mg 82009-0032-10 | Quallent | 1000 capsules | $0.129 | AB | Availability likely | — |
| Duloxetine 60 mg 82009-0173-10 | Quallent | 1000 capsules | $0.129 | AB | Availability likely | — |
| Cymbalta 60 mg 00002-3270-30 | Eli | 30 capsules | $8.972 | — | Discontinued | — |
| Duloxetine 60 mg 00615-8496-05 | NCS | 15 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 25000-0610-03 | MARKSANS | 30 capsules | — | — | FDA listed | — |
| Duloxetine 60 mg 31722-0170-01 | Camber | 100 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 42708-0196-30 | QPharma, | 30 capsules | — | AB | FDA listed | — |
| Duloxetine Hydrochloride 60 mg 46708-0280-10 | Alembic | 100 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 47335-0383-08 | Sun | 100 capsules | — | — | FDA listed | — |
| duloxetine 60 mg 49252-0009-10 | Inventia | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 50090-5940-00 | A-S | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 50090-6775-00 | A-S | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 50090-6893-00 | A-S | 90 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 50090-7897-00 | A-S | 90 capsules | — | AB | FDA listed | — |
| Duloxetine Hydrochloride 60 mg 50771-0203-01 | Yaopharma | 30 capsules | — | — | FDA listed | — |
| Duloxetine Delayed-Release 60 mg 51407-0819-10 | Golden | 1000 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 51655-0237-25 | Northwind | 60 capsules | — | AB | FDA listed | — |
| Duloxetine Hydrochloride 60 mg 59651-0282-30 | Aurobindo | 30 capsules | — | — | FDA listed | — |
| Duloxetine 60 mg 60760-0462-30 | St. | 30 capsules | — | AB | Discontinued | — |
| Duloxetine Hydrochloride 60 mg 62332-0280-30 | Alembic | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 63187-0666-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Duloxetine Delayed-Release 60 mg 63187-0735-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Duloxetine Delayed-Release 60 mg 63629-1992-01 | Bryant | 90 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 63629-8748-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 65841-0801-06 | Zydus | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 67046-1598-03 | Coupler | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 67877-0265-01 | Ascend | 100 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 68071-3519-03 | NuCare | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 68071-3775-09 | NuCare | 90 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 68788-4026-03 | Preferred | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 68788-7672-00 | Preferred | 6 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 68788-8623-03 | Preferred | 30 capsules | — | AB | FDA listed | — |
| duloxetine 60 mg 70247-0014-03 | Qingdao | 30 capsules | — | AB | FDA listed | — |
| Duloxetine Delayed-Release 60 mg 70518-0122-05 | REMEDYREPACK | 90 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 70518-1011-00 | REMEDYREPACK | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 70518-1244-00 | REMEDYREPACK | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 70518-2630-01 | REMEDYREPACK | 30 capsules | — | AB | Discontinued | — |
| Duloxetine 60 mg 71205-0358-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 71335-0402-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Duloxetine Delayed-Release 60 mgthis 71335-0509-03 | Bryant | 60 capsules | — | AB | Discontinued | — |
| Duloxetine 60 mg 71335-1445-01 | Bryant | 30 capsules | — | AB | Discontinued | — |
| Duloxetine 60 mg 71335-2567-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 71335-2625-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 71610-0403-60 | Aphena | 90 capsules | — | AB | FDA listed | — |
| Duloxetine Delayed-Release 60 mg 71610-0743-30 | Aphena | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 72162-1058-03 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Duloxetine Delayed-Release 60 mg 72162-1599-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| Duloxetine D/R 60 mg 72189-0608-30 | Direct_Rx | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 72789-0338-90 | PD-Rx | 90 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 76420-0623-01 | Asclemed | 100 capsules | — | AB | FDA listed | — |
| Duloxetine DR 60 mg 80425-0119-01 | Advanced | 30 capsules | — | AB | FDA listed | — |
| Duloxetine 60 mg 80425-0389-01 | Advanced | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0509-01 | 30 CAPSULE, DELAYED RELEASE PELLETS in 1 BOTTLE (71335-0509-1) | 2022-02-09 | Discontinued by firm |
| 71335-0509-02 | 28 CAPSULE, DELAYED RELEASE PELLETS in 1 BOTTLE (71335-0509-2) | 2022-02-09 | Discontinued by firm |
| 71335-0509-03 You're viewing this | 60 CAPSULE, DELAYED RELEASE PELLETS in 1 BOTTLE (71335-0509-3) | 2022-02-09 | Discontinued by firm |
| 71335-0509-04 | 90 CAPSULE, DELAYED RELEASE PELLETS in 1 BOTTLE (71335-0509-4) | 2022-02-09 | Discontinued by firm |
| 71335-0509-05 | 180 CAPSULE, DELAYED RELEASE PELLETS in 1 BOTTLE (71335-0509-5) | 2022-02-09 | Discontinued by firm |
| 71335-0509-06 | 120 CAPSULE, DELAYED RELEASE PELLETS in 1 BOTTLE (71335-0509-6) | 2022-02-09 | Discontinued by firm |
You're viewing one of 6 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0509-03?
What is the difference between NDC 71335-0509-03 and NDC 71335-0509-02?
What NDC number is used to bill for this package of Duloxetine Delayed-Release DULOXETINE HYDROCHLORIDE 60 mg Capsule, Delayed Release Pellets?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behavior in children, adolescents, and young adults in short-term studies. These studies did not show an increase in the risk of suicidal thoughts and behavior with antidepressant use in patients over age 24; there was a reduction in risk with antidepressant use in patients aged 65 and older [see Warnings and Precautions (5.1) ] . In patients of all ages who are started on antidepressant therapy, monitor closely for worsening, and for emergence of suicidal thoughts and behaviors.
Advise families and caregivers of the need for close observation and communication with the prescriber [see Warnings and Precautions (5.1) ] . WARNING: SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning. Increased risk of suicidal thinking and behavior in children, adolescents, and young adults taking antidepressants ( 5.1 ) Monitor for worsening and emergence of suicidal thoughts and behaviors ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Duloxetine delayed-release capsules is indicated for the treatment of: Major depressive disorder in adults Generalized anxiety disorder in adults and pediatric patients 7 years of age and older Diabetic peripheral neuropathic pain in adults Fibromyalgia in adults and pediatric patients 13 years of age and older Chronic musculoskeletal pain in adults Duloxetine delayed-release capsules are a serotonin and norepinephrine reuptake inhibitor (SNRI) indicated for the treatment of the following conditions: Major depressive disorder (MDD) in adults ( 1 ) Generalized anxiety disorder (GAD) in adults and pediatric patients 7 years of age and older ( 1 ) Diabetic peripheral neuropathic pain (DPNP) in adults ( 1 ) Fibromyalgia (FM) in adults and pediatric patients 13 years of age and older ( 1 ) Chronic musculoskeletal pain in adults ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Take Duloxetine delayed-release capsules once daily, with or without food. Swallow whole; do not crush, chew, or open capsule ( 2.1 ) Indication Starting Dose Target Dose Maximum Dose MDD ( 2.2 ) 40 mg/day to 60 mg/day Acute Treatment: 40 mg/day (20 mg twice daily) to 60 mg/day (once daily or as 30 mg twice daily); Maintenance Treatment: 60 mg/day 120 mg/day GAD ( 2.3 ) Adults 60 mg/day 60 mg/day (once daily) 120 mg/day Geriatric 30 mg/day 60 mg/day (once daily) 120 mg/day Pediatrics (7 to 17 years of age) 30 mg/day 30 to 60 mg/day (once daily) 120 mg/day DPNP ( 2.4 ) 60 mg/day 60 mg/day (once daily) 60 mg/day FM ( 2.5 ) Adults and Pediatrics (13 to 17 years of age) 30 mg/day 60 mg/day (once daily) 60 mg/day Chronic Musculoskeletal Pain ( 2.6 ) 30 mg/day 60 mg/day (once daily) 60 mg/day Discontinuing Duloxetine delayed-release capsules: Gradually reduce dosage to avoid discontinuation symptoms ( 2.8 , 5.7 )
2.1Important Administration Instructions Administer Duloxetine delayed-release capsules orally (with or without meals) and swallow whole. Do not chew or crush, and do not open the delayed-release capsule and sprinkle its contents on food or mix with liquids because these actions might affect the enteric coating. If a dose of Duloxetine delayed-release capsules is missed, take the missed dose as soon as it is remembered.
If it is almost time for the next dose, skip the missed dose and take the next dose at the regular time. Do not take two doses of Duloxetine delayed-release capsules at the same time.
2.2Dosage for Treatment of Major Depressive Disorder in Adults The recommended starting dosage in adults with MDD is 40 mg/day (given as 20 mg twice daily) to 60 mg/day (given either once daily or as 30 mg twice daily). For some patients, it may be desirable to start at 30 mg once daily for 1 week, to allow patients to adjust to Duloxetine delayed-release capsules before increasing to 60 mg once daily. While a 120 mg/day dose was shown to be effective, there is no evidence that doses greater than 60 mg/day confer any additional benefits.
Periodically reassess to determine the need for maintenance treatment and the appropriate dosage for such treatment.
2.3Dosage for Treatment of Generalized Anxiety Disorder Recommended Dosage in Adults Less than 65 Years of Age For most adults less than 65 years of age with GAD, initiate Duloxetine delayed-release capsules 60 mg once daily. For some patients, it may be desirable to start at 30 mg once daily for 1 week, to allow patients to adjust to Duloxetine delayed-release capsules before increasing to 60 mg once daily. While a 120 mg once daily dosage was shown to be effective, there is no evidence that doses greater than 60 mg/day confer additional benefit.
Nevertheless, if a decision is made to increase the dosage beyond 60 mg once daily, increase dosage in increments of 30 mg once daily. Periodically reassess to determine the continued need for maintenance treatment and the appropriate dosage for such treatment. Recommended Dosage in Geriatric Patients In geriatric patients with GAD, initiate Duloxetine delayed-release capsules at a dosage of 30 mg once daily for 2 weeks before considering an increase to the target dose of 60 mg/day.
Thereafter, patients may benefit from doses above 60 mg once daily. If a decision is made to increase the dose beyond 60 mg once daily, increase dose in increments of 30 mg once daily. The maximum dose studied was 120 mg per day.
Recommended Dosage in Pediatric Patients 7 to 17 Years of Age Initiate Duloxetine delayed-release capsules in pediatric patients 7 to 17 years of age with GAD at a dosage of 30 mg once daily for 2 weeks before considering an increase to 60 mg once daily. The recommended dosage range is 30 to 60 mg once daily. Some patients may benefit from dosages above 60 mg once daily.
If a decision is made to increase the dose beyond 60 mg once daily, increase dosage in increments of 30 mg once daily. The maximum do…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Duloxetine delayed-release capsules, USP are available as: 20 mg opaque ochre capsules imprinted with "B" on the cap and "746" on the body 30 mg opaque green (cap) /opaque white (body) capsules imprinted with "B" on the cap and "747" on the body. 40 mg opaque blue (cap) /opaque orange (body) capsules imprinted with "B" on the cap and "750" on the body. 60 mg opaque green (cap) /opaque ochre (body) capsules imprinted with "B" on the cap and "748" on the body Delayed-release capsules: 20 mg, 30 mg, 40 mg and 60 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS The use of MAOIs intended to treat psychiatric disorders with Duloxetine delayed-release capsules or within 5 days of stopping treatment with Duloxetine delayed-release capsules is contraindicated because of an increased risk of serotonin syndrome. The use of Duloxetine delayed-release capsules within 14 days of stopping an MAOI intended to treat psychiatric disorders is contraindicated [see Dosage and Administration (2.8) and Warnings and Precautions (5.4) ]. Starting Duloxetine delayed-release capsules in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome [see Dosage and Administration (2.9) and Warnings and Precautions (5.4) ].
Concomitant use of an MAOI antidepressant with Duloxetine delayed-release capsules is contraindicated Use of Duloxetine delayed-release capsules within 14 days of stopping an MAOI antidepressant is contraindicated In linezolid- or intravenous methylene blue-treated patients, initiation of Duloxetine delayed-release capsules is contraindicated ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hepatotoxicity : Hepatic failure, sometimes fatal, has been reported. Discontinue Duloxetine delayed-release capsules in patients who develop jaundice or other evidence of clinically significant liver dysfunction and should not be resumed unless another cause can be established. Avoid use in patients with substantial alcohol use or evidence of chronic liver disease ( 5.2 ) Orthostatic Hypotension, Falls and Syncope : Consider dosage reduction or discontinuation if these events occur ( 5.3 ) Serotonin Syndrome : Increased risk when co-administered with other serotonergic agents, but also when taken alone.
If it occurs, discontinue Duloxetine delayed-release capsules and serotonergic agents ( 5.4 ) Increased Risk of Bleeding : May increase the risk of bleeding events. Concomitant use of antiplatelet drugs and anticoagulants may increase this risk ( 5.5 , 7.4 , 8.1 ) Severe Skin Reactions : Severe skin reactions, including erythema multiforme and Stevens-Johnson Syndrome (SJS), can occur; Discontinue at the first appearance of blisters, peeling rash, mucosal erosions, or any other sign of hypersensitivity if no other etiology can be identified ( 5.6 ) Activation of Mania or Hypomania : Prior to initiating, screen patients for personal or family history of bipolar disorder, mania, or hypomania ( 5.8 ) Angle-Closure Glaucoma : Has occurred in patients with untreated anatomically narrow angles treated with antidepressants ( 5.9 ) Seizures : Prescribe with care in patients with a history of seizure disorder ( 5.10 ) Blood Pressure Increases : Monitor blood pressure prior to initiating treatment and periodically throughout treatment ( 5.11 ) Inhibitors of CYP1A2 or Thioridazine : Avoid co-administration with Duloxetine delayed-release capsules ( 5.12 ) Hyponatremia : Can occur in association with SIADH; consider discontinuation ( 5.13 ) Glucose Control in Diabetes : In DPNP patients, increases in fasting blood glucose, and HbA 1c have been observed ( 5.14 ) Conditions that Slow Gastric Emptying : Use cautiously in these patients ( 5.14 ) Sexual Dysfunction : Duloxetine delayed-release capsules may cause symptoms of sexual dysfunction ( 5.16 )
5.1Suicidal Thoughts and Behaviors in Children, Adolescents, and Young Adults Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long-standing concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled trials of antidepressant drugs (SSRIs and others) showed that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18-24) with major depressive disorder (MDD) and other psychiatric disorders.
Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4400 patients. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients.
There…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: Suicidal Thoughts and Behaviors in Children, Adolescents, and Young Adults [see Boxed Warning and Warnings and Precautions (5.1) ] Hepatotoxicity [see Warnings and Precautions (5.2) ] Orthostatic Hypotension, Falls and Syncope [see Warnings and Precautions (5.3) ] Serotonin Syndrome [see Warnings and Precautions (5.4) ] Increased Risk of Bleeding [see Warnings and Precautions (5.5) ] Severe Skin Reactions [see Warnings and Precautions (5.6) ] Discontinuation Syndrome [see Warnings and Precautions (5.7) ] Activation of Mania/Hypomania [see Warnings and Precautions (5.8) ] Angle-Closure Glaucoma [see Warnings and Precautions (5.9) ] Seizures [see Warnings and Precautions (5.10) ] Increases in Blood Pressure [see Warnings and Precautions (5.11) ] Clinically Important Drug Interactions [see Warnings and Precautions (5.12) ] Hyponatremia [see Warnings and Precautions (5.13) ] Urinary Hesitation and Retention [see Warnings and Precautions (5.15) ] Sexual Dysfunction [see Warnings and Precautions (5.16) ] Most common adverse reactions (≥5% and at least twice the incidence of placebo-treated patients): ( 6.1 ) Adults : nausea, dry mouth, somnolence, constipation, decreased appetite, and hyperhidrosis Pediatric Patients : decreased weight, decreased appetite, nausea, vomiting, fatigue, and diarrhea To report SUSPECTED ADVERSE REACTIONS, contact Breckenridge Pharmaceutical, Inc. at 1-800-367-3395 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The stated frequencies of adverse reactions represent the proportion of patients who experienced, at least once, one treatment-emergent adverse reaction of the type listed. A reaction was considered treatment-emergent if it occurred for the first time or worsened while receiving therapy following baseline evaluation.
Adverse Reactions in Adults Adult Clinical Trial Database The data described below reflect exposure to duloxetine in placebo-controlled adult trials for MDD (N=3779), GAD (N=1018), OA (N=503), CLBP (N=600), DPNP (N=906), and FM (N=1294). The age range in this pooled population was 17 to 89 years of age. In this pooled population, 66%, 61%, 61%, 43%, and 94% of adult patients were female; and 82%, 73%, 85%, 74%, and 86% of adult patients were Caucasian in the MDD, GAD, OA and CLBP, DPNP, and FM populations, respectively.
Most patients received Duloxetine delayed-release capsules dosages of a total of 60 to 120 mg per day [see Clinical Studies (14) ] . The data below do not include results of the trial that evaluated the efficacy of Duloxetine delayed-release capsules for the treatment of GAD in patients ≥65 years old (Study GAD-5) [see Clinical Studies (14.3) ] ; however, the adverse reactions observed in this geriatric population were generally similar to adverse reactions in the overall adult population. Adverse Reactions Leading to Treatment Discontinuation in Adult Placebo-Controlled Trials Major Depressive Disorder Approximately 8.4% (319/3779) of duloxetine-treated patients in placebo-controlled adult trials for MDD discontinued treatment due to an adverse reaction, compared with 4.6% (117/2536) of placebo-treated patients.
Nausea (Duloxetine 1.1%, placebo 0.4%) was the only adverse reaction reported as a reason for discontinuation and considered to be drug-related (i.e., discontinuation occurring in at least 1% of the duloxetine-treated patients and at a rate of at least twice that of placebo-treated patients). Generalized Anxiety Disorder Approximately 13.7% (139/1018) of the duloxetine-treated patients in placebo-controlled adult trials for GAD discontinued treatment due to an…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Both CYP1A2 and CYP2D6 are responsible for duloxetine metabolism. Potent inhibitors of CYP1A2 should be avoided ( 7.1 ) Potent inhibitors of CYP2D6 may increase Duloxetine delayed-release capsules concentrations ( 7.2 ) Duloxetine delayed-release capsules is a moderate inhibitor of CYP2D6 ( 7.9 )
7.1Inhibitors of CYP1A2 When duloxetine 60 mg was co-administered with fluvoxamine 100 mg, a potent CYP1A2 inhibitor, to male subjects (n=14) duloxetine AUC was increased approximately 6-fold, the C max was increased about 2.5-fold, and duloxetine t 1/2 was increased approximately 3-fold. Other drugs that inhibit CYP1A2 metabolism include cimetidine and quinolone antimicrobials such as ciprofloxacin and enoxacin [see Warnings and Precautions (5.12) ].
7.2Inhibitors of CYP2D6 Concomitant use of duloxetine (40 mg once daily) with paroxetine (20 mg once daily) increased the concentration of duloxetine AUC by about 60%, and greater degrees of inhibition are expected with higher doses of paroxetine. Similar effects would be expected with other potent CYP2D6 inhibitors (e.g., fluoxetine, quinidine) [see Warnings and Precautions (5.12) ].
7.3Dual Inhibition of CYP1A2 and CYP2D6 Concomitant administration of duloxetine 40 mg twice daily with fluvoxamine 100 mg, a potent CYP1A2 inhibitor, to CYP2D6 poor metabolizer subjects (n=14) resulted in a 6-fold increase in duloxetine AUC and C max.
7.4Drugs that Interfere with Hemostasis (e.g., NSAIDs, Aspirin, and Warfarin) Serotonin release by platelets plays an important role in hemostasis. Epidemiological studies of the case-control and cohort design that have demonstrated an association between use of psychotropic drugs that interfere with serotonin reuptake and the occurrence of upper gastrointestinal bleeding have also shown that concurrent use of an NSAID or aspirin may potentiate this risk of bleeding. Altered anticoagulant effects, including increased bleeding, have been reported when SSRIs or SNRIs are co-administered with warfarin.
Concomitant administration of warfarin (2-9 mg once daily) under steady state conditions with Duloxetine delayed-release capsules 60 or 120 mg once daily for up to 14 days in healthy subjects (n=15) did not significantly change INR from baseline (mean INR changes ranged from 0.05 to +0.07). The total warfarin (protein bound plus free drug) pharmacokinetics (AUC τ,ss , C max,ss or t max,ss ) for both R- and S-warfarin were not altered by duloxetine. Because of the potential effect of duloxetine on platelets, patients receiving warfarin therapy should be carefully monitored when Duloxetine delayed-release capsules are initiated or discontinued [see Warnings and Precautions (5.5) ].
7.5Lorazepam Under steady-state conditions for duloxetine (60 mg Q 12 hours) and lorazepam (2 mg Q 12 hours), the pharmacokinetics of duloxetine were not affected by co-administration.
7.6Temazepam Under steady-state conditions for duloxetine (20 mg qhs) and temazepam (30 mg qhs), the pharmacokinetics of duloxetine were not affected by co-administration.
7.7Drugs that Affect Gastric Acidity Duloxetine delayed-release capsules have an enteric coating that resists dissolution until reaching a segment of the gastrointestinal tract where the pH exceeds 5.5. In extremely acidic conditions, Duloxetine delayed-release capsules, unprotected by the enteric coating, may undergo hydrolysis to form naphthol. Caution is advised in using Duloxetine delayed-release capsules in patients with conditions that may slow gastric emptying (e.g., some diabetics).
Drugs that raise the gastrointestinal pH may lead to an earlier release of duloxetine. However, co- administration of Duloxetine delayed-release capsules with aluminum- and magnesium-containing antacids (51 mEq) or Duloxetine delayed-release capsules with famotidine, had no significant effect on the rate or extent of duloxetine absorption after administration of a 40 mg oral dose. It is unknown whether the concomitant adminis…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy : Third trimester use may increase risk for symptoms of poor adaptation (respiratory distress, temperature instability, feeding difficulty, hypotonia, tremor, irritability) in the neonate ( 8.1 ) Hepatic Impairment : Avoid use in patients with chronic liver disease or cirrhosis ( 5.14 ) Renal Impairment : Avoid use in patients with severe renal impairment, GFR <30 mL/minute ( 5.14 )
8.1Pregnancy Risk Summary Data from a postmarketing retrospective cohort study indicate that use of duloxetine in the month before delivery may be associated with an increased risk of postpartum hemorrhage. Data from published literature and from a postmarketing retrospective cohort study have not identified a clear drug-associated risk of major birth defects or other adverse developmental outcomes (see Data ) . There are risks associated with untreated depression and fibromyalgia in pregnancy, and with exposure to SNRIs and SSRIs, including Duloxetine delayed-release capsules, during pregnancy (see Clinical Considerations ).
In rats and rabbits treated with duloxetine during the period of organogenesis, fetal weights were decreased but there was no evidence of developmental effects at doses up to 3 and 6 times, respectively, the maximum recommended human dose (MRHD) of 120 mg/day given to adolescents on a mg/m 2 basis. When duloxetine was administered orally to pregnant rats throughout gestation and lactation, pup weights at birth and pup survival to 1 day postpartum were decreased at a dose 2 times the MRHD given to adolescents on a mg/m 2 basis.
At this dose, pup behaviors consistent with increased reactivity, such as increased startle response to noise and decreased habituation of locomotor activity were observed. Post-weaning growth was not adversely affected. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Women who discontinue antidepressants during pregnancy are more likely to experience a relapse of major depression than women who continue antidepressants.
This finding is from a prospective, longitudinal study that followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy. Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Pregnant women with fibromyalgia are at increased risk for adverse maternal and infant outcomes including preterm premature rupture of membranes, preterm birth, small for gestational age, intrauterine growth restriction, placental disruption, and venous thrombosis.
It is not known if these adverse maternal and fetal outcomes are a direct result of fibromyalgia or other comorbid factors. Maternal Adverse Reactions Use of duloxetine in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions (5.5) ]. Fetal/Neonatal Adverse Reaction Neonates exposed to Duloxetine delayed-release capsules and other SNRIs or SSRIs late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These findings are consistent with either a direct toxic effect of the SNRIs or SSRIs, or possib…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Data from a postmarketing retrospective cohort study indicate that use of duloxetine in the month before delivery may be associated with an increased risk of postpartum hemorrhage. Data from published literature and from a postmarketing retrospective cohort study have not identified a clear drug-associated risk of major birth defects or other adverse developmental outcomes (see Data ) . There are risks associated with untreated depression and fibromyalgia in pregnancy, and with exposure to SNRIs and SSRIs, including Duloxetine delayed-release capsules, during pregnancy (see Clinical Considerations ).
In rats and rabbits treated with duloxetine during the period of organogenesis, fetal weights were decreased but there was no evidence of developmental effects at doses up to 3 and 6 times, respectively, the maximum recommended human dose (MRHD) of 120 mg/day given to adolescents on a mg/m 2 basis. When duloxetine was administered orally to pregnant rats throughout gestation and lactation, pup weights at birth and pup survival to 1 day postpartum were decreased at a dose 2 times the MRHD given to adolescents on a mg/m 2 basis.
At this dose, pup behaviors consistent with increased reactivity, such as increased startle response to noise and decreased habituation of locomotor activity were observed. Post-weaning growth was not adversely affected. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Women who discontinue antidepressants during pregnancy are more likely to experience a relapse of major depression than women who continue antidepressants.
This finding is from a prospective, longitudinal study that followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy. Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Pregnant women with fibromyalgia are at increased risk for adverse maternal and infant outcomes including preterm premature rupture of membranes, preterm birth, small for gestational age, intrauterine growth restriction, placental disruption, and venous thrombosis.
It is not known if these adverse maternal and fetal outcomes are a direct result of fibromyalgia or other comorbid factors. Maternal Adverse Reactions Use of duloxetine in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions (5.5) ]. Fetal/Neonatal Adverse Reaction Neonates exposed to Duloxetine delayed-release capsules and other SNRIs or SSRIs late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These findings are consistent with either a direct toxic effect of the SNRIs or SSRIs, or possibly, a drug discontinuation syndrome.
It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [see Warnings and Precautions (5.4) ]. Data Human Data Data from a postmarketing retrospective claims-based cohort study found an increased risk for postpartum hemorrhage among 955 pregnant women exposed to duloxetine in the last month of pregnancy compared to 4,128,460 unexposed pregnant…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Duloxetine delayed-release capsules have been established for treatment of generalized anxiety disorder (GAD) in patients 7 to 17 years of age and for treatment of juvenile fibromyalgia syndrome in patients 13 to 17 years of age. The safety and effectiveness of Duloxetine delayed-release capsules have not been established in pediatric patients with major depressive disorder (MDD), diabetic peripheral neuropathic pain, or chronic musculoskeletal pain. Antidepressants increased the risk of suicidal thoughts and behavior in pediatric patients.
Monitor all pediatric patients being treated with antidepressants for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of treatment, or at times of dosage changes [see Warnings and Precautions (5.1) ] . Perform regular monitoring of weight and growth in pediatric patients treated with Duloxetine delayed-release capsules [see Adverse Reactions (6.1) ]. Generalized Anxiety Disorder Use of Duloxetine delayed-release capsules for the treatment of GAD in patients 7 to 17 years of age is supported by one 10-week, placebo- controlled trial (GAD-6).
The study included 272 pediatric patients with GAD of which 47% were 7 to 11 years of age (53% were 12 to 17 years of age). Duloxetine delayed-release capsules demonstrated superiority over placebo as measured by greater improvement in the Pediatric Anxiety Rating Scale (PARS) for GAD severity score [see Clinical Studies (14.3) ]. The safety and effectiveness of Duloxetine delayed-release capsules for the treatment of GAD in pediatric patients less than 7 years of age have not been established.
Fibromyalgia Use of Duloxetine delayed-release capsules for treatment of fibromyalgia in patients 13 to 17 years of age is supported by a 13-week placebo- controlled trial in 184 patients with juvenile fibromyalgia syndrome (Study FM-4). Duloxetine delayed-release capsules showed improvement over placebo on the primary endpoint, change from baseline to end-of-treatment on the Brief Pain Inventory (BPI) – Modified Short Form: Adolescent Version 24-hour average pain severity rating [see Clinical Studies (14.5) ] . The safety and effectiveness of Duloxetine delayed-release capsules for the treatment of fibromyalgia in patients less than 13 years of age have not been established.
Major Depressive Disorder The safety and effectiveness of Duloxetine delayed-release capsules have not been established in pediatric patients for the treatment of MDD. Efficacy of Duloxetine delayed-release capsules was not demonstrated in two 10-week, placebo-controlled trials with 800 pediatric patients aged 7 to 17 years old with MDD (MDD-6 and MDD-7). Neither Duloxetine delayed-release capsules nor an active control (approved for treatment of pediatric MDD) was superior to placebo.
The most frequently observed adverse reactions in the MDD pediatric clinical trials included nausea, headache, decreased weight, and abdominal pain. Decreased appetite and weight loss have been observed in association with the use of SSRIs and SNRIs. Juvenile Animal Toxicology Data Duloxetine administration to young rats from post-natal day 21 (weaning) through post-natal day 90 (adult) resulted in decreased body weights that persisted into adulthood, but recovered when drug treatment was discontinued; slightly delayed (~1.5 days) sexual maturation in females, without any effect on fertility; and a delay in learning a complex task in adulthood, which was not observed after drug treatment was discontinued.
These effects were observed at the high dose of 45 mg/kg/day (2 times the MRHD, for a child); the no-effect-level was 20 mg/kg/day (≈1 times the MRHD, for a child).
🧓 Geriatric Use ▾
8.5Geriatric Use Geriatric Exposure in Premarketing Clinical Trials of Duloxetine delayed-release capsules Of the 2,418 patients in MDD trials, 6% (143) were 65 years of age or over. Of the 1,041 patients in CLBP trials, 21% (221) were 65 years of age or over. Of the 487 patients in OA trials, 41% (197) were 65 years of age or over.
Of the 1,074 patients in the DPNP trials, 33% (357) were 65 years of age or over. Of the 1,761 patients in FM trials, 8% (140) were 65 years of age or over. In the MDD, GAD, DPNP, FM, OA, and CLBP studies, no overall differences in safety or effectiveness were generally observed between these patients and younger adult patients, and other reported clinical experience has not identified differences in responses between these geriatric and younger adult patients, but greater sensitivity of some older patients cannot be ruled out.
SSRIs and SNRIs, including Duloxetine delayed-release capsules have been associated with clinically significant hyponatremia in geriatric patients, who may be at greater risk for this adverse reaction [see Warnings and Precautions (5.13) ]. In an analysis of data from all placebo-controlled-trials, Duloxetine delayed-release capsules-treated patients reported a higher rate of falls compared to placebo-treated patients. The increased risk appears to be proportional to a patient's underlying risk for falls.
Underlying risk appears to increase steadily with age. As geriatric patients tend to have a higher prevalence of risk factors for falls such as medications, medical comorbidities and gait disturbances, the impact of increasing age by itself on falls during Duloxetine delayed-release capsules treatment is unclear. Falls with serious consequences including bone fractures and hospitalizations have been reported with Duloxetine delayed-release capsules use [see Warnings and Precautions (5.3) and Adverse Reactions (6.1) ].
The pharmacokinetics of duloxetine after a single dose of 40 mg were compared in healthy elderly females (65 to 77 years) and healthy middle-age females (32 to 50 years). There was no difference in the C max , but the AUC of duloxetine was somewhat (about 25%) higher and the half-life about 4 hours longer in the elderly females. Population pharmacokinetic analyses suggest that the typical values for clearance decrease by approximately 1% for each year of age between 25 to 75 years of age; but age as a predictive factor only accounts for a small percentage of between-patient variability.
Dosage adjustment based on the age of the adult patient is not necessary.
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs and Symptoms In postmarketing experience, fatal outcomes have been reported for acute duloxetine overdoses, primarily with mixed overdoses, but also with duloxetine only, including 1000 mg of duloxetine (approximately 8.3 times the maximum recommended dosage). Signs and symptoms of overdose (duloxetine alone or with mixed drugs) included somnolence, coma, serotonin syndrome, seizures, syncope, tachycardia, hypotension, hypertension, and vomiting.
10.2Management of Overdose There is no specific antidote to a Duloxetine delayed-release capsules overdosage, but if serotonin syndrome ensues, specific treatment (such as with cyproheptadine and/or temperature control) may be considered. In case of acute overdose with Duloxetine delayed-release capsules, treatment should consist of those general measures employed in the management of overdose with any drug, such as assuring an adequate airway, oxygenation, and ventilation and monitoring cardiac rhythm and vital signs.
Gastric lavage with a large-bore orogastric tube with appropriate airway protection, if needed, may be indicated if performed soon after ingestion or in symptomatic patients. Induction of emesis is not recommended. Activated charcoal may be useful in limiting absorption of duloxetine from the gastrointestinal tract.
Administration of activated charcoal has been shown to decrease duloxetine AUC and C max by an average of one-third, although some patients had a limited effect of activated charcoal. Due to the large volume of distribution of duloxetine, forced diuresis, dialysis, hemoperfusion, and exchange transfusion are unlikely to be beneficial. In managing overdose, the possibility of multiple drug involvement should be considered.
A specific caution involves patients who overdose with Duloxetine delayed-release capsules and tricyclic antidepressants. In such a case, decreased clearance of the parent tricyclic and/or its active metabolite may increase the possibility of clinically significant sequelae and extend the time needed for close medical observation [see Warnings and Precautions (5.4) and Drug Interactions (7) ]. Consider contacting a poison control center (1-800-222-1222 or www.poison.org) for additional information on the treatment of overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Although the exact mechanisms of the antidepressant, central pain inhibitory and anxiolytic actions of duloxetine in humans are unknown, these actions are believed to be related to its potentiation of serotonergic and noradrenergic activity in the CNS.
12.2Pharmacodynamics Preclinical studies have shown that duloxetine is a potent inhibitor of neuronal serotonin and norepinephrine reuptake and a less potent inhibitor of dopamine reuptake. Duloxetine has no significant affinity for dopaminergic, adrenergic, cholinergic, histaminergic, opioid, glutamate, and GABA receptors in vitro . Duloxetine does not inhibit monoamine oxidase (MAO).
Duloxetine delayed-release capsules are in a class of drugs known to affect urethral resistance [see Warnings and Precautions (5.15) ]. Cardiac Electrophysiology The effect of Duloxetine delayed-release capsules 160 mg and 200 mg administered twice daily (2.7 and 3.3 times the maximum recommended dosage, respectively) to steady state was evaluated in a randomized, double-blinded, two-way crossover study in 117 healthy female adult subjects. No QT interval prolongation was detected.
Duloxetine delayed-release capsules appears to be associated with concentration-dependent but not clinically meaningful QT shortening.
12.3Pharmacokinetics Duloxetine has an elimination half-life of about 12 hours (range 8 to 17 hours) and its pharmacokinetics are dose proportional over the therapeutic range. Steady-state plasma concentrations are typically achieved after 3 days of dosing. Elimination of duloxetine is mainly through hepatic metabolism involving two P450 isozymes, CYP1A2 and CYP2D6.
Absorption After oral Duloxetine delayed-release capsules administration, duloxetine hydrochloride is well absorbed. There is a median 2 hour lag until absorption begins (T lag ), with maximal plasma concentrations (C max ) of duloxetine occurring 6 hours post dose. There is a 3 hour delay in absorption and a one-third increase in apparent clearance of duloxetine after an evening dose as compared to a morning dose.
Effect of Food: Food does not affect the C max of duloxetine, but delays the time to reach peak concentration from 6 to 10 hours and it marginally decreases the extent of absorption (AUC) by about 10%. Distribution The apparent volume of distribution averages about 1640 L. Duloxetine is highly bound (>90%) to proteins in human plasma, binding primarily to albumin and α 1 -acid glycoprotein.
The interaction between duloxetine and other highly protein bound drugs has not been fully evaluated. Plasma protein binding of duloxetine is not affected by renal or hepatic impairment. Elimination Metabolism Biotransformation and disposition of duloxetine in humans have been determined following oral administration of 14 C-labeled duloxetine.
Duloxetine comprises about 3% of the total radiolabeled material in the plasma, indicating that it undergoes extensive metabolism to numerous metabolites. The major biotransformation pathways for duloxetine involve oxidation of the naphthyl ring followed by conjugation and further oxidation. Both CYP1A2 and CYP2D6 catalyze the oxidation of the naphthyl ring in vitro .
Metabolites found in plasma include 4-hydroxy duloxetine glucuronide and 5-hydroxy, 6-methoxy duloxetine sulfate. Excretion Many additional metabolites have been identified in urine, some representing only minor pathways of elimination. Only trace (<1% of the dose) amounts of unchanged duloxetine are present in the urine.
Most (about 70%) of the duloxetine dose appears in the urine as metabolites of duloxetine; about 20% is excreted in the feces. Duloxetine undergoes extensive metabolism, but the major circulating metabolites have not been shown to contribute significantly to the pharmacologic activity of duloxetine. Specific Populations Pediatric Patients Duloxetine steady-state plasma concentration was comparable in pediatric patients 7 to 17 years of age and adult patien…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Although the exact mechanisms of the antidepressant, central pain inhibitory and anxiolytic actions of duloxetine in humans are unknown, these actions are believed to be related to its potentiation of serotonergic and noradrenergic activity in the CNS.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Duloxetine delayed-release capsules, USP are color green yellow (ochre), imprint B;748 and size 19 mm. NDC: 71335-0509-1: 30 Capsules in a BOTTLE NDC: 71335-0509-2: 28 Capsules in a BOTTLE NDC: 71335-0509-3: 60 Capsules in a BOTTLE NDC: 71335-0509-4: 90 Capsules in a BOTTLE NDC: 71335-0509-5: 180 Capsules in a BOTTLE NDC: 71335-0509-6: 120 Capsules in a BOTTLE Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature]. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 9150
📋 Description ▾
11 DESCRIPTION Duloxetine delayed-release capsules, USP are a selective serotonin and norepinephrine reuptake inhibitor (SNRI) for oral administration. Its chemical designation is (+)-( S )- N -methyl-γ-(1-naphthyloxy)-2-thiophenepropylamine hydrochloride. The empirical formula is C 18 H 19 NOS∙HCl, which corresponds to a molecular weight of 333.88.
The structural formula is: Duloxetine hydrochloride is a white to slightly brownish white solid, which is slightly soluble in water. Each capsule contains enteric-coated pellets of 20, 30, 40 or 60 mg of duloxetine (equivalent to 22.4, 33.7, 44.9 or 67.3 mg of duloxetine hydrochloride, respectively). These enteric-coated pellets are designed to prevent degradation of the drug in the acidic environment of the stomach.
Inactive ingredients include ammonium hydroxide, black iron oxide, hypromellose, methacrylic acid copolymer dispersion (methacrylic acid-ethyl acrylate copolymer, polysorbate 80, sodium lauryl sulfate), potassium hydroxide, propylene glycol, shellac, sucrose, sugar spheres (maize starch, sucrose), talc, titanium dioxide, triethylcitrate, and hard gelatin capsules (gelatin, titanium dioxide). The 20 mg hard gelatin capsule colorant is yellow iron oxide. The 30 mg hard gelatin capsule colorants are FD&C Blue No.
1, FD&C Yellow No. 6, and FD&C Yellow No. 10.
The 40 mg hard gelatin capsule colorants are FD&C Blue No. 2, red iron oxide, and yellow iron oxide. The 60 mg hard gelatin capsule colorants are FD&C Blue No.
1, FD&C Yellow No. 6, FD&C Yellow No.10, and yellow iron oxide.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Suicidal Thoughts and Behaviors — Advise patients, their families, and their caregivers to look for the emergence of suicidal ideation and behavior, especially during treatment and when the dose is adjusted up or down and instruct them to report such symptoms to their healthcare provider [see Boxed Warning and Warnings and Precautions (5.1) ]. Administration — Advise patients to swallow Duloxetine delayed-release capsules whole and to not chew, crush, or open the capsule (do not sprinkle contents on food or mixed with liquids) because these actions might affect the enteric coating.
Hepatotoxicity — Inform patients that severe liver problems, sometimes fatal, have been reported in patients treated with Duloxetine delayed-release capsules. Instruct patients to talk to their healthcare provider if they develop itching, right upper belly pain, dark urine, or yellow skin/eyes while taking Duloxetine delayed-release capsules, which may be signs of liver problems. Instruct patients to talk to their healthcare provider about their alcohol consumption.
Use of Duloxetine delayed-release capsules with heavy alcohol intake may be associated with severe liver injury [see Warnings and Precautions (5.2) ]. Alcohol — Although Duloxetine delayed-release capsules does not increase the impairment of mental and motor skills caused by alcohol, use of Duloxetine delayed-release capsules concomitantly with heavy alcohol intake may be associated with severe liver injury [see Warnings and Precautions (5.2) and Drug Interactions (7.15) ]. Orthostatic Hypotension, Falls and Syncope — Advise patients of the risk of orthostatic hypotension, falls and syncope, especially during the period of initial use and subsequent dose escalation, and in association with the use of concomitant drugs that might potentiate the orthostatic effect of Duloxetine delayed-release capsules [see Warnings and Precautions (5.3) ].
Serotonin Syndrome — Caution patients about the risk of serotonin syndrome with the concomitant use of Duloxetine delayed-release capsules and other serotonergic agents including triptans, tricyclic antidepressants, opioids, lithium, buspirone, tryptophan, amphetamines, and St. John's Wort [see Contraindications (4) , Warnings and Precautions (5.4) , and Drug Interactions (7.14) ]. Advise patients of the signs and symptoms associated with serotonin syndrome that may include mental status changes (e.g., agitation, hallucinations, delirium, and coma), autonomic instability (e.g., tachycardia, labile blood pressure, dizziness, diaphoresis, flushing, hyperthermia), neuromuscular changes (e.g., tremor, rigidity, myoclonus, hyperreflexia, incoordination), seizures, and/or gastrointestinal symptoms (e.g., nausea, vomiting, diarrhea).
Caution patients to seek medical care immediately if they experience these symptoms . Increased Risk of Bleeding — Caution patients about the concomitant use of Duloxetine delayed-release capsules and NSAIDs, aspirin, warfarin, or other drugs that affect coagulation since combined use of psychotropic drugs that interfere with serotonin reuptake and these agents has been associated with an increased risk of bleeding [see Warnings and Precautions (5.5) and Use in Specific Populations (8.1) ]. Severe Skin Reactions — Caution patients that Duloxetine delayed-release capsules may cause serious skin reactions.
This may need to be treated in a hospital and may be life-threatening. Counsel patients to call their doctor right away or get emergency help if they have skin blisters, peeling rash, sores in their mouth, hives, or any other allergic reactions [see Warnings and Precautions (5.6) ]. Discontinuation of Treatment — Instruct patients that discontinuation of Duloxetine delayed-release capsules may be associated with symptoms such as dizziness, headache, nausea, diarrhea, paresthesia, irritability, vomiting, insomnia, anxi…
💬 Medication Guide ▾
MEDICATION GUIDE Duloxetine (doo-LOX-e-teen) Delayed-Release Capsules, USP Rx Only Dispense with Medication Guide available at: www.bpirx.com/products/patientinformation Read this Medication Guide before you start taking Duloxetine delayed-release capsules and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
Talk to your healthcare provider about: all risks and benefits of treatment with antidepressant medicines all treatment choices for depression or other serious mental illness What is the most important information I should know about antidepressant medicines, depression, other serious mental illnesses, and suicidal thoughts or actions? Duloxetine delayed-release capsules and other antidepressant medicines may increase suicidal thoughts or actions in some children, teenagers, or young adults within the first few months of treatment or when the dose is changed.
Depression and other serious mental illnesses are the most important causes of suicidal thoughts or actions. Some people may have a particularly high risk of having suicidal thoughts or actions . These include people who have (or have a family history of) bipolar illness (also called manic-depressive illness).
How can I watch for and try to prevent suicidal thoughts and actions? Pay close attention to any changes in mood, behavior, actions, thoughts, or feelings, especially sudden changes. This is very important when an antidepressant medicine is started or when the dose is changed.
Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you have concerns about symptoms.
Call your healthcare provider right away if you have any of the following symptoms or feelings, especially if they are new, worse, or worry you. In an emergency, call 911. attempts to commit suicide acting aggressive, being angry, or violent new or worse depression panic attacks new or worse irritability an extreme increase in activity or talking (mania) acting on dangerous impulses thoughts about suicide or dying new or worse anxiety feeling very agitated or restless trouble sleeping other unusual changes in behavior or mood What else do I need to know about antidepressant medicines?
Never stop an antidepressant medicine without first talking to a healthcare provider. Stopping an antidepressant medicine suddenly can cause other symptoms. Antidepressants are medicines used to treat depression and other illnesses.
It is important to discuss all the risks of treating depression and also the risks of not treating it. Patients should discuss all treatment choices with your healthcare provider, not just the use of antidepressants. Antidepressant medicines have other side effects.
Talk to your healthcare provider about the side effects of the medicine prescribed for you or your family member. Antidepressant medicines can interact with other medicines. Know all of the medicines that you or your family member takes.
Keep a list of all medicines to show your healthcare provider. Do not start new medicines without first checking with your healthcare provider. What are Duloxetine delayed-release capsules?
Duloxetine delayed-release capsules are a prescription medicine used to treat a certain type of depression called Major Depressive Disorder (MDD). Duloxetine delayed-release capsules belong to a class of medicines known as SNRIs (or serotonin-norepinephrine reuptake inhibitors). Duloxetine delayed-release capsules are also used to treat or manage: Generalized Anxiety Disorder (GAD) Fibromyalgia (FM) Diabetic Peripheral Neuropathic Pain (DPNP) Chronic Musculoskeletal Pain Who should not take Duloxetine delayed-release capsules?
Do Not take Duloxetine delayed-release capsules if you: take…