
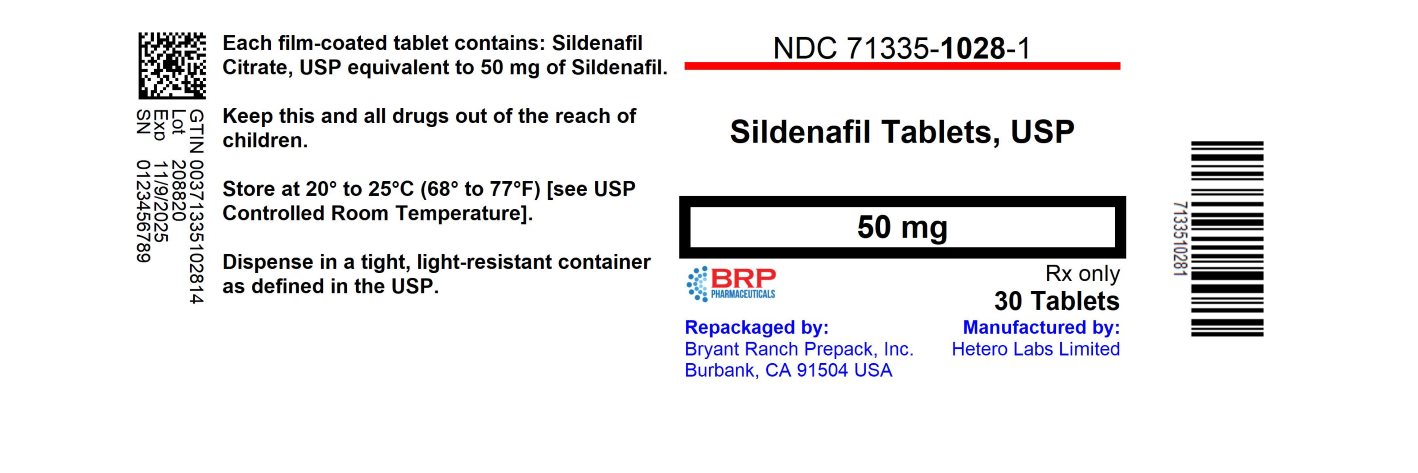
Sildenafil 50 mg Tablet, Film Coated, 7-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phosphodiesterase 5 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Sildenafil (Viagra) is used to treat erectile dysfunction (impotence; inability to get or keep an erection) in men. Sildenafil (Liqrev, Revatio) is used to improve the ability to exercise in adults (Liqrev, Revatio) and children 1 year of age and older (Revatio) with pulmonary arterial hypertension (PAH; high blood pressure in the vessels carrying blood to the lungs, causing shortness of breath, dizziness, and tiredness). Sildenafil is in a class of medications called phosphodiesterase (PDE) inhibitors. Sildenafil treats erectile dysfunction by increasing blood flow to the penis during sexual...
Read the full MedlinePlus article ↗- For erectile dysfunction, you take sildenafil only when you need it — about 30 minutes to 1 hour before sexual activity works best, though anywhere from 30 minutes to 4 hours ahead...
- Can I take Viagra or generic sildenafil just before sex, or do I need to take it every day?
- Both sildenafil and nitrates lower blood pressure, and together their effect on blood pressure can be dangerously large — we're talking about a drop severe enough to cause fainting...
- Why can't I take sildenafil with nitroglycerin or other nitrate medicines?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Sildenafil — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sildenafil 50 mg 00093-5342-01 | Teva | 100 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil Citrate 50 mg 13668-0187-01 | Torrent | 100 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil Citrate 50 mg 27241-0068-03 | Ajanta | 30 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 31722-0710-01 | Camber | 100 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 33342-0042-07 | Macleods | 30 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil Citrate 50 mg 59762-0035-01 | Mylan | 30 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil Citrate 50 mg 60290-0002-01 | Umedica | 30 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 65862-0690-01 | Aurobindo | 100 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 72241-0070-05 | Modavar | 100 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 72888-0016-00 | Advagen | 1000 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil Citrate 50 mg 75834-0240-00 | NIVAGEN | 1000 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 76282-0644-01 | Exelan | 100 tablets | $0.106 | AB | Availability likely | — |
| Sildenafil 50 mg 69097-0952-02 | CIPLA | 30 tablets | $0.209 | AB | FDA listed | — |
| Viagra 50 mg 00069-4210-30 | PFIZER | 30 tablets | $84.570 | AB | Availability likely | — |
| Viagra 50 mg 58151-0427-01 | Viatris | 100 tablets | $84.570 | AB | Availability likely | — |
| Sildenafil 50 mg 31722-0966-01 | Camber | 100 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 35561-0252-10 | Bostal | 30 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 43063-0941-15 | PD-Rx | 15 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 50090-5415-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 50090-6804-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 50090-7181-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 50090-7977-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 52817-0341-10 | TruPharma | 100 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 55801-0339-01 | Appco | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 60219-1752-01 | Amneal | 100 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 63629-7833-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 67296-2241-05 | Redpharm | 5 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 68071-3631-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 68071-3646-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 68071-3743-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 68071-3745-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 68071-3978-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 68071-4674-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 70518-1844-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Sildenafil Citrate 50 mg 70954-0408-10 | ANI | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 71205-0267-20 | Proficient | 20 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 71205-0542-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 71205-0721-04 | Proficient | 4 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 71205-0795-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 71209-0107-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mgthis 71335-1028-07 | Bryant | 7 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 71335-3111-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 71610-0679-02 | Aphena | 2 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 72303-0846-01 | HEC | 30 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 72603-0884-01 | Northstar | 30 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 72789-0103-15 | PD-Rx | 15 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 72789-0405-15 | PD-Rx | 15 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 72865-0102-01 | XLCARE | 100 tablets | — | AB | FDA listed | — |
| Sildenafil Citrate 50 mg 76420-0564-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 82647-0211-14 | Reyoung | 1000 tablets | — | AB | FDA listed | — |
| Sildenafil 50 mg 59746-0435-01 | Jubilant | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1028-01 | 30 TABLET, FILM COATED in 1 BOTTLE (71335-1028-1) | 2019-07-12 | Active |
| 71335-1028-02 | 10 TABLET, FILM COATED in 1 BOTTLE (71335-1028-2) | 2018-12-13 | Active |
| 71335-1028-03 | 15 TABLET, FILM COATED in 1 BOTTLE (71335-1028-3) | 2019-07-11 | Active |
| 71335-1028-04 | 90 TABLET, FILM COATED in 1 BOTTLE (71335-1028-4) | 2021-02-09 | Active |
| 71335-1028-05 | 60 TABLET, FILM COATED in 1 BOTTLE (71335-1028-5) | 2019-11-21 | Active |
| 71335-1028-06 | 20 TABLET, FILM COATED in 1 BOTTLE (71335-1028-6) | 2021-09-07 | Active |
| 71335-1028-07 You're viewing this | 7 TABLET, FILM COATED in 1 BOTTLE (71335-1028-7) | 2019-11-21 | Active |
| 71335-1028-08 | 40 TABLET, FILM COATED in 1 BOTTLE (71335-1028-8) | 2019-11-21 | Active |
You're viewing the smallest of 8 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1028-07?
What is the difference between NDC 71335-1028-07 and NDC 71335-1028-02?
What NDC number is used to bill for this package of Sildenafil 50 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Sildenafil tablets are indicated for the treatment of erectile dysfunction. Sildenafil tablet is a phosphodiesterase-5 (PDE5) inhibitor indicated for the treatment of erectile dysfunction (ED) (1)
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION •For most patients, the recommended dose is 50 mg taken, as needed, approximately 1 hour before sexual activity. However, sildenafil tablets may be taken anywhere from 30 minutes to 4 hours before sexual activity (2.1) •Based on effectiveness and toleration, may increase to a maximum of 100 mg or decrease to 25 mg (2.1) •Maximum recommended dosing frequency is once per day (2.1)
2.1Dosage Information For most patients, the recommended dose is 50 mg taken, as needed, approximately 1 hour before sexual activity. However, sildenafil tablets may be taken anywhere from 30 minutes to 4 hours before sexual activity. The maximum recommended dosing frequency is once per day. Based on effectiveness and toleration, the dose may be increased to a maximum recommended dose of 100 mg or decreased to 25 mg.
2.2Use with Food Sildenafil tablets may be taken with or without food.
2.3Dosage Adjustments in Specific Situations Sildenafil tablets were shown to potentiate the hypotensive effects of nitrates and its administration in patients who use nitric oxide donors such as organic nitrates or organic nitrites in any form is therefore contraindicated [see Contraindications (4.1), Drug Interactions (7.1), and Clinical Pharmacology (12.2)]. When sildenafil tablets are co-administered with an alpha-blocker, patients should be stable on alpha-blocker therapy prior to initiating sildenafil tablets treatment and sildenafil tablets should be initiated at 25 mg [see Warnings and Precautions (5.5), Drug Interactions (7.2), and Clinical Pharmacology (12.2)].
2.4Dosage Adjustments Due to Drug Interactions Ritonavir The recommended dose for ritonavir-treated patients is 25 mg prior to sexual activity and the recommended maximum dose is 25 mg within a 48 hour period because concomitant administration increased the blood levels of sildenafil by 11-fold [see Warnings and Precautions (5.6), Drug Interactions (7.4), and Clinical Pharmacology (12.3)]. CYP3A4 Inhibitors Consider a starting dose of 25 mg in patients treated with strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, or saquinavir) or erythromycin.
Clinical data have shown that co-administration with saquinavir or erythromycin increased plasma levels of sildenafil by about 3 fold [see Drug Interactions (7.4) and Clinical Pharmacology (12.3)].
2.5Dosage Adjustments in Special Populations Consider a starting dose of 25 mg in patients > 65 years, patients with hepatic impairment (e.g., cirrhosis), and patients with severe renal impairment (creatinine clearance <30 mL/minute) because administration of sildenafil tablets in these patients resulted in higher plasma levels of sildenafil [see Use in Specific Populations ( 8.5, 8.6, 8.7) and Clinical Pharmacology ( 12.3)].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Sildenafil Tablets USP, 25 mg are white colored, round-shaped, biconvex, film coated tablets debossed with 'I' on one side and '35' on the other side. Sildenafil Tablets USP, 50 mg are white colored, round-shaped, biconvex, film coated tablets debossed with 'I' on one side and '36' on the other side. Sildenafil Tablets USP, 100 mg are white colored, round-shaped, biconvex, film coated tablets debossed with 'I' on one side and '58' on the other side.
Tablets: 25 mg, 50 mg, 100 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS •Administration of sildenafil tablets to patients using nitric oxide donors, such as organic nitrates or organic nitrites in any form. Sildenafil tablets were shown to potentiate the hypotensive effect of nitrates ( 4.1 , 7.1 , 12.2 ) •Known hypersensitivity to sildenafil or any component of tablet (4.2) •Administration with guanylate cyclase (GC) stimulators, such as riociguat (4.3)
4.1Nitrates Consistent with its known effects on the nitric oxide/cGMP pathway [see Clinical Pharmacology ( 12.1 , 12.2)] , sildenafil tablets were shown to potentiate the hypotensive effects of nitrates, and its administration to patients who are using nitric oxide donors such as organic nitrates or organic nitrites in any form either regularly and/or intermittently is therefore contraindicated. After patients have taken sildenafil tablets, it is unknown when nitrates, if necessary, can be safely administered. Although plasma levels of sildenafil at 24 hours post dose are much lower than at peak concentration, it is unknown whether nitrates can be safely co-administered at this time point [see Dosage and Administration (2.3), Drug Interactions (7.1), and Clinical Pharmacology (12.2)].
4.2Hypersensitivity Reactions Sildenafil tablets are contraindicated in patients with a known hypersensitivity to sildenafil, as contained in sildenafil tablets and REVATIO, or any component of the tablet. Hypersensitivity reactions have been reported, including rash and urticaria [see Adverse Reactions (6.1)].
4.3Concomitant Guanylate Cyclase (GC) Stimulators Do not use sildenafil tablets in patients who are using a GC stimulator, such as riociguat. PDE5 inhibitors, including sildenafil tablets, may potentiate the hypotensive effects of GC stimulators.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS •Patients should not use sildenafil tablets if sexual activity is inadvisable due to cardiovascular status (5.1) •Patients should seek emergency treatment if an erection lasts >4 hours. Use sildenafil tablets with caution in patients predisposed to priapism (5.2) •Patients should stop sildenafil tablets and seek medical care if a sudden loss of vision occurs in one or both eyes, which could be a sign of non arteritic anterior ischemic optic neuropathy (NAION). Sildenafil tablets should be used with caution, and only when the anticipated benefits outweigh the risks, in patients with a history of NAION.
Patients with a”crowded” optic disc may also be at an increased risk of NAION. (5.3) •Patients should stop sildenafil tablets and seek prompt medical attention in the event of sudden decrease or loss of hearing (5.4) •Caution is advised when sildenafil tablets are co-administered with alpha-blockers or anti-hypertensives. Concomitant use may lead to hypotension (5.5) •Decreased blood pressure, syncope, and prolonged erection may occur at higher sildenafil exposures.
In patients taking strong CYP inhibitors, such as ritonavir, sildenafil exposure is increased. Decrease in sildenafil tablets dosage is recommended (2.4, 5.6)
5.1Cardiovascular There is a potential for cardiac risk of sexual activity in patients with preexisting cardiovascular disease. Therefore, treatments for erectile dysfunction, including sildenafil tablets, should not be generally used in men for whom sexual activity is inadvisable because of their underlying cardiovascular status. The evaluation of erectile dysfunction should include a determination of potential underlying causes and the identification of appropriate treatment following a complete medical assessment.
Sildenafil tablets have systemic vasodilatory properties that resulted in transient decreases in supine blood pressure in healthy volunteers (mean maximum decrease of 8.4/5.5 mmHg), [see Clinical Pharmacology (12.2)]. While this normally would be expected to be of little consequence in most patients, prior to prescribing sildenafil tablets, physicians should carefully consider whether their patients with underlying cardiovascular disease could be affected adversely by such vasodilatory effects, especially in combination with sexual activity.
Use with caution in patients with the following underlying conditions which can be particularly sensitive to the actions of vasodilators including sildenafil tablets – those with left ventricular outflow obstruction (e.g., aortic stenosis, idiopathic hypertrophic subaortic stenosis) and those with severely impaired autonomic control of blood pressure. There are no controlled clinical data on the safety or efficacy of sildenafil tablets in the following groups; if prescribed, this should be done with caution. •Patients who have suffered a myocardial infarction, stroke, or life-threatening arrhythmia within the last 6 months; •Patients with resting hypotension (BP <90/50 mmHg) or hypertension (BP >170/110 mmHg); •Patients with cardiac failure or coronary artery disease causing unstable angina.
5.2Prolonged Erection and Priapism Prolonged erection greater than 4 hours and priapism (painful erections greater than 6 hours in duration) have been reported infrequently since market approval of sildenafil tablets. In the event of an erection that persists longer than 4 hours, the patient should seek immediate medical assistance. If priapism is not treated immediately, penile tissue damage and permanent loss of potency could result.
Sildenafil tablets should be used with caution in patients with anatomical deformation of the penis (such as angulation, cavernosal fibrosis or Peyronie's disease), or in patients who have conditions which may predispose them to priapism (such as sickle cell anemia, multiple myeloma, or leukemia). However, there are no controlled clinical data on the safety or efficacy of sildenafil tablets in patients with sickle…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: •Cardiovascular [see Warnings and Precautions (5.1)] •Prolonged Erection and Priapism [see Warnings and Precautions (5.2)] •Effects on the Eye [see Warnings and Precautions (5.3)] •Hearing Loss [ see Warnings and Precautions (5.4)] •Hypotension when Co-administered with Alpha-blockers or Anti-hypertensives [see Warnings and Precautions (5.5)] •Adverse Reactions with the Concomitant Use of Ritonavir [see Warnings and Precautions (5.6)] •Combination with other PDE5 Inhibitors or Other Erectile Dysfunction Therapies [see Warnings and Precautions (5.7)] •Effects on Bleeding [see Warnings and Precautions (5.8)] •Counseling Patients About Sexually Transmitted Diseases [see Warnings and Precautions (5.9)] The most common adverse reactions reported in clinical trials (≥ 2%) are headache, flushing, dyspepsia, abnormal vision, nasal congestion, back pain, myalgia, nausea, dizziness, and rash.
Most common adverse reactions (≥ 2%) include headache, flushing, dyspepsia, abnormal vision, nasal congestion, back pain, myalgia, nausea, dizziness and rash (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Hetero Labs Limited at 866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Sildenafil tablets were administered to over 3700 patients (aged 19 to 87 years) during pre-marketing clinical trials worldwide. Over 550 patients were treated for longer than one year.
In placebo-controlled clinical studies, the discontinuation rate due to adverse reactions for sildenafil tablets (2.5%) was not significantly different from placebo (2.3%). In fixed-dose studies, the incidence of some adverse reactions increased with dose. The type of adverse reactions in flexible-dose studies, which reflect the recommended dosage regimen, was similar to that for fixed-dose studies.
At doses above the recommended dose range, adverse reactions were similar to those detailed in Table 1 below but generally were reported more frequently. Table 1: Adverse Reactions Reported by ≥2% of Patients with Sildenafil Tablets and More Frequently than Placebo in Fixed-Dose Phase II/III Studies Adverse Reaction 25 mg (n=312) 50 mg (n=511) 100 mg (n=506) Placebo (n=607) Headache 16% 21% 28% 7% Flushing 10% 19% 18% 2% Dyspepsia 3% 9% 17% 2% Abnormal vision † 1% 2% 11% 1% Nasal congestion 4% 4% 9% 2% Back pain 3% 4% 4% 2% Myalgia 2% 2% 4% 1% Nausea 2% 3% 3% 1% Dizziness 3% 4% 3% 2% Rash 1% 2% 3% 1% † Abnormal Vision: Mild to moderate in severity and transient, predominantly color tinge to vision, but also increased sensitivity to light, or blurred vision.
When sildenafil tablets were taken as recommended (on an as-needed basis) in flexible-dose, placebo-controlled clinical trials of two to twenty-six weeks duration, patients took sildenafil tablets at least once weekly, and the following adverse reactions were reported: Table 2. Adverse Reactions Reported by ≥2% of Patients Treated with Sildenafil Tablets and More Frequent than Placebo in Flexible-Dose Phase II/III Studies Adverse Reaction SILDENAFIL TABLETS PLACEBO N=734 N=725 Headache 16% 4% Flushing 10% 1% Dyspepsia 7% 2% Nasal Congestion 4% 2% Abnormal Vision † 3% 0% Back pain 2% 2% Dizziness 2% 1% Rash 2% 1% † Abnormal Vision: Mild and transient, predominantly color tinge to vision, but also increased sensitivity to light or blurred vision.
In these studies, only one patient discontinued due to abnormal vision. The following events occurred in <2% of patients in controlled clinical trials; a causal relationship to sildenafil tablets is uncertain. Reported events include those with a plausible relation to drug use; omitted are min…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS •Sildenafil tablets can potentiate the hypotensive effects of nitrates, alpha blockers, and anti-hypertensives ( 4.1 , 5.5 , 7.1 , 7.2 , 7.3 , 12.2 ) •With concomitant use of alpha blockers, initiate sildenafil tablets at 25 mg dose (2.3) •CYP3A4 inhibitors (e.g., ritonavir, ketoconazole, itraconazole, erythromycin): Increase sildenafil tablets exposure (2.4 , 7.4, 12.3 ) •Ritonavir: Do not exceed a maximum single dose of 25 mg in a 48 hour period ( 2.4 , 5.6) •Erythromycin or strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, saquinavir): Consider a starting dose of 25 mg (2.4, 7.4)
7.1Nitrates Administration of sildenafil tablets with nitric oxide donors such as organic nitrates or organic nitrites in any form is contraindicated. Consistent with its known effects on the nitric oxide/cGMP pathway, sildenafil tablets were shown to potentiate the hypotensive effects of nitrates [see Dosage and Administration (2.3), Contraindications (4.1), Clinical Pharmacology (12.2)].
7.2Alpha-blockers Use caution when co-administering alpha-blockers with sildenafil tablets because of potential additive blood pressure-lowering effects. When sildenafil tablets are co-administered with an alpha-blocker, patients should be stable on alpha-blocker therapy prior to initiating sildenafil tablets treatment and sildenafil tablets should be initiated at the lowest dose [see Dosage and Administration (2.3), Warnings and Precautions (5.5), Clinical Pharmacology (12.2)].
7.3Amlodipine When sildenafil tablets 100 mg were co-administered with amlodipine (5 mg or 10 mg) to hypertensive patients, the mean additional reduction on supine blood pressure was 8 mmHg systolic and 7 mmHg diastolic [see Warnings and Precautions (5.5), Clinical Pharmacology (12.2)].
7.4Ritonavir and other CYP3A4 inhibitors Co-administration of ritonavir, a strong CYP3A4 inhibitor, greatly increased the systemic exposure of sildenafil (11-fold increase in AUC). It is therefore recommended not to exceed a maximum single dose of 25 mg of sildenafil tablets in a 48 hour period [see Dosage and Administration ( 2.4), Warnings and Precautions (5.6), Clinical Pharmacology ( 12.3)]. Co-administration of erythromycin, a moderate CYP3A4 inhibitor, resulted in a 160% and 182% increases in sildenafil Cmax and AUC, respectively.
Co-administration of saquinavir, a strong CYP3A4 inhibitor, resulted in 140% and 210% increases in sildenafil Cmax and AUC, respectively. Stronger CYP3A4 inhibitors such as ketoconazole or itraconazole could be expected to have greater effects than seen with saquinavir. A starting dose of 25 mg of sildenafil tablets should be considered in patients taking erythromycin or strong CYP3A4 inhibitors (such as saquinavir, ketoconazole, itracanozole) [see Dosage and Administration (2.4), Clinical Pharmacology ( 12.3)].
7.5Alcohol In a drug-drug interaction study sildenafil 50 mg given with alcohol 0.5 g/kg in which mean maximum blood alcohol levels of 0.08% was achieved, sildenafil did not potentiate the hypotensive effect of alcohol in healthy volunteers [ see Clinical Pharmacology ( 12.2) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS •Geriatric use: Consider a starting dose of 25 mg (2.5 , 8.5) •Severe renal impairment: Consider a starting dose of 25 mg ( 2.5, 8.6) •Hepatic impairment: Consider a starting dose of 25 mg(2.5, 8.7)
8.1Pregnancy Risk Summary Sildenafil tablets is not indicated for use in females. There are no data with the use of sildenafil tablets in pregnant women to inform any drug-associated risks for adverse developmental outcomes. Animal reproduction studies conducted with sildenafil did not show adverse developmental outcomes when administered during organogenesis in rats and rabbits at oral doses up to 16 and 32 times, respectively, the maximum recommended human dose (MRHD) of 100 mg/day on a mg/m2 basis (see Data).
Data Animal Data No evidence of teratogenicity, embryotoxicity or fetotoxicity was observed in rats and rabbits which received up to 200 mg/kg/day during organogenesis. These doses represent, respectively, about 16 and 32 times the MRHD on a mg/m2 basis in a 50 kg subject. In the rat pre- and postnatal development study, the no observed adverse effect dose was 30 mg/kg/day given for 36 days, about 2 times the MRHD on a mg/m2 basis in a 50 kg subject.
8.2Lactation Risk Summary Sildenafil tablets is not indicated for use in females. Limited data indicate that sildenafil and its active metabolite are present in human milk. There is no information on the effects on the breastfed child, or the effects on milk production.
8.4Pediatric Use Sildenafil tablets are not indicated for use in pediatric patients. Safety and effectiveness have not been established in pediatric patients.
8.5Geriatric Use Healthy elderly volunteers (65 years or over) had a reduced clearance of sildenafil resulting in approximately 84% and 107% higher plasma AUC values of sildenafil and its active N-desmethyl metabolite, respectively, compared to those seen in healthy young volunteers (18 to 45 years) [see Clinical Pharmacology (12.3)]. Due to age-differences in plasma protein binding, the corresponding increase in the AUC of free (unbound) sildenafil and its active N-desmethyl metabolite were 45% and 57%, respectively [see Clinical Pharmacology (12.3)].
Of the total number of subjects in clinical studies of sildenafil tablets, 18% were 65 years and older, while 2% were 75 years and older. No overall differences in safety or efficacy were observed between older (≥ 65 years of age) and younger (< 65 years of age) subjects. However, since higher plasma levels may increase the incidence of adverse reactions, a starting dose of 25 mg should be considered in older subjects due to the higher systemic exposure [see Dosage and Administration (2.5)].
8.6Renal Impairment No dose adjustment is required for mild (CLcr=50 to 80 mL/min) and moderate (CLcr=30 to 49 mL/min) renal impairment. In volunteers with severe renal impairment (Clcr<30 mL/min), sildenafil clearance was reduced, resulting in higher plasma exposure of sildenafil (~2 fold), approximately doubling of Cmax and AUC. A starting dose of 25 mg should be considered in patients with severe renal impairment [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3)].
8.7Hepatic Impairment In volunteers with hepatic impairment (Child-Pugh Class A and B), sildenafil clearance was reduced, resulting in higher plasma exposure of sildenafil (47% for Cmax and 85% for AUC). The pharmacokinetics of sildenafil in patients with severely impaired hepatic function (Child-Pugh Class C) have not been studied. A starting dose of 25 mg should be considered in patients with any degree of hepatic impairment [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3)].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Sildenafil tablets is not indicated for use in females. There are no data with the use of sildenafil tablets in pregnant women to inform any drug-associated risks for adverse developmental outcomes. Animal reproduction studies conducted with sildenafil did not show adverse developmental outcomes when administered during organogenesis in rats and rabbits at oral doses up to 16 and 32 times, respectively, the maximum recommended human dose (MRHD) of 100 mg/day on a mg/m2 basis (see Data).
Data Animal Data No evidence of teratogenicity, embryotoxicity or fetotoxicity was observed in rats and rabbits which received up to 200 mg/kg/day during organogenesis. These doses represent, respectively, about 16 and 32 times the MRHD on a mg/m2 basis in a 50 kg subject. In the rat pre- and postnatal development study, the no observed adverse effect dose was 30 mg/kg/day given for 36 days, about 2 times the MRHD on a mg/m2 basis in a 50 kg subject.
🧒 Pediatric Use ▾
8.4Pediatric Use Sildenafil tablets are not indicated for use in pediatric patients. Safety and effectiveness have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Healthy elderly volunteers (65 years or over) had a reduced clearance of sildenafil resulting in approximately 84% and 107% higher plasma AUC values of sildenafil and its active N-desmethyl metabolite, respectively, compared to those seen in healthy young volunteers (18 to 45 years) [see Clinical Pharmacology (12.3)]. Due to age-differences in plasma protein binding, the corresponding increase in the AUC of free (unbound) sildenafil and its active N-desmethyl metabolite were 45% and 57%, respectively [see Clinical Pharmacology (12.3)].
Of the total number of subjects in clinical studies of sildenafil tablets, 18% were 65 years and older, while 2% were 75 years and older. No overall differences in safety or efficacy were observed between older (≥ 65 years of age) and younger (< 65 years of age) subjects. However, since higher plasma levels may increase the incidence of adverse reactions, a starting dose of 25 mg should be considered in older subjects due to the higher systemic exposure [see Dosage and Administration (2.5)].
🆘 Overdosage ▾
10 OVERDOSAGE In studies with healthy volunteers of single doses up to 800 mg, adverse reactions were similar to those seen at lower doses but incidence rates and severities were increased. In cases of overdose, standard supportive measures should be adopted as required. Renal dialysis is not expected to accelerate clearance as sildenafil is highly bound to plasma proteins and it is not eliminated in the urine.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The physiologic mechanism of erection of the penis involves release of nitric oxide (NO) in the corpus cavernosum during sexual stimulation. NO then activates the enzyme guanylate cyclase, which results in increased levels of cyclic guanosine monophosphate (cGMP), producing smooth muscle relaxation in the corpus cavernosum and allowing inflow of blood. Sildenafil enhances the effect of NO by inhibiting phosphodiesterase type 5 (PDE5), which is responsible for degradation of cGMP in the corpus cavernosum.
Sildenafil has no direct relaxant effect on isolated human corpus cavernosum. When sexual stimulation causes local release of NO, inhibition of PDE5 by sildenafil causes increased levels of cGMP in the corpus cavernosum, resulting in smooth muscle relaxation and inflow of blood to the corpus cavernosum. Sildenafil at recommended doses has no effect in the absence of sexual stimulation.
Binding Characteristics Studies in vitro have shown that sildenafil is selective for PDE5. Its effect is more potent on PDE5 than on other known phosphodiesterases (10-fold for PDE6, >80-fold for PDE1, >700-fold for PDE2, PDE3, PDE4, PDE7, PDE8, PDE9, PDE10, and PDE11). Sildenafil is approximately 4,000-fold more selective for PDE5 compared to PDE3.
PDE3 is involved in control of cardiac contractility. Sildenafil is only about 10-fold as potent for PDE5 compared to PDE6, an enzyme found in the retina which is involved in the phototransduction pathway of the retina. This lower selectivity is thought to be the basis for abnormalities related to color vision [see Clinical Pharmacology (12.2)].
In addition to human corpus cavernosum smooth muscle, PDE5 is also found in other tissues including platelets, vascular and visceral smooth muscle, and skeletal muscle, brain, heart, liver, kidney, lung, pancreas, prostate, bladder, testis, and seminal vesicle. The inhibition of PDE5 in some of these tissues by sildenafil may be the basis for the enhanced platelet antiaggregatory activity of NO observed in vitro, an inhibition of platelet thrombus formation in vivo and peripheral arterial-venous dilatation in vivo .
12.2Pharmacodynamics Effects of Sildenafil Tablets on Erectile Response: In eight double-blind, placebo-controlled crossover studies of patients with either organic or psychogenic erectile dysfunction, sexual stimulation resulted in improved erections, as assessed by an objective measurement of hardness and duration of erections (RigiScan®), after sildenafil tablets administration compared with placebo. Most studies assessed the efficacy of sildenafil tablets approximately 60 minutes post dose. The erectile response, as assessed by RigiScan®, generally increased with increasing sildenafil dose and plasma concentration.
The time course of effect was examined in one study, showing an effect for up to 4 hours but the response was diminished compared to 2 hours. Effects of Sildenafil Tablets on Blood Pressure: Single oral doses of sildenafil (100 mg) administered to healthy volunteers produced decreases in sitting blood pressure (mean maximum decrease in systolic/diastolic blood pressure of 8.3/5.3 mmHg). The decrease in sitting blood pressure was most notable approximately 1 to 2 hours after dosing, and was not different than placebo at 8 hours.
Similar effects on blood pressure were noted with 25 mg, 50 mg and 100 mg of sildenafil tablets, therefore the effects are not related to dose or plasma levels within this dosage range. Larger effects were recorded among patients receiving concomitant nitrates [see Contraindications (4.1)]. Figure 1: Mean Change from Baseline in Sitting Systolic Blood Pressure, Healthy Volunteers.
Effects of Sildenafil Tablets on Blood Pressure When Nitroglycerin is Subsequently Administered : Based on the pharmacokinetic profile of a single 100 mg oral dose given to healthy normal volunteers, the plasma levels of sildenafil at 24 hours post dose are approximately 2 ng/mL (co…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The physiologic mechanism of erection of the penis involves release of nitric oxide (NO) in the corpus cavernosum during sexual stimulation. NO then activates the enzyme guanylate cyclase, which results in increased levels of cyclic guanosine monophosphate (cGMP), producing smooth muscle relaxation in the corpus cavernosum and allowing inflow of blood. Sildenafil enhances the effect of NO by inhibiting phosphodiesterase type 5 (PDE5), which is responsible for degradation of cGMP in the corpus cavernosum.
Sildenafil has no direct relaxant effect on isolated human corpus cavernosum. When sexual stimulation causes local release of NO, inhibition of PDE5 by sildenafil causes increased levels of cGMP in the corpus cavernosum, resulting in smooth muscle relaxation and inflow of blood to the corpus cavernosum. Sildenafil at recommended doses has no effect in the absence of sexual stimulation.
Binding Characteristics Studies in vitro have shown that sildenafil is selective for PDE5. Its effect is more potent on PDE5 than on other known phosphodiesterases (10-fold for PDE6, >80-fold for PDE1, >700-fold for PDE2, PDE3, PDE4, PDE7, PDE8, PDE9, PDE10, and PDE11). Sildenafil is approximately 4,000-fold more selective for PDE5 compared to PDE3.
PDE3 is involved in control of cardiac contractility. Sildenafil is only about 10-fold as potent for PDE5 compared to PDE6, an enzyme found in the retina which is involved in the phototransduction pathway of the retina. This lower selectivity is thought to be the basis for abnormalities related to color vision [see Clinical Pharmacology (12.2)].
In addition to human corpus cavernosum smooth muscle, PDE5 is also found in other tissues including platelets, vascular and visceral smooth muscle, and skeletal muscle, brain, heart, liver, kidney, lung, pancreas, prostate, bladder, testis, and seminal vesicle. The inhibition of PDE5 in some of these tissues by sildenafil may be the basis for the enhanced platelet antiaggregatory activity of NO observed in vitro, an inhibition of platelet thrombus formation in vivo and peripheral arterial-venous dilatation in vivo .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Sildenafil Tablets USP, 50 mg are white colored, round-shaped, biconvex, film coated tablets debossed with ' I ' on one side and '36'on the other side. NDC: 71335-1028-6: 20 Tablets in a BOTTLE NDC: 71335-1028-1: 30 Tablets in a BOTTLE NDC: 71335-1028-2: 10 Tablets in a BOTTLE NDC: 71335-1028-3: 15 Tablets in a BOTTLE NDC: 71335-1028-4: 90 Tablets in a BOTTLE NDC: 71335-1028-5: 60 Tablets in a BOTTLE Recommended Storage: Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Sildenafil Tablet, USP an oral therapy for erectile dysfunction, is the citrate salt of sildenafil, a selective inhibitor of cyclic guanosine monophosphate (cGMP)-specific phosphodiesterase type 5 (PDE5). Sildenafil citrate, USP is designated chemically as 1-[[3-(6,7-dihydro-1-methyl-7-oxo-3-propyl-1H-pyrazolo[4,3-d]pyrimidin-5-yl)-4-ethoxyphenyl]sulfonyl]-4-methylpiperazine citrate and has the following structural formula: Sildenafil citrate, USP is a white to off-white crystalline powder with a solubility of 3.5 mg/mL in water and a molecular weight of 666.7.
Sildenafil tablet, USP is formulated as white, film-coated rounde-shaped tablets equivalent to 25 mg, 50 mg and 100 mg of sildenafil for oral administration. In addition to the active ingredient, sildenafil citrate, USP each tablet contains the following inactive ingredients: croscarmellose sodium, dibasic calcium phosphate anhydrous, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, titanium dioxide and triacetin.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information) Nitrates Physicians should discuss with patients the contraindication of sildenafil tablets with regular and/or intermittent use of nitric oxide donors, such as organic nitrates or organic nitrites in any form [see Contraindications (4.1)]. Guanylate Cyclase (GC) Stimulators Physicians should discuss with patients the contraindication of sildenafil tablets with use of guanylate cyclase stimulators such as riociguat [see Contraindications (4.3)].
Concomitant Use with Drugs Which Lower Blood Pressure Physicians should advise patients of the potential for sildenafil tablets to augment the blood pressure lowering effect of alpha-blockers and anti-hypertensive medications. Concomitant administration of sildenafil tablets and an alpha-blocker may lead to symptomatic hypotension in some patients. Therefore, when sildenafil tablets are co-administered with alpha-blockers, patients should be stable on alpha-blocker therapy prior to initiating sildenafil tablets treatment and sildenafil tablets should be initiated at the lowest dose [see Warnings and Precautions (5.5)].
Cardiovascular Considerations Physicians should discuss with patients the potential cardiac risk of sexual activity in patients with preexisting cardiovascular risk factors. Patients who experience symptoms (e.g., angina pectoris, dizziness, nausea) upon initiation of sexual activity should be advised to refrain from further activity and should discuss the episode with their physician [see Warnings and Precautions (5.1)]. Sudden Loss of Vision Physicians should advise patients to stop use of all PDE5 inhibitors, including sildenafil tablets, and seek medical attention in the event of a sudden loss of vision in one or both eyes.
Such an event may be a sign of non-arteritic anterior ischemic optic neuropathy (NAION), a cause of decreased vision including possible permanent loss of vision, that has been reported rarely post-marketing in temporal association with the use of all PDE5 inhibitors. Physicians should also discuss with patients the increased risk of NAION among the general population in patients with a “crowded” optic disc, although evidence is insufficient to support screening of prospective users of PDE5 inhibitor, including sildenafil tablets, for this uncommon condition [see Warnings and Precautions (5.3) and Adverse Reactions (6.2)].
Sudden Hearing Loss Physicians should advise patients to stop taking PDE5 inhibitors, including sildenafil tablets, and seek prompt medical attention in the event of sudden decrease or loss of hearing. These events, which may be accompanied by tinnitus and dizziness, have been reported in temporal association to the intake of PDE5 inhibitors, including sildenafil tablets. It is not possible to determine whether these events are related directly to the use of PDE5 inhibitors or to other factors [see Warnings and Precautions (5.4) and Adverse Reactions (6.2)].
Priapism Physicians should warn patients that prolonged erections greater than 4 hours and priapism (painful erections greater than 6 hours in duration) have been reported infrequently since market approval of sildenafil tablets. In the event of an erection that persists longer than 4 hours, the patient should seek immediate medical assistance. If priapism is not treated immediately, penile tissue damage and permanent loss of potency may result [see Warnings and Precautions (5.2)].
Avoid Use with other PDE5 Inhibitors Physicians should inform patients not to take sildenafil tablets with other PDE5 inhibitors including REVATIO or other pulmonary arterial hypertension (PAH) treatments containing sildenafil. Sildenafil is also marketed as REVATIO for the treatment of PAH. The safety and efficacy of sildenafil tablets with other PDE5 inhibitors, including REVATIO, have not been studied [see Warnings and Precautions (5.7)].
Sexually Transmitted Disease The use of si…