
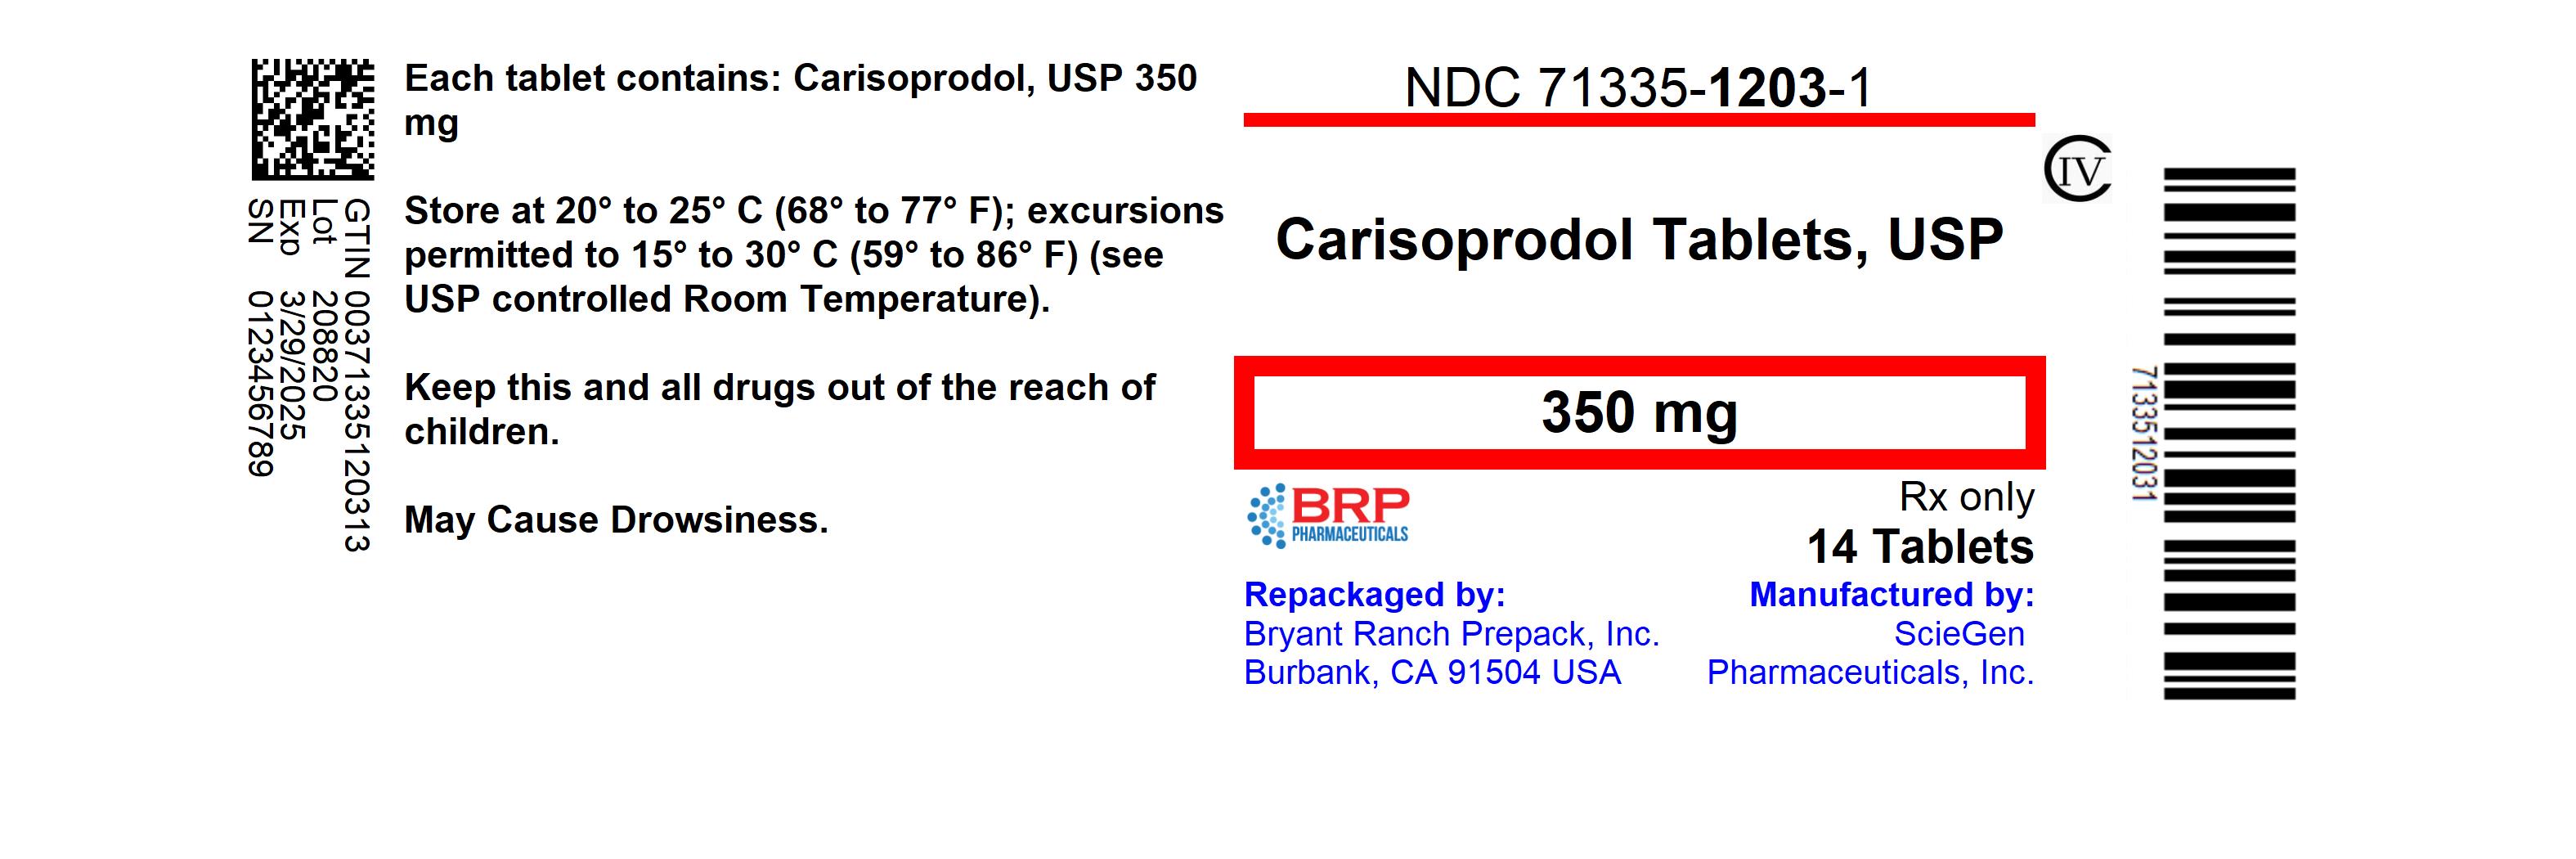
CARISOPRODOL 350 mg Tablet, 20-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Muscle Relaxant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Carisoprodol is used with rest, physical therapy, and other measures to relax muscles and relieve pain and discomfort caused by strains, sprains, and other muscle injuries. Carisoprodol is in a class of medications called skeletal muscle relaxants. It works by acting in the brain and nervous system to allow the muscles to relax.
Read the full MedlinePlus article ↗- Carisoprodol — you may know it by the brand name Soma — is a short-term muscle relaxant for adults dealing with acute muscle pain and discomfort, like a back injury or muscle strai...
- Yes, drowsiness is the most common side effect — it happened in up to 17% of people in clinical trials. You should not drive or operate heavy machinery until you know how carisopro...
- Will it make me really drowsy? Can I drive?
- There is a real risk. Carisoprodol can be habit-forming, and cases of abuse and dependence have been reported — especially with prolonged use or in people with a history of substan...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Carisoprodol — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1410 | $2.82 / 20 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carisoprodol 350 mg 42543-0700-01 | Vensun | 100 tablets | $0.051 | AA | FDA listed | — |
| carisoprodol 350 mg 16571-0781-01 | Rising | 100 tablets | $0.067 | AB | Availability likely | — |
| Carisoprodol 350 mg 50228-0109-01 | ScieGen | 100 tablets | $0.067 | AA | Availability likely | — |
| Carisoprodol 350 mg 50742-0656-01 | Ingenus | 100 tablets | $0.067 | AA | Availability likely | — |
| Carisoprodol 350 mg 62135-0241-12 | Chartwell | 120 tablets | $0.067 | AA | Availability likely | — |
| Carisoprodol Tablets, USP, 350 mg 63561-0127-01 | Granulation | 100 tablets | $0.067 | AA | Availability likely | — |
| Carisoprodol 350 mg 69367-0420-01 | Westminster | 100 tablets | $0.067 | AB | Availability likely | — |
| Carisoprodol 350 mg 69584-0111-10 | Oxford | 100 tablets | $0.067 | AA | Availability likely | — |
| carisoprodol 350 mg 65862-0158-01 | Aurobindo | 100 tablets | $0.071 | — | FDA listed | — |
| Soma 350 mg 00037-2001-01 | Viatris | 100 tablets | $11.386 | AB | Availability likely | — |
| Carisoprodol 350 mg 45865-0233-30 | Medsource | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 50090-5953-05 | A-S | 90 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 50090-5955-00 | A-S | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 52536-0688-10 | Wilshire | 100 tablets | — | AB | FDA listed | — |
| Carisoprodol 350 mg 60760-0397-90 | St. | 90 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 61919-0878-60 | Direct_Rx | 60 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-2416-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-8477-01 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-8478-01 | Bryant | 500 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 63629-8479-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 68071-3421-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Carisoprodol 350 mg 68071-5075-03 | NuCare | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 70518-2800-00 | REMEDYREPACK | 60 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 70518-3792-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Carisoprodol 350 mg 71205-0241-20 | Proficient | 20 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71205-0339-30 | Proficient | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71205-0704-30 | Proficient | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mgthis 71335-1203-04 | Bryant | 20 tablets | — | AA | FDA listed | — |
| Carisoprodol Tablets, USP, 350 mg 71335-3018-01 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 71335-9613-00 | Bryant | 56 tablets | — | AB | FDA listed | — |
| Carisoprodol 350 mg 71335-9621-00 | Bryant | 56 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71610-0617-30 | Aphena | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 71610-0761-30 | Aphena | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72162-1524-00 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72162-1928-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol Tablets, USP, 350 mg 72162-2525-00 | Bryant | 1000 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72189-0310-30 | Directrx | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72189-0386-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Carisoprodol 350 mg 72789-0182-01 | PD-Rx | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 72789-0190-14 | PD-Rx | 14 tablets | — | AA | FDA listed | — |
| Carisoprodol Tablets, USP, 350 mg 72789-0477-01 | PD-Rx | 100 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 76420-0646-01 | Asclemed | 100 tablets | — | AA | FDA listed | — |
| carisoprodol 350 mg 76420-0853-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Carisoprodol 350 mg 80425-0291-01 | Advanced | 30 tablets | — | AA | FDA listed | — |
| Carisoprodol 350 mg 82868-0062-30 | Northwind | 30 tablets | — | AA | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1203-00 | 56 TABLET in 1 BOTTLE (71335-1203-0) | 2021-12-28 | Active |
| 71335-1203-01 | 14 TABLET in 1 BOTTLE (71335-1203-1) | 2019-05-10 | Active |
| 71335-1203-02 | 28 TABLET in 1 BOTTLE (71335-1203-2) | 2021-12-28 | Active |
| 71335-1203-03 | 60 TABLET in 1 BOTTLE (71335-1203-3) | 2019-04-25 | Active |
| 71335-1203-04 You're viewing this | 20 TABLET in 1 BOTTLE (71335-1203-4) | 2019-05-17 | Active |
| 71335-1203-05 | 30 TABLET in 1 BOTTLE (71335-1203-5) | 2019-05-17 | Active |
| 71335-1203-06 | 84 TABLET in 1 BOTTLE (71335-1203-6) | 2021-12-28 | Active |
| 71335-1203-07 | 90 TABLET in 1 BOTTLE (71335-1203-7) | 2019-05-20 | Active |
| 71335-1203-08 | 100 TABLET in 1 BOTTLE (71335-1203-8) | 2021-12-28 | Active |
| 71335-1203-09 | 120 TABLET in 1 BOTTLE (71335-1203-9) | 2019-05-06 | Active |
You're viewing one of 10 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1203-04?
What is the difference between NDC 71335-1203-04 and NDC 71335-1203-01?
What NDC number is used to bill for this package of CARISOPRODOL 350 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Carisoprodol is indicated for the relief of discomfort associated with acute, painful musculoskeletal conditions in adults. Limitation of Use Carisoprodol should only be used for short periods (up to two or three weeks) because adequate evidence of effectiveness for more prolonged use has not been established and because acute, painful musculoskeletal conditions are generally of short duration. [ see Dosage and Administration (2) ]. Carisoprodol is a muscle relaxant indicated for the relief of discomfort associated with acute, painful musculoskeletal conditions in adults.
(1) Limitation of Use Should only be used for acute treatment periods up to two or three weeks (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of carisoprodol tablets is 250 mg to 350 mg three times a day and at bedtime. The recommended maximum duration of carisoprodol tablets use is up to two or three weeks. Recommended dose is 250 mg to 350 mg three times a day and at bedtime. (2)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Carisoprodol tablets USP, 350 mg: round, convex, white tablets, debossed with SG 109 on one side. Tablets: 350 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Carisoprodol tablet is contraindicated in patients with a history of acute intermittent porphyria or a hypersensitivity reaction to a carbamate such as meprobamate. Acute intermittent porphyria (4) Hypersensitivity reactions to a carbamate such as meprobamate (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Due to sedative properties, may impair ability to perform hazardous tasks such as driving or operating machinery (5.1) Additive sedative effects when used with other CNS depressants including alcohol (5.1) Cases of abuse, dependence and withdrawal (5.2 , 9.2 , 9.3) Seizures (5.3)
5.1Sedation Carisoprodol has sedative properties (in the low back pain trials, 13% to 17% of patients who received carisoprodol experienced sedation compared to 6% of patients who received placebo) [ see ADVERSE REACTIONS (6.1) ] and may impair the mental and/or physical abilities required for the performance of potentially hazardous tasks such as driving a motor vehicle or operating machinery. There have been post-marketing reports of motor vehicle accidents associated with the use of carisoprodol. Since the sedative effects of carisoprodol and other CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) may be additive, appropriate caution should be exercised with patients who take more than one of these CNS depressants simultaneously.
5.2Abuse, Dependence, and Withdrawal Carisoprodol, the active ingredient in carisoprodol tablet, has been subject to abuse, dependence, and withdrawal, misuse and criminal diversion. [ see Drug Abuse and Dependence (9.1, 9.2, 9.3) ]. Abuse of carisoprodol poses a risk of overdosage which may lead to death, CNS and respiratory depression, hypotension, seizures and other disorders [ see overdosage (10) ]. Post-marketing experience cases of carisoprodol abuse and dependence have been reported in patients with prolonged use and a history of drug abuse.
Although most of these patients took other drugs of abuse, some patients solely abused carisoprodol. Withdrawal symptoms have been reported following abrupt cessation of carisoprodol after prolonged use. Reported withdrawal symptoms included insomnia, vomiting, abdominal cramps, headache, tremors, muscle twitching, ataxia, hallucinations, and psychosis.
One of carisoprodol’s metabolites, meprobamate (a controlled substance), may also cause dependence [ see Clinical Pharmacology (12.3) ]. To reduce the risk of carisoprodol abuse assess the risk of abuse prior to prescribing. After prescribing, limit the length of treatment to three weeks for the relief of acute musculoskeletal discomfort, keep careful prescription records, monitor for signs of abuse and overdose, and educate patients and their families about abuse and on proper storage and disposal.
5.3Seizures There have been post-marketing reports of seizures in patients who received carisoprodol. Most of these cases have occurred in the setting of multiple drug overdoses (including drugs of abuse, illegal drugs, and alcohol) [ see Overdosage (10) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence > 2%) are drowsiness, dizziness, and headache (6.1) To report SUSPECTED ADVERSE REACTIONS, contact ScieGen Pharmaceuticals, Inc. at 1-855-724-3436 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect rates observed in practice. The data described below are based on 1,387 patients pooled from two double blind, randomized, multicenter, placebo controlled, one-week trials in adult patients with acute, mechanical, lower back pain [ see Clinical Studies (14) ].
In these studies, patients were treated with 250 mg of carisoprodol, 350 mg of carisoprodol, or placebo three times a day and at bedtime for seven days. The mean age was about 41 years old with 54% females and 46% males and 74 % Caucasian, 16 % Black, 9% Asian, and 2% other. There were no deaths and there were no serious adverse reactions in these two trials.
In these two studies, 2.7%, 2%, and 5.4%, of patients treated with placebo, 250 mg of carisoprodol, and 350 mg of carisoprodol, respectively, discontinued due to adverse events; and 0.5%, 0.5%, and 1.8% of patients treated with placebo, 250 mg of carisoprodol, and 350 mg of carisoprodol, respectively, discontinued due to central nervous system adverse reactions. Table 1 displays adverse reactions reported with frequencies greater than 2% and more frequently than placebo in patients treated with carisoprodol in the two trials described above.
Table 1. Patients with Adverse Reactions in Controlled Studies Adverse Reaction Placebo (n=560) n (%) Carisoprodol 250 mg (n=548) n (%) Carisoprodol 350 mg (n=279) n (%) Drowsiness 31 (6) 73 (13) 47 (17) Dizziness 11 (2) 43 (8) 19 (7) Headache 11 (2) 26 (5) 9 (3)
6.2Post-marketing Experience The following events have been reported during postapproval use of carisoprodol. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cardiovascular: Tachycardia, postural hypotension, and facial flushing [ see Overdosage (10) ].
Central Nervous System: Drowsiness, dizziness, vertigo, ataxia, tremor, agitation, irritability, headache, depressive reactions, syncope, insomnia, and seizures [ see Overdosage (10) ]. Gastrointestinal: Nausea, vomiting, and epigastric discomfort. Hematologic: Leukopenia, pancytopenia
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) - additive sedative effects ( 5.1 , 7.1 )
7.1CNS Depressants The sedative effects of carisoprodol and other CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) may be additive. Therefore, caution should be exercised with patients who take more than one of these CNS depressants simultaneously. Concomitant use of carisoprodol and meprobamate, a metabolite of carisoprodol, is not recommended [ see Warnings and Precautions (5.1) ].
7.2CYP2C19 Inhibitors and Inducers Carisoprodol is metabolized in the liver by CYP2C19 to form meprobamate [ see Clinical Pharmacology (12.3) ]. Co-administration of CYP2C19 inhibitors, such as omeprazole or fluvoxamine, with carisoprodol could result in increased exposure of carisoprodol and decreased exposure of meprobamate. Co-administration of CYP2C19 inducers, such as rifampin or St.
John’s Wort, with carisoprodol could result in decreased exposure of carisoprodol and increased exposure of meprobamate. Low dose aspirin also showed an induction effect on CYP2C19. The full pharmacological impact of these potential alterations of exposures in terms of either efficacy or safety of carisoprodol is unknown.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Data over many decades of carisoprodol use in pregnancy have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Data on meprobamate, the primary metabolite of carisoprodol, also do not show a consistent association between maternal use of meprobamate and an increased risk of major birth defects (see Data) . In a published animal reproduction study, pregnant mice administered carisoprodol orally at 2.6- and 4.1-times the maximum recommended human dose ([MRHD] of 1,400 mg per day [350 mg QID] based on body surface area [BSA] comparison) from gestation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival (see Data) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Retrospective case-control and cohort studies of meprobamate use during the first trimester of pregnancy have not consistently identified an increased risk or pattern of major birth defects. For children exposed to meprobamate in-utero, one study found no adverse effect on mental or motor development or IQ scores. Animal Data Embryofetal development studies in animals have not been completed.
In a published pre- and post-natal development animal study, pregnant mice administered carisoprodol orally at 300 mg/kg/day, 750 mg/kg/day, or 1,200 mg/kg/day (approximately 1-, 2.6-, and 4.1-times the MRHD based on BSA comparison) from 7-days prior to gestation through birth and from lactation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival at 2.6- and 4.1-times the MRHD.
8.2Lactation Risk Summary Data from published literature report that carisoprodol and its metabolite, meprobamate, are present in breastmilk. There are no data on the effect of carisoprodol on milk production. There is one report of sedation in an infant who was breastfed by a mother taking carisoprodol (see Clinical Considerations) .
Because there have been no consistent reports of adverse events in breastfed infants over decades of use, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for carisoprodol and any potential adverse effects on the breastfed infant from carisoprodol or from the underlying maternal condition. Clinical Considerations Infants exposed to carisoprodol through breast milk should be monitored for sedation.
8.4Pediatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in pediatric patients less than 16 years of age have not been established.
8.5Geriatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in patients over 65 years old have not been established.
8.6Renal Impairment The safety and pharmacokinetics of carisoprodol in patients with renal impairment have not been evaluated. Since carisoprodol is excreted by the kidney, caution should be exercised if carisoprodol is administered to patients with impaired renal function. Carisoprodol is dialyzable by hemodialysis and peritoneal dialysis.
8.7Hepatic Impairment The safety and pharmacokinetics of carisoprodol in patients with hepatic impairment have not been evaluated. Since carisoprodol is metabolized in the liver, caution should be exercised if carisoprodol is administered to patients with impaired hepatic function.
8.8Patients with Reduced CYP2C19 Activity Patients with reduced CYP2C19 activity have higher exposure to carisoprodol. Therefore, caution should be exercised in administration of carisoprodol to these patients. [ see Clinical Pharmacology (12.3) ].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Data over many decades of carisoprodol use in pregnancy have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Data on meprobamate, the primary metabolite of carisoprodol, also do not show a consistent association between maternal use of meprobamate and an increased risk of major birth defects (see Data) . In a published animal reproduction study, pregnant mice administered carisoprodol orally at 2.6- and 4.1-times the maximum recommended human dose ([MRHD] of 1,400 mg per day [350 mg QID] based on body surface area [BSA] comparison) from gestation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival (see Data) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Retrospective case-control and cohort studies of meprobamate use during the first trimester of pregnancy have not consistently identified an increased risk or pattern of major birth defects. For children exposed to meprobamate in-utero, one study found no adverse effect on mental or motor development or IQ scores. Animal Data Embryofetal development studies in animals have not been completed.
In a published pre- and post-natal development animal study, pregnant mice administered carisoprodol orally at 300 mg/kg/day, 750 mg/kg/day, or 1,200 mg/kg/day (approximately 1-, 2.6-, and 4.1-times the MRHD based on BSA comparison) from 7-days prior to gestation through birth and from lactation through weaning resulted in reduced fetal weights, postnatal weight gain, and postnatal survival at 2.6- and 4.1-times the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in pediatric patients less than 16 years of age have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The efficacy, safety, and pharmacokinetics of carisoprodol in patients over 65 years old have not been established.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Overdosage of carisoprodol commonly produces CNS depression. Death, coma, respiratory depression, hypotension, seizures, delirium, hallucinations, dystonic reactions, nystagmus, blurred vision, mydriasis, euphoria, muscular incoordination, rigidity, and/or headache have been reported with carisoprodol overdosage. Serotonin syndrome has been reported with carisoprodol intoxication.
Many of the carisoprodol overdoses have occurred in the setting of multiple drug overdoses (including drugs of abuse, illegal drugs, and alcohol). The effects of an overdose of carisoprodol and other CNS depressants (e.g., alcohol, benzodiazepines, opioids, tricyclic antidepressants) can be additive even when one of the drugs has been taken in the recommended dosage. Fatal accidental and non-accidental overdoses of carisoprodol have been reported alone or in combination with CNS depressants.
Treatment of Overdosage Basic life support measures should be instituted as dictated by the clinical presentation of the carisoprodol overdose. Vomiting should not be induced because of the risk of CNS and respiratory depression, and subsequent aspiration. Circulatory support should be administered with volume infusion and vasopressor agents if needed.
Seizures should be treated with intravenous benzodiazepines and the reoccurrence of seizures may be treated with phenobarbital. In cases of severe CNS depression, airway protective reflexes may be compromised and tracheal intubation should be considered for airway protection and respiratory support. For decontamination in cases of severe toxicity, activated charcoal should be considered in a hospital setting in patients with large overdoses who present early and are not demonstrating CNS depression and can protect their airway.
For more information on the management of an overdose of carisoprodol, contact a Poison Control Center.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of carisoprodol in relieving discomfort associated with acute painful musculoskeletal conditions has not been clearly identified. In animal studies, muscle relaxation induced by carisoprodol is associated with altered interneuronal activity in the spinal cord and in the descending reticular formation of the brain.
12.2Pharmacodynamics Carisoprodol is a centrally acting skeletal muscle relaxant that does not directly relax skeletal muscles. A metabolite of carisoprodol, meprobamate, has anxiolytic and sedative properties. The degree to which these properties of meprobamate contribute to the safety and efficacy of carisoprodol is unknown.
12.3Pharmacokinetics Absorption The pharmacokinetics of carisoprodol and its metabolite meprobamate were studied in a crossover study of 24 healthy subjects (12 male and 12 female) who received single doses of 250 mg and 350 mg carisoprodol (see Table 2). The exposure of carisoprodol and meprobamate was dose proportional between the 250 mg and 350 mg doses. The C max of meprobamate was 2.5 ± 0.5 μg/mL (mean ± SD) after administration of a single 350 mg dose of carisoprodol, which is approximately 30% of the Cmax of meprobamate (approximately 8 μg/mL) after administration of a single 400 mg dose of meprobamate.
Table 2. Pharmacokinetic Parameters of Carisoprodol and Meprobamate (Mean ± SD, n=24) 250 mg Carisoprodol 350 mg Carisoprodol Carisoprodol C max (μg/mL) 1.2 ± 0.5 1.8 ±
1.0AUC inf (μg*hr/mL) 4.5 ± 3.1 7.0 ±
5.0T max (hr) 1.5 ± 0.8 1.7 ±
0.8T 1/2 (hr) 1.7 ± 0.5 2.0 ±
0.5Meprobamate C max (μg/mL) 1.8 ± 0.3 2.5 ±
0.5AUC inf (μg*hr/mL) 32 ± 6.2 46 ±
9.0T max (hr) 3.6 ± 1.7 4.5 ±
1.9T 1/2 (hr) 9.7 ± 1.7 9.6 ±
1.5Absolute bioavailability of carisoprodol has not been determined. The mean time to peak plasma concentrations (T max ) of carisoprodol was approximately 1.5 to 2 hours. Food Effect: Co-administration of a high-fat meal with carisoprodol (350 mg tablet) had no effect on the pharmacokinetics of carisoprodol.
Therefore, carisoprodol may be administered with or without food. Elimination Metabolism: The major pathway of carisoprodol metabolism is via the liver by cytochrome enzyme CYP2C19 to form meprobamate. This enzyme exhibits genetic polymorphism (see Patients with Reduced CYP2C19 Activity below).
Excretion: Carisoprodol is eliminated by both renal and non-renal routes with a terminal elimination half-life of approximately 2 hours. The half-life of meprobamate is approximately 10 hours. Specific Populations Sex: Exposure of carisoprodol is higher in female than in male subjects (approximately 30 to 50% on a weight adjusted basis).
Overall exposure of meprobamate is comparable between female and male subjects. Patients with Reduced CYP2C19 Activity: Carisoprodol should be used with caution in patients with reduced CYP2C19 activity. Published studies indicate that patients who are poor CYP2C19 metabolizers have a 4-fold increase in exposure to carisoprodol, and concomitant 50% reduced exposure to meprobamate compared to normal CYP2C19 metabolizers.
The prevalence of poor metabolizers in Caucasians and African Americans is approximately 3 to 5% and in Asians is approximately 15 to 20%.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of carisoprodol in relieving discomfort associated with acute painful musculoskeletal conditions has not been clearly identified. In animal studies, muscle relaxation induced by carisoprodol is associated with altered interneuronal activity in the spinal cord and in the descending reticular formation of the brain.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Carisoprodol Tablets, USP 350 mg: round, convex, white tablets, debossed with SG 109 on one side. NDC: 71335-1203-1: 14 Tablets in a BOTTLE NDC: 71335-1203-2: 28 Tablets in a BOTTLE NDC: 71335-1203-3: 60 Tablets in a BOTTLE NDC: 71335-1203-4: 20 Tablets in a BOTTLE NDC: 71335-1203-5: 30 Tablets in a BOTTLE NDC: 71335-1203-6: 84 Tablets in a BOTTLE NDC: 71335-1203-7: 90 Tablets in a BOTTLE NDC: 71335-1203-8: 100 Tablets in a BOTTLE NDC: 71335-1203-9: 120 Tablets in a BOTTLE NDC: 71335-1203-0: 56 Tablets in a BOTTLE Storage Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Carisoprodol tablets, USP are available as 350 mg round, white tablets. Carisoprodol, USP is a white, crystalline powder, having a mild, characteristic odor. It is very slightly soluble in water; freely soluble in alcohol, in chloroform, and in acetone; and its solubility is practically independent of pH.
Carisoprodol is present as a racemic mixture. Chemically, carisoprodol is (±)-2-Methyl-2-propyl-1,3-propanediol carbamate isopropylcarbamate and the molecular formula is C 12 H 24 N 2 O 4 , with a molecular weight of 260.33. The structural formula is: Other ingredients in the Carisoprodol tablets USP, 350 mg include microcrystalline cellulose, lactose monohydrate, pregelatinized starch (maize), croscarmellose sodium, povidone, silicon dioxide and magnesium stearate.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients should be advised to contact their physician if they experience any adverse reactions to carisoprodol. Sedation Advise patients that carisoprodol may cause drowsiness and/or dizziness, and has been associated with motor vehicle accidents. Patients should be advised to avoid taking carisoprodol before engaging in potentially hazardous activities such as driving a motor vehicle or operating machinery [ see Warnings and Precautions (5.1) ].
Avoidance of Alcohol and Other CNS Depressants Advise patients to avoid alcoholic beverages while taking carisoprodol and to check with their doctor before taking other CNS depressants such as benzodiazepines, opioids, tricyclic antidepressants, sedating antihistamines, or other sedatives [ see Warnings and Precautions (5.1) ]. Carisoprodol Should Only Be Used for Short-Term Treatment Advise patients that treatment with carisoprodol should be limited to acute use (up to two or three weeks) for the relief of acute, musculoskeletal discomfort.
In the post-marketing experience with carisoprodol, cases of dependence, withdrawal, and abuse have been reported with prolonged use. If the musculoskeletal symptoms still persist, patients should contact their healthcare provider for further evaluation. Lactation Advise nursing mothers using carisoprodol to monitor neonates for signs of sedation [ see Use in Specific Populations (8.2) ].
Manufactured by: ScieGen Pharmaceuticals, Inc. Hauppauge, NY 11788 Rev: 02/20 Rx only