
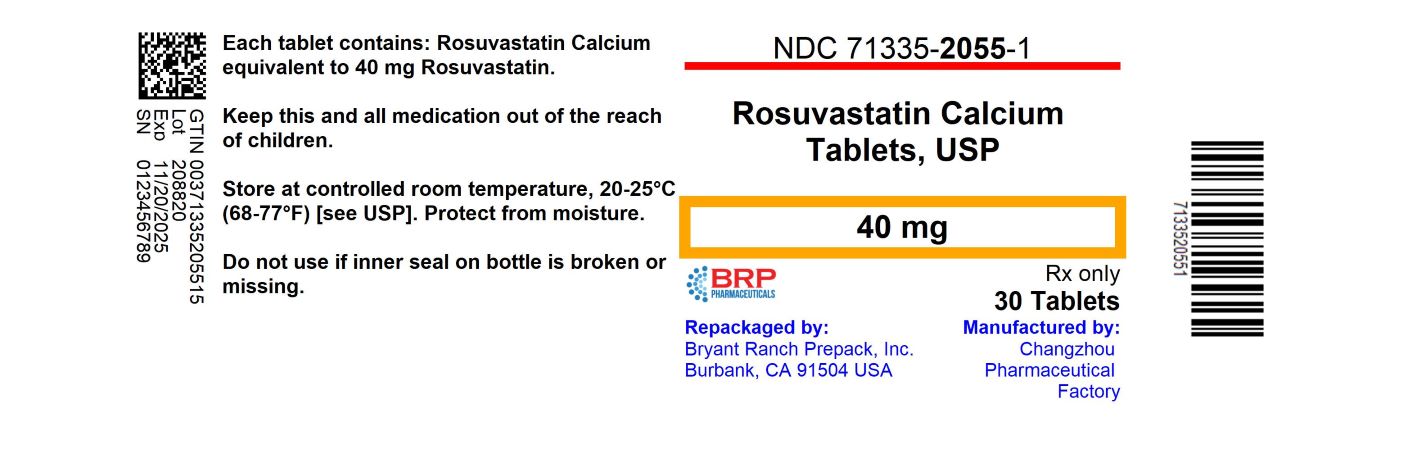
Rosuvastatin Calcium 40 mg Tablet, Film Coated, 10-count
Other active recalls for Rosuvastatin Calcium (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the HMG-CoA Reductase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Rosuvastatin is used to reduce the risk of heart attack or stroke decrease the amount of cholesterol (a fat-like substance that can build up and clog blood vessels causing heart attack or stroke or other health conditions) Rosuvastatin is in a class of medications called HMG-CoA reductase inhibitors (statins). It works by slowing how much cholesterol your body makes. This lowers the amount of cholesterol that can build up on the walls of the arteries and block blood flow to the heart, brain, and other parts of the body.
Read the full MedlinePlus article ↗- Rosuvastatin lowers the amount of LDL — the "bad" cholesterol — and other fats circulating in your blood, while nudging your "good" cholesterol (HDL) a little higher. Depending on...
- What exactly is rosuvastatin supposed to do for me?
- No — you can take rosuvastatin at any time of day that's easiest for you to remember, and food doesn't change how well it's absorbed. The most important thing is taking it consiste...
- Does it matter what time of day I take it, or whether I take it with food?
Patient education
Supplement & herbal interactions
Rosuvastatin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII B1QE5P712K
Hypromellose 2208 is a plant-derived thickening agent that dissolves in water. It's used as a binder to help hold tablet ingredients together and as a coating on pills to control how quickly the medicine releases in your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1900 | $1.90 / 10 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rosuvastatin 40 mg 11788-0133-05 | AiPing | 500 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 13668-0182-05 | Torrent | 500 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 13668-0723-05 | TORRENT | 500 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 16714-0991-01 | NorthStar | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 24658-0264-30 | PURACAP | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 27808-0158-01 | Cranbury | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin 40 mg 31722-0885-30 | Camber | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin 40 mg 50228-0119-10 | ScieGen | 1000 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin 40 mg 50268-0711-15 | AvPAK | 1 tablet | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 57237-0171-05 | Rising | 500 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastain Calcium 40 mg 62135-0693-30 | Chartwell | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin calcium 40 mg 70377-0009-11 | Biocon | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 72603-0367-01 | NorthStar | 30 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 82009-0020-10 | Quallent | 1000 tablets | $0.069 | AB | Availability likely | — |
| Rosuvastatin 40 mg 16729-0287-10 | Accord | 30 tablets | $0.108 | AB | FDA listed | — |
| Crestor 40 mg 00310-7590-30 | AstraZeneca | 30 tablets | $8.806 | AB | Availability likely | — |
| Rosuvastatin Calcium 40 mg 00615-8535-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 33342-0264-07 | Macleods | 30 tablets | — | — | FDA listed | — |
| Rosuvastatin Calcium 40 mg 42677-0304-01 | Shandong | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 50090-5970-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 50090-6611-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 50090-6612-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 50090-7413-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 50090-7414-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 50090-7482-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 50090-7483-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 51407-0156-30 | Golden | 30 tablets | — | AB | Discontinued | — |
| Rosuvastatin 40 mg 51407-0851-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 60290-0046-01 | Umedica | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 65862-0296-05 | Aurobindo | 500 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 67877-0442-05 | Ascend | 500 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 68462-0264-01 | Glenmark | 100 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 68788-8649-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 69367-0362-01 | Westminster | 100 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 69434-0008-01 | Zhejiang | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 70518-3651-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 70518-4220-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 70518-4314-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
| rosuvstatin 40 mg 70756-0056-12 | Lifestar | 1000 tablets | — | — | FDA listed | — |
| Rosuvastatin Calcium 40 mg 71205-0078-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 71205-0176-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 71205-0475-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 71209-0046-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 71335-1103-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Rosuvastatin calcium 40 mg 71335-1939-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mgthis 71335-2055-04 | Bryant | 10 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 71335-2498-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 71610-0078-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 71610-0133-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 71610-0232-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 71610-0793-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 71610-0798-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 72189-0106-30 | DIRECT | 30 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 72205-0005-05 | Novadoz | 500 tablets | — | AB | FDA listed | — |
| Rosuvastatin 40 mg 82009-0191-05 | Quallent | 500 tablets | — | AB | FDA listed | — |
| Rosuvastatin Calcium 40 mg 82804-0176-90 | Proficient | 90 tablets | — | AB | FDA listed | — |
| Rosuvastatin calcium 40 mg 72303-0830-01 | HEC | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-2055-01 | 30 TABLET, FILM COATED in 1 BOTTLE (71335-2055-1) | 2022-03-14 | Active |
| 71335-2055-02 | 90 TABLET, FILM COATED in 1 BOTTLE (71335-2055-2) | 2022-03-14 | Active |
| 71335-2055-03 | 28 TABLET, FILM COATED in 1 BOTTLE (71335-2055-3) | 2022-03-14 | Active |
| 71335-2055-04 You're viewing this | 10 TABLET, FILM COATED in 1 BOTTLE (71335-2055-4) | 2022-03-14 | Active |
| 71335-2055-05 | 60 TABLET, FILM COATED in 1 BOTTLE (71335-2055-5) | 2024-07-10 | Active |
You're viewing the smallest of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-2055-04?
What is the difference between NDC 71335-2055-04 and NDC 71335-2055-03?
What NDC number is used to bill for this package of Rosuvastatin Calcium 40 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Pediatric use information for patients 7 to 17 years of age is approved for AstraZeneca’s CRESTOR (rosuvastatin calcium) tablets. However, due to AstraZeneca’s marketing exclusivity rights, this drug product is not labeled with that pediatric information. Rosuvastatin is an HMG Co-A reductase inhibitor indicated for: • adult patients with hypertriglyceridemia as an adjunct to diet ( 1.3 ) • adult patients with primary dysbetalipoproteinemia (Type III hyperlipoproteinemia) as an adjunct to diet ( 1.4 ) • adult patients with homozygous familial hypercholesterolemia (HoFH) to reduce LDL-C, total-C, and ApoB ( 1.5 ) Limitations of use ( 1.8 ): Rosuvastatin has not been studied in Fredrickson Type I and V dyslipidemias.
1.3Hypertriglyceridemia Rosuvastatin is indicated as adjunctive therapy to diet for the treatment of adult patients with hypertriglyceridemia.
1.4Primary Dysbetalipoproteinemia (Type III Hyperlipoproteinemia) Rosuvastatin is indicated as an adjunct to diet for the treatment of adult patients with primary dysbetalipoproteinemia (Type III Hyperlipoproteinemia).
1.5Adult Patients with Homozygous Familial Hypercholesterolemia Rosuvastatin is indicated as adjunctive therapy to other lipid-lowering treatments (e.g., LDL apheresis) or alone if such treatments are unavailable to reduce LDL-C, Total-C, and ApoB in adult patients with homozygous familial hypercholesterolemia.
1.8Limitations of Use Rosuvastatin has not been studied in Fredrickson Type I and V dyslipidemias.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Rosuvastatin calcium tablets can be taken with or without food, at any time of day. ( 2.1 ) • Dose range: 5-40 mg once daily. Use 40 mg dose only for patients not reaching LDL-C goal with 20 mg. ( 2.1 ) • Adult HoFH: Starting dose 20 mg/day ( 2.1 )
2.1General Dosing Information The dose range for rosuvastatin calcium tablets in adults is 5 to 40 mg orally once daily. The usual starting dose is 10 to 20 mg once daily. The usual starting dose in adult patients with homozygous familial hypercholesterolemia is 20 mg once daily.
The maximum rosuvastatin calcium tablets dose of 40 mg should be used only for those patients who have not achieved their LDL-C goal utilizing the 20 mg dose [see Warnings and Precautions (5.1) ]. Rosuvastatin calcium tablets can be administered as a single dose at any time of day, with or without food. The tablet should be swallowed whole.
When initiating rosuvastatin therapy or switching from another HMG-CoA reductase inhibitor therapy, the appropriate rosuvastatin starting dose should first be utilized, and only then titrated according to the patient’s response and individualized goal of therapy. After initiation or upon titration of rosuvastatin, lipid levels should be analyzed within 2 to 4 weeks and the dosage adjusted accordingly. Pediatric use information for patients 7 to 17 years of age is approved for AstraZeneca’s CRESTOR (rosuvastatin calcium) tablets.
However, due to AstraZeneca’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
2.3Dosing in Asian Patients In Asian patients, consider initiation of rosuvastatin therapy with 5 mg once daily due to increased rosuvastatin plasma concentrations. The increased systemic exposure should be taken into consideration when treating Asian patients not adequately controlled at doses up to 20 mg/day [see Use in Specific Populations (8.8) and Clinical Pharmacology (12.3) ] .
2.4Use with Concomitant Therapy Patients taking cyclosporine and darolutamide The dose of rosuvastatin should not exceed 5 mg once daily [see Warnings and Precautions (5.1) , Drug Interactions (7.1) , Drug Interactions (7.4) and Clinical Pharmacology (12.3) ] . Patients taking gemfibrozil Avoid concomitant use of rosuvastatin with gemfibrozil. If concomitant use cannot be avoided, initiate rosuvastatin at 5 mg once daily.
The dose of rosuvastatin should not exceed 10 mg once daily [see Warnings and Precautions (5.1) , Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] . Patients taking regorafenib Concomitant use of rosuvastatin and regorafenib, the dose of rosuvastatin should not exceed 10 mg once daily. [see Warnings and Precautions (5.1) , Drug Interactions (7.5) and Clinical Pharmacology (12.3) ] . Patients taking atazanavir and ritonavir, lopinavir and ritonavir, simeprevir or combination of dasabuvir/ombitasvir/paritaprevir/ritonavir, elbasvir/grazoprevir, sofosbuvir/velpatasvir and glecaprevir/pibrentasvir Initiate rosuvastatin therapy with 5 mg once daily.
The dose of rosuvastatin should not exceed 10 mg once daily [see Warnings and Precautions (5.1) , Drug Interactions (7.3) and Clinical Pharmacology (12.3) ] .
2.5Dosing in Patients with Severe Renal Impairment For patients with severe renal impairment (CL cr <30 mL/min/1.73 m 2 ) not on hemodialysis, dosing of rosuvastatin should be started at 5 mg once daily and not exceed 10 mg once daily [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 5 mg: Pink, round, biconvex, coated tablets. Debossed as ‘CY’ on one side and ‘5’ on other side. 10 mg: Yellow, round, biconvex, coated tablets.
Debossed as ‘CY’ on one side, and ‘10’ on other side. 20 mg: Yellow, round, biconvex, coated tablets. Debossed as ‘CY’ on one side, and ‘20’ on other side.
40 mg: Pink, round, biconvex, coated tablets. Debossed as ‘CY’ on one side, and ‘40’ on other side. Tablets: 5 mg, 10 mg, 20 mg, and 40 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Rosuvastatin is contraindicated in the following conditions: • Patients with a known hypersensitivity to any component of this product. Hypersensitivity reactions including rash, pruritus, urticaria, and angioedema have been reported with rosuvastatin [see Adverse Reactions (6.1) ] . • Patients with active liver disease, which may include unexplained persistent elevations of hepatic transaminase levels [see Warnings and Precautions (5.3) ] . • Pregnancy [see Use in Specific Populations ( 8.1 , 8.3) ] . • Lactation.
Limited data indicate that rosuvastatin is present in human milk. Because statins have the potential for serious adverse reactions in nursing infants, women who require rosuvastatin treatment should not breastfeed their infants [see Use in Specific Populations (8.2) ] . • Known hypersensitivity to product components ( 4 ) • Active liver disease, which may include unexplained persistent elevations in hepatic transaminase levels ( 4 ) • Pregnancy ( 4 , 8.1 , 8.3 ) • Lactation ( 4 , 8.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Skeletal muscle effects (e.g., myopathy and rhabdomyolysis): Risks increase with use of 40 mg dose, advanced age (≥65), hypothyroidism, renal impairment, and combination use with cyclosporine, darolutamide, regorafenib, certain anti-viral medicines or their combinations. Cases of myopathy and rhabdomyolysis with acute renal failure secondary to myoglobinuria have been reported. Advise patients to promptly report to their physician unexplained and/or persistent muscle pain, tenderness, or weakness and discontinue rosuvastatin calcium tablets if signs or symptoms appear.
( 5.1 , 7.4 , 7.5 , 7.7 , 7.8 ) • Immune-Mediated Necrotizing Myopathy (IMNM): There have been rare reports of IMNM, an autoimmune myopathy, associated with statin use. IMNM is characterized by: proximal muscle weakness and elevated serum creatine kinase, which persist despite discontinuation of statin treatment; positive anti-HMG CoA reductase antibody; muscle biopsy showing necrotizing myopathy; and improvement with immunosuppressive agents. ( 5.2 ) • Liver enzyme abnormalities: Persistent elevations in hepatic transaminases can occur.
Perform liver enzyme tests before initiating therapy and as clinically indicated thereafter. ( 5.3 )
5.1Skeletal Muscle Effects Cases of myopathy and rhabdomyolysis with acute renal failure secondary to myoglobinuria have been reported with HMG-CoA reductase inhibitors, including rosuvastatin. These risks can occur at any dose level, but are increased at the highest dose (40 mg). Rosuvastatin should be prescribed with caution in patients with predisposing factors for myopathy (e.g., age ≥ 65 years, inadequately treated hypothyroidism, renal impairment).
The risk of myopathy during treatment with rosuvastatin may be increased with concurrent administration of gemfibrozil, some other lipid-lowering therapies (other fibrates or niacin), cyclosporine, darolutamide, regorafenib, atazanavir/ritonavir, lopinavir/ritonavir, simeprevir or combination of sofosbuvir/velpatasvir/voxilaprevir, dasabuvir/ombitasvir/paritaprevir/ritonavir, elbasvir/grazoprevir, sofosbuvir/velpatasvir, glecaprevir/pibrentasvir, all combinations with ledipasvir (including ledipasvir/sofosbuvir) [see Dosage and Administration (2) and Drug Interactions (7) ] .
Cases of myopathy, including rhabdomyolysis, have been reported with HMG-CoA reductase inhibitors, including rosuvastatin, coadministered with colchicine, and caution should be exercised when prescribing rosuvastatin with colchicine [see Drug Interactions (7.9) ] . Rosuvastatin therapy should be discontinued if markedly elevated creatine kinase levels occur or myopathy is diagnosed or suspected. Rosuvastatin therapy should also be temporarily withheld in any patient with an acute, serious condition suggestive of myopathy or predisposing to the development of renal failure secondary to rhabdomyolysis (e.g., sepsis, hypotension, dehydration, major surgery, trauma, severe metabolic, endocrine, and electrolyte disorders, or uncontrolled seizures).
All patients should be advised to promptly report to their physician unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever or if muscle signs and symptoms persist after discontinuing rosuvastatin.
5.2Immune-Mediated Necrotizing Myopathy There have been rare reports of immune-mediated necrotizing myopathy (IMNM), an autoimmune myopathy, associated with statin use. IMNM is characterized by: proximal muscle weakness and elevated serum creatine kinase, which persist despite discontinuation of statin treatment; positive anti-HMG CoA reductase antibody; muscle biopsy showing necrotizing myopathy; and improvement with immunosuppressive agents. Additional neuromuscular and serologic testing may be necessary.
Treatment with immunosuppressive agents may be required. Consider risk of IMNM carefully prior to initiation of a different statin. If therapy is initiated with a different statin, monitor for signs…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the label: • Rhabdomyolysis with myoglobinuria and acute renal failure and myopathy (including myositis) [see Warnings and Precautions (5.1) ] • Liver enzyme abnormalities [see Warnings and Precautions (5.3) ] Most frequent adverse reactions (rate > 2%) are headache, myalgia, abdominal pain, asthenia, and nausea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Tris Pharma, Inc. at 1-732-940-0358 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Studies Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in clinical practice. In the rosuvastatin controlled clinical trials database (placebo or active-controlled) of 5394 patients with a mean treatment duration of 15 weeks, 1.4% of patients discontinued due to adverse reactions. The most common adverse reactions that led to treatment discontinuation were: myalgia abdominal pain nausea The most commonly reported adverse reactions (incidence ≥2%) in the Rosuvastatin controlled clinical trial database of 5394 patients were: headache myalgia abdominal pain asthenia nausea Adverse reactions reported in ≥ 2% of patients in placebo-controlled clinical studies and at a rate greater than placebo are shown in Table 1.
These studies had a treatment duration of up to 12 weeks. Table 1. Adverse Reactions 1 Reported in ≥ 2% of Patients Treated with Rosuvastatin and > Placebo in Placebo-Controlled Trials (% of Patients) Adverse Reactions Rosuvastatin 5 mg N = 291 Rosuvastatin 10 mg N = 283 Rosuvastatin 20 mg N = 64 Rosuvastatin 40 mg N = 106 Total Rosuvastatin 5 mg to 40 mg N = 744 Placebo N = 382 Headache 5.5 4.9 3.1 8.5 5.5
5.0Nausea 3.8 3.5 6.3 0 3.4
3.1Myalgia 3.1 2.1 6.3 1.9 2.8
1.3Asthenia 2.4 3.2 4.7 0.9 2.7
2.6Constipation 2.1 2.1 4.7 2.8 2.4 2.4 1 Adverse reactions by COSTART preferred term. Other adverse reactions reported in clinical studies were abdominal pain, dizziness, hypersensitivity (including rash, pruritus, urticaria, and angioedema) and pancreatitis. The following laboratory abnormalities have also been reported: dipstick-positive proteinuria and microscopic hematuria [see Warnings and Precautions (5.5) ] ; elevated creatine phosphokinase, transaminases, glucose, glutamyl transpeptidase, alkaline phosphatase, and bilirubin; and thyroid function abnormalities.
In a clinical trial, involving 981 participants treated with rosuvastatin 40 mg (n=700) or placebo (n=281) with a mean treatment duration of 1.7 years, 5.6% of subjects treated with rosuvastatin versus 2.8% of placebo-treated subjects discontinued due to adverse reactions. The most common adverse reactions that led to treatment discontinuation were: myalgia, hepatic enzyme increased, headache, and nausea. Adverse reactions reported in ≥ 2% of patients and at a rate greater than placebo are shown in Table 2.
Table 2. Adverse Reactions 1 Reported in ≥ 2% of Patients Treated with Rosuvastatin and > Placebo in a Trial (% of Patients) Adverse Reactions Rosuvastatin 40 mg N = 700 Placebo N=281 Myalgia 12.7
12.1Arthralgia 10.1
7.1Headache 6.4
5.3Dizziness 4.0
2.8Increased CPK 2.6
0.7Abdominal pain 2.4
1.8ALT > 3x ULN 2 2.2 0.7 1 Adverse reactions by MedDRA preferred term. 2 Frequency recorded as abnormal laboratory value. In a clinical trial, 17,802 participants were treated with rosuvastatin 20 mg (n = 8,901) or placebo (n = 8,901) for a mean duration of 2 years.
A higher percentage of rosuvastatin-treated patients versus placebo-treated patients, 6.6% and 6.2%, respectively, discontinued study medication due to an adverse event, irrespective of treatment causality. Myalgia was the most common adverse reaction that led to treatment discontinuation. There was a significantly h…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Combination of sofosbuvir/velpatasvir/voxilaprevir or ledipasvir/sofosbuvir: Combination increases rosuvastatin exposure. Use with rosuvastatin is not recommended. ( 2.4 , 5.1 , 7.3 , 12.3 ) • Cyclosporine and darolutamide : Combination increases rosuvastatin exposure.
Limit rosuvastatin dose to 5 mg once daily. ( 2.4 , 5.1 , 7.1 , 7.4 , 12.3 ) • Gemfibrozil: Combination should be avoided. If used together, limit rosuvastatin dose to 10 mg once daily.
( 2.4 , 5.1 , 7.2 ) • Atazanavir/ritonavir, lopinavir/ritonavir, simeprevir or combination of dasabuvir/ombitasvir/paritaprevir/ritonavir, elbasvir/grazoprevir, sofosbuvir/velpatasvir and glecaprevir/pibrentasvir: Combination increases rosuvastatin exposure. Limit rosuvastatin dose to 10 mg once daily. ( 2.4 , 5.1 , 7.3 , 12.3 ) • Regorafenib: Combination increases rosuvastatin exposure.
Limit rosuvastatin dose to 10 mg once daily. ( 2.4 , 5.1 , 7.5 ) • Coumarin anticoagulants: Combination prolongs INR. Achieve stable INR prior to starting rosuvastatin.
Monitor INR frequently until stable upon initiation or alteration of rosuvastatin therapy. ( 5.4 , 7.6 ) • Concomitant lipid-lowering therapies: Use with fibrates or lipid-modifying doses (≥1 g/day) of niacin increases the risk of adverse skeletal muscle effects. Caution should be used when prescribing with rosuvastatin.
( 5.1 , 7.7 , 7.8 )
7.1Cyclosporine Cyclosporine increased rosuvastatin exposure and may result in increased risk of myopathy. Therefore, in patients taking cyclosporine, the dose of rosuvastatin should not exceed 5 mg once daily [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
7.2Gemfibrozil Gemfibrozil significantly increased rosuvastatin exposure. Due to an observed increased risk of myopathy/rhabdomyolysis, combination therapy with rosuvastatin and gemfibrozil should be avoided. If used together, the dose of rosuvastatin should not exceed 10 mg once daily [see Clinical Pharmacology (12.3) ] .
7.3Anti-viral Medications Coadministration of rosuvastatin with certain anti-viral drugs has differing effects on rosuvastatin exposure and may increase risk of myopathy. The combination of sofosbuvir/velpatasvir/voxilaprevir which are anti-Hepatitis C virus (anti-HCV) drugs, increases rosuvastatin exposure. Similarly, the combination of ledipasvir/sofosbuvir may significantly increase rosuvastatin exposure.
For these combinations of anti-HCV drugs, concomitant use with rosuvastatin is not recommended. Simeprevir and combinations of dasabuvir/ombitasvir/paritaprevir/ritonavir, elbasvir/grazoprevir, sofosbuvir/velpatasvir and glecaprevir/pibrentasvir which are anti-HCV drugs, increase rosuvastatin exposure. Combinations of atazanavir/ritonavir and lopinavir/ritonavir, which are anti-HIV-1 drugs, increase rosuvastatin exposure [see Table 4 – Clinical Pharmacology (12.3) ] .
For these anti-viral drugs, the dose of rosuvastatin should not exceed 10 mg once daily. The combinations of fosamprenavir/ritonavir or tipranavir/ritonavir, which are anti-HIV-1 drugs, produce little or no change in rosuvastatin exposure. No dose adjustment is needed for concomitant use with these combinations [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
7.4Darolutamide Darolutamide increased rosuvastatin exposure more than 5 fold. Therefore, in patients taking darolutamide, the dose of rosuvastatin should not exceed 5 mg once daily [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
7.5Regorafenib Regorafenib increased rosuvastatin exposure and may increase the risk of myopathy. If used together, the dose of rosuvastatin should not exceed 10 mg once daily [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ].
7.6Coumarin Anticoagulants Rosuvastatin significantly increased INR in patients receiving couma…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Females of reproductive potential: Advise females of reproductive potential to use effective contraception during treatment with rosuvastatin ( 8.3 ) • Severe renal impairment (not on hemodialysis): Starting dose is 5 mg, not to exceed 10 mg. ( 2.5 , 5.1 , 8.6 ) • Asian population: Consider 5 mg starting dose. ( 2.3 , 8.8 ) Pediatric use information for patients 7 to 17 years of age is approved for AstraZeneca’s CRESTOR (rosuvastatin calcium) tablets.
However, due to AstraZeneca’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
8.1Pregnancy Risk Summary Rosuvastatin is contraindicated for use in pregnant women since safety in pregnant women has not been established and there is no apparent benefit to therapy with rosuvastatin during pregnancy. Because HMG-CoA reductase inhibitors decrease cholesterol synthesis and possibly the synthesis of other biologically active substances derived from cholesterol, rosuvastatin may cause fetal harm when administered to pregnant women. Rosuvastatin should be discontinued as soon as pregnancy is recognized [see Contraindications (4) ] .
Limited published data on the use of rosuvastatin are insufficient to determine a drug-associated risk of major congenital malformations or miscarriage. In animal reproduction studies, there were no adverse developmental effects with oral administration of rosuvastatin during organogenesis at systemic exposures equivalent to a maximum recommended human dose (MRHD) of 40 mg/day in rats or rabbits (based on AUC and body surface area, respectively). In rats and rabbits, decreased pup/fetal survival occurred at 12 times and equivalent, respectively, to the MRHD of 40 mg/day [see Data] .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Human Data Limited published data on rosuvastatin have not shown an increased risk of major congenital malformations or miscarriage.
Rare reports of congenital anomalies have been received following intrauterine exposure to other statins. In a review of approximately 100 prospectively followed pregnancies in women exposed to simvastatin or lovastatin, the incidences of congenital anomalies, spontaneous abortions, and fetal deaths/stillbirths did not exceed what would be expected in the general population. The number of cases is adequate to exclude a ≥3 to 4-fold increase in congenital anomalies over the background incidence.
In 89% of the prospectively followed pregnancies, drug treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified. Animal Data Rosuvastatin crosses the placenta in rats and rabbits and is found in fetal tissue and amniotic fluid at 3% and 20%, respectively, of the maternal plasma concentration following a single 25 mg/kg oral gavage dose on gestation day 16 in rats. A higher fetal tissue distribution (25% maternal plasma concentration) was observed in rabbits after a single oral gavage dose of 1 mg/kg on gestation day 18.
Rosuvastatin administration did not indicate a teratogenic effect in rats at ≤ 25 mg/kg/day or in rabbits ≤ 3 mg/kg/day (doses equivalent to the MRHD of 40 mg/day based on AUC and body surface area, respectively). In female rats given 5, 15 and 50 mg/kg/day before mating and continuing through to gestation day 7 resulted in decreased fetal body weight (female pups) and delayed ossification at 50 mg/kg/day (10 times the human exposure at the MRHD dose of 40 mg/day based on AUC). In pregnant rats given 2, 10 and 50 mg/kg/day of rosuvastatin from gestation day 7 through lactation day 21 (weaning), decreased pup survival occurred at 50 mg/kg/day (dose equivalent to 12 times the MRHD of 40 mg/day based body surface a…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Rosuvastatin is contraindicated for use in pregnant women since safety in pregnant women has not been established and there is no apparent benefit to therapy with rosuvastatin during pregnancy. Because HMG-CoA reductase inhibitors decrease cholesterol synthesis and possibly the synthesis of other biologically active substances derived from cholesterol, rosuvastatin may cause fetal harm when administered to pregnant women. Rosuvastatin should be discontinued as soon as pregnancy is recognized [see Contraindications (4) ] .
Limited published data on the use of rosuvastatin are insufficient to determine a drug-associated risk of major congenital malformations or miscarriage. In animal reproduction studies, there were no adverse developmental effects with oral administration of rosuvastatin during organogenesis at systemic exposures equivalent to a maximum recommended human dose (MRHD) of 40 mg/day in rats or rabbits (based on AUC and body surface area, respectively). In rats and rabbits, decreased pup/fetal survival occurred at 12 times and equivalent, respectively, to the MRHD of 40 mg/day [see Data] .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Human Data Limited published data on rosuvastatin have not shown an increased risk of major congenital malformations or miscarriage.
Rare reports of congenital anomalies have been received following intrauterine exposure to other statins. In a review of approximately 100 prospectively followed pregnancies in women exposed to simvastatin or lovastatin, the incidences of congenital anomalies, spontaneous abortions, and fetal deaths/stillbirths did not exceed what would be expected in the general population. The number of cases is adequate to exclude a ≥3 to 4-fold increase in congenital anomalies over the background incidence.
In 89% of the prospectively followed pregnancies, drug treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified. Animal Data Rosuvastatin crosses the placenta in rats and rabbits and is found in fetal tissue and amniotic fluid at 3% and 20%, respectively, of the maternal plasma concentration following a single 25 mg/kg oral gavage dose on gestation day 16 in rats. A higher fetal tissue distribution (25% maternal plasma concentration) was observed in rabbits after a single oral gavage dose of 1 mg/kg on gestation day 18.
Rosuvastatin administration did not indicate a teratogenic effect in rats at ≤ 25 mg/kg/day or in rabbits ≤ 3 mg/kg/day (doses equivalent to the MRHD of 40 mg/day based on AUC and body surface area, respectively). In female rats given 5, 15 and 50 mg/kg/day before mating and continuing through to gestation day 7 resulted in decreased fetal body weight (female pups) and delayed ossification at 50 mg/kg/day (10 times the human exposure at the MRHD dose of 40 mg/day based on AUC). In pregnant rats given 2, 10 and 50 mg/kg/day of rosuvastatin from gestation day 7 through lactation day 21 (weaning), decreased pup survival occurred at 50 mg/kg/day (dose equivalent to 12 times the MRHD of 40 mg/day based body surface area).
In pregnant rabbits given 0.3, 1, and 3 mg/kg/day of rosuvastatin from gestation day 6 to day 18, decreased fetal viability and maternal mortality was observed at 3 mg/kg/day (dose equivalent to the MRHD of 40 mg/day based on body surface area).
🧒 Pediatric Use ▾
8.4Pediatric Use Pediatric use information for patients 7 to 17 years of age is approved for AstraZeneca’s CRESTOR (rosuvastatin calcium) tablets. However, due to AstraZeneca’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 10,275 patients in clinical studies with rosuvastatin, 3159 (31%) were 65 years and older, and 698 (6.8%) were 75 years and older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Elderly patients are at higher risk of myopathy and rosuvastatin should be prescribed with caution in the elderly [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific treatment in the event of overdose. In the event of overdose, the patient should be treated symptomatically and supportive measures instituted as required. Hemodialysis does not significantly enhance clearance of rosuvastatin.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Rosuvastatin is a selective and competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl coenzyme A to mevalonate, a precursor of cholesterol. In vivo studies in animals, and in vitro studies in cultured animal and human cells have shown rosuvastatin to have a high uptake into, and selectivity for, action in the liver, the target organ for cholesterol lowering. In in vivo and in vitro studies, rosuvastatin produces its lipid-modifying effects in two ways.
First, it increases the number of hepatic LDL receptors on the cell-surface to enhance uptake and catabolism of LDL. Second, rosuvastatin inhibits hepatic synthesis of VLDL, which reduces the total number of VLDL and LDL particles.
12.2Pharmacodynamics Rosuvastatin calcium dose dependently reduces elevated LDL-cholesterol and reduces total cholesterol and triglycerides and increases HDL-cholesterol [see Clinical Studies (14) ] . A therapeutic response to Rosuvastatin calcium is evident within 1 week of commencing therapy and 90% of maximum response is usually achieved in 2 weeks. The maximum response is usually achieved by 4 weeks and is maintained after that.
Individualization of drug dosage should be based on the therapeutic response [see Dosage and Administration (2) ] .
12.3Pharmacokinetics Absorption In clinical pharmacology studies in man, peak plasma concentrations of rosuvastatin were reached 3 to 5 hours following oral dosing. Both C max and AUC increased in approximate proportion to rosuvastatin dose. The absolute bioavailability of rosuvastatin is approximately 20%.
Administration of rosuvastatin with food did not affect the AUC of rosuvastatin. The AUC of rosuvastatin does not differ following evening or morning drug administration. Distribution Mean volume of distribution at steady-state of rosuvastatin is approximately 134 liters.
Rosuvastatin is 88% bound to plasma proteins, mostly albumin. This binding is reversible and independent of plasma concentrations. Elimination Rosuvastatin is primarily eliminated by excretion in the feces.
The elimination half-life of rosuvastatin is approximately 19 hours. Metabolism Rosuvastatin is not extensively metabolized; approximately 10% of a radiolabeled dose is recovered as metabolite. The major metabolite is N-desmethyl rosuvastatin, which is formed principally by cytochrome P450 \ 2C9, and in vitro studies have demonstrated that N-desmethyl rosuvastatin has approximately one-sixth to one-half the HMG-CoA reductase inhibitory activity of the parent compound.
Overall, greater than 90% of active plasma HMG-CoA reductase inhibitory activity is accounted for by the parent compound. Excretion Following oral administration, rosuvastatin and its metabolites are primarily excreted in the feces (90%). After an intravenous dose, approximately 28% of total body clearance was via the renal route, and 72% by the hepatic route.
Specific Populations Racial or Ethnic Groups A population pharmacokinetic analysis revealed no clinically relevant differences in pharmacokinetics among Caucasian, Hispanic, and Black or Afro-Caribbean groups. However, pharmacokinetic studies, including one conducted in the US, have demonstrated an approximate 2-fold elevation in median exposure (AUC and C max ) in Asian subjects when compared with a Caucasian control group. Male and Female Patients There were no differences in plasma concentrations of rosuvastatin between men and women.
Pediatric use information for patients ages 8 to less than 10 years is approved for AstraZeneca’s CRESTOR (rosuvastatin calcium) tablets. However, due to AstraZeneca’s marketing exclusivity rights, this drug product is not labeled with that pediatric information. Geriatric Patients There were no differences in plasma concentrations of rosuvastatin between the nonelderly and elderly populations (age ≥ 65 years).
Patients with Renal Impairment Mild to moderate renal impairment (…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Rosuvastatin is a selective and competitive inhibitor of HMG-CoA reductase, the rate-limiting enzyme that converts 3-hydroxy-3-methylglutaryl coenzyme A to mevalonate, a precursor of cholesterol. In vivo studies in animals, and in vitro studies in cultured animal and human cells have shown rosuvastatin to have a high uptake into, and selectivity for, action in the liver, the target organ for cholesterol lowering. In in vivo and in vitro studies, rosuvastatin produces its lipid-modifying effects in two ways.
First, it increases the number of hepatic LDL receptors on the cell-surface to enhance uptake and catabolism of LDL. Second, rosuvastatin inhibits hepatic synthesis of VLDL, which reduces the total number of VLDL and LDL particles.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Rosuvastatin calcium tablets, 40 mg are Pink, round, biconvex, coated tablet. Debossed as ‘CY’ on one side, and ‘40’ on other side. NDC: 71335-2055-1: 30 Tablets in a BOTTLE NDC: 71335-2055-2: 90 Tablets in a BOTTLE NDC: 71335-2055-3: 28 Tablets in a BOTTLE NDC: 71335-2055-4: 10 Tablets in a BOTTLE NDC: 71335-2055-5: 60 Tablets in a BOTTLE Storage Store at controlled room temperature, 20ºC to 25ºC (68ºF to 77ºF); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature].
Protect from moisture. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Rosuvastatin calcium is a synthetic lipid-lowering agent for oral administration. The chemical name for rosuvastatin calcium is bis[(E)-7-[4-(4-fluorophenyl)-6-isopropyl-2- [methyl(methylsulfonyl)amino] pyrimidin-5-yl](3R,5S)-3,5-dihydroxyhept-6-enoic acid] calcium salt with the following structural formula: The empirical formula for rosuvastatin calcium is (C 22 H 27 FN 3 O 6 S) 2 Ca and the molecular weight is 1001.14. Rosuvastatin calcium is a white amorphous powder that is sparingly soluble in water and methanol, and slightly soluble in ethanol.
Rosuvastatin calcium is a hydrophilic compound with a partition coefficient (octanol/water) of 0.13 at pH of 7.0. Rosuvastatin calcium tablets for oral administration contain 5, 10, 20, or 40 mg of rosuvastatin and the following inactive ingredients: Each tablet contains: anhydrous dibasic calcium phosphate, crospovidone, hypromellose, lactose monohydrate, magnesium stearate, microscrystalline cellulose, titanium dioxide, and triacetin; in addition, the 5 mg and 40 mg strengths contain ferric oxide red, and the 10 mg and 20 mg strength contain ferric oxide yellow.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Patients should be instructed not to take 2 doses of rosuvastatin within 12 hours of each other. Skeletal Muscle Effects Patients should be advised to report promptly unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever or if these muscle signs or symptoms persist after discontinuing rosuvastatin.
Concomitant Use of Antacids When taking rosuvastatin with an aluminum and magnesium hydroxide combination antacid, the antacid should be taken at least 2 hours after rosuvastatin administration. Embryofetal Toxicity Advise females of reproductive potential of the risk to a fetus, to use effective contraception during treatment, and to inform their healthcare provider of a known or suspected pregnancy. [see Contraindications (4) and Use in Specific Populations ( 8.1 , 8.3 )]. Lactation Advise women not to breastfeed during treatment with rosuvastatin [see Contraindications (4) and Use in Specific Populations (8.2) ].
Liver Enzymes It is recommended that liver enzyme tests be performed before the initiation of rosuvastatin and if signs or symptoms of liver injury occur. All patients treated with rosuvastatin should be advised to promptly report any symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice. Manufactured by: Changzhou Pharmaceutical Factory No.518 Laodong East Road Changzhou, Jiangsu, China, 213018 Distributed by: Tris Pharma, Inc.
Monmouth Junction, NJ 08852 www.trispharma.com LB8492 Rev. 05 November 2020