
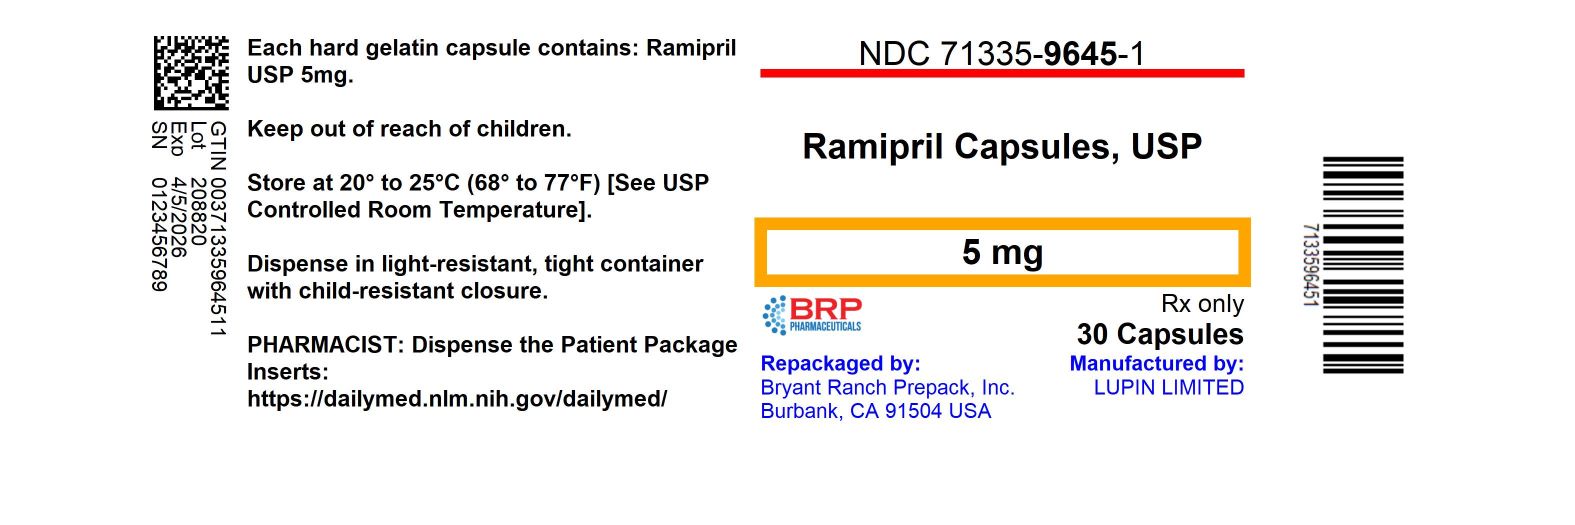
Ramipril 5 mg Capsule, 60-count
Other active recalls for Ramipril (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ramipril is used alone or in combination with other medications: to treat high blood pressure to reduce the risk of heart attack, stroke, or death in patients at risk for these problems to improve survival in patients with heart failure after a heart attack Ramipril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It works by decreasing certain chemicals that tighten the blood vessels, so blood flows more smoothly and the heart can pump blood more efficiently. High blood pressure is a common condition and when not treated, can cause damage to the brain...
Read the full MedlinePlus article ↗- Ramipril blocks an enzyme that your body uses to tighten blood vessels. By blocking it, your blood vessels stay more relaxed, your blood pressure goes down, and your heart doesn't...
- What is ramipril actually doing in my body?
- Yes, a persistent dry, tickly cough is one of the most common side effects of ramipril and all ACE inhibitors. It happens because the drug also affects a substance called bradykini...
- I've heard ramipril causes a cough. Is that true, and will it go away?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ramipril — tap one for details:
Ramipril may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 6HG8UB2MUY
Meglumine is a sugar-alcohol compound used as a solubilizer and pH buffer in medicines. It helps dissolve drugs that don't mix well in water and maintains stable acidity levels in the formulation.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1473 | $8.84 / 60 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ramipril 5 mg 57237-0224-01 | Rising | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 62135-0273-01 | Chartwell | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 65862-0476-01 | Aurobindo | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 68001-0430-00 | BluePoint | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 68180-0590-01 | Lupin | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 68382-0146-01 | Zydus | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 76282-0672-01 | Exelan | 100 capsules | $0.053 | AB | Availability likely | — |
| Ramipril 5 mg 00054-0108-20 | Hikma | 100 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 50090-5673-00 | A-S | 30 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 51407-0708-01 | GSMS, | 100 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 51655-0144-26 | Northwind | 90 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 51655-0296-52 | Northwind | 30 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 63187-0073-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 63629-1254-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 65841-0657-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 70518-4607-00 | REMEDYREPACK | 50 capsules | — | AB | FDA listed | — |
| Ramipril 5 mg 71335-1057-01 | Bryant | 30 capsules | — | AB | Discontinued | — |
| Ramipril 5 mgthis 71335-9645-04 | Bryant | 60 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-9645-01 | 30 CAPSULE in 1 BOTTLE (71335-9645-1) | 2023-02-21 | Active |
| 71335-9645-02 | 20 CAPSULE in 1 BOTTLE (71335-9645-2) | 2023-02-21 | Active |
| 71335-9645-03 | 90 CAPSULE in 1 BOTTLE (71335-9645-3) | 2023-02-21 | Active |
| 71335-9645-04 You're viewing this | 60 CAPSULE in 1 BOTTLE (71335-9645-4) | 2023-02-21 | Active |
| 71335-9645-05 | 10 CAPSULE in 1 BOTTLE (71335-9645-5) | 2023-02-21 | Active |
You're viewing one of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-9645-04?
What is the difference between NDC 71335-9645-04 and NDC 71335-9645-05?
What NDC number is used to bill for this package of Ramipril 5 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning When pregnancy is detected, discontinue ramipril as soon as possible ( 5.6 ). Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus ( 5.6 ). WARNING: FETAL TOXICITY When pregnancy is detected, discontinue ramipril as soon as possible ( 5.6 ).
Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus ( 5.6 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ramipril capsules are an angiotensin converting enzyme (ACE) inhibitor indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. It may be used alone or in combination with thiazide diuretics ( 1.1 ).
In patients 55 years or older at high risk of developing a major cardiovascular event, Ramipril capsules is indicated to reduce the risk of myocardial infarction, stroke, or death from cardiovascular causes ( 2.2 ). Ramipril capsules are indicated in stable patients who have demonstrated clinical signs of congestive heart failure post-myocardial infarction ( 1.3 ).
1.1Hypertension Ramipril capsules are indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including this drug.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Ramipril capsules may be used alone or in combination with thiazide diuretics.
1.2Reduction in the Risk of Myocardial Infarction, Stroke, and Death from Cardiovascular Causes Ramipril capsules is indicated in patients 55 years or older at high risk of developing a major cardiovascular event because of a history of coronary artery disease, stroke, peripheral vascular disease, or diabetes that is accompanied by at least one other cardiovascular risk factor (hypertension, elevated total cholesterol levels, low HDL levels, cigarette smoking, or documented microalbuminuria), to reduce the risk of myocardial infarction, stroke, or death from cardiovascular causes.
Ramipril capsules can be used in addition to other needed treatment (such as antihypertensive, antiplatelet, or lipid-lowering therapy ) [se…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension: Initial dose is 2.5 mg to 20 mg once daily. Adjust dosage according to blood pressure response after 2 to 4 weeks of treatment. The usual maintenance dose following titration is 2.5 mg to 20 mg daily as a single dose or equally divided doses ( 2.1 ).
Reduction in the risk of myocardial infarction, stroke, or death from cardiovascular causes: 2.5 mg once daily for 1 week, 5 mg once daily for 3 weeks, and increased as tolerated to a maintenance dose of 10 mg once daily ( 2.2 ). Heart failure post-myocardial infarction: Starting dose of 2.5 mg twice daily. If patient becomes hypotensive at this dose, decrease dosage to 1.25 mg twice daily.
Increase dose as tolerated toward a target dose of 5 mg twice daily, with dosage increases about 3 weeks apart ( 2.3 ). Dosage adjustment: See respective sections pertaining to dosage adjustment in special situations ( 2.5 ).
2.1Hypertension The recommended initial dose for patients not receiving a diuretic is 2.5 mg once a day. Adjust dose according to blood pressure response. The usual maintenance dosage range is 2.5 mg to 20 mg per day administered as a single dose or in two equally divided doses.
In some patients treated once daily, the antihypertensive effect may diminish toward the end of the dosing interval. In such patients, consider an increase in dosage or twice daily administration. If blood pressure is not controlled with ramipril alone, a diuretic can be added.
2.2Reduction in Risk of Myocardial Infarction, Stroke, and Death from Cardiovascular Causes Initiate dosing at 2.5 mg once daily for 1 week, 5 mg once daily for the next 3 weeks, and then increase as tolerated, to a maintenance dose of 10 mg once daily. If the patient is hypertensive or recently post-myocardial infarction, ramipril capsule can also be given as a divided dose.
2.3Heart Failure Post-Myocardial Infarction For the treatment of post-myocardial infarction patients who have shown signs of congestive heart failure, the recommended starting dose of ramipril is 2.5 mg twice daily (5 mg per day). A patient who becomes hypotensive at this dose may be switched to 1.25 mg twice daily. After one week at the starting dose, increase dose (if tolerated) toward a target dose of 5 mg twice daily, with dosage increases being about 3 weeks apart.
After the initial dose of ramipril, observe the patient under medical supervision for at least two hours and until blood pressure has stabilized for at least an additional hour. If possible, reduce the dose of any concomitant diuretic as this may diminish the likelihood of hypotension. The appearance of hypotension after the initial dose of ramipril does not preclude subsequent careful dose titration with the drug, following effective management of the hypotension [see WARNINGS AND PRECAUTIONS ( 5.5 ), DRUG INTERACTIONS ( 7.1 )] .
2.4General Dosing Information Generally, swallow ramipril capsules whole. The ramipril capsule can also be opened and the contents sprinkled on a small amount (about 4 oz.) of applesauce or mixed in 4 oz. (120 mL) of water or apple juice.
To be sure that ramipril is not lost when such a mixture is used, consume the mixture in its entirety. The described mixtures can be pre-prepared and stored for up to 24 hours at room temperature or up to 48 hours under refrigeration. Concomitant administration of ramipril with potassium supplements, potassium salt substitutes, or potassium-sparing diuretics can lead to increases of serum potassium [see WARNINGS AND PRECAUTIONS ( 5.8 )].
2.5Dosage Adjustment Renal Impairment Establish baseline renal function in patients initiating ramipril. Usual regimens of therapy with ramipril may be followed in patients with estimated creatinine clearance >40 mL/min. However, in patients with worse impairment, 25 % of the usual dose of ramipril is expected to produce full therapeutic levels of ramiprilat [see USE IN SPECIFIC POPULATIONS ( 8.6 )] . Hypertension For patients with hypertension an…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsule: 2.5 mg, 5 mg, 10 mg ( 3 ) Ramipril capsules USP are supplied as hard gelatin capsules containing 2.5 mg, 5 mg, and 10 mg of ramipril.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Angioedema related to previous treatment with an ACE inhibitor, or a history of hereditary or idiopathic angioedema ( 4 ). Ramipril capsules are contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril). Do not administer ramipril capsules within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor ( 4 ).
Do not co-administer aliskiren with ramipril in patients with diabetes ( 4 ). Ramipril is contraindicated in patients who are hypersensitive to this product or any other ACE inhibitor (e.g., a patient who has experienced angioedema during therapy with any other ACE inhibitor). Ramipril capsules are contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril).
Do not administer ramipril capsules within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor [see WARNINGS AND PRECAUTIONS ( 5.1 )]. Do not co-administer ramipril with aliskiren: in patients with diabetes
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Angioedema: increased risk in patients with a prior history ( 5.1 ) Hypotension and hyperkalemia ( 5.5 , 5.8 ) Renal impairment: monitor renal function during therapy ( 5.3 ) Avoid concomitant use of an ACE inhibitor and angiotensin blocker ( 5.7 ) Rare cholestatic jaundice and hepatic failure ( 5.2 ) Rare neutropenia and agranulocytosis ( 5.4 )
5.1Anaphylactoid and Possibly Related Reactions Presumably because drugs that act directly on the renin-angiotensin-aldosterone system (e.g., ACE inhibitors) affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving these drugs (including ramipril) may be subject to a variety of adverse reactions, some of them serious. Angioedema Head and Neck Angioedema: Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor.
Angioedema of the face, extremities, lips, tongue, glottis, and larynx has been reported in patients treated with ACE inhibitors. Angioedema associated with laryngeal edema can be fatal. If laryngeal stridor or angioedema of the face, tongue, or glottis occurs, discontinue treatment with ramipril and institute appropriate therapy immediately.
Where there is involvement of the tongue, glottis, or larynx likely to cause airway obstruction, administer appropriate therapy (e.g., subcutaneous epinephrine solution 1:1000 [0.3 mL to 0.5 mL]) promptly [see ADVERSE REACTIONS ( 6 )] . In considering the use of ramipril, note that in controlled clinical trials ACE inhibitors cause a higher rate of angioedema in Black patients than in non-Black patients. In a large U.S. post-marketing study, angioedema (defined as reports of angio, face, larynx, tongue, or throat edema) was reported in 3/1523 (0.20%) Black patients and in 8/8680 (0.09%) non-Black patients.
These rates were not different statistically. Patients taking concomitant mammalian target of rapamycin (mTOR) inhibitor (e.g. temsirolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema. [see DRUG INTERACTIONS ( 7.7 )] Intestinal Angioedema: Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal.
The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor. Include intestinal angioedema in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain. Anaphylactoid Reactions During Desensitization Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions.
In the same patients, these reactions were avoided when ACE inhibitors were temporarily withheld, but they reappeared upon inadvertent rechallenge. Anaphylactoid Reactions During Membrane Exposure Anaphylactoid reactions have been reported in patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor. Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption.
5.2Hepatic Failure and Impaired Liver Function Rarely, ACE inhibitors, including ramipril, have been associated with a syndrome that starts with cholestatic jaundice and progresses to fulminant hepatic necrosis and sometimes death. The mechanism of this syndrome is not understood. Discontinue ramipril if patient develops jaundice or marked elevations of hepatic enzymes.
As ramipril is primarily metabolized by hepatic esterases to its active moiety, ramiprilat, patients with impaired liver function could develop markedly elevated plasma levels of ramipril. No formal pharmacokinetic studies have been carried out in hyp…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions in patients with hypertension included headache, dizziness, fatigue, and cough ( 6.1 ). To report SUSPECTED ADVERSE REACTIONS, contact Lupin Pharmaceuticals, Inc. at 1-800-399-2561 or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, the adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Hypertension Ramipril has been evaluated for safety in over 4000 patients with hypertension; of these, 1230 patients were studied in U.S. controlled trials, and 1107 were studied in foreign controlled trials. Almost 700 of these patients were treated for at least one year.
The overall incidence of reported adverse events was similar in ramipril and placebo patients. The most frequent clinical side effects (possibly or probably related to study drug) reported by patients receiving ramipril in placebo-controlled trials were: headache (5.4%), dizziness (2.2%), and fatigue or asthenia (2.0%), but only the last one was more common in ramipril patients than in patients given placebo. Generally the side effects were mild and transient, and there was no relation to total dosage within the range of 1.25 mg to 20 mg.
Discontinuation of therapy because of a side effect was required in approximately 3% of U.S. patients treated with ramipril. The most common reasons for discontinuation were: cough (1.0%), dizziness (0.5%), and impotence (0.4%). Of observed side effects considered possibly or probably related to study drug that occurred in U.S. placebo-controlled trials in more than 1% of patients treated with ramipril, only asthenia (fatigue) was more common on ramipril than placebo (2% [n=13/651] vs.
1% [n=2/286], respectively). In placebo-controlled trials, there was also an excess of upper respiratory infection and flu syndrome in the ramipril group, not attributed at that time to ramipril. As these studies were carried out before the relationship of cough to ACE inhibitors was recognized, some of these events may represent ramipril-induced cough.
In a later 1-year study, increased cough was seen in almost 12% of ramipril patients, with about 4% of patients requiring discontinuation of treatment. Reduction in the Risk of Myocardial Infarction, Stroke, and Death from Cardiovascular Causes HOPE Study: Safety data in the Heart Outcomes Prevention Evaluation (HOPE) study were collected as reasons for discontinuation or temporary interruption of treatment. The incidence of cough was similar to that seen in the Acute Infarction Ramipril Efficacy (AIRE) trial.
The rate of angioedema was the same as in previous clinical trials [see WARNINGS AND PRECAUTIONS ( 5.1 )]. Table 1. Reasons for Discontinuation or Temporary Interruption of Treatment—HOPE Study Placebo (N=4652) Ramipril (N=4645) Discontinuation at any time 32% 34% Permanent discontinuation 28% 29% Reasons for stopping Cough 2% 7% Hypotension or dizziness 1.5% 1.9% Angioedema 0.1% 0.3% Heart Failure Post-Myocardial Infarction AIRE Study: Adverse reactions (except laboratory abnormalities) considered possibly/probably related to study drug that occurred in more than 1% of patients and more frequently on ramipril are shown below.
The incidences are from the AIRE study. The follow-up time was between 6 and 46 months for this study. Adverse Event Placebo (N=982) Ramipril (N=1004) Hypotension 5% 11% Cough increased 4% 8% Dizziness 3% 4% Angina pectoris 2% 3% Nausea 1% 2% Postural hypotension 1% 2% Syncope 1% 2% Vomiting 0.5% 2% Vertigo 0.7% 2% Abnormal kidney function 0.5% 1% Diarrhea 0.4% 1% Other Adverse Reactions Other adverse reactions reported in controlled clinical trials (in less than 1% of ramipril patients), or rarer events seen in post-marketing experience, include the following (in some, a causal relation…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Diuretics: Possibility of excessive hypotension ( 7.1 ). Lithium: Use with caution ( 7.4 ). Gold: Nitritoid reactions have been reported ( 7.5 ). NSAIDS use may lead to increased risk of renal impairment and loss of antihypertensive effect ( 7.6 ). mTOR inhibitor or neprilysin inhibitor use may increase angioedema risk ( 7.7 ).
7.1Diuretics Patients on diuretics, especially those in whom diuretic therapy was recently instituted, may occasionally experience an excessive reduction of blood pressure after initiation of therapy with ramipril. The possibility of hypotensive effects with ramipril can be minimized by either decreasing or discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with ramipril. If this is not possible, reduce the starting dose [see DOSAGE AND ADMINISTRATION ( 2 )] .
7.2Agents Increasing Serum Potassium Coadministration of ramipril with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
7.3Other Agents Affecting RAS In general, avoid combined use of RAS inhibitors. [see WARNINGS AND PRECAUTIONS ( 5.7 )] . Do not co-administer aliskiren with ramipril in patients with diabetes [see CONTRAINDICATIONS ( 4 )].
7.4Lithium Increased serum lithium levels and symptoms of lithium toxicity have been reported in patients receiving ACE inhibitors during therapy with lithium; therefore, frequent monitoring of serum lithium levels is recommended. If a diuretic is also used, the risk of lithium toxicity may be increased.
7.5Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including ramipril.
7.6Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including ramipril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving ramipril and NSAID therapy.
The antihypertensive effect of ACE inhibitors, including ramipril, may be attenuated by NSAIDs. 7.7 mTOR Inhibitors or Other Drugs Known to Cause Angioedema Patients taking concomitant mTOR inhibitor (e.g. temsirolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema. [see WARNINGS AND PRECAUTIONS ( 5.1 )]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Discontinue drug if pregnancy is detected ( 5.6 , 8.1 ). Nursing mothers: Ramipril use is not recommended in nursing mothers ( 8.3 ).
8.1Pregnancy Pregnancy Category D Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations. Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death.
When pregnancy is detected, discontinue ramipril as soon as possible. These adverse outcomes are usually associated with use of these drugs in the second and third trimester of pregnancy. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Appropriate management of maternal hypertension during pregnancy is important to optimize outcomes for both mother and fetus. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus. Perform serial ultrasound examinations to assess the intra-amniotic environment.
If oligohydramnios is observed, discontinue ramipril unless it is considered life-saving for the mother. Fetal testing may be appropriate, based on the week of pregnancy. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to ramipril for hypotension, oliguria, and hyperkalemia [see USE IN SPECIFIC POPULATIONS ( 8.4 )] .
8.3Nursing Mothers Ingestion of a single 10 mg oral dose of ramipril resulted in undetectable amounts of ramipril and its metabolites in breast milk. However, because multiple doses may produce low milk concentrations that are not predictable from a single dose, do not use ramipril in nursing mothers.
8.4Pediatric Use Neonates with a history of in utero exposure to ramipril If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Ramipril, which crosses the placenta, can be removed from the neonatal circulation by these means, but limited experience has not shown that such removal is central to the treatment of these infants.
Safety and effectiveness in pediatric patients have not been established. Irreversible kidney damage has been observed in very young rats given a single dose of ramipril.
8.5Geriatric Use Of the total number of patients who received ramipril in U.S. clinical studies of ramipril, 11.0% were ≥65 years of age while 0.2% were ≥75 years of age. No overall differences in effectiveness or safety were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but a greater sensitivity of some older individuals cannot be ruled out. One pharmacokinetic study conducted in hospitalized elderly patients indicated that peak ramiprilat levels and area under the plasma concentration-time curve (AUC) for ramiprilat are higher in older patients.
8.6Renal Impairment A single-dose pharmacokinetic study was conducted in hypertensive patients with varying degrees of renal impairment who received a single 10 mg dose of ramipril. Patients were stratified into four groups based on initial estimates of creatinine clearance: normal (>80 mL/min), mild impairment (40 to 80 mL/min), moderate impairment (15 to 40 mL/min), and severe impairment (<15 mL/min). On average,…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category D Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations. Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death.
When pregnancy is detected, discontinue ramipril as soon as possible. These adverse outcomes are usually associated with use of these drugs in the second and third trimester of pregnancy. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
Appropriate management of maternal hypertension during pregnancy is important to optimize outcomes for both mother and fetus. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus. Perform serial ultrasound examinations to assess the intra-amniotic environment.
If oligohydramnios is observed, discontinue ramipril unless it is considered life-saving for the mother. Fetal testing may be appropriate, based on the week of pregnancy. Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to ramipril for hypotension, oliguria, and hyperkalemia [see USE IN SPECIFIC POPULATIONS ( 8.4 )] .
🧒 Pediatric Use ▾
8.4Pediatric Use Neonates with a history of in utero exposure to ramipril If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Ramipril, which crosses the placenta, can be removed from the neonatal circulation by these means, but limited experience has not shown that such removal is central to the treatment of these infants.
Safety and effectiveness in pediatric patients have not been established. Irreversible kidney damage has been observed in very young rats given a single dose of ramipril.
🆘 Overdosage ▾
10 OVERDOSAGE Single oral doses of ramipril in rats and mice of 10 g/kg to 11 g/kg resulted in significant lethality. In dogs, oral doses as high as 1 g/kg induced only mild gastrointestinal distress. Limited data on human overdosage are available.
The most likely clinical manifestations would be symptoms attributable to hypotension. Laboratory determinations of serum levels of ramipril and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of ramipril overdose. No data are available to suggest physiological maneuvers (e.g., maneuvers to change the pH of the urine) that might accelerate elimination of ramipril and its metabolites.
Similarly, it is not known which, if any, of these substances can be effectively removed from the body by hemodialysis. Angiotensin II could presumably serve as a specific antagonist-antidote in the setting of ramipril overdose, but angiotensin II is essentially unavailable outside of scattered research facilities. Because the hypotensive effect of ramipril is achieved through vasodilation and effective hypovolemia, it is reasonable to treat ramipril overdose by infusion of normal saline solution.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ramipril and ramiprilat inhibit ACE in human subjects and animals. Angiotensin converting enzyme is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium. In hypertensive patients with normal renal function treated with ramipril alone for up to 56 weeks, approximately 4% of patients during the trial had an abnormally high serum potassium and an increase from baseline greater than 0.75 mEq/L, and none of the patients had an abnormally low potassium and a decrease from baseline greater than 0.75 mEq/L.
In the same study, approximately 2% of patients treated with ramipril and hydrochlorothiazide for up to 56 weeks had abnormally high potassium values and an increase from baseline of 0.75 mEq/L or greater; and approximately 2% had abnormally low values and decreases from baseline of 0.75 mEq/L or greater [see WARNINGS AND PRECAUTIONS ( 5.8 )] . Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity. The effect of ramipril on hypertension appears to result at least in part from inhibition of both tissue and circulating ACE activity, thereby reducing angiotensin II formation in tissue and plasma.
Angiotensin converting enzyme is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasopressor peptide, play a role in the therapeutic effects of ramipril remains to be elucidated. While the mechanism through which ramipril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, ramipril has an antihypertensive effect even in patients with low-renin hypertension.
Although ramipril was antihypertensive in all races studied, Black hypertensive patients (usually a low-renin hypertensive population) had a blood pressure lowering response to monotherapy, albeit a smaller average response, than non-Black patients.
12.2Pharmacodynamics Single doses of ramipril of 2.5 mg to 20 mg produce approximately 60% to 80% inhibition of ACE activity 4 hours after dosing with approximately 40% to 60% inhibition after 24 hours. Multiple oral doses of ramipril of 2.0 mg or more cause plasma ACE activity to fall by more than 90% 4 hours after dosing, with over 80% inhibition of ACE activity remaining 24 hours after dosing. The more prolonged effect of even small multiple doses presumably reflects saturation of ACE binding sites by ramiprilat and relatively slow release from those sites.
12.3Pharmacokinetics Absorption Following oral administration of ramipril, peak plasma concentrations (C max ) of ramipril are reached within 1 hour. The extent of absorption is at least 50% to 60%, and is not significantly influenced by the presence of food in the gastrointestinal tract, although the rate of absorption is reduced. In a trial in which subjects received ramipril capsules or the contents of identical capsules dissolved in water, dissolved in apple juice, or suspended in applesauce, serum ramiprilat levels were essentially unrelated to the use or non-use of the concomitant liquid or food.
Distribution Cleavage of the ester group (primarily in the liver) converts ramipril to its active diacid metabolite, ramiprilat. Peak plasma concentrations of ramiprilat are reached 2 to 4 hours after drug intake. The serum protein binding of ramipril is about 73% and that of ramiprilat about 56%; in vitro, these percentages are independent of concentration over the range of 0.01 mcg/mL to 10 mcg/mL.
Metabolism Ramipril is almost completely metabolized to ramiprilat, which has about 6 times the ACE inhibitory activity of ra…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ramipril and ramiprilat inhibit ACE in human subjects and animals. Angiotensin converting enzyme is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. The latter decrease may result in a small increase of serum potassium. In hypertensive patients with normal renal function treated with ramipril alone for up to 56 weeks, approximately 4% of patients during the trial had an abnormally high serum potassium and an increase from baseline greater than 0.75 mEq/L, and none of the patients had an abnormally low potassium and a decrease from baseline greater than 0.75 mEq/L.
In the same study, approximately 2% of patients treated with ramipril and hydrochlorothiazide for up to 56 weeks had abnormally high potassium values and an increase from baseline of 0.75 mEq/L or greater; and approximately 2% had abnormally low values and decreases from baseline of 0.75 mEq/L or greater [see WARNINGS AND PRECAUTIONS ( 5.8 )] . Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity. The effect of ramipril on hypertension appears to result at least in part from inhibition of both tissue and circulating ACE activity, thereby reducing angiotensin II formation in tissue and plasma.
Angiotensin converting enzyme is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasopressor peptide, play a role in the therapeutic effects of ramipril remains to be elucidated. While the mechanism through which ramipril lowers blood pressure is believed to be primarily suppression of the renin-angiotensin-aldosterone system, ramipril has an antihypertensive effect even in patients with low-renin hypertension.
Although ramipril was antihypertensive in all races studied, Black hypertensive patients (usually a low-renin hypertensive population) had a blood pressure lowering response to monotherapy, albeit a smaller average response, than non-Black patients.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ramipril capsules USP, 5 mg are: Size "4" capsules with red cap, imprinted with 'LUPIN' in black ink and red body imprinted with 'RAMIPRIL 5 mg' in black ink, containing white to off-white powder. NDC 71335-9645-1: 30 Capsules in a BOTTLE NDC 71335-9645-2: 20 Capsules in a BOTTLE NDC 71335-9645-3: 90 Capsules in a BOTTLE NDC 71335-9645-4: 60 Capsules in a BOTTLE NDC 71335-9645-5: 10 Capsules in a BOTTLE Dispense in light-resistant, tight container with child-resistant closure. Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Repackaged/Relabeled by: Bryant Ranch Prepack Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Ramipril is a 2-aza-bicyclo [3.3.0]-octane-3-carboxylic acid derivative. It is a white, crystalline substance soluble in polar organic solvents and buffered aqueous solutions. Ramipril melts between 105°-112°C.
The CAS Registry Number is 87333-19-5. Ramipril's chemical name is (2 S ,3a S ,6a S )-1[( S )- N -[( S )-1-Carboxy-3-phenylpropyl] alanyl] octahydrocyclopenta [ b ]pyrrole-2-carboxylic acid, 1-ethyl ester. Ramipril capsules USP are supplied as hard gelatin capsules for oral administration containing 2.5 mg, 5 mg, and 10 mg of ramipril.
The inactive ingredients present are gelatin, meglumine, pregelatinized starch, and titanium dioxide. The 2.5 mg capsule contains D&C yellow #10 and FD&C red #40, the 5 mg capsule shell contains FD&C blue #1 and FD&C red #40, and the 10 mg capsule shell contains FD&C blue #1. The structural formula for ramipril is: Its empirical formula is C 23 H 32 N 2 O 5 and its molecular weight is 416.5.
Ramiprilat, the diacid metabolite of ramipril, is a non-sulfhydryl ACE inhibitor. Ramipril is converted to ramiprilat by hepatic cleavage of the ester group.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Angioedema Angioedema, including laryngeal edema, can occur with treatment with ACE inhibitors, especially following the first dose. Advise patients to immediately report any signs or symptoms suggesting angioedema (swelling of face, eyes, lips, or tongue, or difficulty in breathing) and to temporarily discontinue drug until they have consulted with the prescribing physician. Neutropenia Advise patients to promptly report any indication of infection (e.g., sore throat, fever), which could be a sign of neutropenia.
Symptomatic Hypotension Inform patients that light-headedness can occur, especially during the first days of therapy, and it should be reported. Advise patients to discontinue ramipril if syncope (fainting) occurs, and to follow up with their health care providers. Inform patients that inadequate fluid intake or excessive perspiration, diarrhea, or vomiting while taking ramipril can lead to an excessive fall in blood pressure, with the same consequences of lightheadedness and possible syncope.
Pregnancy Tell female patients of childbearing age about the consequences of exposure to ramipril during pregnancy. Discuss treatment options with women planning to become pregnant. Ask patients to report pregnancies to their physicians as soon as possible.
Hyperkalemia Advise patients not to use salt substitutes containing potassium without consulting their physician. LUPIN and the are registered trademarks of Lupin Pharmaceuticals, Inc. Manufactured for: Lupin Pharmaceuticals, Inc.
Naples, FL 34108 United States MADE IN INDIA Revised: June 2024 ID#: 276375