
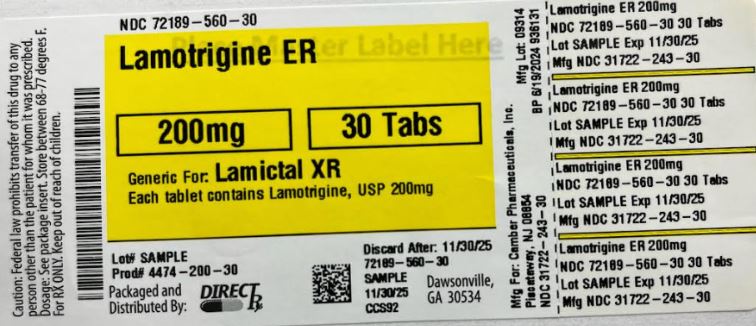
Lamotrigine ER 200 mg Tablet, Film Coated, Extended Release, 30-count — NDC 72189-560-30 (Billing 72189-0560-30)
This is a package of 30 tablets of Lamotrigine ER 200 mg Tablet, Film Coated, Extended Release from Direct_rx, marketed since Jun 2024 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 065253
- GCN: 24739
- HICL (First Databank): 007378
- AHFS class code: 28:12.92.00
- RxCUI (RxNorm): 900156
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Mood Stabilizer class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Lamotrigine extended-release (long-acting) tablets are used with other medications to treat certain types of seizures in patients who have epilepsy. All types of lamotrigine tablets (tablets, orally disintegrating tablets, and chewable tablets) other than the extended-release tablets are used alone or with other medications to treat seizures in people who have epilepsy or Lennox-Gastaut syndrome (a disorder that causes seizures and often causes developmental delays). All types of lamotrigine tablets other than the extended-release tablets are also used to increase the time between episodes of...
Read the full MedlinePlus article ↗- It treats epilepsy, helping control certain seizure types. Some forms, like tablets, chewables and orally disintegrating tablets, are also used to delay mood episodes in bipolar I...
- Lamotrigine can cause serious, even life-threatening skin reactions, mostly in the first 2 to 8 weeks. We can't tell which rashes are dangerous, so call your doctor right away abou...
- Take it by mouth exactly as prescribed, increasing slowly as planned. Skipping ahead raises rash risk. Extended-release tablets are once daily and must be swallowed whole. Food doe...
- Please don't stop on your own. Stopping suddenly can trigger withdrawal seizures. Your doctor will taper you off over at least 2 weeks.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.29 | $38.56 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72189-0560-30 You're viewing this Main listing | 30 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE | 2024-06-19 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lamotrigine 200 mg 00228-1453-03 | Actavis | 30 tablets | $0.609 | AB | Availability likely | — |
| Lamotrigine 200 mg 16714-0626-01 | NorthStar | 30 tablets | $0.609 | AB | Availability likely | — |
| lamotrigine 200 mg 31722-0243-30 | Camber | 30 tablets | $0.609 | AB | Availability likely | — |
| Lamotrigine 200 mg 65162-0986-03 | Amneal | 30 tablets | $0.609 | AB | Availability likely | — |
| Lamictal Xr 200 mg 00173-0757-00 | GlaxoSmithKline | 30 tablets | $32.331 | AB | Availability likely | — |
| Lamotrigine Extended-Release 200 mg 10370-0208-11 | Par | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine 200 mg 42291-0446-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine 200 mg 46708-0417-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine 200 mg 55111-0720-05 | Dr.Reddy's | 500 tablets | — | AB | FDA listed | — |
| Lamotrigine 200 mg 62332-0417-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine 200 mg 68382-0982-05 | Zydus | 500 tablets | — | AB | FDA listed | — |
| lamotrigine 200 mg 69117-0047-01 | Yiling | 30 tablets | — | AB | FDA listed | — |
| lamotrigine 200 mg 70518-4638-00 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| Lamotrigine 200 mg 70771-1517-03 | Zydus | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine ER 200 mg 72189-0467-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Lamotrigine ER 200 mgthis 72189-0560-30 | Direct_rx | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII KC98RO82HJ
A waxy substance made from glycerin and fatty acids. It acts as an emulsifier to help mix oil and water components, and as a thickener to give the medicine proper texture and consistency.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS SKIN RASHES Lamotrigine Extended-Release Tablets can cause serious rashes requiring hospitalization and discontinuation of treatment. The incidence of these rashes, which have included Stevens-Johnson syndrome, is approximately 0.8% (8 per 1,000) in pediatric patients (aged 2 to 16 years) receiving immediate-release lamotrigine as adjunctive therapy for epilepsy and 0.3% (3 per 1,000) in adults on adjunctive therapy for epilepsy. In a prospectively followed cohort of 1,983 pediatric patients (aged 2 to 16 years) with epilepsy taking adjunctive immediate-release lamotrigine, there was 1 rash-related death.
Lamotrigine Extended-Release Tablets are not approved for patients younger than 13 years. In worldwide postmarketing experience, rare cases of toxic epidermal necrolysis and/or rash-related death have been reported in adult and pediatric patients, but their numbers are too few to permit a precise estimate of the rate. The risk of serious rash caused by treatment with Lamotrigine Extended-Release Tabletsis not expected to differ from that with immediate-release lamotrigine.
However, the relatively limited treatment experience with Lamotrigine Extended-Release Tablets makes it difficult to characterize the frequency and risk of serious rashes caused by treatment with Lamotrigine Extended-Release Tablets. Other than age, there are as yet no factors identified that are known to predict the risk of occurrence or the severity of rash caused by Lamotrigine Extended-Release Tablets. There are suggestions, yet to be proven, that the risk of rash may also be increased by (1) coadministration of Lamotrigine Extended-Release Tablets with valproate (includes valproic acid and divalproex sodium), (2) exceeding the recommended initial dose of Lamotrigine Extended-Release Tablets or (3) exceeding the recommended dose escalation for Lamotrigine Extended-Release Tablets.
However, cases have occurred in the absence of these factors. Nearly all cases of life-threatening rashes caused by immediate-release lamotrigine have occurred within 2 to 8 weeks of treatment initiation. However, isolated cases have occurred after prolonged treatment (e.g., 6 months).
Accordingly, duration of therapy cannot be relied upon as means to predict the potential risk heralded by the first appearance of a rash. Although benign rashes are also caused by Lamotrigine Extended-Release Tablets, it is not possible to predict reliably which rashes will prove to be serious or life threatening. Accordingly, Lamotrigine Extended-Release Tablets should ordinarily be discontinued at the first sign of rash, unless the rash is clearly not drug related.
Discontinuation of treatment may not prevent a rash from becoming life threatening or permanently disabling or disfiguring [see Warnings and Precautions ( 5.1)] .
🎯 Indications and Usage ▾
1.1Adjunctive Therapy Lamotrigine Extended-Release Tablets are indicated as adjunctive therapy for primary generalized tonic-clonic (PGTC) seizures and partial-onset seizures with or without secondary generalization in patients aged 13 years and older.
1.2Monotherapy Lamotrigine Extended-Release Tablets are indicated for conversion to monotherapy in patients aged 13 years and older with partial-onset seizures who are receiving treatment with a single antiepileptic drug (AED). Safety and effectiveness of Lamotrigine Extended-Release Tablets have not been established (1) as initial monotherapy or (2) for simultaneous conversion to monotherapy from 2 or more concomitant AEDs.
1.3Limitation of Use Safety and effectiveness of Lamotrigine Extended-Release Tablets for use in patients younger than 13 years have not been established.
⏱️ Dosage and Administration ▾
Lamotrigine Extended-Release Tablets are taken once daily, with or without food. Tablets must be swallowed whole and must not be chewed, crushed, or divided.
2.1General Dosing Considerations Rash There are suggestions, yet to be proven, that the risk of severe, potentially life-threatening rash may be increased by (1) coadministration of Lamotrigine Extended-Release Tablets with valproate, (2) exceeding the recommended initial dose of Lamotrigine Extended-Release Tablets, or (3) exceeding the recommended dose escalation for Lamotrigine Extended-Release Tablets. However, cases have occurred in the absence of these factors [see Boxed Warning]. Therefore, it is important that the dosing recommendations be followed closely.
The risk of nonserious rash may be increased when the recommended initial dose and/or the rate of dose escalation for Lamotrigine Extended-Release Tablets is exceeded and in patients with a history of allergy or rash to other AEDs. It is recommended that Lamotrigine Extended-Release Tablets not be restarted in patients who discontinued due to rash associated with prior treatment with lamotrigine unless the potential benefits clearly outweigh the risks. If the decision is made to restart a patient who has discontinued Lamotrigine Extended-Release Tablets, the need to restart with the initial dosing recommendations should be assessed.
The greater the interval of time since the previous dose, the greater consideration should be given to restarting with the initial dosing recommendations. If a patient has discontinued lamotrigine for a period of more than 5 half-lives, it is recommended that initial dosing recommendations and guidelines be followed. The half-life of lamotrigine is affected by other concomitant medications [see Clinical Pharmacology (12.3)].
Lamotrigine Extended-Release Tablets Added to Drugs Known to Induce or Inhibit Glucuronidation Because lamotrigine is metabolized predominantly by glucuronic acid conjugation, drugs that are known to induce or inhibit glucuronidation may affect the apparent clearance of lamotrigine. Drugs that induce glucuronidation include carbamazepine, phenytoin, phenobarbital, primidone, rifampin, estrogen-containing oral contraceptives, and the protease inhibitors lopinavir/ritonavir and atazanavir/ritonavir. Valproate inhibits glucuronidation.
For dosing considerations for Lamotrigine Extended-Release Tablets in patients on estrogen-containing contraceptives and atazanavir/ritonavir, see below and Table 5. For dosing considerations for Lamotrigine Extended-Release Tablets in patients on other drugs known to induce or inhibit glucuronidation, see Table 1 and Table 5. Target Plasma Levels A therapeutic plasma concentration range has not been established for lamotrigine.
Dosing of Lamotrigine Extended-Release Tablets should be based on therapeutic response [see Clinical Pharmacology (12.3)]. Women Taking Estrogen-Containing Oral Contraceptives Starting Lamotrigine Extended-Release Tablets in Women Taking Estrogen-Containing Oral Contraceptives: Although estrogen-containing oral contraceptives have been shown to increase the clearance of lamotrigine [see Clinical Pharmacology (12.3)], no adjustments to the recommended dose-escalation guidelines for Lamotrigine Extended-Release Tablets should be necessary solely based on the use of estrogen-containing oral contraceptives.
Therefore, dose escalation should follow the recommended guidelines for initiating adjunctive therapy with Lamotrigine Extended-Release Tablets based on the concomitant AED or other concomitant medications (see Table 1). See below for adjustments to maintenance doses of Lamotrigine Extended-Release Tablets in women taking estrogen-containing oral contraceptives. Adjustments to the Maintenance Dose of Lamotrigine Extended-Release Tablets in Women Taking Estrogen-Containing Oral Contraceptives: (1) Taking Estrogen-Containing Oral Contraceptives: In women not taking carbamazepine, phenytoin, phenobarbital, prim… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3.1Extended-Release Tablets 25 mg, yellow, round, biconvex, film-coated tablets printed with ‘Y31’ on one side in black ink and no mark on the reverse side. 50 mg, green, round, biconvex, film-coated tablets printed with ‘Y32’ on one side in black ink and no mark on the reverse side. 100 mg, orange, round, biconvex, film-coated tablets printed with ‘Y33’ on one side in black ink and no mark on the reverse side.
200 mg, blue, round, biconvex, film-coated tablets printed with ‘Y34’on one side in black ink and no mark on the reverse side. 250 mg, purple, caplet-shaped, biconvex, film-coated tablets printed with ‘Y35’ on one side in black ink and no mark on the reverse side. 300 mg, gray, caplet-shaped, biconvex, film-coated tablets printed with ‘Y36’ on one side in black ink and no mark on the reverse side.
⛔ Contraindications ▾
Lamotrigine Extended-Release Tablets are contraindicated in patients who have demonstrated hypersensitivity (e.g., rash, angioedema, acute urticaria, extensive pruritus, mucosal ulceration) to the drug or its ingredients [see BOXED WARNING, Warnings and Precautions ( 5.1, 5.3)] .
⚠️ Warnings and Cautions ▾
5.1Serious Skin Rashes [see Boxed Warning] The risk of serious rash caused by treatment with Lamotrigine Extended-Release Tablets is not expected to differ from that with immediate-release lamotrigine [see Boxed Warning]. However, the relatively limited treatment experience with Lamotrigine Extended-Release Tablets makes it difficult to characterize the frequency and risk of serious rashes caused by treatment with Lamotrigine Extended-Release Tablets. Pediatric Population The incidence of serious rash associated with hospitalization and discontinuation of immediate-release lamotrigine in a prospectively followed cohort of pediatric patients (aged 2 to 16 years) with epilepsy receiving adjunctive therapy with immediate-release lamotrigine was approximately 0.8% (16 of 1,983).
When 14 of these cases were reviewed by 3 expert dermatologists, there was considerable disagreement as to their proper classification. To illustrate, one dermatologist considered none of the cases to be Stevens-Johnson syndrome; another assigned 7 of the 14 to this diagnosis. There was 1 rash-related death in this 1,983-patient cohort.
Additionally, there have been rare cases of toxic epidermal necrolysis with and without permanent sequelae and/or death in U.S. and foreign postmarketing experience. There is evidence that the inclusion of valproate in a multidrug regimen increases the risk of serious, potentially life-threatening rash in pediatric patients. In pediatric patients who used valproate concomitantly, 1.2% (6 of 482) experienced a serious rash compared with 0.6% (6 of 952) patients not taking valproate.
Lamotrigine Extended-Release Tablets are not approved in patients younger than 13 years. Adult Population Serious rash associated with hospitalization and discontinuation of immediate-release lamotrigine occurred in 0.3% (11 of 3,348) of adult patients who received immediate-release lamotrigine in premarketing clinical trials of epilepsy. In worldwide postmarketing experience, rare cases of rash-related death have been reported, but their numbers are too few to permit a precise estimate of the rate.
Among the rashes leading to hospitalization were Stevens-Johnson syndrome, toxic epidermal necrolysis, angioedema, and those associated with multiorgan hypersensitivity [see Warnings and Precautions (5.3)]. There is evidence that the inclusion of valproate in a multidrug regimen increases the risk of serious, potentially life-threatening rash in adults. Specifically, of 584 patients administered immediate-release lamotrigine with valproate in epilepsy clinical trials, 6 (1%) were hospitalized in association with rash; in contrast, 4 (0.16%) of 2,398 clinical trial patients and volunteers administered immediate-release lamotrigine in the absence of valproate were hospitalized.
Patients with History of Allergy or Rash to Other Antiepileptic Drugs The risk of nonserious rash may be increased when the recommended initial dose and/or the rate of dose escalation for Lamotrigine Extended-Release Tablets is exceeded and in patients with a history of allergy or rash to other AEDs.
5.2Hemophagocytic Lymphohistiocytosis Hemophagocytic lymphohistiocytosis (HLH) has occurred in pediatric and adult patients taking Lamotrigine Extended-Release Tablets for various indications. HLH is a life-threatening syndrome of pathologic immune activation characterized by clinical signs and symptoms of extreme systemic inflammation. It is associated with high mortality rates if not recognized early and treated.
Common findings include fever, hepatosplenomegaly, rash, lymphadenopathy, neurologic symptoms, cytopenias, high serum ferritin,hypertriglyceridemia, and liver function and coagulation abnormalities. In cases of HLH reported with Lamotrigine Extended-Release Tablets, patients have presented with signs of systemic inflammation (fever, rash, hepatosplenomegaly, and organ system dysfunction) and blood dyscrasias. Symptoms have been reported to occur within 8 to 24 days foll… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
The following serious adverse reactions are described in more detail in the Warnings and Precautions section of the labeling: • Serious Skin Rashes [see Warnings and Precautions (5.1)] • Hemophagocytic Lymphohistiocytosis [see Warnings and Precautions (5.2)] • Multiorgan Hypersensitivity Reactions and Organ Failure [see Warnings and Precautions (5.3)] • Cardiac Rhythm and Conduction Abnormalities [see Warnings and Precautions (5.4)] • Blood Dyscrasias [see Warnings and Precautions (5.5)] • Suicidal Behavior and Ideation [see Warnings and Precautions (5.6)] • Aseptic Meningitis [see Warnings and Precautions (5.7)] • Withdrawal Seizures [see Warnings and Precautions (5.10)] • Status Epilepticus [see Warnings and Precautions (5.11)] • Sudden Unexplained Death in Epilepsy [see Warnings and Precautions (5.12)]
6.1Clinical Trial Experience with Lamotrigine Extended-Release Tablets for Treatment of Primary Generalized Tonic-Clonic and Partial-Onset Seizures Most Common Adverse Reactions in Clinical Trials Adjunctive Therapy in Patients with Epilepsy: Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in practice. In these 2 trials, adverse reactions led to withdrawal of 4 (2%) patients in the group receiving placebo and 10 (5%) patients in the group receiving Lamotrigine Extended-Release Tablets.
Dizziness was the most common reason for withdrawal in the group receiving Lamotrigine Extended-Release Tablets (5 patients [3%]). The next most common adverse reactions leading to withdrawal in 2 patients each (1%) were rash, headache, nausea, and nystagmus. Table 4 displays the incidence of adverse reactions in these two 19-week, double-blind, placebo-controlled trials of patients with PGTC and partial onset seizures.
Table 4. Adverse Reactions in Pooled, Placebo-Controlled, Adjunctive Trials in Patients with Epilepsy a Body System/ Adverse Reaction Percent of Patients Receiving Adjunctive Lamotrigine Extended-Release Tablets (n = 190) Percent of Patients Receiving Adjunctive Placebo (n = 195) Ear and labyrinth disorders Vertigo 3 <1 Eye disorders Diplopia Vision blurred 5 3 <1 2 Gastrointestinal disorders Nausea Vomiting Diarrhea Constipation Dry mouth 7 6 5 2 2 4 3 3 <1 1 General disorders and administration site conditions Asthenia and fatigue 6 4 Infections and infestations Sinusitis 2 1 Metabolic and nutritional disorders Anorexia 3 2 Musculoskeletal and connective tissue disorder Myalgia 2 0 Nervous system Dizziness Tremor and intention tremor Somnolence Cerebellar coordination and balance disorder Nystagmus 14 6 5 3 2 6 1 3 0 <1 Psychiatric disorders Depression Anxiety 3 3 <1 0 Respiratory, thoracic, and mediastinal disorders Pharyngolaryngeal pain 3 2 Vascular disorder Hot flush 2 0 a Adverse reactions that occurred in at least 2% of patients treated with Lamotrigine Extended-Release Tablets and at a greater incidence than placebo.
Note: In these trials the incidence of nonserious rash was 2% for Lamotrigine Extended-Release Tablets and 3% for placebo. In clinical trials evaluating immediate-release lamotrigine, the rate of serious rash was 0.3% in adults on adjunctive therapy for epilepsy [see Boxed Warning]. Adverse reactions were also analyzed to assess the incidence of the onset of an event in the titration period, and in the maintenance period, and if adverse reactions occurring in the titration phase persisted in the maintenance phase.
The incidence for many adverse reactions caused by treatment with Lamotrigine Extended-Release Tablets was increased relative to placebo (i.e., treatment difference between Lamotrigine Extended-Release Tablets and placebo≥2%) in either the titration or maintenance phases of the trial. During the titration phase, an increased incidence (shown in descending order of percent treatment difference) w… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Significant drug interactions with lamotrigine are summarized in this section. Additional details of these drug interaction studies, which were conducted using immediate-release lamotrigine, are provided in the Clinical Pharmacology section [see Clinical Pharmacology ( 12.3)] . Uridine 5´-diphospho-glucuronyl transferases (UGT) have been identified as the enzymes responsible for metabolism of lamotrigine.
Drugs that induce or inhibit glucuronidation may, therefore, affect the apparent clearance of lamotrigine. Strong or moderate inducers of the cytochrome P450 3A4 (CYP3A4) enzyme, which are also known to induce UGT, may also enhance the metabolism of lamotrigine. Those drugs that have been demonstrated to have a clinically significant impact on lamotrigine metabolism are outlined in Table 13.
Specific dosing guidance for these drugs is provided in the Dosage and Administration section [see Dosage and Administration ( 2.1)] . Table 5. Established and Other Potentially Significant Drug Interactions ↓ = Decreased (induces lamotrigine glucuronidation). ↑ = Increased (inhibits lamotrigine glucuronidation). ? = Conflicting data.
Concomitant Drug Effect on Concentration of Lamotrigine or Concomitant Drug Clinical Comment Estrogen-containing oral contraceptive preparations containing 30 mcg ethinylestradiol and 150 mcg levonorgestrel ↓ lamotrigine Decreased lamotrigine concentrations approximately 50%. ↓ levonorgestrel Decrease in levonorgestrel component by 19%. Carbamazepine and carbamazepine epoxide ↓ lamotrigine Addition of carbamazepine decreases lamotrigine concentration approximately 40%. ? carbamazepine epoxide May increase carbamazepine epoxide levels.
Lopinavir/ritonavir ↓ lamotrigine Decreased lamotrigine concentration approximately 50%. Atazanavir/ritonavir ↓ lamotrigine Decreased lamotrigine AUC approximately 32%. Phenobarbital/primidone ↓ lamotrigine Decreased lamotrigine concentration approximately 40%.
Phenytoin ↓ lamotrigine Decreased lamotrigine concentration approximately 40%. Rifampin ↓ lamotrigine Decreased lamotrigine AUC approximately 40%. Valproate ↑ lamotrigine Increased lamotrigine concentrations slightly more than 2-fold. ? valproate There are conflicting study results regarding effect of lamotrigine on valproate concentrations: 1) a mean 25% decrease in valproate concentrations in healthy volunteers, 2) no change in valproate concentrations in controlled clinical trials in patients with epilepsy.
Effect of Lamotrigine Extended-Release Tablets on Organic Cationic Transporter 2 Substrates Lamotrigine is an inhibitor of renal tubular secretion via organic cationic transporter 2 (OCT2) proteins [see Clinical Pharmacology ( 12.3)] . This may result in increased plasma levels of certain drugs that are substantially excreted via this route. Coadministration of Lamotrigine Extended-Release Tablets with OCT2 substrates with a narrow therapeutic index (e.g., dofetilide) is not recommended.
👥 Use in Specific Populations ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, including Lamotrigine Extended-Release Tablets, during pregnancy. Encourage women who are taking Lamotrigine Extended-Release Tablets during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Data from several prospective pregnancy exposure registries and epidemiological studies of pregnant women have not detected an increased frequency of major congenital malformations or a consistent pattern of malformations among women exposed to lamotrigine compared with the general population (see Data).
In animal studies, administration of lamotrigine during pregnancy resulted in developmental toxicity (increased mortality, decreased body weight, increased structural variation, neurobehavioral abnormalities) at doses lower than those administered clinically. Lamotrigine decreased fetal folate concentrations in rats, an effect known to be associated with adverse pregnancy outcomes in animals and humans (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations As with other AEDs, physiological changes during pregnancy may affect lamotrigine concentrations and/or therapeutic effect. There have been reports of decreased lamotrigine concentrations during pregnancy and restoration of pre-pregnancy concentrations after delivery.
Dose adjustments may be necessary to maintain clinical response. Data Human Data: Data from several international pregnancy registries have not shown an increased risk for malformations overall. The International Lamotrigine Pregnancy Registry reported major congenital malformations in 2.2% (95% CI: 1.6%, 3.1%) of 1,558 infants exposed to lamotrigine monotherapy in the first trimester of pregnancy.
The NAAED Pregnancy Registry reported major congenital malformations among 2.0% of 1,562 infants exposed to lamotrigine monotherapy in the first trimester. EURAP, a large international pregnancy registry focused outside of North America, reported major birth defects in 2.9% (95% CI: 2.3%, 3.7%) of 2,514 exposures to lamotrigine monotherapy in the first trimester. The frequency of major congenital malformations was similar to estimates from the general population.
The NAAED Pregnancy Registry observed an increased risk of isolated oral clefts: among 2,200 infants exposed to lamotrigine early in pregnancy, the risk of oral clefts was 3.2 per 1,000 (95% CI: 1.4, 6.3), a 3-fold increased risk versus unexposed healthy controls. This finding has not been observed in other large international pregnancy registries. Furthermore, a case-control study based on 21 congenital anomaly registries covering over 10 million births in Europe reported an adjusted odds ratio for isolated oral clefts with lamotrigine exposure of 1.45 (95% CI: 0.8, 2.63).
Several meta-analyses have not reported an increased risk of major congenital malformations following lamotrigine exposure in pregnancy compared with healthy and disease-matched controls. No patterns of specific malformation types were observed. The same meta-analyses evaluated the risk of additional maternal and infant outcomes including fetal death, stillbirth, preterm birth, small for gestational age, and neurodevelopmental delay.
Although there are no data suggesting an increased risk of these outcomes with lamotrigine monotherapy exposure, differences in outcome definition, ascertainment methods, and comparator groups limit the conclusions that can be drawn. Animal Data: When lamotrigine was administered to pregnant mice, rats, or rabbits during the period of organogen… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
10.1Human Overdose Experience Overdoses involving quantities up to 15 g have been reported for immediate-release lamotrigine, some of which have been fatal. Overdose has resulted in ataxia, nystagmus, seizures (including tonic-clonic seizures), decreased level of consciousness, coma, and intraventricular conduction delay.
10.2Management of Overdose There are no specific antidotes for lamotrigine. Following a suspected overdose, hospitalization of the patient is advised. General supportive care is indicated, including frequent monitoring of vital signs and close observation of the patient.
If indicated, emesis should be induced; usual precautions should be taken to protect the airway. It is uncertain whether hemodialysis is an effective means of removing lamotrigine from the blood. In 6 renal failure patients, about 20% of the amount of lamotrigine in the body was removed by hemodialysis during a 4-hour session.
A Poison Control Center should be contacted for information on the management of overdosage of Lamotrigine Extended-Release Tablets.
🧬 Clinical Pharmacology ▾
12.1Mechanism of Action The precise mechanism(s) by which lamotrigine exerts its anticonvulsant action are unknown. In animal models designed to detect anticonvulsant activity, lamotrigine was effective in preventing seizure spread in the maximum electroshock (MES) and pentylenetetrazol (scMet) tests, and prevented seizures in the visually and electrically evoked after-discharge (EEAD) tests for antiepileptic activity. Lamotrigine also displayed inhibitory properties in the kindling model in rats both during kindling development and in the fully kindled state.
The relevance of these models to human epilepsy, however, is not known. One proposed mechanism of action of lamotrigine, the relevance of which remains to be established in humans, involves an effect on sodium channels. In vitro pharmacological studies suggest that lamotrigine inhibits voltage-sensitive sodium channels, thereby stabilizing neuronal membranes and consequently modulating presynaptic transmitter release of excitatory amino acids (e.g., glutamate and aspartate).
Effect of Lamotrigine on N-Methyl d-Aspartate-Receptor–Mediated Activity Lamotrigine did not inhibit N-methyl d-aspartate (NMDA)-induced depolarizations in rat cortical slices or NMDA-induced cyclic GMP formation in immature rat cerebellum, nor did lamotrigine displace compounds that are either competitive or noncompetitive ligands at this glutamate receptor complex (CNQX, CGS, TCHP). The IC 50 for lamotrigine effects on NMDA-induced currents (in the presence of 3 µM of glycine) in cultured hippocampal neurons exceeded 100 µM.
12.2Pharmacodynamics Folate Metabolism In vitro, lamotrigine inhibited dihydrofolate reductase, the enzyme that catalyzes the reduction of dihydrofolate to tetrahydrofolate. Inhibition of this enzyme may interfere with the biosynthesis of nucleic acids and proteins. When oral daily doses of lamotrigine were given to pregnant rats during organogenesis, fetal, placental, and maternal folate concentrations were reduced.
Significantly reduced concentrations of folate are associated with teratogenesis [see Use in Specific Populations (8.1)]. Folate concentrations were also reduced in male rats given repeated oral doses of lamotrigine. Reduced concentrations were partially returned to normal when supplemented with folinic acid.
Cardiac Electrophysiology Effect of Lamotrigine: In vitro studies show that lamotrigine exhibits Class IB antiarrhythmic activity at therapeutically relevant concentrations. It inhibits human cardiac sodium channels with rapid onset and offset kinetics and strong voltage dependence, consistent with other Class IB antiarrhythmic agents. At therapeutic doses, Lamotrigine Extended-Release Tablets did not slow ventricular conduction (widen QRS) in healthy individuals in a thorough QT study; however, in patients with clinically important structural or functional heart disease (i.e., patients with heart failure, valvular heart disease, congenital heart disease, conduction system disease, ventricular arrhythmias, cardiac channelopathies [e.g., Brugada syndrome], clinically important ischemic heart disease, or multiple risk factors for coronary artery disease), Lamotrigine Extended-Release Tablets could slow ventricular conduction (widen QRS) and induce proarrhythmia, which can lead to sudden death.
Elevated heart rates could also increase the risk of ventricular conduction slowing with Lamotrigine Extended-Release Tablets. Effect of Lamotrigine Metabolite:In dogs, lamotrigine is extensively metabolized to a 2-N-methyl metabolite. This metabolite causes dose-dependent prolongation of the PR interval, widening of the QRS complex, and, at higher doses, complete AV conduction block.
The in vitro electrophysiological effects of this metabolite have not been studied. Similar cardiovascular effects from this metabolite are not anticipated in humans because only trace amounts of the 2-N-methyl metabolite (<0.6% of lamotrigine dose) have been found in human urine [see Clini… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
Lamotrigine Extended-Release Tablets, USP 25 mg, yellow, round, biconvex, film-coated tablets printed with 'Y31' on one side in black ink and no mark on the reverse side, unit-of-use bottles of 30 with white caps (NDC 31722-240-30). 50 mg, green, round, biconvex, film-coated tablets printed with 'Y32' on one side in black ink and no mark on the reverse side, unit-of-use bottles of 30 with white caps (NDC 31722-241-30). 100 mg, orange, round, biconvex, film-coated tablets printed with ‘Y33' on one side in black ink and no mark on the reverse side, unit-of-use bottles of 30 with white caps (NDC 31722-242-30).
200 mg, blue, round, biconvex, film-coated tablets printed with 'Y34' on one side in black ink and no mark on the reverse side, unit-of-use bottles of 30 with white caps (NDC 72189-560-30). 250 mg, purple, caplet-shaped, biconvex, film-coated tablets printed with ‘Y35' on one side in black ink and no mark on the reverse side, unit-of-use bottles of 30 with white caps (NDC 31722-244-30). 300 mg, gray, caplet-shaped, biconvex, film-coated tablets printed with 'Y36' on one side in black ink and no mark on the reverse side, unit-of-use bottles of 30 with white caps (NDC 31722-245-30).
📦 Storage and Handling ▾
Storage Store at 20° to 25°C(68° to 77°F); excursions permitted to 15° to 30°C(59° to 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
Lamotrigine, an AED of the phenyltriazine class, is chemically unrelated to existing AEDs. Lamotrigine’s chemical name is 3,5-diamino-6-(2,3-dichlorophenyl)- as-triazine, its molecular formula is C 9H 7N 5Cl 2, and its molecular weight is 256.09. Lamotrigine is a white to pale cream-colored powder and has a pK a of 5.7. Lamotrigine is very slightly soluble in water (0.17 mg/mL at 25°C) and slightly soluble in
0.1M HCl (4.1 mg/mL at 25°C). The structural formula is: [Chemical Structure] Lamotrigine Extended-Release Tablets, USP are supplied for oral administration as 25-mg (yellow), 50-mg (green), 100-mg (orange), 200-mg (blue), 250-mg (purple), and 300-mg (gray) tablets. Each tablet contains the labeled amount of lamotrigine and the following inactive ingredients: hypromellose, lactose monohydrate, magnesium stearate, methacrylic acid and ethyl arcylate copolymer dispersion, mono- and di-glycerides, polysorbate 80, silicon dioxide(25- and 50- mg tablets only), sodium hydroxide, sodium lauryl sulfate, titanium dioxide, triethyl citrate, iron oxide black(50- and 300- mg tablets only), iron oxide red(100- and 250- mg tablets only), iron oxide yellow(25-, 50-, 100- mg tablets only), FD&C Blue No.
2 Aluminum Lake(200- and 250- mg tablets only). Tablets are printed with edible black ink (black ink is composed of ferrosoferric oxide, propylene glycol and shellac). Lamotrigine Extended-Release Tablets, USP contain a modified-release formulation as the core.
The tablets are coated with a clear enteric coat to enable a controlled release of drug in the acidic environment of the stomach. The combination of this and the modified-release core are designed to control the dissolution rate of lamotrigine over a period of approximately 12 to 15 hours, leading to a gradual increase in serum lamotrigine levels. FDA approved dissolution test specifications differ from USP.
🔬 Clinical Studies ▾
14.1Adjunctive Therapy for Primary Generalized Tonic-Clonic Seizures The effectiveness of Lamotrigine Extended-Release Tablets as adjunctive therapy in subjects with PGTC seizures was established in a 19-week, international, multicenter, double-blind, randomized, placebo-controlled trial in 143 patients aged 13 years and older (n = 70 on Lamotrigine Extended-Release Tablets, n = 73 on placebo). Patients with at least 3 PGTC seizures during an 8-week baseline phase were randomized to 19 weeks of treatment with Lamotrigine Extended-Release Tablets or placebo added to their current AED regimen of up to 2 drugs.
Patients were dosed on a fixed-dose regimen, with target doses ranging from 200 to 500 mg/day of Lamotrigine Extended-Release Tablets based on concomitant AEDs (target dose = 200 mg for valproate, 300 mg for AEDs not altering plasma lamotrigine levels, and 500 mg for enzyme-inducing AEDs). The primary efficacy endpoint was percent change from baseline in PGTC seizure frequency during the double-blind treatment phase. For the intent-to-treat population, the median percent reduction in PGTC seizure frequency was 75% in patients treated with Lamotrigine Extended-Release Tablets and 32% in patients treated with placebo, a difference that was statistically significant, defined as a 2-sided P value ≤0.05.
Figure 1 presents the percentage of patients (X-axis) with a percent reduction in PGTC seizure frequency (responder rate) from baseline through the entire treatment period at least as great as that represented on the Y-axis. A positive value on the Y-axis indicates an improvement from baseline (i.e., a decrease in seizure frequency), while a negative value indicates a worsening from baseline (i.e., an increase in seizure frequency). Thus, in a display of this type, a curve for an effective treatment is shifted to the left of the curve for placebo.
The proportion of patients achieving any particular level of reduction in PGTC seizure frequency was consistently higher for the group treated with Lamotrigine Extended-Release Tablets compared with the placebo group. For example, 70% of patients randomized to Lamotrigine Extended-Release Tablets experienced a 50% or greater reduction in PGTC seizure frequency, compared with 32% of patients randomized to placebo. Patients with an increase in seizure frequency >100% are represented on the Y-axis as ≥-100%.
Figure 1. Proportion of Patients by Responder Rate for Lamotrigine Extended-Release Tablets and Placebo Group (Primary Generalized Tonic-Clonic Seizures Study) [Figure 1. Proportion of Patients by Responder Rate for Lamotrigine and Placebo Group (Primary Generalized Tonic-Clonic Seizures Study)]
14.2Adjunctive Therapy for Partial-Onset Seizures The effectiveness of immediate-release lamotrigine as adjunctive therapy was initially established in 3 pivotal, multicenter, placebo-controlled, double-blind clinical trials in 355 adults with refractory partial-onset seizures. The effectiveness of Lamotrigine Extended-Release Tablets as adjunctive therapy in partial-onset seizures, with or without secondary generalization, was established in a 19-week, multicenter, double-blind, placebo-controlled trial in 236 patients aged 13 years and older (approximately 93% of patients were aged 16 to 65 years).
Approximately 36% were from the U.S. and approximately 64% were from other countries including Argentina, Brazil, Chile, Germany, India, Korea, Russian Federation, and Ukraine. Patients with at least 8 partial-onset seizures during an 8-week prospective baseline phase (or 4-week prospective baseline coupled with a 4-week historical baseline documented with seizure diary data) were randomized to treatment with Lamotrigine Extended-Release Tablets (n = 116) or placebo (n = 120) added to their current regimen of 1 or 2 AEDs.
Approximately half of the patients were taking 2 concomitant AEDs at baseline. Target doses ranged from 200 to 500 mg/day of Lamotrigine Extended-Release Tablets based on conc… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of carcinogenicity was seen in mice or rats following oral administration of lamotrigine for up to 2 years at doses up to 30 mg/kg/day and 10 to 15 mg/kg/day, respectively. The highest doses tested are less than the human dose of 400 mg/day on a body surface area (mg/m 2) basis. Lamotrigine was negative in in vitro gene mutation (Ames and mouse lymphoma tk) assays and in clastogenicity (in vitro human lymphocyte and in vivo rat bone marrow) assays.
No evidence of impaired fertility was detected in rats given oral doses of lamotrigine up to 20 mg/kg/day. The highest dose tested is less than the human dose of 400 mg/day on a mg/m 2 basis.
📚 References ▾
1. French JA, Wang S, Warnock B, Temkin N. Historical control monotherapy design in the treatment of epilepsy. Epilepsia. 2010; 51(10):1936-1943.
📄 Package Label / Principal Display Panel ▾
72189-560-30
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |