
Dofetilide .125 mg Capsule, 40-count — NDC 72205-039-37 (Billing 72205-0039-37)
This is a package of 40 capsules of Dofetilide .125 mg Capsule from Novadoz Pharmaceuticals LLC, marketed since Jun 2020 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 044360
- GCN: 92287
- GPI-14 (Medi-Span): 35400025000110
- HICL (First Databank): 020864
- AHFS class code: 24:04.04.20
- RxCUI (RxNorm): 310003
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Antiarrhythmic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Dofetilide is a powerful heart medicine that, while it helps fix an abnormal rhythm, can — especially in the first few days — cause a dangerous heart rhythm problem called Torsade...
- Why do I have to go to the hospital just to start this medicine?
- The warning signs to take seriously are a sudden, very fast or wildly irregular heartbeat, feeling like you might faint, actually fainting, or your heart 'fluttering' in a new or a...
- How do I know if dofetilide is causing a problem with my heart rhythm?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Dofetilide — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.5827 | $23.31 / 40 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 72205-0039-37 You're viewing this | 4 BLISTER PACK in 1 CARTON / 10 CAPSULE in 1 BLISTER PACK | — | — | 2020-06-12 | — | Active |
| 72205-0039-60 72205-039-60 Main listing | 60 CAPSULE in 1 BOTTLE | $0.2026 / ea | $12.16 | 2020-06-12 | — | Active |
This pack shows little to no recent Medicaid volume — the 60 capsules pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72205-0039-60?
What NDC number is used to bill for this package of Dofetilide .125 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dofetilide .125 mg 00904-7522-08 | Major | 40 capsules | $0.203 | AB | Availability likely | — |
| Dofetilide 125 ug 42794-0044-10 | Sigmapharm | 60 capsules | $0.203 | AB | Availability likely | — |
| Dofetilide .125 mg 69452-0131-17 | Bionpharma | 60 capsules | $0.203 | AB | Availability likely | — |
| Dofetilide .125 mg 72603-0130-01 | NorthStar | 60 capsules | $0.203 | AB | Availability likely | — |
| Dofetilide .125 mg 75907-0056-60 | Dr. | 60 capsules | $0.203 | AB | Availability likely | — |
| Dofetilide .125 mg 76282-0755-60 | EXELAN | 60 capsules | $0.203 | AB | Availability likely | — |
| Dofetilide .125 mg 16729-0490-12 | Accord | 60 capsules | $0.205 | AB | Availability likely | — |
| Tikosyn .125 mg 00069-5800-43 | Pfizer | 40 capsules | — | AB | Discontinued | — |
| Dofetilide .125 mg 47335-0061-79 | Sun | 40 capsules | — | AB | FDA listed | — |
| Dofetilide .125 mg 59651-0118-05 | Aurobindo | 500 capsules | — | AB | FDA listed | — |
| Dofetilide 0.125mg .125 mg 70010-0024-06 | Granules | 60 capsules | — | AB | FDA listed | — |
| Dofetilide .125 mgthis 72205-0039-37 | Novadoz | 40 capsules | — | AB | FDA listed | — |
| Dofetilide .125 mg 70518-4738-00 | REMEDYREPACK | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING To minimize the risk of induced arrhythmia, patients initiated or re-initiated on dofetilide capsules should be placed for a minimum of 3 days in a facility that can provide calculations of creatinine clearance, continuous electrocardiographic monitoring, and cardiac resuscitation. For detailed instructions regarding dose selection, see DOSAGE AND ADMINISTRATION.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Maintenance of Normal Sinus Rhythm (Delay in AF/AFl Recurrence) Dofetilide capsules are indicated for the maintenance of normal sinus rhythm (delay in time to recurrence of atrial fibrillation/atrial flutter [AF/AFl]) in patients with atrial fibrillation/atrial flutter of greater than one week duration who have been converted to normal sinus rhythm. Because dofetilide capsules can cause life threatening ventricular arrhythmias, it should be reserved for patients in whom atrial fibrillation/atrial flutter is highly symptomatic.
In general, antiarrhythmic therapy for atrial fibrillation/atrial flutter aims to prolong the time in normal sinus rhythm. Recurrence is expected in some patients (see CLINICAL STUDIES ). Conversion of Atrial Fibrillation/Flutter Dofetilide capsules are indicated for the conversion of atrial fibrillation and atrial flutter to normal sinus rhythm.
Dofetilide capsules have not been shown to be effective in patients with paroxysmal atrial fibrillation.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Therapy with dofetilide capsules must be initiated (and, if necessary, re-initiated) in a setting that provides continuous electrocardiographic (ECG) monitoring and in the presence of personnel trained in the management of serious ventricular arrhythmias. Patients should continue to be monitored in this way for a minimum of three days. Additionally, patients should not be discharged within 12 hours of electrical or pharmacological conversion to normal sinus rhythm.
The dose of dofetilide capsules must be individualized according to calculated creatinine clearance and QTc. (QT interval should be used if the heart rate is <60 beats per minute. There are no data on use of dofetilide capsules when the heart rate is <50 beats per minute.) The usual recommended dose of dofetilide capsules are 500 mcg BID, as modified by the dosing algorithm described below.
For consideration of a lower dose, see Special Considerations below. Serum potassium should be maintained within the normal range before dofetilide capsules treatment is initiated and should be maintained within the normal range while the patient remains on dofetilide capsules therapy. (See WARNINGS, Hypokalemia and Potassium-Depleting Diuretics ).
In clinical trials, potassium levels were generally maintained above 3.6 to 4 mEq/L. Patients with atrial fibrillation should be anticoagulated according to usual medical practice prior to electrical or pharmacological cardioversion. Anticoagulant therapy may be continued after cardioversion according to usual medical practice for the treatment of people with AF.
Hypokalemia should be corrected before initiation of dofetilide capsules therapy (see WARNINGS, Ventricular Arrhythmia ). Patients to be discharged on dofetilide capsules therapy from an inpatient setting as described above must have an adequate supply of dofetilide capsules, at the patient’s individualized dose, to allow uninterrupted dosing until the patient can fill a dofetilide capsules prescription. Instructions for Individualized Dose Initiation Initiation of dofetilide capsules Therapy Step 1 .
Electrocardiographic assessment: Prior to administration of the first dose, the QTc or QT must be checked using an average of 5–10 beats. If the QTc or QT is greater than 440 msec (500 msec in patients with ventricular conduction abnormalities), dofetilide capsules are contraindicated. If heart rate is less than 60 beats per minute, QT interval should be used.
Proceed to Step 2 if the QTc or QT is 440 msec. Patients with heart rates <50 beats per minute have not been studied. Step 2 .
Calculation of creatinine clearance: Prior to the administration of the first dose, the patient’s creatinine clearance must be calculated using the following formula: creatinine clearance (male) = (140-age) x actual body weight in kg 72 x serum creatinine (mg/dL) creatinine clearance (female) = (140-age) x actual body weight in kg x 0.85 72 x serum creatinine (mg/dL) When serum creatinine is given in µmol/L, divide the value by 88.4 (1 mg/dL = 88.4 µmol/L). Step 3. Starting Dose: The starting dose of dofetilide capsules is determined as follows: Calculated Creatinine Clearance D ofetilide capsules Dose >60 mL/min 500 mcg twice daily 40 to 60 mL/min 250 mcg twice daily 20 to <40 mL/min 125 mcg twice daily <20 mL/min Dofetilide capsules are contraindicated in these patients Step 4.
Administer the adjusted dofetilide capsules dose and begin continuous ECG monitoring. Step 5. At 2–3 hours after administering the first dose of dofetilide capsules, determine the QTc or QT (if heart rate is less than 60 beats per minute).
If the QTc or QT has increased by greater than 15% compared to the baseline established in Step 1 OR if the QTc or QT is greater than 500 msec (550 msec in patients with ventricular conduction abnormalities), subsequent dosing should be adjusted as follows: If the Starting Dose Based on Then the Adjusted Dose Creatinine Clearance is: (for QTc or QT Prolongation)i… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Dofetilide is contraindicated in patients with congenital or acquired long QT syndromes. Dofetilide should not be used in patients with a baseline QT interval or QTc >440 msec (500 msec in patients with ventricular conduction abnormalities). Dofetilide is also contraindicated in patients with severe renal impairment (calculated creatinine clearance <20 mL/min).
The concomitant use of verapamil or the cation transport system inhibitors cimetidine, trimethoprim (alone or in combination with sulfamethoxazole), or ketoconazole with dofetilide is contraindicated (see WARNINGS and PRECAUTIONS, Drug-Drug Interactions ), as each of these drugs cause a substantial increase in dofetilide plasma concentrations. In addition, other known inhibitors of the renal cation transport system such as prochlorperazine, dolutegravir and megestrol should not be used in patients on dofetilide. The concomitant use of hydrochlorothiazide (alone or in combinations such as with triamterene) with dofetilide is contraindicated (see PRECAUTIONS, Drug-Drug Interactions ) because this has been shown to significantly increase dofetilide plasma concentrations and QT interval prolongation.
Dofetilide is also contraindicated in patients with a known hypersensitivity to the drug.
⚠️ Warnings ▾
WARNINGS Ventricular Arrhythmia: Dofetilide can cause serious ventricular arrhythmias, primarily Torsade de Pointes (TdP) type ventricular tachycardia, a polymorphic ventricular tachycardia associated with QT interval prolongation. QT interval prolongation is directly related to dofetilide plasma concentration. Factors such as reduced creatinine clearance or certain dofetilide drug interactions will increase dofetilide plasma concentration.
The risk of TdP can be reduced by controlling the plasma concentration through adjustment of the initial dofetilide dose according to creatinine clearance and by monitoring the ECG for excessive increases in the QT interval. Treatment with dofetilide must therefore be started only in patients placed for a minimum of three days in a facility that can provide electrocardiographic monitoring and in the presence of personnel trained in the management of serious ventricular arrhythmias. Calculation of the creatinine clearance for all patients must precede administration of the first dose of dofetilide.
For detailed instructions regarding dose selection, see DOSAGE AND ADMINISTRATION. The risk of dofetilide induced ventricular arrhythmia was assessed in three ways in clinical studies: 1) by description of the QT interval and its relation to the dose and plasma concentration of dofetilide; 2) by observing the frequency of TdP in dofetilide-treated patients according to dose; 3) by observing the overall mortality rate in patients with atrial fibrillation and in patients with structural heart disease. Relation of QT Interval to Dose: The QT interval increases linearly with increasing dofetilide dose (see Figures 1 and 2 in CLINICAL PHARMACOLOGY and Dose-Response and Concentration Response for Increase in QT Interval ).
Frequency of Torsade de Pointes: In the supraventricular arrhythmia population (patients with AF and other supraventricular arrhythmias), the overall incidence of Torsade de Pointes was 0.8%. The frequency of TdP by dose is shown in Table 4. There were no cases of TdP on placebo.
Table 4: Summary of Torsade de Pointes in Patients Randomized to Dofetilide by Dose; Patients with Supraventricular Arrhythmias Dofetilide Dose <250 mcg BID 250 mcg BID >250–500 mcg BID >500 mcg BID All Doses Number of Patients 217 388 703 38 1346 Torsade de Pointes 0 1 (0.3%) 6 (0.9%) 4 (10.5%) 11 (0.8%) As shown in Table 5, the rate of TdP was reduced when patients were dosed according to their renal function (see CLINICAL PHARMACOLOGY, Pharmacokinetics in Special Populations, Renal Impairment and DOSAGE AND ADMINISTRATION ).
Table 5: Incidence of Torsade de Pointes Before and After Introduction of Dosing According to Renal Function Population: Total Before After n/N % n/N % n/N % Supraventricular Arrhythmias 11/1346 (0.8%) 6/193 (3.1%) 5/1153 (0.4%) DIAMOND CHF 25/762 (3.3%) 7/148 (4.7%) 18/614 (2.9%) DIAMOND MI 7/749 (0.9%) 3/101 (3.0%) 4/648 (0.6%) DIAMOND AF 4/249 (1.6%) 0/43 (0%) 4/206 (1.9%) The majority of the episodes of TdP occurred within the first three days of dofetilide therapy (10/11 events in the studies of patients with supraventricular arrhythmias; 19/25 and 4/7 events in DIAMOND CHF and DIAMOND MI, respectively; 2/4 events in the DIAMOND AF subpopulation).
Mortality: In a pooled survival analysis of patients in the supraventricular arrhythmia population (low prevalence of structural heart disease), deaths occurred in 0.9% (12/1346) of patients receiving dofetilide and 0.4% (3/677) in the placebo group. Adjusted for duration of therapy, primary diagnosis, age, gender, and prevalence of structural heart disease, the point estimate of the hazard ratio for the pooled studies (dofetilide/placebo) was 1.1 (95% CI: 0.3, 4.3). The DIAMOND CHF and MI trials examined mortality in patients with structural heart disease (ejection fraction ≤35%).
In these large, double-blind studies, deaths occurred in 36% (541/1511) of dofetilide patients and 37% (560/1517) of placebo patients. In an analysis of 506 D… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The dofetilide clinical program involved approximately 8,600 patients in 130 clinical studies of normal volunteers and patients with supraventricular and ventricular arrhythmias. Dofetilide was administered to 5,194 patients, including two large, placebo-controlled mortality trials (DIAMOND CHF and DIAMOND MI) in which 1,511 patients received dofetilide for up to three years. In the following section, adverse reaction data for cardiac arrhythmias and non-cardiac adverse reactions are presented separately for patients included in the supraventricular arrhythmia development program and for patients included in the DIAMOND CHF and MI mortality trials (see CLINICAL STUDIES, Safety in Patients with Structural Heart Disease, DIAMOND Studies, for a description of these trials).
In studies of patients with supraventricular arrhythmias, a total of 1,346 and 677 patients were exposed to dofetilide and placebo for 551 and 207 patient years, respectively. A total of 8.7% of patients in the dofetilide groups were discontinued from clinical trials due to adverse events compared to 8.0% in the placebo groups. The most frequent reason for discontinuation (>1%) was ventricular tachycardia (2.0% on dofetilide vs.
1.3% on placebo). The most frequent adverse events were headache, chest pain, and dizziness. Serious Arrhythmias and Conduction Disturbances: Torsade de Pointes is the only arrhythmia that showed a dose-response relationship to dofetilide treatment.
It did not occur in placebo treated patients. The incidence of Torsade de Pointes in patients with supraventricular arrhythmias was 0.8% (11/1346) (see WARNINGS ). The incidence of Torsade de Pointes in patients who were dosed according to the recommended dosing regimen (see DOSAGE AND ADMINISTRATION ) was 0.8% (4/525).
Table 6 shows the frequency by randomized dose of serious arrhythmias and conduction disturbances reported as adverse events in patients with supraventricular arrhythmias. Table 6: Incidence of Serious Arrhythmias and Conduction Disturbances in Patients with Supraventricular Arrhythmias Dofetilide Dose Placebo Arrhythmia event: <250 mcg BID N=217 250 mcg BID N=388 >250–500 mcg BID N=703 >500 mcg BID N=38 N=677 Ventricular arrhythmias* ^ 3.7% 2.6% 3.4% 15.8% 2.7% Ventricular fibrillation 0 0.3% 0.4% 2.6% 0.1% Ventricular tachycardia^ 3.7% 2.6% 3.3% 13.2% 2.5% Torsade de Pointes 0 0.3% 0.9% 10.5% 0 Various forms of block AV block 0.9% 1.5% 0.4% 0 0.3% Bundle branch block 0 0.5% 0.1% 0 0.1% Heart block 0 0.5% 0.1% 0 0.1% * Patients with more than one arrhythmia are counted only once in this category. ^ Ventricular arrhythmias and ventricular tachycardia include all cases of Torsade de Pointes.
In the DIAMOND trials, a total of 1,511 patients were exposed to dofetilide for 1757 patient years. The incidence of Torsade de Pointes was 3.3% in CHF patients and 0.9% in patients with a recent MI. Table 7 shows the incidence of serious arrhythmias and conduction disturbances reported as adverse events in the DIAMOND subpopulation that had AF at entry to these trials.
Table 7: Incidence of Serious Arrhythmias and Conduction Disturbances in Patients with AF at Entry to the DIAMOND Studies Dofetilide Placebo N=249 N=257 Ventricular arrhythmias* ^ 14.5% 13.6% Ventricular fibrillation 4.8% 3.1% Ventricular tachycardia^ 12.4% 11.3% Torsade de Pointes 1.6% 0 Various forms of block AV block 0.8% 2.7% (Left) bundle branch block 0 0.4% Heart block 1.2% 0.8% * Patients with more than one arrhythmia are counted only once in this category. ^ Ventricular arrhythmias and ventricular tachycardia include all cases of Torsade de Pointes.
Other Adverse Reactions: Table 8 presents other adverse events reported with a frequency of >2% on dofetilide and reported numerically more frequently on dofetilide than on placebo in the studies of patients with supraventricular arrhythmias. Table 8: Frequency of Adverse Events Occurring at >2% on Dofetilide, and Numerically More Frequently on Dofetil… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug-Drug Interactions Cimetidine: (see WARNINGS, CONTRAINDICATIONS ) Concomitant use of cimetidine is contraindicated. Cimetidine at 400 mg BID (the usual prescription dose) co-administered with dofetilide (500 mcg BID) for 7 days has been shown to increase dofetilide plasma levels by 58%. Cimetidine at doses of 100 mg BID (OTC dose) resulted in a 13% increase in dofetilide plasma levels (500 mcg single dose).
No studies have been conducted at intermediate doses of cimetidine. If a patient requires dofetilide and anti-ulcer therapy, it is suggested that omeprazole, ranitidine, or antacids (aluminum and magnesium hydroxides) be used as alternatives to cimetidine, as these agents have no effect on the pharmacokinetic profile of dofetilide. Verapamil: (see CONTRAINDICATIONS ) Concomitant use of verapamil is contraindicated.
Co-administration of dofetilide with verapamil resulted in increases in dofetilide peak plasma levels of 42%, although overall exposure to dofetilide was not significantly increased. In an analysis of the supraventricular arrhythmia and DIAMOND patient populations, the concomitant administration of verapamil with dofetilide was associated with a higher occurrence of Torsade de Pointes. Ketoconazole: (see WARNINGS, CONTRAINDICATIONS ) Concomitant use of ketoconazole is contraindicated.
Ketoconazole at 400 mg daily (the maximum approved prescription dose) co-administered with dofetilide (500 mcg BID) for 7 days has been shown to increase dofetilide C max by 53% in males and 97% in females, and AUC by 41% in males and 69% in females. Trimethoprim Alone or in Combination with Sulfamethoxazole: (see WARNINGS, CONTRAINDICATIONS ) Concomitant use of trimethoprim alone or in combination with sulfamethoxazole is contraindicated. Trimethoprim 160 mg in combination with 800 mg sulfamethoxazole co-administered BID with dofetilide (500 mcg BID) for 4 days has been shown to increase dofetilide AUC by 103% and C max by 93%.
Hydrochlorothiazide (HCTZ) Alone or in Combination with Triamterene: (see CONTRAINDICATIONS ) Concomitant use of HCTZ alone or in combination with triamterene is contraindicated. HCTZ 50 mg QD or HCTZ/triamterene 50/100 mg QD was co-administered with dofetilide (500 mcg BID) for 5 days (following 2 days of diuretic use at half dose). In patients receiving HCTZ alone, dofetilide AUC increased by 27% and C max by 21%.
However, the pharmacodynamic effect increased by 197% (QTc increase over time) and by 95% (maximum QTc increase). In patients receiving HCTZ in combination with triamterene, dofetilide AUC increased by 30% and C max by 16%. However, the pharmacodynamic effect increased by 190% (QTc increase over time) and by 84% (maximum QTc increase).
The pharmacodynamic effects can be explained by a combination of the increase in dofetilide exposure and the reductions in serum potassium. In the DIAMOND trials, 1252 patients were treated with dofetilide and diuretics concomitantly, of whom 493 died compared to 508 deaths among the 1248 patients receiving placebo and diuretics. Of the 229 patients who had potassium depleting diuretics added to their concomitant medications in the DIAMOND trials, the patients on dofetilide had a non-significantly reduced relative risk for death of 0.68 (95% CI: 0.376, 1.230).
Potential Drug Interactions Dofetilide is eliminated in the kidney by cationic secretion. Inhibitors of renal cationic secretion are contraindicated with dofetilide. In addition, drugs that are actively secreted via this route (e.g., triamterene, metformin, and amiloride) should be co-administered with care as they might increase dofetilide levels.
Dofetilide is metabolized to a small extent by the CYP3A4 isoenzyme of the cytochrome P450 system. Inhibitors of the CYP3A4 isoenzyme could increase systemic dofetilide exposure. Inhibitors of this isoenzyme (e.g., macrolide antibiotics, azole antifungal agents, protease inhibitors, serotonin reuptake inhibitors, amiodarone, cannabinoids, diltiazem, grapefruit… [Excerpted — this section continues on DailyMed.]
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions None known.
🤰 Pregnancy ▾
Pregnancy Dofetilide has been shown to adversely affect in utero growth and survival of rats and mice when orally administered during organogenesis at doses of 2 or more mg/kg/day. Other than an increased incidence of non-ossified 5 th metacarpal, and the occurrence of hydroureter and hydronephroses at doses as low as 1 mg/kg/day in the rat, structural anomalies associated with drug treatment were not observed in either species at doses below 2 mg/kg/day. The clearest drug-effect associations were for sternebral and vertebral anomalies in both species; cleft palate, adactyly, levocardia, dilation of cerebral ventricles, hydroureter, hydronephroses, and unossified metacarpal in the rat; and increased incidence of unossified calcaneum in the mouse.
The “no observed adverse effect dose” in both species was 0.5 mg/kg/day. The mean dofetilide AUCs (0–24hr) at this dose in the rat and mouse are estimated to be about equal to the maximum likely human AUC and about half the likely human AUC, respectively. There are no adequate and well controlled studies in pregnant women.
Therefore, dofetilide should only be administered to pregnant women where the benefit to the patient justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of dofetilide in children (<18 years old) has not been established.
🧓 Geriatric Use ▾
Geriatric Use Of the total number of patients in clinical studies of dofetilide, 46% were 65 to 89 years old. No overall differences in safety, effect on QTc, or effectiveness were observed between elderly and younger patients. Because elderly patients are more likely to have decreased renal function with a reduced creatinine clearance, care must be taken in dose selection (see DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE There is no known antidote to dofetilide; treatment of overdose should therefore be symptomatic and supportive. The most prominent manifestation of overdosage is likely to be excessive prolongation of the QT interval. In cases of overdose, cardiac monitoring should be initiated.
Charcoal slurry may be given soon after overdosing but has been useful only when given within 15 minutes of dofetilide administration. Treatment of Torsade de Pointes or overdose may include administration of isoproterenol infusion, with or without cardiac pacing. Administration of intravenous magnesium sulfate may be effective in the management of Torsade de Pointes.
Close medical monitoring and supervision should continue until the QT interval returns to normal levels. Isoproterenol infusion into anesthetized dogs with cardiac pacing rapidly attenuates the dofetilide-induced prolongation of atrial and ventricular effective refractory periods in a dose- dependent manner. Magnesium sulfate, administered prophylactically either intravenously or orally in a dog model, was effective in the prevention of dofetilide-induced Torsade de Pointes ventricular tachycardia.
Similarly, in man, intravenous magnesium sulfate may terminate Torsade de Pointes, irrespective of cause. Dofetilide overdose was rare in clinical studies; there were two reported cases of dofetilide overdose in the oral clinical program. One patient received very high multiples of the recommended dose (28 capsules), was treated with gastric aspiration 30 minutes later, and experienced no events.
One patient inadvertently received two 500 mcg doses one hour apart and experienced ventricular fibrillation and cardiac arrest 2 hours after the second dose. In the supraventricular arrhythmia population, only 38 patients received doses greater than 500 mcg BID, all of whom received 750 mcg BID irrespective of creatinine clearance. In this very small patient population, the incidence of Torsade de Pointes was 10.5% (4/38 patients), and the incidence of new ventricular fibrillation was 2.6% (1/38 patients).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Dofetilide shows Vaughan Williams Class III antiarrhythmic activity. The mechanism of action is blockade of the cardiac ion channel carrying the rapid component of the delayed rectifier potassium current, I Kr . At concentrations covering several orders of magnitude, dofetilide blocks only I Kr with no relevant block of the other repolarizing potassium currents (e.g., I Ks , I K1 ).
At clinically relevant concentrations, dofetilide has no effect on sodium channels (associated with Class I effect), adrenergic alpha-receptors, or adrenergic beta-receptors. Electrophysiology Dofetilide increases the monophasic action potential duration in a predictable, concentration-dependent manner, primarily due to delayed repolarization. This effect, and the related increase in effective refractory period, is observed in the atria and ventricles in both resting and paced electrophysiology studies.
The increase in QT interval observed on the surface ECG is a result of prolongation of both effective and functional refractory periods in the His-Purkinje system and the ventricles. Dofetilide did not influence cardiac conduction velocity and sinus node function in a variety of studies in patients with or without structural heart disease. This is consistent with a lack of effect of dofetilide on the PR interval and QRS width in patients with pre-existing heart block and/or sick sinus syndrome.
In patients, dofetilide terminates induced re-entrant tachyarrhythmias (e.g., atrial fibrillation/flutter and ventricular tachycardia) and prevents their re-induction. Dofetilide does not increase the electrical energy required to convert electrically induced ventricular fibrillation, and it significantly reduces the defibrillation threshold in patients with ventricular tachycardia and ventricular fibrillation undergoing implantation of a cardioverter-defibrillator device. Hemodynamic Effects In hemodynamic studies, dofetilide had no effect on cardiac output, cardiac index, stroke volume index, or systemic vascular resistance in patients with ventricular tachycardia, mild to moderate congestive heart failure or angina, and either normal or low left ventricular ejection fraction.
There was no evidence of a negative inotropic effect related to dofetilide therapy in patients with atrial fibrillation. There was no increase in heart failure in patients with significant left ventricular dysfunction (see CLINICAL STUDIES, Safety in Patients with Structural Heart Disease, DIAMOND Studies ). In the overall clinical program, dofetilide did not affect blood pressure.
Heart rate was decreased by 4–6 bpm in studies in patients. Pharmacokinetics, General Absorption and Distribution: The oral bioavailability of dofetilide is >90%, with maximal plasma concentrations occurring at about 2-3 hours in the fasted state. Oral bioavailability is unaffected by food or antacid.
The terminal half-life of dofetilide is approximately 10 hours; steady state plasma concentrations are attained within 2–3 days, with an accumulation index of 1.5 to 2.0. Plasma concentrations are dose proportional. Plasma protein binding of dofetilide is 60–70%, is independent of plasma concentration, and is unaffected by renal impairment.
Volume of distribution is 3 L/kg. Metabolism and Excretion: Approximately 80% of a single dose of dofetilide is excreted in urine, of which approximately 80% is excreted as unchanged dofetilide with the remaining 20% consisting of inactive or minimally active metabolites. Renal elimination involves both glomerular filtration and active tubular secretion (via the cation transport system, a process that can be inhibited by cimetidine, trimethoprim, prochlorperazine, megestrol, ketoconazole and dolutegravir).
In vitro studies with human liver microsomes show that dofetilide can be metabolized by CYP3A4, but it has a low affinity for this isoenzyme. Metabolites are formed by N-dealkylation and N-oxidation. There are no quantifiable meta… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Dofetilide 125 mcg (0.125 mg) capsules are supplied as Size “4” hard gelatin capsules with white opaque body imprinted with “1” with black color band and light orange opaque cap imprinted with “MD” in black ink are available in: Dofetilide 250 mcg (0.25 mg) capsules are supplied as Size “4” hard gelatin capsules with peach opaque body imprinted with “2” with black color band and peach opaque cap imprinted with “MD” in black ink are available in: Dofetilide 500 mcg (0.5 mg) capsules are supplied as Size “2” hard gelatin capsules with white opaque body imprinted with “3” with black color band and peach opaque cap imprinted with “MD” in black ink are available in: 125 mcg (0.125 mg) 250 mcg (0.25 mg) 500 mcg (0.5 mg) Body 1 2 3 Cap MD MD MD Bottle of 60 72205-039-60 72205-040-60 72205-041-60 Unit dose/40 72205-039-37 72205-040-37 72205-041-37 Store at 15° to 30° C (59° to 86° F) [see USP Controlled Room Temperature].
PROTECT FROM MOISTURE AND HUMIDITY. Dispense in tight (USP), child-resistant containers. Rx only Manufactured by: MSN Laboratories Private Limited Telangana – 509 228, INDIA Distributed by: Novadoz Pharmaceuticals LLC Piscataway, NJ 08854-3714 Issued on: February 2020
📋 Description ▾
DESCRIPTION Dofetilide capsules are an antiarrhythmic drug with Class III (cardiac action potential duration prolonging) properties. Its molecular formula is C 19 H 27 N 3 O 5 S 2 and it has a molecular weight of 441.6. The structural formula is The chemical name for dofetilide is: N-[4-[2-[methyl[2-[4-[(methylsulfonyl)amino]phenoxy]ethyl]amino]ethyl]phenyl]- methanesulfonamide. Dofetilide USP is a white to off-white powder. It is soluble in
1.0N sodium hydroxide, acetone, 0.1N hydrochloric acid, very slightly soluble in isopropyl alcohol and insoluble in water. Dofetilide capsules contain the following inactive ingredients: magnesium stearate, pregelatinized starch, silicified microcrystalline cellulose.The capsule shell contains titanium dioxide, FD&C yellow 6 and gelatin, additionally 125 mcg capsule shell contains D&C yellow 10 and FD&C red 40. The printing ink contains shellac, iron oxide black, propylene glycol and potassium hydroxide.
Dofetilide capsules are supplied for oral administration in three dosage strengths: 125 mcg (0.125 mg) light orange and white capsules, 250 mcg (0.25 mg) peach capsules, and 500 mcg (0.5 mg) peach and white capsules. struct
💬 Information for Patients ▾
Information for Patients Please refer patient to the Medication Guide. Prior to initiation of dofetilide therapy, the patient should be advised to read the Medication Guide and reread it each time therapy is renewed in case the patient’s status has changed. The patient should be fully instructed on the need for compliance with the recommended dosing of dofetilide and the potential for drug interactions, and the need for periodic monitoring of QTc and renal function to minimize the risk of serious abnormal rhythms.
Medications and Supplements: Assessment of patients’ medication history should include all over-the-counter, prescription, and herbal/natural preparations with emphasis on preparations that may affect the pharmacokinetics of dofetilide such as cimetidine (see CONTRAINDICATIONS ), trimethoprim alone or in combination with sulfamethoxazole (see WARNINGS, CONTRAINDICATIONS ), prochlorperazine (see WARNINGS, CONTRAINDICATIONS ), megestrol (see WARNINGS, CONTRAINDICATIONS ), ketoconazole (see WARNINGS, CONTRAINDICATIONS ), dolutegravir (see CONTRAINDICATIONS ), hydrochlorothiazide (alone or in combinations such as with triamterene) (see CONTRAINDICATIONS ), other cardiovascular drugs (especially verapamil – see CONTRAINDICATIONS ), phenothiazines, and tricyclic antidepressants (see WARNINGS ).If a patient is taking dofetilide and requires anti-ulcer therapy, omeprazole, ranitidine, or antacids (aluminum and magnesium hydroxides) should be used as alternatives to cimetidine, as these agents have no effect on the pharmacokinetics of dofetilide.
Patients should be instructed to notify their health care providers of any change in over-the-counter, prescription, or supplement use. If a patient is hospitalized or is prescribed a new medication for any condition, the patient must inform the health care provider of ongoing dofetilide therapy. Patients should also check with their health care provider and/or pharmacist prior to taking a new over-the counter preparation.
Electrolyte Imbalance: If patients experience symptoms that may be associated with altered electrolyte balance, such as excessive or prolonged diarrhea, sweating, or vomiting or loss of appetite or thirst, these conditions should immediately be reported to their health care provider. Dosing Schedule: Patients should be instructed NOT to double the next dose if a dose is missed. The next dose should be taken at the usual time.
💬 Medication Guide ▾
MEDICATION GUIDE Dofetilide (doe fet’ i lide) Capsules Read the Medication Guide before you start taking dofetilide capsules and each time you get a refill. This information does not take the place of talking with your doctor about your condition or treatment. What is the most important information I should know about dofetilide capsules?
Dofetilide capsules can cause serious side effects, including a type of abnormal heartbeat called Torsade de Pointes, which can lead to death. To establish the right dose of dofetilide capsules, treatment with dofetilide capsules must be started in a hospital where your heart rate and kidney function will be checked for the first 3 days of treatment. It is important that when you go home, you take the exact dose of dofetilide capsules that your doctor prescribed for you.
While you take dofetilide capsules, always watch for signs of abnormal heartbeat. Call your doctor and go to the hospital right away if you: feel faint become dizzy, or have a fast heartbeat What are dofetilide capsules? Dofetilide capsules are prescription medicine that is used to treat an irregular heartbeat (atrial fibrillation or atrial flutter).
It is not known if dofetilide capsules are safe and effective in children under 18 years of age. Who should not take dofetilide capsules ? Do not take dofetilide capsules if you: have an irregular heartbeat called long QT syndrome have kidney problems or are on kidney dialysis take any of these medicines: cimetidine (TAGAMET, TAGAMET HB)* verapamil (CALAN, CALAN SR, COVERA-HS, ISOPTIN, ISOPTIN SR, VERELAN, VERELAN PM, TARKA)* ketoconazole (NIZORAL, XOLEGEL, EXTINA)* trimethoprim alone (PROLOPRIM, TRIMPEX)* or the combination of trimethoprim and sulfamethoxazole (BACTRIM, SEPTRA SULFATRIM)* prochlorperazine (COMPAZINE, COMPO)* megestrol (MEGACE)* dolutegravir (TIVICAY)* hydrochlorothiazide alone or in combination with other medicines (such as ESIDRIX, EZIDE, HYDRODIURIL, HYDRO-PAR, MICROZIDE, or ORETIC)* Ask your doctor if you are not sure if any of your medicines are the kind listed above. are allergic to dofetilide in dofetilide capsules.
See the end of this leaflet for a complete list of ingredients in dofetilide capsules. What should I tell my doctor before taking dofetilide capsules? Before taking dofetilide capsules, tell your doctor about all of your medical conditions including if you: have heart problems have kidney or liver problems are pregnant or plan to become pregnant.
It is not known if dofetilide capsules will harm your unborn baby. are breast-feeding or plan to breast-feed. It is not known if dofetilide passes into your breast milk. You and your doctor should decide if you will take dofetilide capsules or breast-feed.
You should not do both. Especially tell your doctor if you take medicines to treat: heart problems high blood pressure depression or other mental problems asthma allergies, or hay fever skin problems infections Ask your doctor if you are not sure about the medicines you take. Tell your doctor about all prescription and non-prescription medicines, vitamins, dietary supplements, and any natural or herbal remedies.
Dofetilide capsules and other medicines may affect each other, causing serious side effects. If you take dofetilide capsules with certain medicines, you will be more likely to have a different type of abnormal heartbeat. See “Who should not take dofetilide capsules?” Know the medicines you take.
Keep a list of your medicines and show it to your doctor and pharmacist when you get a new medicine. How should I take dofetilide capsules? Take dofetilide capsules exactly as your doctor tells you.
Do not change your dofetilide capsules dose unless your doctor tells you to. Your doctor will do tests before you start and while you take dofetilide capsules. Do not stop taking dofetilide capsules until your doctor tells you to stop.
If you miss a dose, just take the next dose at your regular time. Do not take 2 doses of dofetilide capsules at the same t… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS Renal Impairment The overall systemic clearance of dofetilide is decreased and plasma concentration increased with decreasing creatinine clearance. The dose of dofetilide must be adjusted based on creatinine clearance (see DOSAGE AND ADMINISTRATION ). Patients undergoing dialysis were not included in clinical studies, and appropriate dosing recommendations for these patients are unknown.
There is no information about the effectiveness of hemodialysis in removing dofetilide from plasma. Hepatic Impairment After adjustment for creatinine clearance, no additional dose adjustment is required for patients with mild or moderate hepatic impairment. Patients with severe hepatic impairment have not been studied.
Dofetilide should be used with particular caution in these patients. Cardiac Conduction Disturbances Animal and human studies have not shown any adverse effects of dofetilide on conduction velocity. No effect on AV nodal conduction following dofetilide treatment was noted in normal volunteers and in patients with 1 st degree heart block.
Patients with sick sinus syndrome or with 2 nd or 3 rd degree heart block were not included in the Phase 3 clinical trials unless a functioning pacemaker was present. Dofetilide has been used safely in conjunction with pacemakers (53 patients in DIAMOND studies, 136 in trials in patients with ventricular and supraventricular arrhythmias). Information for Patients Please refer patient to the Medication Guide.
Prior to initiation of dofetilide therapy, the patient should be advised to read the Medication Guide and reread it each time therapy is renewed in case the patient’s status has changed. The patient should be fully instructed on the need for compliance with the recommended dosing of dofetilide and the potential for drug interactions, and the need for periodic monitoring of QTc and renal function to minimize the risk of serious abnormal rhythms. Medications and Supplements: Assessment of patients’ medication history should include all over-the-counter, prescription, and herbal/natural preparations with emphasis on preparations that may affect the pharmacokinetics of dofetilide such as cimetidine (see CONTRAINDICATIONS ), trimethoprim alone or in combination with sulfamethoxazole (see WARNINGS, CONTRAINDICATIONS ), prochlorperazine (see WARNINGS, CONTRAINDICATIONS ), megestrol (see WARNINGS, CONTRAINDICATIONS ), ketoconazole (see WARNINGS, CONTRAINDICATIONS ), dolutegravir (see CONTRAINDICATIONS ), hydrochlorothiazide (alone or in combinations such as with triamterene) (see CONTRAINDICATIONS ), other cardiovascular drugs (especially verapamil – see CONTRAINDICATIONS ), phenothiazines, and tricyclic antidepressants (see WARNINGS ).If a patient is taking dofetilide and requires anti-ulcer therapy, omeprazole, ranitidine, or antacids (aluminum and magnesium hydroxides) should be used as alternatives to cimetidine, as these agents have no effect on the pharmacokinetics of dofetilide.
Patients should be instructed to notify their health care providers of any change in over-the-counter, prescription, or supplement use. If a patient is hospitalized or is prescribed a new medication for any condition, the patient must inform the health care provider of ongoing dofetilide therapy. Patients should also check with their health care provider and/or pharmacist prior to taking a new over-the counter preparation.
Electrolyte Imbalance: If patients experience symptoms that may be associated with altered electrolyte balance, such as excessive or prolonged diarrhea, sweating, or vomiting or loss of appetite or thirst, these conditions should immediately be reported to their health care provider. Dosing Schedule: Patients should be instructed NOT to double the next dose if a dose is missed. The next dose should be taken at the usual time.
Drug/Laboratory Test Interactions None known. Drug-Drug Interactions Cimetidine: (see WARNINGS, CONTRAINDICATIONS ) Concomitant use of cimetidine is contraindicat… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers There is no information on the presence of dofetilide in breast milk. Patients should be advised not to breast-feed an infant if they are taking dofetilide.
🔬 Clinical Studies ▾
CLINICAL STUDIES Chronic Atrial Fibrillation and/or Atrial Flutter Two randomized, parallel, double-blind, placebo-controlled, dose-response trials evaluated the ability of dofetilide 1) to convert patients with atrial fibrillation or atrial flutter (AF/AFl) of more than 1 week duration to normal sinus rhythm (NSR) and 2) to maintain NSR (delay time to recurrence of AF/AFl) after drug-induced or electrical cardioversion. A total of 996 patients with a one week to two year history of atrial fibrillation/atrial flutter were enrolled.
Both studies randomized patients to placebo or to doses of dofetilide 125 mcg, 250 mcg, 500 mcg, or in one study a comparator drug, given twice a day (these doses were lowered based on calculated creatinine clearance and, in one of the studies, for QT interval or QTc). All patients were started on therapy in a hospital where their ECG was monitored (see DOSAGE AND ADMINISTRATION). Patients were excluded from participation if they had syncope within the past 6 months, AV block greater than first degree, MI or unstable angina within 1 month, cardiac surgery within 2 months, history of QT interval prolongation or polymorphic ventricular tachycardia associated with use of antiarrhythmic drugs, QT interval or QTc >440 msec, serum creatinine >2.5 mg/mL, significant diseases of other organ systems; used cimetidine; or used drugs known to prolong the QT interval.
Both studies enrolled mostly Caucasians (over 90%), males (over 70%), and patients ≥65 years of age (over 50%). Most (>90%) were NYHA Functional Class I or II. Approximately one-half had structural heart disease (including ischemic heart disease, cardiomyopathies, and valvular disease) and about one-half were hypertensive.
A substantial proportion of patients were on concomitant therapy, including digoxin (over 60%), diuretics (over 20%), and ACE inhibitors (over 30%). About 90% were on anticoagulants. Acute conversion rates are shown in Table 1 for randomized doses (doses were adjusted for calculated creatinine clearance and, in Study 1, for QT interval or QTc).
Of patients who converted pharmacologically, approximately 70% converted within 24–36 hours. Table 1: Conversion of Atrial Fibrillation/Flutter to Normal Sinus Rhythm DofetilideDose Placebo 125 mcg BID 250 mcg BID 500 mcg BID Study 1 5/82(6%) 8/82(10%) 23/77(30%) 1/84(1%) Study 2 8/135(6%) 14/133(11%) 38/129(29%) 2/137(1%) Patients who did not convert to NSR with randomized therapy within 48-72 hours had electrical cardioversion. Those patients remaining in NSR after conversion in hospital were continued on randomized therapy as outpatients (maintenance period) for up to one year unless they experienced a recurrence of atrial fibrillation/atrial flutter or withdrew for other reasons.
Table 2 shows, by randomized dose, the percentage of patients at 6 and 12 months in both studies who remained on treatment in NSR and the percentage of patients who withdrew because of recurrence of AF/AFl or adverse events. Table 2: Patient Status at 6 and 12 Months Post Randomization Dofetilide Dose Placebo 125 mcg BID 250 mcg BID 500 mcg BID Study 1 Randomized 82 82 77 84 Achieved NSR 60 61 61 68 6 months Still on treatment in NSR 38% 44% 52% 32% D/C for recurrence 55% 49% 33% 63% D/C for AEs 3% 3% 8% 4% 12 months Still on treatment in NSR 32% 26% 46% 22% D/C for recurrence 58% 57% 36% 72% D/C for AEs 7% 11% 8% 6% Study 2 Randomized 135 133 129 137 Achieved NSR 103 118 100 106 6 months Still on treatment in NSR 41% 49% 57% 22% D/C for recurrence 48% 42% 27% 72% D/C for AEs 9% 6% 10% 4% 12 months Still on treatment in NSR 25% 42% 49% 16% D/C for recurrence 59% 47% 32% 76% D/C for AEs 11% 6% 12% 5% Note that columns do not add up to 100% due to discontinuations for “other” reasons.
Table 3 and Figures 3 and 4 show, by randomized dose, the effectiveness of dofetilide in maintaining NSR using Kaplan Meier analysis, which shows patients remaining on treatment. Table 3: P-Values and Median Time (days) to Recurren… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Dofetilide had no genotoxic effects, with or without metabolic activation, based on the bacterial mutation assay and tests of cytogenetic aberrations in vivo in mouse bone marrow and in vitro in human lymphocytes. Rats and mice treated with dofetilide in the diet for two years showed no evidence of an increased incidence of tumors compared to controls. The highest dofetilide dose administered for 24 months was 10 mg/kg/day to rats and 20 mg/kg/day to mice.
Mean dofetilide AUCs (0–24hr) at these doses were about 26 and 10 times, respectively, the maximum likely human AUC. There was no effect on mating or fertility when dofetilide was administered to male and female rats at doses as high as 1.0 mg/kg/day, a dose that would be expected to provide a mean dofetilide AUC (0–24hr) about 3 times the maximum likely human AUC. Increased incidences of testicular atrophy and epididymal oligospermia and a reduction in testicular weight were, however, observed in other studies in rats.
Reduced testicular weight and increased incidence of testicular atrophy were also consistent findings in dogs and mice. The no effect doses for these findings in chronic administration studies in these 3 species (3, 0.1, and 6 mg/kg/day) were associated with mean dofetilide AUCs that were about 4, 1.3, and 3 times the maximum likely human AUC, respectively.
📄 Package Label / Principal Display Panel ▾
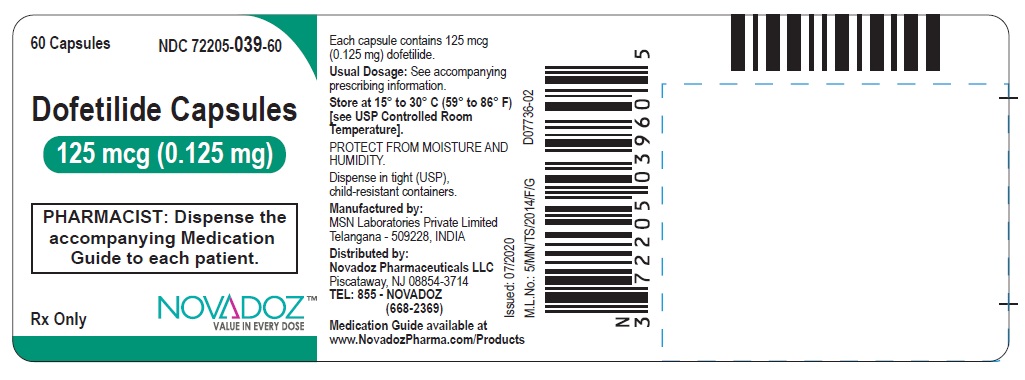
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Dofetilide-125mcg-60s-container-label: Dofetilide-250mcg-60s-container-label: Dofetilide-500mcg-60s-container-label: dofetilide-125mcg-60s-cntr-label dofetilide-250mcg-60s-cntr-label dofetilide-500mcg-60s-cntr-label
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |