
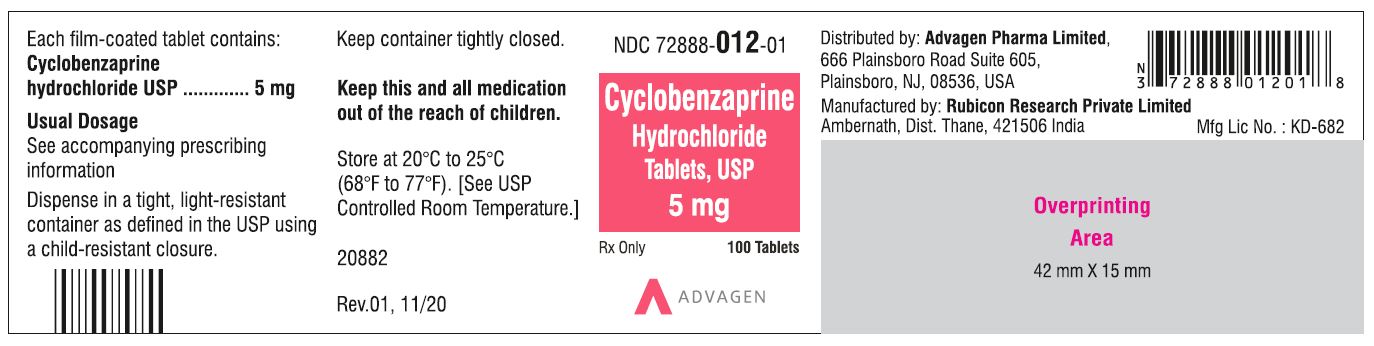
CYCLOBENZAPRINE HYDROCHLORIDE 5 mg Tablet, Film Coated, 500-count
Other active recalls for Cyclobenzaprine Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Muscle Relaxant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's a muscle relaxant prescribed to help ease muscle spasms, pain, and stiffness from acute musculoskeletal injuries — like a back strain or a pulled muscle. It's meant to be used...
- What is cyclobenzaprine actually used for?
- Yes, drowsiness is one of the most common side effects — it's real and can be significant. You should not drive, operate heavy machinery, or do anything that requires sharp focus u...
- Will this make me really drowsy? Can I drive?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.022 | $10.75 / 500 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2033 | $101.65 / 500 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1547 | $77.35 / 500 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cyclobenzaprine Hydrochloride 5 mg 00093-3420-01 | Teva | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 00904-7400-04 | Major | 1 tablet | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 10702-0006-01 | KVK-TECH, | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 16571-0782-01 | Rising | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine hydrochloride 5 mg 29300-0413-01 | Unichem | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 50268-0190-15 | AvPAK | 1 tablet | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 52817-0330-10 | TruPharma | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 59746-0211-06 | Jubilant | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 64980-0655-01 | Rising | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 68084-0753-25 | American | 1 tablet | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 69097-0845-07 | Cipla | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mg 72603-0310-01 | NORTHSTAR | 100 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine Hydrochloride 5 mgthis 72888-0012-05 | Advagen | 500 tablets | $0.021 | AB | Availability likely | — |
| Cyclobenzaprine hydrochloride 5 mg 00615-8508-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 42708-0172-20 | QPharma | 20 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 42708-0197-20 | QPharma, | 20 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 43063-0494-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 43547-0399-01 | Solco | 10 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine hydrochloride 5 mg 50090-5756-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 51655-0427-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 51655-0818-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 53746-0540-01 | Amneal | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 60429-0876-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 60760-0766-04 | ST. | 4 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 62332-0646-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 63187-0094-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 63629-1212-01 | Bryant | 500 tablets | — | AB | Discontinued | — |
| Cyclobenzaprine Hydrochloride 5 mg 63629-1213-01 | Bryant | 100 tablets | — | AB | Discontinued | — |
| Cyclobenzaprine Hydrochloride 5 mg 63629-2424-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 65162-0540-10 | Amneal | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 65862-0190-01 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 67046-1110-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 68071-2790-02 | NuCare | 12 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 68071-3475-02 | NuCare | 12 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine hydrochloride 5 mg 68071-3567-02 | NuCare | 12 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 68071-3915-02 | NuCare | 12 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 68071-4655-02 | NuCare | 12 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 68788-8221-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 68788-8471-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine hydrochloride 5 mg 68788-8706-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 70518-2611-01 | REMEDYREPACK | 90 tablets | — | AB | Discontinued | — |
| Cyclobenzaprine hydrochloride 5 mg 70518-3251-00 | REMEDYREPACK | 90 tablets | — | AB | Discontinued | — |
| Cyclobenzaprine Hydrochloride 5 mg 70518-3814-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 71205-0356-15 | Proficient | 15 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 71205-0678-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 71335-1099-00 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine hydrochloride 5 mg 71335-1961-00 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 71335-2156-00 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 71335-2479-00 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 72162-1358-01 | Bryant | 100 tablets | — | AB | Discontinued | — |
| Cyclobenzaprine Hydrochloride 5 mg 72162-1692-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 72189-0280-30 | DirectRx | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 72189-0283-20 | DirectRx | 20 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 72789-0073-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 72789-0115-10 | PD-Rx | 10 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 72789-0547-21 | PD-Rx | 21 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 76420-0030-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 76420-0269-01 | Asclemed | 1 tablet | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 76420-0828-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine hydrochloride 5 mg 76420-0839-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine HCL 5 mg 80425-0016-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine HCL 5 mg 80425-0017-01 | Advanced | 60 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine HCL 5 mg 80425-0155-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 82461-0714-90 | Medcore | 90 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 82868-0008-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Cyclobenzaprine Hydrochloride 5 mg 85534-0005-00 | HAWAII | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 72888-0012-00 | 1000 TABLET, FILM COATED in 1 BOTTLE (72888-012-00) | $0.0215 / ea | $21.45 | 2021-11-01 | Active |
| 72888-0012-01 | 100 TABLET, FILM COATED in 1 BOTTLE (72888-012-01) | $0.0215 / ea | $2.15 | 2017-05-31 | Active |
| 72888-0012-05 You're viewing this | 500 TABLET, FILM COATED in 1 BOTTLE (72888-012-05) | $0.0215 / ea | $10.73 | 2017-05-31 | Active |
You're viewing one of 3 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 3 priced pack sizes ($0.0215 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 46% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 72888-0012-05?
What is the difference between NDC 72888-0012-05 and NDC 72888-0012-01?
What NDC number is used to bill for this package of CYCLOBENZAPRINE HYDROCHLORIDE 5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Cyclobenzaprine hydrochloride tablets, USP are indicated as an adjunct to rest and physical therapy for relief of muscle spasm associated with acute, painful musculoskeletal conditions. Improvement is manifested by relief of muscle spasm and its associated signs and symptoms, namely, pain, tenderness, limitation of motion, and restriction in activities of daily living. Cyclobenzaprine hydrochloride tablets should be used only for short periods (up to 2 or 3 weeks) because adequate evidence of effectiveness for more prolonged use is not available and because muscle spasm associated with acute, painful musculoskeletal conditions is generally of short duration and specific therapy for longer periods is seldom warranted.
Cyclobenzaprine hydrochloride tablets have not been found effective in the treatment of spasticity associated with cerebral or spinal cord disease, or in children with cerebral palsy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION For most patients, the recommended dose of cyclobenzaprine hydrochloride tablets is 5 mg three times a day. Based on individual patient response, the dose may be increased to 10 mg three times a day. Use of cyclobenzaprine hydrochloride tablets for periods longer than 2 or 3 weeks is not recommended (see INDICATIONS AND USAGE) .
Less frequent dosing should be considered for hepatically impaired or elderly patients (see PRECAUTIONS: Impaired Hepatic Function , and Use in the Elderly).
⛔ Contraindications ▾
CONTRAINDICATIONS Hypersensitivity to any component of this product. Concomitant use of monoamine oxidase (MAO) inhibitors or within 14 days after their discontinuation. Hyperpyretic crisis seizures and deaths have occurred in patients receiving cyclobenzaprine (or structurally similar tricyclic antidepressants) concomitantly with MAO inhibitor drugs.
Acute recovery phase of myocardial infarction, and patients with arrhythmias, heart block or conduction disturbances, or congestive heart failure. Hyperthyroidism.
⚠️ Warnings ▾
WARNINGS Serotonin Syndrome The development of a potentially life-threatening serotonin syndrome has been reported with cyclobenzaprine hydrochloride when used in combination with other drugs, such as selective serotonin reuptake inhibitors (SSRIs), serotonin norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), tramadol, bupropion, meperidine, verapamil, or (MAO) inhibitors. The concomitant use of cyclobenzaprine hydrochloride with MAO inhibitors is contraindicated (see CONTRAINDICATIONS ). Serotonin syndrome symptoms may include mental status changes (e.g., confusion, agitation, hallucinations), autonomic instability (e.g., diaphoresis, tachycardia, labile blood pressure, hyperthermia), neuromuscular abnormalities (e.g., tremor, ataxia, hyperreflexia, clonus, muscle rigidity), and/or gastrointestinal symptoms (e.g., nausea, vomiting, diarrhea).
Treatment with cyclobenzaprine hydrochloride and any concomitant serotonergic agents should be discontinued immediately if the above reactions occur and supportive symptomatic treatment should be initiated. If concomitant treatment with cyclobenzaprine hydrochloride and other serotonergic drugs is clinically warranted, careful observation is advised, particularly during treatment initiation or dose increases (see PRECAUTIONS: Drug Interactions ). Cyclobenzaprine is closely related to the tricyclic antidepressants, e.g., amitriptyline and imipramine.
In short term studies for indications other than muscle spasm associated with acute musculoskeletal conditions, and usually at doses somewhat greater than those recommended for skeletal muscle spasm, some of the more serious central nervous system reactions noted with the tricyclic antidepressants have occurred (see WARNINGS , below, and ADVERSE REACTIONS ). Tricyclic antidepressants have been reported to produce arrhythmias, sinus tachycardia, prolongation of the conduction time leading to myocardial infarction and stroke.
Cyclobenzaprine may enhance the effects of alcohol, barbiturates, and other CNS depressants.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Incidence of most common adverse reactions in the two double-blind*, placebo-controlled 5 mg studies (incidence of > 3% on cyclobenzaprine hydrochloride 5 mg): Cyclobenzaprine Hydrochloride 5 mg Cyclobenzaprine Hydrochloride 10 mg Placebo N = 464 N = 249 N = 469 Drowsiness 29% 38% 10% Dry Mouth 21% 32% 7% Fatigue 6% 6% 3% Headache 5% 5% 8% *Note: Cyclobenzaprine hydrochloride 10 mg data are from one clinical trial. Cyclobenzaprine hydrochloride 5 mg and placebo data are from two studies. Adverse reactions which were reported in 1% to 3% of the patients were: abdominal pain, acid regurgitation, constipation, diarrhea, dizziness, nausea, irritability, mental acuity decreased, nervousness, upper respiratory infection, and pharyngitis.
The following list of adverse reactions is based on the experience in 473 patients treated with cyclobenzaprine hydrochloride 10 mg in additional controlled clinical studies, 7,607 patients in the postmarketing surveillance program, and reports received since the drug was marketed. The overall incidence of adverse reactions among patients in the surveillance program was less than the incidence in the controlled clinical studies. The adverse reactions reported most frequently with cyclobenzaprine were drowsiness, dry mouth and dizziness.
The incidence of these common adverse reactions was lower in the surveillance program than in the controlled clinical studies: Clinical Studies with Cyclobenzaprine hydrochloride 10 mg Surveillance Program with Cyclobenzaprine hydrochloride 10 mg Drowsiness 39% 16% Dry Mouth 27% 7% Dizziness 11% 3% Among the less frequent adverse reactions, there was no appreciable difference in incidence in controlled clinical studies or in the surveillance program. Adverse reactions which were reported in 1% to 3% of the patients were: fatigue/tiredness, asthenia, nausea, constipation, dyspepsia, unpleasant taste, blurred vision, headache, nervousness, and confusion.
The following adverse reactions have been reported in postmarketing experience or with an incidence of less than 1% of patients in clinical trials with the 10 mg tablet: Body as a Whole: Syncope; malaise. Cardiovascular: Tachycardia; arrhythmia; vasodilatation; palpitation; hypotension. Digestive: Vomiting; anorexia; diarrhea; gastrointestinal pain; gastritis; thirst; flatulence; edema of the tongue; abnormal liver function and rare reports of hepatitis, jaundice and cholestasis.
Hypersensitivity: Anaphylaxis; angioedema; pruritus; facial edema; urticaria; rash. Musculoskeletal: Local weakness. Nervous System and Psychiatric: Seizures; ataxia; vertigo; dysarthria; tremors; hypertonia; convulsions; muscle twitching; disorientation; insomnia; depressed mood; abnormal sensations; anxiety; agitation; psychosis; abnormal thinking and dreaming; hallucinations; excitement; paresthesia; diplopia, serotonin syndrome.
Skin: Sweating. Special Senses: Ageusia; tinnitus. Urogenital: Urinary frequency and/or retention.
Causal Relationship Unknown Other reactions, reported rarely for cyclobenzaprine under circumstances where a causal relationship could not be established or reported for other tricyclic drugs, are listed to serve as alerting information to physicians: Body as a Whole: Chest pain; edema. Cardiovascular: Hypertension; myocardial infarction; heart block; stroke. Digestive: Paralytic ileus; tongue discoloration; stomatitis; parotid swelling.
Endocrine: Inappropriate ADH syndrome. Hematic and Lymphatic: Purpura; bone marrow depression; leukopenia; eosinophilia; thrombocytopenia. Metabolic, Nutritional and Immune: Elevation and lowering of blood sugar levels; weight gain or loss.
Musculoskeletal: Myalgia. Nervous System and Psychiatric: Decreased or increased libido; abnormal gait; delusions; aggressive behavior; paranoia; peripheral neuropathy; Bell's palsy; alteration in EEG patterns; extrapyramidal symptoms. Respiratory: Dyspnea.
Skin: Photosensitization; alopecia. Urogenital: Impaired urination; dilata…
🆘 Overdosage ▾
OVERDOSAGE Although rare, deaths may occur from overdosage with cyclobenzaprine. Multiple drug ingestion (including alcohol) is common in deliberate cyclobenzaprine overdose. As management of overdose is complex and changing, it is recommended that the physician contact a poison control center for current information on treatment .
Signs and symptoms of toxicity may develop rapidly after cyclobenzaprine overdose; therefore, hospital monitoring is required as soon as possible. The acute oral LD 50 of cyclobenzaprine is approximately 338 and 425 mg/kg in mice and rats, respectively. Manifestations The most common effects associated with cyclobenzaprine overdose are drowsiness and tachycardia.
Less frequent manifestations include tremor, agitation, coma, ataxia, hypertension, slurred speech, confusion, dizziness, nausea, vomiting, and hallucinations. Rare but potentially critical manifestations of overdose are cardiac arrest, chest pain, cardiac dysrhythmias, severe hypotension, seizures, and neuroleptic malignant syndrome. Changes in the electrocardiogram, particularly in QRS axis or width, are clinically significant indicators of cyclobenzaprine toxicity.
Other potential effects of overdosage include any of the symptoms listed under ADVERSE REACTIONS. Management General As management of overdose is complex and changing, it is recommended that the physician contact a poison control center for current information on treatment. In order to protect against the rare but potentially critical manifestations described above, obtain an ECG and immediately initiate cardiac monitoring.
Protect the patient's airway, establish an intravenous line and initiate gastric decontamination. Observation with cardiac monitoring and observation for signs of CNS or respiratory depression, hypotension, cardiac dysrhythmias and/or conduction blocks, and seizures is necessary. If signs of toxicity occur at any time during this period, extended monitoring is required.
Monitoring of plasma drug levels should not guide management of the patient. Dialysis is probably of no value because of low plasma concentrations of the drug. Gastrointestinal Decontamination All patients suspected of an overdose with cyclobenzaprine should receive gastrointestinal decontamination.
This should include large volume gastric lavage followed by activated charcoal. If consciousness is impaired, the airway should be secured prior to lavage and emesis is contraindicated. Cardiovascular A maximal limb-lead QRS duration of ≥ 0.10 seconds may be the best indication of the severity of the overdose.
Serum alkalinization, to a pH of 7.45 to 7.55, using intravenous sodium bicarbonate and hyperventilation (as needed), should be instituted for patients with dysrhythmias and/or QRS widening. A pH > 7.60 or a pCO 2 < 20 mmHg is undesirable. Dysrhythmias unresponsive to sodium bicarbonate therapy/hyperventilation may respond to lidocaine, bretylium or phenytoin.
Type 1A and 1C antiarrhythmics are generally contraindicated (e.g., quinidine, disopyramide, and procainamide). CNS In patients with CNS depression, early intubation is advised because of the potential for abrupt deterioration. Seizures should be controlled with benzodiazepines or, if these are ineffective, other anticonvulsants (e.g., phenobarbital, phenytoin).
Physostigmine is not recommended except to treat life-threatening symptoms that have been unresponsive to other therapies, and then only in close consultation with a poison control center. Psychiatric Follow-up Since overdosage is often deliberate, patients may attempt suicide by other means during the recovery phase. Psychiatric referral may be appropriate.
Pediatric Management The principles of management of child and adult overdosages are similar. It is strongly recommended that the physician contact the local poison control center for specific pediatric treatment.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Cyclobenzaprine hydrochloride relieves skeletal muscle spasm of local origin without interfering with muscle function. It is ineffective in muscle spasm due to central nervous system disease. Cyclobenzaprine reduced or abolished skeletal muscle hyperactivity in several animal models.
Animal studies indicate that cyclobenzaprine does not act at the neuromuscular junction or directly on skeletal muscle. Such studies show that cyclobenzaprine acts primarily within the central nervous system at brain stem as opposed to spinal cord levels, although its action on the latter may contribute to its overall skeletal muscle relaxant activity. Evidence suggests that the net effect of cyclobenzaprine is a reduction of tonic somatic motor activity, influencing both gamma (γ) and alpha (α) motor systems.
Pharmacological studies in animals showed a similarity between the effects of cyclobenzaprine and the structurally related tricyclic antidepressants, including reserpine antagonism, norepinephrine potentiation, potent peripheral and central anticholinergic effects, and sedation. Cyclobenzaprine caused slight to moderate increase in heart rate in animals. Pharmacokinetics Estimates of mean oral bioavailability of cyclobenzaprine range from 33% to 55%.
Cyclobenzaprine exhibits linear pharmacokinetics over the dose range 2.5 mg to 10 mg, and is subject to enterohepatic circulation. It is highly bound to plasma proteins. Drug accumulates when dosed 3 times a day, reaching steady-state within 3 to 4 days at plasma concentrations about 4-fold higher than after a single dose.
At steady-state in healthy subjects receiving 10 mg t.i.d. (n = 18), peak plasma concentration was 25.9 ng/mL (range, 12.8 to 46.1 ng/mL), and area under the concentration-time (AUC) curve over an 8-hour dosing interval was 177 ng·hr/mL (range, 80 to 319 ng·hr/mL). Cyclobenzaprine is extensively metabolized, and is excreted primarily as glucuronides via the kidney.
Cytochromes P450 3A4, 1A2, and, to a lesser extent, 2D6, mediate N-demethylation, one of the oxidative pathways for cyclobenzaprine. Cyclobenzaprine is eliminated quite slowly, with an effective half-life of 18 hours (range 8 to 37 hours; n = 18); plasma clearance is
0.7L/min. The plasma concentration of cyclobenzaprine is generally higher in the elderly and in patients with hepatic impairment (see PRECAUTIONS: Use in the Elderly and PRECAUTIONS: Impaired Hepatic Function ). Elderly In a pharmacokinetic study in elderly individuals (≥ 65 yrs old), mean (n = 10) steady-state cyclobenzaprine AUC values were approximately 1.7-fold (171 ng·hr/mL, range 96.1 to 255.3) higher than those seen in a group of 18 younger adults (101.4 ng·hr/mL, range 36.1 to 182.9) from another study.
Elderly male subjects had the highest observed mean increase, approximately 2.4-fold (198.3 ng·hr/mL, range 155.6 to 255.3 vs. 83.2 ng·hr/mL, range 41.1 to 142.5 for younger males) while levels in elderly females were increased to a much lesser extent, approximately 1.2-fold (143.8 ng·hr/mL, range 96.1 to 196.3 vs. 115.9 ng·hr/mL, range 36.1 to 182.9 for younger females).
In light of these findings, therapy with cyclobenzaprine in the elderly should be initiated with a 5 mg dose and titrated slowly upward. Hepatic Impairment In a pharmacokinetic study of 16 subjects with hepatic impairment (15 mild, 1 moderate per Child-Pugh score), both AUC and C max were approximately double the values seen in the healthy control group. Based on the findings, cyclobenzaprine should be used with caution in subjects with mild hepatic impairment starting with the 5 mg dose and titrating slowly upward.
Due to the lack of data in subjects with more severe hepatic insufficiency, the use of cyclobenzaprine in subjects with moderate to severe impairment is not recommended. No significant effect on plasma levels or bioavailability of cyclobenzaprine or aspirin was noted when single or multiple doses of the two drugs were administered concomitantly…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cyclobenzaprine Hydrochloride Tablets, USP are available containing 5 mg, 7.5 mg or 10 mg of cyclobenzaprine hydrochloride, USP. The 5 mg tablets are butter scotch yellow film-coated, round tablets debossed with 020 on one side and plain on other side. They are available as follows: NDC 72888-012-01 bottles of 100 tablets NDC 72888-012-05 bottles of 500 tablets NDC 72888-012-00 bottles of 1000 tablets The 7.5 mg tablets are white to off-white film-coated, round tablets debossed with 021 on one side and plain on other side.
They are available as follows: NDC 72888-013-01 bottles of 100 tablets The 10 mg tablets are orange-yellow film-coated, round tablets debossed with 022 on one side and plain on other side. They are available as follows: NDC 72888-014-01 bottles of 100 tablets NDC 72888-014-05 bottles of 500 tablets NDC 72888-014-00 bottles of 1000 tablets Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Distributed by: Advagen Pharma Ltd East Windsor, NJ 08520, USA.
Manufactured by: Rubicon Research Limited, Thane 421506, India Rev: 01/2026
📋 Description ▾
DESCRIPTION Cyclobenzaprine hydrochloride, USP is a tricyclic amine salt which is white to off white, odourless, crystalline powder with the molecular formula C 20 H 21 N • HCl and a molecular weight of 311.9. It has a melting point of 217°C, and a pKa of 8.47 at 25°C. It is freely soluble in water, in alcohol and in methanol, sparingly soluble in isopropanol, slightly soluble in chloroform and in methylene chloride, insoluble in n-hexane.
If aqueous solutions are made alkaline, the free base separates. Cyclobenzaprine hydrochloride is designated chemically as 3-(5H -dibenzo[a,d] cyclohepten-5-ylidene)- N,N -dimethyl-1-propanamine hydrochloride, and has the following structural formula: Cyclobenzaprine hydrochloride tablets, USP are available as 5 mg, 7.5 mg and 10 mg tablets for oral administration. Each 5 mg, 7.5 mg and 10 mg tablet contains cyclobenzaprine hydrochloride and the following inactive ingredients: crospovidone, hypromellose, lactose anhydrous, macrogol, magnesium stearate, polysorbate 80, pregelatinized starch, silicified microcrystalline cellulose, titanium dioxide.
The tablets of 5 mg and 10 mg also contain D&C Yellow #10 Aluminum Lake and FD&C Yellow #6 Sunset Yellow FCF Aluminum Lake. In addition, the 5 mg tablets contain FD&C Blue #2/INDIGO Carmine Aluminum Lake. Image