
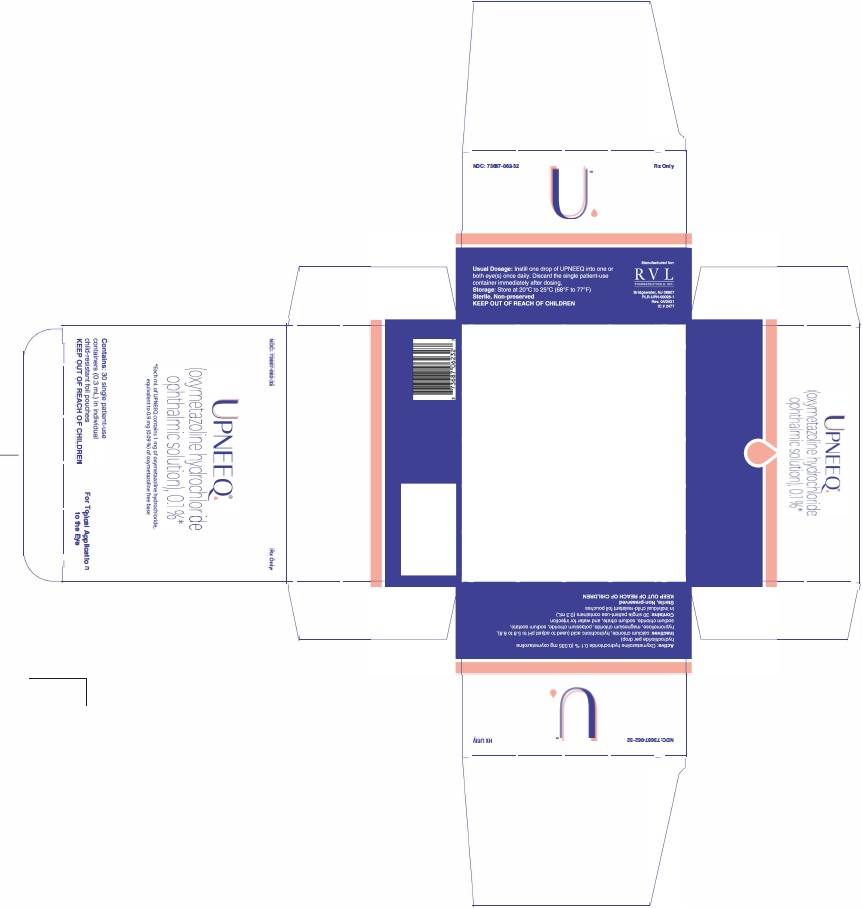
UPNEEQ Oxymetazoline hydrochloride ophthalmic 1 mg/mL Solution/ Drops, 15 ampules — NDC 73687-062-25 (Billing 73687-0062-25)
This is a package of 15 ampules of UPNEEQ Oxymetazoline hydrochloride ophthalmic 1 mg/mL Solution/ Drops from RVL Pharmaceuticals, Inc., no longer marketed (first marketed Aug 2020), no longer in the FDA NDC Directory. It is the main listing for this product, which comes in 5 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 2391749
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Vasoconstrictor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It's really important not to use the nasal spray for more than 3 days in a row. If you keep using it longer, your nose can actually become dependent on it — and when you stop, the...
- Can I use the nasal spray every day for my chronic stuffiness?
- You should check with your doctor or pharmacist first. Oxymetazoline can affect blood pressure on its own, and it can interact with antihypertensive drugs like beta-blockers. This...
- I take blood pressure medication. Is it okay to use oxymetazoline?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 73687-0062-25 You're viewing this Main listing | 15 AMPULE in 1 CARTON / .3 mL in 1 AMPULE | 2020-08-21 | — | Discontinued by firm |
| 73687-0062-32 73687-062-32 | 30 AMPULE in 1 CARTON / .3 mL in 1 AMPULE | 2020-08-21 | — | Active |
| 73687-0062-34 73687-062-34 | 30 AMPULE in 1 CARTON / .3 mL in 1 AMPULE | 2020-08-21 | — | Discontinued by firm |
| 73687-0062-45 73687-062-45 | 45 AMPULE in 1 CARTON / .3 mL in 1 AMPULE | 2020-09-01 | — | Discontinued by firm |
| 73687-0062-68 73687-062-68 | 5 AMPULE in 1 CARTON / .3 mL in 1 AMPULE Sample | 2020-10-19 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 73687-0062-68?
What NDC number is used to bill for this package of UPNEEQ Oxymetazoline hydrochloride ophthalmic 1 mg/mL Solution/ Drops?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Upneeq 1 mg/mLthis 73687-0062-25 | RVL | 15 ampules | — | — | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11324722 ↗ | Method of use | U-2849 | Dec 16, 2039 |
| US 8357714 ↗ | Method of use | U-2849 | Aug 26, 2031 |
| US 9867808 ↗ | Method of use | U-2849 | Aug 26, 2031 |
| US 10940138 ↗ | Method of use | U-2849 | Dec 16, 2039 |
| US 10799481 ↗ | Method of use | U-2849 | Dec 16, 2039 |
| US 11701343 ↗ | Method of use | U-2849 | Dec 16, 2039 |
| US 10912765 ↗ | Method of use | U-2849 | Aug 26, 2031 |
| US 12648930 ↗ | Method of use | U-2849 | Dec 16, 2039 |
| US 10898573 ↗ | Drug product | — | Dec 16, 2039 |
| US 12605363 ↗ | Drug product | — | Dec 16, 2039 |
| US 10814001 ↗ | Drug product | — | Dec 16, 2039 |
| US 11311515 ↗ | Drug product | — | Dec 16, 2039 |
| US 11541036 ↗ | Drug product | — | Dec 16, 2039 |
| US 11103482 ↗ | Drug product | — | Dec 16, 2039 |
Is there a generic version of this drug?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M4I0D6VV5M
Calcium chloride is a salt compound that acts as a firming agent and source of calcium ions in medications. It's used in formulations to help maintain tablet structure, improve texture, or serve as a buffering agent.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 02F3473H9O
A mineral salt used in medications as a source of magnesium. It helps bind ingredients together, improve texture, and maintain the product's stability during storage.
-
UNII 660YQ98I10
Potassium chloride is a mineral salt used in medicines as a buffer and to help maintain the proper pH balance and stability of the formulation during storage and use.
-
UNII 4550K0SC9B
Sodium acetate is a salt derived from acetic acid. It acts as a buffer to help maintain the medicine's pH stability and may serve as a preservative or solubilizer in liquid formulations.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 1Q73Q2JULR
Sodium citrate is a salt derived from citric acid. It works as a buffer to maintain the medicine's pH level and may also help improve taste or act as a preservative in the formulation.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE UPNEEQ is indicated for the treatment of acquired blepharoptosis in adults. UPNEEQ is indicated for the treatment of acquired blepharoptosis in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Instill one drop of UPNEEQ into one or both ptotic eye(s) once daily. Discard the single patient-use container immediately after dosing. Contact lenses should be removed prior to instillation of UPNEEQ and may be reinserted 15 minutes following its administration.
If more than one topical ophthalmic drug is being used, the drugs should be administered at least 15 minutes between applications. Instill one drop into one or both ptotic eye(s) once daily. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS UPNEEQ (oxymetazoline hydrochloride ophthalmic solution), 0.1%, equivalent to 0.09% as oxymetazoline base, is formulated for topical ocular delivery as a sterile, non-preserved, clear, colorless to slightly yellow ophthalmic solution. Ophthalmic solution, 0.1% oxymetazoline as salt, equivalent to 0.09% oxymetazoline as base. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Ptosis may be associated with neurologic or orbital diseases such as stroke and/or cerebral aneurysm, Horner syndrome, myasthenia gravis, external ophthalmoplegia, orbital infection and orbital masses. Consideration should be given to these conditions in the presence of ptosis with decreased levator muscle function and/or other neurologic signs. ( 5.1 ) Alpha-adrenergic agonists as a class may impact blood pressure.
Advise patients with cardiovascular disease, orthostatic hypotension, and/or uncontrolled hypertension or hypotension to seek medical care if their condition worsens. ( 5.2 ) Use with caution in patients with cerebral or coronary insufficiency or Sjögren’s syndrome and advise patients to seek medical care if signs and symptoms of potentiation of vascular insufficiency develop. ( 5.3 ) Advise patients to seek immediate medical care if pain, redness, blurred vision and photophobia occur (signs and symptoms of acute angle closure).
( 5.4 )
5.1Ptosis as Presenting Sign of Serious Neurologic Disease Ptosis may be associated with neurologic or orbital diseases such as stroke and/or cerebral aneurysm, Horner syndrome, myasthenia gravis, external ophthalmoplegia, orbital infection and orbital masses. Consideration should be given to these conditions in the presence of ptosis with decreased levator muscle function and/or other neurologic signs.
5.2Potential Impacts on Cardiovascular Disease Alpha-adrenergic agonists may impact blood pressure. UPNEEQ should be used with caution in patients with severe or unstable cardiovascular disease, orthostatic hypotension, and uncontrolled hypertension or hypotension. Advise patients with cardiovascular disease, orthostatic hypotension, and/or uncontrolled hypertension/hypotension to seek immediate medical care if their condition worsens.
5.3Potentiation of Vascular Insufficiency UPNEEQ should be used with caution in patients with cerebral or coronary insufficiency, or Sjögren’s syndrome. Advise patients to seek immediate medical care if signs and symptoms of potentiation of vascular insufficiency develop.
5.4Risk of Angle Closure Glaucoma UPNEEQ may increase the risk of angle closure glaucoma in patients with untreated narrow-angle glaucoma. Advise patients to seek immediate medical care if signs and symptoms of acute angle closure glaucoma develop.
5.5Risk of Contamination Patients should not touch the tip of the single patient-use container to their eye or to any surface, in order to avoid eye injury or contamination of the solution.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence 1-5%) are: punctate keratitis, conjunctival hyperemia, dry eye, vision blurred, instillation site pain, eye irritation and headache. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact RVL Pharmaceuticals, Inc. at 1-877-482-3788 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. A total of 360 subjects with acquired blepharoptosis were treated with UPNEEQ once daily in each eye for at least 6 weeks in three controlled Phase 3 clinical trials, including 203 subjects treated with UPNEEQ for 6 weeks and 157 subjects treated with UPNEEQ for 12 weeks.
Adverse reactions that occurred in 1-5% of subjects treated with UPNEEQ were punctate keratitis, conjunctival hyperemia, dry eye, blurred vision, instillation site pain, eye irritation and headache.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Anti-hypertensives/Cardiac Glycosides Alpha-adrenergic agonists, as a class, may impact blood pressure. Caution in using drugs such as beta-blockers, anti-hypertensives, and/or cardiac glycosides is advised. Caution should also be exercised in patients receiving alpha adrenergic receptor antagonists such as in the treatment of cardiovascular disease, or benign prostatic hypertrophy.
7.2Monoamine Oxidase Inhibitors Caution is advised in patients taking MAO inhibitors which can affect the metabolism and uptake of circulating amines.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on UPNEEQ use in pregnant women to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, there were no adverse developmental effects observed after oral administration of oxymetazoline hydrochloride in pregnant rats and rabbits at systemic exposures up to 7 and 278 times the maximum recommended human ophthalmic dose (MRHOD), respectively, based on dose comparison. [see Data] . The estimated background risks of major birth defects and miscarriage for the indicated population are unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Animal Data Effects on embryo-fetal development were evaluated in rats and rabbits following oral administration of oxymetazoline hydrochloride during the period of organogenesis.
Oxymetazoline hydrochloride did not cause adverse effects to the fetus at oral doses up to 0.2 mg/kg/day in pregnant rats during the period of organogenesis (28 times the MRHOD, on a dose comparison basis). Oxymetazoline hydrochloride did not cause adverse effects to the fetus at oral doses up to 1 mg/kg/day in pregnant rabbits during the period of organogenesis (278 times the MRHOD, on a dose comparison basis). Maternal toxicity, including decreased maternal body weight, was produced at the high dose of 1 mg/kg/day in pregnant rabbits and was associated with findings of delayed skeletal ossification.
In a rat prenatal and postnatal development study, oxymetazoline hydrochloride was orally administered to pregnant rats once daily from gestation day 6 through lactation day 20. Maternal toxicity was produced at the high dose of 0.2 mg/kg/day (28 times the MRHOD, on a dose comparison basis) in pregnant rats and was associated with an increase in pup mortality and reduced pup body weights. Delayed sexual maturation was noted at 0.1 mg/kg/day (14 times the MRHOD, on a dose comparison basis).
Oxymetazoline hydrochloride did not have any adverse effects on fetal development at a dose of 0.05 mg/kg/day (7 times the MRHOD, on a dose comparison basis).
8.2Lactation Risk Summary No clinical data are available to assess the effects of oxymetazoline on the quantity or rate of breastmilk production, or to establish the level of oxymetazoline present in human breastmilk post-dose. Oxymetazoline was detected in the milk of lactating rats. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for UPNEEQ and any potential adverse effects on the breastfed child from UPNEEQ.
8.4Pediatric Use Safety and effectiveness of UPNEEQ have not been established in pediatric patients under 13 years of age.
8.5Geriatric Use Three hundred and fifteen subjects aged 65 years and older received treatment with UPNEEQ (n = 216) or vehicle (n = 99) in clinical trials. No overall differences in safety or effectiveness were observed between subjects 65 years of age and older and younger subjects.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on UPNEEQ use in pregnant women to inform a drug-associated risk for major birth defects and miscarriage. In animal reproduction studies, there were no adverse developmental effects observed after oral administration of oxymetazoline hydrochloride in pregnant rats and rabbits at systemic exposures up to 7 and 278 times the maximum recommended human ophthalmic dose (MRHOD), respectively, based on dose comparison. [see Data] . The estimated background risks of major birth defects and miscarriage for the indicated population are unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Animal Data Effects on embryo-fetal development were evaluated in rats and rabbits following oral administration of oxymetazoline hydrochloride during the period of organogenesis.
Oxymetazoline hydrochloride did not cause adverse effects to the fetus at oral doses up to 0.2 mg/kg/day in pregnant rats during the period of organogenesis (28 times the MRHOD, on a dose comparison basis). Oxymetazoline hydrochloride did not cause adverse effects to the fetus at oral doses up to 1 mg/kg/day in pregnant rabbits during the period of organogenesis (278 times the MRHOD, on a dose comparison basis). Maternal toxicity, including decreased maternal body weight, was produced at the high dose of 1 mg/kg/day in pregnant rabbits and was associated with findings of delayed skeletal ossification.
In a rat prenatal and postnatal development study, oxymetazoline hydrochloride was orally administered to pregnant rats once daily from gestation day 6 through lactation day 20. Maternal toxicity was produced at the high dose of 0.2 mg/kg/day (28 times the MRHOD, on a dose comparison basis) in pregnant rats and was associated with an increase in pup mortality and reduced pup body weights. Delayed sexual maturation was noted at 0.1 mg/kg/day (14 times the MRHOD, on a dose comparison basis).
Oxymetazoline hydrochloride did not have any adverse effects on fetal development at a dose of 0.05 mg/kg/day (7 times the MRHOD, on a dose comparison basis).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of UPNEEQ have not been established in pediatric patients under 13 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use Three hundred and fifteen subjects aged 65 years and older received treatment with UPNEEQ (n = 216) or vehicle (n = 99) in clinical trials. No overall differences in safety or effectiveness were observed between subjects 65 years of age and older and younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE Accidental oral ingestion of topical intended solutions (including ophthalmic solutions and nasal sprays) containing imidazoline derivatives (e.g., oxymetazoline) in children has resulted in serious adverse events requiring hospitalization, including nausea, vomiting, lethargy, tachycardia, decreased respiration, bradycardia, hypotension, hypertension, sedation, somnolence, mydriasis, stupor, hypothermia, drooling, and coma. Keep UPNEEQ out of reach of children.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Oxymetazoline is an alpha adrenoceptor agonist targeting a subset of adrenoreceptors in Mueller’s muscle of the eyelid.
12.2Pharmacodynamics In safety and efficacy studies, Study RVL-1201-201 and Study RVL-1201-202, the pharmacodynamics of UPNEEQ was assessed using an objective photographic measure, marginal reflex distance 1 (MRD1). MRD1 is the distance from the central pupillary light reflex to the central margin of the upper lid. The maximum increase in MRD1 was observed approximately 2 hours post dose in both studies.
The MRD1 increase continued through 8 hours post dose.
12.3Pharmacokinetics Absorption The pharmacokinetics of oxymetazoline was evaluated in 24 healthy adult subjects following single-drop administration of UPNEEQ to each eye. The total dose of oxymetazoline HCl was 0.07 mg. Following ocular administration of UPNEEQ, the time to reach peak oxymetazoline concentration (T max ) values ranged from 0.5 to 12 hours with a median T max of 2 hours.
The oxymetazoline mean ± standard deviation (SD) peak concentration (C max ) and area under the concentration-time curve (AUC inf ) were 30.5 ± 12.7 pg/mL and 468 ±214 pg*hr/mL, respectively. Distribution An in vitro study demonstrated that oxymetazoline is 56.7% to 57.5% bound to human plasma proteins. Elimination The oxymetazoline mean terminal half-life (t ½ ) following administration of UPNEEQ in healthy adult subjects is 8.3 hours and ranged from 5.6 to 13.9 hours.
Metabolism In vitro studies using human liver microsomes showed that oxymetazoline was minimally metabolized, generating mono-oxygenated and dehydrogenated products of oxymetazoline. The percentage of parent drug oxymetazoline remaining was 95.9% after a 120-minute incubation with human liver microsomes. Excretion The excretion of oxymetazoline following administration of UPNEEQ has not been characterized in humans.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Oxymetazoline is an alpha adrenoceptor agonist targeting a subset of adrenoreceptors in Mueller’s muscle of the eyelid.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING UPNEEQ (oxymetazoline hydrochloride ophthalmic solution), 0.1% is an aseptically prepared, sterile, non-preserved, clear, colorless to slightly yellow ophthalmic solution; 0.3 mL fill in a clear, low-density polyethylene, single patient-use container in a child-resistant foil pouch. NDC 73687-062-32 Carton of 30 single patient-use containers in individual child-resistant foil pouches. Storage: Store at 20°C to 25°C (68°F to 77°F).
Protect from excessive heat. Keep out of reach of children. Store single patient-use containers in the child-resistant foil pouches.
Opened containers should be discarded immediately after use.
📋 Description ▾
11 DESCRIPTION UPNEEQ (oxymetazoline hydrochloride ophthalmic solution), 0.1% contains oxymetazoline hydrochloride, an alpha adrenoceptor agonist. UPNEEQ is an aseptically prepared, sterile, non-preserved ophthalmic solution. The chemical name is 6-tert-Butyl-3-(2-imidazolin-2-ylmethyl)-2,4- dimethylphenol monohydrochloride, and the molecular mass is 296.84.
Oxymetazoline HCl is freely soluble in water and ethanol and has a partition coefficient of 0.1 in 1-octanol/water. The molecular formula of oxymetazoline HCl is C 16 H 24 N 2 O∙HCl, and its structural formula is: Each mL of UPNEEQ (oxymetazoline hydrochloride ophthalmic solution) 0.1% contains 1 mg of oxymetazoline hydrochloride, equivalent to 0.9 mg (0.09%) of oxymetazoline free base. The ophthalmic solution contains the following inactive ingredients: calcium chloride, hydrochloric acid (used to adjust pH to 5.8 to 6.8), hypromellose, magnesium chloride, potassium chloride, sodium acetate, sodium chloride, sodium citrate, and water for injection.
Oxymetazoline Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and/or caregiver to read the FDA-approved patient labeling (Instructions for Use). When to Seek Medical Care Ptosis may be associated with neurologic or orbital diseases such as stroke and/or cerebral aneurysm, Horner syndrome, myasthenia gravis, external ophthalmoplegia, orbital infection and orbital masses. Consideration should be given to these conditions in the presence of ptosis with decreased levator muscle function and/or other neurologic signs [see Warnings and Precautions ( 5.1 )] .
Alpha-adrenergic agonists as a class may impact blood pressure. Advise patients with cardiovascular disease, orthostatic hypotension, and/or uncontrolled hypertension or hypotension to seek medical care if their condition worsens [see Warnings and Precautions ( 5.2 )] . Use with caution in patients with cerebral or coronary insufficiency or Sjögren’s syndrome and advise patients to seek medical care if signs and symptoms of potentiation of vascular insufficiency develop [see Warnings and Precautions ( 5.3 )] .
Advise patients to seek immediate medical care if signs and symptoms of acute narrow-angle glaucoma develop [see Warnings and Precautions ( 5.4 )] . Administration Instructions Use with Contact Lenses Advise patients that contact lenses should be removed prior to administration of UPNEEQ and can be re-inserted 15 minutes following administration [see Dosage and Administration ( 2 )] . Use with Other Ophthalmic Drugs If more than one topical ophthalmic drug is being used, the drugs should be administered at least 15 minutes between applications.
Administration Advise patients that the solution from one single patient-use container is to be used immediately after opening to dose one or both eye(s). The single patient-use container, including any remaining contents, should be discarded immediately after administration [see Dosage and Administration ( 2 )] . Storage and Handling Instructions Handling the Single Patient-Use Container Advise patients not to touch the tip of the single patient-use container to their eye or to any surface, in order to avoid eye injury or contamination of the solution.
Storage Information Instruct patients to keep the single patient-use containers in the child-resistant foil pouches until ready to use. Keep out of reach of children. To report SUSPECTED ADVERSE REACTIONS, contact RVL Pharmaceuticals, Inc. at 1-877-482-3788 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . © 2026 RVL Pharmaceuticals, Inc.
All rights reserved. Bridgewater, New Jersey 08807 Patents 8357714, 9867808, 10799481, 10814001, 10898573, 10912765, 10940138, 11103482, 11311515, 11324722, 11541036, 11701343, 12605363, and 12648930 Made in the U.S.A. Manufactured for: RVL Pharmaceuticals, Inc.
PLR-UPN-00007-10 IC # 2284
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The pharmacokinetics of oxymetazoline was evaluated in 24 healthy adult subjects following single-drop administration of UPNEEQ to each eye. The total dose of oxymetazoline HCl was 0.07 mg. Following ocular administration of UPNEEQ, the time to reach peak oxymetazoline concentration (T max ) values ranged from 0.5 to 12 hours with a median T max of 2 hours.
The oxymetazoline mean ± standard deviation (SD) peak concentration (C max ) and area under the concentration-time curve (AUC inf ) were 30.5 ± 12.7 pg/mL and 468 ±214 pg*hr/mL, respectively. Distribution An in vitro study demonstrated that oxymetazoline is 56.7% to 57.5% bound to human plasma proteins. Elimination The oxymetazoline mean terminal half-life (t ½ ) following administration of UPNEEQ in healthy adult subjects is 8.3 hours and ranged from 5.6 to 13.9 hours.
Metabolism In vitro studies using human liver microsomes showed that oxymetazoline was minimally metabolized, generating mono-oxygenated and dehydrogenated products of oxymetazoline. The percentage of parent drug oxymetazoline remaining was 95.9% after a 120-minute incubation with human liver microsomes. Excretion The excretion of oxymetazoline following administration of UPNEEQ has not been characterized in humans.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In safety and efficacy studies, Study RVL-1201-201 and Study RVL-1201-202, the pharmacodynamics of UPNEEQ was assessed using an objective photographic measure, marginal reflex distance 1 (MRD1). MRD1 is the distance from the central pupillary light reflex to the central margin of the upper lid. The maximum increase in MRD1 was observed approximately 2 hours post dose in both studies.
The MRD1 increase continued through 8 hours post dose.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES UPNEEQ was evaluated for the treatment of acquired blepharoptosis in two randomized, double-masked, vehicle-controlled, parallel-group clinical efficacy trials. Both studies were randomized in an approximate 2:1 ratio of active versus vehicle. Efficacy was assessed with the Leicester Peripheral Field Test (LPFT) (primary) and photographic measurement of Marginal reflex distance 1 (MRD1).
The primary efficacy endpoints were ordered in a hierarchy to compare UPNEEQ to vehicle on the mean increase from baseline (Day 1 Hour 0) in number of points seen on the top 4 rows of the LPFT in the study eye at Hour 6 on Day 1 and Hour 2 on Day 14. In Trial 1, a total of 140 subjects were randomized 94 patients to the UPNEEQ group and 46 patients to the vehicle group. Treatments were administered once daily to each eye for 42 days (6 weeks).
The mean age of the subjects was 64 years. In Trial 2, a total of 164 subjects were randomized 109 patients to the UPNEEQ group and 55 patients to the vehicle group. Treatments were administered once daily to each eye for 42 days (6 weeks).
The mean age of the subjects was 63 years. In both trials, each patient had a designated study eye. The increases in the number of points seen in the superior visual field in the study eye of the UPNEEQ group compared to the vehicle group were statistically significant at both time points, showing that the improvement in superior visual field was evident at the 2-hour time point and maintained at the 6-hour time point.
The results from both trials on the primary endpoint are presented below. Observed and Change from Baseline in Mean Points Seen in Superior Visual Field on LPFT in the Study Eye at Primary Efficacy Time Points (ITT Population) CL = confidence limit; LPFT = Leicester Peripheral Field Test; ITT (intent-to-treat) – included all randomized subjects who received at least one dose of study medication; SD = standard deviation a p-value and 95% CI were based on ANCOVA model adjusted for baseline LFPT points. Marginal reflex distance 1 (MRD1), showed a positive effect with UPNEEQ treatment.
Greater MRD1 increases were observed for the UPNEEQ group than the vehicle group on day 1 at 6 hours post dose and on day 14 at 2 hours post dose. Table
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Oxymetazoline hydrochloride was not associated with an increased incidence of neoplastic or proliferative changes in transgenic mice given oral doses of 0.5, 1.0, or 2.5 mg/kg/day oxymetazoline hydrochloride for 6 months. Mutagenesis Oxymetazoline hydrochloride revealed no evidence of mutagenic or clastogenic potential based on the results of two in vitro genotoxicity tests (Ames assay and human lymphocyte chromosomal aberration assay) and one in vivo gentoxicity test (mouse micronucleus assay).
Impairment of Fertility Effects on fertility and early embryonic development were evaluated in rats following oral administration of 0.05, 0.1, or 0.2 mg/kg/day oxymetazoline hydrochloride prior to and during mating and through early pregnancy. Decreased number of corpora lutea and increased post-implantation losses were noted at 0.2 mg/kg/day oxymetazoline hydrochloride (28 times the MRHOD, on a dose comparison basis). However, no treatment related effects on mating parameters were noted at 0.2 mg/kg/day oxymetazoline hydrochloride.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Oxymetazoline hydrochloride was not associated with an increased incidence of neoplastic or proliferative changes in transgenic mice given oral doses of 0.5, 1.0, or 2.5 mg/kg/day oxymetazoline hydrochloride for 6 months. Mutagenesis Oxymetazoline hydrochloride revealed no evidence of mutagenic or clastogenic potential based on the results of two in vitro genotoxicity tests (Ames assay and human lymphocyte chromosomal aberration assay) and one in vivo gentoxicity test (mouse micronucleus assay).
Impairment of Fertility Effects on fertility and early embryonic development were evaluated in rats following oral administration of 0.05, 0.1, or 0.2 mg/kg/day oxymetazoline hydrochloride prior to and during mating and through early pregnancy. Decreased number of corpora lutea and increased post-implantation losses were noted at 0.2 mg/kg/day oxymetazoline hydrochloride (28 times the MRHOD, on a dose comparison basis). However, no treatment related effects on mating parameters were noted at 0.2 mg/kg/day oxymetazoline hydrochloride.
📄 Patient Package Insert ▾
INSTRUCTIONS FOR USE UPNEEQ ® (up-NEEK) (oxymetazoline hydrochloride ophthalmic solution), 0.1% for topical ophthalmic use Read this Instructions for Use before you start using UPNEEQ and each time you get a refill. There may be new information. This leaflet does not take the place of talking to your healthcare provider about your medical condition or your treatment.
UPNEEQ single patient-use container after removal from its individual child-resistant foil pouch Important Information You Need to Know Before Using UPNEEQ UPNEEQ is for use in the eye. UPNEEQ can be harmful if swallowed. UPNEEQ is supplied as single patient-use containers individually packaged in a child-resistant foil pouch.
Do not remove a single patient-use container from the child-resistant foil pouch until you are ready to use UPNEEQ. Wash your hands before each use to make sure you do not infect your eyes while using UPNEEQ. If you are using UPNEEQ with other eye (ophthalmic) medicines, you should wait at least 15 minutes between using UPNEEQ and the other medicines.
If you wear contact lenses, remove them before using UPNEEQ. You should wait at least 15 minutes before placing them back into your eyes. Using UPNEEQ Do not let the tip of the UPNEEQ single patient-use container touch your eye or any other surfaces to avoid contamination or injury to your eye.
Use 1 drop of UPNEEQ in the affected eye 1 time each day. Each single patient-use container of UPNEEQ will give you enough medicine to treat both eyes 1 time each day if needed. There is some extra UPNEEQ in each single patient-use container in case you miss getting the drop into your eye.
Storing UPNEEQ Store UPNEEQ at room temperature between 68°F to 77°F (20°C to 25°C). Store UPNEEQ single patient-use containers in the child-resistant foil pouches they come in. Protect UPNEEQ from excessive heat.
Keep UPNEEQ and all medicines out of the reach of children. Disposing of UPNEEQ After you have applied the daily dose of medicine, throw away (dispose of) the single patient-use container and any unused UPNEEQ. Do not save any unused UPNEEQ.
Follow Step 1 to Step 11 each time you use UPNEEQ: Step 1. Remove 1 UPNEEQ child-resistant foil-pouch from the carton. Step 2 .
Make sure the single patient-use container within the foil is moved completely away from the dotted line (see Figure A ). Step 3. Cut the foil along the dotted line using scissors (see Figure B ) .
Figure A Figure B Step 4. Remove the single patient-use container from the foil pouch and then hold it by the long flat end (see Figure C ). Figure C Step 5.
Hold the single patient-use container upright and tap the top of the container gently to make sure that the medicine is in the bottom part of the container (see Figure D ). Figure D Step 6. Open the single patient-use container by twisting off the tab (see Figure E ).
Do not let the tip of the container touch your eye or any other surfaces. Figure E Step 7. Tilt your head backwards.
If you are not able to tilt your head, lie down. Step 8. Gently pull your lower eyelid downwards and look up (see Figure F ).
Figure F Step 9. Place the tip of the single patient-use container close to your eye, but be careful not to touch your eye with it (see Figure G) . Step 10.
Gently squeeze the single patient-use container and let 1 drop of UPNEEQ fall into the space between your lower eyelid and your eye (see Figure G ). If a drop misses your eye, try again. Figure G Step 11.
Repeat Step 7 to Step 10 for your other eye if instructed to do so by your healthcare provider. There is enough UPNEEQ in one container for both eyes if needed. After you have applied the daily dose of UPNEEQ, throw away the opened single patient-use container with any remaining medicine.
Be sure to keep this medicine away from children. If you use contact lenses, wait at least 15 minutes before placing them back into your eyes. Manufactured for: RVL Pharmaceuticals, Inc.
Bridgewater, NJ 08807 1-877-482-3788 PLR-UPN-00007-10 This Instructio… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL UPNEEQ 30ct Trade Carton NDC: 73687-062-32 Upneeq 30ct Trade Carton
PRINCIPAL DISPLAY PANEL UPNEEQ Trade Foil Pouch NDC: 73687-062-70 Upneeq Trade Foil Rev. 112021 Upneeq Trade Foil Rev. 112021
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |