
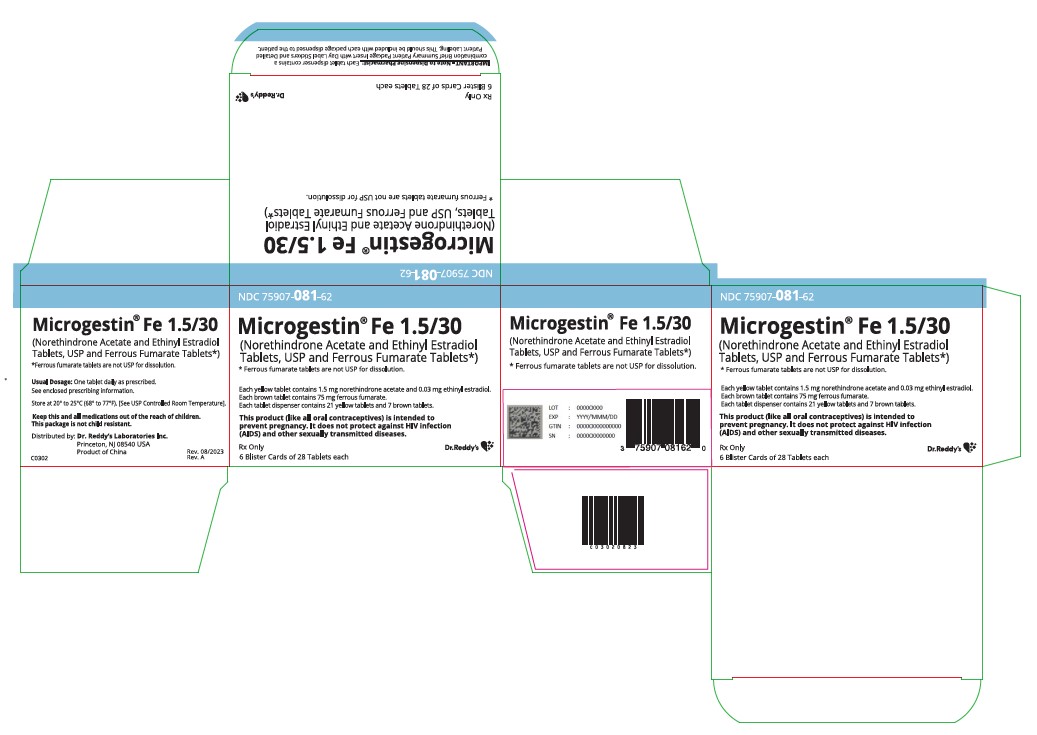
Microgestin Fe 1.5/30 Norethindrone Acetate/Ethinyl Estradiol and Ferrous Fumarate Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Iron bivalent, oral preparations class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.138 | $0.83 / 6 kit |
| Medicaid paysCMS SDUD · 12 mo | $0.2788 | $1.67 / 6 kit |
| Medicare drug plans payPart D · Q2 2026 | $0.2257 | $1.35 / 6 kit |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Microgestin Fe 1/20 75907-0082-28 | Dr. | 1 packet | $0.131 | AB | Availability likely | save 5% |
| Larin Fe 1/20 16714-0406-01 | Northstar | 1 packet | $0.131 | AB | Availability likely | save 5% |
| Larin Fe 1.5/30 16714-0405-01 | Northstar | 1 packet | $0.138 | AB | Availability likely | — |
| Microgestin Fe 1.5/30this 75907-0081-62 | Dr. | 1 kit | $0.138 | AB | Availability likely | — |
| Microgestin Fe 1/20 51862-0866-01 | Mayne | 1 packet | $0.149 | AB | FDA listed | +8% |
| Microgestin Fe 1.5/30 51862-0870-01 | Mayne | 1 packet | $0.171 | AB | FDA listed | +24% |
| Larin 24 Fe 16714-0416-01 | Northstar | 1 packet | $0.186 | AB | Availability likely | +35% |
| Microgestin 24 Fe 51862-0648-01 | Mayne | 1 packet | $0.321 | AB | FDA listed | +132% |
| Microgestin Fe 1.5/30 82804-0096-28 | Proficient | 1 kit | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 75907-0081-28 | 1 BLISTER PACK in 1 PACKET (75907-081-28) / 1 KIT in 1 BLISTER PACK | $0.1382 / ea | $0.14 | 2024-05-01 | Active |
| 75907-0081-62 You're viewing this | 6 BLISTER PACK in 1 CARTON (75907-081-62) / 1 KIT in 1 BLISTER PACK | $0.1382 / ea | $0.83 | 2024-05-01 | Active |
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1382 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 75907-0081-62?
What NDC number is used to bill for this package of Microgestin Fe 1.5/30 Norethindrone Acetate/Ethinyl Estradiol and Ferrous Fumarate Kit?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: CIGARETTE SMOKING AND SERIOUS CARDIOVASCULAR EVENTS Cigarette smoking increases the risk of serious cardiovascular events from combination oral contraceptive (COC) use. This risk increases with age, particularly in women over 35 years of age, and with the number of cigarettes smoked. For this reason, COCs, including Microgestin Fe 1.5/30, are contraindicated in women who are over 35 years of age and smoke (see CONTRAINDICATIONS and WARNINGS ).
Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with heavy smoking (15 or more cigarettes per day) and is quite marked in women over 35 years of age. Women who use oral contraceptives are strongly advised not to smoke.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Microgestin Fe 1.5/30 is indicated for the prevention of pregnancy in women who elect to use oral contraceptives as a method of contraception. Oral contraceptives are highly effective. Table I lists the typical accidental pregnancy rates for users of combination oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, depends upon the reliability with which they are used. Correct and consistent use of methods can result in lower failure rates. table1
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The compact tablet dispenser has been designed to make oral contraceptive dosing as easy and as convenient as possible. The tablets are arranged in four rows of seven tablets each, with the days of the week appearing on the compact tablet dispenser above the first row of tablets. Note: Each compact tablet dispenser has been preprinted with the days of the week, starting with Sunday, to facilitate a Sunday-Start regimen.
Six different day label stickers have been provided with the Detailed Patient & Brief Summary Patient Package Insert in order to accommodate a Day-1 Start regimen. If the patient is using the Day-1 Start regimen, she should place the self-adhesive day label sticker that corresponds to her starting day over the preprinted days. Important: The patient should be instructed to use an additional method of protection until after the first week of administration in the initial cycle when utilizing the Sunday-Start regimen.
The possibility of ovulation and conception prior to initiation of use should be considered. To achieve maximum contraceptive effectiveness, Microgestin Fe 1.5/30 should be taken exactly as directed and at intervals not exceeding 24 hours. Microgestin Fe 1.5/30 provides a continuous administration regimen consisting of 21 yellow tablets of norethindrone acetate and ethinyl estradiol and 7 brown non-hormone containing tablets of ferrous fumarate.
The ferrous fumarate tablets are present to facilitate ease of drug administration via a 28-day regimen and do not serve any therapeutic purpose. There is no need for the patient to count days between cycles because there are no “off-tablet days.’’ A. Sunday-Start Regimen: The patient begins taking the first yellow tablet from the top row of the dispenser (labeled Sunday) on the first Sunday after menstrual flow begins.
When the menstrual flow begins on Sunday, the first yellow tablet is taken on the same day. The patient takes one yellow tablet daily for 21 days. The last yellow tablet in the dispenser will be taken on a Saturday.
Upon completion of all 21 yellow tablets, and without interruption, the patient takes one brown tablet daily for 7 days. Upon completion of this first course of tablets, the patient begins a second course of 28-day tablets, without interruption, the next day (Sunday), starting with the Sunday yellow tablet in the top row. Adhering to this regimen of one yellow tablet daily for 21 days, followed without interruption by one brown tablet daily for seven days, the patient will start all subsequent cycles on a Sunday.
B. Day-1 Start Regimen: The first day of menstrual flow is Day 1. The patient places the self-adhesive day label sticker that corresponds to her starting day over the preprinted days on the compact tablet dispenser.
She starts taking one yellow tablet daily, beginning with the first yellow tablet in the top row. After the last yellow tablet (at the end of the third row) has been taken, the patient will then take the brown tablets for a week (7 days). For all subsequent cycles, the patient begins a new 28 tablet regimen on the eighth day after taking her last yellow tablet, again starting with the first tablet in the top row after placing the appropriate day label sticker over the preprinted days on the compact tablet dispenser.
Following this regimen of 21 yellow tablets and 7 brown tablets, the patient will start all subsequent cycles on the same day of the week as the first course. Tablets should be taken regularly with a meal or at bedtime. It should be stressed that efficacy of medication depends on strict adherence to the dosage schedule.
Special Notes on Administration Menstruation usually begins two or three days, but may begin as late as the fourth or fifth day, after the brown tablets have been started. In any event, the next course of tablets should be started without interruption. If spotting occurs while the patient is taking yellow tablets, continue medication without interruption.
I…
⛔ Contraindications ▾
CONTRAINDICATIONS Oral contraceptives are contraindicated in women who currently have the following conditions: Thrombophlebitis or thromboembolic disorders A past history of deep vein thrombophlebitis or thromboembolic disorders Cerebral vascular or coronary artery disease Current diagnosis of, or history of, breast cancer, which may be hormone sensitive Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Hepatic adenomas or carcinomas Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see Warnings, RISK OF LIVER ENZYME ELEVATIONS WITH CONCOMITANT HEPATITIS C TREATMENT ).
⚠️ Warnings ▾
WARNINGS The use of oral contraceptives is associated with increased risks of several serious conditions including myocardial infarction, thromboembolism, stroke, hepatic neoplasia, and gallbladder disease, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as hypertension, hyperlipidemias, obesity, and diabetes. Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks.
The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with higher formulations of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with lower formulations of both estrogens and progestogens remains to be determined. Throughout this labeling, epidemiological studies reported are of two types: retrospective or case control studies and prospective or cohort studies.
Case control studies provide a measure of the relative risk of a disease, namely, a ratio of the incidence of a disease among oral contraceptive users to that among nonusers. The relative risk does not provide information on the actual clinical occurrence of a disease. Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral contraceptive users and nonusers.
The attributable risk does provide information about the actual occurrence of a disease in the population (adapted from References 8 and 9 with the author's permission). For further information, the reader is referred to a text on epidemiological methods. 1.
Thromboembolic Disorders and Other Vascular Problems a. Myocardial infarction An increased risk of myocardial infarction has been attributed to oral contraceptive use. This risk is primarily in smokers or women with other underlying risk factors for coronary artery disease such as hypertension, hypercholesterolemia, morbid obesity, and diabetes.
The relative risk of heart attack for current oral contraceptive users has been estimated to be two to six (10-16) . The risk is very low under the age of 30. Smoking in combination with oral contraceptive use has been shown to contribute substantially to the incidence of myocardial infarctions in women in their mid-thirties or older with smoking accounting for the majority of excess cases (17) .
Mortality rates associated with circulatory disease have been shown to increase substantially in smokers over the age of 35 and non-smokers over the age of 40 (Table II) among women who use oral contraceptives. Oral contraceptives may compound the effects of well-known risk factors, such as hypertension, diabetes, hyperlipidemias, age and obesity (19) . In particular, some progestogens are known to decrease HDL cholesterol and cause glucose intolerance, while estrogens may create a state of hyperinsulinism (20-24) .
Oral contraceptives have been shown to increase blood pressure among users (see section 10 in WARNINGS). Similar effects on risk factors have been associated with an increased risk of heart disease. Oral contraceptives must be used with caution in women with cardiovascular disease risk factors. table2 b.
Thromboembolism An increased risk of thromboembolic and thrombotic disease associated with the use of oral contraceptives is well established. Case control studies have found the relative risk of users compared to non-users to be 3 for the first episode of superficial venous thrombosis, 4 to 11 for deep vein thrombosis or pulmonary embolism, and 1.5 to 6 for women with predisposing conditions for venous thromboembolic disease (9,10,25-30) . Cohort studies have shown the relative risk to be somewhat lower, about 3 for new cases and about 4.5 for new cases requiring hospitalization (31) .
The risk of thromboem…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS An increased risk of the following serious adverse reactions has been associated with the use of oral contraceptives (see WARNINGS section): Thrombophlebitis Arterial thromboembolism Pulmonary embolism Myocardial infarction Cerebral hemorrhage Cerebral thrombosis Hypertension Gallbladder disease Hepatic adenomas or benign liver tumors Post Marketing Experience Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 - 1.12 (Figure 1) (70-74) .
Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 1) (70,73,75) . One of these studies reported no association between breast cancer risk and COC use. The other two studies found an increased relative risk of 1.19 - 1.33 with current or recent use.
Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8-10 years of COC use. FIGURE 1: RELEVANT STUDIES OF RISK OF BREAST CANCER WITH COMBINED ORAL CONTRACEPTIVES RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs. There is evidence of an association between the following conditions and the use of oral contraceptives, although additional confirmatory studies are needed: Mesenteric thrombosis Retinal thrombosis The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug-related: Nausea Vomiting Gastrointestinal symptoms (such as abdominal cramps and bloating) Breakthrough bleeding Spotting Change in menstrual flow Amenorrhea Temporary infertility after discontinuation of treatment Edema Melasma which may persist Breast changes: tenderness, enlargement, secretion Change in weight (increase or decrease) Change in cervical erosion and secretion Diminution in lactation when given immediately postpartum Cholestatic jaundice Migraine Rash (allergic) Depression Reduced tolerance to carbohydrates Vaginal candidiasis Change in corneal curvature (steepening) Intolerance to contact lenses The following adverse reactions have been reported in users of oral contraceptives and the association has been neither confirmed nor refuted: Pre-menstrual syndrome Cataracts Changes in appetite Cystitis-like syndrome Headache Nervousness Dizziness Hirsutism Loss of scalp hair Erythema multiforme Erythema nodosum Hemorrhagic eruption Vaginitis Porphyria Impaired renal function Hemolytic uremic syndrome Budd-Chiari syndrome Acne Changes in libido Colitis image RELEVANT
🆘 Overdosage ▾
OVERDOSAGE Serious ill effects have not been reported following acute ingestion of large doses of oral contraceptives by young children. Overdosage may cause nausea, and withdrawal bleeding may occur in females.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation). Pharmacokinetics The pharmacokinetics of Microgestin Fe 1.5/30 have not been characterized; however, the following pharmacokinetic information regarding norethindrone acetate and ethinyl estradiol is taken from the literature.
Absorption Norethindrone acetate appears to be completely and rapidly deacetylated to norethindrone after oral administration, since the disposition of norethindrone acetate is indistinguishable from that of orally administered norethindrone (1) . Norethindrone acetate and ethinyl estradiol are subject to first-pass metabolism after oral dosing, resulting in an absolute bioavailability of approximately 64% for norethindrone and 43% for ethinyl estradiol (1-3) . Distribution Volume of distribution of norethindrone and ethinyl estradiol ranges from 2 to 4 L/kg (1-3) .
Plasma protein binding of both steroids is extensive (greater than 95%); norethindrone binds to both albumin and sex hormone binding globulin, whereas ethinyl estradiol binds only to albumin (4) . Metabolism Norethindrone undergoes extensive biotransformation, primarily via reduction, followed by sulfate and glucuronide conjugation. The majority of metabolites in the circulation are sulfates, with glucuronides accounting for most of the urinary metabolites (5) .
A small amount of norethindrone acetate is metabolically converted to ethinyl estradiol. Ethinyl estradiol is also extensively metabolized, both by oxidation and by conjugation with sulfate and glucuronide. Sulfates are the major circulating conjugates of ethinyl estradiol and glucuronides predominate in urine.
The primary oxidative metabolite is 2-hydroxy ethinyl estradiol, formed by the CYP3A4 isoform of cytochrome P450. Part of the first-pass metabolism of ethinyl estradiol is believed to occur in gastrointestinal mucosa. Ethinyl estradiol may undergo enterohepatic circulation (6) .
Excretion Norethindrone and ethinyl estradiol are excreted in both urine and feces, primarily as metabolites (5,6) . Plasma clearance values for norethindrone and ethinyl estradiol are similar (approximately
0.4L/hr/kg) (1-3) . Special Population Race: The effect of race on the disposition of Microgestin Fe 1.5/30 has not been evaluated. Renal Insufficiency The effect of renal disease on the disposition of Microgestin Fe 1.5/30 has not been evaluated.
In premenopausal women with chronic renal failure undergoing peritoneal dialysis who received multiple doses of an oral contraceptive containing ethinyl estradiol and norethindrone, plasma ethinyl estradiol concentrations were higher and norethindrone concentrations were unchanged compared to concentrations in premenopausal women with normal renal function. Hepatic Insufficiency The effect of hepatic disease on the disposition of Microgestin Fe 1.5/30 has not been evaluated. However, ethinyl estradiol and norethindrone may be poorly metabolized in patients with impaired liver function.
Drug-Drug Interactions Numerous drug-drug interactions have been reported for oral contraceptives. A summary of these is found under PRECAUTIONS, Drug Interactions .
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Microgestin Fe 1.5/30 is available in dispensers (NDC 75907-081-28) each containing 21 yellow tablets and 7 brown tablets. Each yellow, biconvex, round tablet debossed with “L3” on one side contains 1.5 mg of norethindrone acetate and 30 mcg of ethinyl estradiol. Each brown, biconvex, round tablet debossed with “F” on one side and “ N ” on the other side contains 75 mg ferrous fumarate.
Microgestin Fe 1.5/30 Tablets are available in the following configurations: Carton of 6 NDC 75907-081-62 Store at 20 ˚ C to 25 ˚ C (68 ˚ F to 77 ˚ F)[See USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Microgestin Fe 1.5/30 is a progestogen-estrogen combination. Microgestin Fe 1.5/30 provides a continuous dosage regimen consisting of 21 yellow oral contraceptive tablets and seven brown ferrous fumarate tablets. The ferrous fumarate tablets are present to facilitate ease of drug administration via a 28-day regimen, are non-hormonal, and do not serve any therapeutic purpose.
Each yellow tablet contains norethindrone acetate (17 alpha-ethinyl-19-nortestosterone acetate), 1.5 mg; ethinyl estradiol (17 alpha-ethinyl-1,3,5(10)-estratriene-3, 17 beta-diol), 30 mcg. Also contains polyvinyl alcohol, titanium dioxide, talc, macrogol/polyethylglycol 3350 , lecithin (soya), iron oxide yellow, FD&C Blue No.2 Aluminum Lake, D&C Yellow No.10 Aluminum Lake, FD&C Yellow No.6 Aluminum Lake, lactose, magnesium stearate and pregelatinized corn starch. The structural formulas are as follows: Each brown placebo tablet contains ferrous fumarate, polyvinyl alcohol, talc, macrogol/polyethylene glycol 3350 NF, lecithin (soya), iron oxide black, iron oxide yellow, microcrystalline cellulose, hydroxypropyl cellulose, magnesium stearate and crospovidone.
The ferrous fumarate tablets do not serve any therapeutic purpose. Structural Formula