
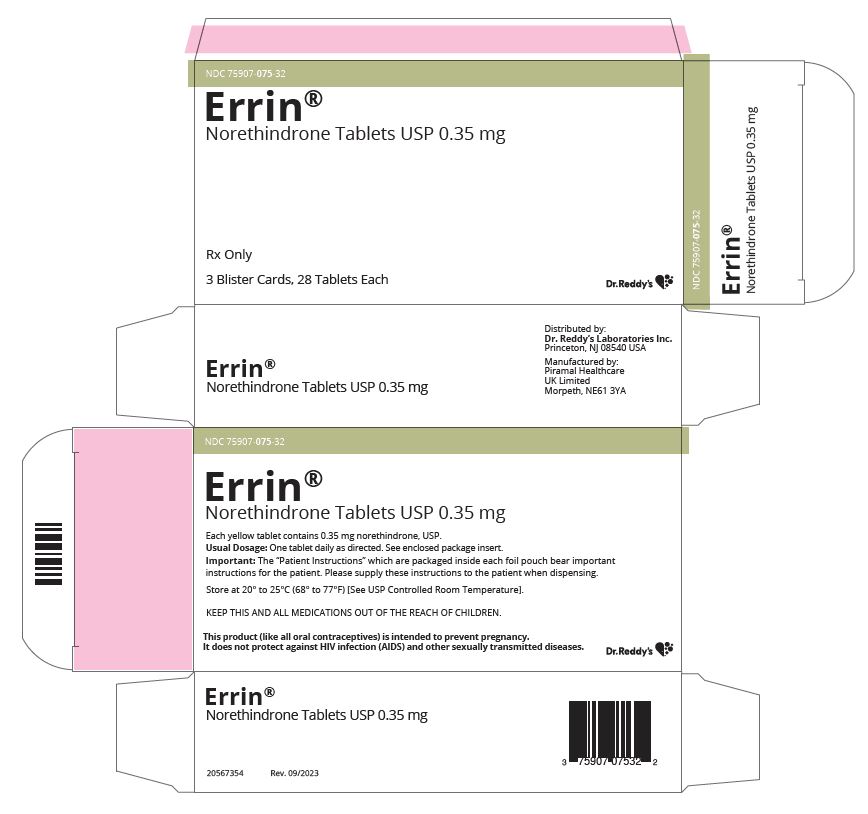
ERRIN NORETHINDRONE .35 mg Tablet, 84-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Norethindrone is used to treat endometriosis (a condition in which the type of tissue that lines the uterus [womb] grows in other areas of the body and causes pain, heavy or irregular menstruation [periods], and other symptoms). Norethindrone is also used to treat abnormal periods or bleeding and to bring on a normal menstrual cycle in women who menstruated normally in the past but have not menstruated for at least 3 months and who are not pregnant or experiencing menopause (change of life; the end of monthly menstrual periods). Norethindrone is in a class of medications called progestins. It...
Read the full MedlinePlus article ↗- It depends on the product. Most norethindrone tablets — including brands like Camila, Errin, Emzahh, and Affodel — are progestin-only birth control pills taken daily to prevent pre...
- Regular combination birth control pills contain two hormones — estrogen and progestin. Norethindrone is a progestin-only pill, sometimes called the 'mini-pill.' Because it has no e...
- How is this different from regular birth control pills?
- The most common thing people notice is irregular bleeding — spotting between periods, or changes in your cycle. Headache, breast tenderness, nausea, and dizziness are also reported...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Norethindrone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 7Z8S9VYZ4B
Ethylcellulose is a plant-derived thickener and film-former made by chemically modifying cellulose. It's used as a binder to hold tablet ingredients together, a coating to control how quickly medicine is released, or a thickener in liquid formulations.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.091 | $7.62 / 84 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2050 | $17.22 / 84 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1480 | $12.43 / 84 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Camila .35 mg 51862-0884-03 | Mayne | 84 tablets | $0.091 | AB1 | Discontinued | — |
| Errin .35 mg 51862-0886-03 | Mayne | 84 tablets | $0.091 | AB2 | Discontinued | — |
| Incassia .35 mg 65862-0925-28 | Aurobindo | 1 tablet | $0.091 | AB1 | Availability likely | — |
| Lyleq .35 mg 50102-0300-13 | Afaxys | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Emzahh .35 mg 59651-0136-28 | Aurobindo | 1 tablet | $0.091 | AB2 | Availability likely | — |
| Meleya .35 mg 70700-0317-85 | Xiromed | 84 tablets | $0.091 | AB2 | Availability likely | — |
| Norethindrone .35 mg 68462-0305-29 | Glenmark | 84 tablets | $0.091 | AB2 | Availability likely | — |
| Norethindrone .35 mg 00378-7292-53 | Mylan | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Orquidea .35 mg 70700-0316-85 | Xiromed, | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Camila .35 mg 75907-0074-32 | Dr. | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Norethindrone .35 mg 68180-0876-73 | Lupin | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Jencycla .35 mg 68180-0877-73 | Lupin | 28 tablets | $0.091 | AB2 | Availability likely | — |
| Heather .35 mg 68462-0303-29 | Glenmark | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Nora BE .35 mg 00480-3475-16 | Teva | 168 tablets | $0.091 | AB1 | Availability likely | — |
| Errin .35 mgthis 75907-0075-32 | Dr. | 84 tablets | $0.091 | AB2 | Availability likely | — |
| Nora BE .35 mg 52544-0629-28 | Actavis | 168 tablets | $0.094 | AB1 | Discontinued | +4% |
| Norethindrone .35 mg 63187-0748-28 | Proficient | 28 tablets | — | AB2 | FDA listed | — |
| Errin .35 mg 71205-0526-28 | Proficient | 28 tablets | — | AB2 | FDA listed | — |
| Norethindrone .35 mg 60505-4900-08 | Apotex | 84 tablets | — | AB1 | FDA listed | — |
| Affodel .35 mg 79929-0015-07 | Naari | 2352 tablets | — | AB1 | FDA listed | — |
| Norethindrone .35 mg 82804-0175-28 | Proficient | 28 tablets | — | AB1 | FDA listed | — |
| Norethindrone .35 mg 50090-6161-00 | A-S | 28 tablets | — | AB1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 75907-0075-32 You're viewing this | 3 BLISTER PACK in 1 CARTON (75907-075-32) / 28 TABLET in 1 BLISTER PACK (75907-075-28) | 2024-03-10 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE 1. Indications Progestin-only oral contraceptives are indicated for the prevention of pregnancy. 2.
Efficacy If used perfectly, the first-year failure rate for progestin-only oral contraceptives is 0.3%. However, the typical failure rate is estimated to be closer to 9%, due to late or omitted pills. Table 1 lists the pregnancy rates for users of all major methods of contraception.
Table 1: Percentage of Women Experiencing an Unintended Pregnancy During the First Year of Typical Use and the First Year of Perfect Use of Contraception and the Percentage Continuing Use at the End of the First Year. United States. % of Women Experiencing an Unintended Pregnancy within the First Year of Use % of Women Continuing Use at One Year Among couples attempting to avoid pregnancy, the percentage who continue to use a method for 1 year. Method (1) Typical Use Among typical couples who initiate use of a method (not necessarily for the first time), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason.
Estimates of the probability of pregnancy during the first year of typical use for spermicides, withdrawal, fertility awareness-based methods, the diaphragm, the male condom, the oral contraceptive pill, and Depo-Provera are taken from the 1995 National Survey of Family Growth corrected for underreporting of abortion; see the text for the derivation of estimates for the other methods. (2) Perfect Use Among couples who initiate use of a method (not necessarily for the first time) and who use it perfectly (both consistently and correctly), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason.
See the text for the derivation of the estimate for each method. (3) (4) Emergency Contraception: Emergency contraceptive pills or insertion of a copper intrauterine contraceptive after unprotected intercourse substantially reduces the risk of pregnancy. ella, Plan B One-Step and Next Choice are the only dedicated products specifically marketed for emergency contraception. The label for Plan B One-Step (one dose is 1 white pill) says to take the pill within 72 hours after unprotected intercourse.
Research has shown that all of the brands listed here are effective when used within 120 hours after unprotected sex. The label for Next Choice (one dose is 1 peach pill) says to take 1 pill within 72 hours after unprotected intercourse and another pill 12 hours later. Research has shown that both pills can be taken at the same time with no decrease in efficacy or increase in side effects and that they are effective when used within 120 hours after unprotected sex.
The FDA has in addition declared the following 19 brands of oral contraceptives to be safe and effective for emergency contraception: Ogestrel (1 dose is 2 white pills), Nordette (1 dose is 4 light-orange pills), Cryselle, Levora, Low-Ogestrel, Lo/Ovral, or Quasence (1 dose is 4 white pills), Jolessa, Portia, Seasonale or Trivora (1 dose is 4 pink pills), Seasonique (1 dose is 4 light-blue-green pills), Enpresse (one dose is 4 orange pills), Lessina (1 dose is 5 pink pills), Aviane or LoSeasonique (one dose is 5 orange pills), Lutera or Sronyx (one dose is 5 white pills), and Lybrel (one dose is 6 yellow pills).
(See Chapter 6). Lactational Amenorrhea Method: LAM is highly effective, temporary method of contraception. However, to maintain effective protection against pregnancy, another method of contraception must be used as soon as menstruation resumes, the frequency or duration of breastfeeds is reduced, bottle feeds are introduced, or the baby reaches 6 months of age.
(See Chapter 18). Source: Trussell J, Contraceptive Efficacy. In Hatcher RA, Trussell J, Nelson AL, Cates W, Kowal D, Policar M.
Contraceptive Technology: Twentieth Revised Edition. New York NY: Ardent Media, 2011. Notes: No Method The percentages becoming pregnant in columns (2) and (3…
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Errin ® must be taken exactly as directed. One tablet is taken every day, at the same time. Administration is continuous, with no interruption between pill packs. See Detailed Patient Labeling for detailed instruction.
⛔ Contraindications ▾
CONTRAINDICATIONS Progestin-only oral contraceptives (POPs) should not be used by women who currently have the following conditions: Known or suspected pregnancy Known or suspected carcinoma of the breast Undiagnosed abnormal genital bleeding Hypersensitivity to any component of this product Benign or malignant liver tumors Acute liver disease
⚠️ Warnings ▾
WARNINGS Cigarette smoking increases the risk of serious cardiovascular disease. Women who use oral contraceptives should be strongly advised not to smoke. Errin ® does not contain estrogen and, therefore, this insert does not discuss the serious health risks that have been associated with the estrogen component of combined oral contraceptives (COCs).
The healthcare professional is referred to the prescribing information of combined oral contraceptives for a discussion of those risks. The relationship between progestin-only oral contraceptives and these risks is not fully defined. The healthcare professional should remain alert to the earliest manifestation of symptoms of any serious disease and discontinue oral contraceptive therapy when appropriate.
1. Ectopic Pregnancy The incidence of ectopic pregnancies for progestin-only oral contraceptive users is 5 per 1000 woman-years. Up to 10% of pregnancies reported in clinical studies of progestin-only oral contraceptive users are extrauterine.
Although symptoms of ectopic pregnancy should be watched for, a history of ectopic pregnancy need not be considered a contraindication to use of this contraceptive method. Healthcare professionals should be alert to the possibility of an ectopic pregnancy in women who become pregnant or complain of lower abdominal pain while on progestin-only oral contraceptives. 2.
Delayed Follicular Atresia/Ovarian Cysts If follicular development occurs, atresia of the follicle is sometimes delayed and the follicle may continue to grow beyond the size it would attain in a normal cycle. Generally these enlarged follicles disappear spontaneously. Often they are asymptomatic; in some cases they are associated with mild abdominal pain.
Rarely they may twist or rupture, requiring surgical intervention. 3. Irregular Genital Bleeding Irregular menstrual patterns are common among women using progestin-only oral contraceptives.
If genital bleeding is suggestive of infection, malignancy or other abnormal conditions, such nonpharmacologic causes should be ruled out. If prolonged amenorrhea occurs, the possibility of pregnancy should be evaluated. 4.
Carcinoma of the Breast and Reproductive Organs Some epidemiological studies of oral contraceptive users have reported an increased relative risk of developing breast cancer, particularly at a younger age and apparently related to duration of use. These studies have predominantly involved combined oral contraceptives and there is insufficient data to determine whether the use of POPs similarly increases the risk. A meta-analysis of 54 studies found a small increase in the frequency of having breast cancer diagnosed for women who were currently using combined oral contraceptives or had used them within the past ten years.
This increase in the frequency of breast cancer diagnosis, within ten years of stopping use, was generally accounted for by cancers localized to the breast. There was no increase in the frequency of having breast cancer diagnosed ten or more years after cessation of use. Women with breast cancer should not use oral contraceptives because the role of female hormones in breast cancer has not been fully determined.
Some studies suggest that oral contraceptive use has been associated with an increase in the risk of cervical intraepithelial neoplasia in some populations of women. However, there continues to be controversy about the extent to which such findings may be due to differences in sexual behavior and other factors. There is insufficient data to determine whether the use of POPs increases the risk of developing cervical intraepithelial neoplasia.
5. Hepatic Neoplasia Benign hepatic adenomas are associated with combined oral contraceptive use, although the incidence of benign tumors is rare in the United States. Rupture of benign, hepatic adenomas may cause death through intra-abdominal hemorrhage.
Studies have shown an increased risk of developing hepatocellular carcinoma in combined oral contraceptiv…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions reported with the use of POPs include: Menstrual irregularity is the most frequently reported side effect. Frequent and irregular bleeding are common, while long duration of bleeding episodes and amenorrhea are less likely. Headache, breast tenderness, nausea, and dizziness are increased among progestin-only oral contraceptive users in some studies.
Androgenic side effects such as acne, hirsutism, and weight gain occur rarely. The following adverse reactions were also reported in clinical trials or during post-marketing experience: Gastrointestinal Disorders: vomiting, abdominal pain; General Disorders and Administration Site Conditions: fatigue, edema; Psychiatric Disorders: depression, nervousness; Musculoskeletal and Connective Tissue Disorders: pain in extremity; Reproductive System and Breast Disorders: genital discharge; breast pain, menstruation delayed, suppressed lactation, vaginal hemorrhage, menorrhagia, withdrawal bleed when product is stopped; Immune System Disorders: anaphylactic/anaphylactoid reaction, hypersensitivity; Hepatobiliary Disorders: hepatitis, jaundice cholestatic; Skin and Subcutaneous Tissue Disorders: alopecia, rash, rash pruritic.
To report SUSPECTED ADVERSE EVENTS, contact Dr. Reddy's Laboratories at 1-888-375-3784 or FDA at 1-800-FDA-1088 or http://www.fda.gov/medwatch for voluntary reporting of adverse reactions.
🔄 Drug Interactions ▾
4. Drug Interactions Consult the labeling of concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations. • Effect of Other Drugs on Hormonal Contraceptives Substances decreasing the systemic concentrations of hormonal contraceptives (HCs) and potentially diminishing the efficacy of HCs Drugs or herbal products that induce certain enzymes, including cytochrome P450 3A4 (CYP3A4), may decrease the systemic concentrations of HCs and potentially diminish the effectiveness of HCs or increase breakthrough bleeding.
Some drugs or herbal products that may decrease the effectiveness of HCs include efavirenz, phenytoin, barbiturates, carbamazepine, bosentan, felbamate, griseofulvin, oxcarbazepine, rifampicin, rifabutin, rufinamide, aprepitant, and products containing St. John's wort. Interactions between HCs and other drugs may lead to breakthrough bleeding and/or contraceptive failure.
Counsel women to use an alternative non-hormonal method of contraception or a back-up method when enzyme inducers are used with HCs, and to continue back-up non-hormonal contraception for 28 days after discontinuing the enzyme inducer to ensure contraceptive reliability. Substances increasing the systemic concentrations of HCs Co-administration of certain HCs and strong or moderate CYP3A4 inhibitors such as itraconazole, voriconazole, fluconazole, grapefruit juice, or ketoconazole may increase the systemic concentrations of progestins, including norethindrone.
Human Immunodeficiency Virus (HIV)/Hepatitis C Virus (HCV) protease inhibitors and nonnucleoside reverse transcriptase inhibitors Significant decreases in systemic concentrations of progestin have been noted in cases of co-administration with some HIV protease inhibitors (e.g., nelfinavir, ritonavir, darunavir/ritonavir, (fos)amprenavir/ritonavir, lopinavir/ritonavir, and tipranavir/ritonavir), some HCV protease inhibitors (e.g., boceprevir and telaprevir), and some non-nucleoside reverse transcriptase inhibitors (e.g., nevirapine, efavirenz).
In contrast, significant increases in systemic exposure of the progestin have been noted in cases of co-administration with certain other HIV protease inhibitors (e.g., indinavir and atazanavir/ritonavir) and with other non-nucleoside reverse transcriptase inhibitors (e.g., etravirine). These changes may be clinically relevant in some cases. Consult the prescribing information of anti-viral and anti-retroviral concomitant medications to identify potential interactions. • Effects of Hormonal Contraceptives on Other Drugs Hormonal contraceptives may affect the metabolism of other drugs.
Consequently, systemic concentrations may either increase (for example, cyclosporine) or decrease. Consult the labeling of all concurrently-used drugs to obtain further information about interactions with hormonal contraceptives or the potential for enzyme alterations. • Interactions between ulipristal and hormonal contraceptives Effectiveness of progestin-containing hormonal contraceptives and emergency contraceptive ulipristal acetate may be decreased if progestin-containing hormonal contraceptives are used within five days after ulipristal acetate dosing.
Therefore, if a woman wishes to use Errin ® after using ulipristal acetate, she should do so no sooner than 5 days after the intake of ulipristal acetate and she should use a reliable barrier method for subsequent acts of intercourse until her next menstrual period.
🔄 Drug / Laboratory Test Interactions ▾
5. Interactions with Laboratory Tests The following endocrine tests may be affected by progestin-only oral contraceptive use: Sex hormone-binding globulin (SHBG) concentrations may be decreased. Thyroxine concentrations may be decreased, due to a decrease in thyroid binding globulin (TBG).
🤰 Pregnancy ▾
7. Pregnancy Many studies have found no effects on fetal development associated with long-term use of contraceptive doses of oral progestins. The few studies of infant growth and development that have been conducted have not demonstrated significant adverse effects. It is nonetheless prudent to rule out suspected pregnancy before initiating any hormonal contraceptive use.
🧒 Pediatric Use ▾
9. Pediatric Use Safety and efficacy of Errin ® Tablets have been established in women of reproductive age. Safety and efficacy are expected to be the same for postpubertal adolescents under the age of 16 and for users 16 years and older. Use of this product before menarche is not indicated.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of serious ill effects from overdosage, including ingestion by children.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY 1. Mode of Action Errin ® progestin-only oral contraceptives prevent conception by suppressing ovulation in approximately half of users, thickening the cervical mucus to inhibit sperm penetration, lowering the midcycle LH and FSH peaks, slowing the movement of the ovum through the fallopian tubes, and altering the endometrium. 2.
Pharmacokinetics Serum progestin levels peak about two hours after oral administration, followed by rapid distribution and elimination. By 24 hours after drug ingestion, serum levels are near baseline, making efficacy dependent upon rigid adherence to the dosing schedule. There are large variations in serum levels among individual users.
Progestin-only administration results in lower steady-state serum progestin levels and a shorter elimination half-life than concomitant administration with estrogens.
🧬 Mechanism of Action ▾
1. Mode of Action Errin ® progestin-only oral contraceptives prevent conception by suppressing ovulation in approximately half of users, thickening the cervical mucus to inhibit sperm penetration, lowering the midcycle LH and FSH peaks, slowing the movement of the ovum through the fallopian tubes, and altering the endometrium.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Errin ® (norethindrone tablets USP, 0.35 mg) are packaged in cartons of three blister cards each containing 28 tablets (NDC 75907-075-32). Each yellow, round, flat-faced, beveled-edge, unscored tablet is debossed with m on one side and 886 on the other side. Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. KEEP THIS AND ALL MEDICATIONS OUT OF THE REACH OF CHILDREN.
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. KEEP THIS AND ALL MEDICATIONS OUT OF THE REACH OF CHILDREN.
📋 Description ▾
DESCRIPTION Errin ® Tablets Norethindrone, USP is a white to creamy white, odorless, crystalline powder. It is stable in air. Practically insoluble in water; soluble in chloroform and in dioxane; sparingly soluble in alcohol; slightly soluble in ether.
The chemical name for norethindrone is 17-Hydroxy-19-nor-17α-pregn-4-en-20-yn-3-one. The structural formula is as follows: C 20 H 26 O 2 M.W.298.42 Each yellow tablet contains 0.35 mg norethindrone, USP and has the following inactive ingredients: anhydrous lactose, corn starch, D&C yellow no. 10 aluminum lake, ethylcellulose aqueous dispersion, lactose monohydrate, magnesium stearate, microcrystalline cellulose and povidone.
Meets USP Dissolution Test 2.
💬 Information for Patients ▾
INFORMATION FOR THE PATIENT See " Detailed Patient Labeling " for detailed information. Counseling Issues The following points should be discussed with prospective users before prescribing progestin-only oral contraceptives: The necessity of taking pills at the same time every day, including throughout all bleeding episodes. The need to use a backup method such as a condom and spermicide for the next 48 hours whenever a progestin-only oral contraceptive is taken 3 or more hours late.
The potential side effects of progestin-only oral contraceptives, particularly menstrual irregularities. The need to inform the healthcare professional of prolonged episodes of bleeding, amenorrhea or severe abdominal pain. The importance of using a barrier method in addition to progestin-only oral contraceptives if a woman is at risk of contracting or transmitting STDs/HIV.