
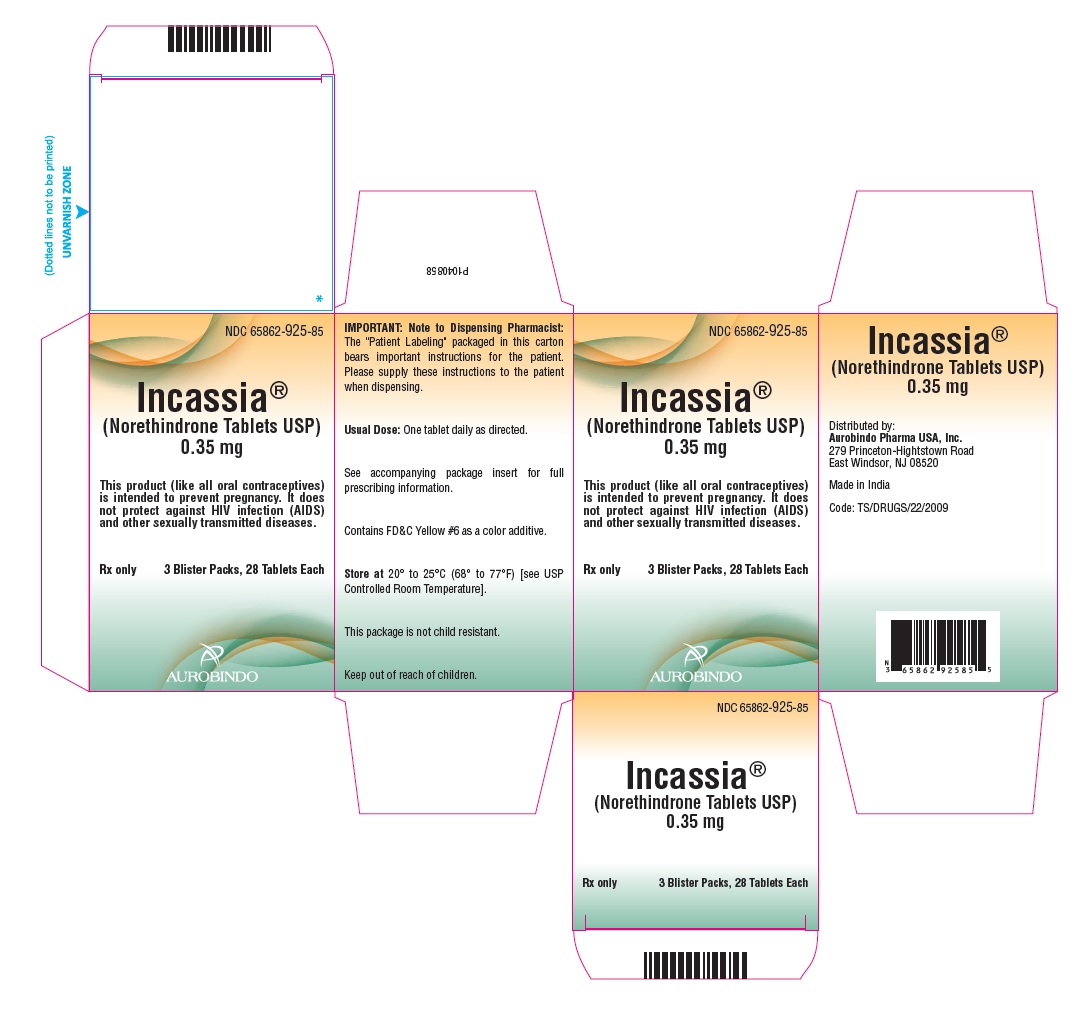
Incassia NORETHINDRONE .35 mg Tablet, 1 tablet
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Norethindrone is used to treat endometriosis (a condition in which the type of tissue that lines the uterus [womb] grows in other areas of the body and causes pain, heavy or irregular menstruation [periods], and other symptoms). Norethindrone is also used to treat abnormal periods or bleeding and to bring on a normal menstrual cycle in women who menstruated normally in the past but have not menstruated for at least 3 months and who are not pregnant or experiencing menopause (change of life; the end of monthly menstrual periods). Norethindrone is in a class of medications called progestins. It...
Read the full MedlinePlus article ↗- It depends on the product. Most norethindrone tablets — including brands like Camila, Errin, Emzahh, and Affodel — are progestin-only birth control pills taken daily to prevent pre...
- Regular combination birth control pills contain two hormones — estrogen and progestin. Norethindrone is a progestin-only pill, sometimes called the 'mini-pill.' Because it has no e...
- How is this different from regular birth control pills?
- The most common thing people notice is irregular bleeding — spotting between periods, or changes in your cycle. Headache, breast tenderness, nausea, and dizziness are also reported...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Norethindrone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.091 | $0.09 / 1 tablet |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1560 | $0.16 / 1 tablet |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Camila .35 mg 51862-0884-03 | Mayne | 84 tablets | $0.091 | AB1 | Discontinued | — |
| Errin .35 mg 51862-0886-03 | Mayne | 84 tablets | $0.091 | AB2 | Discontinued | — |
| Incassia .35 mgthis 65862-0925-28 | Aurobindo | 1 tablet | $0.091 | AB1 | Availability likely | — |
| Lyleq .35 mg 50102-0300-13 | Afaxys | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Emzahh .35 mg 59651-0136-28 | Aurobindo | 1 tablet | $0.091 | AB2 | Availability likely | — |
| Meleya .35 mg 70700-0317-85 | Xiromed | 84 tablets | $0.091 | AB2 | Availability likely | — |
| Norethindrone .35 mg 68462-0305-29 | Glenmark | 84 tablets | $0.091 | AB2 | Availability likely | — |
| Norethindrone .35 mg 00378-7292-53 | Mylan | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Orquidea .35 mg 70700-0316-85 | Xiromed, | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Camila .35 mg 75907-0074-32 | Dr. | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Norethindrone .35 mg 68180-0876-73 | Lupin | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Jencycla .35 mg 68180-0877-73 | Lupin | 28 tablets | $0.091 | AB2 | Availability likely | — |
| Heather .35 mg 68462-0303-29 | Glenmark | 84 tablets | $0.091 | AB1 | Availability likely | — |
| Nora BE .35 mg 00480-3475-16 | Teva | 168 tablets | $0.091 | AB1 | Availability likely | — |
| Errin .35 mg 75907-0075-32 | Dr. | 84 tablets | $0.091 | AB2 | Availability likely | — |
| Nora BE .35 mg 52544-0629-28 | Actavis | 168 tablets | $0.094 | AB1 | Discontinued | +4% |
| Norethindrone .35 mg 63187-0748-28 | Proficient | 28 tablets | — | AB2 | FDA listed | — |
| Errin .35 mg 71205-0526-28 | Proficient | 28 tablets | — | AB2 | FDA listed | — |
| Norethindrone .35 mg 60505-4900-08 | Apotex | 84 tablets | — | AB1 | FDA listed | — |
| Affodel .35 mg 79929-0015-07 | Naari | 2352 tablets | — | AB1 | FDA listed | — |
| Norethindrone .35 mg 82804-0175-28 | Proficient | 28 tablets | — | AB1 | FDA listed | — |
| Norethindrone .35 mg 50090-6161-00 | A-S | 28 tablets | — | AB1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0925-28 You're viewing this | 1 BLISTER PACK in 1 CARTON (65862-925-28) / 1 TABLET in 1 BLISTER PACK | $0.0907 / ea | $0.09 | 2016-09-23 | Active |
| 65862-0925-85 | 3 BLISTER PACK in 1 CARTON (65862-925-85) / 1 TABLET in 1 BLISTER PACK | $0.0907 / ea | $0.27 | 2016-09-23 | Active |
| 65862-0925-86 | 6 BLISTER PACK in 1 CARTON (65862-925-86) / 1 TABLET in 1 BLISTER PACK | — | — | 2016-09-23 | Active |
| 65862-0925-87 | 1 POUCH in 1 CARTON (65862-925-87) / 1 TABLET in 1 POUCH | — | — | 2016-09-23 | Active |
| 65862-0925-88 | 3 POUCH in 1 CARTON (65862-925-88) / 1 TABLET in 1 POUCH | — | — | 2016-09-23 | Active |
| 65862-0925-92 | 6 POUCH in 1 CARTON (65862-925-92) / 1 TABLET in 1 POUCH | — | — | 2016-09-23 | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.0907 NADAC).
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0925-28?
What is the difference between NDC 65862-0925-28 and NDC 65862-0925-87?
What NDC number is used to bill for this package of Incassia NORETHINDRONE .35 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE 1. Indications Progestin - only oral contraceptives are indicated for the prevention of pregnancy. 2.
Efficacy If used perfectly, the first-year failure rate for progestin - only oral contraceptives is 0.5%. However, the typical failure rate is estimated to be closer to 5%, due to late or omitted pills. The following table lists the pregnancy rates for users of all major methods of contraception.
Table 2: Percentage of Women Experiencing an Unintended Pregnancy During the First Year of Typical Use and the First Year of Perfect Use of Contraception and the Percentage Continuing Use at the End of the First Year. United States. % of Women Experiencing an Unintended Pregnancy within the First Year of Use % of Women Continuing Use at One Year 3 Method (1) Typical Use 1 (2) Perfect Use 2 (3) (4) Chance 4 85 85 Spermicides 5 26 6 40 Periodic abstinence 25 63 Calendar 9 Ovulation Method 3 Sympto-Thermal 6 2 Post-Ovulation 1 Cap 7 Parous Women 40 26 42 Nulliparous Women 20 9 56 Sponge Parous Women 40 20 42 Nulliparous Women 20 9 56 Diaphragm 7 20 6 56 Withdrawal 19 4 Condom 8 Female (Reality) 21 5 56 Male 14 3 61 Pill 5 71 Progestin only
0.5 Combined
0.1IUDs Progesterone T 2 1.5 81 Copper T380A 0.8 0.6 78 LNg20 0.1 0.1 81 Depo-Provera ® 0.3 0.3 70 Levonorgestrel Implants (Norplant ® ) 0.05 0.05 88 Female Sterilization 0.5 0.5 100 Male Sterilization 0.15 0.1 100 Emergency Contraceptive Pills Treatment initiated within 72 hours after unprotected intercourse reduces the risk of pregnancy by at least 75%. 9 Lactational Amenorrhea Method LAM is a highly effective, temporary method of contraception. 10 Source: Trussell, J, Contraceptive Efficacy.
In: Hatcher RA, Trussell J, Stewart F, Cates W, Stewart GK, Kowal D, Guest F, Contraceptive Technology: Seventeenth Revised Edition. New York NY: Irvington Publishers, 1998. Among typical couples who initiate use of a method (not necessarily for the first time), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any reason.
Among couples who initiate use of a method (not necessarily for the first time), and who use it perfectly (both consistently and correctly), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. Among couples attempting to avoid pregnancy, the percentage who continue to use a method for one year. The percentage of women becoming pregnant noted in columns (2) and (3) are based on data from populations where contraception is not used and from women who cease using contraception in order to become pregnant.
Among such populations, about 89% become pregnant within one year. This estimate was lowered slightly (to 85%) to represent the percentage that would become pregnant within one year among women now relying on reversible methods of contraception if they abandoned contraception altogether. Foams, creams, gels, vaginal suppositories, and vaginal film.
Cervical mucus (ovulation) method supplemented by calendar in the pre-ovulatory and basal body temperature in the post-ovulatory phases. With spermicidal cream or jelly. Without spermicides.
The treatment schedule is one dose within 72 hours after unprotected intercourse, and a second dose 12 hours after the first dose. The Food and Drug Administration has declared the following brands of oral contraceptives to be safe and effective for emergency contraception: Ovral ® (1 dose is 2 white pills), Alesse ® (1 dose is 5 pink pills), Nordette ® or Levlen ® (1 dose is 4 yellow pills). However, to maintain effective protection against pregnancy, another method of contraception must be used as soon as menstruation resumes, the frequency or duration of breastfeeds is reduced, bottle feeds are introduced, or the baby reaches 6 months of age.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Incassia tablets must be taken exactly as directed. One tablet is taken every day, at the same time. Administration is continuous, with no interruption between pill packs. See PATIENT LABELING for detailed instructions.
⛔ Contraindications ▾
CONTRAINDICATIONS Progestin - only oral contraceptives (POPs) should not be used by women who currently have the following conditions: Known or suspected pregnancy Known or suspected carcinoma of the breast Undiagnosed abnormal genital bleeding Hypersensitivity to any component of this product Benign or malignant liver tumors Acute liver disease
⚠️ Warnings ▾
WARNINGS Cigarette smoking greatly increases the possibility of suffering heart attacks and strokes. Women who use oral contraceptives are strongly advised not to smoke. Incassia does not contain estrogen and, therefore, this insert does not discuss the serious health risks that have been associated with the estrogen component of combined oral contraceptives.
The health care provider is referred to the prescribing information of combined oral contraceptives for a discussion of those risks, including, but not limited to, an increased risk of serious cardiovascular disease in women who smoke, carcinoma of the breast and reproductive organs, hepatic neoplasia, and changes in carbohydrate and lipid metabolism. The relationship between progestin-only oral contraceptives and these risks have not been established and there are no studies definitely linking progestin - only pill (POP) use to an increased risk of heart attack or stroke.
The physician should remain alert to the earliest manifestation of symptoms of any serious disease and discontinue oral contraceptive therapy when appropriate. 1 . Ectopic Pregnancy The incidence of ectopic pregnancies for progestin - only oral contraceptive users is 5 per 1000 woman-years.
Up to 10% of pregnancies reported in clinical studies of progestin-only oral contraceptive users are extrauterine. Although symptoms of ectopic pregnancy should be watched for, a history of ectopic pregnancy need not be considered a contraindication to use of this contraceptive method. Health providers should be alert to the possibility of an ectopic pregnancy in women who become pregnant or complain of lower abdominal pain while on progestin-only oral contraceptives.
2. Delayed Follicular Atresia/Ovarian Cysts If follicular development occurs, atresia of the follicle is sometimes delayed, and the follicle may continue to grow beyond the size it would attain in a normal cycle. Generally these enlarged follicles disappear spontaneously.
Often they are asymptomatic; in some cases they are associated with mild abdominal pain. Rarely they may twist or rupture, requiring surgical intervention. 3.
Irregular Genital Bleeding Irregular menstrual patterns are common among women using progestin-only oral contraceptives. If genital bleeding is suggestive of infection, malignancy or other abnormal conditions, such nonpharmacologic causes should be ruled out. If prolonged amenorrhea occurs, the possibility of pregnancy should be evaluated.
4 . Carcinoma of the Breast and Reproductive Organs Some epidemiologic studies of oral contraceptive users have reported an increased relative risk of developing breast cancer, particularly at a younger age and apparently related to duration of use. These studies have predominantly involved combined oral contraceptives and there is insufficient data to determine whether the use of POPs similarly increase the risk.
Women with breast cancer should not use oral contraceptives because the role of female hormone in breast cancer has not been fully determined. Some studies suggest that oral contraceptive use has been associated with an increase in the risk of cervical intraepithelial neoplasia in some populations of women. However, there continues to be controversy about the extent to which such findings may be due to differences in sexual behavior and other factors.
There is insufficient data to determine whether the use of POPs increases the risk of developing cervical intraepithelial neoplasia. 5. Hepatic Neoplasia Benign hepatic adenomas are associated with combined oral contraceptive use, although the incidence of benign tumors is rare in the United States.
Rupture of benign, hepatic adenomas may cause death through intraabdominal hemorrhage. Studies from Britain and the U.S. have shown an increased risk of developing hepatocellular carcinoma in combined oral contraceptive users. However, these cancers are rare.
There is insufficient data to determine whether POPs increase the risk of developing…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Menstrual irregularity is the most frequently reported side effect. Frequent and irregular bleeding are common, while long duration of bleeding episodes and amenorrhea are less likely. Headache, breast tenderness, nausea, and dizziness are increased among progestin-only oral contraceptive users in some studies. Androgenic side effects such as acne, hirsutism, and weight gain occur rarely.
🆘 Overdosage ▾
OVERDOSAGE There have been no reports of serious ill effects from overdosage, including ingestion by children.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY 1. Mode of Action Incassia progestin-only oral contraceptives prevent conception by suppressing ovulation in approximately half of users, thickening the cervical mucus to inhibit sperm penetration, lowering the mid-cycle LH and FSH peaks, slowing the movement of the ovum through the fallopian tubes, and altering the endometrium. 2.
Pharmacokinetics Absorption Norethindrone is rapidly absorbed with maximum plasma concentrations occurring within 1 to 2 hours after Incassia administration (see Table 1). Norethindrone appears to be completely absorbed following oral administration; however, it is subject to first pass metabolism resulting in an absolute bioavailability of approximately 65%. Peak plasma concentrations occur approximately 1 hour after administration (mean T max 1.2 hours).
The mean (SD) C max was 4816.8 (1532.6) pg/mL and generally occurred within 1 hour (mean) of tablet administration, ranging from 0.5 to 2 hours. The mean (SD) C avg was 885 (250) pg/mL, however, the mean concentration at 24 hrs was 130 (47) pg/mL. Table 1 provides summary statistics of the pharmacokinetic parameters associated with single dose Incassia administration.
Table 1: Mean ± SD Pharmacokinetic Parameters Following Single Dose Administration of Incassia in 12 Healthy Female Subjects Under Fasting Conditions Pharmacokinetic Parameter Norethindrone 0.35 mg T max (hr) C max (pg/mL) AUC (0 - 48) (pg·h/mL) t½ (h) 1.2 ± 0.5 4817 ± 1533 21233 ± 6002 7.7 ±
0.5The food effect on the rate and extent of norethindrone absorption after Incassia administration has not been evaluated. Distribution Following oral administration, norethindrone is 36% bound to sex hormone-binding globulin (SHBG) and 61% bound to albumin. Volume of distribution of norethindrone is approximately 4 L/kg.
Metabolism Norethindrone undergoes extensive biotransformation, primarily via reduction, followed by sulfate and glucuronide conjugation; less than 5% of a norethindrone dose is excreted unchanged; greater than 50% and 20 to 40% of a dose is excreted in urine and feces, respectively. The majority of metabolites in the circulation are sulfate, with glucuronides accounting for most of the urinary metabolites. Excretion Plasma clearance rate for norethindrone has been estimated to be approximately 600 L/day.
Norethindrone is excreted in both urine and feces, primarily as metabolites. The mean terminal elimination half-life of norethindrone following single dose administration of Incassia is approximately 8 hours. Figure 1: Mean ± SD Norethindrone Plasma Concentrations Following Norethindrone Administration
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Incassia ( Norethindrone Tablets USP, 0.35 mg) are light yellow to yellow, round, flat faced beveled edge tablets, debossed with ‘S’ on one side and ‘14’ on other side of the tablet and are available in Blister Pack Containing 28 tablets. The blister packs are available in the following packages: The Blister Packs are packed in Pouches and the pouches are packaged in cartons Carton of 1 Pouch NDC 65862-925-87 Carton of 3 Pouches NDC 65862-925-88 Carton of 6 Pouches NDC 65862-925-92 The Blister Packs are packed in cartons Carton of 1 Blister Pack NDC 65862-925-28 Carton of 3 Blister Packs NDC 65862-925-85 Carton of 6 Blister Packs NDC 65862-925-86 STORAGE Store at controlled room temperature 20° to 25°C (68° to 77° F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Each light yellow to yellow Incassia ® tablet provides a continuous oral contraceptive regimen of 0.35 mg norethindrone USP daily, and the inactive ingredients include corn starch, D&C Yellow No. 10 aluminum lake, FD&C Yellow # 6 aluminum lake, lactose monohydrate, magnesium stearate, povidone and talc. The chemical name for norethindrone is 17-Hydroxy-19-Nor-17α-pregn-4-en-20-yn-3-one. The structural formula follows: Chemical Structure
💬 Information for Patients ▾
INFORMATION FOR THE PATIENT 1. See PATIENT LABELING for detailed information. 2.
Counseling Issues The following points should be discussed with prospective users before prescribing progestin-only oral contraceptives: The necessity of taking pills at the same time every day, including throughout all bleeding episodes. The need to use a backup method such as condoms and spermicides for the next 48 hours whenever a progestin-only oral contraceptive is taken 3 or more hours late. The potential side effects of progestin-only oral contraceptives, particularly menstrual irregularities.
The need to inform the clinician of prolonged episodes of bleeding, amenorrhea or severe abdominal pain. The importance of using a barrier method in addition to progestin-only oral contraceptives if a woman is at risk of contracting or transmitting STDs/HIV.