
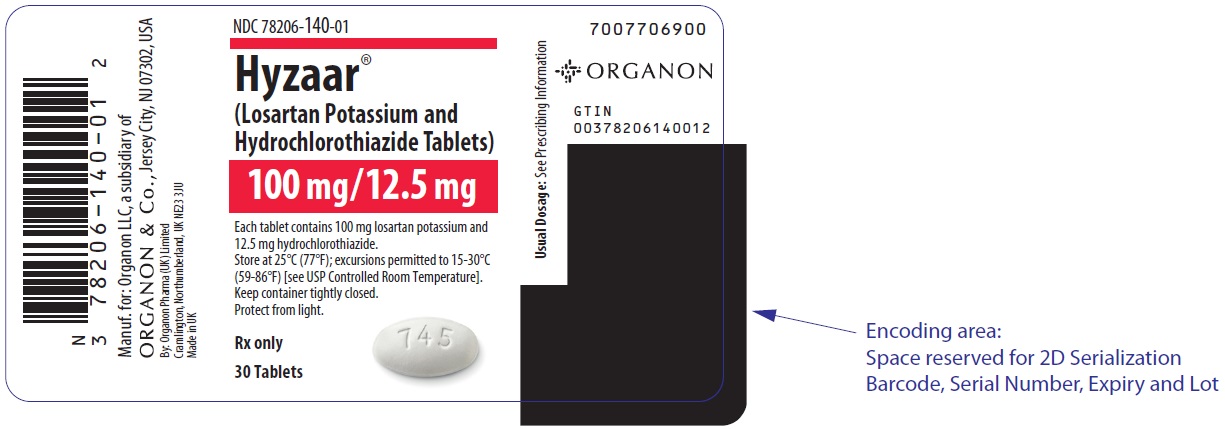
HYZAAR losartan potassium and hydrochlorothiazide 100 mg; 12.5 mg Tablet, Film Coated, 90-count
Other active recalls for Losartan Potassium And Hydrochlorothiazide (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin 2 Receptor Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's working in two ways at once to lower your blood pressure. Losartan relaxes your blood vessels by blocking a hormone called angiotensin II that would otherwise tighten them. Hy...
- What exactly is this medication doing for me?
- You can take it with or without food — a meal won't significantly change how well it works. Picking a consistent time each day (morning is common) helps you remember it and keeps y...
- Can I take this with food, and does it matter what time of day I take it?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $6.820 | $613.80 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $5.08 | $457.24 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 78206-0140-01 | 30 TABLET, FILM COATED in 1 BOTTLE (78206-140-01) | $6.82 / ea | $204.60 | 2021-06-01 | Active |
| 78206-0140-02 You're viewing this | 90 TABLET, FILM COATED in 1 BOTTLE (78206-140-02) | $6.82 / ea | $613.80 | 2021-06-01 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($6.82 NADAC).
Pack size FAQ
What quantity is in NDC 78206-0140-02?
What is the difference between NDC 78206-0140-02 and NDC 78206-0140-01?
What NDC number is used to bill for this package of HYZAAR losartan potassium and hydrochlorothiazide 100 mg; 12.5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue HYZAAR as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions (5.1) ] . WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue HYZAAR as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE HYZAAR is a combination of losartan, an angiotensin II receptor blocker (ARB) and hydrochlorothiazide, a diuretic indicated for: Treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.1 ) Reduction of the risk of stroke in patients with hypertension and left ventricular hypertrophy.
There is evidence that this benefit does not apply to Black patients. ( 1.2 )
1.1Hypertension HYZAAR ® is indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure lowers the risk of fatal and non-fatal cardiovascular (CV) events, primarily strokes and myocardial infarction. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including losartan and hydrochlorothiazide.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in Black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. This fixed dose combination is not indicated for initial therapy of hypertension, except when the hypertension is severe enough that the value of achieving prompt blood pressure control exceeds the risk of initiating combination therapy in these patients [see Clinical Studies (14) and Dosage and Administration (2.1) ] .
HYZAAR may be administered with other antihypertensive agents.
1.2Hypertensive Patients with Left Ventricular Hypertrophy HYZAAR is indicated to reduce the risk of stroke in patients with hypertension and left ventricular hypertrophy, but there is evidence that this benefit does not apply to Black patients. [See Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) , and Dosage and Administration (2.2) .]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension Usual starting dose: 50/12.5 mg once daily. ( 2.1 ) Titrate as needed to a maximum dose of 100/25 mg. ( 2.1 ) Hypertensive Patients with Left Ventricular Hypertrophy Not controlled on monotherapy: Initiate with 50/12.5 mg. Titrate as needed to a maximum of 100/25 mg. ( 2.2 )
2.1Hypertension The usual starting dose of HYZAAR is 50/12.5 (losartan 50 mg/hydrochlorothiazide 12.5 mg) once daily. The dosage can be increased after 3 weeks of therapy to a maximum of 100/25 (losartan 100 mg/hydrochlorothiazide 25 mg) once daily as needed to control blood pressure [see Clinical Studies (14.2) ] . Initiate a patient whose blood pressure is not adequately controlled with losartan 50 mg monotherapy with HYZAAR 50/12.5 once daily.
If blood pressure remains uncontrolled after about 3 weeks of therapy, the dosage may be increased to two tablets of HYZAAR 50/12.5 once daily or one tablet of HYZAAR 100/25 once daily. Initiate a patient whose blood pressure is not adequately controlled with losartan 100 mg monotherapy with HYZAAR 100/12.5 (losartan 100 mg/hydrochlorothiazide 12.5 mg) once daily. If blood pressure remains uncontrolled after about 3 weeks of therapy, increase the dose to two tablets of HYZAAR 50/12.5 once daily or one tablet of HYZAAR 100/25 once daily.
Initiate a patient whose blood pressure is inadequately controlled with hydrochlorothiazide 25 mg once daily, or is controlled but who experiences hypokalemia with this regimen, on HYZAAR 50/12.5 once daily, reducing the dose of hydrochlorothiazide without reducing the overall expected antihypertensive response. Evaluate the clinical response to HYZAAR 50/12.5 and, if blood pressure remains uncontrolled after about 3 weeks of therapy, increase the dose to two tablets of HYZAAR 50/12.5 once daily or one tablet of HYZAAR 100/25 once daily.
2.2Hypertensive Patients with Left Ventricular Hypertrophy In patients whose blood pressure is not adequately controlled on 50 mg losartan potassium, initiate treatment with HYZAAR 50/12.5. If additional blood pressure reduction is needed, increase the dose to HYZAAR 100/12.5, followed by HYZAAR 100/25. For further blood pressure reduction add other antihypertensives [see Clinical Studies (14) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS HYZAAR 50/12.5 are yellow, oval, film-coated tablets, with code 717 on one side. HYZAAR 100/12.5 are white, oval, film-coated tablets, with code 745 on one side. HYZAAR 100/25 are light yellow, oval, film-coated tablets, with code 747 on one side. Tablets (losartan potassium/hydrochlorothiazide content): 50/12.5 mg; 100/12.5 mg; and 100/25 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS HYZAAR is contraindicated: In patients who are hypersensitive to any component of this product. In patients with anuria For coadministration with aliskiren in patients with diabetes Hypersensitivity to any component of HYZAAR. ( 4 ) Anuria. ( 4 ) Coadministration with aliskiren in patients with diabetes. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume or salt depletion prior to administration of HYZAAR. ( 5.2 ) Monitor renal function and potassium in susceptible patients. ( 5.3 ) Observe for clinical signs of fluid or electrolyte imbalance. ( 5.5 ) Acute angle-closure glaucoma. ( 5.6 ) Exacerbation of systemic lupus erythematosus. ( 5.7 )
5.1Fetal Toxicity HYZAAR can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue HYZAAR as soon as possible. Thiazides cross the placental barrier and appear in cord blood.
Adverse reactions include fetal or neonatal jaundice, thrombocytopenia [see Use in Specific Populations (8.1) ] .
5.2Hypotension in Volume- or Salt-Depleted Patients In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients (e.g., those being treated with high doses of diuretics), symptomatic hypotension may occur after initiation of treatment with HYZAAR. Correct volume or salt depletion prior to administration of HYZAAR. Do not use HYZAAR as initial therapy in patients with intravascular volume depletion.
5.3Impaired Renal Function Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on HYZAAR. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on HYZAAR [see Drug Interactions (7.3) and Use in Specific Populations (8.8) ] .
5.4Hypersensitivity Hypersensitivity reactions to hydrochlorothiazide may occur in patients with or without a history of allergy or bronchial asthma but are more likely in patients with such a history [see Adverse Reactions (6.2) ] .
5.5Electrolyte and Metabolic Effects In double-blind clinical trials of various doses of losartan potassium and hydrochlorothiazide, the incidence of hypertensive patients who developed hypokalemia (serum potassium <3.5 mEq/L) was 6.7% versus 3.5% for placebo; the incidence of hyperkalemia (serum potassium >5.7 mEq/L) was 0.4% versus 0% for placebo. HYZAAR contains hydrochlorothiazide which can cause hypokalemia, hyponatremia and hypomagnesemia. Hypomagnesemia can result in hypokalemia which may be difficult to treat despite potassium repletion.
HYZAAR also contains losartan which can cause hyperkalemia. Monitor serum electrolytes periodically [see Drug Interactions (7.1) ] . Concomitant use of other drugs that may increase serum potassium may lead to hyperkalemia [see Drug Interactions (7.1) ] .
Hydrochlorothiazide may alter glucose tolerance and raise serum levels of cholesterol and triglycerides. Hyperuricemia may occur or frank gout may be precipitated in patients receiving thiazide therapy. Because losartan decreases uric acid, losartan in combination with hydrochlorothiazide attenuates the diuretic-induced hyperuricemia.
Hydrochlorothiazide decreases urinary calcium excretion and may cause elevations of serum calcium. Monitor calcium levels.
5.6Acute Myopia and Secondary Angle-Closure Glaucoma Hydrochlorothiazide, a sulfonamide, can cause an idiosyncratic reaction, resulting in acute transient myopia and acute angle-closure glaucoma. Symptoms include acute onset of decreased visual acuity or ocular pai…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥2% and greater than placebo) are dizziness, upper respiratory infection, cough, and back pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Losartan potassium-hydrochlorothiazide has been evaluated for safety in 858 patients treated for essential hypertension and 3889 patients treated for hypertension and left ventricular hypertrophy. Most adverse reactions have been mild and transient in nature and have not required discontinuation of therapy.
In controlled clinical trials, discontinuation of therapy due to clinical adverse events was required in only 2.8% and 2.3% of patients treated with the combination and placebo, respectively. In these double-blind controlled clinical trials, adverse reactions occurring in greater than 2% of subjects treated with losartan-hydrochlorothiazide and at a greater rate than placebo were: back pain (2.1% vs 0.6%), dizziness (5.7% vs 2.9%), and upper respiratory infection (6.1% vs 4.6%). The following additional adverse reactions have been reported in clinical trials with HYZAAR and/or the individual components: Blood and the lymphatic system disorders: Anemia, aplastic anemia, hemolytic anemia, leukopenia, agranulocytosis.
Metabolism and nutrition disorders: Anorexia, hyperglycemia, hyperuricemia, electrolyte imbalance including hyponatremia and hypokalemia. Psychiatric disorders: Insomnia, restlessness. Nervous system disorders: Dysgeusia, headache, migraine, paraesthesias.
Eye disorders: Xanthopsia, transient blurred vision. Cardiac disorders: Palpitation, tachycardia. Vascular disorders: Dose-related orthostatic effects, necrotizing angiitis (vasculitis, cutaneous vasculitis).
Respiratory, thoracic and mediastinal disorders: Nasal congestion. Gastrointestinal disorders: Dyspepsia, abdominal pain, gastric irritation, cramping, nausea, vomiting, pancreatitis, sialoadenitis. Hepato-biliary disorders: Jaundice (intrahepatic cholestatic jaundice).
Skin and subcutaneous tissue disorders: Rash, pruritus, purpura, toxic epidermal necrolysis, urticaria, photosensitivity, cutaneous lupus erythematosus. Musculoskeletal and connective tissue disorders: Muscle cramps, muscle spasm. Renal and urinary disorders: Glycosuria, renal dysfunction, interstitial nephritis, renal failure.
Reproductive system and breast disorders: Erectile dysfunction/impotence. General disorders and administration site conditions: Chest pain, malaise, weakness. Investigations: Liver function abnormalities.
Cough Persistent dry cough has been associated with ACE-inhibitor use and in practice can be a cause of discontinuation of ACE-inhibitor therapy. Two prospective, parallel-group, double-blind, randomized, controlled trials were conducted to assess the effects of losartan on the incidence of cough in hypertensive patients who had experienced cough while receiving ACE-inhibitor therapy. Patients who had typical ACE-inhibitor cough when challenged with lisinopril, whose cough disappeared on placebo, were randomized to losartan 50 mg, lisinopril 20 mg, or either placebo (one study, n=97) or 25 mg hydrochlorothiazide (n=135).
The double-blind treatment period lasted up to 8 weeks. The incidence of cough is shown in Table 1 below. Table 1: Study 1 Demographics = (89% Caucasian, 64% female) HCTZ Losartan Lisinopril Cough 25% 17% 69% Study 2 Demographics = (90% Caucasian, 51% female) Placebo Losartan Lisinopril Cough 35% 29% 62% These studies demonstrate that the incidence of cough associated with losartan therapy, in a population that all had cough associated with A…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Agents increasing serum potassium: Risk of hyperkalemia. ( 7.1 ) Lithium: Risk of lithium toxicity. ( 7.2 ) Non-Steroidal Anti-Inflammatory Drugs (NSAIDs): increased risk of renal impairment and reduced diuretic, natriuretic, and antihypertensive effects.
( 7.3 ) Dual inhibition of the renin-angiotensin system: increased risk of renal impairment, hypotension, syncope, and hyperkalemia. ( 7.4 ) Antidiabetic drugs: dosage adjustment of antidiabetic may be required. ( 7.5 ) Cholestyramine and colestipol: Reduced absorption of thiazides.
( 7.5 )
7.1Agents Increasing Serum Potassium Coadministration of losartan with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
7.2Lithium Increases in serum lithium concentrations and lithium toxicity have been reported with concomitant use of angiotensin II receptor antagonists or thiazide diuretics. Monitor lithium levels in patients receiving HYZAAR and lithium.
7.3Non-Steroidal Anti-Inflammatory Agents Including Selective Cyclooxygenase-2 Inhibitors Losartan Potassium In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists (including losartan) may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving losartan and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including losartan, may be attenuated by NSAIDs, including selective COX-2 inhibitors. Hydrochlorothiazide The administration of a non-steroidal anti-inflammatory agent including a selective COX-2 inhibitor can reduce the diuretic, natriuretic, and antihypertensive effects of loop, potassium-sparing and thiazide diuretics. Therefore, when HYZAAR and non-steroidal anti-inflammatory agents including selective COX-2 inhibitors are used concomitantly, observe closely to determine if the desired effect of the diuretic is obtained.
In patients receiving diuretic therapy, coadministration of NSAIDs with angiotensin receptor blockers, including losartan, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving hydrochlorothiazide, losartan, and NSAID therapy.
7.4Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, syncope, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The Veterans Affairs Nephropathy in Diabetes (VA NEPHRON-D) trial enrolled 1448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratio, and decreased estimated glomerular filtration rate (GFR 30 to 89.9 mL/min), randomized them to lisinopril or placebo on a background of losartan therapy and followed them for a median of 2.2 years.
Patients receiving the combination of losartan and lisinopril did not obtain any additional benefit compared to monotherapy for the combined endpoint of decline in GFR, end-stage renal disease, or death, but experienced an increased incidence of hyperkalemia and acute kidney injury compared with the monotherapy group. Closely monitor blood pressure, renal function, and electrolytes in patients on HYZAAR and other agents that affect the RAS. Do not coadminister aliskiren with HYZAAR in patients with diabetes.
Avoid use of aliskiren with HYZAAR in patients with renal impairment (GFR <60 mL/min).
7.5The Use of Hydrochlorothiazide with Other Drugs When administered concurrently, the following drugs may interact with thiazide diuretics [see Clinical Pharmacology (12.3) ]: Antidiabetic drugs (oral agents and…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Hepatic Impairment: HYZAAR is not recommended for initial therapy, because the recommended starting dose is not available. ( 8.7 )
8.1Pregnancy Risk Summary HYZAAR can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue HYZAAR as soon as possible (see Clinical Considerations ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Losartan: Use of drugs that act on the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: oligohydramnios, reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue HYZAAR, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of gestation.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to HYZAAR for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to HYZAAR, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide: Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not alter the course of pre-eclampsia, these drugs should not be used to treat hypertension in pregnant women.
The use of hydrochlorothiazide for other indications in pregnancy should be avoided. Data Animal Data There was no evidence of teratogenicity in rats or rabbits treated with a maximum losartan potassium dose of 10 mg/kg/day in combination with 2.5 mg/kg/day of hydrochlorothiazide. At these dosages, respective exposures (AUCs) of losartan, its active metabolite, and hydrochlorothiazide in rabbits were approximately 5, 1.5, and 1.0 times those achieved in humans with 100 mg losartan in com…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary HYZAAR can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue HYZAAR as soon as possible (see Clinical Considerations ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Losartan: Use of drugs that act on the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: oligohydramnios, reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue HYZAAR, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of gestation.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to HYZAAR for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to HYZAAR, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Hydrochlorothiazide: Thiazides can cross the placenta, and concentrations reached in the umbilical vein approach those in the maternal plasma. Hydrochlorothiazide, like other diuretics, can cause placental hypoperfusion.
It accumulates in the amniotic fluid, with reported concentrations up to 19 times higher than in umbilical vein plasma. Use of thiazides during pregnancy is associated with a risk of fetal or neonatal jaundice or thrombocytopenia. Since they do not alter the course of pre-eclampsia, these drugs should not be used to treat hypertension in pregnant women.
The use of hydrochlorothiazide for other indications in pregnancy should be avoided. Data Animal Data There was no evidence of teratogenicity in rats or rabbits treated with a maximum losartan potassium dose of 10 mg/kg/day in combination with 2.5 mg/kg/day of hydrochlorothiazide. At these dosages, respective exposures (AUCs) of losartan, its active metabolite, and hydrochlorothiazide in rabbits were approximately 5, 1.5, and 1.0 times those achieved in humans with 100 mg losartan in combination with 25 mg hydrochlorothiazide.
AUC values for losartan, its active metabolite and hydrochlorothiazide, extrapolated from data obtained with losartan ad…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of HYZAAR in pediatric patients have not been established. Neonates with a history of in utero exposure to HYZAAR: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusion or dialysis may be required as means of reversing hypotension and/or substituting for disordered renal function.
🧓 Geriatric Use ▾
8.5Geriatric Use In a controlled clinical study for the reduction in the combined risk of cardiovascular death, stroke and myocardial infarction in hypertensive patients with left ventricular hypertrophy, 2857 patients (62%) were 65 years and over, while 808 patients (18%) were 75 years and over. In an effort to control blood pressure in this study, patients were coadministered losartan and hydrochlorothiazide 74% of the total time they were on study drug. No overall differences in effectiveness were observed between these patients and younger patients.
Adverse events were somewhat more frequent in the elderly compared to non-elderly patients for both the losartan-hydrochlorothiazide and the control groups [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Losartan Potassium Significant lethality was observed in mice and rats after oral administration of 1000 mg/kg and 2000 mg/kg, respectively, about 44 and 170 times the maximum recommended human dose on a mg/m 2 basis. Limited data are available in regard to overdosage in humans. The most likely manifestation of overdosage would be hypotension and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation.
If symptomatic hypotension should occur, supportive treatment should be instituted. Neither losartan nor its active metabolite can be removed by hemodialysis. Hydrochlorothiazide The oral LD 50 of hydrochlorothiazide is greater than 10 g/kg in both mice and rats.
The most common signs and symptoms observed are those caused by electrolyte depletion (hypokalemia, hypochloremia, hyponatremia) and dehydration resulting from excessive diuresis. If digitalis has also been administered, hypokalemia may accentuate cardiac arrhythmias. The degree to which hydrochlorothiazide is removed by hemodialysis has not been established.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Losartan Potassium Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)], is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis. Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor.
The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor. Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic.
Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is unknown.
12.2Pharmacodynamics Losartan Potassium Losartan inhibits the pressor effect of angiotensin II (as well as angiotensin I) infusions. A dose of 100 mg inhibits the pressor effect by about 85% at peak with 25-40% inhibition persisting for 24 hours. Removal of the negative feedback of angiotensin II causes a doubling to tripling in plasma renin activity and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Losartan does not affect the response to bradykinin, whereas ACE inhibitors increase the response to bradykinin. Aldosterone plasma concentrations fall following losartan administration. In spite of the effect of losartan on aldosterone secretion, very little effect on serum potassium was observed.
The effect of losartan is substantially present within one week but in some studies the maximal effect occurred in 3-6 weeks. In long-term follow-up studies (without placebo control) the effect of losartan appeared to be maintained for up to a year. There is no apparent rebound effect after abrupt withdrawal of losartan.
There was essentially no change in average heart rate in losartan-treated patients in controlled trials. Hydrochlorothiazide After oral administration of hydrochlorothiazide, diuresis begins within 2 hours, peaks in about 4 hours, and lasts about 6 to 12 hours. Drug Interactions Hydrochlorothiazide Alcohol, barbiturates, or narcotics — potentiation of orthostatic hypotension may occur.
Other antihypertensive drugs — additive effect or potentiation. Skeletal muscle relaxants, nondepolarizing (e.g., tubocurarine) — possible increased responsiveness to the muscle relaxant. Corticosteroids, ACTH, or glycyrrhizin (found in liquorice) — intensified elect…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Losartan Potassium Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)], is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis. Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor.
The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor. Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation. Hydrochlorothiazide Hydrochlorothiazide is a thiazide diuretic.
Thiazides affect the renal tubular mechanisms of electrolyte reabsorption, directly increasing excretion of sodium and chloride in approximately equivalent amounts. Indirectly, the diuretic action of hydrochlorothiazide reduces plasma volume, with consequent increases in plasma renin activity, increases in aldosterone secretion, increases in urinary potassium loss, and decreases in serum potassium. The renin-aldosterone link is mediated by angiotensin II, so coadministration of an angiotensin II receptor antagonist tends to reverse the potassium loss associated with these diuretics.
The mechanism of the antihypertensive effect of thiazides is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING HYZAAR is supplied as a film-coated tablet. Losartan/ Hydrochlorothiazide Color Shape Engraving NDC 78206-xxx-xx Bottle/ 30 Bottle/ 90 50/12.5 mg yellow oval 717 139-01 139-02 100/12.5 mg white oval 745 140-01 140-02 100/25 mg light yellow oval 747 141-01 141-02 Store at 77°F (25°C); excursions permitted to 59°F to 86°F (15°C to 30°C). Keep container tightly closed. Protect from light.
📦 Storage and Handling ▾
Store at 77°F (25°C); excursions permitted to 59°F to 86°F (15°C to 30°C). Keep container tightly closed. Protect from light.
📋 Description ▾
11 DESCRIPTION HYZAAR 50/12.5 (losartan potassium-hydrochlorothiazide), HYZAAR 100/12.5 (losartan potassium-hydrochlorothiazide) and HYZAAR 100/25 (losartan potassium-hydrochlorothiazide) tablets combine an angiotensin II receptor blocker acting on the AT 1 receptor subtype and a diuretic, hydrochlorothiazide. Losartan potassium, a non-peptide molecule, is chemically described as 2-butyl-4-chloro-1-[ p- ( o -1 H -tetrazol-5-ylphenyl)benzyl]imidazole-5-methanol monopotassium salt. Its empirical formula is C 22 H 22 ClKN 6 O, and its structural formula is: Losartan potassium is a white to off-white free-flowing crystalline powder with a molecular weight of 461.01.
It is freely soluble in water, soluble in alcohols, and slightly soluble in common organic solvents, such as acetonitrile and methyl ethyl ketone. Oxidation of the 5-hydroxymethyl group on the imidazole ring results in the active metabolite of losartan. Hydrochlorothiazide is 6-chloro-3,4-dihydro-2 H -1,2,4-benzothiadiazine-7-sulfonamide 1,1-dioxide.
Its empirical formula is C 7 H 8 ClN 3 O 4 S 2 and its structural formula is: Hydrochlorothiazide is a white, or practically white, crystalline powder with a molecular weight of 297.74, which is slightly soluble in water, but freely soluble in sodium hydroxide solution. HYZAAR is available for oral administration in three tablet combinations of losartan and hydrochlorothiazide. HYZAAR 50/12.5 contains 50 mg of losartan potassium and 12.5 mg of hydrochlorothiazide.
HYZAAR 100/12.5 contains 100 mg of losartan potassium and 12.5 mg of hydrochlorothiazide. HYZAAR 100/25 contains 100 mg of losartan potassium and 25 mg of hydrochlorothiazide. Inactive ingredients are microcrystalline cellulose, lactose hydrous, pregelatinized starch, magnesium stearate, hydroxypropyl cellulose, hypromellose, and titanium dioxide.
HYZAAR 50/12.5 and HYZAAR 100/25 also contain D&C yellow No. 10 aluminum lake. HYZAAR 50/12.5, HYZAAR 100/12.5, and HYZAAR 100/25 may also contain carnauba wax.
HYZAAR 50/12.5 contains 4.24 mg (0.108 mEq) of potassium, HYZAAR 100/12.5 contains 8.48 mg (0.216 mEq) of potassium, and HYZAAR 100/25 contains 8.48 mg (0.216 mEq) of potassium. Chemical Structure of Losartan Potassium Chemical Structure of Hydrochlorothiazide
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Pregnancy: Advise female patients of childbearing age about the consequences of exposure to HYZAAR during pregnancy. Discuss treatment options with women planning to become pregnant.
Tell patients to report pregnancies to their physicians as soon as possible [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ]. Symptomatic Hypotension: Advise patients that lightheadedness can occur, especially during the first days of therapy, and to report this symptom to a healthcare provider. Inform patients that dehydration from inadequate fluid intake, excessive perspiration, vomiting, or diarrhea may lead to an excessive fall in blood pressure.
If syncope occurs, advise patients to contact their healthcare provider [see Warnings and Precautions (5.2) ] . Potassium Supplements: Advise patients not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider [see Drug Interactions (7.1) ] . Acute Myopia and Secondary Angle-closure Glaucoma: Advise patients to discontinue HYZAAR and seek immediate medical attention if they experience symptoms of acute myopia or secondary angle-closure glaucoma [see Warnings and Precautions (5.6) ].
Non-melanoma Skin Cancer: Instruct patients taking hydrochlorothiazide to protect skin from the sun and undergo regular skin cancer screening.