
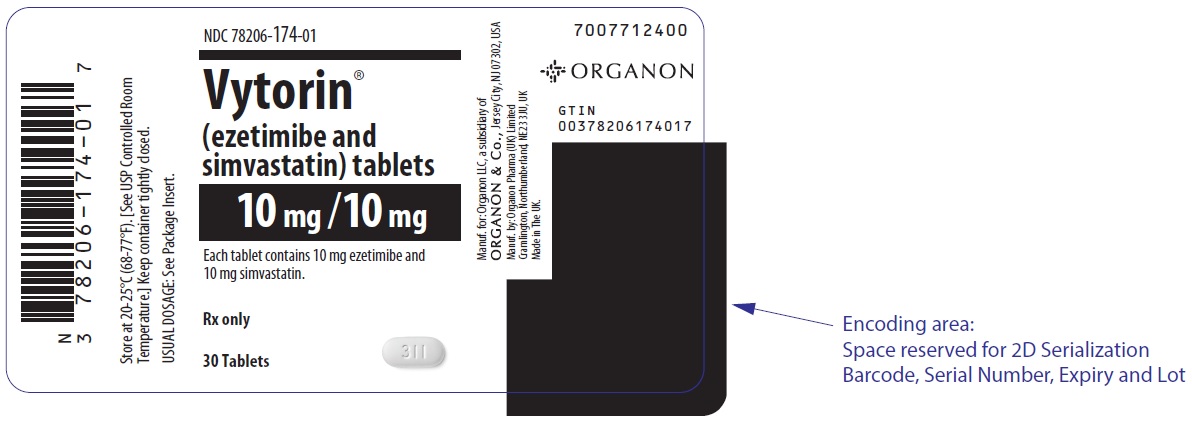
Vytorin ezetimibe and simvastatin 10 mg; 10 mg Tablet, 30-count — NDC 78206-174-01 (Billing 78206-0174-01)
This is a package of 30 tablets of Vytorin ezetimibe and simvastatin 10 mg; 10 mg Tablet from Organon LLC, marketed since Jun 2021 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
Other active recalls for Ezetimibe And Simvastatin (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 057859
- GCN: 23121
- GPI-14 (Medi-Span): 39994002300320
- HICL (First Databank): 026505
- AHFS class code: 24:06.05.00
- RxCUI (RxNorm): 476345
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Dietary Cholesterol Absorption Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Ezetimibe is used along with diet, alone or in combination with another cholesterol-lowering medications (HMG-CoA reductase inhibitors [statins]) to reduce the amount of low-density lipoprotein (LDL) cholesterol ('bad cholesterol') in the blood in adults and children 10 years of age or older who have familial heterozygous hypercholesterolemia (an inherited condition in which cholesterol cannot be removed from the body normally). It is also used along with diet, alone or in combination with other cholesterol-lowering medications (HMG-CoA reductase inhibitors [statins] or fenofibrate) in adults...
Read the full MedlinePlus article ↗- It lowers LDL cholesterol when diet alone hasn’t been enough. That includes high cholesterol and inherited forms. Vytorin’s simvastatin is also used to reduce heart attack, stroke...
- Take one tablet by mouth in the evening, with or without food. If you miss a dose, take it as soon as you remember, but don’t double up the next one. If you take cholestyramine or...
- Common ones are headache, muscle aches, diarrhea, cold-like symptoms and higher liver enzymes on blood tests. Most people do fine. Tell me or your doctor if anything bothers you.
- Call promptly for muscle pain, tenderness or weakness you can’t explain, especially with fever or feeling unwell. Also call for yellow skin or eyes, or signs of allergic reaction l...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $14.25 | $427.44 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 78206-0174-01 You're viewing this Main listing | 30 TABLET in 1 BOTTLE | 2021-06-01 | — | Active |
| 78206-0174-02 78206-174-02 | 90 TABLET in 1 BOTTLE | 2021-06-01 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 78206-0174-02?
What NDC number is used to bill for this package of Vytorin ezetimibe and simvastatin 10 mg; 10 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ezetimibe and Simvastatin 10 mg/1; 10 mg 43598-0742-10 | Dr.Reddys | 1000 tablets | $0.274 | AB | Availability likely | — |
| ezetimibe and simvastatin 10 mg/1; 10 mg 16714-0778-01 | NORTHSTAR | 30 tablets | $0.383 | AB | Discontinued | — |
| Ezetimibe and Simvastatin 10 mg/1; 10 mg 69238-1155-03 | Amneal | 30 tablets | $0.383 | — | Discontinued | — |
| Ezetimibe and Simvastatin 10 mg/1; 10 mg 51407-0190-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Ezetimibe and Simvastatin 10 mg/1; 10 mg 59651-0835-30 | Aurobindo | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe and Simvastatin 10 mg/1; 10 mg 67877-0507-01 | Ascend | 1000 tablets | — | AB | FDA listed | — |
| ezetimibe and simvastatin 10 mg/1; 10 mg 68462-0321-10 | Glenmark | 1000 tablets | — | AB | FDA listed | — |
| Vytorin 10 mg/1; 10 mgthis 78206-0174-01 | Organon | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 8D4SNN7V92
Propyl gallate is a synthetic antioxidant derived from gallic acid. It prevents oils and fats in the medicine from oxidizing and spoiling, helping the product stay stable and effective during storage.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE VYTORIN VYTORIN ® is a combination of simvastatin and ezetimibe indicated: As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia. In adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). As an adjunct to other LDL-C-lowering therapies to reduce elevated LDL-C in adults with homozygous familial hypercholesterolemia (HoFH).
Simvastatin Simvastatin, when used as a component of VYTORIN, is indicated to reduce the risk of total mortality by reducing risk of coronary heart disease death, non-fatal myocardial infarction and stroke, and the need for coronary and non-coronary revascularization procedures in adults with established coronary heart disease, cerebrovascular disease, peripheral vascular disease, and/or diabetes, who are at high risk of coronary heart disease events. VYTORIN is a combination of ezetimibe, a dietary cholesterol absorption inhibitor, and simvastatin, an HMG-CoA reductase inhibitor (statin) indicated: ( 1 ) As an adjunct to diet to reduce elevated low density lipoprotein cholesterol (LDL-C): In adults with primary hyperlipidemia.
In adults and pediatric patients aged 10 years and older with heterozygous familial hypercholesterolemia (HeFH). As an adjunct to other LDL-C lowering therapies to reduce LDL-C in adults with homozygous familial hypercholesterolemia (HoFH). Simvastatin Simvastatin, when used as a component of VYTORIN, is indicated to reduce the risk of total mortality by reducing risk of coronary heart disease death, non-fatal myocardial infarction and stroke, and the need for coronary and non-coronary revascularization procedures in adults with established coronary heart disease, cerebrovascular disease, peripheral vascular disease, and/or diabetes, who are at high risk of coronary heart disease events.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Important Dosage and Administration Information: ( 2.1 ) Take VYTORIN orally once daily in the evening with or without food. Maximum recommended dosage is VYTORIN 10/40 mg once daily. VYTORIN 10/80 mg daily dosage is restricted to patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity.
For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose.
Assess LDL-C when clinically appropriate, as early as 2 weeks after initiating VYTORIN, and adjust the dosage if necessary. Adults: Recommended dosage range of 10/10 mg to 10/40 mg once daily. ( 2.2 ) See full prescribing information for VYTORIN dosage modifications due to drug interactions.
( 2.3 ) Patients with Renal Impairment: Doses exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment. ( 2.4 )
2.1Important Dosage and Administration Information Take VYTORIN orally once daily in the evening with or without food. The maximum recommended dosage is VYTORIN 10/40 mg once daily. The VYTORIN 10/80 mg daily dosage is restricted to adult patients who have been taking VYTORIN 10/80 mg daily chronically (e.g., for 12 months or more) without evidence of muscle toxicity [see Warnings and Precautions (5.1) ] .
For patients that require a high-intensity statin or are unable to achieve their LDL-C goal receiving VYTORIN 10/40 mg daily, prescribe alternative LDL-C-lowering treatment. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose.
Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating VYTORIN, and adjust the dosage if necessary.
2.2Recommended Dosage in Adult Patients The recommended dosage range of VYTORIN 10/10 mg to 10/40 mg once a day.
2.3Recommended Dosage in Pediatric Patients 10 Years of Age and Older with HeFH The recommended dosage range of VYTORIN 10/10 mg to 10/40 mg once a day.
2.4Recommended Dosage in Patients with Renal Impairment Renal impairment is a risk factor for statin-associated myopathy. Doses of VYTORIN exceeding 10/20 mg should be used with caution and close monitoring in patients with moderate to severe renal impairment [see Warnings and Precautions (5.1) and Use in Specific Populations (8.6) ] . There are no dosage adjustment recommendations for patients with mild renal impairment.
2.5Dosage Modifications Due to Drug Interactions Concomitant use of VYTORIN with the following drugs requires dosage modification of VYTORIN [see Warnings and Precautions (5.1) and Drug Interactions (7.1) ] . Patients taking Lomitapide Reduce the dosage of VYTORIN by 50%. Do not exceed VYTORIN 10/20 mg once daily (or 10/40 mg once daily for patients who have previously taken VYTORIN 10/80 mg daily chronically while taking lomitapide) [see Dosage and Administration (2.1) ] .
Patients taking Verapamil, Diltiazem, or Dronedarone Do not exceed VYTORIN 10/10 mg once daily. Patients taking Amiodarone, Amlodipine, or Ranolazine Do not exceed VYTORIN 10/20 mg once daily. Patients taking Bile Acid Sequestrants In patients taking a bile acid sequestrant, administer VYTORIN at least 2 hours before or 4 hours after the bile acid sequestrant.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS VYTORIN tablets: 10/10, (ezetimibe 10 mg and simvastatin 10 mg tablets) are white to off-white capsule-shaped and debossed with “311” on one side. 10/20, (ezetimibe 10 mg and simvastatin 20 mg tablets) are white to off-white capsule-shaped and debossed with “312” on one side. 10/40, (ezetimibe 10 mg and simvastatin 40 mg tablets) are white to off-white capsule-shaped and debossed with “313” on one side.
10/80, (ezetimibe 10 mg and simvastatin 80 mg tablets) are white to off-white capsule-shaped and debossed with “315” on one side. Tablets (ezetimibe mg/simvastatin mg): 10/10, 10/20, 10/40, 10/80 ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS VYTORIN is contraindicated in the following conditions: Concomitant use of strong CYP3A4 inhibitors (select azole anti-fungals, macrolide antibiotics, anti-viral medications, and nefazodone) [see Drug Interactions (7.1) ] . Concomitant use of cyclosporine, danazol, or danazol [see Drug Interactions (7.1) ] . Acute liver failure or decompensated cirrhosis [see Warnings and Precautions (5.3) ] .
Hypersensitivity to simvastatin, ezetimibe, or any excipients in VYTORIN. Hypersensitivity reactions, including anaphylaxis, angioedema, and Stevens-Johnson syndrome, have been reported [see Adverse Reactions (6.2) ] . Concomitant use of strong CYP3A4 inhibitors (select azole anti-fungals, macrolide antibiotics, anti-viral medications and nefazodone).
( 4 ) Concomitant use of cyclosporine, danazol or gemfibrozil. ( 4 ) Acute liver failure or decompensated cirrhosis. ( 4 ) Hypersensitivity to simvastatin, ezetimibe or any excipient of VYTORIN.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myopathy and Rhabdomyolysis: Risk factors include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs, and higher VYTORIN dosage. Chinese patients may be at higher risk for myopathy. Discontinue VYTORIN if markedly elevated CK levels occur or myopathy is diagnosed or suspected.
Temporarily discontinue VYTORIN in patients experiencing an acute or serious condition at high risk of developing renal failure secondary to rhabdomyolysis. Inform patients of the risk of myopathy and rhabdomyolysis when starting or increasing VYTORIN dosage. Instruct patients to promptly report unexplained muscle pain, tenderness, or weakness, particularly if accompanied by malaise or fever.
( 5.1 ) Immune-Mediated Necrotizing Myopathy (IMNM): Rare reports of IMNM, an autoimmune myopathy, have been reported. Discontinue VYTORIN if IMNM is suspected. ( 5.2 ) Hepatic Dysfunction: Increases in serum transaminases have occurred, some persistent.
Rare reports of fatal and non-fatal hepatic failure have occurred. Consider testing liver enzyme before initiating therapy and as clinically indicated thereafter. If serious hepatic injury with clinical symptoms and/or hyperbilirubinemia or jaundice occurs, promptly discontinue VYTORIN.
( 5.3 )
5.1Myopathy and Rhabdomyolysis VYTORIN may cause myopathy and rhabdomyolysis. Acute kidney injury secondary to myoglobinuria and rare fatalities have occurred as a result of rhabdomyolysis in patients treated with statins, including VYTORIN. In clinical trials of 24,747 simvastatin-treated patients with a median follow-up of 4 years, the incidence of myopathy, defined as unexplained muscle weakness, pain, or tenderness accompanied by creatinine kinase (CK) increases greater than ten times the upper limit of normal (10 X ULN), were approximately 0.03%, 0.08%, and 0.61% in patients treated with simvastatin 20 mg, 40 mg, and 80 mg daily, respectively.
In another clinical trial of 12,064 simvastatin-treated patients (with a history of myocardial infarction) with a mean follow-up of 6.7 years, the incidences of myopathy in patients taking simvastatin 20 mg and 80 mg daily were approximately 0.02% and 0.9%, respectively. The incidences of rhabdomyolysis (defined as myopathy with a CK >40 X ULN) in patients taking simvastatin 20 mg and 80 mg daily were approximately 0% and 0.4%, respectively [see Adverse Reactions (6.1) ] . In the Trial of Heart and Renal Protection (SHARP), 9270 patients with chronic kidney disease were allocated to receive VYTORIN 10/20 mg daily (n=4650) or placebo (n=4620).
During a median follow-up period of 4.9 years, the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum creatine kinase [CK] >10 times upper limit of normal [ULN]) was 0.2% for VYTORIN and 0.1% for placebo: the incidence of rhabdomyolysis (defined as myopathy with a CK > 40 times ULN) was 0.09% for VYTORIN and 0.02% for placebo. In postmarketing experience with ezetimibe, cases of myopathy and rhabdomyolysis have been reported. Most patients who developed rhabdomyolysis were taking a statin prior to initiating ezetimibe.
However, rhabdomyolysis has been reported with ezetimibe monotherapy and with the addition of ezetimibe to agents known to be associated with increased risk of rhabdomyolysis, such as fibric acid derivatives. VYTORIN and a fenofibrate, if taking concomitantly, should both be immediately discontinued if myopathy is diagnosed or suspected. Risk Factors for Myopathy Risk factors for myopathy include age 65 years or greater, uncontrolled hypothyroidism, renal impairment, concomitant use with certain other drugs (including other lipid-lowering therapies), and higher VYTORIN dosage; Chinese patients on VYTORIN may be at higher risk for myopathy [see Contraindications (4) , Drug Interactions (7.1) , and Use in Specific Populations (8.8) ] .
The risk of myopathy is increased by elevated plasma levels of simvastatin a… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the label: Myopathy and Rhabdomyolysis [see Warnings and Precautions (5.1) ] Immune-Mediated Necrotizing Myopathy [see Warnings and Precautions (5.2) ] Hepatic Dysfunction [see Warnings and Precautions (5.3) ] Increases in HbA1c and Fasting Serum Glucose Levels [see Warnings and Precautions (5.4) ] Common (incidence ≥2% and greater than placebo) adverse reactions in clinical trials: headache, increased ALT, myalgia, upper respiratory tract infection, and diarrhea.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Organon LLC, a subsidiary of Organon & Co., at 1-844-674-3200 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. VYTORIN In the VYTORIN (ezetimibe and simvastatin) placebo-controlled clinical trials database of 1420 patients (age range 20-83 years, 52% female, 87% White, 3% Black or African American, 3% Asians, 5% other races identified as Hispanic or Latino ethnicity) with a median treatment duration of 27 weeks, 5% of patients on VYTORIN and 2.2% of patients on placebo discontinued due to adverse reactions.
The most commonly reported adverse reactions (incidence ≥2% and greater than placebo) in controlled clinical trials were: headache (5.8%), increased ALT (3.7%), myalgia (3.6%), upper respiratory tract infection (3.6%), and diarrhea (2.8%). The most common adverse reactions in the group treated with VYTORIN that led to treatment discontinuation and occurred at a rate greater than placebo were: increased ALT (0.9%), myalgia (0.6%), increased AST (0.4%), and back pain (0.4%). VYTORIN has been evaluated for safety in more than 10,189 patients in clinical trials.
Table 1 summarizes the frequency of clinical adverse reactions reported in ≥2% of patients treated with VYTORIN (n=1420) and at an incidence greater than placebo from four placebo-controlled trials. Table 1 Includes two placebo-controlled combination studies in which the active ingredients equivalent to VYTORIN were coadministered and two placebo-controlled studies in which VYTORIN was administered. : Adverse Reactions Reported ≥2% of Patients Treated with VYTORIN at an Incidence Greater than Placebo Regardless of Causality % Placebo N = 371 % Ezetimibe 10 mg N = 302 % Simvastatin All doses.
N = 1234 % VYTORIN N = 1420 Headache 5.4 6.0 5.9
5.8Upper respiratory tract infection 2.7 5.0 5.0
3.6Myalgia 2.4 2.3 2.6
3.6Diarrhea 2.2 5.0 3.7
2.8Pain in extremity 1.3 3.0 2.0
2.3Influenza 0.8 1.0 1.9
2.3Study of Heart and Renal Protection In SHARP , 9270 patients were allocated to VYTORIN 10/20 mg daily (n=4650) or placebo (n=4620) for a median follow-up period of 4.9 years. The proportion of patients who permanently discontinued trial treatment as a result of either an adverse event or abnormal safety blood result was 10.4% vs. 9.8% among patients allocated to VYTORIN and placebo, respectively.
Comparing those allocated to VYTORIN vs. placebo, the incidence of myopathy (defined as unexplained muscle weakness or pain with a serum CK >10 times ULN) was 0.2% vs. 0.1% and the incidence of rhabdomyolysis (defined as myopathy with a CK >40 times ULN) was 0.09% vs. 0.02%, respectively.
Consecutive elevations of transaminases (>3 X ULN) occurred in 0.7% vs. 0.6%, respectively. Patients were asked about the occurrence of unexplained muscle pain or weakness at each trial visit: 21.5% vs.
20.9% patients ever reported muscle symptoms in the VYTORIN and placebo groups, respectively. Cancer was diagnosed during the trial in 9.4% vs. 9.5% of patients assigned to VYTORIN and placebo, respectively.
Ezetimibe Other adverse reactions reported with ezetimibe in placebo-control… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS VYTORIN See full prescribing information for details regarding concomitant use of VYTORIN with other drugs or grapefruit juice that increase the risk of myopathy and rhabdomyolysis. ( 2.3 , 7.1 ) Cholestyramine: Combination decreases exposure of ezetimibe. ( 2.3 , 7.2 ) Coumarin Anticoagulants: Obtain INR before VYTORIN initiation and monitor INR during VYTORIN dosage initiation or adjustment.
( 7.3 ) Digoxin : During VYTORIN initiation, monitor digoxin levels. ( 7.3 ) Fenofibrates: Combination increases exposure of ezetimibe. If cholelithiasis is suspected in a patient receiving ezetimibe and a fenofibrate, gallbladder studies are indicated and alternative lipid-lowering therapy should be considered.
( 7.3 , 12.3 )
7.1Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN VYTORIN is a substrate of CYP3A4 and of the transport protein OATP1B1. VYTORIN plasma levels can be significantly increased with concomitant administration of inhibitors of CYP3A4 and OATP1B1. Table 2 includes a list of drugs that increase the risk of myopathy and rhabdomyolysis when used concomitantly with VYTORIN and instructions for preventing or managing them [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3) ] .
Table 2: Drug Interactions that Increase the Risk of Myopathy and Rhabdomyolysis with VYTORIN Strong CYP3A4 inhibitors Clinical Impact: Simvastatin is a substrate of CYP3A4. Concomitant use of strong CYP3A4 inhibitors with VYTORIN increases simvastatin exposure and increases the risk of myopathy and rhabdomyolysis, particularly with higher VYTORIN dosages. Intervention: Concomitant use of strong CYP3A4 inhibitors with VYTORIN is contraindicated [see Contraindications (4) ] .
If treatment with a CYP3A4 inhibitor is unavoidable, suspend VYTORIN during the course of strong CYP3A4 inhibitor treatment. Examples: Select azole anti-fungals (e.g., itraconazole, ketoconazole, posaconazole, and voriconazole), select macrolide antibiotics (e.g., erythromycin and clarithromycin, telithromycin), select HIV protease inhibitors (e.g., nelfinavir, ritonavir, and darunavir/ritonavir), select HCV protease inhibitors (e.g., boceprevir and telaprevir), cobicistat-containing products, and nefazodone. Cyclosporine, Danazol, or Gemfibrozil Clinical Impact: The risk of myopathy and rhabdomyolysis is increased with concomitant use of cyclosporine, danazol, or gemfibrozil with VYTORIN.
Gemfibrozil may cause myopathy when given alone. Intervention: Concomitant use of cyclosporine, danazol, or gemfibrozil with VYTORIN is contraindicated [see Contraindications (4) ] . Amiodarone, Dronedarone, Ranolazine, or Calcium Channel Blockers Clinical Impact: The risk of myopathy and rhabdomyolysis is increased by concomitant use of amiodarone, dronedarone, ranolazine, or calcium channel blockers with VYTORIN.
Intervention: For patients taking verapamil, diltiazem, or dronedarone, do not exceed VYTORIN 10/10 mg daily. For patients taking amiodarone, amlodipine, or ranolazine, do not exceed VYTORIN 10/20 mg daily [see Dosage and Administration (2.3) ] . Lomitapide Clinical Impact: Simvastatin exposure is approximately doubled with concomitant use of lomitapide and the risk of myopathy and rhabdomyolysis is increased.
Intervention: Reduce the dose of VYTORIN by 50% if initiating lomitapide. Do not exceed VYTORIN 10/20 mg daily (or VYTORIN 10/40 mg daily for patients who have previously taken VYTORIN 10/80 mg daily chronically) while taking lomitapide [see Dosage and Administration (2.1 , 2.3) ] . Daptomycin Clinical Impact: Cases of rhabdomyolysis have been reported with simvastatin administered with daptomycin.
Both VYTORIN and daptomycin can cause myopathy and rhabdomyolysis when given alone and the risk of myopathy and rhabdomyolysis may be increased by coadministration. Intervention: If treatment with daptomycin is required, consider temporarily suspending VYTORIN during the course of daptomycin treatment. Niacin C… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm ( 8.1 ) Lactation: Breastfeeding not recommended during treatment with VYTORIN. ( 8.2 )
8.1Pregnancy VYTORIN Risk Summary Discontinue VYTORIN when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. VYTORIN decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, VYTORIN may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with VYTORIN use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data ) . In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered simvastatin during the period of organogenesis at doses that resulted in 2.5 and 2 times, respectively, the human exposure at the maximum recommended human dosage of 80 mg/day, based on body surface area (mg/m 2 ).
In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Ezetimibe There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Simvastatin A Medicaid cohort linkage trial of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods.
The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus. There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified.
Trial limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births. Animal Data Ezetimibe In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6-15) and rabbits (gestation days 7-19), there was no evidence of maternal toxicity or embryolethality at any dose tested (250, 500, 1000 mg/kg/day) at exposure equivalent to 10 to 150… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy VYTORIN Risk Summary Discontinue VYTORIN when pregnancy is recognized. Alternatively, consider the ongoing therapeutic needs of the individual patient. VYTORIN decreases synthesis of cholesterol and possibly other biologically active substances derived from cholesterol; therefore, VYTORIN may cause fetal harm when administered to pregnant patients based on the mechanism of action [see Clinical Pharmacology (12.1) ] .
In addition, treatment of hyperlipidemia is not generally necessary during pregnancy. Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hyperlipidemia for most patients. Available data from case series and prospective and retrospective observational cohort studies over decades of use with statins in pregnant women have not identified a drug-associated risk of major congenital malformations.
Published data from prospective and retrospective observational cohort studies with VYTORIN use in pregnant women are insufficient to determine if there is a drug-associated risk of miscarriage (see Data ) . In animal reproduction studies, no adverse developmental effects were observed in pregnant rats or rabbits orally administered simvastatin during the period of organogenesis at doses that resulted in 2.5 and 2 times, respectively, the human exposure at the maximum recommended human dosage of 80 mg/day, based on body surface area (mg/m 2 ).
In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Human Data Ezetimibe There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Simvastatin A Medicaid cohort linkage trial of 1152 statin-exposed pregnant women compared to 886,996 controls did not find a significant teratogenic effect from maternal use of statins in the first trimester of pregnancy, after adjusting for potential confounders – including maternal age, diabetes mellitus, hypertension, obesity, and alcohol and tobacco use – using propensity score-based methods.
The relative risk of congenital malformations between the group with statin use and the group with no statin use in the first trimester was 1.07 (95% confidence interval 0.85 to 1.37) after controlling for confounders, particularly pre-existing diabetes mellitus. There were also no statistically significant increases in any of the organ-specific malformations assessed after accounting for confounders. In the majority of pregnancies, statin treatment was initiated prior to pregnancy and was discontinued at some point in the first trimester when pregnancy was identified.
Trial limitations include reliance on physician coding to define the presence of a malformation, lack of control for certain confounders such as body mass index, use of prescription dispensing as verification for the use of a statin, and lack of information on non-live births. Animal Data Ezetimibe In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6-15) and rabbits (gestation days 7-19), there was no evidence of maternal toxicity or embryolethality at any dose tested (250, 500, 1000 mg/kg/day) at exposure equivalent to 10 to 150 times the clinical exposure, based on AUC, in rats and rabbits.
In rats, increased incidences of common fetal skeletal findings (extra pair of thoraci… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ezetimibe in combination with a statin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of VYTORIN for this indication is based on a double-blind, placebo-controlled clinical trial in 248 pediatric patients (142 males and 106 postmenarchal females) 10 years of age and older with HeFH [see Clinical Studies (14) ] . In this limited controlled trial, there was no significant effect on growth or sexual maturation in the adolescent males or females, or on menstrual cycle length in females.
The safety and effectiveness of VYTORIN have not been established in pediatric patients younger than 10 years of age with HeFH, or in pediatric patients with other types of hyperlipidemia.
🧓 Geriatric Use ▾
8.5Geriatric Use Advanced age (≥65 years) is a risk factor for VYTORIN-associated myopathy and rhabdomyolysis. Dose selection for an elderly patient should be cautious, recognizing the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of myopathy. Monitor geriatric patients receiving VYTORIN for the increased risk of myopathy [see Warnings and Precautions (5.1) ] .
Of the 10,189 patients who received VYTORIN in clinical studies, 3242 (32%) were 65 and older (this included 844 (8%) who were 75 and older). No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidotes for VYTORIN are known. In the event of an overdose with VYTORIN, consider contacting the Poison Help Line (1-800-222-1222) or a medical toxicologist for overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action VYTORIN Plasma cholesterol is derived from intestinal absorption and endogenous synthesis. VYTORIN contains ezetimibe and simvastatin, two lipid-lowering compounds with complementary mechanisms of action. Ezetimibe Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine.
The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver. This causes a reduction of hepatic cholesterol stores and an increase in clearance of cholesterol from the blood.
Simvastatin Simvastatin is a prodrug and is hydrolyzed to its active β-hydroxyacid form, simvastatin acid, after administration. Simvastatin acid and its metabolites are inhibitors of HMG-CoA reductase, the rate-limiting enzyme converts HMG-CoA to mevalonate, a precursor of cholesterol.
12.2Pharmacodynamics VYTORIN reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. Ezetimibe In a 2-week clinical trial in 18 hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo. Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E and did not impair adrenocortical steroid hormone production.
Simvastatin Inhibition of HMG-CoA reductase by simvastatin acid accelerates the expression of LDL-receptors, followed by the uptake of LDL-C from blood to the liver, leading to a decrease in plasma LDL-C and total cholesterol. Sustained inhibition of cholesterol synthesis in the liver also decreases levels of very-low density lipoproteins. The maximum LDL-C reduction of ZOCOR is usually achieved by 4 weeks and is maintained after that.
12.3Pharmacokinetics The results of a bioequivalence trial in healthy subjects demonstrated that the VYTORIN (ezetimibe and simvastatin) 10 mg/10 mg to 10 mg/80 mg combination tablets are bioequivalent to coadministration of corresponding doses of ezetimibe (ZETIA ® ) and simvastatin (ZOCOR ® ) as individual tablets. Absorption Ezetimibe After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide). Mean maximum plasma concentrations (C max ) occur within 1 to 2 hours for ezetimibe-glucuronide and 4 to 12 hours for ezetimibe.
The absolute bioavailability of ezetimibe cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. Simvastatin The availability of the β-hydroxyacid to the systemic circulation following an oral dose of simvastatin was found to be less than 5% of the dose, consistent with extensive hepatic first-pass extraction. Effect of Food on Oral Absorption Ezetimibe Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as 10-mg tablets.
The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Simvastatin Relative to the fasting state, the plasma profiles of both active and total inhibitors of HMG-CoA reductase were not affected when simvastatin was administered immediately before an American Heart Association recommended low-fat meal. Distribution Ezetimibe Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins.
Simvastatin Both simvastatin and its β-hydroxyacid metabolite are highly bound (approximately 95%) to human plasma proteins. When radiolabeled simvastatin was administered to rats, simvastatin-derived radioactivity crossed the blood-brain barrier. Elimination Metabolism Ezet… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action VYTORIN Plasma cholesterol is derived from intestinal absorption and endogenous synthesis. VYTORIN contains ezetimibe and simvastatin, two lipid-lowering compounds with complementary mechanisms of action. Ezetimibe Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine.
The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver. This causes a reduction of hepatic cholesterol stores and an increase in clearance of cholesterol from the blood.
Simvastatin Simvastatin is a prodrug and is hydrolyzed to its active β-hydroxyacid form, simvastatin acid, after administration. Simvastatin acid and its metabolites are inhibitors of HMG-CoA reductase, the rate-limiting enzyme converts HMG-CoA to mevalonate, a precursor of cholesterol.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING VYTORIN tablets are supplied as follows: Strength How Supplied NDC Tablet Description 10/10 mg unit of use bottles of 30 78206-174-01 white to off-white capsule-shaped tablets with code “311” on one side unit of use bottles of 90 78206-174-02 10/20 mg unit of use bottles of 30 78206-175-01 white to off-white capsule-shaped tablets with code “312” on one side unit of use bottles of 90 78206-175-02 10/40 mg unit of use bottles of 30 78206-176-01 white to off-white capsule-shaped tablets with code “313” on one side unit of use bottles of 90 78206-176-02 10/80 mg unit of use bottles of 30 78206-177-01 white to off-white capsule-shaped tablets with code “315” on one side unit of use bottles of 90 78206-177-02 Storage Store at 68°F to 77°F (20°C to 25°C). [See USP Controlled Room Temperature.] Keep container tightly closed.
📦 Storage and Handling ▾
Storage Store at 68°F to 77°F (20°C to 25°C). [See USP Controlled Room Temperature.] Keep container tightly closed.
📋 Description ▾
11 DESCRIPTION VYTORIN contains ezetimibe, a dietary cholesterol absorption inhibitor, and simvastatin, an HMG CoA reductase inhibitor. The chemical name of ezetimibe is 1-(4-fluorophenyl)-3(R)-[3-(4-fluorophenyl)-3(S)-hydroxypropyl]-4(S)-(4-hydroxyphenyl)-2-azetidinone. The empirical formula is C 24 H 21 F 2 NO 3 and its molecular weight is 409.4.
Ezetimibe is a white, crystalline powder that is freely to very soluble in ethanol, methanol, and acetone and practically insoluble in water. Its structural formula is: Simvastatin, an inactive lactone, is hydrolyzed to the corresponding β-hydroxyacid form, which is an inhibitor of HMG-CoA reductase. Simvastatin is butanoic acid, 2,2-dimethyl-,1,2,3,7,8,8a-hexahydro-3,7-dimethyl-8-[2-(tetrahydro-4-hydroxy-6-oxo-2 H -pyran-2-yl)-ethyl]-1-naphthalenyl ester, [1 S -[1α,3α,7β,8β(2 S *,4 S *),-8aβ]].
The empirical formula of simvastatin is C 25 H 38 O 5 and its molecular weight is 418.57. Simvastatin is a white to off-white, nonhygroscopic, crystalline powder that is practically insoluble in water and freely soluble in chloroform, methanol and ethanol. Its structural formula is: VYTORIN is available for oral use as tablets containing 10 mg of ezetimibe, and 10 mg of simvastatin (VYTORIN 10/10), 20 mg of simvastatin (VYTORIN 10/20), 40 mg of simvastatin (VYTORIN 10/40), or 80 mg of simvastatin (VYTORIN 10/80).
Each tablet contains the following inactive ingredients: butylated hydroxyanisole NF, citric acid monohydrate USP, croscarmellose sodium NF, hypromellose USP, lactose monohydrate NF, magnesium stearate NF, microcrystalline cellulose NF, and propyl gallate NF. Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Myopathy and Rhabdomyolysis Advise patients that VYTORIN may cause myopathy and rhabdomyolysis. Inform patients taking the 80 mg daily dose of simvastatin that they are at an increased risk.
Inform patients that the risk is also increased when taking certain types of medication or consuming grapefruit juice and they should discuss all medication, both prescription and over the counter, with their healthcare provider. Instruct patients to inform other healthcare providers prescribing a new medication or increasing the dose of an existing medication that they are taking VYTORIN. Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness particularly if accompanied by malaise or fever [see Contraindications (4) , Warnings and Precautions (5.1) , and Drug Interactions (7.1) ] .
Hepatic Dysfunction Inform patients that VYTORIN may cause liver enzyme elevations and possibly liver failure. Advise patients to promptly report fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice [see Warnings and Precautions (5.3) ] . Increases in HbA1c and Fasting Serum Glucose Levels Inform patients that increases in HbA1c and fasting serum glucose levels may occur with VYTORIN.
Encourage patients to optimize lifestyle measures, including regular exercise, maintaining a healthy body weight, and making healthy food choices [see Warnings and Precautions (5.4) ] . Pregnancy Advise pregnant patients and patients who can become pregnant of the potential risk to a fetus. Advise patients to inform their healthcare provider of a known or suspected pregnancy to discuss if VYTORIN should be discontinued [see Use in Specific Populations (8.1) ] .
Lactation Advise patients that breastfeeding is not recommended during treatment with VYTORIN [see Use in Specific Populations (8.2) ] . Missed Dose Instruct patients to take VYTORIN only as prescribed. If a dose is missed, it should be taken as soon as possible.
Advise patients not to double their next dose.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The results of a bioequivalence trial in healthy subjects demonstrated that the VYTORIN (ezetimibe and simvastatin) 10 mg/10 mg to 10 mg/80 mg combination tablets are bioequivalent to coadministration of corresponding doses of ezetimibe (ZETIA ® ) and simvastatin (ZOCOR ® ) as individual tablets. Absorption Ezetimibe After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide). Mean maximum plasma concentrations (C max ) occur within 1 to 2 hours for ezetimibe-glucuronide and 4 to 12 hours for ezetimibe.
The absolute bioavailability of ezetimibe cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. Simvastatin The availability of the β-hydroxyacid to the systemic circulation following an oral dose of simvastatin was found to be less than 5% of the dose, consistent with extensive hepatic first-pass extraction. Effect of Food on Oral Absorption Ezetimibe Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as 10-mg tablets.
The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Simvastatin Relative to the fasting state, the plasma profiles of both active and total inhibitors of HMG-CoA reductase were not affected when simvastatin was administered immediately before an American Heart Association recommended low-fat meal. Distribution Ezetimibe Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins.
Simvastatin Both simvastatin and its β-hydroxyacid metabolite are highly bound (approximately 95%) to human plasma proteins. When radiolabeled simvastatin was administered to rats, simvastatin-derived radioactivity crossed the blood-brain barrier. Elimination Metabolism Ezetimibe Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation with subsequent biliary and renal excretion.
Minimal oxidative metabolism has been observed in all species evaluated. In humans, ezetimibe is rapidly metabolized to ezetimibe-glucuronide. Ezetimibe and ezetimibe-glucuronide are the major drug-derived compounds detected in plasma, constituting approximately 10 to 20% and 80 to 90% of the total drug in plasma, respectively.
Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide. Plasma concentration-time profiles exhibit multiple peaks, suggesting enterohepatic recycling. Simvastatin Simvastatin is a lactone that is readily hydrolyzed in vivo to the corresponding β-hydroxyacid, a potent inhibitor of HMG-CoA reductase.
Inhibition of HMG-CoA reductase is a basis for an assay in pharmacokinetic studies of the β-hydroxyacid metabolites (active inhibitors) and, following base hydrolysis, active plus latent inhibitors (total inhibitors) in plasma following administration of simvastatin. The major active metabolites of simvastatin present in human plasma are the β-hydroxyacid of simvastatin and its 6'-hydroxy, 6'-hydroxymethyl, and 6'-exomethylene derivatives. Excretion Ezetimibe Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma.
After 48 hours, there were no detectable levels of radioactivity in the plasma. Approximately 78% and 11% of the administered radioactivity were recovered in the feces and urine, respectively, over a 10-day collection period. Ezetimibe was the major component in feces and accounted for 69% of the administered dose, while ezetimibe-glucuronide was the major component in urine and accounted for 9% of the administered dose.
Simvastatin Following an oral dose of 14 C-labeled simvastatin in man, 13% of the dose was excreted in urine and 60% in feces. Plasma concentrat… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics VYTORIN reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. Ezetimibe In a 2-week clinical trial in 18 hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo. Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E and did not impair adrenocortical steroid hormone production.
Simvastatin Inhibition of HMG-CoA reductase by simvastatin acid accelerates the expression of LDL-receptors, followed by the uptake of LDL-C from blood to the liver, leading to a decrease in plasma LDL-C and total cholesterol. Sustained inhibition of cholesterol synthesis in the liver also decreases levels of very-low density lipoproteins. The maximum LDL-C reduction of ZOCOR is usually achieved by 4 weeks and is maintained after that.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Primary Hyperlipidemia in Adults VYTORIN VYTORIN reduces LDL-C in adult patients with primary hyperlipidemia. Maximal to near maximal response is generally achieved within 2 weeks and maintained during chronic therapy. VYTORIN is effective in males and females with primary hyperlipidemia.
There were insufficient numbers of patients who self-identified as Black or African American, Asian, or other races to determine if these patients responded differently than White patients. Five multicenter, double-blind trials conducted with either VYTORIN or coadministered ezetimibe and simvastatin equivalent to VYTORIN in patients with primary hyperlipidemia are reported: two were comparisons with simvastatin, two were comparisons with atorvastatin, and one was a comparison with rosuvastatin. In a multicenter, double-blind, placebo-controlled, 12-week trial, 1528 patients with primary hyperlipidemia were randomized to one of ten treatment groups: placebo, ezetimibe (10 mg), simvastatin (10 mg, 20 mg, 40 mg, or 80 mg), or VYTORIN (10/10, 10/20, 10/40, or 10/80).
When patients receiving VYTORIN were compared to those receiving all doses of simvastatin, VYTORIN significantly lowered total-C, LDL-C, Apo B, TG, and non-HDL-C. The effects of VYTORIN on HDL-C were similar to the effects seen with simvastatin. Further analysis showed VYTORIN significantly increased HDL-C compared with placebo.
(See Table 8 .) The lipid response to VYTORIN was similar in patients with TG levels greater than or less than 200 mg/dL. Table 8: Response to VYTORIN in Patients with Primary Hyperlipidemia (Mean For triglycerides, median % change from baseline. % Change from Untreated Baseline Baseline - on no lipid-lowering drug. ) Treatment (Daily Dose) N Total-C LDL-C Apo B HDL-C TG Non-HDL-C Pooled data (All VYTORIN doses) VYTORIN doses pooled (10/10-10/80) significantly reduced total-C, LDL-C, Apo B, TG, and non-HDL-C compared to simvastatin and significantly increased HDL-C compared to placebo.
609 -38 -53 -42 +7 -24 -49 Pooled data (All simvastatin doses) 622 -28 -39 -32 +7 -21 -36 Ezetimibe 10 mg 149 -13 -19 -15 +5 -11 -18 Placebo 148 -1 -2 0 0 -2 -2 VYTORIN by dose 10/10 152 -31 -45 -35 +8 -23 -41 10/20 156 -36 -52 -41 +10 -24 -47 10/40 147 -39 -55 -44 +6 -23 -51 10/80 154 -43 -60 -49 +6 -31 -56 Simvastatin by dose 10 mg 158 -23 -33 -26 +5 -17 -30 20 mg 150 -24 -34 -28 +7 -18 -32 40 mg 156 -29 -41 -33 +8 -21 -38 80 mg 158 -35 -49 -39 +7 -27 -45 In a multicenter, double-blind, controlled, 23-week trial, 710 patients with known CHD or CHD risk equivalents, as defined by the NCEP ATP III guidelines, and an LDL-C ≥130 mg/dL were randomized to one of four treatment groups: coadministered ezetimibe and simvastatin equivalent to VYTORIN (10/10, 10/20, and 10/40) or simvastatin 20 mg.
Patients not reaching an LDL-C <100 mg/dL had their simvastatin dose titrated at 6-week intervals to a maximal dose of 80 mg. At Week 5, the LDL-C reductions with VYTORIN 10/10, 10/20, or 10/40 were significantly larger than with simvastatin 20 mg (see Table 9 ). Table 9: Response to VYTORIN after 5 Weeks in Patients with CHD or CHD Risk Equivalents and an LDL-C ≥130 mg/dL Simvastatin 20 mg VYTORIN 10/10 VYTORIN 10/20 VYTORIN 10/40 N 253 251 109 97 Mean baseline LDL-C 174 165 167 171 Percent change LDL-C -38 -47 -53 -59 In a multicenter, double-blind, 6-week trial, 1902 patients with primary hyperlipidemia were randomized to one of eight treatment groups: VYTORIN (10/10, 10/20, 10/40, or 10/80) or atorvastatin (10 mg, 20 mg, 40 mg, or 80 mg).
Across the dosage range, when patients receiving VYTORIN were compared to those receiving milligram-equivalent statin doses of atorvastatin, VYTORIN lowered total-C, LDL-C, Apo B, and non-HDL-C significantly more than atorvastatin. Only the 10/40 mg and 10/80 mg VYTORIN doses increased HDL-C significantly more than the corresponding milligram-equivalent statin dose of atorvastatin. The effects of VYTORIN on TG were similar to the eff… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility VYTORIN No animal carcinogenicity or fertility studies have been conducted with the combination of ezetimibe and simvastatin. The combination of ezetimibe with simvastatin did not show evidence of mutagenicity in vitro in a microbial mutagenicity (Ames) test with Salmonella typhimurium and Escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with ezetimibe and simvastatin with or without metabolic activation.
There was no evidence of genotoxicity at doses up to 600 mg/kg with the combination of ezetimibe and simvastatin (1:1) in the in vivo mouse micronucleus test. Ezetimibe A 104-week dietary carcinogenicity trial with ezetimibe was conducted in rats at doses up to 1500 mg/kg/day (males) and 500 mg/kg/day (females) (~20 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). A 104-week dietary carcinogenicity trial with ezetimibe was also conducted in mice at doses up to 500 mg/kg/day (>150 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
There were no statistically significant increases in tumor incidences in drug-treated rats or mice. No evidence of mutagenicity was observed in vitro in a microbial mutagenicity (Ames) test with Salmonella typhimurium and Escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with or without metabolic activation.
In addition, there was no evidence of genotoxicity in the in vivo mouse micronucleus test. In oral (gavage) fertility studies of ezetimibe conducted in rats, there was no evidence of reproductive toxicity at doses up to 1000 mg/kg/day in male or female rats (~7 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). Simvastatin In a 72-week carcinogenicity trial, mice were administered daily doses of simvastatin of 25, 100, and 400 mg/kg body weight, which resulted in mean plasma drug levels approximately 1, 4, and 8 times higher than the mean human plasma drug level, respectively, (as total inhibitory activity based on AUC) after an 80-mg oral dose.
Liver carcinomas were significantly increased in high-dose females and mid- and high-dose males with a maximum incidence of 90% in males. The incidence of adenomas of the liver was significantly increased in mid- and high-dose females. Drug treatment also significantly increased the incidence of lung adenomas in mid- and high-dose males and females.
Adenomas of the Harderian gland (a gland of the eye of rodents) were significantly higher in high-dose mice than in controls. No evidence of a tumorigenic effect was observed at 25 mg/kg/day. In a separate 92-week carcinogenicity trial in mice at doses up to 25 mg/kg/day, no evidence of a tumorigenic effect was observed (mean plasma drug levels were 1 times higher than humans given 80 mg simvastatin as measured by AUC).
In a two-year trial in rats at 25 mg/kg/day, there was a statistically significant increase in the incidence of thyroid follicular adenomas in female rats exposed to approximately 11 times higher levels of simvastatin than in humans given 80 mg simvastatin (as measured by AUC). A second two-year rat carcinogenicity trial with doses of 50 and 100 mg/kg/day produced hepatocellular adenomas and carcinomas (in female rats at both doses and in males at 100 mg/kg/day). Thyroid follicular cell adenomas were increased in males and females at both doses; thyroid follicular cell carcinomas were increased in females at 100 mg/kg/day.
The increased incidence of thyroid neoplasms appears to be consistent with findings from other statins. These treatment levels represented plasma drug levels (AUC) of approximately 7 and 15 times (males) and 22 and 25 times (females) the mean hum… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility VYTORIN No animal carcinogenicity or fertility studies have been conducted with the combination of ezetimibe and simvastatin. The combination of ezetimibe with simvastatin did not show evidence of mutagenicity in vitro in a microbial mutagenicity (Ames) test with Salmonella typhimurium and Escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with ezetimibe and simvastatin with or without metabolic activation.
There was no evidence of genotoxicity at doses up to 600 mg/kg with the combination of ezetimibe and simvastatin (1:1) in the in vivo mouse micronucleus test. Ezetimibe A 104-week dietary carcinogenicity trial with ezetimibe was conducted in rats at doses up to 1500 mg/kg/day (males) and 500 mg/kg/day (females) (~20 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). A 104-week dietary carcinogenicity trial with ezetimibe was also conducted in mice at doses up to 500 mg/kg/day (>150 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
There were no statistically significant increases in tumor incidences in drug-treated rats or mice. No evidence of mutagenicity was observed in vitro in a microbial mutagenicity (Ames) test with Salmonella typhimurium and Escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with or without metabolic activation.
In addition, there was no evidence of genotoxicity in the in vivo mouse micronucleus test. In oral (gavage) fertility studies of ezetimibe conducted in rats, there was no evidence of reproductive toxicity at doses up to 1000 mg/kg/day in male or female rats (~7 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). Simvastatin In a 72-week carcinogenicity trial, mice were administered daily doses of simvastatin of 25, 100, and 400 mg/kg body weight, which resulted in mean plasma drug levels approximately 1, 4, and 8 times higher than the mean human plasma drug level, respectively, (as total inhibitory activity based on AUC) after an 80-mg oral dose.
Liver carcinomas were significantly increased in high-dose females and mid- and high-dose males with a maximum incidence of 90% in males. The incidence of adenomas of the liver was significantly increased in mid- and high-dose females. Drug treatment also significantly increased the incidence of lung adenomas in mid- and high-dose males and females.
Adenomas of the Harderian gland (a gland of the eye of rodents) were significantly higher in high-dose mice than in controls. No evidence of a tumorigenic effect was observed at 25 mg/kg/day. In a separate 92-week carcinogenicity trial in mice at doses up to 25 mg/kg/day, no evidence of a tumorigenic effect was observed (mean plasma drug levels were 1 times higher than humans given 80 mg simvastatin as measured by AUC).
In a two-year trial in rats at 25 mg/kg/day, there was a statistically significant increase in the incidence of thyroid follicular adenomas in female rats exposed to approximately 11 times higher levels of simvastatin than in humans given 80 mg simvastatin (as measured by AUC). A second two-year rat carcinogenicity trial with doses of 50 and 100 mg/kg/day produced hepatocellular adenomas and carcinomas (in female rats at both doses and in males at 100 mg/kg/day). Thyroid follicular cell adenomas were increased in males and females at both doses; thyroid follicular cell carcinomas were increased in females at 100 mg/kg/day.
The increased incidence of thyroid neoplasms appears to be consistent with findings from other statins. These treatment levels represented plasma drug levels (AUC) of approximately 7 and 15 times (males) and 22 and 25 times (females) the mean human plasma drug exposure af… [Excerpted — this section continues on DailyMed.]
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 2/2024 PATIENT INFORMATION VYTORIN ® [VI-tor-in] (ezetimibe and simvastatin) tablets, for oral use Read this Information carefully before you start taking VYTORIN ® and each time you get a VYTORIN.
There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment. If you have any questions about VYTORIN, ask your healthcare provider.
Only your healthcare provider can determine if VYTORIN is right for you. What is VYTORIN? VYTORIN is a prescription medicine that contains the cholesterol lowering medicines, simvastatin and ezetimibe: VYTORIN is used along with diet to lower elevated low-density lipoprotein cholesterol (LDL-C) or bad cholesterol in: adults with primary hyperlipidemia (high level of fats in your blood). adults and children 10 years of age and older with heterozygous familial hypercholesterolemia (HeFH).
HeFH is an inherited condition that causes high levels of bad cholesterol. VYTORIN is also used with other cholesterol lowering treatments to lower elevated LDL-C levels in adults with homozygous familial hypercholesterolemia (HoFH). HoFH is an inherited condition that causes high levels of bad cholesterol.
Simvastatin when used as a component of VYTORIN is used to lower: the risk of death by lowering the risk of heart disease death. the risk of heart attacks and strokes. the need for certain types of heart and blood vessel procedures to improve blood flow called arterial revascularization in people with known heart, cerebrovascular disease (conditions that affect blood flow and the blood vessels in the brain), peripheral vascular disease (a blood circulation disorder that causes the blood vessels outside of your heart and brain to narrow, block, or spasm), and diabetes, who are at high risk for heart disease problems.
The safety and effectiveness of VYTORIN has not been established in children younger than 10 years of age with inherited heterozygous familial hypercholesterolemia (HeFH) or other types of hyperlipidemia. Do not take VYTORIN if you: take certain medicines called CYP3A4 inhibitors such as: certain antifungal medicines (such as itraconazole, ketoconazole, posaconazole, voriconazole). certain antibiotics (including erythromycin, clarithromycin, telithromycin). HIV protease inhibitors (such as indinavir, nelfinavir, ritonavir, saquinavir, tipranavir, or atazanavir and cobicistat-containing products such as (elvitegravir/cobicistat/emtricitabine/tenofovir disoproxil fumarate). certain hepatitis C virus protease inhibitors (such as boceprevir or telaprevir). the antidepressant nefazodone. take medicines called cyclosporine, danazol, or gemfibrozil. have liver problems. are allergic to simvastatin, ezetimibe, or any of the ingredients in VYTORIN.
See the end of this Patient Information leaflet for a complete list of ingredients in VYTORIN. Ask your healthcare provider or pharmacist if you are not sure if your medicine is listed above. Before you take VYTORIN, tell your healthcare provider about all of your medical conditions, including if you: have unexplained muscle aches or weakness. have or have had myasthenia gravis (a disease causing general muscle weakness including in some cases muscles used for breathing), ocular myasthenia (a disease causing eye muscle weakness). have kidney problems. have liver problems or drink more than 2 glasses of alcohol daily. have thyroid problems. are 65 years of age or older. are of Chinese descent. are pregnant or plan to become pregnant.
If you become pregnant while taking VYTORIN, call your healthcare provider right away to discuss stopping VYTORIN. are breastfeeding or plan to breastfeed. It is not known if VYTORIN passes into your breast milk. Do not breastfeed while taking VYTORIN.
Tell your healthcare provider about all the medicines you take , including prescription and over-the-c… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 2/2024 Dosage and Administration ( 2.1 , 2.2 , 2.3 , 2.4 , 2.5 ) 2/2024 Contraindications, Pregnancy and Lactation ( 4 ) Removed 2/2024 Warnings and Precautions ( 5.1 , 5.2 , 5.3 ) 2/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 10 mg /10 mg Tablet Bottle Label NDC 78206-174-01 Vytorin ® (ezetimibe and simvastatin) tablets 10 mg /10 mg Each tablet contains 10 mg ezetimibe and 10 mg simvastatin. Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 10 mg /10 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg /20 mg Tablet Bottle Label NDC 78206-175-01 Vytorin ® (ezetimibe and simvastatin) tablets 10 mg /20 mg Each tablet contains 10 mg ezetimibe and 20 mg simvastatin. Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 10 mg /20 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg /40 mg Tablet Bottle Label NDC 78206-176-01 Vytorin ® (ezetimibe and simvastatin) tablets 10 mg /40 mg Each tablet contains 10 mg ezetimibe and 40 mg simvastatin. Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 10 mg /40 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 10 mg /80 mg Tablet Bottle Label NDC 78206-177-01 Vytorin ® (ezetimibe and simvastatin) tablets 10 mg /80 mg Each tablet contains 10 mg ezetimibe and 80 mg simvastatin. Rx only 30 Tablets PRINCIPAL DISPLAY PANEL - 10 mg /80 mg Tablet Bottle Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |