
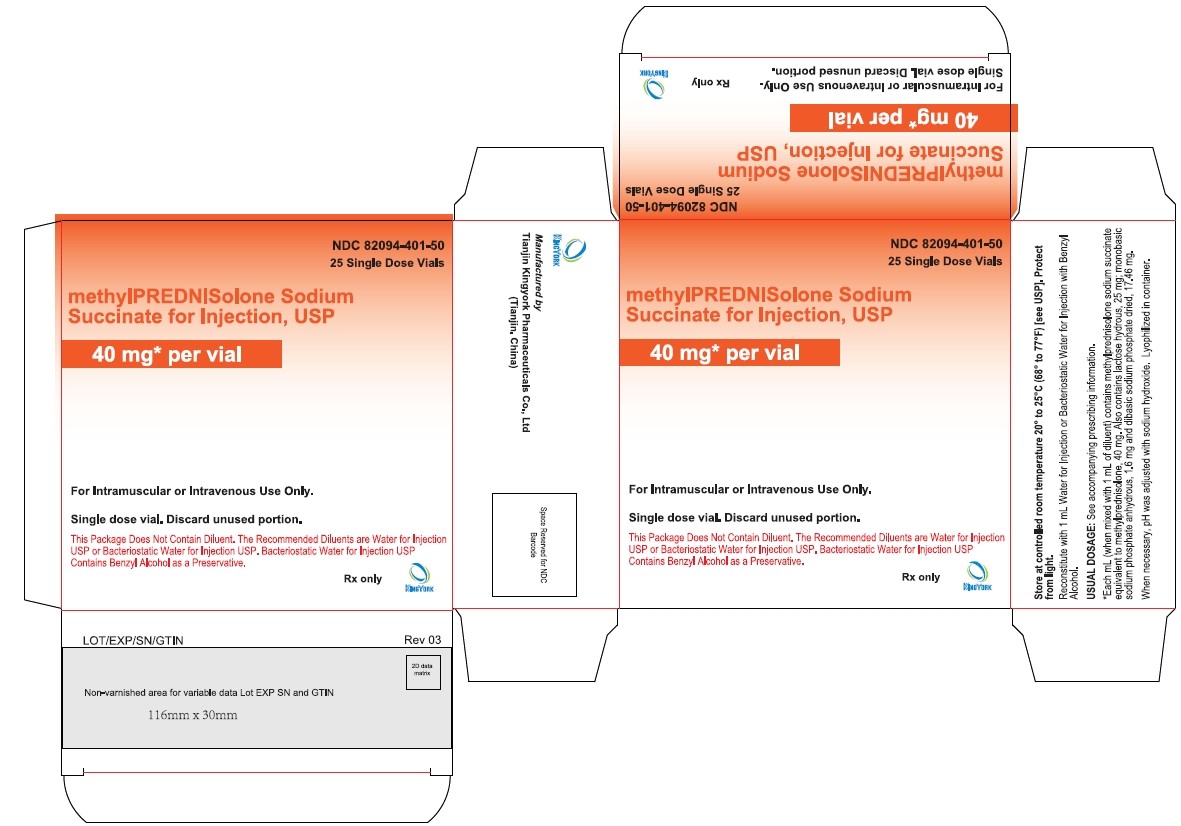
Methylprednisolone Sodium Succinate 125 mg/2mL Injection, Powder, Lyophilized, For Solution
Other active recalls for Methylprednisolone (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Methylprednisolone is used for a very wide range of conditions — basically anything where your immune system or inflammation is causing the problem. That includes severe allergic r...
- What conditions does methylprednisolone actually treat?
- It really depends on what you're being treated for. Some people take a short course for an acute flare and then stop. Others need longer-term treatment for chronic conditions. The...
- How long will I need to take this medication?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methylprednisolone — tap one for details:
Methylprednisolone may be associated with lower levels of 9 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
17.4 mg / 2 mL
UNII 22ADO53M6F
A mineral salt derived from phosphoric acid, used as a buffer to maintain the pH balance of the medication and help stabilize the active ingredients.
-
1.84 mg / 2 mL
UNII 593YOG76RN
A salt made from sodium and phosphate that helps regulate acidity and maintain proper pH balance in the medicine. It also acts as a buffer to keep the product stable.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Methylprednisolone Sodium Succinate 125 mg 00143-9754-25 | Hikma | 25 vials | $3.585 | AP | Availability likely | — |
| Methylprednisolone sodium succinate 125 mg/2mL 43598-0129-25 | Dr. | 25 vials | $3.585 | AP | Availability likely | — |
| Methylprednisolone Sodium Succinate 125 mg/2mL 63323-0258-03 | Fresenius | 25 vials | $3.585 | AP | Discontinued | — |
| Solu-Medrol 125 mg/2mL 00009-0047-22 | Pharmacia | 25 vials | $10.051 | AP | Availability likely | — |
| Solu-Medrol 125 mg/2mL 00404-9957-02 | Henry | 1 vial | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 50090-0271-00 | A-S | 2 ml | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 51662-1263-01 | HF | 1 ml | — | AP | FDA listed | — |
| Methylprednisolone Sodium Succinate 125 mg 55150-0263-03 | Eugia | 25 vials | — | — | FDA listed | — |
| Solu-Medrol 125 mg/2mL 55154-3941-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 55154-3944-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Methylprednisolone Sodium Succinate 125 mg/2mL 70121-1001-05 | Amneal | 25 vials | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 70518-2023-02 | REMEDYREPACK | 25 vials | — | AP | Discontinued | — |
| Methylprednisolone sodium succinate 125 mg/2mL 70518-3684-00 | REMEDYREPACK | 25 vials | — | AP | FDA listed | — |
| Methylprednisolone Sodium Succinate 125 mg 70518-4345-00 | REMEDYREPACK | 25 vials | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 71872-7061-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 71872-7232-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Methylprednisolone Sodium Succinate 125 mg 72572-0098-25 | Civica, | 25 vials | — | AP | FDA listed | — |
| Methylprednisolone Sodium Succinate 125 mg/2mLthis 82094-0402-50 | Tianjin | 25 vials | — | AP | FDA listed | — |
| Solu-Medrol 125 mg/2mL 84549-0047-22 | ProPharma | 2 ml | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 82094-0402-50 You're viewing this | 25 VIAL in 1 CARTON (82094-402-50) / 2 mL in 1 VIAL (82094-402-01) | 2021-04-20 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE When oral therapy is not feasible, and the strength, dosage form, and route of administration of the drug reasonably lend the preparation to the treatment of the condition, the intravenous or intramuscular use of methylprednisolone sodium succinate for injection, USP is indicated as follows: Allergic states: Control of severe or incapacitating allergic conditions intractable to adequate trials of conventional treatment in asthma, atopic dermatitis, contact dermatitis, drug hypersensitivity reactions, serum sickness, transfusion reactions.
Dermatologic diseases: Bullous dermatitis herpetiformis, exfoliative erythroderma, mycosis fungoides, pemphigus, severe erythema multiforme (Stevens-Johnson syndrome). Endocrine disorders: Primary or secondary adrenocortical insufficiency (hydrocortisone or cortisone is the drug of choice; synthetic analogs may be used in conjunction with mineralocorticoids where applicable; in infancy, mineralocorticoid supplementation is of particular importance), congenital adrenal hyperplasia, hypercalcemia associated with cancer, nonsuppurative thyroiditis.
Gastrointestinal diseases: To tide the patient over a critical period of the disease in regional enteritis (systemic therapy) and ulcerative colitis. Hematologic disorders: Acquired (autoimmune) hemolytic anemia, congenital (erythroid) hypoplastic anemia (Diamond-Blackfan anemia), idiopathic thrombocytopenic purpura in adults (intravenous administration only; intramuscular administration is contraindicated), pure red cell aplasia, selected cases of secondary thrombocytopenia. Miscellaneous: Trichinosis with neurologic or myocardial involvement, tuberculous meningitis with subarachnoid block or impending block when used concurrently with appropriate antituberculous chemotherapy.
Neoplastic diseases: For the palliative management of leukemias and lymphomas. Nervous System: Acute exacerbations of multiple sclerosis; cerebral edema associated with primary or metastatic brain tumor, or craniotomy. Ophthalmic diseases: Sympathetic ophthalmia, uveitis and ocular inflammatory conditions unresponsive to topical corticosteroids.
Renal diseases: To induce diuresis or remission of proteinuria in idiopathic nephrotic syndrome or that due to lupus erythematosus. Respiratory diseases: Berylliosis, fulminating or disseminated pulmonary tuberculosis when used concurrently with appropriate antituberculous chemotherapy, idiopathic eosinophilic pneumonias, symptomatic sarcoidosis. Rheumatic disorders: As adjunctive therapy for short-term administration (to tide the patient over an acute episode or exacerbation) in acute gouty arthritis; acute rheumatic carditis; ankylosing spondylitis; psoriatic arthritis; rheumatoid arthritis, including juvenile rheumatoid arthritis (selected cases may require low-dose maintenance therapy).
For the treatment of dermatomyositis, temporal arteritis, polymyositis, and systemic lupus erythematosus.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION NOTE: After mixing as directed, some of the methylprednisolone sodium succinate for injection, USP formulations contain benzyl alcohol (see DESCRIPTION , WARNINGS and PRECAUTIONS, Pediatric Use ) Because of possible physical incompatibilities, methylprednisolone sodium succinate for injection, USP should not be diluted or mixed with other solutions. For reconstitution of methylprednisolone sodium succinate for injection, use only Water for Injection or Bacteriostatic Water for Injection with Benzyl Alcohol at room temperature (see DESCRIPTION ).
Prepare intravenous infusions only after reconstitution, use 5% dextrose in water, isotonic saline solution, or 5% dextrose in isotonic saline solution. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. This preparation may be administered by intravenous injection, by intravenous infusion, or by intramuscular injection, the preferred method for initial emergency use being intravenous injection.
Following the initial emergency period, consideration should be given to employing a longer acting injectable preparation or an oral preparation. There are reports of cardiac arrhythmias and/or cardiac arrest following the rapid administration of large intravenous doses of methylprednisolone sodium succinate for injection, USP ( greater than 0.5 gram administered over a period of less than 10 minutes ). Bradycardia has been reported during or after the administration of large doses of methylprednisolone sodium succinate, and may be unrelated to the speed or duration of infusion.
When high dose therapy is desired, the recommended dose of methylprednisolone sodium succinate for injection, USP sterile powder is 30 mg/kg administered intravenously over at least 30 minutes. This dose may be repeated every 4 to 6 hours for 48 hours. In general, high dose corticosteroid therapy should be continued only until the patient’s condition has stabilized; usually not beyond 48 to 72 hours.
In other indications, initial dosage will vary from 10 to 40 mg of methylprednisolone depending on the specific disease entity being treated. However, in certain overwhelming, acute, life-threatening situations, administrations in dosages exceeding the usual dosages may be justified and may be in multiples of the oral dosages. It Should Be Emphasized that Dosage Requirements are Variable and Must Be Individualized on the Basis of the Disease Under Treatment and the Response of the Patient.
After a favorable response is noted, the proper maintenance dosage should be determined by decreasing the initial drug dosage in small decrements at appropriate time intervals until the lowest dosage which will maintain an adequate clinical response is reached. Situations which may make dosage adjustments necessary are changes in clinical status secondary to remissions or exacerbations in the disease process, the patient’s individual drug responsiveness, and the effect of patient exposure to stressful situations not directly related to the disease entity under treatment.
In this latter situation, it may be necessary to increase the dosage of the corticosteroid for a period of time consistent with the patient’s condition. If after long-term therapy the drug is to be stopped, it is recommended that it be withdrawn gradually rather than abruptly. Methylprednisolone sodium succinate for injection, USP may be administered by intravenous or intramuscular injection or by intravenous infusion, the preferred method for initial emergency use being intravenous injection.
To administer by intravenous (or intramuscular) injection, prepare solution as directed. The desired dose may be administered intravenously over a period of several minutes. If desired, the medication may be administered in diluted solutions by adding Water for Injection or other suitable diluent (see below) to the vial and withdrawing the indicated…
⛔ Contraindications ▾
CONTRAINDICATIONS Methylprednisolone sodium succinate for injection, USP Sterile Powder is contraindicated: in systemic fungal infections and patients with known hypersensitivity to the product and its constituents. The methylprednisolone sodium succinate for injection, USP 40 mg presentation includes lactose monohydrate produced from cow’s milk. This presentation is therefore contraindicated in patients with a known or suspected hypersensitivity to cow’s milk or its components or other dairy products because it may contain trace amounts of milk ingredients. for intrathecal administration.
Reports of severe medical events have been associated with this route of administration. Intramuscular corticosteroid preparations are contraindicated for idiopathic thrombocytopenic purpura. Additional contraindication for the use of methylprednisolone sodium succinate for injection, USP Sterile powder preserved with benzyl alcohol: Formulations preserved with benzyl alcohol are contraindicated for use in premature infants.
(see WARNINGS and PRECAUTIONS, Pediatric Use ).
⚠️ Warnings ▾
WARNINGS Serious Neurologic Adverse Reactions with Epidural Administration Serious neurologic events, some resulting in death, have been reported with epidural injection of corticosteroids. Specific events reported include, but are not limited to, spinal cord infarction, paraplegia, quadriplegia, cortical blindness, and stroke. These serious neurologic events have been reported with and without use of fluoroscopy.
The safety and effectiveness of epidural administration of corticosteroids have not been established, and corticosteroids are not approved for this use. General Formulations with preservative ( see DESCRIPTION ) contain benzyl alcohol, which is potentially toxic when administered locally to neural tissue. Exposure to excessive amounts of benzyl alcohol has been associated with toxicity (hypotension, metabolic acidosis), particularly in neonates, and an increased incidence of kernicterus, particularly in small preterm infants.
There have been rare reports of deaths, primarily in preterm infants, associated with exposure to excessive amounts of benzyl alcohol. The amount of benzyl alcohol from medications is usually considered negligible compared to that received in flush solutions containing benzyl alcohol. Administration of high dosages of medications containing this preservative must take into account the total amount of benzyl alcohol administered.
The amount of benzyl alcohol at which toxicity may occur is not known. If the patient requires more than the recommended dosages or other medications containing this preservative, the practitioner must consider the daily metabolic load of benzyl alcohol from these combined sources (see PRECAUTIONS, Pediatric Use ). Injection of methylprednisolone sodium succinate may result in dermal and/or subdermal changes forming depressions in the skin at the injection site.
In order to minimize the incidence of dermal and subdermal atrophy, care must be exercised not to exceed recommended doses in injections. Injection into the deltoid muscle should be avoided because of a high incidence of subcutaneous atrophy. Rare instances of anaphylactoid reactions have occurred in patients receiving corticosteroid therapy (see ADVERSE REACTIONS ).
In patients receiving the 40 mg presentation of methylprednisolone sodium succinate during the treatment for acute allergic conditions and where these symptoms worsen or any new allergic symptoms occur, consideration should be given to the potential for hypersensitivity reactions to cow’s milk ingredients (see CONTRAINDICATIONS ).f appropriate, administration of methylprednisolone sodium succinate for injection, USP should be stopped, and the patient’s condition should be treated accordingly. Alternative treatments, including the use of corticosteroid formulations that do not contain ingredients produced from cow’s milk, should be considered for acute allergy management, where appropriate.
Increased dosage of rapidly acting corticosteroids is indicated in patients on corticosteroid therapy who are subjected to any unusual stress before, during, and after the stressful situation. Results from one multicenter, randomized, placebo-controlled study with methylprednisolone hemisuccinate, an intravenous corticosteroid, showed an increase in early (at 2 weeks) and late (at 6 months) mortality in patients with cranial trauma who were determined not to have other clear indications for corticosteroid treatment.
High doses of systemic corticosteroids, including methylprednisolone sodium succinate, should not be used for the treatment of traumatic brain injury. Cardio-renal Average and large doses of corticosteroids can cause elevation of blood pressure, salt and water retention, and increased excretion of potassium. These effects are less likely to occur with the synthetic derivatives except when used in large doses.
Dietary salt restriction and potassium supplementation may be necessary. All corticosteroids increase calcium excretion. Literature reports sugges…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions have been reported with methylprednisolone sodium succinate or other corticosteroids: Allergic reactions: Allergic or hypersensitivity reactions, anaphylactoid reaction, anaphylaxis, angioedema. Blood and lymphatic system disorders: Leukocytosis. Cardiovascular: Bradycardia, cardiac arrest, cardiac arrhythmias, cardiac enlargement, circulatory collapse, congestive heart failure, fat embolism, hypertension, hypertrophic cardiomyopathy in premature infants, myocardial rupture following recent myocardial infarction (see WARNINGS ), pulmonary edema, syncope, tachycardia, thromboembolism, thrombophlebitis, vasculitis.
Dermatologic: Acne, allergic dermatitis, burning or tingling (especially in the perineal area after intravenous injection), cutaneous and subcutaneous atrophy, dry scaly skin, ecchymoses and petechiae, edema, erythema, hyperpigmentation, hypopigmentation, impaired wound healing, increased sweating, rash, sterile abscess, striae, suppressed reactions to skin tests, thin fragile skin, thinning scalp hair, urticaria. Endocrine: Decreased carbohydrate and glucose tolerance, development of cushingoid state, glycosuria, hirsutism, hypertrichosis, increased requirements for insulin or oral hypoglycemic agents in diabetes, manifestations of latent diabetes mellitus, menstrual irregularities, secondary adrenocortical and pituitary unresponsiveness (particularly in times of stress, as in trauma, surgery, or illness), suppression of growth in pediatric patients.
Fluid and electrolyte disturbances: Congestive heart failure in susceptible patients, fluid retention, hypokalemic alkalosis, potassium loss, sodium retention. Gastrointestinal: Abdominal distention, bowel/bladder dysfunction (after intrathecal administration), elevation in serum liver enzyme levels (usually reversible upon discontinuation), hepatomegaly, increased appetite, nausea, pancreatitis, peptic ulcer with possible perforation and hemorrhage, perforation of the small and large intestine (particularly in patients with inflammatory bowel disease), ulcerative esophagitis.
Hepatobiliary: Hepatitis (see WARNINGS , Drug-Induced Liver Injury ). Metabolic: Negative nitrogen balance due to protein catabolism. Musculoskeletal: Aseptic necrosis of femoral and humeral heads, Charcot-like arthropathy, loss of muscle mass, muscle weakness, osteoporosis, pathologic fracture of long bones, post injection flare (following intra-articular use), steroid myopathy, tendon rupture, vertebral compression fractures.
Neurologic/Psychiatric: Convulsions, depression, emotional instability, euphoria, headache, increased intracranial pressure with papilledema (pseudotumor cerebri) usually following discontinuation of treatment, insomnia, mood swings, neuritis, neuropathy, paresthesia, personality changes, psychic disorders, vertigo. Arachnoiditis, meningitis, paraparesis/paraplegia, and sensory disturbances have occurred after intrathecal administration (see WARNINGS, Neurologic ). Ophthalmic: Exophthalmos, glaucoma, increased intraocular pressure, posterior subcapsular cataracts, rare instances of blindness associated with periocular injections.
Vascular :Flushing. Other: Abnormal fat deposits, decreased resistance to infection, hiccups, increased or decreased motility and number of spermatozoa, injection site infections following non-sterile administration (see WARNINGS ), malaise, moon face, weight gain. To report SUSPECTED ADVERSE REACTIONS, contact Tianjin Kingyork Pharmaceuticals Co., Ltd, at 86-22-25299571 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch. for voluntary reporting of adverse reactions.
🔄 Drug Interactions ▾
Drug Interactions Aminoglutethimide: Aminoglutethimide may lead to a loss of corticosteroid-induced adrenal suppression. Amphotericin B injection and potassium-depleting agents: When corticosteroids are administered concomitantly with potassium-depleting agents (i.e., amphotericin B, diuretics), patients should be observed closely for development of hypokalemia. There have been cases reported in which concomitant use of amphotericin B and hydrocortisone was followed by cardiac enlargement and congestive heart failure.
Antibiotics: Macrolide antibiotics have been reported to cause a significant decrease in corticosteroid clearance (see Drug Interactions , Hepatic Enzyme Inhibitors ). Anticholinesterases: Concomitant use of anticholinesterase agents and corticosteroids may produce severe weakness in patients with myasthenia gravis. If possible, anticholinesterase agents should be withdrawn at least 24 hours before initiating corticosteroid therapy.
Anticoagulants, oral: Coadministration of corticosteroids and warfarin usually results in inhibition of response to warfarin, although there have been some conflicting reports. Therefore, coagulation indices should be monitored frequently to maintain the desired anticoagulant effect. Antidiabetics: Because corticosteroids may increase blood glucose concentrations, dosage adjustments of antidiabetic agents may be required.
Antitubercular drugs: Serum concentrations of isoniazid may be decreased. Cholestyramine: Cholestyramine may increase the clearance of corticosteroids. Cyclosporine: Increased activity of both cyclosporine and corticosteroids may occur when the two are used concurrently.
Convulsions have been reported with this concurrent use. Digitalis glycosides: Patients on digitalis glycosides may be at increased risk of arrhythmias due to hypokalemia. Estrogens, including oral contraceptives: Estrogens may decrease the hepatic metabolism of certain corticosteroids, thereby increasing their effect.
Hepatic Enzyme Inducers (e.g., barbiturates, phenytoin, carbamazepine, rifampin): Drugs which induce cytochrome P450 3A4 enzyme activity may enhance the metabolism of corticosteroids and require that the dosage of the corticosteroid be increased. Hepatic Enzyme Inhibitors (e.g., ketoconazole, macrolide antibiotics such as erythromycin and troleandomycin): Drugs which inhibit cytochrome P450 3A4 have the potential to result in increased plasma concentrations of corticosteroids. Ketoconazole: Ketoconazole has been reported to significantly decrease the metabolism of certain corticosteroids by up to 60%, leading to an increased risk of corticosteroid side effects.
Nonsteroidal anti-inflammatory agents (NSAIDs): Concomitant use of aspirin (or other nonsteroidal anti-inflammatory agents) and corticosteroids increases the risk of gastrointestinal side effects. Aspirin should be used cautiously in conjunction with corticosteroids in hypoprothrombinemia. The clearance of salicylates may be increased with concurrent use of corticosteroids.
Skin tests: Corticosteroids may suppress reactions to skin tests. Vaccines: Patients on prolonged corticosteroid therapy may exhibit a diminished response to toxoids and live or inactivated vaccines due to inhibition of antibody response. Corticosteroids may also potentiate the replication of some organisms contained in live attenuated vaccines.
Routine administration of vaccines or toxoids should be deferred until corticosteroid therapy is discontinued if possible (see WARNINGS, Immunosuppression and Increased Risk of Infection, Vaccination ).
🤰 Pregnancy ▾
Pregnancy: Teratogenic effects Corticosteroids have been shown to be teratogenic in many species when given in doses equivalent to the human dose. Animal studies in which corticosteroids have been given to pregnant mice, rats, and rabbits have yielded an increased incidence of cleft palate in the offspring. There are no adequate and well-controlled studies in pregnant women.
Corticosteroids should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Infants born to mothers who have received corticosteroids during pregnancy should be carefully observed for signs of hypoadrenalism. After mixing as directed, this product contains benzyl alcohol as a preservative.
Benzyl alcohol can cross the placenta. See PRECAUTIONS: Pediatric use .
🧒 Pediatric Use ▾
Pediatric Use Some formulations of this product contain benzyl alcohol as a preservative(see DESCRIPTION ). Carefully examine vials to determine formulation that is being used. Benzyl alcohol, a component of this product, has been associated with serious adverse events and death, particularly in pediatric patients.
The “gasping syndrome” (characterized by central nervous system depression, metabolic acidosis, gasping respirations, and high levels of benzyl alcohol and its metabolites found in the blood and urine) has been associated with benzyl alcohol dosages >99 mg/kg/day in neonates and low-birth-weight neonates. Additional symptoms may include gradual neurological deterioration, seizures, intracranial hemorrhage, hematologic abnormalities, skin breakdown, hepatic and renal failure, hypotension, bradycardia, and cardiovascular collapse.
Although normal therapeutic doses of this product ordinarily delivers amounts of benzyl alcohol that are substantially lower than those reported in association with the “gasping syndrome”, the minimum amount of benzyl alcohol at which toxicity may occur is not known. The risk of benzyl alcohol toxicity depends on the quantity administered and the hepatic capacity to detoxify the chemical. Premature and low-birth-weight infants, as well as patients receiving high dosages, may be more likely to develop toxicity.
Practitioners administering this and other medications containing benzyl alcohol should consider the combined daily metabolic load of benzyl alcohol from all sources. The efficacy and safety of corticosteroids in the pediatric population are based on the well-established course of effect of corticosteroids which is similar in pediatric and adult populations. Published studies provide evidence of efficacy and safety in pediatric patients for the treatment of nephrotic syndrome (>2 years of age), and aggressive lymphomas and leukemias (>1 month of age).
Other indications for pediatric use of corticosteroids, e.g., severe asthma and wheezing, are based on adequate and well-controlled trials conducted in adults, on the premises that the course of the diseases and their pathophysiology are considered to be substantially similar in both populations. The adverse effects of corticosteroids in pediatric patients are similar to those in adults (see ADVERSE REACTIONS ). Like adults, pediatric patients should be carefully observed with frequent measurements of blood pressure, weight, height, intraocular pressure, and clinical evaluation for the presence of infection, psychosocial disturbances, thromboembolism, peptic ulcers, cataracts, and osteoporosis.
Pediatric patients who are treated with corticosteroids by any route, including systemically administered corticosteroids, may experience a decrease in their growth velocity. This negative impact of corticosteroids on growth has been observed at low systemic doses and in the absence of laboratory evidence of HPA axis suppression (i.e., cosyntropin stimulation and basal cortisol plasma levels). Growth velocity may therefore be a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA axis function.
The linear growth of pediatric patients treated with corticosteroids should be monitored, and the potential growth effects of prolonged treatment should be weighed against clinical benefits obtained and the availability of treatment alternatives. In order to minimize the potential growth effects of corticosteroids, pediatric patients should be titrated to the lowest effective dose. Hypertrophic cardiomyopathy may develop after administration of methylprednisolone to prematurely born infants, therefore appropriate diagnostic evaluation and monitoring of cardiac function and structure should be performed.
🆘 Overdosage ▾
OVERDOSAGE Treatment of acute overdosage is by supportive and symptomatic therapy. For chronic overdosage in the face of severe disease requiring continuous steroid therapy, the dosage of the corticosteroid may be reduced only temporarily, or alternate day treatment may be introduced.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Glucocorticoids, naturally occurring and synthetic, are adrenocortical steroids that are readily absorbed from the gastrointestinal tract. Naturally occurring glucocorticoids (hydrocortisone and cortisone), which also have salt-retaining properties, are used as replacement therapy in adrenocortical deficiency states. Their synthetic analogs are primarily used for their potent anti-inflammatory effects in disorders of many organ systems.
Glucocorticoids cause profound and varied metabolic effects. In addition, they modify the body's immune responses to diverse stimuli. Methylprednisolone is a potent anti-inflammatory steroid with greater anti-inflammatory potency than prednisolone and even less tendency than prednisolone to induce sodium and water retention.
Methylprednisolone sodium succinate has the same metabolic and anti-inflammatory actions as methylprednisolone. When given parenterally and in equimolar quantities, the two compounds are equivalent in biologic activity. Following the intravenous injection of methylprednisolone sodium succinate, demonstrable effects are evident within one hour and persist for a variable period.
Excretion of the administered dose is nearly complete within 12 hours. Thus, if constantly high blood levels are required, injections should be made every 4 to 6 hours. This preparation is also rapidly absorbed when administered intramuscularly and is excreted in a pattern similar to that observed after intravenous injection.
📦 How Supplied / Storage and Handling ▾
Methylprednisolone sodium succinate for injection, USP is a sterile, white or off-white lyophilized lumps or powder, available in the following packages: NDC Methylprednisolone Sodium Succinate for Injection, USP Packaging Configuration NDC 82094-401-50 40 mg Single- Dose Vial 25 vials per Carton NDC 82094-402-50 125 mg Single- Dose Vial 25 vials per Carton NDC 82094-403-50 500 mg Multi-Dose Vial 1 vial per Carton NDC 82094-404-50 1 g Multi-Dose Vial 1 vial per Carton NDC 82094-405-50 2 g Single –Dose Vial 1 vial per Carton Manufactured By Tianjin Kingyork Pharmaceuticals Co., Ltd.
(Tianjin. China) Dec 2025
📋 Description ▾
DESCRIPTION Methylprednisolone sodium succinate for injection, USP is an anti-inflammatory glucocorticoid, which contains methylprednisolone sodium succinate as the active ingredient. Methylprednisolone sodium succinate, USP, is the sodium succinate ester of methylprednisolone, and it occurs as a white, or nearly white, odorless hygroscopic, amorphous solid. It is very soluble in water and in alcohol; it is insoluble in chloroform and is very slightly soluble in acetone.
The chemical name for methylprednisolone sodium succinate is pregna-1,4-diene-3,20-dione, 21-(3-carboxy-1-oxopropoxy)-11, 17-dihydroxy-6-methyl-monosodium salt, (6α, 11β), and the molecular weight is 496.53. The structural formula is represented below: Methylprednisolone sodium succinate is soluble in water; it may be administered in a small volume of diluent and is well suited for intravenous use in situations where high blood levels of methylprednisolone are required rapidly. Methylprednisolone sodium succinate for injection, USP is available in following strengths for intravenous or intramuscular administration: 40 mg (Single- Dose Vial) Each mL (when mixed as directed) contains methylprednisolone sodium succinate equivalent to 40 mg methylprednisolone, also 1.6 mg monobasic sodium phosphate anhydrous; 17.46 mg dibasic sodium phosphate dried; and 25mg lactose hydrous.
This package does not contain diluent. The recommended diluents are Water for Injection USP or Bacteriostatic water for Injection USP. Bacteriostatic Water for Injection USP contains benzyl alcohol as a preservative.
125 mg (Single- Dose Vial) Each 2 mL (when mixed as directed) contains methylprednisolone sodium succinate equivalent to 125 mg methylprednisolone; also 1.6 mg monobasic sodium phosphate anhydrous; and 17.4 mg dibasic sodium phosphate dried. This package does not contain diluent. The recommended diluents are Water for Injection USP or Bacteriostatic water for Injection USP.
Bacteriostatic Water for Injection USP contains benzyl alcohol as a preservative. 500mg (Multi-Dose) Each 8 mL (when mixed as directed) contains methylprednisolone sodium succinate equivalent to 500 mg methylprednisolone; also 6.4 mg monobasic sodium phosphate anhydrous; 69.6 mg dibasic sodium phosphate dried. This package does not contain diluent.
Recommended diluent Bacteriostatic water for Injection contains benzyl alcohol as a preservative. 1 gram (Multi-Dose) Each 16 mL (when mixed as directed) contains methylprednisolone sodium succinate equivalent to 1 gram methylprednisolone; also 12.8 mg monobasic sodium phosphate anhydrous; 139.2 mg dibasic sodium phosphate dried. This package does not contain diluent.
Recommended diluent Bacteriostatic water for Injection contains benzyl alcohol as a preservative. 2 gram (Single- Dose Vial) Each 30.6 mL (when mixed as directed) contains methylprednisolone sodium succinate equivalent to 2 grams methylprednisolone; also 25.6 mg monobasic sodium phosphate anhydrous; 278 mg dibasic sodium phosphate dried. This package does not contain diluent.
Recommended diluent Bacteriostatic water for Injection contains benzyl alcohol as a preservative. IMPORTANT – Use only Water for Injection or Bacteriostatic Water for Injection with Benzyl Alcohol when reconstituting methylprednisolone sodium succinate for injection, USP. Use within 48 hours after mixing.
When necessary, the pH of each formula was adjusted with sodium hydroxide so that the pH of the reconstituted solution is within the USP specified range of 7 to 8. formula