
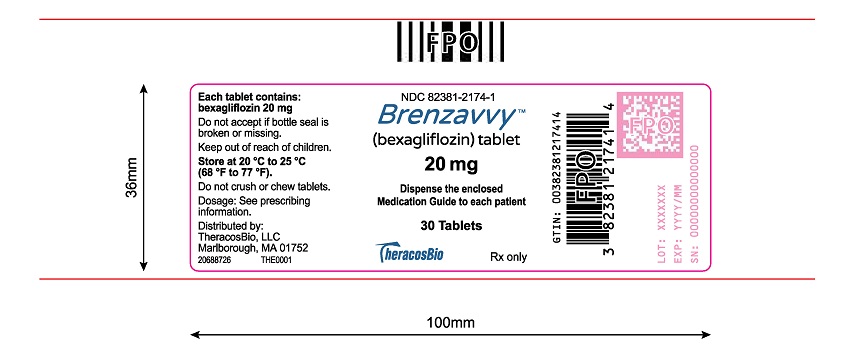
BRENZAVVY Bexagliflozin 20 mg Tablet, 30-count — NDC 82381-2174-1 (Billing 82381-2174-01)
This is a package of 30 tablets of BRENZAVVY Bexagliflozin 20 mg Tablet from TheracosBio, LLC, marketed since Jul 2023 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 82381-2174-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 82381 labeler · 2174 product · 1 package
- Package marketed since
- Jul 13, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 8238121741 4
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 084339
- GCN: 53596
- HICL (First Databank): 048644
- AHFS class code: 68:20.18.00
- RxCUI (RxNorm): 2637859
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Sodium-Glucose Cotransporter 2 Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Bexagliflozin is used along with diet and exercise to lower blood sugar levels in adults with type 2 diabetes (condition in which blood sugar is too high because the body does not produce or use insulin normally). Bexagliflozin is in a class of medications called sodium-glucose co-transporter 2 (SGLT2) inhibitors. It works by lowering blood sugar by causing the kidneys to get rid of more glucose in the urine. Bexagliflozin is not used to treat type 1 diabetes (condition in which the body does not produce insulin and, therefore, cannot control the amount of sugar in the blood). Over time, peopl...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 82381-2174-01 You're viewing this Main listing | 30 TABLET in 1 BOTTLE | 2023-07-13 | — | Active |
| 82381-2174-02 82381-2174-2 | 90 TABLET in 1 BOTTLE | 2023-07-13 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 82381-2174-02?
What NDC number is used to bill for this package of BRENZAVVY Bexagliflozin 20 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bexagliflozin 20 mg 51407-0918-30 | Golden | 30 tablets | — | — | FDA listed | — |
| Bexagliflozin 20 mg 82381-2000-08 | TheracosBio, | 30 tablets | — | — | FDA listed | — |
| Brenzavvy 20 mgthis 82381-2174-01 | TheracosBio, | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10533032 ↗ | Method of use | U-2214 | Jul 3, 2031 |
| US 8802637 ↗ | Drug substance | U-2214 | Aug 22, 2028 |
| US 8106021 ↗ | Method of use | U-2214 | Aug 22, 2028 |
| US 7838499 ↗ | Drug substance | U-2214 | Jan 30, 2029 |
| US 12594243 ↗ | Drug product | — | Oct 5, 2041 |
| US 8987323 ↗ | Drug substance | — | May 14, 2032 |
| US 10981942 ↗ | Drug substance | — | Jun 13, 2031 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Jan 20, 2028 |
Is there a generic version of BRENZAVVY 20 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from TheracosBio, LLC labeler code 82381
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BRENZAVVY is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. Limitations of Use BRENZAVVY is not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus. [see Warnings and Precautions ( 5.1 )] . BRENZAVVY is a sodium-glucose co-transporter 2 (SGLT2) inhibitor indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
( 1 ) Limitation of Use: Not recommended for use to improve glycemic control in patients with type 1 diabetes mellitus. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Recommended dose: 20 mg once daily, taken in the morning, with or without food. Do not crush or chew the tablet. ( 2.2 ) • Assess renal function before initiating BRENZAVVY and as clinically indicated.
Correct volume depletion before initiating ( 2.1 ) • Not recommended if eGFR less than 30 mL/min/1.73 m 2 . ( 2.1 ) • Withhold BRENZAVVY for at least 3 days, if possible, prior to surgery or procedures associated with prolonged fasting ( 2.3 ).
2.1Testing Prior to Initiation and During Treatment with BRENZAVVY • Assess renal function prior to initiation of BRENZAVVY and periodically thereafter as clinically indicated [see Warnings and Precautions ( 5.3 )] . BRENZAVVY is not recommended in patients with an eGFR less than 30 mL/min/1.73 m 2 • Assess volume status. In patients with volume depletion, correct this condition before initiating BRENZAVVY [see Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.5 , 8.6 )].
2.2Recommended Dosage • The recommended dosage of BRENZAVVY is 20 mg orally taken once daily in the morning, with or without food [see Clinical Pharmacology ( 12.3 )] . • Do not crush or chew the tablet.
2.3Temporary Interruption for Surgery • Withhold BRENZAVVY for at least 3 days, if possible, prior to surgery or procedures associated with prolonged fasting. Resume BRENZAVVY when the patient is clinically stable and has resumed oral intake [see Warnings and Precautions ( 5.1 ) and Clinical Pharmacology ( 12.2 )] .
2.4Recommendations Regarding Missed Dose If a dose is missed, instruct patients to take the dose as soon as possible. Advise patients not to double up the next dose.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 20 mg, blue, caplet-shaped, biconvex, bevel-edged, debossed with “2” and inverted “2” on one side. Tablets: 20 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS BRENZAVVY is contraindicated in patients: With hypersensitivity to bexagliflozin or any excipient in BRENZAVVY. Anaphylaxis and angioedema have been reported with sodium-glucose co-transporter 2 (SGLT2) inhibitors. • Hypersensitivity to bexagliflozin or any excipient in BRENZAVVY
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis: Consider ketone monitoring in patients at risk for ketoacidosis, as indicated. Assess for ketoacidosis regardless of presenting blood glucose levels and discontinue BRENZAVVY if ketoacidosis is suspected. Monitor patients for resolution of ketoacidosis before restarting.
( 5.1 ) Lower limb amputation: Monitor patients for infections or ulcers of the lower limbs, and institute appropriate treatment. ( 5.2 ) Volume depletion: May result in acute kidney injury. Before initiating BRENZAVVY, assess and correct volume status in patients with impaired renal function or low systolic blood pressure, elderly patients or patients on diuretics.
Monitor for signs and symptoms during therapy. ( 5.3 ) Genitourinary Infections, including Urosepsis, Pyelonephritis:, Necrotizing Fasciitis of the Perineum (Fournier’s Gangrene), and Genital Mycotic Infections: Monitor patients for signs and symptoms of genitourinary infections and treat promptly, if indicated. Immediately evaluate patients presenting with pain or tenderness, erythema, or swelling in the genital or perineal area, along with fever or malaise, for necrotizing fasciitis and if suspected, discontinue BRENZAVVY, and promptly institute appropriate medical and/or surgical intervention.
( 5.4 ) Hypoglycemia: Consider a lower dose of insulin or insulin secretagogue to reduce risk of hypoglycemia when used in combination with BRENZAVVY. ( 5.5 )
5.1Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis In patients with type 1 diabetes mellitus, BRENZAVVY significantly increases the risk of diabetic ketoacidosis, a life-threatening event, beyond background rate. In placebo-controlled trials of patients with type 1 diabetes mellitus, the risk of ketoacidosis was markedly increased in patients who received sodium glucose transporter 2 (SGLT2) inhibitors compared to patients who received placebo. BRENZAVVY is not indicated for glycemic control in patients with type 1 diabetes mellitus.
Type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are also risk factors for ketoacidosis. There have been postmarketing reports of fatal events of ketoacidosis in patients with type 2 diabetes mellitus using SGLT2 inhibitors. Precipitating conditions for diabetic ketoacidosis or other ketoacidosis include under-insulinization due to insulin dose reduction or missed insulin doses, acute febrile illness, reduced caloric intake, ketogenic diet, surgery, volume depletion, and alcohol abuse.
Signs and symptoms are consistent with dehydration and severe metabolic acidosis and include nausea, vomiting, abdominal pain, generalized malaise, and shortness of breath. Blood glucose levels at presentation may be below those typically expected for diabetic ketoacidosis (e.g., less than 250 mg/dL). Ketoacidosis and glucosuria may persist longer than typically expected.
Urinary glucose excretion persists for 3 days after discontinuing BRENZAVVY [see Clinical Pharmacology ( 12.2 )] ; however, there have been postmarketing reports of ketoacidosis and/or glucosuria lasting greater than 6 days and some up to 2 weeks after discontinuation of SGLT2 inhibitors. Consider ketone monitoring in patients at risk for ketoacidosis if indicated by the clinical situation. Assess for ketoacidosis regardless of presenting blood glucose levels in patients who present with signs and symptoms consistent with severe metabolic acidosis.
If ketoacidosis is suspected, discontinue BRENZAVVY, promptly evaluate, and treat ketoacidosis, if confirmed. Monitor patients for resolution of ketoacidosis before restarting BRENZAVVY. Withhold BRENZAVVY, if possible, in temporary clinical situations that could predispose patients to ketoacidosis.
Resume BRENZAVVY when the patient is clinically stable and has resumed oral intake [see Dosage and Administration ( 2.3 )] .… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following important adverse reactions are described below and elsewhere in the labeling: Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis [see Warnings and Precautions ( 5.1 )] Lower Limb Amputation [see Warnings and Precautions ( 5.2 ) ] Volume Depletion [see Warnings and Precautions ( 5.3 )] Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier’s Gangrene), and Genital Mycotic Infections [see Warnings and Precautions ( 5.4 )] Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues [see Warnings and Precautions ( 5.5 )] Most common adverse reactions (incidence > 5%) are female genital mycotic infections, urinary tract infection and increased urination.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact TheracosBio at 1-855-BRENZAVVY (1-855-273-6928) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Pool of Placebo-Controlled Trials Evaluating BRENZAVVY 20 mg The data in Table 1 are derived from three trials in adults with type 2 diabetes mellitus: two 24-week placebo-controlled trials (one as monotherapy and another as add-on to metformin therapy; Trials 1 and 2, respectively) [see Clinical Studies ( 14.2 , 14.3 )] and a 12-week, placebo-controlled, dose-ranging, monotherapy trial (only the data from the 20 mg dosage of BRENZAVVY per day were included in this pool).
In these pooled trials, patients received placebo (N = 300) or BRENZAVVY 20 mg (N = 372), once daily. The mean age of the population was 56 years and 5% of the patients were older than 75 years of age. Fifty-seven percent (57%) were male and 45% were White, 38% Asian, 15% Black and 2% other races.
At baseline, the mean duration of type 2 diabetes mellitus was 7.7 years and the mean hemoglobin A1c (HbA1c) was 8.2%. Established microvascular complications of type 2 diabetes mellitus at baseline included diabetic nephropathy (0.8%), retinopathy (24%), and peripheral neuropathy (33%). Baseline renal function was eGFR ≥ 60 mL/min/1.73 m 2 in 98% of patients and eGFR 45 to < 60 mL/min/1.73 m 2 in 2% of patients (mean eGFR 92 mL/min/1.73 m 2 ).
Table 1 shows common adverse reactions associated with the use of BRENZAVVY in these trials. These adverse reactions occurred more commonly in BRENZAVVY-treated patients than placebo-treated patients, and occurred in at least 2% of BRENZAVVY-treated patients. Table 1.
Adverse Reactions in Adults with Type 2 Diabetes Mellitus - Monotherapy or in Combination with Metformin* Percentage of Patients Placebo N = 300 BRENZAVVY N = 372 Increased urination a 3 7 Urinary tract infection b 4 6 Female genital mycotic infections c 0 6 Thirst d 2 3 Vaginal pruritus e 0 3 Male genital mycotic infection f 1 2 Hypoglycemia 1 2 * The three placebo-controlled trials included two monotherapy trials and one add-on combination trial with metformin in adults with type 2 diabetes mellitus (Trials 1, 2, and a 12-week dose ranging trial).
Adverse reactions were those that occurred more commonly in BRENZAVVY-treated patients than placebo-treated patients and occurred in at least 2% of BRENZAVVY-treated patients. a Includes: polyuria, pollakiuria, micturition urgency, nocturia. b Includes: dysuria, urinary tract infection, nitrite urine present, streptococcal urinary tract infection, cystitis. c Includes: vulvovaginal mycotic infection, vaginal infection, genital infection fungal, vulvovaginal candidiasis. Percentages calculated with the number of female patients in each group as denominator: placebo (N = 130), BRENZAVVY (N = 156). d Includes: thirst, polydipsia. e Includes: pruritus genital, vulvovaginal pruritus.
Percentages cal… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See Table 4 for clinically significant interactions with BRENZAVVY. Table 4. Clinically Significant Interactions with BRENZAVVY UGT Enzyme Inducers Clinical Impact UGT Enzyme Inducers may significantly reduce exposure to BRENZAVVY and lead to a decreased efficacy [ see Clinical Pharmacology ( 12.3 )].
Intervention Consider adding another antihyperglycemic agent in patients who require additional glycemic control. Concomitant Use with Insulin and Insulin Secretagogues Clinical Impact The risk of hypoglycemia is increased when BRENZAVVY is used in combination with insulin and/or an insulin secretagogue. Intervention A lower dose of insulin or insulin secretagogue may be required to minimize the risk of hypoglycemia when used in combination with BRENZAVVY.
Lithium Clinical Impact Concomitant use with SGLT2 inhibitors such as BRENZAVVY may decrease serum lithium concentrations. Intervention Monitor serum lithium concentration more frequently upon BRENZAVVY initiation and discontinuation. Positive Urine Glucose Test Clinical Impact SGLT2 inhibitors increase urinary glucose excretion and will lead to positive urine glucose tests.
Intervention Monitoring glycemic control with urine glucose tests is not recommended in patients taking SGLT2 inhibitors. Use alternative methods to monitor glycemic control. Interference with 1,5-anhydroglucitol (1,5-AG) Assay Clinical Impact Measurements of 1,5-AG are unreliable in assessing glycemic control in patients taking SGLT2 inhibitors.
Intervention Monitoring glycemic control with 1,5-AG assay is not recommended. Use alternative methods to monitor glycemic control.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Advise females of the potential risk to a fetus especially during the second and third trimesters. BRENZAVVY is not recommended during the second and third trimesters of pregnancy. ( 8.1 ) Lactation: Not recommended when breastfeeding.
( 8.2 ) Geriatric patients: Higher incidence of adverse reactions related to volume depletion. ( 8.5 ) Renal Impairment: Higher incidence of adverse reactions related to reduced renal function. ( 8.6 ) Hepatic Impairment: Not recommended for patients with severe hepatic impairment.
( 8.7 )
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects, BRENZAVVY is not recommended during the second and third trimesters of pregnancy. The available data on use of BRENZAVVY during pregnancy are insufficient to determine a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations ) .
In animal studies, adverse renal pelvic and tubule dilatations that were not fully reversible were observed in rats when bexagliflozin was administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy at exposures 11 times the 20 mg clinical dose (see Data ) . The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a peri-conceptional HbA1c > 7% and has been reported to be as high as 20% to 25% in women with a peri-conceptional HbA1c > 10%.
The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypoglycemia and hyperglycemia occur more frequently during pregnancy in patients with pre-gestational diabetes.
Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data Bexagliflozin administered to juvenile rats at 0.3, 3 or 30 mg/kg/day by oral gavage from postnatal days 21 to 90 caused a dose dependent increase in the incidence and severity of renal pelvic and tubular dilatation at ≥ 3 mg/kg (11 times the clinical dose of 20 mg based on AUC).
These outcomes occurred with drug exposure during periods of renal development in rats equivalent to the late second and third trimester of human renal development and did not fully reverse following a 1-month recovery period. In embryofetal development studies in rats and rabbits, bexagliflozin was administered at 7, 40, and 200 mg/kg/day (rats) and 5, 25, and 150 mg/kg/day (rabbits) during organogenesis. No adverse developmental effects were observed in rats at doses up to 200 mg/kg/day (551 times the clinical dose of 20 mg based on AUC).
Reduced maternal body weight, embryo lethality, and fetal malformations were observed in rabbits at 150 mg/kg/day (368 times the clinical dose of 20 mg based on AUC). In a prenatal and postnatal development study, bexagliflozin was administered to maternal rats by oral gavage during organogenesis and until weaning at doses of 7, 40, or 200 mg/kg/day. Maternal mortality occurred at ≥ 40 mg/kg (79 times the clinical dose of 20 mg based on AUC), primarily following parturition.
Reduced gestational body weight, increased post-implantation loss, and smaller litter size were noted at 200 mg/kg (361 times the clinical dose of 20 mg based on AUC). In the offspring, lower body weight gain and decreased survival were noted at 200 mg/kg, which occurred in the presence of significant matern… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on animal data showing adverse renal effects, BRENZAVVY is not recommended during the second and third trimesters of pregnancy. The available data on use of BRENZAVVY during pregnancy are insufficient to determine a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy (see Clinical Considerations ) .
In animal studies, adverse renal pelvic and tubule dilatations that were not fully reversible were observed in rats when bexagliflozin was administered during a period of renal development corresponding to the late second and third trimesters of human pregnancy at exposures 11 times the 20 mg clinical dose (see Data ) . The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a peri-conceptional HbA1c > 7% and has been reported to be as high as 20% to 25% in women with a peri-conceptional HbA1c > 10%.
The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Hypoglycemia and hyperglycemia occur more frequently during pregnancy in patients with pre-gestational diabetes.
Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data Bexagliflozin administered to juvenile rats at 0.3, 3 or 30 mg/kg/day by oral gavage from postnatal days 21 to 90 caused a dose dependent increase in the incidence and severity of renal pelvic and tubular dilatation at ≥ 3 mg/kg (11 times the clinical dose of 20 mg based on AUC).
These outcomes occurred with drug exposure during periods of renal development in rats equivalent to the late second and third trimester of human renal development and did not fully reverse following a 1-month recovery period. In embryofetal development studies in rats and rabbits, bexagliflozin was administered at 7, 40, and 200 mg/kg/day (rats) and 5, 25, and 150 mg/kg/day (rabbits) during organogenesis. No adverse developmental effects were observed in rats at doses up to 200 mg/kg/day (551 times the clinical dose of 20 mg based on AUC).
Reduced maternal body weight, embryo lethality, and fetal malformations were observed in rabbits at 150 mg/kg/day (368 times the clinical dose of 20 mg based on AUC). In a prenatal and postnatal development study, bexagliflozin was administered to maternal rats by oral gavage during organogenesis and until weaning at doses of 7, 40, or 200 mg/kg/day. Maternal mortality occurred at ≥ 40 mg/kg (79 times the clinical dose of 20 mg based on AUC), primarily following parturition.
Reduced gestational body weight, increased post-implantation loss, and smaller litter size were noted at 200 mg/kg (361 times the clinical dose of 20 mg based on AUC). In the offspring, lower body weight gain and decreased survival were noted at 200 mg/kg, which occurred in the presence of significant maternal toxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BRENZAVVY have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use In 9 clinical trials of BRENZAVVY, 1047 (40.6%) patients 65 years and older, and 212 (8.2%) patients 75 years and older were exposed to BRENZAVVY [see Clinical Studies ( 14 )] . One of the 9 trials enrolled patients with type 2 diabetes mellitus who had either established CVD or were at increased risk for CVD (Trial 6), and had a total of 571 (50%) patients treated with BRENZAVVY who were 65 years and older, and 113 (10%) patients treated with BRENZAVVY who were 75 years and older [see Clinical Studies ( 14.5 )] .
No overall differences in the effectiveness of BRENZAVVY have been observed between patients 65 years of age and older and younger adult patients. Among patients aged 65 and older in this trial, volume depletion events were reported in 7.6% and 9.8% of patients in the placebo and BRENZAVVY groups, respectively [see Warnings and Precautions ( 5.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE In the event of an overdose of BRENZAVVY, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Employ the usual supportive measures as dictated by the patient’s clinical status. Removal of bexagliflozin by hemodialysis has not been studied.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bexagliflozin is an inhibitor of sodium-glucose co-transporter 2 (SGLT2), the transporter responsible for reabsorption of the majority of glucose from the renal glomerular filtrate in the renal proximal tubule. By inhibiting SGLT2, bexagliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion.
12.2Pharmacodynamics Urinary Glucose Excretion and Urinary Volume Dose-dependent increases in urinary glucose excretion (UGE) accompanied by increases in urine volume were observed in healthy subjects and in adults with type 2 diabetes mellitus following single- and multiple-dose administration of bexagliflozin. Dose-response analysis indicates that 20 mg bexagliflozin provides near-maximal UGE. Elevated UGE was maintained after multiple-dose administration.
Cardiac Electrophysiology At 5 times the recommended dose, bexagliflozin does not prolong the QTc interval to any clinically significant extent.
12.3Pharmacokinetics The pharmacokinetics of bexagliflozin are similar in healthy subjects and adults with type 2 diabetes mellitus. Following dosing in the fasted state, mean C max and AUC 0-∞ were 134 ng/mL and 1,162 ng·h/mL, respectively. Bexagliflozin does not exhibit time-dependent pharmacokinetics and accumulates in plasma up to ~20% following multiple dosing.
Absorption Following oral administration of BRENZAVVY, peak plasma concentrations of bexagliflozin were reached between 2 – 4 hours post-dose and can be delayed if taken after a meal or by medications that slow gastric emptying. Plasma C max and AUC of bexagliflozin increase in a dose-proportional manner following single doses from 3 mg (0.15 times the recommended dose) to 90 mg (4.5 times the recommended dose). Effect of Food Administration of BRENZAVVY after consumption of a standard high-fat, high-caloric meal increased C max and AUC by 31% and 10%, respectively, compared to dosing in the fasted state.
The median T max was increased to 5 hours. The effects of food on bexagliflozin pharmacokinetics are not considered clinically relevant [see Dosage and Administration ( 2.2 )] . Distribution Bexagliflozin is approximately 93% bound to plasma protein.
Neither renal nor hepatic impairment substantially alters protein binding. The apparent volume of distribution is 262 L. Elimination Metabolism Bexagliflozin is mainly metabolized by UGT1A9 and, to a lesser extent, CYP3A.
In plasma the most abundant metabolite is the pharmacologically inactive 3′- O -glucuronide, which was found to constitute 32.2% of the parent compound AUC in a radiolabeled tracer study. None of the metabolites are expected to have clinically relevant pharmacological effects. Excretion The apparent oral clearance of bexagliflozin is
19.1L/h by population pharmacokinetic modeling. The apparent terminal elimination half-life of bexagliflozin was approximately 12 hours. Following administration of an oral [ 14 C]-bexagliflozin solution to healthy subjects, 91.6% of input radioactivity was recovered, 51.1% in feces, the majority as bexagliflozin, and 40.5% in urine, largely as the 3′- O -glucuronide.
The proportion of input radioactivity recovered as bexagliflozin in urine and feces was 1.5% and 28.7%, respectively Specific Populations Patients with Renal Impairment In a clinical pharmacology study in patients with type 2 diabetes mellitus and mild (eGFR 60 to 89 mL/min/1.73 m 2 ), moderate (eGFR 30 to 59 mL/min/1.73 m 2 ), and severe (eGFR less than 30 mL/min/1.73 m 2 ) renal impairment, the AUC of bexagliflozin was 7%, 34% and 54% greater than in patients with normal renal function, respectively, after administration of a single 20 mg dose of BRENZAVVY.
These increases in bexagliflozin AUC are not considered clinically meaningful. Consistent with the mechanism of action of bexagliflozin, the 24-hour UGE in patients with type 2 diabetes mellitus and mild, moderate, and severe… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bexagliflozin is an inhibitor of sodium-glucose co-transporter 2 (SGLT2), the transporter responsible for reabsorption of the majority of glucose from the renal glomerular filtrate in the renal proximal tubule. By inhibiting SGLT2, bexagliflozin reduces renal reabsorption of filtered glucose and lowers the renal threshold for glucose, and thereby increases urinary glucose excretion.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BRENZAVVY 20 mg tablets are blue, caplet-shaped, biconvex, bevel-edged, film-coated debossed with “2” and inverted “2” on one side. • Bottles of 30 tablets – NDC 82381-2174-1 • Bottles of 90 tablets – NDC 82381-2174-2 Storage and Handling Store from 20 °C to 25 °C (68 °F to 77 °F); excursions permitted between 15 °C to 30 °C (59 °F to 86 °F) [see USP Controlled Room Temperature] .
📋 Description ▾
11 DESCRIPTION BRENZAVVY tablets for oral use contain bexagliflozin, an SGLT2 inhibitor. The chemical name of bexagliflozin is (2S,3R,4R,5S,6R)-2-(4-chloro-3-(4-(2-cyclopropoxyethoxy)benzyl)phenyl)-6-(hydroxymethyl)tetrahydro-2H-pyran-3,4,5-triol. The molecular formula is C 24 H 29 ClO 7 and the molecular weight is 464.94 g/mol.
The structural formula is: Bexagliflozin is a white/off-white to pale yellow powder. It is very slightly soluble in water and freely soluble in methanol, acetone, ethylene glycol, and propylene glycol. It is slightly soluble in heptane, cyclohexane, and toluene.
Crystalline bexagliflozin is not hygroscopic. Each film-coated tablet contains 20 mg of bexagliflozin and the inactive ingredients colloidal silicon dioxide, glyceryl dibehenate, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene oxide, and poloxamer 188. In addition, the film coating ingredient, Opadry ® II Blue 85F99153, contains the inactive ingredients FD&C Blue #1/Brilliant Blue FCF Aluminum Lake, FD&C Blue #2/Indigo Carmine Aluminum Lake, macrogol 3350, partially hydrolyzed polyvinyl alcohol, talc, and titanium dioxide. brenzavvy-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Diabetic Ketoacidosis in Patients with Type 1 Diabetes Mellitus and Other Ketoacidosis Inform patients that BRENZAVVY can cause potentially fatal ketoacidosis and that type 2 diabetes mellitus and pancreatic disorders (e.g., history of pancreatitis or pancreatic surgery) are risk factors. Educate all patients on precipitating factors (such as insulin dose reduction or missed insulin doses, infection, reduced caloric intake, ketogenic diet, surgery, dehydration, and alcohol abuse) and symptoms of ketoacidosis (including nausea, vomiting, abdominal pain, tiredness, and labored breathing).
Inform patients that blood glucose may be normal even in the presence of ketoacidosis. Advise patients that they may be asked to monitor ketones. If symptoms of ketoacidosis occur, instruct patients to discontinue BRENZAVVY and seek medical attention immediately [see Warnings and Precautions ( 5.1 )] .
Lower Limb Amputation Counsel patients on the importance of routine preventive foot care. Instruct patients to monitor for any new pain or tenderness, sores or ulcers, or infections involving the leg or foot and to seek medical advice immediately if such signs or symptoms develop [see Warnings and Precautions ( 5.2 )] . Volume Depletion Inform patients that symptomatic hypotension may occur with BRENZAVVY and advise them to contact their healthcare provider if they experience such symptoms.
Inform patients that dehydration may increase the risk of hypotension, and to maintain adequate fluid intake. [see Warnings and Precautions ( 5.3 )] . Genitourinary Infections, including Urosepsis, Pyelonephritis, Necrotizing Fasciitis of the Perineum (Fournier’s Gangrene), and Genital Mycotic Infections Counsel patients that genitourinary infections may occur when taking BRENZAVVY and may become serious. Educate patients on the symptoms and advise them to seek medical advice if symptoms occur.
Specifically, advise patients to promptly seek medical attention if they develop pain or tenderness, redness, or swelling of the genitals or the area from the genitals back to the rectum, along with a fever above 100.4°F or malaise. [see Warnings and Precautions ( 5.4 )] . Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues Inform patients that the incidence of hypoglycemia may increase when BRENZAVVY is added to insulin and/or an insulin secretagogue. Educate patients or caregivers on the signs and symptoms of hypoglycemia [see Warnings and Precautions ( 5.5 )] .
Pregnancy Advise pregnant patients and females of reproductive potential of the potential risk to a fetus with treatment with BRENZAVVY. Instruct patients to inform their healthcare provider if pregnant or planning to become pregnant [see Use in Specific Populations ( 8.1 )]. Lactation Advise patients that breastfeeding is not recommended during treatment with BRENZAVVY [see Use in Specific Populations ( 8.2 )].
Laboratory Tests Inform patients that their urine will test positive for glucose while taking BRENZAVVY due to its mechanism of action. [see Drug Interactions ( 7 )] Missed Dose Instruct patients to take BRENZAVVY only as prescribed. If a dose is missed, it should be taken as soon as possible. Advise patients not to double their next dose .[see Dosage and Administration ( 2.4 )].
Distributed by: TheracosBio, LLC 945 Concord Street Framingham, MA 01701 USA BRENZAVVY is a registered trademark of TheracosBio, LLC Other brands listed are the trademarks of their respective owners and are not trademarks of TheracosBio, LLC Copyright © 2026 TheracosBio, LLC All rights reserved.
💬 Medication Guide ▾
MEDGUIDE SECTION MEDICATION GUIDE BRENZAVVY ® (bren-ZA-vee) (bexagliflozin) tablets for oral use What is the most important information I should know about BRENZAVVY? BRENZAVVY can cause serious side effects, including: Diabetic Ketoacidosis (increased ketones in your blood or urine) in people with type 1 diabetes and other ketoacidosis. BRENZAVVY can cause ketoacidosis that can be life-threatening and may lead to death.
Ketoacidosis is a serious condition which needs to be treated in a hospital. People with type 1 diabetes have a high risk of getting ketoacidosis. People with type 2 diabetes or pancreas problems also have an increased risk of getting ketoacidosis.
Ketoacidosis can also happen in people who: are sick, cannot eat or drink as usual, skip meals, are on a diet high in fat and low in carbohydrates (ketogenic diet), take less than the usual amount of insulin or miss insulin doses, drink too much alcohol, have a loss of too much fluid from the body (volume depletion), or who have surgery. Ketoacidosis can happen even if your blood sugar is less than 250 mg/dL. Your healthcare provider may ask you to periodically check ketones in your urine or blood.
Stop taking BRENZAVVY and call your healthcare provider or get medical help right away if you get any of the following. If possible, check for ketones in your urine or blood, even if your blood sugar is less than 250 mg/dL. o nausea otiredness ovomiting otrouble breathing ostomach-area (abdominal) pain o ketones in your urine or blood Amputations. BRENZAVVY may increase your risk of lower limb amputations.
You may be at a higher risk of lower limb amputation if you: have a history of amputation have had blocked or narrowed blood vessels, usually in your leg have damage to the nerves (neuropathy) in your leg have had diabetic foot ulcers or sores Call your healthcare provider right away if you have new pain or tenderness, any sores, ulcers, or infections in your leg or foot. Talk to your healthcare provider about proper foot care. Dehydration.
BRENZAVVY can cause some people to become dehydrated (the loss of body water and salt). Dehydration can make you feel dizzy, faint, light-headed, or weak, especially when you stand up (orthostatic hypotension). There have been reports of sudden worsening of kidney function in people who are taking BRENZAVVY.
You may be at higher risk of dehydration if you: take medicines that lower your blood pressure, including diuretics (water pills) are on a low sodium (salt) diet have kidney problems are 65 years of age or older Talk to your healthcare provider about what you can do to prevent dehydration including how much fluid you should drink on a daily basis.Call your healthcare provider right away if you reduce the amount of food or liquid you drink, for example if you are sick or cannot eat, or start to lose liquids from your body, for example from vomiting or diarrhea.
Genital and urinary tract infections. BRENZAVVY can cause serious infections in your genital area or urinary tract that could require hospitalization. A rare but serious bacterial infection called necrotizing fasciitis can cause damage to the tissue under the skin in the area between and around the anus and genitals (perineum).
This infection may require hospitalization, multiple surgeries, and could lead to death. Seek medical attention immediately if you have a fever or you are feeling very weak, tired or uncomfortable (malaise), and you develop any of the following symptoms in the area between and around your anus and genitals: o pain or tenderness o swelling o redness of skin (erythema) Also tell your healthcare provider if you have any of these signs or symptoms of urinary tract infections or yeast infections: Urinary tract infection: • burning feeling when you urinate • need to urinate often or right away • pain in the lower part of your stomach (pelvis) • blood in your urine You may also have a fever, back pain, nausea or vomiting Vaginal yeast infection: • vaginal o… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of bexagliflozin are similar in healthy subjects and adults with type 2 diabetes mellitus. Following dosing in the fasted state, mean C max and AUC 0-∞ were 134 ng/mL and 1,162 ng·h/mL, respectively. Bexagliflozin does not exhibit time-dependent pharmacokinetics and accumulates in plasma up to ~20% following multiple dosing.
Absorption Following oral administration of BRENZAVVY, peak plasma concentrations of bexagliflozin were reached between 2 – 4 hours post-dose and can be delayed if taken after a meal or by medications that slow gastric emptying. Plasma C max and AUC of bexagliflozin increase in a dose-proportional manner following single doses from 3 mg (0.15 times the recommended dose) to 90 mg (4.5 times the recommended dose). Effect of Food Administration of BRENZAVVY after consumption of a standard high-fat, high-caloric meal increased C max and AUC by 31% and 10%, respectively, compared to dosing in the fasted state.
The median T max was increased to 5 hours. The effects of food on bexagliflozin pharmacokinetics are not considered clinically relevant [see Dosage and Administration ( 2.2 )] . Distribution Bexagliflozin is approximately 93% bound to plasma protein.
Neither renal nor hepatic impairment substantially alters protein binding. The apparent volume of distribution is 262 L. Elimination Metabolism Bexagliflozin is mainly metabolized by UGT1A9 and, to a lesser extent, CYP3A.
In plasma the most abundant metabolite is the pharmacologically inactive 3′- O -glucuronide, which was found to constitute 32.2% of the parent compound AUC in a radiolabeled tracer study. None of the metabolites are expected to have clinically relevant pharmacological effects. Excretion The apparent oral clearance of bexagliflozin is
19.1L/h by population pharmacokinetic modeling. The apparent terminal elimination half-life of bexagliflozin was approximately 12 hours. Following administration of an oral [ 14 C]-bexagliflozin solution to healthy subjects, 91.6% of input radioactivity was recovered, 51.1% in feces, the majority as bexagliflozin, and 40.5% in urine, largely as the 3′- O -glucuronide.
The proportion of input radioactivity recovered as bexagliflozin in urine and feces was 1.5% and 28.7%, respectively Specific Populations Patients with Renal Impairment In a clinical pharmacology study in patients with type 2 diabetes mellitus and mild (eGFR 60 to 89 mL/min/1.73 m 2 ), moderate (eGFR 30 to 59 mL/min/1.73 m 2 ), and severe (eGFR less than 30 mL/min/1.73 m 2 ) renal impairment, the AUC of bexagliflozin was 7%, 34% and 54% greater than in patients with normal renal function, respectively, after administration of a single 20 mg dose of BRENZAVVY.
These increases in bexagliflozin AUC are not considered clinically meaningful. Consistent with the mechanism of action of bexagliflozin, the 24-hour UGE in patients with type 2 diabetes mellitus and mild, moderate, and severe renal impairment was 17%, 60%, and 83% lower than in patients with type 2 diabetes mellitus with normal renal function, respectively. Therefore, the glucose-lowering pharmacodynamic response to bexagliflozin declines with increasing severity of renal impairment [see Dosage and Administration ( 2.1 ), Warnings and Precautions ( 5.3 ), Use in Specific Populations ( 8.6 ), and Clinical Studies ( 14 )] .
The impact of hemodialysis on bexagliflozin exposure is not known. Patients with Hepatic Impairment In patients with moderate hepatic impairment (Child-Pugh class B), the AUC of bexagliflozin increased by 28%, and C max increased by 6.3% compared to subjects with normal hepatic function. These increases in bexagliflozin AUC and C max are not considered clinically meaningful.
There is no clinical experience in patients with Child-Pugh class C (severe) hepatic impairment [see Use in Specific Populations ( 8.7 ) Effects of Age, Body Weight, Sex, and Race Based on a population pharmacokinetic analysis, age, body weight, sex and race do… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Urinary Glucose Excretion and Urinary Volume Dose-dependent increases in urinary glucose excretion (UGE) accompanied by increases in urine volume were observed in healthy subjects and in adults with type 2 diabetes mellitus following single- and multiple-dose administration of bexagliflozin. Dose-response analysis indicates that 20 mg bexagliflozin provides near-maximal UGE. Elevated UGE was maintained after multiple-dose administration.
Cardiac Electrophysiology At 5 times the recommended dose, bexagliflozin does not prolong the QTc interval to any clinically significant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Overview of Clinical Trials BRENZAVVY has been studied as monotherapy (Trial 1) and in combination with metformin in adults with type 2 diabetes mellitus (Trials 2, 3, and 4) [see Clinical Studies ( 14.2 and 14.3 )] . BRENZAVVY has also been studied in adults with type 2 diabetes mellitus with moderate renal impairment (Trial 5) [see Clinical Studies ( 14.4 )] , and in adults with type 2 diabetes mellitus with established CVD or at increased risk for CVD (Trial 6) [see Clinical Studies ( 14.5 )] . Treatment with BRENZAVVY reduced hemoglobin A1c (HbA1c) compared to placebo and efficacy was noninferior to glimepiride (up-titrated to a maximum dose of 6 mg) and sitagliptin 100 mg once daily (see Trials 3 and 4).
The reduction in HbA1c by BRENZAVVY was shown across subgroups of age, sex, race, and geographic region.
14.2Glycemic Control in Adults with Type 2 Diabetes Mellitus - Monotherapy (Trial 1) A total of 207 adults with type 2 diabetes mellitus inadequately controlled (HbA1c between 7% and 10.5%) by diet and exercise participated in a randomized, double-blind, multi-center, 24-week, placebo-controlled trial (NCT02715258; referred to as Trial 1) to evaluate the efficacy of BRENZAVVY monotherapy. Patients were either treatment naïve or had discontinued a single oral antihyperglycemic treatment ≥ 6 weeks prior to entering a 2-week, single-blind, placebo run-in period.
Upon completion of the run-in period they were randomized (1:2) to placebo or BRENZAVVY 20 mg administered orally once daily. The mean age of the population was 55 years and 4% of the patients were older than 75 years of age. Forty-eight percent (48%) were male and 74% were White, 10% were Asian, 15% were Black and 1% were other races.
Fifty-two percent (52%) were Hispanic/Latino. At week 24, treatment with BRENZAVVY provided a statistically significant reduction in HbA1c compared to placebo (see Table 5 ). Table 5.
Glycemic Results from a 24-Week Placebo-Controlled Monotherapy Trial of BRENZAVVY in Adults with Type 2 Diabetes Mellitus (Trial 1) Placebo N = 69 BRENZAVVY N = 138 HbA1c (%) Baseline mean 7.9
8.1Change from baseline [adjusted mean (SE)] a -0.1 (0.1) -0.5 (0.1) Difference from placebo [adjusted mean] (95% CI) -0.4 (-0.6, -0.1) * Proportion of patients (%) achieving HbA1c <7% b 20% 31% FPG (mg/dL) Baseline mean 170 169 Change from baseline [adjusted mean (SE)] c -3 (4) -16 (3) Difference from placebo [adjusted mean] (95% CI) -14 (-24, -3) SE: Standard Error; CI: Confidence Interval; FPG: Fasting plasma glucose * Statistically significant (multiplicity adjusted one-sided p-value < 0.025) a Intention to treat population.
ANCOVA was used to analyze data using imputed values by return to baseline analysis for missing data at week 24 (9% and 7% for bexagliflozin and placebo, respectively). The ANCOVA model included treatment, country, background anti-diabetes treatment status (treatment naïve or not) and the baseline HbA1c value as a covariate. b Crude proportion using imputed HbA1c values for missing data at week 24 and averaged across multiply imputed datasets c Same model as for HbA1c endpoint but with baseline FPG instead of baseline HbA1c as a covariate.
Figure 3. Mean Change from Baseline in HbA1c (%) by Time and Treatment Vertical lines represent 95% confidence intervals. Treatment group least squares mean changes from baseline in HbA1c were estimated by an ANCOVA model using observed data for intermediate visits.
Numbers of patients per arm per measurement shown below plot. Return-to-baseline (RTB) analysis results at Week 24 are plotted to the right separately. brenzavvy-figure-3
14.3Glycemic Control in Adults with Type 2 Diabetes Mellitus – Combination Therapy (Trials 2, 3 and 4) Add-on Combination Therapy with Metformin (Trial 2) A total of 317 adults with type 2 diabetes mellitus inadequately controlled (HbA1c between 7.5% and 10.5%) by metformin monotherapy (≥ 1,000 mg/day or ≥ 1,500 mg/day for ≥ 8 weeks depending on… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Carcinogenesis was evaluated in 2-year studies in CD-1 mice at oral gavage doses of 15, 50, and 150 mg/kg/day and in Sprague-Dawley (SD) rats at 3, 10, and 30 mg/kg/day. In male rats, the dose was reduced to 1, 3, and 10 mg/kg/day at week 73 due to exacerbation of chronic progressive nephropathy resulting in excessive mortality. There were no drug-related neoplastic findings in mice or rats at up to the highest doses tested representing up to 156 times (mice) and 68 times (rats) the clinical dose of 20 mg based on AUC.
Mutagenesis Bexagliflozin was not mutagenic or clastogenic with or without metabolic activation in the in vitro Ames bacterial mutagenicity assay, the in vitro CHO cell assay, an in vivo micronucleus assay in rats, and an in vivo unscheduled hepatic DNA synthesis study in rats. Impairment of Fertility Bexagliflozin had no effects on mating, fertility or early embryonic development in male or female rats at any dose up to the highest dose of 200 mg/kg/day, which resulted in exposures 280 times (males) and 439 times (females) the 20 mg clinical dose (based on AUC).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Carcinogenesis was evaluated in 2-year studies in CD-1 mice at oral gavage doses of 15, 50, and 150 mg/kg/day and in Sprague-Dawley (SD) rats at 3, 10, and 30 mg/kg/day. In male rats, the dose was reduced to 1, 3, and 10 mg/kg/day at week 73 due to exacerbation of chronic progressive nephropathy resulting in excessive mortality. There were no drug-related neoplastic findings in mice or rats at up to the highest doses tested representing up to 156 times (mice) and 68 times (rats) the clinical dose of 20 mg based on AUC.
Mutagenesis Bexagliflozin was not mutagenic or clastogenic with or without metabolic activation in the in vitro Ames bacterial mutagenicity assay, the in vitro CHO cell assay, an in vivo micronucleus assay in rats, and an in vivo unscheduled hepatic DNA synthesis study in rats. Impairment of Fertility Bexagliflozin had no effects on mating, fertility or early embryonic development in male or female rats at any dose up to the highest dose of 200 mg/kg/day, which resulted in exposures 280 times (males) and 439 times (females) the 20 mg clinical dose (based on AUC).
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.4 ) 06/2026
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL brenzavvy-label-30s brenzavvy-label-90s
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |