
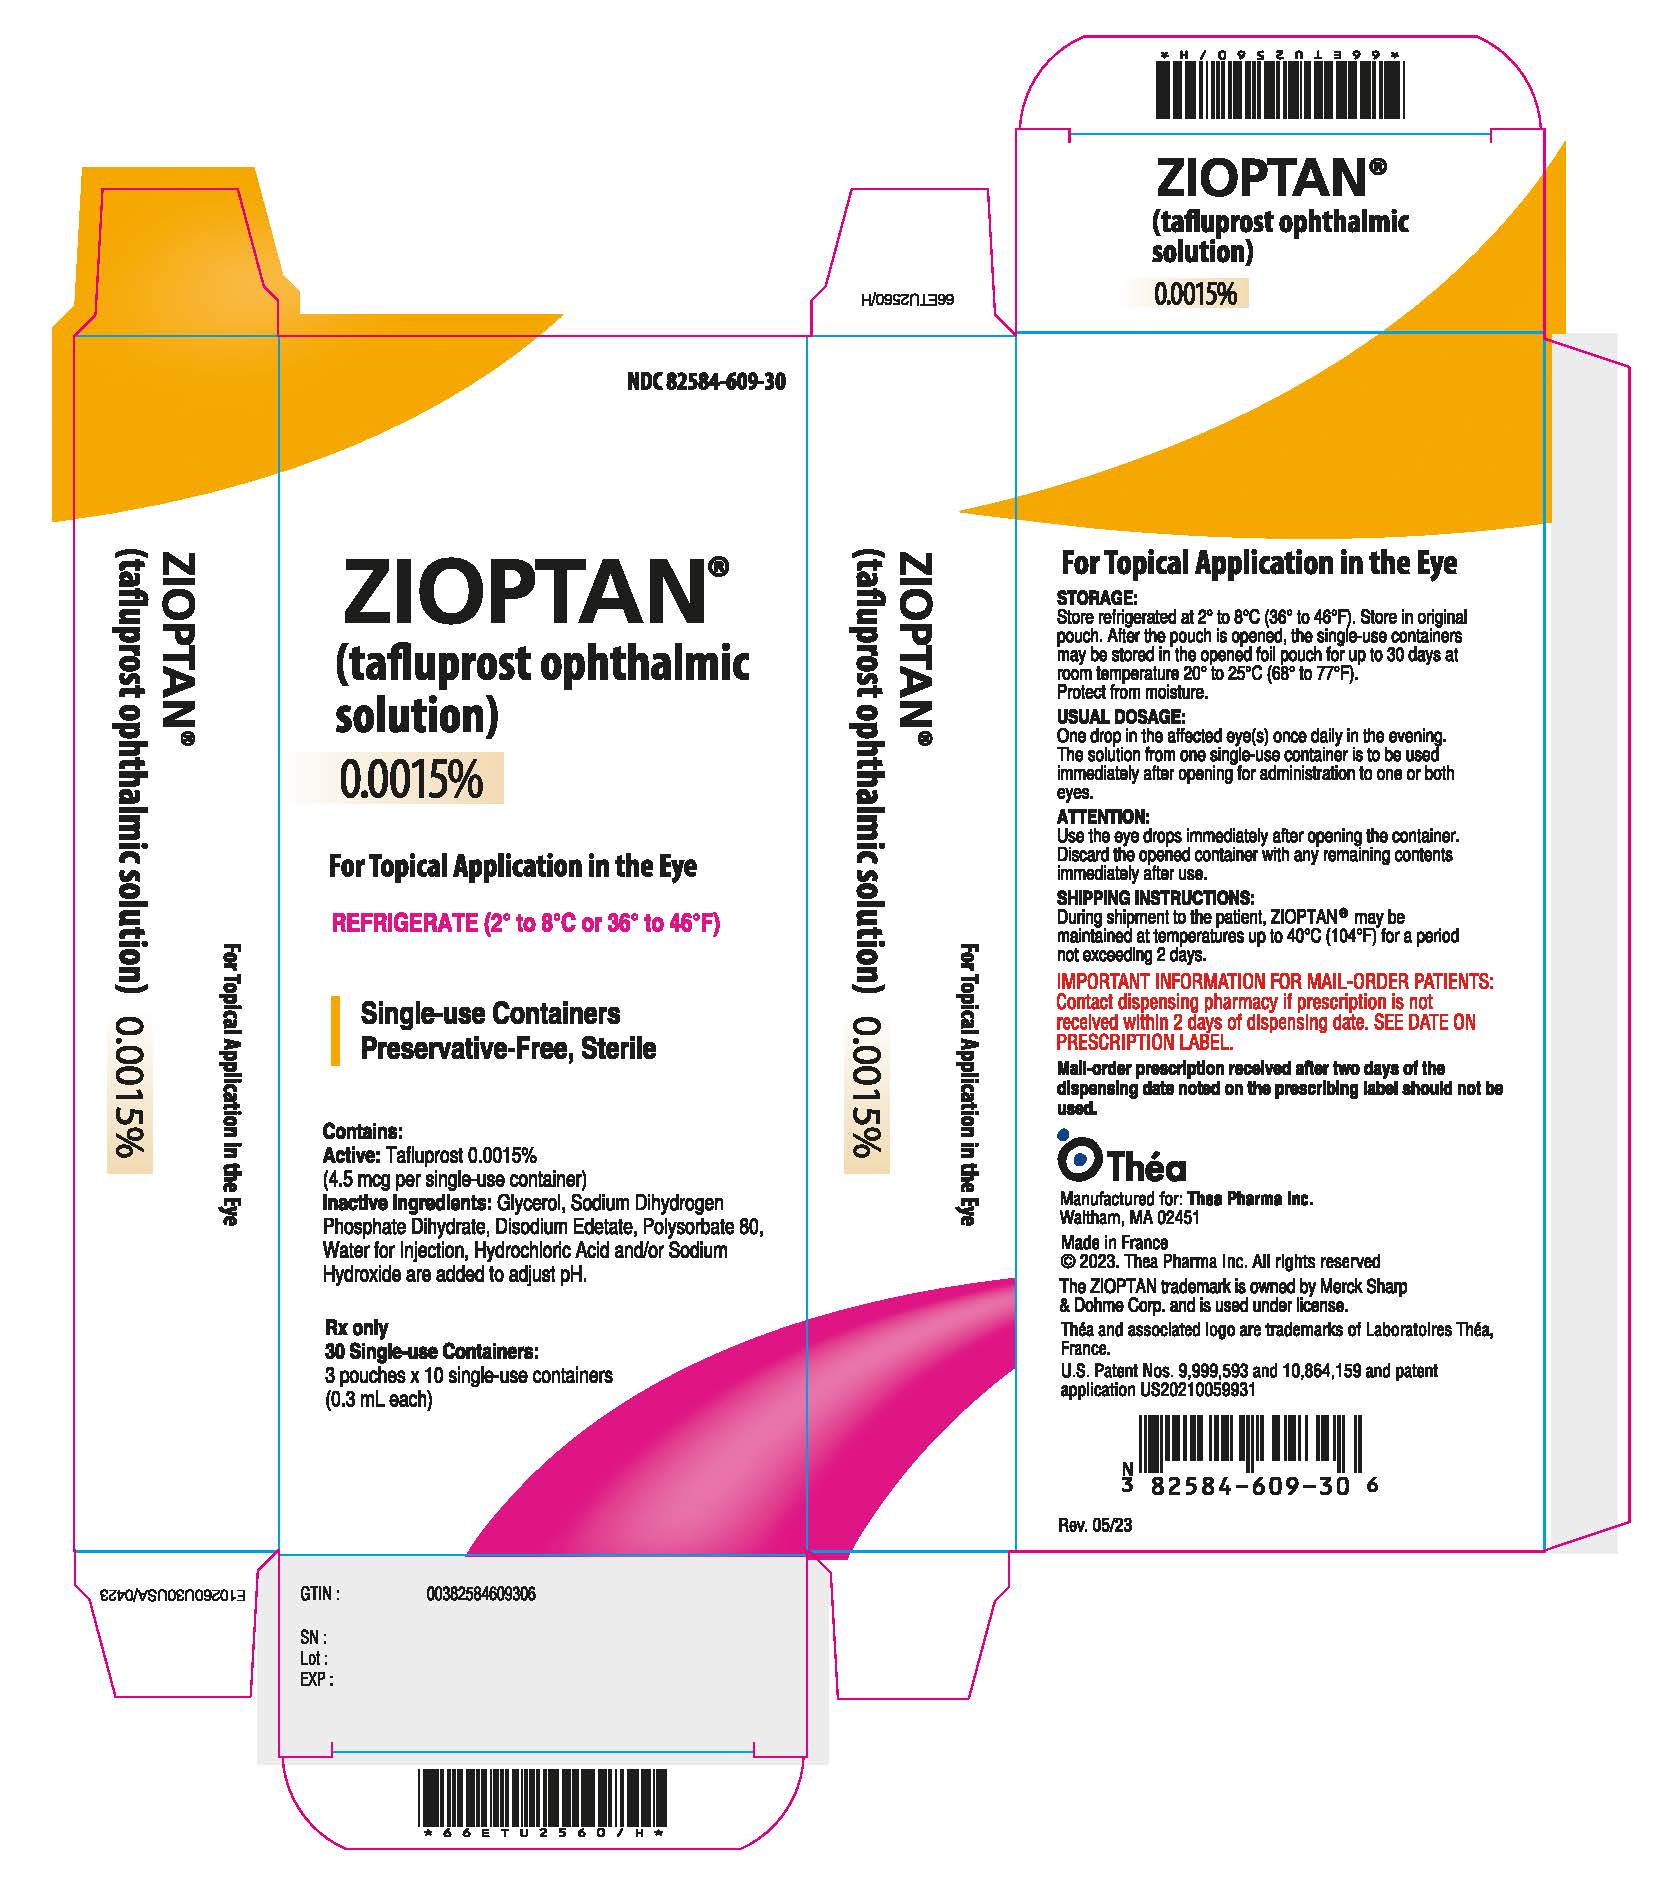
ZIOPTAN Tafluprost .015 mg/mL Solution/ Drops
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Prostaglandin Analog class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tafluprost ophthalmic is used to treat glaucoma (a condition in which increased pressure in the eye can lead to gradual loss of vision) and ocular hypertension (a condition which causes increased pressure in the eye). Tafluprost is in a class of medications called prostaglandin analogs. It works to lower pressure in the eye by increasing the flow of natural eye fluids out of the eye.
Read the full MedlinePlus article ↗- The evening timing isn't just a suggestion — studies show tafluprost works best when used at night, with its peak pressure-lowering effect hitting around 12 hours after you apply i...
- Why do I have to use this drop in the evening specifically?
- It can, yes — and this is one of the most important things to know. Tafluprost can gradually increase the brown pigment in your iris, which may darken the color of your eye over mo...
- Will this drug change the color of my eyes?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tafluprost — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 5QWK665956
A salt derived from phosphoric acid and sodium, used primarily as a buffer to control the acidity or pH of a medication, helping keep it stable during storage and use.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $8.491 | $254.73 / 30 vials |
| Medicaid paysCMS SDUD · 12 mo | $20.76 | $622.92 / 30 vials |
| Medicare drug plans payPart D · Q2 2026 | $8.44 | $253.23 / 30 vials |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tafluprost .0045 mg/.3mL 00781-6184-87 | Sandoz | 6 pouches | $2.487 | AT | Availability likely | save 71% |
| Tafluprost .015 mg/mL 50742-0339-30 | Ingenus | 6 pouches | $2.487 | AT | Availability likely | save 71% |
| Tafluprost Ophthalmic .0045 mg/.3mL 66993-0429-30 | Prasco | 3 pouches | $2.487 | AT | Availability likely | save 71% |
| Zioptan .015 mg/mLthis 82584-0609-30 | Thea | 3 pouches | $8.491 | AT | Availability likely | — |
| tafluprost .0045 mg/.3mL 42571-0264-26 | Micro | 1 pouch | — | AT | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10864159 ↗ | Method of use | U-778 | May 28, 2029 |
| US 9999593 ↗ | Drug product | — | May 28, 2029 |
Is there a generic version of ZIOPTAN 0.0015% EYE DROP?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 82584-0609-30 You're viewing this | 3 POUCH in 1 CARTON (82584-609-30) / 10 VIAL, SINGLE-USE in 1 POUCH (82584-609-01) / .3 mL in 1 VIAL, SINGLE-USE | 2022-10-28 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ZIOPTAN® is indicated for reducing elevated intraocular pressure in patients with open-angle glaucoma or ocular hypertension. ZIOPTAN is a prostaglandin analog indicated for reducing elevated intraocular pressure in patients with open-angle glaucoma or ocular hypertension. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Apply one drop in the affected eye(s) once daily in the evening. ( 2 )
2.1Recommended Dosage The recommended dosage is one drop in the conjunctival sac of the affected eye(s) once daily in the evening.
2.2Administration Instructions ZIOPTAN should not be administered more than once daily since it has been shown that more frequent administration of prostaglandin analogs may lessen the intraocular pressure (IOP) lowering effect. Reduction of the intraocular pressure starts approximately 2 to 4 hours after the first administration with the maximum effect reached after 12 hours. ZIOPTAN may be used concomitantly with other topical ophthalmic drug products to lower IOP.
If more than one topical ophthalmic product is being used, each one should be administered at least 5 minutes apart. The solution from one single-dose container is to be used immediately after opening for administration to one or both eyes. Since sterility cannot be maintained after the single-dose container is opened, discard the open single-dose container and the remaining contents immediately after administration.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ophthalmic solution: 0.0015% tafluprost in a single-dose container. Ophthalmic solution: 0.0015% tafluprost in a single-dose container. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS . Most common ocular adverse reaction is conjunctival hyperemia (4% to 20%). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Thea Pharma Inc. at 1-833-838-4028 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Preservative-containing or nonpreserved tafluprost 0.0015% was evaluated in 905 patients in five controlled clinical studies of up to 24-months duration. The most common adverse reaction observed in patients treated with tafluprost was conjunctival hyperemia which was reported in a range of 4% to 20% of patients.
Approximately 1% of patients discontinued therapy due to ocular adverse reactions. Ocular adverse reactions reported at an incidence of ≥ 2% in these clinical studies included ocular stinging/irritation (7%), ocular pruritus including allergic conjunctivitis (5%), cataract (3%), dry eye (3%), ocular pain (3%), eyelash darkening (2%), growth of eyelashes (2%) and vision blurred (2%). Nonocular adverse reactions reported at an incidence of 2% to 6% in these clinical studies in patients treated with tafluprost 0.0015% were headache (6%), common cold (4%), cough (3%) and urinary tract infection (2%).
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of tafluprost. Because postapproval adverse reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Respiratory disorders: exacerbation of asthma, dyspnea Eye disorders: iritis/uveitis In postmarketing use with prostaglandin analogs, periorbital and lid changes including deepening of the eyelid sulcus have been observed.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS . Use in pediatric patients is not recommended because of potential safety concerns related to increased pigmentation following long-term chronic use. ( 8.4 )
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of ZIOPTAN administration in pregnant women to inform of drug-associated risks. In animal reproduction studies, intravenous administration of tafluprost to pregnant rabbits and rats throughout organogenesis resulted in embryofetal toxicities at exposures ≥5-times the human dose in rabbit and ≥2362-times the human dose in rat. (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In embryo-fetal development studies, intravenous administration of tafluprost to pregnant rats and rabbits during organogenesis caused increases in post-implantation losses in both species and reductions in fetal body weights in rats (≥0.03 mcg/kg/day in rabbits, 5-times the maximum clinical exposure based on Cmax; ≥10 mcg/kg/day in rats, 2362-times the maximum clinical exposure based on Cmax). Tafluprost also increased the incidence of vertebral skeletal abnormalities in rats and the incidence of skull, brain and spine malformations in rabbits at these same doses.
In rats, there were no adverse effects on embryo-fetal development at a dose of 3 mcg/kg/day corresponding to maternal plasma levels of tafluprost acid that were 343 times the maximum clinical exposure based on Cmax. At the no-effect dose in rabbits (0.01 mcg/kg/day), maternal plasma levels of tafluprost acid were below the lower level of quantification (20 pg/mL). In a pre- and postnatal development study, intravenous administration of tafluprost to pregnant rats during organogenesis and through birth and lactation, caused increased mortality of newborns, decreased body weights and delayed pinna unfolding in offsprings.
The no observed adverse effect level was at a tafluprost intravenous dose of 0.3 mcg/kg/day which is greater than 3 times the maximum recommended clinical dose based on body surface area comparison.
8.2Lactation Risk Summary There are no data on the presence of tafluprost or its metabolites in human milk, the effects on the breastfed infant, or the effects on milk production following topical ocular administration. Tafluprost and/or its metabolites are present in rat milk following ocular administration. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
8.4Pediatric Use Use in pediatric patients is not recommended because of potential safety concerns related to increased pigmentation following long-term chronic use.
8.5Geriatric Use No overall clinical differences in safety or effectiveness have been observed between elderly and other adult patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of ZIOPTAN administration in pregnant women to inform of drug-associated risks. In animal reproduction studies, intravenous administration of tafluprost to pregnant rabbits and rats throughout organogenesis resulted in embryofetal toxicities at exposures ≥5-times the human dose in rabbit and ≥2362-times the human dose in rat. (see Data).
The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In embryo-fetal development studies, intravenous administration of tafluprost to pregnant rats and rabbits during organogenesis caused increases in post-implantation losses in both species and reductions in fetal body weights in rats (≥0.03 mcg/kg/day in rabbits, 5-times the maximum clinical exposure based on Cmax; ≥10 mcg/kg/day in rats, 2362-times the maximum clinical exposure based on Cmax). Tafluprost also increased the incidence of vertebral skeletal abnormalities in rats and the incidence of skull, brain and spine malformations in rabbits at these same doses.
In rats, there were no adverse effects on embryo-fetal development at a dose of 3 mcg/kg/day corresponding to maternal plasma levels of tafluprost acid that were 343 times the maximum clinical exposure based on Cmax. At the no-effect dose in rabbits (0.01 mcg/kg/day), maternal plasma levels of tafluprost acid were below the lower level of quantification (20 pg/mL). In a pre- and postnatal development study, intravenous administration of tafluprost to pregnant rats during organogenesis and through birth and lactation, caused increased mortality of newborns, decreased body weights and delayed pinna unfolding in offsprings.
The no observed adverse effect level was at a tafluprost intravenous dose of 0.3 mcg/kg/day which is greater than 3 times the maximum recommended clinical dose based on body surface area comparison.
🧒 Pediatric Use ▾
8.4Pediatric Use Use in pediatric patients is not recommended because of potential safety concerns related to increased pigmentation following long-term chronic use.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall clinical differences in safety or effectiveness have been observed between elderly and other adult patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY .
12.1Mechanism of Action Tafluprost acid, a prostaglandin analog is a selective FP prostanoid receptor agonist which is believed to reduce intraocular pressure by increasing uveoscleral outflow. The exact mechanism of action is unknown at this time.
12.3Pharmacokinetics . Absorption Following instillation, tafluprost is absorbed through the cornea and is hydrolyzed to the biologically active acid metabolite, tafluprost acid. Following instillation of one drop of the 0.0015% solution once daily into each eye of healthy volunteers, the plasma concentrations of tafluprost acid peaked at a median time of 10 minutes on both Days 1 and 8.
The mean plasma Cmax of tafluprost acid were 26 pg/mL and 27 pg/mL on Day 1, and Day 8, respectively. The mean plasma AUC estimates of tafluprost acid were 394 pg*min/mL and 432 pg*min/mL on day 1 and 8, respectively. Elimination Metabolism Tafluprost, an ester prodrug, is hydrolyzed to its biologically active acid metabolite in the eye.
The acid metabolite is further metabolized via fatty acid β-oxidation and phase II conjugation. Mean plasma tafluprost acid concentrations were below the limit of quantification of the bioanalytical assay (10 pg/mL) at 30 minutes following topical ocular administration of tafluprost 0.0015% ophthalmic solution.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tafluprost acid, a prostaglandin analog is a selective FP prostanoid receptor agonist which is believed to reduce intraocular pressure by increasing uveoscleral outflow. The exact mechanism of action is unknown at this time.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ZIOPTAN (tafluprost ophthalmic solution) 0.0015% is supplied as a sterile solution in translucent low density polyethylene single-dose containers packaged in foil pouches (10 single-dose containers per pouch). Each single-dose container has 0.3 mL solution corresponding to 0.0045 mg tafluprost. NDC 82584-609-30; Unit-of-Use Carton of 30.
Storage: Store refrigerated at 2° to 8°C (36° to 46°F). During shipment ZIOPTAN may be maintained at temperatures up to 40°C (104°F) for a period not exceeding 2 days. Mail-order prescriptions received after two days of the dispensing date noted in the prescribing label should not be used.
Store in the original pouch. After the pouch is opened, unopened single-dose containers may be stored in the opened foil pouch for up to 30 days at room temperature 20° to 25°C (68° to 77°F). Protect from moisture.
Write down the date you open the foil pouch in the space provided on the pouch. Discard any unopened containers 30 days after first opening the pouch.
📦 Storage and Handling ▾
Storage: Store refrigerated at 2° to 8°C (36° to 46°F). During shipment ZIOPTAN may be maintained at temperatures up to 40°C (104°F) for a period not exceeding 2 days. Mail-order prescriptions received after two days of the dispensing date noted in the prescribing label should not be used.
Store in the original pouch. After the pouch is opened, unopened single-dose containers may be stored in the opened foil pouch for up to 30 days at room temperature 20° to 25°C (68° to 77°F). Protect from moisture.
Write down the date you open the foil pouch in the space provided on the pouch. Discard any unopened containers 30 days after first opening the pouch.
📋 Description ▾
11 DESCRIPTION ZIOPTAN (tafluprost ophthalmic solution) 0.0015% contains tafluprost, a fluorinated analog of prostaglandin F2α, for topical ophthalmic use. The chemical name for tafluprost is 1-methylethyl (5Z)-7-{(1R,2R,3R,5S)-2-[(1E)-3,3-difluoro-4-phenoxy-1-butenyl}-3,5-dihydroxycyclopentyl]-5-heptenoate. The molecular formula of tafluprost is C25H34F2O5 and its molecular weight is 452.53.
Its structural formula is: Tafluprost is a colorless to light yellow viscous liquid that is practically insoluble in water. ZIOPTAN is supplied as a sterile solution with a pH range of 5.5 to 6.7 and an Osmolality range of 260 to 300 mOsmo/kg. ZIOPTAN contains Active: tafluprost 0.015 mg/mL; Inactives: disodium edetate, hydrochloric acid and/or sodium hydroxide (to adjust pH), glycerol, polysorbate 80, sodium dihydrogen phosphate dihydrate, and Water for Injection.
ZIOPTAN does not contain a preservative. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Potential for Pigmentation Advise patients about the potential for increased brown pigmentation of the iris, which may be permanent. Also inform patients about the possibility of eyelid skin darkening, which may be reversible after discontinuation of ZIOPTAN.
Potential for Eyelash Changes Inform patients of the possibility of eyelash and vellus hair changes in the treated eye during treatment with ZIOPTAN. These changes may result in a disparity between eyes in length, thickness, pigmentation, number of eyelashes or vellus hairs, and/or direction of eyelash growth. Eyelash changes are usually reversible upon discontinuation of treatment.
Once Nightly Application Advise patients to not exceed once daily dosing since more frequent administration may decrease the intraocular pressure lowering effect of ZIOPTAN. Handling the Single-Dose Container Advise patients that ZIOPTAN is a sterile solution that does not contain a preservative. The solution from one single-dose container is to be used immediately after opening for administration to one or both eyes.
Since sterility cannot be maintained after the single-dose container is opened, discard the open container and remaining contents immediately after administration. Open a new single-dose container every time you use ZIOPTAN. When to Seek Physician Advice Advise patients that if they develop a new ocular condition (e.g., trauma or infection), experience a sudden decrease in visual acuity, have ocular surgery, or develop any ocular reactions, particularly conjunctivitis and eyelid reactions, they should immediately seek their physician's advice concerning the continued use of ZIOPTAN.
Use with Other Ophthalmic Drugs Advise patients if more than one topical ophthalmic drug is being used, the drugs should be administered at least five (5) minutes between applications. Storage Information Instruct patients on proper storage of cartons, unopened foil pouches, and opened foil pouches [see How Supplied/Storage and Handling (16) ]. ecommended storage for cartons and unopened foil pouches is to store refrigerated at 2° to 8°C (36° to 46°F). After the pouch is opened, the single-dose containers may be stored in the opened foil pouch for up to 30 days at room temperature 20° to 25°C (68° to 77°F).
Protect from moisture.