
Chlorophyll 100 mg Ingredients & Drug Interactions
by NOW
What is this page for?
First and foremost: checking Chlorophyll 100 mg against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Chlorophyll 100 mg is a dietary supplement by NOW with 2 active ingredients. Its ingredients are commonly taken for high cholesterol, digestive complaints, menopausal symptoms.Based on those ingredients, 698 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Alfalfa, Powder, Sodium Copper Chlorophyllin. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Chlorophyll 100 mg by NOW
Ask about any prescription or over-the-counter medication and we check it for interactions with Chlorophyll 100 mg by NOW — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Chlorophyll 100 mg by NOW
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
This product contains 2 active ingredients: alfalfa powder and sodium copper chlorophyllin. Alfalfa is a plant commonly used in supplements; sodium copper chlorophyllin is a water-soluble form of chlorophyll, the pigment that makes plants green.
Both come from plant sources. The capsule also contains hypromellose and stearic acid as inactive ingredients (binders and capsule material).
Does it work?
Strong evidence
The evidence on alfalfa's effectiveness for the conditions it's promoted for — blood sugar control, digestive upset, cholesterol, and menopausal symptoms — is insufficient to rate. For sodium copper chlorophyllin, the data shows it is likely effective for cystic fibrosis and possibly effective for kidney damage caused by the drug amphotericin B.
Beyond those two uses, the evidence is insufficient to rate or not yet established in the data we hold.
How safe is it?
Well-documented data
Alfalfa leaf is generally well tolerated in small amounts, but most common side effects from supplements and case reports include abdominal discomfort, diarrhea, flatulence, and intestinal gas — especially in the first week of use. Rarely, chronic alfalfa use has been linked to a lupus-like syndrome, and dermatitis (skin inflammation) has occurred with large doses.
Sodium is essential in normal dietary amounts, but excess sodium from supplements is linked to high blood pressure, heart strain, and kidney disease. For pregnancy and breastfeeding: alfalfa is rated possibly unsafe due to its estrogen-like activity, and not enough safety data exists for breastfeeding — talk with your doctor or pharmacist.
Sodium is likely safe in pregnancy at usual dietary levels but possibly unsafe at higher intakes or supplement doses.
Meds to double-check
Major interaction found
Before taking this product, check with your pharmacist if you take warfarin or other blood thinners (Major interaction with alfalfa), or any of these Moderate-severity drug types: blood pressure medications, corticosteroids, lithium, birth control pills, hormone therapy, diabetes medications, immunosuppressants, or photosensitizing drugs. Also check if you take didanosine, sodium phosphates, tolvaptan, or any other sodium-containing medications.
The bottom line
Scorecard at a glanceFully disclosed formula with strong clinical evidence behind its ingredients' uses. Major medication interactions have been identified, and safety information is well characterized.
This product is worth considering only if you're using it for cystic fibrosis or amphotericin B kidney toxicity — and only under medical supervision. If you take any medication, especially blood thinners, blood pressure drugs, lithium, or birth control, talk with your pharmacist before starting.
The sodium content and alfalfa's hormone-like effects add to the caution list.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 2 of 2 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Chlorophyll 100 mg, straight from the product label.
| Brand | NOW |
|---|---|
| Barcode (UPC) | 733739026453 |
| Net contents | 90 Veg Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Jul 25, 2024 |
| DSLD ID | 313809 |
| Product type | Botanical With Nutrients |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Kosher, Halal, Gluten Free, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
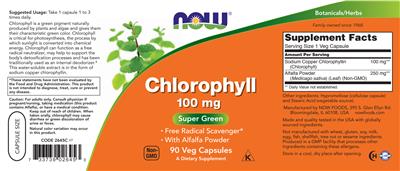
Supplement Facts
The label details for Chlorophyll 100 mg by NOW, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Alfalfa, Powder | 250 mg | -- |
| Sodium Copper Chlorophyllin | 100 mg | -- |
Other ingredients: Hypromellose, Stearic Acid
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
Suggested Usage: Take 1 capsule 1 to 3 times daily.
Formula
Chlorophyll is green pigment naturally produced by plants and algae and gives them their characteristic green color. Chlorophyll is critical for photosynthesis, the process by which sunlight is converted into chemical energy. Chlorophyll can function as a free radical neutralizer, may help to support the body's detoxification processes and has been traditionally used as an internal deodorizer.
This water-soluble extract is in the form of sodium copper chlorophyllin.
Chlorophyll 100 mg with alfalfa powder
Triangle K (Kosher)
Crescent H (Halal)
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Precautions
Caution: For adults only. Keep out of reach of children.
Consult physician if pregnant/nursing, taking medication (this product contains Alfalfa), or have a medical condition.
Keep out of reach of children.
When taken orally, chlorophyll may cause diarrhea or green discoloration of urine or feces.
Not manufactured with wheat, gluten, soy, milk, egg, fish, shellfish or tree nut ingredients. Produced in a GMP facility that processes other ingredients containing these allergens.
Formulation
Natural color variation may occur in this product.
Super green Free radical scavenger
Non-GMO
Made and quality tested in the USA with globally sourced ingredients.
Not manufactured with wheat, gluten, soy, milk, egg, fish, shellfish or tree nut ingredients.
FDA Statement of Identity
A Dietary Supplement
Seals/Symbols
Triangle K (Kosher)
Crescent H (Halal) GMP Quality Assured
General Statements
Botanicals/Herbs Family owned since 1968.
Storage
Store in a cool, dry place after opening.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Chlorophyll 100 mg by NOW label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Chlorophyll 100 mg by NOW
These are the 2 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Veg Capsule(s) Dosage formCapsule Servings per container90 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Alfalfa, Powder
Interacts with583 drugs
Alfalfa is a nutrient-rich legume that people use for high cholesterol, menopause symptoms, and general wellness, but solid human evidence for most of...
Alfalfa, Powder monograph & interactionsSodium Copper Chlorophyllin
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium Copper Chlorophyllin monograph & interactionsOther (inactive) ingredients: Hypromellose, Stearic Acid. These complete the product’s ingredient list but are not active constituents.
Chlorophyll 100 mg by NOW Drug Interactions
HelloPharmacist Interaction Report
NOW's Chlorophyll 100 mg contains alfalfa and sodium copper chlorophyllin, and together these ingredients interact with a substantial number of medications.
The most serious interaction is between alfalfa and warfarin (Coumadin), a blood thinner (anticoagulant). Alfalfa is high in vitamin K, which can reduce warfarin's ability to prevent blood clots — a Major-severity concern.
Read the full breakdown — every affected drug type, severity by severity
Alfalfa also carries Moderate-severity interactions with photosensitizing drugs (drugs that increase skin sensitivity to sunlight), birth control pills, hormone replacement therapy, immunosuppressants (drugs that suppress the immune system), and diabetes medications. The sodium in this product interacts with blood pressure medications, corticosteroids, lithium, didanosine, sodium phosphates, tolvaptan, and other sodium-containing drugs — all Moderate severity, mainly because excess sodium can raise blood pressure or cause dangerously high sodium levels in your blood.
Altogether, these interactions span 690 individual medications. Because the ingredient list is short but the interaction footprint is large, it's especially important to run your exact medications through the checker below before starting this supplement.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Chlorophyll 100 mg?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Chlorophyll 100 mg interact with 698 drugs. Click any drug to see the details.
2 of the 2 ingredients in Chlorophyll 100 mg interact with drugs. Each result below shows which ingredient is responsible. Alfalfa, Powder Sodium Copper Chlorophyllin
WarfarinWarfarin
How Warfarin interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderWarfarin (coumadin) Major
Interaction Summary
Theoretically, alfalfa might reduce the anticoagulant activity of warfarin.
Read the full Alfalfa, Powder + Warfarin interactionWarfarin SodiumCoumadin, Panwarfin, Sofarin
How Warfarin Sodium interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderWarfarin (coumadin) Major
Interaction Summary
Theoretically, alfalfa might reduce the anticoagulant activity of warfarin.
Read the full Alfalfa, Powder + Warfarin Sodium interaction6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderImmunosuppressants Moderate
Interaction Summary
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
Read the full Alfalfa, Powder + 6-mercaptopurine interactionAbrocitinibCibinqo
How Abrocitinib interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderImmunosuppressants Moderate
Interaction Summary
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
Read the full Alfalfa, Powder + Abrocitinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, alfalfa might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Alfalfa, Powder + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Sodium Copper ChlorophyllinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium Copper Chlorophyllin + Acebutolol interactionAcepromazineAtravet
How Acepromazine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acepromazine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PhenylpropanolamineMulti Symptom Cold Relief
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Dextromethorphan, PseudoephedrineChildren's Tylenol Cold Plus Cough, Tylenol Cold Ex Strength
How Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, SalicylamideRhinogesic GG
How Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Guaifenesin, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylephrineAlka-Seltzer PLUS, Histex SR, Protid
How Acetaminophen, Chlorpheniramine, Phenylephrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, Phenylephrine, SalicylamideRhinogesic, Rhinogesic JR
How Acetaminophen, Chlorpheniramine, Phenylephrine, Salicylamide interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Phenylephrine, Salicylamide interactionAcetaminophen, Chlorpheniramine, PhenylpropanolamineAlumadrine, Conex, Sinadrin Max Strength, Sinulin
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, OpiumHista-Derfule
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, PhenyltoloxamineNorel Plus
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionAcetaminophen, Chlorpheniramine, PseudoephedrineAlka-Seltzer PLUS Liquid Gels, Children's Tylenol Cold, Codimal, Comtrex, Extra Strength Tylenol Allergy Sinus, Lorsin +3 more
How Acetaminophen, Chlorpheniramine, Pseudoephedrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionAcetaminophen, Dexbrompheniramine, PseudoephedrineSinadrin Plus
How Acetaminophen, Dexbrompheniramine, Pseudoephedrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionAcetaminophen, DiphenhydramineTylenol PM, Tylenol PM Ex Strength
How Acetaminophen, Diphenhydramine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Diphenhydramine interactionAcetaminophen, Diphenhydramine, PseudoephedrineChildren's Tylenol Allergy, Cold Control, Contac Night Allergy Relief
How Acetaminophen, Diphenhydramine, Pseudoephedrine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionAcetaminophen, IbuprofenCombogesic
How Acetaminophen, Ibuprofen interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Ibuprofen interactionAcetaminophen, Phenylephrine, ChlorpheniramineSuper Cold Tabs
How Acetaminophen, Phenylephrine, Chlorpheniramine interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetaminophen, Phenylephrine, Chlorpheniramine interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Chlorophyll 100 mg — through 2 ingredients. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acetazolamide interactionSodium Copper ChlorophyllinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium Copper Chlorophyllin + Acetazolamide interactionAcetohexamideDymelor
How Acetohexamide interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderAntidiabetes Drugs, Photosensitizing Drugs Moderate
Interaction Summary
Theoretically, alfalfa might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Alfalfa, Powder + Acetohexamide interactionAcitretinSoriatane
How Acitretin interacts with Chlorophyll 100 mg — through 1 ingredient. Tap an ingredient for the detail:
Alfalfa, PowderPhotosensitizing Drugs Moderate
Interaction Summary
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Read the full Alfalfa, Powder + Acitretin interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Chlorophyll 100 mg with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Alfalfa, Powder
Warfarin (Coumadin)
Theoretically, alfalfa might reduce the anticoagulant activity of warfarin.
Alfalfa contains a large amount of vitamin K. This could theoretically interfere with the activity of warfarin.
Antidiabetes Drugs
Theoretically, alfalfa might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research suggests that alfalfa decreases blood sugar in diabetic mice. Also, in one case report, a diabetic patient experienced hypoglycemia after consuming alfalfa extract. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Contraceptive Drugs
Theoretically, alfalfa might interfere with the activity of contraceptive drugs.
Alfalfa contains coumestrol, a phytoestrogen, and isoflavonoids, which have estrogenic effects.
Estrogens
Theoretically, alfalfa might interfere with hormone therapy.
Alfalfa contains coumestrol, a phytoestrogen, and isoflavonoids, which have estrogenic effects.
Immunosuppressants
Theoretically, alfalfa might decrease the efficacy of immunosuppressive therapy.
In vitro research and human case reports suggest that alfalfa may have immunostimulant effects.
Photosensitizing Drugs
Theoretically, concomitant use of alfalfa with photosensitizing drugs might have additive effects.
Animal research suggests that excessive doses of alfalfa may increase photosensitivity, possibly due to its chlorophyll content. It is unclear if this effect would be clinically relevant in humans.
Sodium Copper Chlorophyllin
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Brand information
Manufacturer and brand details for Chlorophyll 100 mg, from the product label.
NOW
See all NOW products- Name
- NOW Foods
- Street Address
- 395 S. Glen Ellyn Rd.
- City
- Bloomingdale
- State
- IL
- ZipCode
- 60108
- Web Address
- nowfoods.com
Chlorophyll 100 mg by NOW: Common Questions
Does Chlorophyll 100 mg by NOW interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Does alfalfa really interfere with warfarin?
What are the most common side effects?
Is this safe during pregnancy?
What is sodium copper chlorophyllin, and why is it in here?
Can I use this if I take birth control?
Does this product have any fillers or 'other ingredients'?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Chlorophyll 100 mg is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Chlorophyll 100 mg’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Alfalfa
Interacts with 583 drugsAlfalfa is a nutrient-rich legume that people use for high cholesterol, menopause symptoms, and general wellness, but solid human evidence for most of these uses is limited. It is best avoid...
Read the full Alfalfa monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph →Sources & How We Checked
Chlorophyll 100 mg's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 70 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Alfalfa 32 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Kurzer MS, Xu X. Dietary phytoestrogens. Annu Rev Nutr 1997;17:353-81. PubMed
- Farber JM, Carter AO, Varughese PV, et al. Listeriosis traced to the consumption of alfalfa tablets and soft cheese [Letter to the Editor]. N Engl J Med 1990;322:338. PubMed
- Molgaard J, von Schenck H, Olsson AG. Alfalfa seeds lower low density lipoprotein cholesterol and apolipoprotein B concentrations in patients with type II hyperlipoproteinemia. Atherosclerosis 1987;65:173-9. PubMed
- Light TD, Light JA. Acute renal transplant rejection possibly related to herbal medications. Am J Transplant 2003;3:1608-9. PubMed
- Prete PE. The mechanism of action of L-canavanine in inducing autoimmune phenomena. Arthritis Rheum 1985;28:1198-200. PubMed
- Alcocer-Varela J, Iglesias A, Llorente L, Alarcon-Segovia D. Effects of L-canavanine on T cells may explain the induction of systemic lupus erythematosus by alfalfa. Arthritis Rheum 1985;28:52-7. PubMed
- Roberts JL, Hayashi JA. Exacerbation of SLE associated with alfalfa ingestion. N Engl J Med 1983;308:1361. DOI
- Feingold, R. M. Should we fear "health foods"? Arch Intern Med 7-12-1999;159(13):1502. PubMed
- Taormina, P. J., Beuchat, L. R., and Slutsker, L. Infections associated with eating seed sprouts: an international concern. Emerg.Infect.Dis 1999;5(5):626-634. PubMed
- Backer, H. D., Mohle-Boetani, J. C., Werner, S. B., Abbott, S. L., Farrar, J., and Vugia, D. J. High incidence of extra-intestinal infections in a Salmonella Havana outbreak associated with alfalfa sprouts. Public Health Rep. 2000;115(4):339-345. PubMed
- Mohle-Boetani J, Werner B, Polumbo M, and et al. From the Centers for Disease Control and Prevention. Alfalfa sprouts-- Arizona, California, Colorado, and New Mexico, February-April, 2001. JAMA 2-6-2002;287(5):581-582.
- Howard, M. B. and Hutcheson, S. W. Growth dynamics of Salmonella enterica strains on alfalfa sprouts and in waste seed irrigation water. Appl.Environ.Microbiol. 2003;69(1):548-553.
- Winthrop, K. L., Palumbo, M. S., Farrar, J. A., Mohle-Boetani, J. C., Abbott, S., Beatty, M. E., Inami, G., and Werner, S. B. Alfalfa sprouts and Salmonella Kottbus infection: a multistate outbreak following inadequate seed disinfection with heat and chl
- Strapp, C. M., Shearer, A. E., and Joerger, R. D. Survey of retail alfalfa sprouts and mushrooms for the presence of Escherichia coil O157:H7, Salmonella, and Listeria with BAX, and evaluation of this polymerase chain reaction-based system with experimen
- Akaogi, J., Barker, T., Kuroda, Y., Nacionales, D. C., Yamasaki, Y., Stevens, B. R., Reeves, W. H., and Satoh, M. Role of non-protein amino acid L-canavanine in autoimmunity. Autoimmun.Rev 2006;5(6):429-435. PubMed
- Burden and causes of foodborne disease in Australia: Annual report of the OzFoodNet network, 2005. Commun.Dis Intell. 2006;30(3):278-300.
- Shemesh, M., Lindner, H. R., and Ayalon, N. Affinity of rabbit uterine oestradiol receptor for phyto-oestrogens and its use in a competitive protein-binding radioassay for plasma coumestrol. J Reprod.Fertil. 1972;29(1):1-9. PubMed
- Elakovich, S. D. and Hampton, J. M. Analysis of coumestrol, a phytoestrogen, in alfalfa tablets sold for human consumption. J Agric.Food Chem. 1984;32(1):173-175. PubMed
- Malinow, M. R., Bardana, E. J., Jr., Pirofsky, B., Craig, S., and McLaughlin, P. Systemic lupus erythematosus-like syndrome in monkeys fed alfalfa sprouts: role of a nonprotein amino acid. Science 4-23-1982;216(4544):415-417. PubMed
- Malinow, M. R., McLaughlin, P., and Stafford, C. Alfalfa seeds: effects on cholesterol metabolism. Experientia 5-15-1980;36(5):562-564. PubMed
- Farnsworth, N. R. Alfalfa pills and autoimmune diseases. Am J Clin Nutr. 1995;62(5):1026-1028. DOI
- Herbert, V. and Kasdan, T. S. Alfalfa, vitamin E, and autoimmune disorders. Am J Clin Nutr 1994;60(4):639-640.
- Mahon, B. E., Ponka, A., Hall, W. N., Komatsu, K., Dietrich, S. E., Siitonen, A., Cage, G., Hayes, P. S., Lambert-Fair, M. A., Bean, N. H., Griffin, P. M., and Slutsker, L. An international outbreak of Salmonella infections caused by alfalfa sprouts grow
- Gray, A. M. and Flatt, P. R. Pancreatic and extra-pancreatic effects of the traditional anti- diabetic plant, Medicago sativa (lucerne). Br J Nutr. 1997;78(2):325-334.
- Van Beneden, C. A., Keene, W. E., Strang, R. A., Werker, D. H., King, A. S., Mahon, B., Hedberg, K., Bell, A., Kelly, M. T., Balan, V. K., Mac Kenzie, W. R., and Fleming, D. Multinational outbreak of Salmonella enterica serotype Newport infections due to
- Rubenstein AH, Levin NW, and Elliott GA. Manganese-induced hypoglycemia. Lancet 1962;1348-1351.
- Kaufman W. Alfalfa seed dermatitis. JAMA 1954;155(12):1058-1059. PubMed
- Ponka A, Andersson Y, Siitonen A, and et al. Salmonella in alfalfa sprouts. Lancet 1995;345:462-463. PubMed
- Puschner B, Chen X, Read D, Affolter VK. Alfalfa hay induced primary photosensitization in horses. Vet J. 2016 May;211:32-8. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC