
Perfect Amino Electrolytes Watermelon Ingredients & Drug Interactions
by BodyHealth
What is this page for?
First and foremost: checking Perfect Amino Electrolytes Watermelon against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Perfect Amino Electrolytes Watermelon is a dietary supplement by BodyHealth with 13 active ingredients. Its ingredients are commonly taken for zinc deficiency, immune support, cold symptoms.Based on those ingredients, 853 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are L-Tryptophan, Magnesium, Sodium. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Perfect Amino Electrolytes Watermelon by BodyHealth
Ask about any prescription or over-the-counter medication and we check it for interactions with Perfect Amino Electrolytes Watermelon by BodyHealth — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Perfect Amino Electrolytes Watermelon by BodyHealth
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Perfect Amino Electrolytes Watermelon contains 13 active ingredients: nine amino acids (L-leucine, L-isoleucine, L-methionine, L-lysine hydrochloride, L-phenylalanine, L-valine, L-threonine, and L-tryptophan) plus four electrolytes and trace minerals (zinc, sodium, magnesium, and potassium). The amino acids are building blocks for muscle protein and neurotransmitters; the electrolytes help with hydration and nerve and muscle function.
The product also contains inactive ingredients—citric acid, watermelon flavor, malic acid, stevia, monk fruit, and beet juice powder—which are fillers and flavoring agents.
Does it work?
Not established
Evidence for this product's ingredients varies. Magnesium is effective for indigestion and constipation, and L-lysine is possibly effective for cold sores.
L-methionine is possibly effective for preventing neural tube birth defects in pregnancy. Zinc is effective for zinc deficiency and likely effective for Wilson disease, and possibly effective for acne, age-related macular degeneration, and diabetes.
Most other uses tested—L-phenylalanine for ADHD, L-tryptophan for depression, threonine for ALS—show either insufficient evidence or possibly ineffective ratings. Sodium and potassium have been tested for specific medical conditions (sodium for cystic fibrosis, potassium for none listed in our data), but this product is marketed as an electrolyte supplement for hydration and muscle support, not for those conditions, and the evidence for that general use is not established in the data we hold.
How safe is it?
Well-documented data
Magnesium and zinc are generally well tolerated at recommended doses. L-methionine is usually safe at food amounts but high-dose supplements may cause side effects including dizziness, drowsiness, and increased homocysteine; safety in pregnancy and breastfeeding has not been proven.
L-lysine is generally well tolerated but may cause stomach upset, abdominal pain, and diarrhea at high amounts; supplement safety in pregnancy and breastfeeding is not well studied. L-phenylalanine is not recommended in pregnancy and should be avoided while breastfeeding, and people with PKU (phenylketonuria) must avoid it.
L-tryptophan may cause headache, drowsiness, nausea, and diarrhea, and has a historical safety concern—a contaminated batch in 1989 caused a rare neurological disorder; safety in pregnancy and breastfeeding is not established. L-threonine from food is safe; supplement safety at higher doses and during pregnancy and breastfeeding is not well studied.
Sodium in excess is linked to high blood pressure and worsened heart and kidney disease. Potassium from food is safe, but supplements can cause dangerously high blood levels, especially in people with kidney disease.
Meds to double-check
Major interaction found
Check before starting if you take levodopa (Parkinson disease), CNS depressants like opioids or sleep aids, quinolone antibiotics (ciprofloxacin), tetracyclines (doxycycline), cephalexin, blood pressure medicines, ACE inhibitors, ARBs, potassium-sparing diuretics, calcium channel blockers, lithium, MAOIs, skeletal muscle relaxants, or HIV medications. Magnesium and zinc interfere with absorption of many antibiotics and other drugs—your pharmacist can help space doses correctly.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with no established evidence rating for its marketed use. Major medication interactions have been identified, and safety information is well characterized.
This is an amino acid and electrolyte blend intended for muscle recovery and hydration. If you take any prescription medications—especially Parkinson drugs, sedatives, blood pressure medications, antibiotics, or HIV drugs—check with your pharmacist before adding this product.
Pregnant or breastfeeding people should talk with their doctor first, as several ingredients lack safety data in these situations. People with kidney disease, those on lithium or potassium-controlling drugs, and anyone with PKU should avoid it.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 9 of 13 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Nov 22, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Perfect Amino Electrolytes Watermelon, straight from the product label.
| Brand | BodyHealth |
|---|---|
| Barcode (UPC) | 850041072173 |
| Net contents | 5.5 Ounce(s); 156 Gram(s) |
| Market status | On market |
| Date entered into DSLD | Nov 22, 2024 |
| DSLD ID | 322558 |
| Product type | Other Combinations |
| Supplement form | Powder |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Vegan, Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free, Sugar Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
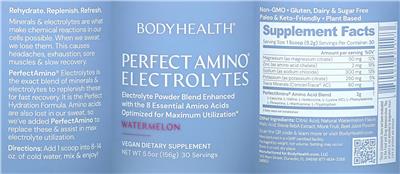
Supplement Facts
The label details for Perfect Amino Electrolytes Watermelon by BodyHealth, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| L-Leucine | 0 NP | -- |
| L-Isoleucine | 0 NP | -- |
| L-Methionine | 0 NP | -- |
| L-Lysine Hydrochloride | 0 NP | -- |
| L-Phenylalanine | 0 NP | -- |
| L-Valine | 0 NP | -- |
| Zinc | 2 mg | 18% |
| L-Threonine | 0 NP | -- |
| L-Tryptophan | 0 NP | -- |
| Sodium | 300 mg | 13% |
| Magnesium | 50 mg | 12% |
| Potassium | 250 mg | 5% |
| ConcenTrace AC | 80 mg | -- |
| PerfectAmino Amino Acid Blend | 2 Gram(s) | -- |
Other ingredients: Citric Acid, Watermelon Flavor, Natural, Malic Acid, Stevia Rebaudioside A, Monk Fruit, Beet Juice, Powder
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
Rehydrate. Replenish. Refresh.
Vegan Dietary Supplement
Non-GMO Gluten, dairy & sugar free
Plant based
Manufactured in a cGMP certified facility.
Formula
Minerals & electrolytes are what make chemical reactions in our cells possible. When we sweat, we lose them. This causes headaches, exhaustion, sore muscles & slow recovery. PerfectAmino Electrolytes is the exact blend of minerals & electrolytes to replenish these for fast recovery. It is the Perfect Hydration Formula. Amino acids are also lost in our sweat, so we've added PerfectAmino to replace these & assist in max electrolyte utilization.
Electrolyte powder blend enhanced with the 8 essential amino acids optimized for maximum utilization
Paleo & Keto-friendly
Suggested/Recommended/Usage/Directions
Directions: Add 1 scoop into 8-14 oz. of cold water, mix & enjoy!
FDA Statement of Identity
Vegan Dietary Supplement
General Statements
Scan the QR code & learn more or visit BodyHealth.com
Storage
Packaged by weight, not volume. Settling may occur. Store in a cool dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Perfect Amino Electrolytes Watermelon by BodyHealth label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Perfect Amino Electrolytes Watermelon by BodyHealth
These are the 13 active ingredients this product is made of. Select any to open its full monograph.
Serving size5.2 Gram(s) Dosage formPowder Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Zinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsSodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsConcenTrace AC
PerfectAmino Amino Acid Blend
- › L-Leucine
- › L-Isoleucine
- › L-Methionine
- › L-Lysine Hydrochloride
- › L-Phenylalanine
- › L-Valine
- › L-Threonine
- › L-Tryptophan
Other (inactive) ingredients: Citric Acid, Watermelon Flavor, Natural, Malic Acid, Stevia Rebaudioside A, Monk Fruit, Beet Juice, Powder. These complete the product’s ingredient list but are not active constituents.
Perfect Amino Electrolytes Watermelon by BodyHealth Drug Interactions
HelloPharmacist Interaction Report
Perfect Amino Electrolytes Watermelon by BodyHealth contains several amino acids and electrolytes with documented interactions.
The most serious concern is L-phenylalanine, which has a Major interaction with levodopa (used for Parkinson disease)—phenylalanine competes with levodopa for transport into the brain, potentially reducing its effectiveness and worsening tremor and rigidity.
Read the full breakdown — every affected drug type, severity by severity
L-tryptophan carries Major interactions with CNS depressants (sedatives, sleep aids, opioids), where combining them might add up to dangerous drowsiness. Threonine and magnesium each have one Major interaction: threonine with NMDA antagonists (like memantine for Alzheimer disease), and magnesium with levodopa/carbidopa.
Altogether, these interactions span 848 individual medications.
Moderate interactions affect many drug classes: zinc reduces absorption of quinolone antibiotics (like ciprofloxacin), tetracyclines (like doxycycline), cephalexin, and penicillamine, as well as HIV medications (ritonavir and integrase inhibitors); L-lysine may blunt 5-HT4 agonists; L-phenylalanine interacts with baclofen and MAOIs; L-tryptophan with serotonergic drugs (SSRIs, SNRIs); magnesium with skeletal muscle relaxants, calcium channel blockers, quinolones, bisphosphonates, sulfonylureas, and antacids; sodium with blood-pressure drugs, lithium, and corticosteroids; and potassium with ACE inhibitors, ARBs, and potassium-sparing diuretics.
L-leucine, L-isoleucine, L-valine, and ConcenTrace AC were not checked—we hold no data for them. Run your exact medications through the checker below before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Perfect Amino Electrolytes Watermelon?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Perfect Amino Electrolytes Watermelon interact with 853 drugs. Click any drug to see the details.
8 of the 13 ingredients in Perfect Amino Electrolytes Watermelon interact with drugs. Each result below shows which ingredient is responsible. L-Tryptophan Magnesium Sodium Zinc Potassium L-Phenylalanine L-Threonine L-Lysine Hydrochloride
AcepromazineAtravet
How Acepromazine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acepromazine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanSerotonergic Drugs, Cns Depressants Major
Interaction Summary
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
Read the full L-tryptophan + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, OpiumHista-Derfule
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanSerotonergic Drugs, Cns Depressants Major
Interaction Summary
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
Read the full L-tryptophan + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionAcetaminophen, Chlorzoxazone, CodeineAcetazone Forte C8, Parafon Forte C8
How Acetaminophen, Chlorzoxazone, Codeine interacts with Perfect Amino Electrolytes Watermelon — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Chlorzoxazone, Codeine interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Chlorzoxazone, Codeine interactionAcetaminophen, CodeineTylenol No.3, Tylenol w/ Codeine
How Acetaminophen, Codeine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine interactionAcetaminophen, Codeine, DoxylamineMersyndol
How Acetaminophen, Codeine, Doxylamine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine, Doxylamine interactionAcetaminophen, Codeine, MethocarbamolAcetaminophen, Codeine, Methocarbamol, Robaxacet 8
How Acetaminophen, Codeine, Methocarbamol interacts with Perfect Amino Electrolytes Watermelon — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine, Methocarbamol interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Codeine, Methocarbamol interactionAcetaminophen, Dichloralantipyrine, IsomethepteneAmidrine, Midchlor, Migquin, Migratine
How Acetaminophen, Dichloralantipyrine, Isometheptene interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichloralantipyrine, Isometheptene interactionAcetaminophen, Dichloralphenazone, IsomethepteneMidrin
How Acetaminophen, Dichloralphenazone, Isometheptene interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichloralphenazone, Isometheptene interactionAcetaminophen, Dichlorophenazone, IsometheptaneIsocom
How Acetaminophen, Dichlorophenazone, Isometheptane interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichlorophenazone, Isometheptane interactionAcetaminophen, DiphenhydramineTylenol PM, Tylenol PM Ex Strength
How Acetaminophen, Diphenhydramine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Diphenhydramine interactionAcetaminophen, Diphenhydramine, PseudoephedrineChildren's Tylenol Allergy, Cold Control, Contac Night Allergy Relief
How Acetaminophen, Diphenhydramine, Pseudoephedrine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionAcetaminophen, HydrocodoneAnexsia, Anodynos DHC, Azdone, Co-Gesic, Doucet, Lorcet +9 more
How Acetaminophen, Hydrocodone interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Hydrocodone interactionAcetaminophen, MeperidineDemerol APAP
How Acetaminophen, Meperidine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants, Serotonergic Drugs Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Meperidine interactionAcetaminophen, OxycodonePercocet, Roxicet, Tylox, Xartemis XR
How Acetaminophen, Oxycodone interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Oxycodone interactionAcetaminophen, PentazocineTalacen
How Acetaminophen, Pentazocine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Pentazocine interactionAcetaminophen, PropoxypheneDarvocet-N 100, Darvocet-N 50, E-Lor, Wygesic
How Acetaminophen, Propoxyphene interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Propoxyphene interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Perfect Amino Electrolytes Watermelon — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetazolamide interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acetazolamide interactionAlfentanilAlfenta
How Alfentanil interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Alfentanil interactionAlprazolamNiravam, Xanax
How Alprazolam interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Alprazolam interactionAluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium HydroxideAscriptin Codeine #2
How Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interacts with Perfect Amino Electrolytes Watermelon — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionMagnesiumAntacids, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Use of acid reducers may reduce the laxative effect of magnesium oxide.
Read the full Magnesium + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAminoglutethimideCytadren
How Aminoglutethimide interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aminoglutethimide interactionAminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Perfect Amino Electrolytes Watermelon — through 1 ingredient. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aminophylline, Amobarbital, Ephedrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Perfect Amino Electrolytes Watermelon with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
L-Tryptophan
Cns Depressants
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Clinical research shows that L-tryptophan can cause fatigue and drowsiness.
Serotonergic Drugs
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
L-tryptophan is a precursor to serotonin. Theoretically, combining serotonergic drugs with L-tryptophan might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
L-Phenylalanine
Levodopa
Phenylalanine, especially in high doses, can reduce the effectiveness of levodopa.
Phenylalanine competes with levodopa for carrier-mediated transport into the brain. The resulting reduction in levels of levodopa in the brain can exacerbate tremor, rigidity, and the "on-off" phenomenon in patients with Parkinson disease.
Baclofen
Concomitant intake of phenylalanine may reduce the intestinal absorption of baclofen.
Phenylalanine and baclofen share the same intestinal carrier for absorption; phenylalanine competitively inhibits the absorption of baclofen, reducing its plasma levels.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use of L-phenylalanine and non-selective MAOIs might increase the risk of hypertensive crisis.
L-phenylalanine is metabolized to tyrosine. Some evidence suggests that L-phenylalanine, given with the non-selective MAOI pargyline, might prevent the elimination of tyramine, increasing the risk of hypertensive crisis. However, this was not reported in a small number of patients when using L-phenylalanine with the partially selective MAO-B inhibitor, selegiline.
L-Threonine
Nmda Antagonists
Theoretically, threonine might decrease the effects of NMDA antagonists.
Threonine increases central nervous system (CNS) glycine levels. Glycine seems to bind a site on NMDA receptors and enhance the activity of the receptors.
L-Lysine Hydrochloride
5-Ht4 Agonists
Theoretically, lysine may reduce the effects of 5-HT4 agonists.
Animal research suggests that L-lysine is a partial serotonin receptor 4 (5-HT4) antagonist and inhibits diarrhea induced by the 5-HT4 agonist, 5-hydroxytryptophane.
Brand information
Manufacturer and brand details for Perfect Amino Electrolytes Watermelon, from the product label.
BodyHealth
See all BodyHealth products- Name
- BodyHealth.com, LLC.
- Street Address
- 745 Main Street
- City
- Dunedin
- State
- FL
- ZipCode
- 34698
- Phone Number
- (877) 804-3258
- Web Address
- BodyHealth.com
Perfect Amino Electrolytes Watermelon by BodyHealth: Common Questions
Does Perfect Amino Electrolytes Watermelon by BodyHealth interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this if I'm pregnant or breastfeeding?
What are the amino acids in this product for?
Will this help with muscle recovery after exercise?
Can I take this with my blood pressure medicine?
What side effects might I experience?
Is this safe for someone with kidney disease?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Perfect Amino Electrolytes Watermelon is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Perfect Amino Electrolytes Watermelon’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Zinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographMethionine
Methionine is an essential amino acid that your body needs for protein building and many basic chemical reactions. Most people get enough from a normal diet, and supplements are generally no...
Read the full Methionine monograph → Herb & supplement monographLysine
Interacts with 1 drugLysine is an essential amino acid your body cannot make on its own, so it must come from food or supplements. People most often take extra lysine to try to prevent or shorten cold sores, but...
Read the full Lysine monograph → Herb & supplement monographPhenylalanine
Interacts with 16 drugsPhenylalanine is an essential amino acid the body uses to make brain chemicals like dopamine and norepinephrine. Some people take it for mood, vitiligo, or pain, but the evidence is mostly l...
Read the full Phenylalanine monograph → Herb & supplement monographThreonine
Interacts with 3 drugsThreonine is an essential amino acid your body needs but cannot make, so you must get it from food or supplements. Most people get plenty from a normal diet, and high-quality evidence for ta...
Read the full Threonine monograph → Herb & supplement monographL-tryptophan
Interacts with 394 drugsL-tryptophan is an essential amino acid the body uses to make serotonin and melatonin, and people take it to support sleep and mood. The evidence for supplement use is limited and mixed, and...
Read the full L-tryptophan monograph →Sources & How We Checked
Perfect Amino Electrolytes Watermelon's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 284 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Methionine 12 references
- La Vecchia C, Negri E, Franceschi S, Decarli A. Case-control study on influence of methionine, nitrite, and salt on gastric carcinogenesis in northern Italy. Nutr Cancer 1997;27:65-8. PubMed
- Btaiche IF, Khalidi N. Parenteral nutrition-associated liver complications in children. Pharmacotherapy 2002;22:188-211.. PubMed
- Cottington EM, LaMantia C, Stabler SP, et al. Adverse event associated with methionine loading test: a case report. Arterioscler Thromb Vasc Biol 2002;22:1046-50.. PubMed
- Anon. Should methionine be added to paracetamol formulations? Drug Ther Perspect 1997;10:11-3. DOI
- Smulders, Y. M., Rakic, M., Slaats, E. H., Treskes, M., Sijbrands, E. J., Odekerken, D. A., Stehouwer, C. D., and Silberbusch, J. Fasting and post-methionine homocysteine levels in NIDDM. Determinants and correlations with retinopathy, albuminuria, and c
- McAuley, D. F., Hanratty, C. G., McGurk, C., Nugent, A. G., and Johnston, G. D. Effect of methionine supplementation on endothelial function, plasma homocysteine, and lipid peroxidation. J.Toxicol.Clin.Toxicol. 1999;37(4):435-440. PubMed
- Hanratty, C. G., McGrath, L. T., McAuley, D. F., Young, I. S., and Johnston, G. D. The effects of oral methionine and homocysteine on endothelial function. Heart 2001;85(3):326-330. PubMed
- Ward, M., McNulty, H., McPartlin, J., Strain, J. J., Weir, D. G., and Scott, J. M. Effect of supplemental methionine on plasma homocysteine concentrations in healthy men: a preliminary study. Int.J.Vitam.Nutr.Res. 2001;71(1):82-86. PubMed
- Yaghmai, R., Kashani, A. H., Geraghty, M. T., Okoh, J., Pomper, M., Tangerman, A., Wagner, C., Stabler, S. P., Allen, R. H., Mudd, S. H., and Braverman, N. Progressive cerebral edema associated with high methionine levels and betaine therapy in a patient
- Talukdar R, Murthy HV, Reddy DN. Role of methionine containing antioxidant combination in the management of pain in chronic pancreatitis: a systematic review and meta-analysis. Pancreatology 2015;15(2):136-44. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids. Washington, DC: The National Academies Press, 2005. Available at: https://doi.org/10.17226 DOI
- Khairan P, Sobue T, Eshak ES, et al. Association of B Vitamins and Methionine Intake with the Risk of Gastric Cancer: The Japan Public Health Center-based Prospective Study. Cancer Prev Res (Phila) 2022;15(2):101-110. PubMed
Lysine 7 references
- Thein DJ, Hurt WC. Lysine as a prophylactic agent in the treatment of recurrent herpes simplex labialis. Oral Surg Oral Med Oral Pathol 1984;58:659-66. PubMed
- McCune MA, Perry HO, Muller SA, O'Fallon WM. Treatment of recurrent herpes simplex infections with L-lysine monohydrochloride. Cutis 1984;34:366-73.
- DiGiovanna JJ, Blank H. Failure of lysine in frequently recurrent herpes simplex infection. Treatment and prophylaxis. Arch Dermatol 1984;120:48-51. DOI
- Milman N, Scheibel J, Jessen O. Lysine prophylaxis in recurrent herpes simplex labialis: a double-blind, controlled crossover study. Acta Derm Venereol 1980;60:85-7.
- Griffith RS, Walsh DE, Myrmel KH, et al. Success of L-lysine therapy in frequently recurrent herpes simplex infection. Treatment and prophylaxis. Dermatologica 1987;175:183-90. DOI
- Lo JC, Chertow GM, Rennke H, Seifter JL. Fanconi's syndrome and tubulointerstitial nephritis in association with L-lysine ingestion. Am J Kidney Dis 1996;28:614-7. PubMed
- Smriga M, Torii K. L-Lysine acts like a partial serotonin receptor 4 antagonist and inhibits serotonin-mediated intestinal pathologies and anxiety in rats. Proc Natl Acad Sci U S A. 2003 Dec 23;100(26):15370-5.
Phenylalanine 23 references
- Rouse B, Azen C, Koch R, et al. Maternal phenylketonuria collaborative Study (MPKUCS) offspring: facial anomalies, malformations, and early neurological sequelae. Am J Med Genet 1997;69:89-95. DOI
- Sturtevant FM. Use of aspartame in pregnancy. Int J Fertil 1985;30:85-7.
- Silkaitis RP, Mosnaim AD. Pathways linking L-phenylalanine and 2-phenylethylamine with p-tyramine in rabbit brain. Brain Res 1976;114:105-15.
- Lehmann WD, Theobald N, Fischer R, Heinrich HC. Stereospecificity of phenylalanine plasma kinetics and hydroxylation in man following oral application of a stable isotope-labelled pseudo-racemic mixture of L- and D-phenylalanine. Clin Chim Acta 1983;128 PubMed
- Mosnik DM, Spring B, Rogers K, Baruah S. Tardive dyskinesia exacerbated after ingestion of phenylalanine by schizophrenic patients. Neuropsychopharmacology 1997;16:136-46. PubMed
- Siddiqui AH, Stolk LM, Bhaggoe R, et al. L-phenylalanine and UVA irradiation in the treatment of vitiligo. Dermatology 1994;88:215-8. PubMed
- Birkmayer W, Riederer P, Linauer W, Knoll J. L-deprenyl plus L-phenylalanine in the treatment of depression. J Neural Transm 1984;59:81-7. PubMed
- Nutt JG, Woodward WR, Hammerstad JP, et al. The "on-off" phenomenon in Parkinson's disease. Relation to levodopa absorption and transport. N Engl J Med 1984;310:483-8. PubMed
- Baruzzi A, Contin M, Riva R, et al. Influence of meal ingestion time on pharmacokinetics of orally administered levodopa in parkinsonian patients. Clin Neuropharmacol 1987;10:527-37. PubMed
- Juncos JL, Fabbrini G, Mouradian MM, et al. Dietary influences on the antiparkinsonian response to levodopa. Arch Neurol 1987;44:1003-5. PubMed
- Eriksson T, Granerus AK, Linde A, et al. "On-off" phenomenon in Parkinson's disease: relationship between dopa and other large neutral amino acids in plasma. Neurology 1988;38:1245-8. PubMed
- Baker GB, Bornstein RA, Rouget AC, et al. Phenylethylaminergic mechanisms in attention-deficit disorder. Biol Psychiatry 1991;29:15-22.. PubMed
- Wood DR, Reimherr FW, Wender PH. Treatment of attention deficit disorder with DL-phenylalanine. Psychiatry Res 1985;16:21-6.. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids (Macronutrients). Washington, DC: National Academy Press, 2002. Available at: http://www.n
- Cederbaum S. Phenylketonuria: an update. Curr Opin Pediatr 2002;14:702-6. PubMed
- Cejudo-Ferragud, E., Nacher, A., Polache, A., Cercos-Fortea, T., Merino, M., and Casabo, V. G. Evidence of competitive inhibition for the intestinal absorption of baclofen by phenylalanine. Int J of Pharm (Amsterdam) 1996;132:63-69. DOI
- Fischer, E., Heller, B., Nachon, M., and Spatz, H. Therapy of depression by phenylalanine. Preliminary note. Arzneimittelforschung. 1975;25(1):132.
- Beckmann, H., Strauss, M. A., and Ludolph, E. Dl-phenylalanine in depressed patients: an open study. J.Neural Transm. 1977;41(2-3):123-134. PubMed
- Sabelli, H. C., Fawcett, J., Gusovsky, F., Javaid, J. I., Wynn, P., Edwards, J., Jeffriess, H., and Kravitz, H. Clinical studies on the phenylethylamine hypothesis of affective disorder: urine and blood phenylacetic acid and phenylalanine dietary supplem
- Cotzias, G. C., Van Woert, M. H., and Schiffer, L. M. Aromatic amino acids and modification of parkinsonism. N Engl.J Med 2-16-1967;276(7):374-379. PubMed
- Kravitz, H. M., Sabelli, H. C., and Fawcett, J. Dietary supplements of phenylalanine and other amino acid precursors of brain neuroamines in the treatment of depressive disorders. J Am Osteopath.Assoc 1984;84(1 Suppl):119-123. DOI
- Mann, J., Peselow, E. D., Snyderman, S., and Gershon, S. D-phenylalanine in endogenous depression. Am.J.Psychiatry 1980;137(12):1611-1612. PubMed
- Katoulis AC, Alevizou A, Bozi E, et al. A randomized, double-blind, vehicle-controlled study of a preparation containing undecylenoyl phenylalanine 2% in the treatment of solar lentigines. Clin Exp Dermatol 2010;35(5):473-6. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Threonine 4 references
- Tandan R, Bromberg MB, Forshew D, et al. A controlled trial of amino acid therapy in amyotrophic lateral sclerosis: I. Clinical, functional, and maximum isometric torque data. Neurology 1996;47:1220-6. PubMed
- Lee A, Patterson V. A double blind study of L-threonine in patients with spinal spasticity. Acta Neurol Scand 1993;88:334-8. PubMed
- Blin O, Pouget J, Aubrespy G, et al. A double-blind placebo controlled trial of L-threonine in amyotrophic lateral sclerosis. J Neurol 1992;239:79-81.
- Roufs JB. L-threonine as a symptomatic treatment for amyotrophic lateral sclerosis (ALS). Med Hypotheses 1991;34:20-3. PubMed
L-tryptophan 18 references
- Messiha FS. Fluoxetine: adverse effects and drug-drug interactions. J Toxicol Clin Toxicol 1993;31:603-30. PubMed
- Devoe LD, Castillo RA, Searle NS. Maternal dietary substrates and human fetal biophysical activity. The effects of tryptophan and glucose on fetal breathing movements. Am J Obstet Gynecol 1986;155:135-9. DOI
- Lieberman HR, Corkin S, Spring BJ. The effects of dietary neurotransmitter precursors on human behavior. Am J Clin Nutr 1985;42:366-70. PubMed
- U. S. Food and Drug Administration, Center for Food Safety and Applied Nutrition, Office of Nutritional Products, Labeling, and Dietary Supplements. Information Paper on L-Tryptophan and 5-hydroxy-L-tryptophan, February 2001.
- Sullivan EA, Kamb ML, Jones JL, et al. The natural history of eosinophilia-myalgia syndrome in a tryptophan-exposed cohort in South Carolina. Arch Intern Med 1996;156:973-9. DOI
- Philen RM, Hill RH, Flanders WD, et al. Tryptophan contaminants associated with eosinophilia-myalgia syndrome. Am J Epidemiol 1993;138:154-9. PubMed
- Bohme A, Wolter M, Hoelzer D. L-tryptophan-related eosinophilia-myalgia syndrome possibly associated with a chronic B-lymphocytic leukemia. Ann Hematol 1998;77:235-8. PubMed
- Singhal AB, Caviness VS, Begleiter AF, et al. Cerebral vasoconstriction and stroke after use of serotonergic drugs. Neurology 2002;58:130-3. PubMed
- Priori R, Conti F, Luan FL, et al. Chronic fatigue: a peculiar evolution of eosinophilia myalgia syndrome following treatment with L-tryptophan in four Italian adolescents. Eur J Pediatr 1994;153:344-6..
- Klein R, Berg PA. A comparative study on antibodies to nucleoli and 5-hydroxytryptamine in patients with fibromyalgia syndrome and tryptophan-induced eosinophilia-myalgia syndrome. Clin Investig 1994;72:541-9.. PubMed
- Simat TJ, Kleeberg KK, Muller B, Sierts A. Synthesis, formation, and occurrence of contaminants in biotechnologically manufactured L-tryptophan. Adv Exp Med Biol 1999;467:469-80.. PubMed
- Shaw K, Turner J, Del Mar C. Tryptophan and 5-hydroxytryptophan for depression. Cochrane Database Syst Rev 2002;(1):CD003198. PubMed
- Kilbourne EM, Philen RM, Kamb ML, Falk H. Tryptophan produced by Showa Denko and epidemic eosinophilia-myalgia syndrome. J Rheumatol Suppl 1996;46:81-8.
- Horwitz RI, Daniels SR. Bias or biology: evaluating the epidemiologic studies of L-tryptophan and the eosinophilia-myalgia syndrome. J Rheumatol Suppl 1996;46:60-72.
- Shapiro S. Epidemiologic studies of the association of L-tryptophan with the eosinophilia-myalgia syndrome: a critique. J Rheumatol Suppl 1996;46:44-58.
- Mayeno AN, Gleich GJ. The eosinophilia-myalgia syndrome: lessons from Germany. Mayo Clin Proc 1994;69:702-4. PubMed
- Carr L, Ruther E, Berg PA, Lehnert H. Eosinophilia-myalgia syndrome in Germany: an epidemiologic review. Mayo Clin Proc 1994;69:620-5. PubMed
- Ullrich SS, Fitzgerald PCE, Giesbertz P, Steinert RE, Horowitz M, Feinle-Bisset C. Effects of intragastric administration of tryptophan on the blood glucose response to a nutrient drink and energy intake, in lean and obese men. Nutrients 2018;10(4). pii: PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC