
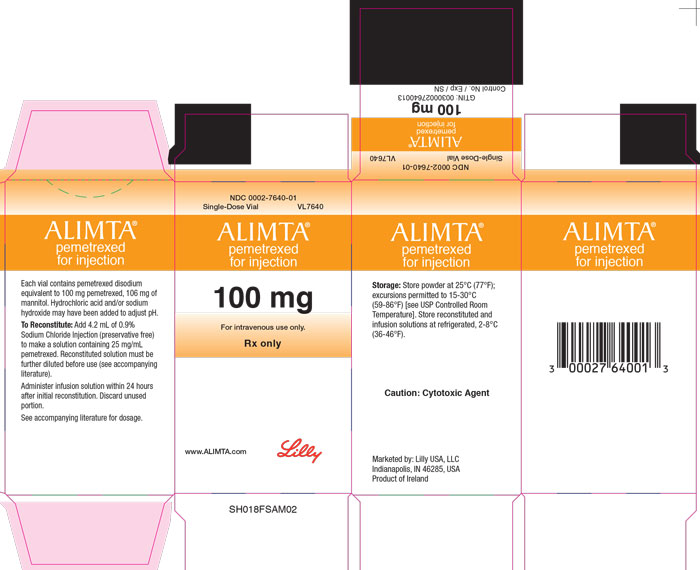
Alimta Pemetrexed disodium 100 mg/4mL Injection, Powder, Lyophilized, For Solution
Other active recalls for Pemetrexed Disodium (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Folate Analog Metabolic Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Pemetrexed injection is used in combination with other chemotherapy medications as a first treatment for a certain type of non-small cell lung cancer (NSCLC) that has spread to nearby tissues or to other parts of the body. Pemetrexed injection is also used alone to treat NSCLC as ongoing treatment in people who have already received certain chemotherapy medications and whose cancer has not worsened and in people who could not be treated successfully with other chemotherapy medications. Pemetrexed injection is also in combination with another chemotherapy medication as a first treatment for mal...
Read the full MedlinePlus article ↗- The folic acid and vitamin B12 aren't just a nice-to-have — they're a required part of your treatment. Without them, pemetrexed is much more likely to cause severe drops in your bl...
- Why do I have to take vitamins before and during my pemetrexed treatment?
- The ones that can't wait are signs of infection — fever, chills, or feeling suddenly very unwell — because your white blood cell count may be dangerously low. Also call right away...
- What side effects should I definitely call my doctor about right away?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
106 mg / 4 mL
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $659.72 | $2,638.89 / 4 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J9305 | $6.952 / J9305 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Alimta 100 mg/4mLthis 00002-7640-01 | Eli | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 16729-0229-03 | Accord | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4.2mL 25021-0260-10 | Sagent | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 31722-0336-31 | Camber | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg 43547-0632-01 | Solco | 100 injections | — | AP | FDA listed | — |
| Pemetrexed disodium 100 mg/4mL 43598-0386-62 | Dr. | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 55150-0381-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 63323-0134-10 | Fresenius | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 67184-0503-01 | Qilu | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 68001-0535-41 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 68001-0538-41 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 68001-0543-41 | BluePoint | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4mL 70069-0834-01 | Somerset | 1 vial | — | AP | FDA listed | — |
| pemetrexed 100 mg/4mL 70710-1654-01 | Zydus | 1 vial | — | AP | FDA listed | — |
| pemetrexed 100 mg/4mL 70771-1691-01 | Zydus | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/4.2mL 71288-0145-10 | Meitheal | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/10mL 71288-0166-10 | Meitheal | 1 vial | — | AP | Discontinued | — |
| Pemetrexed 100 mg/4mL 72338-0100-01 | Waverley | 1 vial | — | AP | FDA listed | — |
| Pemetrexed 100 mg/10mL 72603-0325-01 | NorthStar | 1 vial | — | AP | FDA listed | — |
| Pemetrexed Dipotassium 100 mg/4mL 83831-0111-01 | Avyxa | 1 vial | — | — | FDA listed | — |
| Axtle 100 mg/4mL 83831-0131-01 | Avyxa | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00002-7640-01 You're viewing this | 1 VIAL in 1 CARTON (0002-7640-01) / 4 mL in 1 VIAL | 2008-01-15 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ALIMTA ® is a folate analog metabolic inhibitor indicated: in combination with pembrolizumab and platinum chemotherapy, for the initial treatment of patients with metastatic non-squamous non-small cell lung cancer (NSCLC), with no EGFR or ALK genomic tumor aberrations. ( 1.1 ) in combination with cisplatin for the initial treatment of patients with locally advanced or metastatic, non-squamous NSCLC. ( 1.1 ) as a single agent for the maintenance treatment of patients with locally advanced or metastatic, non-squamous NSCLC whose disease has not progressed after four cycles of platinum-based first-line chemotherapy.
( 1.1 ) as a single agent for the treatment of patients with recurrent, metastatic non-squamous, NSCLC after prior chemotherapy. ( 1.1 ) Limitations of Use: ALIMTA is not indicated for the treatment of patients with squamous cell, non-small cell lung cancer. ( 1.1 ) initial treatment, in combination with cisplatin, of patients with malignant pleural mesothelioma whose disease is unresectable or who are otherwise not candidates for curative surgery.
( 1.2 )
1.1Non-Squamous Non-Small Cell Lung Cancer (NSCLC) ALIMTA ® is indicated: in combination with pembrolizumab and platinum chemotherapy, for the initial treatment of patients with metastatic non-squamous non-small cell lung cancer (NSCLC), with no EGFR or ALK genomic tumor aberrations. in combination with cisplatin for the initial treatment of patients with locally advanced or metastatic, non-squamous NSCLC. as a single agent for the maintenance treatment of patients with locally advanced or metastatic, non-squamous NSCLC whose disease has not progressed after four cycles of platinum-based first-line chemotherapy. as a single agent for the treatment of patients with recurrent, metastatic non-squamous, NSCLC after prior chemotherapy.
Limitations of Use: ALIMTA is not indicated for the treatment of patients with squamous cell, non-small cell lung cancer [see Clinical Studies ( 14.1 )].
1.2Mesothelioma ALIMTA is indicated, in combination with cisplatin, for the initial treatment of patients with malignant pleural mesothelioma whose disease is unresectable or who are otherwise not candidates for curative surgery.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of ALIMTA administered with pembrolizumab and platinum chemotherapy in patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes, administered after pembrolizumab and prior to platinum chemotherapy, on Day 1 of each 21-day cycle. ( 2.1 ) The recommended dose of ALIMTA, administered as a single agent or with cisplatin, in patients with creatinine clearance of 45 mL/minute or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes on Day 1 of each 21-day cycle.
( 2.1 , 2.2 ) Initiate folic acid 400 mcg to 1000 mcg orally, once daily, beginning 7 days prior to the first dose of ALIMTA and continue until 21 days after the last dose of ALIMTA. ( 2.4 ) Administer vitamin B 12 , 1 mg intramuscularly, 1 week prior to the first dose of ALIMTA and every 3 cycles. ( 2.4 ) Administer dexamethasone 4 mg orally, twice daily the day before, the day of, and the day after ALIMTA administration.
( 2.4 )
2.1Recommended Dosage for Non-Squamous NSCLC The recommended dose of ALIMTA when administered with pembrolizumab and platinum chemotherapy for the initial treatment of metastatic non-squamous NSCLC in patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes administered after pembrolizumab and prior to carboplatin or cisplatin on Day 1 of each 21-day cycle for 4 cycles. Following completion of platinum-based therapy, treatment with ALIMTA with or without pembrolizumab is administered until disease progression or unacceptable toxicity.
Please refer to the full prescribing information for pembrolizumab and for carboplatin or cisplatin. The recommended dose of ALIMTA when administered with cisplatin for initial treatment of locally advanced or metastatic non-squamous NSCLC in patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes administered prior to cisplatin on Day 1 of each 21-day cycle for up to six cycles in the absence of disease progression or unacceptable toxicity.
The recommended dose of ALIMTA for maintenance treatment of non-squamous NSCLC in patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes on Day 1 of each 21-day cycle until disease progression or unacceptable toxicity after four cycles of platinum-based first-line chemotherapy. The recommended dose of ALIMTA for treatment of recurrent non-squamous NSCLC in patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes on Day 1 of each 21-day cycle until disease progression or unacceptable toxicity.
2.2Recommended Dosage for Mesothelioma The recommended dose of ALIMTA when administered with cisplatin in patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater is 500 mg/m 2 as an intravenous infusion over 10 minutes on Day 1 of each 21-day cycle until disease progression or unacceptable toxicity.
2.3Renal Impairment ALIMTA dosing recommendations are provided for patients with a creatinine clearance (calculated by Cockcroft-Gault equation) of 45 mL/min or greater [see Dosage and Administration ( 2.1 , 2.2 )] . There is no recommended dose for patients whose creatinine clearance is less than 45 mL/min [see Use in Specific Populations ( 8.6 )] .
2.4Premedication and Concomitant Medications to Mitigate Toxicity Vitamin Supplementation Initiate folic acid 400 mcg to 1000 mcg orally once daily, beginning 7 days before the first dose of ALIMTA and continuing until 21 days after the last dose of ALIMTA [see Warnings and Precautions ( 5.1 )] . Administer vitamin B 12 , 1 mg intramuscular…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 100 mg or 500 mg pemetrexed as a white to light-yellow or green-yellow lyophilized powder in single-dose vials for reconstitution. For Injection: 100 mg or 500 mg lyophilized powder in single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ALIMTA is contraindicated in patients with a history of severe hypersensitivity reaction to pemetrexed [see Adverse Reactions ( 6.1 )]. History of severe hypersensitivity reaction to pemetrexed. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myelosuppression: Can cause severe bone marrow suppression resulting in cytopenia and an increased risk of infection. Do not administer ALIMTA when the absolute neutrophil count is less than 1500 cells/mm 3 and platelets are less than 100,000 cells/mm 3 . Initiate supplementation with oral folic acid and intramuscular vitamin B 12 to reduce the severity of hematologic and gastrointestinal toxicity of ALIMTA.
( 2.4 , 5.1 ) Renal Failure: Can cause severe, and sometimes fatal, renal failure. Do not administer when creatinine clearance is less than 45 mL/min. ( 2.3 , 5.2 ) Bullous and Exfoliative Skin Toxicity: Permanently discontinue for severe and life-threatening bullous, blistering or exfoliating skin toxicity.
( 5.3 ) Interstitial Pneumonitis: Withhold for acute onset of new or progressive unexplained pulmonary symptoms. Permanently discontinue if pneumonitis is confirmed. ( 5.4 ) Radiation Recall: Can occur in patients who received radiation weeks to years previously; permanently discontinue for signs of radiation recall.
( 5.5 ) Embryo-Fetal Toxicity: Can cause fetal harm. Advise patients of the potential risk to a fetus and to use effective contraception. ( 5.7 , 8.1 , 8.3 )
5.1Myelosuppression and Increased Risk of Myelosuppression without Vitamin Supplementation ALIMTA can cause severe myelosuppression resulting in a requirement for transfusions and which may lead to neutropenic infection. The risk of myelosuppression is increased in patients who do not receive vitamin supplementation. In Study JMCH, incidences of Grade 3-4 neutropenia (38% versus 23%), thrombocytopenia (9% versus 5%), febrile neutropenia (9% versus 0.6%), and neutropenic infection (6% versus 0) were higher in patients who received ALIMTA plus cisplatin without vitamin supplementation as compared to patients who were fully supplemented with folic acid and vitamin B 12 prior to and throughout ALIMTA plus cisplatin treatment.
Initiate supplementation with oral folic acid and intramuscular vitamin B 12 prior to the first dose of ALIMTA; continue vitamin supplementation during treatment and for 21 days after the last dose of ALIMTA to reduce the severity of hematologic and gastrointestinal toxicity of ALIMTA [see Dosage and Administration ( 2.4 )] . Obtain a complete blood count at the beginning of each cycle. Do not administer ALIMTA until the ANC is at least 1500 cells/mm 3 and platelet count is at least 100,000 cells/mm 3 .
Permanently reduce ALIMTA in patients with an ANC of less than 500 cells/mm 3 or platelet count of less than 50,000 cells/mm 3 in previous cycles [see Dosage and Administration ( 2.6 )] . In Studies JMDB and JMCH, among patients who received vitamin supplementation, incidence of Grade 3-4 neutropenia was 15% and 23%, the incidence of Grade 3-4 anemia was 6% and 4%, and incidence of Grade 3-4 thrombocytopenia was 4% and 5%, respectively. In Study JMCH, 18% of patients in the ALIMTA arm required red blood cell transfusions compared to 7% of patients in the cisplatin arm [see Adverse Reactions ( 6.1 )].
In Studies JMEN, PARAMOUNT, and JMEI, where all patients received vitamin supplementation, incidence of Grade 3-4 neutropenia ranged from 3% to 5%, and incidence of Grade 3-4 anemia ranged from 3% to 5%.
5.2Renal Failure ALIMTA can cause severe, and sometimes fatal, renal toxicity. The incidences of renal failure in clinical studies in which patients received ALIMTA with cisplatin were: 2.1% in Study JMDB and 2.2% in Study JMCH. The incidence of renal failure in clinical studies in which patients received ALIMTA as a single agent ranged from 0.4% to 0.6% (Studies JMEN, PARAMOUNT, and JMEI [see Adverse Reactions ( 6.1 )] .
Determine creatinine clearance before each dose and periodically monitor renal function during treatment with ALIMTA. Withhold ALIMTA in patients with a creatinine clearance of less than 45 mL/minute [see Dosage and Administration ( 2.3 )] .
5.3 Bullous and Exfoliative Skin Toxicity Serious a…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling: Myelosuppression [see Warnings and Precautions ( 5.1 )] Renal failure [see Warnings and Precautions ( 5.2 )] Bullous and exfoliative skin toxicity [see Warning and Precautions ( 5.3 )] Interstitial pneumonitis [see Warnings and Precautions ( 5.4 )] Radiation recall [see Warnings and Precautions ( 5.5 )] The most common adverse reactions (incidence ≥20%) of ALIMTA, when administered as a single agent are fatigue, nausea, and anorexia.
( 6.1 ) The most common adverse reactions (incidence ≥20%) of ALIMTA when administered with cisplatin are vomiting, neutropenia, anemia, stomatitis/pharyngitis, thrombocytopenia, and constipation. ( 6.1 ) The most common adverse reactions (incidence ≥20%) of ALIMTA when administered in combination with pembrolizumab and platinum chemotherapy are fatigue/asthenia, nausea, constipation, diarrhea, decreased appetite, rash, vomiting, cough, dyspnea, and pyrexia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Eli Lilly and Company at 1-800-LillyRx (1-800-545-5979) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reactions rates cannot be directly compared to rates in other clinical trials and may not reflect the rates observed in clinical practice. In clinical trials, the most common adverse reactions (incidence ≥20%) of ALIMTA, when administered as a single agent, are fatigue, nausea, and anorexia. The most common adverse reactions (incidence ≥20%) of ALIMTA, when administered in combination with cisplatin are vomiting, neutropenia, anemia, stomatitis/pharyngitis, thrombocytopenia, and constipation.
The most common adverse reactions (incidence ≥20%) of ALIMTA, when administered in combination with pembrolizumab and platinum chemotherapy, are fatigue/asthenia, nausea, constipation, diarrhea, decreased appetite, rash, vomiting, cough, dyspnea, and pyrexia. Non-Squamous NSCLC First-line Treatment of Metastatic Non-squamous NSCLC with Pembrolizumab and Platinum Chemotherapy The safety of ALIMTA, in combination with pembrolizumab and investigator's choice of platinum (either carboplatin or cisplatin), was investigated in Study KEYNOTE-189, a multicenter, double-blind, randomized (2:1), active-controlled trial in patients with previously untreated, metastatic non-squamous NSCLC with no EGFR or ALK genomic tumor aberrations.
A total of 607 patients received ALIMTA, pembrolizumab, and platinum every 3 weeks for 4 cycles followed by ALIMTA and pembrolizumab (n=405), or placebo, ALIMTA, and platinum every 3 weeks for 4 cycles followed by placebo and ALIMTA (n=202). Patients with autoimmune disease that required systemic therapy within 2 years of treatment; a medical condition that required immunosuppression; or who had received more than 30 Gy of thoracic radiation within the prior 26 weeks were ineligible [see Clinical Studies ( 14.1 )] .
The median duration of exposure to ALIMTA was 7.2 months (range: 1 day to 1.7 years). Seventy-two percent of patients received carboplatin. The study population characteristics were: median age of 64 years (range: 34 to 84), 49% age 65 years or older, 59% male, 94% White and 3% Asian, and 18% with history of brain metastases at baseline.
ALIMTA was discontinued for adverse reactions in 23% of patients in the ALIMTA, pembrolizumab, and platinum arm. The most common adverse reactions resulting in discontinuation of ALIMTA in this arm were acute kidney injury (3%) and pneumonitis (2%). Adverse reactions leading to interruption of ALIMTA occurred in 49% of patients in the ALIMTA, pembrolizumab, and platinum arm.
The most common adverse reactions or laboratory abnormalities leading to interruption of ALIMTA in this arm (≥2%) were neutropenia (12%), anemia (7%), asthenia (4%), pneumonia (4%), thrombocytopenia (4%), increased blood creatinine (3%),…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Ibuprofen increased risk of ALIMTA toxicity in patients with mild to moderate renal impairment. Modify the ibuprofen dosage as recommended for patients with a creatinine clearance between 45 mL/min and 79 mL/min. ( 2.5 , 5.6 , 7 ) Effects of Ibuprofen on Pemetrexed Ibuprofen increases exposure (AUC) of pemetrexed [see Clinical Pharmacology ( 12.3 )] .
In patients with creatinine clearance between 45 mL/min and 79 mL/min: Avoid administration of ibuprofen for 2 days before, the day of, and 2 days following administration of ALIMTA [see Dosage and Administration ( 2.5 )] . Monitor patients more frequently for myelosuppression, renal, and gastrointestinal toxicity, if concomitant administration of ibuprofen cannot be avoided.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, ALIMTA can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )] . There are no available data on ALIMTA use in pregnant women. In animal reproduction studies, intravenous administration of pemetrexed to pregnant mice during the period of organogenesis was teratogenic, resulting in developmental delays and malformations at doses lower than the recommended human dose of 500 mg/m 2 [see Data ] .
Advise pregnant women of the potential risk to a fetus [see Use in Special Populations ( 8.3 )] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Pemetrexed was teratogenic in mice.
Daily dosing of pemetrexed by intravenous injection to pregnant mice during the period of organogenesis increased the incidence of fetal malformations (cleft palate; protruding tongue; enlarged or misshaped kidney; and fused lumbar vertebra) at doses (based on BSA) 0.03 times the human dose of 500 mg/m 2 . At doses, based on BSA, greater than or equal to 0.0012 times the 500 mg/m 2 human dose, pemetrexed administration resulted in dose-dependent increases in developmental delays (incomplete ossification of talus and skull bone; and decreased fetal weight).
8.2Lactation Risk Summary There is no information regarding the presence of pemetrexed or its metabolites in human milk, the effects on the breastfed infant, or the effects on milk production. Because of the potential for serious adverse reactions in breastfed infants from ALIMTA, advise women not to breastfeed during treatment with ALIMTA and for one week after the last dose.
8.3Females and Males of Reproductive Potential Based on animal data ALIMTA can cause malformations and developmental delays when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )] . Pregnancy Testing Verify pregnancy status of females of reproductive potential prior to initiating Pemetrexed Injection [see Use in Specific Populations ( 8.1 )] . Contraception Females Because of the potential for genotoxicity, advise females of reproductive potential to use effective contraception during treatment with ALIMTA and for 6 months after the last dose.
Males Because of the potential for genotoxicity, advise males with female partners of reproductive potential to use effective contraception during treatment with ALIMTA and for 3 months after the last dose [see Nonclinical Toxicology ( 13.1 )] . Infertility Males ALIMTA may impair fertility in males of reproductive potential. It is not known whether these effects on fertility are reversible [see Nonclinical Toxicology ( 13.1 )] .
8.4Pediatric Use The safety and effectiveness of ALIMTA in pediatric patients have not been established. The safety and pharmacokinetics of ALIMTA were evaluated in two clinical studies conducted in pediatric patients with recurrent solid tumors (NCT00070473 N=32 and NCT00520936 N=72). Patients in both studies received concomitant vitamin B 12 and folic acid supplementation and dexamethasone.
No tumor responses were observed. Adverse reactions observed in pediatric patients were similar to those observed in adults. Single-dose pharmacokinetics of ALIMTA were evaluated in 22 patients age 4 to 18 years enrolled in NCT00070473 were within range of values in adults.
8.5Geriatric Use Of the 3,946 patients enrolled in clinical studies of ALIMTA, 34% were 65 and over and 4% were 75 and over. No overall differences in effectiveness were observed between these patients and younger patients. The incidences of Grade 3-4 anemia, fatigue, thrombocytopenia, hypertension, and neutropenia were higher in patients 65 years of age and older as compared to younger patients: in at least one of five randomized clinic…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, ALIMTA can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology ( 12.1 )] . There are no available data on ALIMTA use in pregnant women. In animal reproduction studies, intravenous administration of pemetrexed to pregnant mice during the period of organogenesis was teratogenic, resulting in developmental delays and malformations at doses lower than the recommended human dose of 500 mg/m 2 [see Data ] .
Advise pregnant women of the potential risk to a fetus [see Use in Special Populations ( 8.3 )] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Pemetrexed was teratogenic in mice.
Daily dosing of pemetrexed by intravenous injection to pregnant mice during the period of organogenesis increased the incidence of fetal malformations (cleft palate; protruding tongue; enlarged or misshaped kidney; and fused lumbar vertebra) at doses (based on BSA) 0.03 times the human dose of 500 mg/m 2 . At doses, based on BSA, greater than or equal to 0.0012 times the 500 mg/m 2 human dose, pemetrexed administration resulted in dose-dependent increases in developmental delays (incomplete ossification of talus and skull bone; and decreased fetal weight).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ALIMTA in pediatric patients have not been established. The safety and pharmacokinetics of ALIMTA were evaluated in two clinical studies conducted in pediatric patients with recurrent solid tumors (NCT00070473 N=32 and NCT00520936 N=72). Patients in both studies received concomitant vitamin B 12 and folic acid supplementation and dexamethasone.
No tumor responses were observed. Adverse reactions observed in pediatric patients were similar to those observed in adults. Single-dose pharmacokinetics of ALIMTA were evaluated in 22 patients age 4 to 18 years enrolled in NCT00070473 were within range of values in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 3,946 patients enrolled in clinical studies of ALIMTA, 34% were 65 and over and 4% were 75 and over. No overall differences in effectiveness were observed between these patients and younger patients. The incidences of Grade 3-4 anemia, fatigue, thrombocytopenia, hypertension, and neutropenia were higher in patients 65 years of age and older as compared to younger patients: in at least one of five randomized clinical trials. [see Adverse Reactions ( 6.1 ) and Clinical Studies ( 14.1 , 14.2 )].
🆘 Overdosage ▾
10 OVERDOSAGE No drugs are approved for the treatment of ALIMTA overdose. Based on animal studies, administration of leucovorin may mitigate the toxicities of ALIMTA overdosage. It is not known whether pemetrexed is dialyzable.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action ALIMTA is a folate analog metabolic inhibitor that disrupts folate-dependent metabolic processes essential for cell replication. In vitro studies show that pemetrexed inhibits thymidylate synthase (TS), dihydrofolate reductase, and glycinamide ribonucleotide formyltransferase (GARFT), which are folate-dependent enzymes involved in the de novo biosynthesis of thymidine and purine nucleotides. Pemetrexed is taken into cells by membrane carriers such as the reduced folate carrier and membrane folate binding protein transport systems.
Once in the cell, pemetrexed is converted to polyglutamate forms by the enzyme folylpolyglutamate synthetase. The polyglutamate forms are retained in cells and are inhibitors of TS and GARFT.
12.2Pharmacodynamics Pemetrexed inhibited the in vitro growth of mesothelioma cell lines (MSTO-211H, NCI-H2052) and showed synergistic effects when combined with cisplatin. Based on population pharmacodynamic analyses, the depth of the absolute neutrophil counts (ANC) nadir correlates with the systemic exposure to pemetrexed and supplementation with folic acid and vitamin B 12 . There is no cumulative effect of pemetrexed exposure on ANC nadir over multiple treatment cycles.
12.3Pharmacokinetics Absorption The pharmacokinetics of pemetrexed when ALIMTA was administered as a single agent in doses ranging from 0.2 to 838 mg/m 2 infused over a 10-minute period have been evaluated in 426 cancer patients with a variety of solid tumors. Pemetrexed total systemic exposure (AUC) and maximum plasma concentration (C max ) increased proportionally with increase of dose. The pharmacokinetics of pemetrexed did not change over multiple treatment cycles.
Distribution Pemetrexed has a steady-state volume of distribution of 16.1 liters. In vitro studies indicated that pemetrexed is 81% bound to plasma proteins. Elimination The total systemic clearance of pemetrexed is 91.8 mL/min and the elimination half-life of pemetrexed is 3.5 hours in patients with normal renal function (creatinine clearance of 90 mL/min).
As renal function decreases, the clearance of pemetrexed decreases and exposure (AUC) of pemetrexed increases. Metabolism Pemetrexed is not metabolized to an appreciable extent. Excretion Pemetrexed is primarily eliminated in the urine, with 70% to 90% of the dose recovered unchanged within the first 24 hours following administration.
In vitro studies indicated that pemetrexed is a substrate of OAT3 (organic anion transporter 3), a transporter that is involved in the active secretion of pemetrexed. Specific Populations Age (26 to 80 years) and sex had no clinically meaningful effect on the systemic exposure of pemetrexed based on population pharmacokinetic analyses. Racial Groups The pharmacokinetics of pemetrexed were similar in Whites and Blacks or African Americans.
Insufficient data are available for other ethnic groups. Patients with Hepatic Impairment Pemetrexed has not been formally studied in patients with hepatic impairment. No effect of elevated AST, ALT, or total bilirubin on the PK of pemetrexed was observed in clinical studies.
Patients with Renal Impairment Pharmacokinetic analyses of pemetrexed included 127 patients with impaired renal function. Plasma clearance of pemetrexed decreases as renal function decreases, with a resultant increase in systemic exposure. Patients with creatinine clearances of 45, 50, and 80 mL/min had 65%, 54%, and 13% increases, respectively in systemic exposure (AUC) compared to patients with creatinine clearance of 100 mL/min [see Dosage and Administration ( 2.3 ) and Warnings and Precautions ( 5.2 )] .
Third-Space Fluid The pemetrexed plasma concentrations in patients with various solid tumors with stable, mild to moderate third-space fluid were comparable to those observed in patients without third space fluid collections. The effect of severe third space fluid on pharmacokinetics is not known. Drug Interaction Studies Drugs Inh…
🧬 Mechanism of Action ▾
12.1Mechanism of Action ALIMTA is a folate analog metabolic inhibitor that disrupts folate-dependent metabolic processes essential for cell replication. In vitro studies show that pemetrexed inhibits thymidylate synthase (TS), dihydrofolate reductase, and glycinamide ribonucleotide formyltransferase (GARFT), which are folate-dependent enzymes involved in the de novo biosynthesis of thymidine and purine nucleotides. Pemetrexed is taken into cells by membrane carriers such as the reduced folate carrier and membrane folate binding protein transport systems.
Once in the cell, pemetrexed is converted to polyglutamate forms by the enzyme folylpolyglutamate synthetase. The polyglutamate forms are retained in cells and are inhibitors of TS and GARFT.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied ALIMTA, pemetrexed for injection, is a white-to-light yellow or green-yellow lyophilized powder supplied in single-dose vials for reconstitution for intravenous infusion. NDC 0002-7640-01 (VL7640): Carton containing one (1) single-dose vial of 100 mg pemetrexed. NDC 0002-7623-01 (VL7623): Carton containing one (1) single-dose vial of 500 mg pemetrexed.
Storage and Handling Store at 25°C (77°F); excursions permitted to 15 °C -30 °C (59 °F - 86 °F) [see USP Controlled Room Temperature]. ALIMTA is a hazardous drug. Follow applicable special handling and disposal procedures.
1
How Supplied ALIMTA, pemetrexed for injection, is a white-to-light yellow or green-yellow lyophilized powder supplied in single-dose vials for reconstitution for intravenous infusion. NDC 0002-7640-01 (VL7640): Carton containing one (1) single-dose vial of 100 mg pemetrexed. NDC 0002-7623-01 (VL7623): Carton containing one (1) single-dose vial of 500 mg pemetrexed.
📦 Storage and Handling ▾
Storage and Handling Store at 25°C (77°F); excursions permitted to 15 °C -30 °C (59 °F - 86 °F) [see USP Controlled Room Temperature]. ALIMTA is a hazardous drug. Follow applicable special handling and disposal procedures. 1
📋 Description ▾
11 DESCRIPTION ALIMTA (pemetrexed for injection) is a folate analog metabolic inhibitor. The drug substance, pemetrexed disodium heptahydrate, has the chemical name L-glutamic acid, N -[4-[2-(2-amino-4,7-dihydro-4-oxo-1 H -pyrrolo[2,3- d ]pyrimidin-5-yl)ethyl]benzoyl]-, disodium salt, heptahydrate with a molecular formula of C 20 H 19 N 5 Na 2 O 6 •7H 2 O and a molecular weight of 597.49. The structural formula is as follows: ALIMTA is a sterile white-to-light yellow or green-yellow lyophilized powder in single-dose vials to be reconstituted for intravenous infusion.
Each 100-mg vial of ALIMTA contains 100 mg pemetrexed (equivalent to 139.8 mg pemetrexed disodium heptahydrate) and 106 mg mannitol. Each 500-mg vial of ALIMTA contains 500 mg pemetrexed (equivalent to 699 mg pemetrexed disodium heptahydrate) and 500 mg mannitol. Hydrochloric acid and/or sodium hydroxide may have been added to adjust pH.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Premedication and Concomitant Medication : Instruct patients to take folic acid as directed and to keep appointments for vitamin B 12 injections to reduce the risk of treatment-related toxicity. Instruct patients of the requirement to take corticosteroids to reduce the risks of treatment-related toxicity [see Dosage and Administration ( 2.4 ) and Warnings and Precautions ( 5.1 ) ].
Myelosuppression : Inform patients of the risk of low blood cell counts and instruct them to immediately contact their physician for signs of infection, fever, bleeding, or symptoms of anemia [see Warnings and Precautions ( 5.1 )] . Renal Failure : Inform patients of the risks of renal failure, which may be exacerbated in patients with dehydration arising from severe vomiting or diarrhea. Instruct patients to immediately contact their healthcare provider for a decrease in urine output [see Warnings and Precautions ( 5.2 )] .
Bullous and Exfoliative Skin Disorders : Inform patients of the risks of severe and exfoliative skin disorders. Instruct patients to immediately contact their healthcare provider for development of bullous lesions or exfoliation in the skin or mucous membranes [see Warnings and Precautions ( 5.3 )] . Interstitial Pneumonitis : Inform patients of the risks of pneumonitis.
Instruct patients to immediately contact their healthcare provider for development of dyspnea or persistent cough [see Warnings and Precautions ( 5.4 )] . Radiation Recall : Inform patients who have received prior radiation of the risks of radiation recall. Instruct patients to immediately contact their healthcare provider for development of inflammation or blisters in an area that was previously irradiated [see Warnings and Precautions ( 5.5 )] .
Increased Risk of Toxicity with Ibuprofen in Patients with Renal Impairment : Advise patients with mild to moderate renal impairment of the risks associated with concomitant ibuprofen use and instruct them to avoid use of all ibuprofen containing products for 2 days before, the day of, and 2 days following administration of ALIMTA [see Dosage and Administration ( 2.5 ), Warnings and Precautions ( 5.6 ), and Drug Interactions ( 7 )] . Embryo-Fetal Toxicity : Advise females of reproductive potential and males with female partners of reproductive potential of the potential risk to a fetus [see Warnings and Precautions ( 5.7 ) and Use in Specific Populations ( 8.1 )] .
Advise females of reproductive potential to use effective contraception during treatment with ALIMTA and for 6 months after the last dose. Advise females to inform their prescriber of a known or suspected pregnancy. Advise males with female partners of reproductive potential to use effective contraception during treatment with ALIMTA and for 3 months after the last dose [see Warnings and Precautions ( 5.7 ) and Use in Specific Populations ( 8.3 )] .
Lactation : Advise women not to breastfeed during treatment with ALIMTA and for 1 week after the last dose [see Use in Specific Populations ( 8.2 )] . Marketed by: Lilly USA, LLC Indianapolis, IN 46285, USA Copyright © 2004, 2022, Eli Lilly and Company. All rights reserved.
ALM-0005-USPI-20220831