
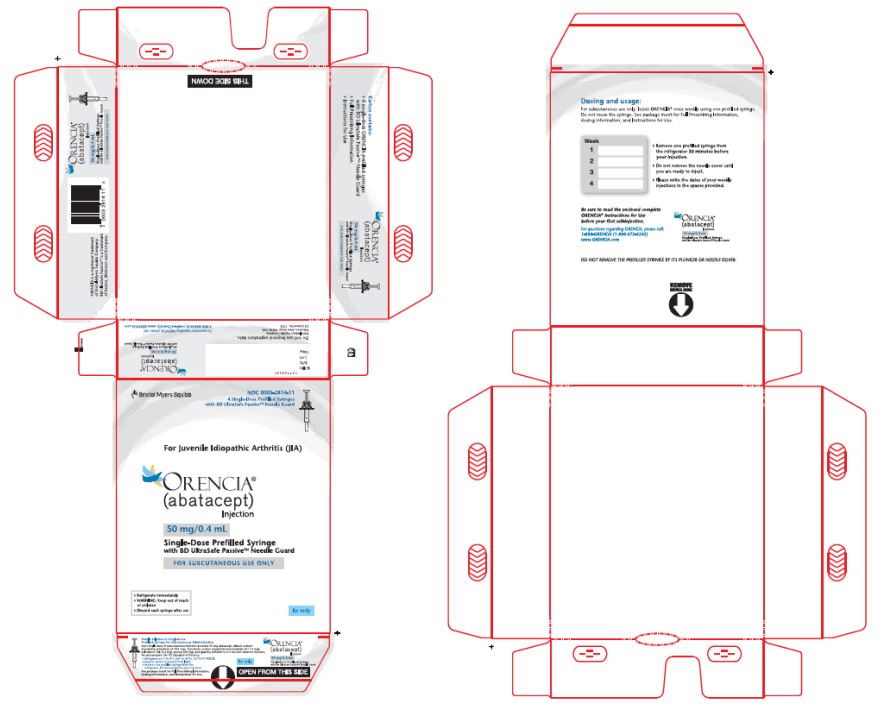
ORENCIA abatacept 125 mg/mL Injection, Solution, 4 syringes — NDC 0003-2188-11 (Billing 00003-2188-11)
This is a package of 4 syringes of ORENCIA abatacept 125 mg/mL Injection, Solution from E.R. Squibb & Sons, L.L.C., marketed since Jul 2011 and currently FDA-listed; retail pharmacies pay about $1,469.23 per mL (NADAC).
NDC database record
One package, one record: these facts belong to NDC 0003-2188-11 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0003 labeler · 2188 product · 11 package
- Package marketed since
- Oct 1, 2013
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0003218811 1
- Medicaid fills, this package
- 4,173 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067681
- GCN: 30289
- GPI-14 (Medi-Span): 6640001000E520
- HICL (First Databank): 037825
- AHFS class code: 90:24.92.00
- RxCUI (RxNorm): 616015
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Selective T Cell Costimulation Modulator class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Abatacept is used: alone or in combination with other medications to reduce the pain, swelling, difficulty with daily activities, and joint damage caused by rheumatoid arthritis (a condition in which the body attacks its own joints causing pain, swelling, and loss of function) in adults who have not been helped by other medications. alone or in combination with methotrexate (Otrexup, Rasuvo, Reditrex, Trexall, Xatmep) to treat polyarticular juvenile idiopathic arthritis (PJIA; a type of childhood arthritis that affects five or more joints during the first six months of the condition, causin...
Read the full MedlinePlus article ↗- Orencia is not a steroid. It's a biologic — a medicine made from proteins — that selectively calms down overactive immune cells called T cells. Your doctor may have prescribed it f...
- What exactly is Orencia used for, and is it a steroid?
- It depends on which form your doctor prescribed. The subcutaneous (under-the-skin) form of Orencia is designed to be injected at home, usually once a week. The intravenous (IV) for...
- Can I give myself the injection at home, or do I always have to go to a clinic?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with abatacept — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1,469.230 | $5,876.92 / 4 ml |
| Medicaid paysCMS SDUD · 12 mo | $1,433.96 | $5,735.84 / 4 ml |
| Medicare drug plans payPart D · Q2 2026 | $1,450.76 | $5,803.05 / 4 ml |
| Medicare Part B allowsASP · J0129 | $45.859 / J0129 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00003-2188-11 You're viewing this | 4 SYRINGE, GLASS in 1 CARTON / 1 mL in 1 SYRINGE, GLASS | $1,469.23 / mL | $5,876.92 | 2013-10-01 | — | Active |
| 00003-2188-21 0003-2188-21 | 1 SYRINGE, GLASS in 1 CARTON / 1 mL in 1 SYRINGE, GLASS | — | — | 2013-10-01 | — | Discontinued by firm |
| 00003-2188-50 0003-2188-50 | 1 SYRINGE, GLASS in 1 CARTON / 1 mL in 1 SYRINGE, GLASS | — | — | 2016-07-05 | — | Discontinued by firm |
| 00003-2188-51 0003-2188-51 Main listing | 4 SYRINGE, GLASS in 1 CARTON / 1 mL in 1 SYRINGE, GLASS | $1,471.09 / mL | $5,884.36 | 2016-06-07 | — | Active |
| 00003-2188-90 0003-2188-90 | 1 SYRINGE, GLASS in 1 CARTON / 1 mL in 1 SYRINGE, GLASS Sample | — | — | 2016-07-12 | — | Active |
| 00003-2188-91 0003-2188-91 | 1 SYRINGE, GLASS in 1 CARTON / 1 mL in 1 SYRINGE, GLASS Sample | — | — | 2013-10-01 | — | Active |
This pack has the lowest per-mL cost of the 2 priced pack sizes ($1,469.23 NADAC).
This pack accounts for about 13% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00003-2188-21?
What NDC number is used to bill for this package of ORENCIA abatacept 125 mg/mL Injection, Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Orencia 125 mg/mLthis 00003-2188-11 | E.R. | 4 syringes | $1,469.230 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Abatacept Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
8 mg / 1 mL
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
0.838 mg / 1 mL
UNII 22ADO53M6F
A mineral salt derived from phosphoric acid, used as a buffer to maintain the pH balance of the medication and help stabilize the active ingredients.
-
0.286 mg / 1 mL
UNII 3980JIH2SW
A salt form of phosphoric acid that acts as a buffer and pH adjuster in medicines. It helps keep the product at the correct acidity level for stability and effectiveness.
-
170 mg / 1 mL
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from E.R. Squibb & Sons, L.L.C. labeler code 00003
- Eliquis apixaban .5 mg Tablet, For Suspension NDC 0003-1028-12
- Cobenfy xanomeline and trospium chloride 100 mg; 20 mg Capsule, Coated Pellets NDC 0003-1100-14
- Baraclude entecavir .5 mg Tablet, Film Coated NDC 0003-1611-12
- Baraclude entecavir 1 mg Tablet, Film Coated NDC 0003-1612-12
- BARACLUDE entecavir .05 mg/mL Solution NDC 0003-1614-12
- ORENCIA abatacept 250 mg/15mL Injection, Powder, Lyophilized, For Solution NDC 0003-2187-10
- Empliciti elotuzumab 300 mg Injection, Powder, Lyophilized, For Solution NDC 0003-2291-11
- YERVOY ipilimumab 5 mg/mL Injection NDC 0003-2327-11
- YERVOY ipilimumab 5 mg/mL Injection NDC 0003-2328-22
- Azactam Aztreonam 1 g Injection, Powder, For Solution NDC 0003-2560-16
- Azactam Aztreonam 2 g Injection, Powder, For Solution NDC 0003-2570-16
- ORENCIA abatacept 50 mg/.4mL Injection, Solution NDC 0003-2814-11
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ORENCIA is a selective T cell costimulation modulator indicated for: • the treatment of adult patients with moderately to severely active rheumatoid arthritis (RA). (1.1) • the treatment of patients 2 years of age and older with moderately to severely active polyarticular juvenile idiopathic arthritis (pJIA). (1.2) • the treatment of patients 2 years of age and older with active psoriatic arthritis (PsA).
(1.3) • the prophylaxis of acute graft versus host disease (aGVHD), in combination with a calcineurin inhibitor and methotrexate, in adults and pediatric patients 2 years of age and older undergoing hematopoietic stem cell transplantation (HSCT) from a matched or 1 allele-mismatched unrelated donor. (1.4) Limitations of Use: Concomitant use of ORENCIA with other immunosuppressives [e.g., biologic disease-modifying antirheumatic drugs (bDMARDS), Janus kinase (JAK) inhibitors] is not recommended. ( 1.5 , 5.1)
1.1Adult Rheumatoid Arthritis ORENCIA ® is indicated for the treatment of adult patients with moderately to severely active rheumatoid arthritis (RA).
1.2Polyarticular Juvenile Idiopathic Arthritis ORENCIA is indicated for the treatment of patients 2 years of age and older with moderately to severely active polyarticular juvenile idiopathic arthritis (pJIA).
1.3Psoriatic Arthritis ORENCIA is indicated for the treatment of patients 2 years of age and older with active psoriatic arthritis (PsA).
1.4Prophylaxis for Acute Graft versus Host Disease ORENCIA is indicated for the prophylaxis of acute graft versus host disease (aGVHD), in combination with a calcineurin inhibitor and methotrexate, in adults and pediatric patients 2 years of age and older undergoing hematopoietic stem cell transplantation (HSCT) from a matched or 1 allele-mismatched unrelated-donor.
1.5Limitations of Use The concomitant use of ORENCIA with other potent immunosuppressants [e.g., biologic disease-modifying antirheumatic drugs (bDMARDs), Janus kinase (JAK) inhibitors] is not recommended.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Intravenous Use for Adult RA (2.1) and Adult PsA (2.3) • Administer at 0, 2, and 4 weeks, and every 4 weeks thereafter, as a 30-minute infusion Body Weight of Patient Dose Number of Vials Less than 60 kg 500 mg 2 60 to 100 kg 750 mg 3 More than 100 kg 1,000 mg 4 Subcutaneous Use for Adult RA (2.1) • Prior to the first subcutaneous dose, may administer an optional loading dose as a single intravenous infusion as per body weight categories above. • Administer 125 mg by subcutaneous injection once weekly (within a day of the intravenous infusion if infusion given). • Patients switching from intravenous use to subcutaneous use, administer first subcutaneous dose instead of next scheduled intravenous dose.
Intravenous Use for pJIA in Pediatric Patients ≥6 Years Old (2.2) • Pediatric patients weighing <75 kg administer 10 mg/kg intravenously and those weighing ≥75 kg administer the adult intravenous dosing regimen (not to exceed a maximum dose of 1,000 mg), as a 30-minute infusion. • Subsequently administer infusions at 2 and 4 weeks and every 4 weeks thereafter. Subcutaneous Use for pJIA and PsA in Pediatric Patients ≥2 Years Old (2.2) • Administer subcutaneously without an intravenous loading dose Body Weight of Pediatric Patient Dose (once weekly) 10 kg to less than 25 kg 50 mg 25 kg to less than 50 kg 87.5 mg 50 kg or more 125 mg Subcutaneous Use for Adult PsA ( 2.3 ) • Administer 125 mg by subcutaneous injection once weekly without an intravenous loading dose. • Patients switching from intravenous use to subcutaneous use, administer first subcutaneous dose instead of next scheduled intravenous dose.
Intravenous Use for Prophylaxis of aGVHD (2.4) • For patients 6 years and older, administer at a 10 mg/kg dose (maximum dose 1,000 mg) as a 60-minute infusion on the day before transplantation, followed by a dose on Day 5, 14, and 28 after transplant. • For patients 2 to less than 6 years old, administer a 15 mg/kg dose as a 60-minute infusion on the day before transplantation, followed by a 12 mg/kg dose as a 60-minute infusion on Day 5, 14, and 28 after transplant. Preparation and Administration Instructions ( 2.5 , 2.6 ) • Administer as a 30-minute intravenous infusion for RA, pJIA, and adult PsA.
(2.5) • Administer as a 60-minute intravenous infusion for aGVHD prophylaxis. (2.5) • See the Full Prescribing Information for preparation and administration instructions for intravenous infusion and recommendations for subcutaneous use. (2.5, 2.6) Prepare ORENCIA using only the silicone-free disposable syringe.
(2.5)
2.1Dosage in Adult Rheumatoid Arthritis For adult patients with RA, administer as an intravenous infusion or as a subcutaneous injection. ORENCIA may be used as monotherapy or concomitantly with disease-modifying antirheumatic drugs (DMARDs) other than JAK inhibitors or bDMARDs (e.g., TNF antagonists). Intravenous Dosage Reconstitute ORENCIA lyophilized powder and administer after dilution [see Dosage and Administration (2.5) ] as a 30-minute intravenous infusion utilizing the weight range-based dosing recommended in Table 1.
Following the initial intravenous infusion, administer as an intravenous infusion at 2 and 4 weeks and every 4 weeks thereafter. Table 1: Dose of ORENCIA for Intravenous Infusion in Adult RA Patients Body Weight of Adult Patient Dose Number of Vials a a Each vial provides 250 mg of abatacept for administration. Less than 60 kg 500 mg 2 60 to 100 kg 750 mg 3 More than 100 kg 1,000 mg 4 Subcutaneous Dosage Prior to the first subcutaneous dose, an optional loading dose may be administered as a single intravenous infusion (as per body weight categories in Table 1).
If an intravenous loading dose is used, administer the first subcutaneous injection within one day of the infusion. Administer ORENCIA 125 mg in prefilled syringes or in ORENCIA ClickJect™ autoinjector by subcutaneous injection once weekly [see Dosage and Administration (2.6) ] . For patients switching from ORENCIA… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Intravenous Infusion • For injection: 250 mg lyophilized powder in a single-dose vial. (3) Subcutaneous Use • Injection: 50 mg/0.4 mL, 87.5 mg/0.7 mL, 125 mg/mL solution in single-dose prefilled syringe. (3) • Injection: 125 mg/mL solution in a single-dose prefilled ClickJect™ autoinjectors.
(3) • Intravenous Infusion For injection: 250 mg white lyophilized powder in a single-dose vial [see Dosage and Administration (2.1 , 2.2 , 2.3 , 2.5 )] . • Subcutaneous Use Injection: 50 mg/0.4 mL, 87.5 mg/0.7 mL, and 125 mg/mL of a clear to slightly opalescent, colorless to pale-yellow solution in a single-dose prefilled glass syringe. Injection: 125 mg/mL of a clear to slightly opalescent, colorless to pale-yellow solution in a single-dose prefilled ClickJect autoinjector.
• Intravenous Infusion For injection: 250 mg white lyophilized powder in a single-dose vial [see Dosage and Administration (2.1 , 2.2 , 2.3 , 2.5 )] . • Subcutaneous Use Injection: 50 mg/0.4 mL, 87.5 mg/0.7 mL, and 125 mg/mL of a clear to slightly opalescent, colorless to pale-yellow solution in a single-dose prefilled glass syringe. Injection: 125 mg/mL of a clear to slightly opalescent, colorless to pale-yellow solution in a single-dose prefilled ClickJect autoinjector.
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Concomitant use with a TNF antagonist can increase the risk of infections and serious infections. (5.1) • Hypersensitivity and anaphylaxis have occurred. (5.2) • Serious infections reported.
Patients with a history of recurrent infections or underlying conditions predisposing to infections may experience more infections. Discontinue if a serious infection develops. (5.3) • Screen for latent TB infection prior to initiating therapy.
Patients testing positive should be treated prior to initiating ORENCIA. (5.3) • Screen for viral hepatitis prior to initiating ORENCIA. (5.3) • Update vaccinations prior to initiating ORENCIA.
Live vaccines should not be given concurrently or within 3 months of discontinuation. ORENCIA may blunt the effectiveness of some immunizations. (5.4) • COPD patients may develop more frequent respiratory adverse reactions.
(5.5) • Cytomegalovirus (CMV) and Epstein-Barr Virus (EBV) reactivation in patients treated for aGVHD prophylaxis. (5.7)
5.1Increased Risk of Infection with Concomitant Use of TNF Antagonists, Other Biologic RA/PsA Therapy, or JAK Inhibitors In controlled clinical trials in patients with adult RA, patients receiving concomitant intravenous ORENCIA and TNF antagonist therapy experienced more infections (63% vs. 43%) and serious infections (4.4% vs. 0.8%) compared to patients treated with only TNF antagonists [see Adverse Reactions (6.1) ] .
These trials failed to demonstrate an important enhancement of efficacy with concomitant administration of ORENCIA with TNF antagonists; therefore, concurrent therapy with ORENCIA and a TNF antagonist is not recommended. While transitioning from TNF antagonist therapy to ORENCIA therapy, patients should be monitored for signs of infection. Additionally, concomitant use of ORENCIA with other biologic RA/PsA therapy or JAK inhibitors is not recommended.
5.2Hypersensitivity Reactions In clinical trials of 2688 adult RA patients treated with intravenous ORENCIA, there were two cases (<0.1%) of anaphylaxis reactions. Other reactions potentially associated with drug hypersensitivity, such as hypotension, urticaria, and dyspnea, each occurred in less than 0.9% of ORENCIA-treated patients. Of the 190 ORENCIA-treated patients in pJIA clinical trials, there was one case of a hypersensitivity reaction (0.5%) [see Adverse Reactions (6.1 )] .
In postmarketing experience, fatal anaphylaxis following the first infusion of ORENCIA and life-threatening cases of angioedema have been reported. Angioedema has occurred as early as after the first dose of ORENCIA, but also has occurred with subsequent doses. Angioedema reactions have occurred within hours of administration and in some instances had a delayed onset (i.e., days).
Appropriate medical support measures for the treatment of hypersensitivity reactions should be available for immediate use in the event of a reaction. If an anaphylactic or other serious allergic reaction occurs, administration of intravenous or subcutaneous ORENCIA should be stopped immediately with appropriate therapy instituted, and the use of ORENCIA should be permanently discontinued.
5.3Infections Serious infections, including sepsis and pneumonia, have been reported in patients receiving ORENCIA (serious infections were reported in 3% and 1.9% of RA patients treated with intravenous ORENCIA and placebo, respectively) [see Adverse Reactions (6.1) ] . Some of these infections have been fatal. Many of the serious infections have occurred in patients on concomitant immunosuppressive therapy which in addition to their underlying disease, could further predispose them to infection.
A higher rate of serious infections has been observed in adult RA patients treated with concurrent TNF antagonists and ORENCIA compared to those treated with ORENCIA alone [see Warnings and Precautions (5.1) ] . Healthcare providers should exercise caution when considering the use of ORENCIA in patients with a history of recurrent infections,… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Increased Risk of Infection with Concomitant Use with TNF Antagonists, Other Biologic RA/PsA Therapy, or JAK Inhibitors [see Warnings and Precautions (5.1) ] • Hypersensitivity Reactions [see Warnings and Precautions (5.2) ] • Infections [see Warnings and Precautions (5.3) ] • Increased Risk of Adverse Reactions When Used in Patients with Chronic Obstructive Pulmonary Disease (COPD) [see Warnings and Precautions (5.5) ] • Immunosuppression [see Warnings and Precautions (5.6) ] • Cytomegalovirus (CMV) and Epstein-Barr Virus (EBV) Reactivation in aGVHD Prophylaxis after Hematopoietic Stem Cell Transplant (HSCT) [see Warnings and Precautions (5.7) ] • Most common adverse events (≥10%) in RA are headache, upper respiratory tract infection, nasopharyngitis, and nausea.
(6.1) • Most common adverse reactions (≥10%) in prophylaxis of aGVHD are anemia, hypertension, CMV reactivation/CMV infection, pyrexia, pneumonia, epistaxis, CD4 lymphocytes decreased, hypermagnesemia, and acute kidney injury. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Bristol-Myers Squibb at 1-800-721-5072 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying and controlled conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not predict the rates observed in a broader patient population in clinical practice. Adverse Reactions in Adult Patients with RA Adverse Reactions in Adult Patients with RA Treated with Intravenous ORENCIA The data from placebo-controlled studies described herein reflect exposure to ORENCIA administered intravenously in patients with active RA (1955 patients with ORENCIA, 989 with placebo) (Studies I through VI) [see Clinical Studies (14.1) ] .
The studies had either a double-blind, placebo-controlled period of 6 months (258 patients with ORENCIA, 133 with placebo) or 1 year (1697 patients with ORENCIA, 856 with placebo). A subset of these patients received concomitant biologic DMARD therapy, such as a TNF antagonist (204 patients with ORENCIA, 134 with placebo). The concomitant use of ORENCIA with a TNF antagonist is not recommended [see Indications and Usage (1.5) ] .
The majority of patients in RA clinical studies received one or more of the following concomitant medications with ORENCIA: methotrexate, nonsteroidal anti-inflammatory drugs (NSAIDs), corticosteroids, TNF antagonist, azathioprine, chloroquine, gold, hydroxychloroquine, leflunomide, sulfasalazine, and anakinra. The most serious adverse reactions were serious infections and malignancies. The most commonly reported adverse events (occurring in ≥10% of patients treated with ORENCIA) were headache, upper respiratory tract infection, nasopharyngitis, and nausea.
The adverse reactions most frequently resulting in clinical intervention (interruption or discontinuation of ORENCIA) were due to infection. The most frequently reported infections resulting in dose interruption were upper respiratory tract infection (1%), bronchitis (0.7%), and herpes zoster (0.7%). The most frequent infections resulting in discontinuation were pneumonia (0.2%), localized infection (0.2%), and bronchitis (0.1%).
Most Common Adverse Reactions in Adult Patients with RA Treated with Intravenous ORENCIA Adverse reactions occurring in 3% or more of patients and at least 1% more frequently in ORENCIA-treated patients (intravenous) during placebo-controlled RA studies are summarized in Table 4. Table 4: Most Common Adverse Reactions* During Placebo-Controlled RA Studies of Intravenous ORENCIA Intravenous ORENCIA (n=1955) a Placebo (n=989) b * Occurred in ≥3% patients and >1% more frequently in ORENCIA-treated patients. a Includes 204 patients on concomitant biologic DMARDs (adalimumab, anakinra, etaner… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Immunosuppressants Concomitant administration of a TNF antagonist with ORENCIA has been associated with an increased risk of serious infections and no significant additional efficacy over use of the TNF antagonists alone. Concurrent therapy with ORENCIA and TNF antagonists is not recommended [see Warnings and Precautions (5.1) ]. There is insufficient experience to assess the safety and efficacy of ORENCIA administered concurrently with other biologic RA therapy, such as anakinra, or other biologic PsA therapy, and JAK inhibitors and therefore such use is not recommended. [see Warnings and Precautions (5.1) ] .
7.2Blood Glucose Testing Parenteral drug products containing maltose can interfere with the readings of blood glucose monitors that use test strips with glucose dehydrogenase pyrroloquinoline quinone (GDH-PQQ). The GDH-PQQ based glucose monitoring systems may react with the maltose present in ORENCIA for intravenous administration, resulting in falsely elevated blood glucose readings on the day of infusion. When receiving intravenous ORENCIA, patients that require blood glucose monitoring should be advised to consider methods that do not react with maltose, such as those based on glucose dehydrogenase nicotine adenine dinucleotide (GDH-NAD), glucose oxidase, or glucose hexokinase test methods.
ORENCIA for subcutaneous administration does not contain maltose; therefore, patients do not need to alter their glucose monitoring.
🔄 Drug / Laboratory Test Interactions ▾
7.2Blood Glucose Testing Parenteral drug products containing maltose can interfere with the readings of blood glucose monitors that use test strips with glucose dehydrogenase pyrroloquinoline quinone (GDH-PQQ). The GDH-PQQ based glucose monitoring systems may react with the maltose present in ORENCIA for intravenous administration, resulting in falsely elevated blood glucose readings on the day of infusion. When receiving intravenous ORENCIA, patients that require blood glucose monitoring should be advised to consider methods that do not react with maltose, such as those based on glucose dehydrogenase nicotine adenine dinucleotide (GDH-NAD), glucose oxidase, or glucose hexokinase test methods.
ORENCIA for subcutaneous administration does not contain maltose; therefore, patients do not need to alter their glucose monitoring.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary The data with ORENCIA use in pregnant women are insufficient to inform on drug-associated risk. However, there are clinical considerations for administering live vaccines to infants who were exposed to ORENCIA while in utero (see Clinical Considerations) . In reproductive toxicology studies in rats and rabbits, no fetal malformations were observed with intravenous administration of ORENCIA during organogenesis at doses that produced exposures approximately 29 times the exposure at the maximum recommended human dose (MRHD) of 10 mg/kg/month on an AUC basis.
However, in a pre- and postnatal development study in rats, ORENCIA altered immune function in female rats at 11 times the MRHD on an AUC basis. Clinical Considerations Infants and Administration of Live Vaccines It is unknown if abatacept can cross the placenta into the fetus when a woman is treated with ORENCIA during pregnancy. Abatacept is an immunomodulatory agent.
It is unknown if the immune response of an infant who was exposed in utero to abatacept and subsequently administered a live vaccine is impacted. Risks and benefits should be considered prior to vaccinating such infants [see Warnings and Precautions (5.4) ] . Data Human Data There are no adequate and well-controlled studies of ORENCIA use in pregnant women.
The data with ORENCIA use in pregnant women are insufficient to inform on drug-associated risk. Animal Data Intravenous administration of abatacept during organogenesis to mice (10, 55, or 300 mg/kg/day), rats (10, 45, or 200 mg/kg/day), and rabbits (10, 45, or 200 mg/kg every 3 days) produced exposures in rats and rabbits that were approximately 29 times the MRHD on an AUC basis (at maternal doses of 200 mg/kg/day in rats and rabbits), and no embryotoxicity or fetal malformations were observed in any species. In a study of pre- and postnatal development in rats (10, 45, or 200 mg/kg every 3 days from gestation day 6 through lactation day 21), alterations in immune function in female offspring, consisting of a 9-fold increase in T-cell-dependent antibody response relative to controls on postnatal day (PND) 56 and thyroiditis in a single female pup on PND 112, occurred at approximately 11 times the MRHD on an AUC basis (at a maternal dose of 200 mg/kg).
No adverse effects were observed at approximately 3 times the MRHD (a maternal dose of 45 mg/kg). It is not known if immunologic perturbations in rats are relevant indicators of a risk for development of autoimmune diseases in humans exposed in utero to abatacept. Exposure to abatacept in the juvenile rat, which may be more representative of the fetal immune system state in the human, resulted in immune system abnormalities including inflammation of the thyroid and pancreas [see Nonclinical Toxicology (13.2) ] .
8.2Lactation Risk Summary There is no information regarding the presence of abatacept in human milk, the effects on the breastfed infant, or the effects on milk production. However, abatacept was present in the milk of lactating rats dosed with abatacept.
8.4Pediatric Use Polyarticular Juvenile Idiopathic Arthritis The safety and effectiveness of ORENCIA for reducing signs and symptoms in patients 2 years of age and older with moderately to severely active polyarticular juvenile idiopathic arthritis (pJIA) have been established (ORENCIA may be used as monotherapy or concomitantly with methotrexate). Use of ORENCIA for this indication is supported by evidence from the following studies: Intravenous Use : A randomized withdrawal efficacy, safety, and pharmacokinetic study of intravenous ORENCIA in 190 pediatric patients 6 to 17 years of age with pJIA [see Clinical Pharmacology (12.3) and Clinical Studies (14.2) ] .
Given that population pharmacokinetic (PK) analyses (after intravenous ORENCIA administration) showed that clearance of abatacept increased with baseline body weight, intravenous ORENCIA is administered either weight-based or weight… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The data with ORENCIA use in pregnant women are insufficient to inform on drug-associated risk. However, there are clinical considerations for administering live vaccines to infants who were exposed to ORENCIA while in utero (see Clinical Considerations) . In reproductive toxicology studies in rats and rabbits, no fetal malformations were observed with intravenous administration of ORENCIA during organogenesis at doses that produced exposures approximately 29 times the exposure at the maximum recommended human dose (MRHD) of 10 mg/kg/month on an AUC basis.
However, in a pre- and postnatal development study in rats, ORENCIA altered immune function in female rats at 11 times the MRHD on an AUC basis. Clinical Considerations Infants and Administration of Live Vaccines It is unknown if abatacept can cross the placenta into the fetus when a woman is treated with ORENCIA during pregnancy. Abatacept is an immunomodulatory agent.
It is unknown if the immune response of an infant who was exposed in utero to abatacept and subsequently administered a live vaccine is impacted. Risks and benefits should be considered prior to vaccinating such infants [see Warnings and Precautions (5.4) ] . Data Human Data There are no adequate and well-controlled studies of ORENCIA use in pregnant women.
The data with ORENCIA use in pregnant women are insufficient to inform on drug-associated risk. Animal Data Intravenous administration of abatacept during organogenesis to mice (10, 55, or 300 mg/kg/day), rats (10, 45, or 200 mg/kg/day), and rabbits (10, 45, or 200 mg/kg every 3 days) produced exposures in rats and rabbits that were approximately 29 times the MRHD on an AUC basis (at maternal doses of 200 mg/kg/day in rats and rabbits), and no embryotoxicity or fetal malformations were observed in any species. In a study of pre- and postnatal development in rats (10, 45, or 200 mg/kg every 3 days from gestation day 6 through lactation day 21), alterations in immune function in female offspring, consisting of a 9-fold increase in T-cell-dependent antibody response relative to controls on postnatal day (PND) 56 and thyroiditis in a single female pup on PND 112, occurred at approximately 11 times the MRHD on an AUC basis (at a maternal dose of 200 mg/kg).
No adverse effects were observed at approximately 3 times the MRHD (a maternal dose of 45 mg/kg). It is not known if immunologic perturbations in rats are relevant indicators of a risk for development of autoimmune diseases in humans exposed in utero to abatacept. Exposure to abatacept in the juvenile rat, which may be more representative of the fetal immune system state in the human, resulted in immune system abnormalities including inflammation of the thyroid and pancreas [see Nonclinical Toxicology (13.2) ] .
🧒 Pediatric Use ▾
8.4Pediatric Use Polyarticular Juvenile Idiopathic Arthritis The safety and effectiveness of ORENCIA for reducing signs and symptoms in patients 2 years of age and older with moderately to severely active polyarticular juvenile idiopathic arthritis (pJIA) have been established (ORENCIA may be used as monotherapy or concomitantly with methotrexate). Use of ORENCIA for this indication is supported by evidence from the following studies: Intravenous Use : A randomized withdrawal efficacy, safety, and pharmacokinetic study of intravenous ORENCIA in 190 pediatric patients 6 to 17 years of age with pJIA [see Clinical Pharmacology (12.3) and Clinical Studies (14.2) ] .
Given that population pharmacokinetic (PK) analyses (after intravenous ORENCIA administration) showed that clearance of abatacept increased with baseline body weight, intravenous ORENCIA is administered either weight-based or weight ranged based [see Dosage and Administration (2.2) ] . Intravenous ORENCIA administration has not been studied in patients younger than 6 years of age. Subcutaneous Use : An open-label PK and safety study of subcutaneous ORENCIA in 205 pediatric patients aged 2 to 17 years old with pJIA, extrapolation of effectiveness of intravenous ORENCIA in patients with pJIA and subcutaneous ORENCIA in patients with RA [see Clinical Pharmacology (12.3) and Clinical Studies (14.2)] .
Given that population PK analyses (after subcutaneous ORENCIA injection) in pJIA patients showed that there was a trend toward higher clearance of abatacept with increasing body weight, subcutaneous ORENCIA dosage is weight range-based [see Dosage and Administration (2.2) ] . The safety and effectiveness of ORENCIA use in pJIA in pediatric patients less than two years of age have not been established. Acute Graft Versus Host Disease Prophylaxis The safety and effectiveness of ORENCIA for the prophylaxis of Acute Graft Versus Host Disease (aGVHD), in combination with a calcineurin inhibitor and methotrexate, in pediatric patients aged 2 years of age and older undergoing HSCT from a matched or 1 allele-mismatched unrelated donor have been established.
Use of ORENCIA for this indication is supported by evidence from: • adequate and well-controlled studies in adults and pediatric patients aged 6 years and older administered a dose of 10 mg/kg intravenously on the day before transplantation followed by a dose of 10 mg/kg intravenously on Days 5, 14, and 28 after transplantation and • pharmacokinetic modeling and simulations of abatacept exposure in pediatric patients aged 2 to less than 6 years administered a dose of 15 mg/kg intravenously on the day before transplantation followed by a dose of 12 mg/kg intravenously on Days 5, 14, and 28 after transplantation.
Furthermore, the course of disease is sufficiently similar in pediatric patients aged 2 years to less than 6 years to that of patients aged 6 years and older to allow extrapolation of data to younger pediatric patients [see Clinical Pharmacology (12.3) and Clinical Studies (14.4) ] . No new safety signals were observed in pediatric patients aged 6 years and older in Study GVHD-1. The safety and effectiveness of ORENCIA for this indication have not been established in pediatric patients less than 2 years of age.
Psoriatic Arthritis Subcutaneous Administration The safety and effectiveness of subcutaneous ORENCIA have been established for treatment of psoriatic arthritis in pediatric patients 2 to 17 years old. Use of ORENCIA in this age group is supported by evidence from adequate and well-controlled studies of ORENCIA in adults with PsA, pharmacokinetic data from adult patients with RA, adult patients with PsA, and pediatric patients with pJIA, and safety data from clinical studies in pediatric patients 2 to 17 years old with pJIA using the subcutaneous formulation.
The observed pre-dose (trough) concentrations are generally comparable between adults with RA and PsA and pediatric patients with JIA with active polyarthritis,… [Excerpted — this section continues on DailyMed.]
🧓 Geriatric Use ▾
8.5Geriatric Use Rheumatoid Arthritis A total of 323 patients 65 years of age and older, including 53 patients 75 years and older, received ORENCIA in clinical studies. No overall differences in safety or effectiveness were observed between geriatric patients (patients aged 65 years of age and older) and younger adults, and other reported clinical experience has not identified differences in responses between geriatric patients and younger adults, but greater sensitivity of some geriatric patients cannot be ruled out.
The frequency of serious infection and malignancy among ORENCIA-treated patients over age 65 was higher than for those under age 65. Because there is a higher incidence of infections and malignancies in the geriatric population in general, caution should be used when treating geriatric patients. Acute Graft Versus Host Disease Prophylaxis Of the 116 patients in Study GVHD-1 who received ORENCIA at a dose of 10 mg/kg for the prophylaxis of aGVHD, 12 (10%) were 65 years of age and older, and 2 (2%) patients were 75 years of age and older [see Clinical Studies (14.4) ].
Clinical studies of ORENCIA for aGVHD did not include sufficient numbers of patients 65 years of age and older to determine whether they respond differently from younger adult patients.
🆘 Overdosage ▾
10 OVERDOSAGE ORENCIA doses up to 50 mg/kg (5 times the maximum recommended dose in patients aged 6 years and older and 3.3 times the maximum recommended dose in patients aged 2 to less than 6 years) have been administered intravenously without apparent toxic effect. In case of overdosage, it is recommended that the patient be monitored for any signs or symptoms of adverse reactions and appropriate symptomatic treatment instituted.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Abatacept, a selective costimulation modulator, inhibits T-cell (T lymphocyte) activation by binding to CD80 and CD86, thereby blocking interaction with CD28. This interaction provides a costimulatory signal necessary for full activation of T lymphocytes. Activated T lymphocytes are implicated in the pathogenesis of RA, pJIA and PsA and are found in the synovium of patients with RA, pJIA and PsA.
In vitro , abatacept decreases T-cell proliferation and inhibits the production of the cytokines TNF alpha (TNFα), interferon-γ, and interleukin-2. In a rat collagen-induced arthritis model, abatacept suppresses inflammation, decreases anti-collagen antibody production, and reduces antigen specific production of interferon-γ. The relationship of these biological response markers to the mechanisms by which ORENCIA exerts its clinical effects is unknown.
12.2Pharmacodynamics In clinical trials with ORENCIA at doses approximating 10 mg/kg, decreases were observed in serum levels of soluble interleukin-2 receptor (sIL-2R), interleukin-6 (IL-6), rheumatoid factor (RF), C-reactive protein (CRP), matrix metalloproteinase-3 (MMP3), and TNFα. The relationship of these biological response markers to the mechanisms by which ORENCIA exerts its clinical effects is unknown. No formal pharmacodynamic analyses of biologic response markers have been performed in patients exposed to ORENCIA as prophylaxis for aGVHD.
12.3Pharmacokinetics Healthy Adults and Adult RA - Intravenous Administration The pharmacokinetics of abatacept were studied in healthy adult subjects after a single 10 mg/kg intravenous infusion and in RA patients after multiple 10 mg/kg intravenous infusions of ORENCIA (see Table 7). Table 7: Pharmacokinetic Parameters (Mean, Range) in Healthy Subjects and RA Patients After 10 mg/kg ORENCIA Intravenous Infusion(s) PK Parameter Healthy Subjects (After 10 mg/kg Single Dose) n=13 RA Patients (After 10 mg/kg Multiple Doses a ) n=14 a Multiple intravenous infusions of ORENCIA were administered at days 1, 15, 30, and monthly thereafter.
Peak Concentration (C max ) [mcg/mL] 292 (175-427) 295 (171-398) Terminal half-life (t 1/2 ) [days] 16.7 (12-23) 13.1 (8-25) Systemic clearance (CL) [mL/h/kg] 0.23 (0.16-0.30) 0.22 (0.13-0.47) Volume of distribution (Vss) [L/kg] 0.09 (0.06-0.13) 0.07 (0.02-0.13) The pharmacokinetics of abatacept in RA patients and healthy subjects appeared to be comparable. In RA patients, after multiple intravenous infusions, the pharmacokinetics of abatacept showed proportional increases of C max and AUC over the dose range of 2 mg/kg to 10 mg/kg.
At 10 mg/kg, serum concentration appeared to reach a steady state by day 60 with a mean (range) trough concentration of 24 mcg/mL (1 to 66 mcg/mL). No systemic accumulation of abatacept occurred upon continued repeated treatment with 10 mg/kg at monthly intervals in RA patients. Population pharmacokinetic analyses in RA patients revealed that there was a trend toward higher clearance of abatacept with increasing body weight.
Age and gender (when corrected for body weight) did not affect clearance. Concomitant methotrexate, NSAIDs, corticosteroids, and TNF antagonists did not influence abatacept clearance. No formal studies were conducted to examine the effects of either renal or hepatic impairment on the pharmacokinetics of abatacept.
Adult RA - Subcutaneous Administration Abatacept exhibited linear pharmacokinetics following subcutaneous administration. The mean (range) for C min and C max at steady state observed after 85 days of treatment was 32.5 mcg/mL (6.6 to 113.8 mcg/mL) and 48.1 mcg/mL (9.8 to 132.4 mcg/mL), respectively. The bioavailability of abatacept following subcutaneous administration relative to intravenous administration was 79%.
Mean estimates for systemic clearance (0.28 mL/h/kg), volume of distribution (0.11 L/kg), and terminal half-life (14.3 days) were comparable between subcutaneous and intravenous administra… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Abatacept, a selective costimulation modulator, inhibits T-cell (T lymphocyte) activation by binding to CD80 and CD86, thereby blocking interaction with CD28. This interaction provides a costimulatory signal necessary for full activation of T lymphocytes. Activated T lymphocytes are implicated in the pathogenesis of RA, pJIA and PsA and are found in the synovium of patients with RA, pJIA and PsA.
In vitro , abatacept decreases T-cell proliferation and inhibits the production of the cytokines TNF alpha (TNFα), interferon-γ, and interleukin-2. In a rat collagen-induced arthritis model, abatacept suppresses inflammation, decreases anti-collagen antibody production, and reduces antigen specific production of interferon-γ. The relationship of these biological response markers to the mechanisms by which ORENCIA exerts its clinical effects is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING For Intravenous Infusion ORENCIA ® (abatacept) for injection is a white lyophilized powder for intravenous infusion after reconstitution and dilution. It is supplied as an individually packaged, single-dose vial (one may use less than the full contents of the vial or use more than one vial) with a silicone-free disposable syringe, providing 250 mg of abatacept: NDC 0003-2187-13: in a carton presentation For Subcutaneous Use ORENCIA ® (abatacept) injection and ORENCIA ® ClickJect (abatacept) injection are clear to slightly opalescent, colorless to pale yellow solutions for subcutaneous administration.
Prefilled Syringe ORENCIA (abatacept) injection, 50 mg/0.4 mL, 87.5 mg/0.7 mL, and 125 mg/mL, is supplied as single-dose disposable prefilled glass syringes with BD UltraSafe Passive™ needle guard and flange extenders. The Type I glass syringe has a coated stopper and fixed stainless steel needle (5 bevel, 29-gauge thin wall, ½-inch needle) covered with a rigid needle shield. The prefilled syringe provides ORENCIA in the following packages: NDC 0003-2814-11 (50 mg/0.4 mL): pack of 4 syringes with a passive needle safety guard NDC 0003-2818-11 (87.5 mg/0.7 mL): pack of 4 syringes with a passive needle safety guard NDC 0003-2188-11 (125 mg/mL): pack of 4 syringes with a passive needle safety guard ClickJect Autoinjector ORENCIA (abatacept) ClickJect, 125 mg/mL, is supplied as a single-dose disposable prefilled autoinjector.
The Type I glass syringe contained in the autoinjector has a coated stopper and fixed stainless steel needle (5 bevel, 27-gauge special thin wall, ½-inch needle) covered with a rigid needle shield. The autoinjector provides 125 mg of abatacept in 1 mL and is provided in the following package: NDC 0003-2188-51: pack of 4 autoinjectors Storage Refrigerate ORENCIA lyophilized powder supplied in a vial at 2°C to 8°C (36°F to 46°F). Do not use beyond the expiration date on the vial.
Protect the vials from light by storing in the original package until time of use. Refrigerate ORENCIA solution supplied in a prefilled syringe or ClickJect autoinjector at 2°C to 8°C (36°F to 46°F). Do not use beyond the expiration date on the prefilled syringe or autoinjector.
Protect from light by storing in the original package until time of use. Do not allow the prefilled syringe or autoinjector to freeze.
📦 Storage and Handling ▾
Storage Refrigerate ORENCIA lyophilized powder supplied in a vial at 2°C to 8°C (36°F to 46°F). Do not use beyond the expiration date on the vial. Protect the vials from light by storing in the original package until time of use.
Refrigerate ORENCIA solution supplied in a prefilled syringe or ClickJect autoinjector at 2°C to 8°C (36°F to 46°F). Do not use beyond the expiration date on the prefilled syringe or autoinjector. Protect from light by storing in the original package until time of use.
Do not allow the prefilled syringe or autoinjector to freeze.
📋 Description ▾
11 DESCRIPTION Abatacept is a selective T-cell costimulation modulator. Abatacept is a soluble fusion protein that consists of the extracellular domain of human cytotoxic T-lymphocyte-associated antigen 4 (CTLA-4) linked to the modified Fc (hinge, CH2, and CH3 domains) portion of human immunoglobulin G1 (IgG1). Abatacept is produced by recombinant DNA technology in a mammalian cell expression system.
The apparent molecular weight of abatacept is 92 kilodaltons. ORENCIA (abatacept) for injection is a sterile, white, preservative-free lyophilized powder for reconstitution and dilution prior to intravenous infusion. Following reconstitution of the lyophilized powder with 10 mL of Sterile Water for Injection, USP, the reconstituted solution of ORENCIA is clear, colorless to pale yellow, with a concentration of 25 mg/mL and with a pH range of 7.2 to 7.8.
Each single-dose vial of ORENCIA provides 250 mg abatacept, maltose (500 mg), monobasic sodium phosphate (17.2 mg), and sodium chloride (14.6 mg). ORENCIA (abatacept) injection is a sterile, preservative-free, clear to slightly opalescent, colorless to pale-yellow solution with a pH range of 6.8 to 7.4 for subcutaneous administration. ORENCIA injection is supplied as a single-dose prefilled syringe or as a single-dose ClickJect autoinjector (see Table 6).
Table 6: Contents of ORENCIA Subcutaneous Injection Presentation Active Ingredient Quantity and Volume Inactive Ingredient Content ORENCIA injection 50 mg/0.4 mL prefilled syringe 50 mg of abatacept in 0.4 mL of solution dibasic sodium phosphate anhydrous (0.335 mg) monobasic sodium phosphate monohydrate (0.114 mg) poloxamer 188 (3.2 mg) sucrose (68 mg) qs to 0.4 mL Water for Injection, USP ORENCIA injection 87.5 mg/0.7 mL prefilled syringe 87.5 mg of abatacept in 0.7 mL of solution dibasic sodium phosphate anhydrous (0.587 mg) monobasic sodium phosphate monohydrate (0.200 mg) poloxamer 188 (5.6 mg) sucrose (119 mg) qs to 0.7 mL Water for Injection, USP ORENCIA injection 125 mg/mL prefilled syringe and ClickJect autoinjector 125 mg of abatacept in 1 mL of solution dibasic sodium phosphate anhydrous (0.838 mg) monobasic sodium phosphate monohydrate (0.286 mg) poloxamer 188 (8 mg) sucrose (170 mg) qs to 1 mL Water for Injection, USP Unlike the lyophilized formulation for intravenous use, the ORENCIA solutions for subcutaneous administration contain no maltose.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Increased Risk of Infection with Concomitant Use With Immunosuppressants for RA Inform patients that the concomitant use with other immunosuppressives (e.g., biologic DMARDs, JAK inhibitors) is not recommended [see Warnings and Precautions (5.1) and Drug Interactions (7.1) ]. Hypersensitivity Reactions Instruct patients to immediately tell their healthcare professional if they experience symptoms of an allergic reaction on the day of administration or the day after ORENCIA administration [see Warnings and Precautions (5.2) ] .
Infections Inform patients that serious infections have been reported in patients receiving ORENCIA [see Warnings and Precautions (5.3) ] . Immunizations Inform patients that live vaccines should not be given concurrently with ORENCIA or within 3 months of its discontinuation [see Warnings and Precautions (5.4) ] . Blood Glucose Testing Maltose is contained in ORENCIA for intravenous administration and can give falsely elevated blood glucose readings with certain blood glucose monitors on the day of ORENCIA infusion.
Advise patients treated with intravenous ORENCIA who are using GDH-PQQ-based monitoring systems for glucose (e.g., diabetics) to consider using other methods for glucose monitoring. This recommendation is not applicable to patients treated with subcutaneous ORENCIA [see Drug Interactions (7.2) ] . Disposal of Prefilled Syringes and ClickJect Autoinjectors Advise patients to follow disposal instructions in the Instructions for Use.
A puncture-resistant container for disposal of needles and syringes should be used. Instruct patients that they will need to follow their community guidelines for the correct way to dispose of their sharps disposal container. Instruct patients not to recycle their used sharps disposal container.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Healthy Adults and Adult RA - Intravenous Administration The pharmacokinetics of abatacept were studied in healthy adult subjects after a single 10 mg/kg intravenous infusion and in RA patients after multiple 10 mg/kg intravenous infusions of ORENCIA (see Table 7). Table 7: Pharmacokinetic Parameters (Mean, Range) in Healthy Subjects and RA Patients After 10 mg/kg ORENCIA Intravenous Infusion(s) PK Parameter Healthy Subjects (After 10 mg/kg Single Dose) n=13 RA Patients (After 10 mg/kg Multiple Doses a ) n=14 a Multiple intravenous infusions of ORENCIA were administered at days 1, 15, 30, and monthly thereafter.
Peak Concentration (C max ) [mcg/mL] 292 (175-427) 295 (171-398) Terminal half-life (t 1/2 ) [days] 16.7 (12-23) 13.1 (8-25) Systemic clearance (CL) [mL/h/kg] 0.23 (0.16-0.30) 0.22 (0.13-0.47) Volume of distribution (Vss) [L/kg] 0.09 (0.06-0.13) 0.07 (0.02-0.13) The pharmacokinetics of abatacept in RA patients and healthy subjects appeared to be comparable. In RA patients, after multiple intravenous infusions, the pharmacokinetics of abatacept showed proportional increases of C max and AUC over the dose range of 2 mg/kg to 10 mg/kg.
At 10 mg/kg, serum concentration appeared to reach a steady state by day 60 with a mean (range) trough concentration of 24 mcg/mL (1 to 66 mcg/mL). No systemic accumulation of abatacept occurred upon continued repeated treatment with 10 mg/kg at monthly intervals in RA patients. Population pharmacokinetic analyses in RA patients revealed that there was a trend toward higher clearance of abatacept with increasing body weight.
Age and gender (when corrected for body weight) did not affect clearance. Concomitant methotrexate, NSAIDs, corticosteroids, and TNF antagonists did not influence abatacept clearance. No formal studies were conducted to examine the effects of either renal or hepatic impairment on the pharmacokinetics of abatacept.
Adult RA - Subcutaneous Administration Abatacept exhibited linear pharmacokinetics following subcutaneous administration. The mean (range) for C min and C max at steady state observed after 85 days of treatment was 32.5 mcg/mL (6.6 to 113.8 mcg/mL) and 48.1 mcg/mL (9.8 to 132.4 mcg/mL), respectively. The bioavailability of abatacept following subcutaneous administration relative to intravenous administration was 79%.
Mean estimates for systemic clearance (0.28 mL/h/kg), volume of distribution (0.11 L/kg), and terminal half-life (14.3 days) were comparable between subcutaneous and intravenous administration. Study SC-2 was conducted to determine the effect of subcutaneous monotherapy use of ORENCIA on immunogenicity (without an intravenous loading dose) in 100 RA patients [see Adverse Reactions (6.3) ] . In this study, a mean trough concentration of 12.6 mcg/mL was achieved after 2 weeks of dosing.
Consistent with the intravenous data, population pharmacokinetic analyses for subcutaneous ORENCIA in RA patients revealed that there was a trend toward higher clearance of abatacept with increasing body weight [see Dosage and Administration (2.1) ] . Age and gender (when corrected for body weight) did not affect apparent clearance. Concomitant medication, such as methotrexate, corticosteroids, and NSAIDs, did not influence abatacept apparent clearance.
Polyarticular Juvenile Idiopathic Arthritis - Intravenous Administration In Study JIA-1 among patients 6 to 17 years of age, the mean (range) steady state serum peak and trough concentrations of abatacept were 217 mcg/mL (57 to 700 mcg/mL) and 11.9 mcg/mL (0.15 to 44.6 mcg/mL) [see Clinical Studies (14.2)] . Population pharmacokinetic analyses of the serum concentration data showed that clearance of abatacept increased with baseline body weight [see Dosage and Administration (2.2) ] . The estimated mean (range) clearance of abatacept in the juvenile idiopathic arthritis patients was 0.4 mL/h/kg (0.20 to 1.12 mL/h/kg).
After accounting for the effect of body weight, the clearance of abatacept was… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In clinical trials with ORENCIA at doses approximating 10 mg/kg, decreases were observed in serum levels of soluble interleukin-2 receptor (sIL-2R), interleukin-6 (IL-6), rheumatoid factor (RF), C-reactive protein (CRP), matrix metalloproteinase-3 (MMP3), and TNFα. The relationship of these biological response markers to the mechanisms by which ORENCIA exerts its clinical effects is unknown. No formal pharmacodynamic analyses of biologic response markers have been performed in patients exposed to ORENCIA as prophylaxis for aGVHD.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Adult Rheumatoid Arthritis Description of Clinical Studies of Intravenous ORENCIA for the Treatment of Patients with RA The efficacy and safety of ORENCIA for intravenous administration were assessed in six randomized, double-blind, controlled studies (five placebo-controlled and one active-controlled) in patients ≥18 years of age with active RA diagnosed according to American College of Rheumatology (ACR) criteria. Studies I, II, III, IV, and VI required patients to have at least 12 tender and 10 swollen joints at randomization, and Study V did not require any specific number of tender or swollen joints.
ORENCIA or placebo treatment was given intravenously at weeks 0, 2, and 4 and then every 4 weeks thereafter in Studies I, II, III, IV, and VI. • Study I (NCT00279760) evaluated ORENCIA as monotherapy in 122 patients with active RA who had failed at least one non-biologic DMARD or etanercept. • In Study II (NCT00162266) and Study III (NCT00048568), the efficacy of ORENCIA were assessed in patients with an inadequate response to MTX and who were continued on their stable dose of MTX. • In Study IV (NCT00048581), the efficacy of ORENCIA was assessed in patients with an inadequate response to a TNF antagonist, with the TNF antagonist discontinued prior to randomization; other DMARDs were permitted. • Study V (NCT00048932) primarily assessed safety in patients with active RA requiring additional intervention in spite of current therapy with DMARDs; all DMARDs used at enrollment were continued.
Patients in Study V were not excluded for comorbid medical conditions. • In Study VI (NCT00122382), the efficacy and safety of ORENCIA were assessed in methotrexate-naive patients with RA of less than 2 years disease duration. In Study VI, patients previously naive to methotrexate were randomized to receive ORENCIA plus methotrexate or methotrexate plus placebo. Study I patients were randomized to receive one of three doses of ORENCIA (0.5, 2, or 10 mg/kg) or placebo ending at week 8.
Study II patients were randomized to receive ORENCIA 2 or 10 mg/kg or placebo for 12 months. Study III, IV, V, and VI patients were randomized to receive a dose of ORENCIA based on weight range or placebo for 12 months (Studies III, V, and VI) or 6 months (Study IV). The dose of ORENCIA was 500 mg for patients weighing less than 60 kg, 750 mg for patients weighing 60 to 100 kg, and 1,000 mg for patients weighing greater than 100 kg.
Description of Clinical Studies of Subcutaneous or Intravenous ORENCIA for the Treatment of Patients with Adult RA The efficacy of ORENCIA for subcutaneous administration were assessed in Study SC-1 (NCT00559585), which was a randomized, double-blind, double-dummy, non-inferiority study that compared ORENCIA administered subcutaneously to ORENCIA administered intravenously in 1457 patients with moderate to severely active RA, receiving background methotrexate (MTX), and experiencing an inadequate response to methotrexate (MTX-IR).
In Study SC-1, patients were randomized with stratification by body weight (<60 kg, 60 to 100 kg, >100 kg) to receive (1) ORENCIA 125 mg subcutaneous injections weekly, after a single intravenous loading dose of ORENCIA based on body weight or (2) ORENCIA intravenously on Days 1, 15, 29, and every four weeks thereafter. Subjects continued taking their current dose of MTX from the day of randomization. Clinical Response in Adult RA Patients The percent of ORENCIA-treated patients achieving ACR 20, 50, and 70 responses and major clinical response in Studies I, III, IV, and VI are shown in Table 9.
ORENCIA-treated patients had higher ACR 20, 50, and 70 response rates at 6 months compared to placebo-treated patients. Month 6 ACR response rates in Study II for the 10 mg/kg group were similar to the ORENCIA group in Study III. In Studies III and IV, improvement in the ACR 20 response rate versus placebo was observed within 15 days in some patients and within 29 days versus MTX in Study V… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a mouse carcinogenicity study, weekly subcutaneous injections of 20, 65, or 200 mg/kg of abatacept administered for up to 84 weeks in males and 88 weeks in females were associated with increases in the incidence of malignant lymphomas (all doses) and mammary gland tumors (intermediate- and high-dose in females). The mice from this study were infected with murine leukemia virus and mouse mammary tumor virus. These viruses are associated with an increased incidence of lymphomas and mammary gland tumors, respectively, in immunosuppressed mice.
The doses used in these studies produced exposures 0.8, 2.0, and 3.0 times higher, respectively, than the exposure associated with the maximum recommended human dose (MRHD) of 10 mg/kg based on AUC (area under the time-concentration curve). The relevance of these findings to the clinical use of ORENCIA is unknown. In a one-year toxicity study in cynomolgus monkeys, abatacept was administered intravenously once weekly at doses up to 50 mg/kg (producing 9 times the MRHD exposure based on AUC).
Abatacept was not associated with any significant drug-related toxicity. Reversible pharmacological effects consisted of minimal transient decreases in serum IgG and minimal to severe lymphoid depletion of germinal centers in the spleen and/or lymph nodes. No evidence of lymphomas or preneoplastic morphologic changes was observed, despite the presence of a virus (lymphocryptovirus) known to cause these lesions in immunosuppressed monkeys within the time frame of this study.
The relevance of these findings to the clinical use of ORENCIA is unknown. No mutagenic potential of abatacept was observed in the in vitro bacterial reverse mutation (Ames) or Chinese hamster ovary/hypoxanthine guanine phosphoribosyl-transferase (CHO/HGPRT) forward point mutation assays with or without metabolic activation, and no chromosomal aberrations were observed in human lymphocytes treated with abatacept with or without metabolic activation. Abatacept had no adverse effects on male or female fertility in rats at doses up to 200 mg/kg every three days (11 times the MRHD exposure based on AUC).
13.2Animal Toxicology and/or Pharmacology In studies of adult mice and monkeys, inhibition of TDAR was apparent. However, infection and mortality, altered T-helper cells, and inflammation of thyroid and pancreas were not observed.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a mouse carcinogenicity study, weekly subcutaneous injections of 20, 65, or 200 mg/kg of abatacept administered for up to 84 weeks in males and 88 weeks in females were associated with increases in the incidence of malignant lymphomas (all doses) and mammary gland tumors (intermediate- and high-dose in females). The mice from this study were infected with murine leukemia virus and mouse mammary tumor virus. These viruses are associated with an increased incidence of lymphomas and mammary gland tumors, respectively, in immunosuppressed mice.
The doses used in these studies produced exposures 0.8, 2.0, and 3.0 times higher, respectively, than the exposure associated with the maximum recommended human dose (MRHD) of 10 mg/kg based on AUC (area under the time-concentration curve). The relevance of these findings to the clinical use of ORENCIA is unknown. In a one-year toxicity study in cynomolgus monkeys, abatacept was administered intravenously once weekly at doses up to 50 mg/kg (producing 9 times the MRHD exposure based on AUC).
Abatacept was not associated with any significant drug-related toxicity. Reversible pharmacological effects consisted of minimal transient decreases in serum IgG and minimal to severe lymphoid depletion of germinal centers in the spleen and/or lymph nodes. No evidence of lymphomas or preneoplastic morphologic changes was observed, despite the presence of a virus (lymphocryptovirus) known to cause these lesions in immunosuppressed monkeys within the time frame of this study.
The relevance of these findings to the clinical use of ORENCIA is unknown. No mutagenic potential of abatacept was observed in the in vitro bacterial reverse mutation (Ames) or Chinese hamster ovary/hypoxanthine guanine phosphoribosyl-transferase (CHO/HGPRT) forward point mutation assays with or without metabolic activation, and no chromosomal aberrations were observed in human lymphocytes treated with abatacept with or without metabolic activation. Abatacept had no adverse effects on male or female fertility in rats at doses up to 200 mg/kg every three days (11 times the MRHD exposure based on AUC).
📄 Patient Package Insert ▾
PATIENT INFORMATION ORENCIA ® (oh-REN-see-ah) (abatacept) injection, for intravenous or subcutaneous use What is ORENCIA? ORENCIA is a prescription medicine that reduces signs and symptoms in: • adults with moderate to severe rheumatoid arthritis (RA), including those who have not been helped enough by other medicines for RA. ORENCIA may prevent further damage to your bones and joints and may help your ability to perform daily activities.
In adults, ORENCIA may be used alone or with other RA treatments other than tumor necrosis factor (TNF) antagonists. • people 2 years of age and older with moderate to severe polyarticular juvenile idiopathic arthritis (pJIA). ORENCIA may be used alone or with methotrexate. • people 2 years of age and older with active psoriatic arthritis (PsA). In adults, ORENCIA can be used alone or with other PsA treatments.
In children, ORENCIA can be used alone or with methotrexate. ORENCIA is also used for the preventative treatment of acute graft versus host disease (aGVHD), in combination with a calcineurin inhibitor and methotrexate, in: • people 2 years of age and older undergoing hematopoietic stem cell transplantation (HSCT) from a matched or 1 allele-mismatched unrelated-donor. It is not known if ORENCIA is safe and effective in children less than two years of age for the treatment of pJIA.
It is not known if ORENCIA is safe and effective in children less than two years of age for the treatment of PsA. It is not known if ORENCIA is safe and effective in children less than two years of age for the preventative treatment of aGVHD. Before you receive or use ORENCIA, tell your healthcare provider about all of your medical conditions, including if you: • have any kind of infection even if it is small (such as an open cut or sore), or an infection that is in your whole body (such as the flu).
If you have an infection during treatment with ORENCIA, you may have a higher chance for getting serious side effects. • have an infection that will not go away or an infection that keeps coming back. • are allergic to abatacept or any of the ingredients in ORENCIA. See the end of this Patient Information leaflet for a complete list of ingredients in ORENCIA. • have or have had inflammation of your liver due to an infection (viral hepatitis). Your healthcare provider may examine you for hepatitis before treatment with ORENCIA. • have had a lung infection called tuberculosis (TB), a positive skin test for TB, or you recently have been in close contact with someone who has had TB.
Your healthcare provider may examine you for TB or perform a skin test before treatment with ORENCIA. Symptoms of TB may include: o a cough that does not go away o weight loss o fever o night sweats • have a history of Epstein-Barr Virus (EBV) or Cytomegalovirus (CMV) in people receiving ORENCIA for preventative treatment of aGVHD during HSCT from an unrelated donor. • are scheduled to have surgery. • recently received a vaccination or are scheduled for a vaccination. • have a history of a breathing problem called chronic obstructive pulmonary disease (COPD). • have diabetes and use a blood glucose monitor to check your blood sugar (blood glucose) levels. o ORENCIA for intravenous infusion (given through a needle placed in a vein) contains maltose, a type of sugar, that can give false high blood sugar readings with certain types of blood glucose monitors on the day of ORENCIA infusion.
Your healthcare provider may tell you to use a different way to monitor your blood sugar levels. o ORENCIA for subcutaneous injection (injected under the skin) does not contain maltose. You do not need to change your blood sugar monitoring if you are using ORENCIA subcutaneously. • are pregnant or plan to become pregnant. It is not known if ORENCIA can harm your unborn baby.
If you took ORENCIA during pregnancy, talk to your healthcare provider before your baby receives any vaccines. • are breastfeeding or plan to breastfeed. It is not known if ORENCIA passe… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use ORENCIA ® (oh-REN-see-ah) (abatacept) Prefilled syringe with BD UltraSafe Passive ™ needle guard ORENCIA ® prefilled syringe with BD UltraSafe Passive ™ needle guard (abatacept) Injection Read these instructions before you start using your ORENCIA prefilled syringe and each time you get a refill. There may be new information. Before you use the prefilled syringe for the first time, make sure your healthcare provider shows you the right way to use it and decides that you or a caregiver may be able to give your injections of ORENCIA at home.
Important: • Keep the prefilled syringe in the refrigerator until ready to use. • Do not freeze. Before you begin: get to know your prefilled syringe There are 3 types of prefilled syringes: The type of prefilled syringe you receive depends on the dose prescribed by your healthcare provider. The 125 mg/mL prefilled syringe is shown below.
Before use After use The prefilled syringe has a flange extender that makes it easier to hold and inject, and a needle guard that automatically covers the needle after a complete injection. • Do not remove the needle cover until you are ready to inject. • Do not pull back on the plunger at any time. • Do not recap the prefilled syringe at any time, as this may damage, bend, or break the needle. Go to Step 1 Step 1: Preparing for an ORENCIA injection Gather and place supplies for your injection on a clean, flat surface.
Only the prefilled syringe is included in the package: Alcohol swab Prefilled syringe with UltraSafe Passive needle guard Adhesive bandage Sharps disposal container Cotton ball or gauze Let your prefilled syringe warm up. Remove 1 prefilled syringe from the refrigerator and wait 30 minutes to allow it to reach room temperature. • Do not speed up the warming process in any way, such as using the microwave or placing the syringe in warm water. • Do not remove the needle cover while allowing the prefilled syringe to reach room temperature.
Wash your hands well with soap and water. Go to Step 2 Step 2: Examine the prefilled syringe Hold the prefilled syringe by the body with the needle cover pointing down as shown. • Check the expiration date printed on the label. Do not use if the expiration date has passed. • Check the prefilled syringe for damage.
Do not use if it is cracked or broken. Check the Liquid. • Check the liquid in the prefilled syringe through the viewing window. It should be clear and colorless to pale yellow. • Do not inject if the liquid is cloudy, discolored, or has particles in it.
Note : the 50 mg prefilled syringe is shown. Note: It is normal to see an air bubble. Do not attempt to remove it.
Go to Step 3 Step 3: Check the dose on the prefilled syringe Hold the syringe at eye level. Look closely to make sure that the amount of liquid in the prefilled syringe is at or just above the fill line for your prescribed dose: Do not use if your prefilled syringe does not have the correct amount of liquid. Call your pharmacist immediately.
Go to Step 4 Step 4: Choose and prepare an injection site Choose your injection site. Choose your injection site in either the stomach (abdomen) , front of the thighs, or outer area of upper arm (only if caregiver administered). Rotate injection site. • Each week you can use the same area of your body but use a different injection site in that area. • Do not inject into an area where the skin is tender, bruised, red, scaly, or hard.
Do not give the injection in any areas with scars or stretch marks. • Record the date, time, and site where you inject. Gently clean injection site. • Wipe the injection site with an alcohol swab and let it air dry. • Do not touch the injection site again before giving the injection. • Do not fan or blow on the clean area. Remove the needle cover by holding the body of the prefilled syringe with one hand and pulling the cover straight off with your other hand.
Do not put the needle cover back on the needle after you remove it. Throw away the needle co… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
ORENCIA 250 mg/vial for Injection Representative Packaging See How Supplied section for a complete list of available packages of ORENCIA. Rx only NDC 0003-2187-13 ORENCIA ® (abatacept) Lyophilized Powder for IV Infusion 250 mg/vial ONLY USE THE SILICONE-FREE DISPOSABLE SYRINGE INCLUDED IN THE PACKAGE FOR RECONSTITUTION Bristol-Myers Squibb Company Princeton, New Jersey 08543 USA US License No. 1713 orencia-250mgvial
ORENCIA 50 mg/0.4 mL Injection Representative Packaging Bristol-Myers Squibb NDC 0003-2814-11 4 Single-Dose Prefilled Syringes with BD UltraSafe Passive™ Needle Guard ORENCIA® (abatacept) Injection 50 mg/0.4mL Single-Dose Prefilled Syringe with BD UltraSafe Passive™ Needle Guard FOR SUBCUTANEOUS USE ONLY WARNING: Keep out of reach of children Discard each syringe after use Rx only orencia-50mg-carton
ORENCIA 87.5 mg/0.7 mL Injection Representative Packaging Bristol-Myers Squibb NDC 0003-2818-11 4 Single-Dose Prefilled Syringes with BD UltraSafe Passive™ Needle Guard ORENCIA® (abatacept) Injection 87.5 mg/0.7mL Single-Dose Prefilled Syringe with BD UltraSafe Passive™ Needle Guard FOR SUBCUTANEOUS USE ONLY WARNING: Keep out of reach of children Discard each syringe after use Rx only orencia-87pt5mg-carton
ORENCIA 125 mg/mL Injection Representative Packaging Bristol-Myers Squibb NDC 0003-2188-11 4 Single-Dose Prefilled Syringes with BD UltraSafe Passive ™ Needle Guard ORENCIA ® (abatacept) Injection 125 mg/mL Single-Dose Prefilled Syringe with BD UltraSafe Passive ™ Needle Guard FOR SUBCUTANEOUS USE ONLY WARNING: Keep out of reach of children Discard each syringe after use Rx only orencia-125mg-carton
ORENCIA 125 mg/mL ClickJect Representative Packaging Bristol-Myers Squibb NDC 0003-2188-51 4 Single-Dose Prefilled Autoinjectors ORENCIA ® ClickJect ™ (abatacept) Injection 125 mg/mL Single-Dose Autoinjector FOR SUBCUTANEOUS USE ONLY Refrigerate immediately WARNING: Keep out of reach of children Discard each autoinjector after use Open from this side Rx only orencia-4ct-clickjet-carton