
Medrol methylprednisolone 4 mg Tablet, 21-count — NDC 0009-0056-04 (Billing 00009-0056-04)
This is a package of 21 tablets of Medrol methylprednisolone 4 mg Tablet from Pharmacia & Upjohn Company LLC, marketed since Oct 1957 and currently FDA-listed; retail pharmacies pay about $0.2911 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0009-0056-04 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0009 labeler · 0056 product · 04 package
- Package marketed since
- Oct 24, 1957
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 21 EA per package
- Barcode (UPC)
- 0300090056025, 0300090022013, 0300090073015, 0300090020019
- Medicaid fills, this package
- 111 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Methylprednisolone (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 045311
- GCN: 37499
- GPI-14 (Medi-Span): 22100030000310
- HICL (First Databank): 002877
- AHFS class code: 68:04.00.00
- RxCUI (RxNorm): 197969
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It is a steroid that calms inflammation and allergic reactions. Depending on the product, it is used for allergic conditions, skin diseases, adrenal gland problems, and (as tablets...
- Take the tablets by mouth exactly as your prescriber directs. The dose depends on your condition and how you respond. Your prescriber may lower it step by step. Injections are give...
- Steroids can increase appetite and weight, cause fluid retention, trouble sleeping, mood swings, acne, thin skin, and slower wound healing. Call your doctor if you notice signs of...
- If you have taken it for a long time, do not stop suddenly. Steroids can suppress your body’s own steroid production, so your prescriber will lower the dose gradually.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methylprednisolone — tap one for details:
Methylprednisolone may be associated with lower levels of 9 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.291 | $6.11 / 21 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4823 | $10.13 / 21 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3001 | $6.30 / 21 tablets |
| Medicare Part B allowsASP · J7509 | $0.160 / J7509 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00009-0056-02 0009-0056-02 | 100 TABLET in 1 BOTTLE | $0.2454 / ea | $24.54 | 1957-10-24 | — | Active |
| 00009-0056-04 You're viewing this Main listing | 1 DOSE PACK in 1 CARTON / 21 TABLET in 1 DOSE PACK | $0.2911 / ea | $6.11 | 1957-10-24 | — | Active |
Per ea, this pack runs about 19% above the cheapest pack (100-count, $0.2454 vs $0.2911 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00009-0056-02?
What NDC number is used to bill for this package of Medrol methylprednisolone 4 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| methylprednisolone 4 mg 00904-6914-61 | Major | 100 tablets | $0.121 | AB | Availability likely | save 58% |
| Methylprednisolone 4 mg 62135-0760-01 | Chartwell | 100 tablets | $0.121 | — | Availability likely | save 58% |
| Methylprednisolone 4 mg 68084-0149-01 | American | 100 tablets | $0.121 | AB | Availability likely | save 58% |
| methylprednisolone 4 mg 68382-0916-01 | Zydus | 100 tablets | $0.121 | AB | Availability likely | save 58% |
| Methylprednisolone 4 mg 42806-0400-01 | Epic | 100 tablets | $0.124 | AB | Availability likely | save 57% |
| MethylPREDNISolone 4 mg 00603-4593-15 | Par | 21 tablets | $0.136 | AB | Availability likely | save 53% |
| Methylprednisolone 4 mg 59762-4440-02 | Mylan | 21 tablets | $0.136 | AB | Availability likely | save 53% |
| methylprednisolone 4 mg 68001-0624-01 | BluePoint | 21 tablets | $0.136 | AB | Availability likely | save 53% |
| Medrol 4 mgthis 00009-0056-04 | Pharmacia | 21 tablets | $0.291 | AB | Availability likely | — |
| MethylPREDNISolone 4 mg 55289-0649-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 57582-0101-01 | Tianjin | 100 tablets | — | AB | FDA listed | — |
| MethylPREDNISolone 4 mg 63629-2218-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 68071-2370-01 | NuCare | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 68071-5221-01 | NuCare | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 69306-0400-21 | Doc | 21 tablets | — | AB | FDA listed | — |
| methylprednisolone 4 mg 70771-1348-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| MethylPREDNISolone 4 mg 72162-1161-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| methylprednisolone 4 mg 82804-0007-21 | Proficient | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 85509-1400-02 | PHOENIX | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 85766-0037-01 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 71205-0453-21 | Proficient | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 76420-0041-21 | Asclemed | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 76420-0193-21 | Asclemed | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 63187-0160-21 | Proficient | 21 tablets | — | AB | FDA listed | — |
| MethylPREDNISolone 4 mg 63629-2226-01 | Bryant | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 80425-0230-01 | Advanced | 21 tablets | — | AB | FDA listed | — |
| methylprednisolone 4 mg 50090-3811-00 | A-S | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 80425-0231-01 | Advanced | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 80425-0255-01 | Advanced | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 50090-3094-00 | A-S | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 72189-0264-21 | Direct_Rx | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 68788-7833-02 | Preferred | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 70518-2864-00 | REMEDYREPACK | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 60760-0961-21 | St. | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 70518-4213-00 | REMEDYREPACK | 21 tablets | — | AB | FDA listed | — |
| Methylprednisolone 4 mg 85534-0035-00 | HAWAII | 21 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Methylprednisolone inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Pharmacia & Upjohn Company LLC labeler code 00009
- Cortef hydrocortisone 20 mg Tablet NDC 0009-0044-01
- Parecoxib Sodium 40 mg Injection, Powder, For Solution NDC 0009-0046-01
- SOLU-MEDROL methylprednisolone sodium succinate 125 mg/2mL Injection, Powder, For Solution NDC 0009-0047-04
- Provera medroxyprogesterone acetate 10 mg Tablet NDC 0009-0051-01
- progesterone 1 kg/kg Powder NDC 0009-0052-01
- Xanax alprazolam .5 mg Tablet NDC 0009-0055-01
- Dinoprostone 1 kg/kg Powder NDC 0009-0058-01
- Methylprednisolone Hemisuccinate 1 kg/kg Powder NDC 0009-0062-01
- CLindamycin Palmitate 1 kg/kg Powder NDC 0009-0063-02
- Provera medroxyprogesterone acetate 2.5 mg Tablet NDC 0009-0065-01
- Medroxyprogesterone 1 kg/kg Powder NDC 0009-0067-01
- Hydrocortisone 1 kg/kg Powder NDC 0009-0069-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE MEDROL Tablets are indicated in the following conditions: 1. Endocrine Disorders Primary or secondary adrenocortical insufficiency (hydrocortisone or cortisone is the first choice; synthetic analogs may be used in conjunction with mineralocorticoids where applicable; in infancy mineralocorticoid supplementation is of particular importance). Congenital adrenal hyperplasia Nonsuppurative thyroiditis Hypercalcemia associated with cancer 2.
Rheumatic Disorders As adjunctive therapy for short-term administration (to tide the patient over an acute episode or exacerbation) in: Rheumatoid arthritis, including juvenile rheumatoid arthritis (selected cases may require low-dose maintenance therapy) Ankylosing spondylitis Acute and subacute bursitis Synovitis of osteoarthritis Acute nonspecific tenosynovitis Post-traumatic osteoarthritis Psoriatic arthritis Epicondylitis Acute gouty arthritis 3. Collagen Diseases During an exacerbation or as maintenance therapy in selected cases of: Systemic lupus erythematosus Systemic dermatomyositis (polymyositis) Acute rheumatic carditis 4.
Dermatologic Diseases Bullous dermatitis herpetiformis Severe erythema multiforme (Stevens-Johnson syndrome) Severe seborrheic dermatitis Exfoliative dermatitis Mycosis fungoides Pemphigus Severe psoriasis 5. Allergic States Control of severe or incapacitating allergic conditions intractable to adequate trials of conventional treatment: Seasonal or perennial allergic rhinitis Drug hypersensitivity reactions Serum sickness Contact dermatitis Bronchial asthma Atopic dermatitis 6. Ophthalmic Diseases Severe acute and chronic allergic and inflammatory processes involving the eye and its adnexa such as: Allergic corneal marginal ulcers Herpes zoster ophthalmicus Anterior segment inflammation Diffuse posterior uveitis and choroiditis Sympathetic ophthalmia Keratitis Optic neuritis Allergic conjunctivitis Chorioretinitis Iritis and iridocyclitis 7.
Respiratory Diseases Symptomatic sarcoidosis Berylliosis Loeffler's syndrome not manageable by other means Fulminating or disseminated pulmonary tuberculosis when used concurrently with appropriate antituberculous chemotherapy Aspiration pneumonitis 8. Hematologic Disorders Idiopathic thrombocytopenic purpura in adults Secondary thrombocytopenia in adults Acquired (autoimmune) hemolytic anemia Erythroblastopenia (RBC anemia) Congenital (erythroid) hypoplastic anemia 9. Neoplastic Diseases For palliative management of: Leukemias and lymphomas in adults Acute leukemia of childhood 10.
Edematous States To induce a diuresis or remission of proteinuria in the nephrotic syndrome, without uremia, of the idiopathic type or that due to lupus erythematosus. 11. Gastrointestinal Diseases To tide the patient over a critical period of the disease in: Ulcerative colitis Regional enteritis 12.
Nervous System Acute exacerbations of multiple sclerosis 13. Miscellaneous Tuberculous meningitis with subarachnoid block or impending block when used concurrently with appropriate antituberculous chemotherapy. Trichinosis with neurologic or myocardial involvement.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The initial dosage of MEDROL Tablets may vary from 4 mg to 48 mg of methylprednisolone per day depending on the specific disease entity being treated. In situations of less severity lower doses will generally suffice while in selected patients higher initial doses may be required. The initial dosage should be maintained or adjusted until a satisfactory response is noted.
If after a reasonable period of time there is a lack of satisfactory clinical response, MEDROL should be discontinued and the patient transferred to other appropriate therapy. IT SHOULD BE EMPHASIZED THAT DOSAGE REQUIREMENTS ARE VARIABLE AND MUST BE INDIVIDUALIZED ON THE BASIS OF THE DISEASE UNDER TREATMENT AND THE RESPONSE OF THE PATIENT . After a favorable response is noted, the proper maintenance dosage should be determined by decreasing the initial drug dosage in small decrements at appropriate time intervals until the lowest dosage which will maintain an adequate clinical response is reached.
It should be kept in mind that constant monitoring is needed in regard to drug dosage. Included in the situations which may make dosage adjustments necessary are changes in clinical status secondary to remissions or exacerbations in the disease process, the patient's individual drug responsiveness, and the effect of patient exposure to stressful situations not directly related to the disease entity under treatment; in this latter situation it may be necessary to increase the dosage of MEDROL for a period of time consistent with the patient's condition.
If after long-term therapy the drug is to be stopped, it is recommended that it be withdrawn gradually rather than abruptly. Multiple Sclerosis: In treatment of acute exacerbations of multiple sclerosis daily doses of 200 mg of prednisolone for a week followed by 80 mg every other day for 1 month have been shown to be effective (4 mg of methylprednisolone is equivalent to 5 mg of prednisolone). ADT ® (Alternate Day Therapy): Alternate day therapy is a corticosteroid dosing regimen in which twice the usual daily dose of corticoid is administered every other morning.
The purpose of this mode of therapy is to provide the patient requiring long-term pharmacologic dose treatment with the beneficial effects of corticoids while minimizing certain undesirable effects, including pituitary-adrenal suppression, the Cushingoid state, corticoid withdrawal symptoms, and growth suppression in children. The rationale for this treatment schedule is based on two major premises: (a) the anti-inflammatory or therapeutic effect of corticoids persists longer than their physical presence and metabolic effects and (b) administration of the corticosteroid every other morning allows for reestablishment of more nearly normal hypothalamic-pituitary-adrenal (HPA) activity on the off-steroid day.
A brief review of the HPA physiology may be helpful in understanding this rationale. Acting primarily through the hypothalamus a fall in free cortisol stimulates the pituitary gland to produce increasing amounts of corticotropin (ACTH) while a rise in free cortisol inhibits ACTH secretion. Normally the HPA system is characterized by diurnal (circadian) rhythm.
Serum levels of ACTH rise from a low point about 10 pm to a peak level about 6 am. Increasing levels of ACTH stimulate adrenal cortical activity resulting in a rise in plasma cortisol with maximal levels occurring between 2 am and 8 am. This rise in cortisol dampens ACTH production and in turn adrenal cortical activity.
There is a gradual fall in plasma corticoids during the day with lowest levels occurring about midnight. The diurnal rhythm of the HPA axis is lost in Cushing's disease, a syndrome of adrenal cortical hyperfunction characterized by obesity with centripetal fat distribution, thinning of the skin with easy bruisability, muscle wasting with weakness, hypertension, latent diabetes, osteoporosis, electrolyte imbalance, etc. The same clinical findings of hyperadren… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Systemic fungal infections and known hypersensitivity to components.
⚠️ Warnings ▾
WARNINGS In patients on corticosteroid therapy subjected to unusual stress, increased dosage of rapidly acting corticosteroids before, during, and after the stressful situation is indicated. Immunosuppression and Increased Risk of Infection Corticosteroids, including MEDROL, suppress the immune system and increase the risk of infection with any pathogen, including viral, bacterial, fungal, protozoan, or helminthic pathogens. Corticosteroids can: • Reduce resistance to new infections • Exacerbate existing infections • Increase the risk of disseminated infections • Increase the risk of reactivation or exacerbation of latent infections • Mask some signs of infection Corticosteroid-associated infections can be mild but can be severe and at times fatal.
The rate of infectious complications increases with increasing corticosteroid dosages. Monitor for the development of infection and consider MEDROL withdrawal or dosage reduction as needed. Tuberculosis If MEDROL is used to treat a condition in patients with latent tuberculosis or tuberculin reactivity, reactivation of tuberculosis may occur.
Closely monitor such patients for reactivation. During prolonged MEDROL therapy, patients with latent tuberculosis or tuberculin reactivity should receive chemoprophylaxis. Varicella Zoster and Measles Viral Infections Varicella and measles can have a serious or even fatal course in non-immune patients taking corticosteroids, including MEDROL.
In corticosteroid-treated patients who have not had these diseases or are non-immune, particular care should be taken to avoid exposure to varicella and measles: • If a MEDROL-treated patient is exposed to varicella, prophylaxis with varicella zoster immune globulin may be indicated. If varicella develops, treatment with antiviral agents may be considered. • If a MEDROL-treated patient is exposed to measles, prophylaxis with immunoglobulin may be indicated. Hepatitis B Virus Reactivation Hepatitis B virus reactivation can occur in patients who are hepatitis B carriers treated with immunosuppressive dosages of corticosteroids, including MEDROL.
Reactivation can also occur infrequently in corticosteroid-treated patients who appear to have resolved hepatitis B infection. Screen patients for hepatitis B infection before initiating immunosuppressive (e.g., prolonged) treatment with MEDROL. For patients who show evidence of hepatitis B infection, recommend consultation with physicians with expertise in managing hepatitis B regarding monitoring and consideration for hepatitis B antiviral therapy.
Fungal Infections Corticosteroids, including MEDROL, may exacerbate systemic fungal infections; therefore, avoid MEDROL use in the presence of such infections unless MEDROL is needed to control drug reactions. For patients on chronic MEDROL therapy who develop systemic fungal infections, MEDROL withdrawal or dosage reduction is recommended. Amebiasis Corticosteroids, including MEDROL, may activate latent amebiasis.
Therefore, it is recommended that latent amebiasis or active amebiasis be ruled out before initiating MEDROL in patients who have spent time in the tropics or patients with unexplained diarrhea. Strongyloides Infestation Corticosteroids, including MEDROL, should be used with great care in patients with known or suspected Strongyloides (threadworm) infestation. In such patients, corticosteroid-induced immunosuppression may lead to Strongyloides hyperinfection and dissemination with widespread larval migration, often accompanied by severe enterocolitis and potentially fatal gram-negative septicemia.
Cerebral Malaria Avoid corticosteroids, including MEDROL, in patients with cerebral malaria. Ophthalmic Effects Prolonged use of corticosteroids may produce posterior subcapsular cataracts, glaucoma with possible damage to the optic nerves, and may enhance the establishment of secondary ocular infections due to fungi or viruses. Kaposi’s Sarcoma Kaposi’s sarcoma has been reported to occur in patients receiving corti… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Fluid and Electrolyte Disturbances • Sodium retention • Congestive heart failure in susceptible patients • Hypertension • Fluid retention • Potassium loss • Hypokalemic alkalosis Musculoskeletal • Muscle weakness • Loss of muscle mass • Steroid myopathy • Osteoporosis • Tendon rupture, particularly of the Achilles tendon • Vertebral compression fractures • Aseptic necrosis of femoral and humeral heads • Pathologic fracture of long bones Gastrointestinal • Peptic ulcer with possible perforation and hemorrhage • Pancreatitis • Abdominal distention • Ulcerative esophagitis Increases in alanine transaminase (ALT, SGPT), aspartate transaminase (AST, SGOT), and alkaline phosphatase have been observed following corticosteroid treatment.
These changes are usually small, not associated with any clinical syndrome and are reversible upon discontinuation. Dermatologic • Impaired wound healing • Petechiae and ecchymoses • May suppress reactions to skin tests • Thin fragile skin • Facial erythema • Increased sweating Neurological • Increased intracranial pressure with papilledema (pseudo-tumor cerebri) usually after treatment • Convulsions • Vertigo • Headache Endocrine • Development of Cushingoid state • Suppression of growth in children • Secondary adrenocortical and pituitary unresponsiveness, particularly in times of stress, as in trauma, surgery or illness • Menstrual irregularities • Decreased carbohydrate tolerance • Manifestations of latent diabetes mellitus • Increased requirements of insulin or oral hypoglycemic agents in diabetics Ophthalmic • Posterior subcapsular cataracts • Increased intraocular pressure • Glaucoma • Exophthalmos Metabolic • Negative nitrogen balance due to protein catabolism Vascular • Flushing The following additional reactions have been reported following oral as well as parenteral therapy: Urticaria and other allergic, anaphylactic or hypersensitivity reactions.
🔄 Drug Interactions ▾
DRUG INTERACTIONS The pharmacokinetic interactions listed below are potentially clinically important. Mutual inhibition of metabolism occurs with concurrent use of cyclosporin and methylprednisolone; therefore, it is possible that adverse events associated with the individual use of either drug may be more apt to occur. Convulsions have been reported with concurrent use of methylprednisolone and cyclosporin.
Drugs that induce hepatic enzymes such as phenobarbital, phenytoin and rifampin may increase the clearance of methylprednisolone and may require increases in methylprednisolone dose to achieve the desired response. Drugs such as troleandomycin and ketoconazole may inhibit the metabolism of methylprednisolone and thus decrease its clearance. Therefore, the dose of methylprednisolone should be titrated to avoid steroid toxicity.
Methylprednisolone may increase the clearance of chronic high dose aspirin. This could lead to decreased salicylate serum levels or increase the risk of salicylate toxicity when methylprednisolone is withdrawn. Aspirin should be used cautiously in conjunction with corticosteroids in patients suffering from hypoprothrombinemia.
The effect of methylprednisolone on oral anticoagulants is variable. There are reports of enhanced as well as diminished effects of anticoagulant when given concurrently with corticosteroids. Therefore, coagulation indices should be monitored to maintain the desired anticoagulant effect.
🤰 Pregnancy ▾
Usage in Pregnancy Since adequate human reproduction studies have not been done with corticosteroids, the use of these drugs in pregnancy, nursing mothers or women of child-bearing potential requires that the possible benefits of the drug be weighed against the potential hazards to the mother and embryo or fetus. Infants born of mothers who have received substantial doses of corticosteroids during pregnancy, should be carefully observed for signs of hypoadrenalism.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED MEDROL Tablets are available in the following strengths and package sizes: 2 mg (white, elliptical, scored, imprinted MEDROL 2) Bottles of 100 NDC 0009-0020-01 4 mg (white, elliptical, scored, imprinted MEDROL 4) Bottles of 100 NDC 0009-0056-02 DOSEPAK ™ Unit of Use (21 tablets) NDC 0009-0056-04 8 mg (white, elliptical, scored, imprinted MEDROL 8) Bottles of 25 NDC 0009-0022-01 16 mg (white, elliptical, scored, imprinted MEDROL 16) Bottles of 50 NDC 0009-0073-01 32 mg (white, elliptical, scored, imprinted MEDROL 32) Bottles of 25 NDC 0009-0176-01 Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP].
📦 Storage and Handling ▾
Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP].
📋 Description ▾
DESCRIPTION MEDROL Tablets contain methylprednisolone which is a glucocorticoid. Glucocorticoids are adrenocortical steroids, both naturally occurring and synthetic, which are readily absorbed from the gastrointestinal tract. Methylprednisolone occurs as a white to practically white, odorless, crystalline powder.
It is sparingly soluble in alcohol, in dioxane, and in methanol, slightly soluble in acetone, and in chloroform, and very slightly soluble in ether. It is practically insoluble in water. The chemical name for methylprednisolone is pregna-1,4-diene-3,20-dione, 11,17,21-trihydroxy-6-methyl-, (6α,11β)-and the molecular weight is 374.48.
The structural formula is represented below: Each MEDROL Tablet for oral administration contains 2 mg, 4 mg, 8 mg, 16 mg or 32 mg of methylprednisolone. Inactive ingredients: 2 mg 4 mg and 8 mg Calcium Stearate Calcium Stearate Corn Starch Corn Starch Lactose Lactose Mineral Oil Sucrose Sorbic Acid Sucrose 16 mg and 32 mg Calcium Stearate Corn Starch Lactose Mineral Oil Sucrose ACTIONS Naturally occurring glucocorticoids (hydrocortisone and cortisone), which also have salt-retaining properties, are used as replacement therapy in adrenocortical deficiency states.
Their synthetic analogs are primarily used for their potent anti-inflammatory effects in disorders of many organ systems. Glucocorticoids cause profound and varied metabolic effects. In addition, they modify the body's immune responses to diverse stimuli.
Chemical Structure
💬 Information for Patients ▾
Information for the Patient Persons who are on immunosuppressant doses of corticosteroids should be warned to avoid exposure to chickenpox or measles. Patients should also be advised that if they are exposed, medical advice should be sought without delay.
⚠️ Precautions ▾
PRECAUTIONS General Precautions Drug-induced secondary adrenocortical insufficiency may be minimized by gradual reduction of dosage. This type of relative insufficiency may persist for months after discontinuation of therapy; therefore, in any situation of stress occurring during that period, hormone therapy should be reinstituted. Since mineralocorticoid secretion may be impaired, salt and/or a mineralocorticoid should be administered concurrently.
There is an enhanced effect of corticosteroids on patients with hypothyroidism and in those with cirrhosis. Corticosteroids should be used cautiously in patients with ocular herpes simplex because of possible corneal perforation. The lowest possible dose of corticosteroid should be used to control the condition under treatment, and when reduction in dosage is possible, the reduction should be gradual.
Psychic derangements may appear when corticosteroids are used, ranging from euphoria, insomnia, mood swings, personality changes, and severe depression, to frank psychotic manifestations. Also, existing emotional instability or psychotic tendencies may be aggravated by corticosteroids. Caution is required in patients with systemic sclerosis because an increased incidence of scleroderma renal crisis has been observed with corticosteroids, including methylprednisolone.
Steroids should be used with caution in nonspecific ulcerative colitis, if there is a probability of impending perforation, abscess or other pyogenic infection; diverticulitis; fresh intestinal anastomoses; active or latent peptic ulcer; renal insufficiency; hypertension; osteoporosis; and myasthenia gravis. Growth and development of infants and children on prolonged corticosteroid therapy should be carefully observed. Although controlled clinical trials have shown corticosteroids to be effective in speeding the resolution of acute exacerbations of multiple sclerosis, they do not show that corticosteroids affect the ultimate outcome or natural history of the disease.
The studies do show that relatively high doses of corticosteroids are necessary to demonstrate a significant effect. (See DOSAGE AND ADMINISTRATION .) Since complications of treatment with glucocorticoids are dependent on the size of the dose and the duration of treatment, a risk/benefit decision must be made in each individual case as to dose and duration of treatment and as to whether daily or intermittent therapy should be used. In post marketing experience, tumor lysis syndrome (TLS) has been reported in patients with malignancies, including hematological malignancies and solid tumors, following the use of systemic corticosteroids alone or in combination with other chemotherapeutic agents.
Patients at high risk of TLS, such as patients with tumors that have a high proliferative rate, high tumor burden and high sensitivity to cytotoxic agents, should be monitored closely and appropriate precautions should be taken. DRUG INTERACTIONS The pharmacokinetic interactions listed below are potentially clinically important. Mutual inhibition of metabolism occurs with concurrent use of cyclosporin and methylprednisolone; therefore, it is possible that adverse events associated with the individual use of either drug may be more apt to occur.
Convulsions have been reported with concurrent use of methylprednisolone and cyclosporin. Drugs that induce hepatic enzymes such as phenobarbital, phenytoin and rifampin may increase the clearance of methylprednisolone and may require increases in methylprednisolone dose to achieve the desired response. Drugs such as troleandomycin and ketoconazole may inhibit the metabolism of methylprednisolone and thus decrease its clearance.
Therefore, the dose of methylprednisolone should be titrated to avoid steroid toxicity. Methylprednisolone may increase the clearance of chronic high dose aspirin. This could lead to decreased salicylate serum levels or increase the risk of salicylate toxicity when methylprednisolone is withdrawn.
Aspirin… [Excerpted — this section continues on DailyMed.]
📚 References ▾
REFERENCES 1 Fekety R. Infections associated with corticosteroids and immunosuppressive therapy. In: Gorbach SL, Bartlett JG, Blacklow NR, eds. Infectious Diseases . Philadelphia: WBSaunders Company 1992:1050–1. 2 Stuck AE, Minder CE, Frey FJ. Risk of infectious complications in patients taking glucocorticoids. Rev Infect Dis 1989:11(6):954–63.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 4 mg Tablet Bottle Label Pfizer NDC 0009-0056-02 Medrol ® methylprednisolone tablets, USP 4 mg 100 Tablets Rx only Distributed by Pharmacia & Upjohn Company LLC A Subsidiary of Pfizer Inc. New York, NY 10007 PRINCIPAL DISPLAY PANEL - 4 mg Tablet Bottle Label
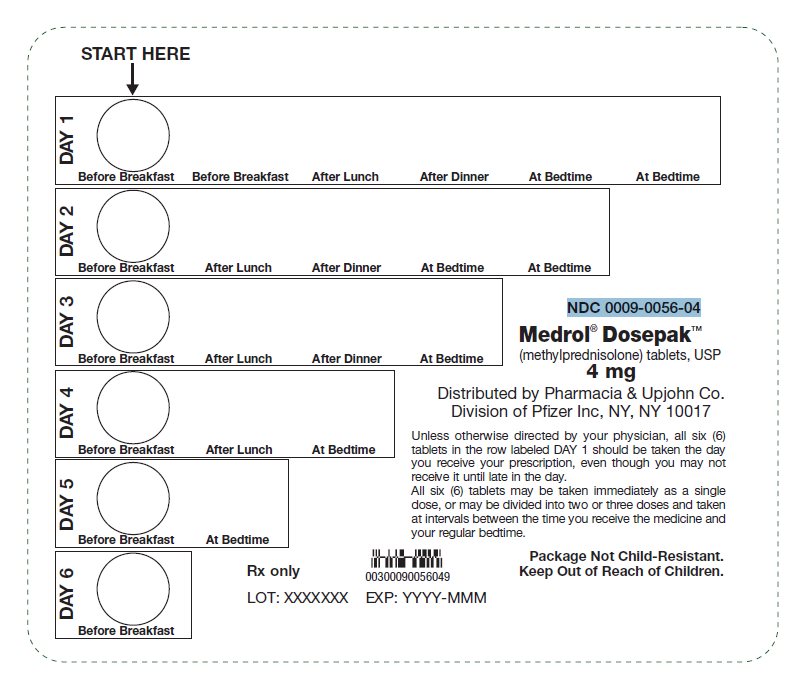
PRINCIPAL DISPLAY PANEL - 4 mg Tablet Dose Pack START HERE DAY 1 Before Breakfast Before Breakfast After Lunch After Dinner At Bedtime At Bedtime DAY 2 Before Breakfast After Lunch After Dinner At Bedtime At Bedtime DAY 3 Before Breakfast After Lunch After Dinner At Bedtime DAY 4 Before Breakfast After Lunch At Bedtime DAY 5 Before Breakfast At Bedtime DAY 6 Before Breakfast NDC 0009-0056-04 Medrol ® Dosepak™ (methylprednisolone) tablets, USP 4 mg Distributed by Pharmacia & Upjohn Company LLC, A subsidiary of Pfizer Inc., New York, NY 10001 Unless otherwise directed by your physician, all six (6) tablets in the row labeled DAY 1 should be taken the day you receive your prescription, even though you may not receive it until late in the day.
All six (6) tablets may be taken immediately as a single dose, or may be divided into two or three doses and taken at intervals between the time you receive the medicine and your regular bedtime. Rx only Package Not Child-Resistant. Keep Out of Reach of Children.
LOT: XXXXXXX EXP: YYYY-MMM PRINCIPAL DISPLAY PANEL - 4 mg Tablet Dose Pack
PRINCIPAL DISPLAY PANEL - 4 mg Tablet Dose Pack Carton NDC 0009-0056-04 Pfizer Medrol ® Dosepak™ 4 mg (methylprednisolone) tablets, USP Unit of Use One blister containing 21 tablets Rx only PRINCIPAL DISPLAY PANEL - 4 mg Tablet Dose Pack Carton
PRINCIPAL DISPLAY PANEL - 8 mg Tablet Bottle Label Pfizer NDC 0009-0022-01 Medrol ® methylprednisolone tablets, USP 8 mg 25 Tablets Rx only Distributed by Pharmacia & Upjohn Company LLC A Subsidiary of Pfizer Inc. New York, NY 10001 PRINCIPAL DISPLAY PANEL - 8 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 16 mg Tablet Bottle Label Pfizer NDC 0009-0073-01 Medrol ® methylprednisolone tablets, USP 16 mg 50 Tablets Rx only Distributed by Pharmacia & Upjohn Company LLC A Subsidiary of Pfizer Inc. New York, NY 10001 PRINCIPAL DISPLAY PANEL - 16 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 32 mg Tablet Bottle Label Pfizer NDC 0009-0176-01 Medrol ® methylprednisolone tablets, USP 32 mg 25 Tablets Rx only Distributed by Pharmacia & Upjohn Co Division of Pfizer Inc, NY, NY 10017 Principal Display Panel - 32 mg Bottle Tablet Label
PRINCIPAL DISPLAY PANEL - 2 mg Tablet Bottle Label Pfizer NDC 0009-0020-01 Medrol ® methylprednisolone tablets, USP 2 mg 100 Tablets Rx only Distributed by Pharmacia & Upjohn Company LLC A Subsidiary of Pfizer Inc. New York, NY 10001 PRINCIPAL DISPLAY PANEL - 2 mg Tablet Bottle Label