
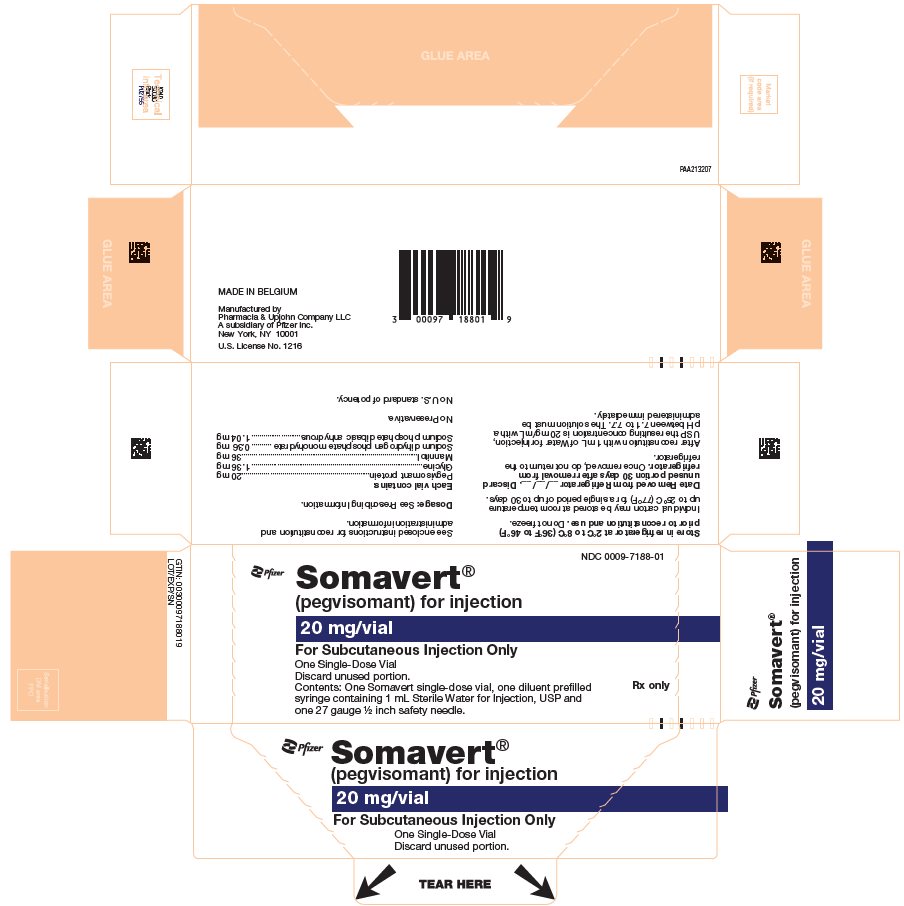
SOMAVERT pegvisomant Kit
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Growth Hormone Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Acromegaly happens when your body makes too much growth hormone for too long — it can cause bones, hands, feet, and facial features to enlarge, and it raises the risk of other heal...
- What exactly is acromegaly, and why do I need this medication?
- Before you start injecting at home, your healthcare team will train you on the technique. Each day, you'll mix the powder with the provided sterile water, swirl gently (never shake...
- How do I give myself this injection at home?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $615.24 | — |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Somavertthis 00009-7188-01 | Pharmacia | 1 kit | — | — | FDA listed | — |
| Somavert 00009-7166-01 | Pharmacia | 1 kit | — | — | FDA listed | — |
| Somavert 00009-7199-01 | Pharmacia | 1 kit | — | — | FDA listed | — |
| Somavert 00009-7200-01 | Pharmacia | 1 kit | — | — | FDA listed | — |
| Somavert 00009-7168-01 | Pharmacia | 1 kit | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00009-7188-01 You're viewing this | 1 KIT in 1 CARTON (0009-7188-01) * 1 mL in 1 VIAL, SINGLE-DOSE (0009-5179-02) * 1 mL in 1 SYRINGE (0009-5936-01) | 2016-10-01 | Active |
| 00009-7188-30 | 30 KIT in 1 CARTON (0009-7188-30) / 1 KIT in 1 KIT * 1 mL in 1 VIAL, SINGLE-DOSE (0009-5179-02) * 1 mL in 1 SYRINGE (0009-5936-01) | 2022-01-17 | Active |
Pack size FAQ
What quantity is in NDC 00009-7188-01?
What NDC number is used to bill for this package of SOMAVERT pegvisomant Kit?
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SOMAVERT is indicated for the treatment of acromegaly in patients who have had an inadequate response to surgery or radiation therapy, or for whom these therapies are not appropriate. The goal of treatment is to normalize serum insulin-like growth factor-1 (IGF-1) levels. SOMAVERT is a growth hormone receptor antagonist indicated for the treatment of acromegaly in patients who have had an inadequate response to surgery or radiation therapy, or for whom these therapies are not appropriate.
The goal of treatment is to normalize serum insulin-like growth factor-1 (IGF-1) levels. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Administer a 40 mg loading dose subcutaneously under physician supervision. ( 2.1 ) • After proper injection instruction, on day after loading dose, patients or caregivers begin daily subcutaneous injections of 10 mg. ( 2.1 ) • Adjust dosage in 5 mg increments or decrements until serum IGF-1 concentrations are maintained within age-adjusted normal range.
Do not adjust dosage based on growth hormone (GH) levels or signs or symptoms of acromegaly. ( 2.1 ) • Dosage range is 10 mg to 30 mg once daily. ( 2.1 ) • Perform liver tests prior to first dosage and if greater than 3 times upper limit of normal should work-up prior to SOMAVERT administration.
( 2.2 ) • Follow reconstitution and injection procedures. ( 2.3 , 2.4 )
2.1Dosage Information The recommended loading dose of SOMAVERT is 40 mg given subcutaneously, under healthcare provider supervision. Provide proper training in subcutaneous injection technique to patients or their caregivers so they can receive once daily subcutaneous injections. On the next day following the loading dose, instruct patients or their caregivers to begin daily subcutaneous injections of 10 mg of SOMAVERT.
Titrate the dosage to normalize serum IGF-1 concentrations (serum IGF-1 concentrations should be measured every four to six weeks). The dosage should not be based on growth hormone (GH) concentrations or signs and symptoms of acromegaly. It is unknown whether patients who remain symptomatic while achieving normalized IGF-1 concentrations would benefit from increased SOMAVERT dosage. • Increase the dosage by 5 mg increments every 4–6 weeks if IGF-1 concentrations are elevated. • Decrease the dosage by 5 mg decrements every 4–6 weeks if IGF-1 concentrations are below the normal range. • IGF-1 levels should also be monitored when a SOMAVERT dose given in multiple injections is converted to a single daily injection [see Clinical Pharmacology (12) ] .
The recommended dosage range is between 10 mg to 30 mg given subcutaneously once daily and the maximum daily dosage is 30 mg given subcutaneously once daily.
2.2Assess Liver Tests Prior to Initiation of SOMAVERT Prior to the start of SOMAVERT, patients should have an assessment of baseline levels of liver tests [serum alanine aminotransferase (ALT), aspartate aminotransferase (AST), serum total bilirubin (TBIL), and alkaline phosphatase (ALP)]. For recommendations regarding initiation of SOMAVERT based on baseline liver tests and recommendations for monitoring of liver tests while on SOMAVERT, refer to Table 1 in Warning and Precautions (5.2) .
2.3Loading Dose Injection Procedure The following instructions are for the healthcare provider to reconstitute and prepare the 40 mg loading dose. The healthcare provider will need to reconstitute 2 vials of lyophilized powder of SOMAVERT each containing 20 mg of pegvisomant with supplied diluent [two vials of lyophilized powder and two syringes containing 1 mL of diluent (Sterile Water for Injection, USP) will be needed for the 40 mg loading dose]. The healthcare provider will also need to inject the reconstituted SOMAVERT solution twice into the patient's upper arm, upper thigh, abdomen, or buttocks (each injection in a different area). a) Before administering the loading dose, remove 1 vial of lyophilized powder of SOMAVERT containing 20 mg of pegvisomant and one syringe containing 1 mL of diluent from the refrigerator, if refrigerated, about 10 minutes prior to the planned injection time. b) Reconstitute the first 20 mg vial of lyophilized powder of SOMAVERT containing 20 mg of pegvisomant with diluent.
When using the diluent in the syringe, inject the contents of the syringe slowly onto the sides of the vial containing lyophilized powder of SOMAVERT. Do not inject the diluent directly on the powder. c) Do not invert the vial or shake the solution as this may cause denaturation of the pegvisomant protein. Slowly swirl the solution to ensure that all of the lyophilized powder has g…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For injection: 10 mg, 15 mg, 20 mg, 25 mg or 30 mg white lyophilized powder in a single-dose vial for reconstitution supplied with a prefilled syringe containing 1 mL of diluent (Sterile Water for Injection, USP). For injection: 10 mg, 15 mg, 20 mg, 25 mg or 30 mg lyophilized powder in a single-dose vial for reconstitution supplied with a prefilled syringe containing 1 mL of diluent (Sterile Water for Injection, USP). ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypoglycemia : Monitor blood glucose in patients with diabetes mellitus and reduce anti-diabetic drug therapy as necessary. ( 5.1 ) • Liver Toxicity: Should have more frequent liver tests and/or discontinue SOMAVERT. ( 5.2 ) • Systemic Hypersensitivity : Monitor closely when re-initiating SOMAVERT in patients with systemic hypersensitivity. ( 5.5 )
5.1Hypoglycemia Associated With GH Lowering in Patients With Diabetes Mellitus GH opposes the effects of insulin on carbohydrate metabolism by decreasing insulin sensitivity; thus, glucose tolerance may improve in some patients treated with SOMAVERT. Patients should be carefully monitored and doses of anti-diabetic drugs reduced as necessary to avoid hypoglycemia in patients with diabetes mellitus.
5.2Liver Toxicity Baseline serum alanine aminotransferase (ALT), aspartate aminotransferase (AST), serum total bilirubin (TBIL), and alkaline phosphatase (ALP) levels should be obtained prior to initiating therapy with SOMAVERT. Table 1 lists recommendations regarding initiation of treatment with SOMAVERT, based on the results of these liver tests (LTs). Asymptomatic, transient elevations in transaminases up to 15 times ULN have been observed in <2% of subjects among two open-label trials (with a total of 147 patients).
These reports were not associated with an increase in bilirubin. Transaminase elevations normalized with time, most often after suspending treatment. Postmarketing reports have identified elevations in serum hepatic transaminases up to greater than 20 times ULN associated with elevation in total bilirubin greater than 2 times ULN.
In many of these cases, discontinuation of SOMAVERT therapy resulted in improvement or resolution of hepatic laboratory abnormalities. SOMAVERT should be used in accordance with the information presented in Table 2 with respect to liver test abnormalities while on SOMAVERT treatment. Table 1.
Recommendations of Initiating SOMAVERT Based on Baseline LTs and Periodic Monitoring of LTs During SOMAVERT Treatment Baseline LT Levels Recommendations Normal • May treat with SOMAVERT. • Monitor LTs at monthly intervals during the first 6 months of treatment, quarterly for the next 6 months and then bi-annually for the next year. Elevated, but less than or equal to 3 times ULN May treat with SOMAVERT; however, monitor LTs monthly for at least one year after initiation of therapy and then bi-annually for the next year.
Greater than 3 times ULN • Do not treat with SOMAVERT until a comprehensive workup establishes the cause of the patient's liver dysfunction. • Determine if cholelithiasis or choledocholithiasis is present, particularly in patients with a history of prior therapy with somatostatin analogs. • Based on the workup, consider initiation of therapy with SOMAVERT. • If the decision is to treat, LTs and clinical symptoms should be monitored very closely. If a patient develops LT elevations, or any other signs or symptoms of liver dysfunction while receiving SOMAVERT, the following patient management is recommended (Table 2).
Table 2. Clinical Recommendations Based on Liver Test Results While on SOMAVERT LT Levels and Clinical Signs/Symptoms Recommendations Greater than or equal to 3 but less than 5 times ULN (without signs/symptoms of hepatitis or other liver injury, or increase in serum TBIL) • May continue therapy with SOMAVERT. However, monitor LTs weekly to determine if further increases occur (see below). • Perform a comprehensive hepatic workup to discern if an alternative cause of liver dysfunction is present.
At least 5 times ULN, or transaminase elevations at least 3 times ULN associated with any increase in serum TBIL (with or without signs/symptoms of hepatitis or other liver injury) • Discontinue SOMAVERT immediately. • Perform a comprehensive hepatic workup, including serial LTs, to determine if and when serum levels return to normal. • If LTs normalize (regardless of whether an alternative cause of the live…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Clinically significant adverse reactions that appear in other section of the labeling include: • Hypoglycemia Associated with GH Lowering in Patients with Diabetes Mellitus [see Warnings and Precautions (5.1) ] • Liver Toxicity [see Warnings and Precautions (5.2) ] • Cross-Reactivity with GH Assays [see Warnings and Precautions (5.3) ] • Lipohypertrophy [see Warnings and Precautions (5.4) ] • Systemic Hypersensitivity [see Warnings and Precautions (5.5) ] Elevations of serum concentrations of ALT and AST greater than ten times the ULN were reported in two patients (0.8%) exposed to SOMAVERT in pre-approval clinical studies.
One patient was rechallenged with SOMAVERT, and the recurrence of elevated transaminase levels suggested a probable causal relationship between administration of the drug and the elevation in liver enzymes. A liver biopsy performed on the second patient was consistent with chronic hepatitis of unknown etiology. In both patients, the transaminase elevations normalized after discontinuation of the drug.
Elevations in ALT and AST levels were not associated with increased levels of TBIL and ALP, with the exception of two patients with minimal associated increases in ALP levels (i.e., less than 3 times ULN). The transaminase elevations did not appear to be related to the dose of SOMAVERT administered, generally occurred within 4 to 12 weeks of initiation of therapy, and were not associated with any identifiable biochemical, phenotypic, or genetic predictors. Most common reported adverse reactions (>6%) are infection, pain, nausea, diarrhea, abnormal liver tests, flu syndrome, injection site reaction.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In a 12-week randomized, placebo-controlled, double-blind, fixed-dose study of SOMAVERT in subjects with acromegaly, 32 subjects received placebo and 80 subjects received SOMAVERT once daily [see Clinical Studies (14) ] . A total of 108 subjects (30 placebo, 78 SOMAVERT) completed 12 weeks of study treatment.
Overall, eight patients with acromegaly (5.3%) withdrew from pre-marketing clinical studies because of adverse events, including two patients with marked transaminase elevations, one patient with lipohypertrophy at the injection sites, and one patient with substantial weight gain. Most adverse events did not appear to be dose-dependent. Table 3 shows the incidence of adverse events that were reported in at least two patients treated with SOMAVERT and at frequencies greater than placebo during the 12-week, placebo-controlled study.
Table 3. Adverse Reactions in a 12-week Placebo-Controlled Study in Patients with Acromegaly Table includes only those events that were reported in at least 2 patients and at a higher incidence in patients treated with SOMAVERT than in patients treated with placebo. Placebo n=32 SOMAVERT 10 mg/day n=26 15 mg/day n=26 20 mg/day N=28 Infection The 6 events coded as "infection" in the group treated with SOMAVERT 10 mg were reported as cold symptoms (3), upper respiratory infection (1), blister (1), and ear infection (1).
The 2 events in the placebo group were reported as cold symptoms (1) and chest infection (1). 2 (6%) 6 (23%) 0 0 Pain 2 (6%) 2 (8%) 1 (4%) 4 (14%) Nausea 1 (3%) 0 2 (8%) 4 (14%) Diarrhea 1 (3%) 1 (4%) 0 4 (14%) Abnormal liver function tests 1 (3%) 3 (12%) 1 (4%) 1 (4%) Flu syndrome 0 1 (4%) 3 (12%) 2 (7%) Injection site reaction 0 2 (8%) 1 (4%) 3 (11%) Dizziness 2 (6%) 2 (8%) 1 (4%) 1 (4%) Accidental injury 1 (3%) 2 (8%) 1 (4%) 0 Back pain 1 (3%) 2 (8%) 0 1 (4%) Sinusitis 1 (3%) 2 (8%) 0 1 (4%) Chest pain 0 1 (4%) 2 (8%) 0 Periphe…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Insulin and/or Oral hypoglycemic Agents: Patients with acromegaly and with diabetes mellitus may require careful monitoring and dose reductions of insulin and/or oral hypoglycemic agents. ( 5.2 , 7.1 ) • Opioids: Patients on opioids may need higher SOMAVERT doses to achieve appropriate IGF-1 suppression. ( 7.2 )
7.1Insulin and/or Oral Hypoglycemic Agents After initiation of SOMAVERT, patients with acromegaly and diabetes mellitus treated with insulin and/or oral hypoglycemic agents may require dose reductions of insulin and/or oral hypoglycemic agents [see Warnings and Precautions (5.1) ] .
7.2Opioids In clinical studies, patients taking opioids often needed higher SOMAVERT doses to normalize IGF-1 concentrations compared with patients not receiving opioids. The mechanism of this interaction is not known.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and Males of Reproductive Potential: Advise premenopausal females of the potential for an unintended pregnancy. ( 8.3 )
8.1Pregnancy Risk Summary Postmarketing reports of SOMAVERT use in pregnant women are insufficient to establish a drug-associated risk for major birth defects, miscarriage or adverse maternal or fetal outcomes. Acromegaly may improve during pregnancy (see Clinical Considerations ) . In animal reproduction studies, fetotoxicity was observed at a dose that was 6 times the maximum recommended human dose based on body surface area following subcutaneous administration of pegvisomant during organogenesis or during the preimplantation period (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Disease-associated maternal and/or embryofetal risk Published data from case reports, case series, and a small interventional study in pregnant women with acromegaly have demonstrated that acromegaly may improve or stabilize without treatment during pregnancy, particularly if acromegaly is treated before pregnancy.
In rare cases, acromegaly may worsen during pregnancy. Since IGF-1 levels may change physiologically during pregnancy and interpreting IGF-1 and growth hormone levels in pregnant women with acromegaly may be unreliable, clinical monitoring is recommended. Data Animal Data The effects of pegvisomant on early embryonic development and embryo-fetal development were evaluated in two separate studies, which were conducted in pregnant rabbits with pegvisomant at subcutaneous doses of 1, 3, and 10 mg/kg/day.
There was no evidence of teratogenic effects associated with pegvisomant administration during organogenesis. At the 10-mg/kg/day dose (6 times the maximum human therapeutic dose based on body surface area), a reproducible, slight increase in post-implantation loss was observed in both studies.
8.2Lactation Risk Summary Limited information from a case report in published literature reported that the level of pegvisomant in human milk was below the level of detection. There is no information available on the effects of the drug on the breastfed infant or the effects of the drug on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for SOMAVERT and any potential adverse effects on the breastfed child from SOMAVERT or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Discuss the potential for unintended pregnancy with premenopausal women as the therapeutic benefits of a reduction in growth hormone (GH) levels and normalization of insulin-like growth factor 1 (IGF-1) concentration in acromegalic females treated with pegvisomant may lead to improved fertility.
8.4Pediatric Use The safety and effectiveness of SOMAVERT in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of SOMAVERT did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8.6Renal Impairment SOMAVERT was not studied in patients with renal impairment and the safety and efficacy in these patients is not known.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Postmarketing reports of SOMAVERT use in pregnant women are insufficient to establish a drug-associated risk for major birth defects, miscarriage or adverse maternal or fetal outcomes. Acromegaly may improve during pregnancy (see Clinical Considerations ) . In animal reproduction studies, fetotoxicity was observed at a dose that was 6 times the maximum recommended human dose based on body surface area following subcutaneous administration of pegvisomant during organogenesis or during the preimplantation period (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Disease-associated maternal and/or embryofetal risk Published data from case reports, case series, and a small interventional study in pregnant women with acromegaly have demonstrated that acromegaly may improve or stabilize without treatment during pregnancy, particularly if acromegaly is treated before pregnancy.
In rare cases, acromegaly may worsen during pregnancy. Since IGF-1 levels may change physiologically during pregnancy and interpreting IGF-1 and growth hormone levels in pregnant women with acromegaly may be unreliable, clinical monitoring is recommended. Data Animal Data The effects of pegvisomant on early embryonic development and embryo-fetal development were evaluated in two separate studies, which were conducted in pregnant rabbits with pegvisomant at subcutaneous doses of 1, 3, and 10 mg/kg/day.
There was no evidence of teratogenic effects associated with pegvisomant administration during organogenesis. At the 10-mg/kg/day dose (6 times the maximum human therapeutic dose based on body surface area), a reproducible, slight increase in post-implantation loss was observed in both studies.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of SOMAVERT in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of SOMAVERT did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE In one reported incident of acute overdose with SOMAVERT during pre-marketing clinical studies, a patient self-administered 80 mg/day (2.7 times the maximum recommended maintenance dosage) for seven days. The patient experienced a slight increase in fatigue, had no other complaints, and demonstrated no significant clinical laboratory abnormalities. In cases of overdose, administration of SOMAVERT should be discontinued and not resumed until IGF-1 levels return to within or above the normal range.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Pegvisomant selectively binds to growth hormone (GH) receptors on cell surfaces, where it blocks the binding of endogenous GH, and thus interferes with GH signal transduction. Inhibition of GH action results in decreased serum concentrations of IGF-1, as well as other GH-responsive serum proteins such as free IGF-1, the acid-labile subunit of IGF-1 (ALS), and insulin-like growth factor binding protein-3 (IGFBP-3).
12.2Pharmacodynamics Pegvisomant binds selectively to the GH receptor, and does not cross-react with 19 other cytokine receptors tested, including prolactin. Pegvisomant leads to decreased serum concentrations of IGF-1, free IGF-1, ALS, and IGFBP-3 [see Clinical Studies (14, Figure 1) ] .
12.3Pharmacokinetics Absorption: Following subcutaneous administration, peak serum pegvisomant concentrations are not generally attained until 33 to 77 hours after administration. The mean extent of absorption of a 20-mg subcutaneous dose was 57%, relative to a 10-mg intravenous dose. Distribution: The mean apparent volume of distribution of pegvisomant is 7 L (12% coefficient of variation), suggesting that pegvisomant does not distribute extensively into tissues.
After a single subcutaneous administration, exposure (C max , AUC) to pegvisomant increases disproportionately with increasing dose. Mean ± SEM serum pegvisomant concentrations after 12 weeks of therapy with daily doses of 10, 15, and 20 mg were 6600 ± 1330; 16,000 ± 2200; and 27,000 ± 3100 ng/mL, respectively. The relative bioavailability of 1 × 30 mg pegvisomant was compared to 2 × 15 mg pegvisomant in a single-dose study.
The AUC inf and C max of pegvisomant when administered as one injection of 30 mg strength was approximately 6% and 4% greater, respectively, as compared to when administered as two injections of 15 mg strengths. Metabolism and Elimination: The pegvisomant molecule contains covalently bound polyethylene glycol polymers in order to reduce the clearance rate. Clearance of pegvisomant following multiple doses is lower than seen following a single-dose.
The mean total body systemic clearance of pegvisomant following multiple doses is estimated to range between 36 to 28 mL/h for subcutaneous doses ranging from 10 to 20 mg/day, respectively. Clearance of pegvisomant was found to increase with body weight. Pegvisomant is eliminated from serum with a mean half-life estimates ranging from 60 to 138 hours following either single or multiple doses.
Less than 1% of administered drug is recovered in the urine over 96 hours. The elimination route of pegvisomant has not been studied in humans. Drug Interaction Studies In clinical studies, patients on opioids often needed higher serum pegvisomant concentrations to achieve appropriate IGF-1 suppression compared with patients not receiving opioids.
The mechanism of this interaction is not known [see Drug Interactions (7.2) ] . Specific Populations No pharmacokinetic studies have been conducted in patients with renal impairment, patients with hepatic impairment, geriatric patients, or pediatric patients and the effects of race on the pharmacokinetics of pegvisomant has not been studied. No gender effect on the pharmacokinetics of pegvisomant was found in a population pharmacokinetic analysis.
12.6Immunogenicity The observed incidence of anti-drug antibodies is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of anti-drug antibodies in the studies described below with the incidence of anti-drug antibodies in other studies, including those of SOMAVERT or other growth hormone analogs. In pre-marketing clinical studies, approximately 17% of the SOMAVERT-treated patients developed low titer, non‑neutralizing anti-GH antibodies.
Although the presence of these antibodies did not appear to impact the efficacy of SOMAVERT, the long term clinical significance of these antibodies is not…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Pegvisomant selectively binds to growth hormone (GH) receptors on cell surfaces, where it blocks the binding of endogenous GH, and thus interferes with GH signal transduction. Inhibition of GH action results in decreased serum concentrations of IGF-1, as well as other GH-responsive serum proteins such as free IGF-1, the acid-labile subunit of IGF-1 (ALS), and insulin-like growth factor binding protein-3 (IGFBP-3).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SOMAVERT (pegvisomant) for injection is a white lyophilized powder supplied in the following strengths and package configurations: One Day Package Configuration Strength NDC Description 10 mg per vial 0009-7166-01 One single-dose vial with one prefilled syringe containing 1 mL of diluent (Sterile Water for Injection, USP) and a separate 27 -gauge ½ inch safety needle per carton 15 mg per vial 0009-7168-01 20 mg per vial 0009-7188-01 25 mg per vial 0009-7199-01 30 mg per vial 0009-7200-01 30-Day Package Configuration Strength NDC Description 10 mg per vial 0009-7166-30 Each outer carton contains three intermediate cartons, 30 prefilled syringes containing 1 mL of diluent (Sterile Water for Injection, USP), and 30 separate 27-gauge ½ inch safety needles.
Each intermediate carton contains ten single-dose vials of Somavert. 15 mg per vial 0009-7168-30 20 mg per vial 0009-7188-30 25 mg per vial 0009-7199-30 30 mg per vial 0009-7200-30 Storage Prior to reconstitution: • The One Day Package of SOMAVERT should be stored in a refrigerator at 2°C to 8°C (36°F to 46°F). • For the 30-Day Package, remove the three intermediate cartons containing the SOMAVERT vials and store in a refrigerator at 2°C to 8°C (36°F to 46°F). • For convenience, the One Day Package and intermediate cartons in the 30-Day Package containing the SOMAVERT vial(s), may be stored at room temperature up to 25°C (77°F) for a single period of up to 30 days. o In the space provided on the carton, record the date when the carton was removed from the refrigerator and the discard date (30 days after removal from the refrigerator). o Once the carton has been stored at room temperature, it should not be placed back into the refrigerator.
If not used within 30 days at room temperature, the vial(s) should be discarded. Discard the SOMAVERT vial(s) after the expiration date printed on the carton or the discard date, whichever is sooner. The prefilled syringe(s) may be stored at a temperature up to 30°C (86°F) until the expiration date printed on the carton, at which point they should be discarded.
Do not freeze.
📦 Storage and Handling ▾
Storage Prior to reconstitution: • The One Day Package of SOMAVERT should be stored in a refrigerator at 2°C to 8°C (36°F to 46°F). • For the 30-Day Package, remove the three intermediate cartons containing the SOMAVERT vials and store in a refrigerator at 2°C to 8°C (36°F to 46°F). • For convenience, the One Day Package and intermediate cartons in the 30-Day Package containing the SOMAVERT vial(s), may be stored at room temperature up to 25°C (77°F) for a single period of up to 30 days. o In the space provided on the carton, record the date when the carton was removed from the refrigerator and the discard date (30 days after removal from the refrigerator). o Once the carton has been stored at room temperature, it should not be placed back into the refrigerator.
If not used within 30 days at room temperature, the vial(s) should be discarded. Discard the SOMAVERT vial(s) after the expiration date printed on the carton or the discard date, whichever is sooner. The prefilled syringe(s) may be stored at a temperature up to 30°C (86°F) until the expiration date printed on the carton, at which point they should be discarded.
Do not freeze.
📋 Description ▾
11 DESCRIPTION Pegvisomant is an analog of human growth hormone (GH) of recombinant DNA origin that acts as a GH receptor antagonist. It contains 191 amino acid residues. The molecular weight of pegvisomant is 22 kDa.
The molecular weight of the PEG portion of pegvisomant is approximately 5 kDa. The predominant molecular weights of pegvisomant are thus approximately 42, 47, and 52 kDa. The schematic shows the amino acid sequence of the pegvisomant protein (PEG polymers are shown attached to the 5 most probable attachment sites).
Pegvisomant is synthesized by a specific strain of Escherichia coli bacteria that has been genetically modified by the addition of a plasmid that carries a gene for GH receptor antagonist. Stippled residues indicate PEG attachment sites (Phe 1 , Lys 38 , Lys 41 , Lys 70 , Lys 115 , Lys 120 , Lys 140 , Lys 145 , Lys 158 ) Shown below are the amino acid substitutions in pegvisomant, relative to human GH. hGH Pegvisomant His 18 Asp 18 Ala 21 Asn 21 Gly 120 Lys 120 Arg 167 Asn 167 Lys 168 Ala 168 Asp 171 Ser 171 Lys 172 Arg 172 Glu 174 Ser 174 Ile 179 Thr 179 SOMAVERT (pegvisomant) for injection is a sterile, white lyophilized powder intended for subcutaneous injection after reconstitution.
SOMAVERT is supplied in packages that include a single-dose prefilled syringe containing 1 mL of Sterile Water for Injection, USP, that is a sterile, nonpyrogenic preparation of water for injection that contains no bacteriostat, antimicrobial agent, or added buffer, to be used as a diluent. SOMAVERT is available in single-dose sterile vials containing 10 mg, 15 mg, 20 mg, 25 mg or 30 mg of pegvisomant. SOMAVERT 10 mg, 15 mg, and 20 mg vials also contain glycine (1.36 mg), mannitol (36 mg), sodium dihydrogen phosphate monohydrate (0.36 mg), and sodium phosphate dibasic anhydrous (1.04 mg).
After reconstitution with 1 mL of Water for Injection, USP, the resulting concentration is 10 mg/mL, 15 mg/mL and 20 mg/mL, respectively, with a pH of 7.1 – 7.7. SOMAVERT 25 mg vial also contains glycine (1.7 mg), mannitol (45 mg), sodium dihydrogen phosphate monohydrate (0.45 mg), and sodium phosphate dibasic anhydrous (1.3 mg). After reconstitution with 1 mL of Water for Injection, USP, the resulting concentration is 25 mg/mL with a pH of 7.1 – 7.7.
SOMAVERT 30 mg vial also contains glycine (2.04 mg), mannitol (54 mg), sodium dihydrogen phosphate monohydrate (0.54 mg), and sodium phosphate dibasic anhydrous (1.56 mg). After reconstitution with 1 mL of Water for Injection, USP, the resulting concentration is 30 mg/mL with a pH of 7.1 – 7.7. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Inform patients (and/or their caregivers) of the following information to aid in the safe and effective use of SOMAVERT: • Not to use SOMAVERT if they are allergic to SOMAVERT or anything in it. • They will need blood testing to check IGF-1 levels and liver tests before and during treatment with SOMAVERT and that the dose of SOMAVERT may be changed based on the results of these tests. • SOMAVERT has not been studied in pregnant women and instruct them to notify their healthcare provider as soon as they are aware that they are pregnant. • It is not known whether SOMAVERT is excreted in human milk and instruct them to notify their healthcare provider if they plan to do so. • Pregnancy: Inform female patients that treatment with SOMAVERT may result in unintended pregnancy [see Females and Males of Reproductive Potential (8.3) ].
Advise patients (and/or their caregivers) of the following adverse reactions: • The most common reported adverse reactions are injection site reaction, elevations of liver tests, pain, nausea, and diarrhea. • If they have liver test elevations they may need to have more frequent liver tests and/or discontinue SOMAVERT. Instruct patients to immediately discontinue therapy and contact their physician if they become jaundiced. • GH-secreting tumors may enlarge in people with acromegaly and that these tumors need to be watched carefully and monitored by MRI imaging. • Thickening under the skin may occur at the injection site that could lead to lumps and that switching sites may prevent or lessen this. • If they have diabetes mellitus, they may require careful monitoring and dose reductions of insulin and/or oral hypoglycemic agents while on SOMAVERT. • If they take opioids, they may need higher SOMAVERT doses to achieve appropriate IGF-1 suppression.
Inform patients (and/or their caregivers) about the storage options prior to reconstitution of the product [see How Supplied/Storage and Handling (16) ] . Advise patients to follow the directions for reconstitution provided in the Instructions for Use. Include that spraying the diluent directly onto the powder may cause foaming and that shaking may induce denaturation (destruction) of the active ingredient (therefore do not shake ).
U.S. License No. 1216 This product's labeling may have been updated.
For the most recent prescribing information, please visit www.pfizer.com . LAB-0782-4.0 Logo