
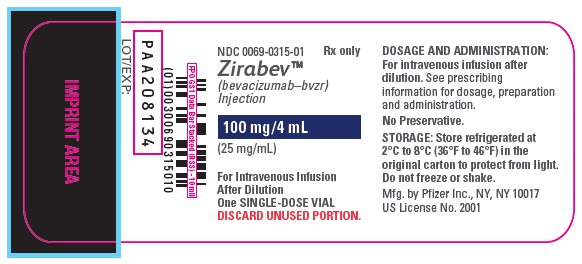
Zirabev bevacizumab-bvzr 100 mg/4mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vascular Endothelial Growth Factor Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Bevacizumab injection products are used to treat a variety of solid tumors. This includes certain lung, kidney, liver, brain, colon, rectal, female reproductive organ or peritoneal (tissue that lines the abdomen) cancers. Bevacizumab injection products are in a class of medications called antiangiogenic agents. They work by stopping the formation of blood vessels that bring oxygen and nutrients to tumors. This may slow the growth and spread of tumors.
Read the full MedlinePlus article ↗- Bevacizumab works by blocking a protein called VEGF, which tumors use to grow new blood vessels. Without that blood supply, the tumor has a harder time getting the nutrients it nee...
- What exactly does bevacizumab do, and why am I getting it?
- Bevacizumab is given through an IV — directly into a vein — by a nurse or infusion specialist at a clinic or cancer center. Your first infusion runs slowly over 90 minutes so the t...
- How is it given, and how long does each infusion take?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.2 mg / 4 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
0.8 mg / 4 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
9.4 mg / 4 mL
UNII AB6MNQ6J6L
Succinic acid is an organic acid derived from natural sources or chemical synthesis. In medications, it functions as a buffer to help maintain the proper pH level and may also serve as a preservative or flavor enhancer in formulations.
-
340 mg / 4 mL
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $68.23 | $272.91 / 4 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · Q5118 | $25.889 / Q5118 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Zirabev 100 mg/4mLthis 00069-0315-01 | Pfizer | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
6 biosimilars are FDA-licensed for this reference biologic — see the list below. (Biologics have no small-molecule generics.)
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Jun 27, 2031 |
Is there a biosimilar for ZIRABEV 100 MG/4 ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00069-0315-01 You're viewing this | 1 VIAL, SINGLE-USE in 1 CARTON (0069-0315-01) / 4 mL in 1 VIAL, SINGLE-USE | 2020-01-13 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ZIRABEV is a vascular endothelial growth factor inhibitor indicated for the treatment of: • Metastatic colorectal cancer, in combination with intravenous fluorouracil-based chemotherapy for first- or second-line treatment. ( 1.1 ) • Metastatic colorectal cancer, in combination with fluoropyrimidine-irinotecan- or fluoropyrimidine-oxaliplatin-based chemotherapy for second-line treatment in patients who have progressed on a first-line bevacizumab product-containing regimen. ( 1.1 ) Limitations of Use : ZIRABEV is not indicated for adjuvant treatment of colon cancer.
( 1.1 ) • Unresectable, locally advanced, recurrent or metastatic non-squamous non-small cell lung cancer, in combination with carboplatin and paclitaxel for first-line treatment. ( 1.2 ) • Recurrent glioblastoma in adults. ( 1.3 ) • Metastatic renal cell carcinoma in combination with interferon alfa.
( 1.4 ) • Persistent, recurrent, or metastatic cervical cancer, in combination with paclitaxel and cisplatin or paclitaxel and topotecan. ( 1.5 ) • Epithelial ovarian, fallopian tube, or primary peritoneal cancer: o in combination with carboplatin and paclitaxel, followed by ZIRABEV as a single agent, for stage III or IV disease following initial surgical resection. ( 1.6 ) o in combination with paclitaxel, pegylated liposomal doxorubicin, or topotecan for platinum-resistant recurrent disease who received no more than 2 prior chemotherapy regimens.
( 1.6 ) o in combination with carboplatin and paclitaxel or carboplatin and gemcitabine, followed by ZIRABEV as a single agent, for platinum-sensitive recurrent disease. ( 1.6 )
1.1Metastatic Colorectal Cancer ZIRABEV, in combination with intravenous fluorouracil-based chemotherapy, is indicated for the first- or second-line treatment of patients with metastatic colorectal cancer (mCRC). ZIRABEV, in combination with fluoropyrimidine-irinotecan- or fluoropyrimidine-oxaliplatin-based chemotherapy, is indicated for the second-line treatment of patients with mCRC who have progressed on a first-line bevacizumab product-containing regimen. Limitations of Use: ZIRABEV is not indicated for adjuvant treatment of colon cancer [see Clinical Studies (14.2) ].
1.2First-Line Non-Squamous Non-Small Cell Lung Cancer ZIRABEV, in combination with carboplatin and paclitaxel, is indicated for the first-line treatment of patients with unresectable, locally advanced, recurrent or metastatic non–squamous non–small cell lung cancer (NSCLC).
1.3Recurrent Glioblastoma ZIRABEV is indicated for the treatment of recurrent glioblastoma (GBM) in adults.
1.4Metastatic Renal Cell Carcinoma ZIRABEV, in combination with interferon alfa, is indicated for the treatment of metastatic renal cell carcinoma (mRCC).
1.5Persistent, Recurrent, or Metastatic Cervical Cancer ZIRABEV, in combination with paclitaxel and cisplatin or paclitaxel and topotecan, is indicated for the treatment of patients with persistent, recurrent, or metastatic cervical cancer.
1.6Epithelial Ovarian, Fallopian Tube, or Primary Peritoneal Cancer ZIRABEV, in combination with carboplatin and paclitaxel, followed by ZIRABEV as a single agent, is indicated for the treatment of patients with stage III or IV epithelial ovarian, fallopian tube, or primary peritoneal cancer following initial surgical resection. ZIRABEV, in combination with paclitaxel, pegylated liposomal doxorubicin, or topotecan, is indicated for the treatment of patients with platinum-resistant recurrent epithelial ovarian, fallopian tube, or primary peritoneal cancer who received no more than 2 prior chemotherapy regimens.
ZIRABEV, in combination with carboplatin and paclitaxel, or with carboplatin and gemcitabine, followed by ZIRABEV as a single agent, is indicated for the treatment of patients with platinum-sensitive recurrent epithelial ovarian, fallopian tube, or primary peritoneal cancer.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Withhold for at least 28 days prior to elective surgery. Do not administer ZIRABEV for 28 days following major surgery and until adequate wound healing. ( 2.1 ) Metastatic colorectal cancer.
( 2.2 ) • 5 mg/kg every 2 weeks with bolus-IFL. • 10 mg/kg every 2 weeks with FOLFOX4. • 5 mg/ kg every 2 weeks or 7.5 mg/kg every 3 weeks with fluoropyrimidine-irinotecan- or fluoropyrimidine-oxaliplatin based chemotherapy after progression on a first-line bevacizumab product containing regimen. First-line non−squamous non−small cell lung cancer. ( 2.3 ) • 15 mg/kg every 3 weeks with carboplatin and paclitaxel.
Recurrent glioblastoma. ( 2.4 ) • 10 mg/kg every 2 weeks. Metastatic renal cell carcinoma.
( 2.5 ) • 10 mg/kg every 2 weeks with interferon alfa. Persistent, recurrent, or metastatic cervical cancer. ( 2.6 ) • 15 mg/kg every 3 weeks with paclitaxel and cisplatin or paclitaxel and topotecan.
Stage III or IV epithelial ovarian, fallopian tube or primary peritoneal cancer following initial surgical resection. ( 2.7 ) • 15 mg/kg every 3 weeks with carboplatin and paclitaxel for up to 6 cycles, followed by 15 mg/kg every 3 weeks as a single agent, for a total of up to 22 cycles. Platinum-resistant recurrent epithelial ovarian, fallopian tube or primary peritoneal cancer.
( 2.7 ) • 10 mg/kg every 2 weeks with paclitaxel, pegylated liposomal doxorubicin, or topotecan given every week. • 15 mg/kg every 3 weeks with topotecan given every 3 weeks Platinum-sensitive recurrent epithelial ovarian, fallopian tube, or primary peritoneal cancer. ( 2.7 ) • 15 mg/kg every 3 weeks with carboplatin and paclitaxel for 6–8 cycles, followed by 15 mg/kg every 3 weeks as a single agent. • 15 mg/kg every 3 weeks with carboplatin and gemcitabine for 6–10 cycles, followed by 15 mg/kg every 3 weeks as a single agent.
Administer as an intravenous infusion after dilution. See full Prescribing Information for preparation and administration instructions and dosage modifications for adverse reactions. ( 2.8 , 2.9 )
2.1Important Administration Information Withhold for at least 28 days prior to elective surgery. Do not administer ZIRABEV until at least 28 days following major surgery and until adequate wound healing.
2.2Metastatic Colorectal Cancer The recommended dosage when ZIRABEV is administered in combination with intravenous fluorouracil-based chemotherapy is: • 5 mg/kg intravenously every 2 weeks in combination with bolus-IFL. • 10 mg/kg intravenously every 2 weeks in combination with FOLFOX4. • 5 mg/kg intravenously every 2 weeks or 7.5 mg/kg intravenously every 3 weeks in combination with fluoropyrimidine-irinotecan- or fluoropyrimidine-oxaliplatin-based chemotherapy in patients who have progressed on a first-line bevacizumab product-containing regimen.
2.3First-Line Non-Squamous Non-Small Cell Lung Cancer The recommended dosage is 15 mg/kg intravenously every 3 weeks in combination with carboplatin and paclitaxel.
2.4Recurrent Glioblastoma The recommended dosage is 10 mg/kg intravenously every 2 weeks.
2.5Metastatic Renal Cell Carcinoma The recommended dosage is 10 mg/kg intravenously every 2 weeks in combination with interferon alfa.
2.6Persistent, Recurrent, or Metastatic Cervical Cancer The recommended dosage is 15 mg/kg intravenously every 3 weeks in combination with paclitaxel and cisplatin or in combination with paclitaxel and topotecan.
2.7Epithelial Ovarian, Fallopian Tube, or Primary Peritoneal Cancer Stage III or IV Disease Following Initial Surgical Resection The recommended dosage is 15 mg/kg intravenously every 3 weeks in combination with carboplatin and paclitaxel for up to 6 cycles, followed by ZIRABEV 15 mg/kg every 3 weeks as a single agent for a total of up to 22 cycles or until disease progression, whichever occurs earlier. Recurrent Disease Platinum Resistant The recommended dosage is 10 mg/kg intravenously every 2 weeks in combination with paclitaxel, pegylated liposomal doxorubicin, or topotecan (ever…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 100 mg/4 mL (25 mg/mL) or 400 mg/16 mL (25 mg/mL) clear to slightly opalescent, colorless to pale brown solution in a single-dose vial Injection: 100 mg/4 mL (25 mg/mL) or 400 mg/16 mL (25 mg/mL) in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Gastrointestinal Perforations and Fistula: Discontinue for gastrointestinal perforations, tracheoesophageal fistula, grade 4 fistula, or fistula formation involving any organ. ( 5.1 ) • Surgery and Wound Healing Complications: In patients who experience wound healing complications during ZIRABEV treatment, withhold ZIRABEV until adequate wound healing. Withhold for at least 28 days prior to elective surgery.
Do not administer ZIRABEV for at least 28 days following a major surgery, and until adequate wound healing. The safety of resumption of bevacizumab products after resolution of wound healing complication has not been established. Discontinue for wound healing complications of necrotizing fasciitis.
( 5.2 ) • Hemorrhage: Severe or fatal hemorrhages have occurred. Do not administer for recent hemoptysis. Discontinue for Grade 3–4 hemorrhage.
( 5.3 ) • Arterial Thromboembolic Events (ATE): Discontinue for severe ATE. ( 5.4 ) • Venous Thromboembolic Events (VTE): Discontinue for Grade 4 VTE. ( 5.5 ) • Hypertension: Monitor blood pressure and treat hypertension.
Withhold if not medically controlled; resume once controlled. Discontinue for hypertensive crisis or hypertensive encephalopathy. ( 5.6 ) • Posterior Reversible Encephalopathy Syndrome (PRES): Discontinue.
( 5.7 ) • Renal Injury and Proteinuria: Monitor urine protein. Discontinue for nephrotic syndrome. Withhold until less than 2 grams of protein in urine.
( 5.8 ) • Infusion–Related Reactions: Decrease rate for infusion-related reactions. Discontinue for severe infusion-related reactions and administer medical therapy. ( 5.9 ) • Embryo-Fetal Toxicity: May cause fetal harm.
Advise females of potential risk to fetus and need for use of effective contraception. ( 5.10 , 8.1 , 8.3 ) • Ovarian Failure: Advise females of the potential risk. ( 5.11 , 8.3 ) • Congestive Heart Failure (CHF): Discontinue ZIRABEV in patients who develop CHF.
( 5.12 )
5.1Gastrointestinal Perforations and Fistulae Serious and sometimes fatal gastrointestinal perforation occurred at a higher incidence in patients receiving bevacizumab products compared to patients receiving chemotherapy. The incidence ranged from 0.3% to 3% across clinical studies, with the highest incidence in patients with a history of prior pelvic radiation. Perforation can be complicated by intra-abdominal abscess, fistula formation, and the need for diverting ostomies.
The majority of perforations occurred within 50 days of the first dose [see Adverse Reactions (6.1) ] . Serious fistulae (including, tracheoesophageal, bronchopleural, biliary, vaginal, renal and bladder sites) occurred at a higher incidence in patients receiving bevacizumab products compared to patients receiving chemotherapy. The incidence ranged from <1% to 1.8% across clinical studies, with the highest incidence in patients with cervical cancer.
The majority of fistulae occurred within 6 months of the first dose. Patients who develop a gastrointestinal vaginal fistula may also have a bowel obstruction and require surgical intervention, as well as a diverting ostomy. Avoid ZIRABEV in patients with ovarian cancer who have evidence of recto-sigmoid involvement by pelvic examination or bowel involvement on CT scan or clinical symptoms of bowel obstruction.
Discontinue in patients who develop gastrointestinal perforation, tracheoesophageal fistula or any Grade 4 fistula. Discontinue in patients with fistula formation involving any internal organ .
5.2Surgery and Wound Healing Complications In a controlled clinical study in which bevacizumab was not administered within 28 days of major surgical procedures, the incidence of wound healing complications, including serious and fatal complications, was 15% in patients with mCRC who underwent surgery while receiving bevacizumab and 4% in patients who did not receive bevacizumab. In a controlled clinical study in patients with relapsed or recurrent GBM, the incidence of wound healing events w…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Gastrointestinal Perforations and Fistulae [see Warnings and Precautions (5.1) ] . • Surgery and Wound Healing Complications [see Warnings and Precautions (5.2) ]. • Hemorrhage [see Warnings and Precautions (5.3) ]. • Arterial Thromboembolic Events [see Warnings and Precautions (5.4) ]. • Venous Thromboembolic Events [see Warnings and Precautions (5.5) ]. • Hypertension [see Warnings and Precautions (5.6) ]. • Posterior Reversible Encephalopathy Syndrome [see Warnings and Precautions (5.7) ]. • Renal Injury and Proteinuria [see Warnings and Precautions (5.8) ]. • Infusion-Related Reactions [see Warnings and Precautions (5.9) ]. • Ovarian Failure [see Warnings and Precautions (5.11) ]. • Congestive Heart Failure [see Warnings and Precautions (5.12) ].
Most common adverse reactions incidence (incidence > 10%) are epistaxis, headache, hypertension, rhinitis, proteinuria, taste alteration, dry skin, hemorrhage, lacrimation disorder, back pain and exfoliative dermatitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 and https://www.pfizer.com or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. The safety data in Warnings and Precautions and described below reflect exposure to bevacizumab in 4463 patients including those with mCRC (AVF2107g, E3200), non-squamous NSCLC (E4599), GBM (EORTC 26101), mRCC (BO17705), cervical cancer (GOG-0240), epithelial ovarian, fallopian tube, or primary peritoneal cancer (MO22224, AVF4095, GOG-0213, and GOG-0218) or another cancer at the recommended dose and schedule for a median of 6 to 23 doses.
The most common adverse reactions observed in patients receiving bevacizumab as a single agent or in combination with other anti-cancer therapies at a rate >10% were epistaxis, headache, hypertension, rhinitis, proteinuria, taste alteration, dry skin, hemorrhage, lacrimation disorder, back pain, and exfoliative dermatitis. Across clinical studies, bevacizumab was discontinued in 8% to 22% of patients because of adverse reactions [see Clinical Studies (14) ]. Metastatic Colorectal Cancer In Combination with bolus IFL The safety of bevacizumab was evaluated in 392 patients who received at least one dose of bevacizumab in a double-blind, active-controlled study (AVF2107g), which compared bevacizumab (5 mg/kg every 2 weeks) with bolus-IFL to placebo with bolus IFL in patients with mCRC [see Clinical Studies (14.1) ] .
Patients were randomized (1:1:1) to placebo with bolus IFL, bevacizumab with bolus IFL, or bevacizumab with fluorouracil and leucovorin. The demographics of the safety population were similar to the demographics of the efficacy population. All Grades 3–4 adverse reactions and selected Grades 1–2 adverse reactions (i.e., hypertension, proteinuria, thromboembolic events) were collected in the entire study population.
Adverse reactions are presented in Table 2. Table 2: Grades 3–4 Adverse Reactions Occurring at Higher Incidence (≥2%) in Patients Receiving Bevacizumab vs. Placebo in Study AVF2107g Adverse Reaction NCI-CTC version 3 Bevacizumab with IFL (N=392) Placebo with IFL (N=396) Hematology Leukopenia 37% 31% Neutropenia 21% 14% Gastrointestinal Diarrhea 34% 25% Abdominal pain 8% 5% Constipation 4% 2% Vascular Hypertension 12% 2% Deep vein thrombosis 9% 5% Intra-abdominal thrombosis 3% 1% Syncope 3% 1% General Asthenia 10% 7% Pain 8% 5% In Combination with FOLFOX4 The safety of bevacizumab was evaluated in 521 patients in an open-label, active-controlled study (E3200) in patients who were previously treated with irinotecan and fluorouracil for initial…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Effects of ZIRABEV on Other Drugs No clinically meaningful effect on the pharmacokinetics of irinotecan or its active metabolite SN38, interferon alfa, carboplatin or paclitaxel was observed when bevacizumab was administered in combination with these drugs; however, 3 of the 8 patients receiving bevacizumab with paclitaxel and carboplatin had lower paclitaxel exposure after four cycles of treatment (at Day 63) than those at Day 0, while patients receiving paclitaxel and carboplatin alone had a greater paclitaxel exposure at Day 63 than at Day 0.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and their mechanism of action [see Clinical Pharmacology (12.1) ] , bevacizumab products may cause fetal harm in pregnant women. Limited postmarketing reports describe cases of fetal malformations with use of bevacizumab products in pregnancy; however, these reports are insufficient to determine drug associated risks. In animal reproduction studies, intravenous administration of bevacizumab to pregnant rabbits every 3 days during organogenesis at doses approximately 1 to 10 times the clinical dose of 10 mg/kg produced fetal resorptions, decreased maternal and fetal weight gain and multiple congenital malformations including corneal opacities and abnormal ossification of the skull and skeleton including limb and phalangeal defects (see Data ) .
Furthermore, animal models link angiogenesis and VEGF and VEGFR2 to critical aspects of female reproduction, embryo-fetal development, and postnatal development. Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Pregnant rabbits dosed with 10 mg/kg to 100 mg/kg bevacizumab (approximately 1 to 10 times the clinical dose of 10 mg/kg) every three days during the period of organogenesis (gestation day 6–18) exhibited decreases in maternal and fetal body weights and increased number of fetal resorptions. There were dose-related increases in the number of litters containing fetuses with any type of malformation (42% for the 0 mg/kg dose, 76% for the 30 mg/kg dose, and 95% for the 100 mg/kg dose) or fetal alterations (9% for the 0 mg/kg dose, 15% for the 30 mg/kg dose, and 61% for the 100 mg/kg dose).
Skeletal deformities were observed at all dose levels, with some abnormalities including meningocele observed only at the 100 mg/kg dose level. Teratogenic effects included: reduced or irregular ossification in the skull, jaw, spine, ribs, tibia and bones of the paws; fontanel, rib and hindlimb deformities; corneal opacity; and absent hindlimb phalanges.
8.2Lactation Risk Summary No data are available regarding the presence of bevacizumab products in human milk, the effects on the breast fed infant, or the effects on milk production. Human IgG is present in human milk, but published data suggest that breast milk antibodies do not enter the neonatal and infant circulation in substantial amounts. Because of the potential for serious adverse reactions in breastfed infants, advise women not to breastfeed during treatment with ZIRABEV and for 6 months after the last dose.
8.3Females and Males of Reproductive Potential Contraception Females Bevacizumab products may cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Advise females of reproductive potential to use effective contraception during treatment with ZIRABEV and for 6 months after the last dose. Infertility Females Bevacizumab products increase the risk of ovarian failure and may impair fertility.
Inform females of reproductive potential of the risk of ovarian failure prior to the first-dose of ZIRABEV. Long-term effects of bevacizumab products on fertility are not known. In a clinical study of 179 premenopausal women randomized to receive chemotherapy with or without bevacizumab, the incidence of ovarian failure was higher in patients who received bevacizumab with chemotherapy (34%) compared to patients who received chemotherapy alone (2%).
After discontinuing bevacizumab with chemotherapy, recovery of ovarian function occurred in 22% of these patients [see Warnings and Precautions (5.11) , Adverse Reactions (6.1) ].
8.4Pediatric Use The safety and effectiveness of bevacizumab products in pediatric patients have not been established. In published literature re…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and their mechanism of action [see Clinical Pharmacology (12.1) ] , bevacizumab products may cause fetal harm in pregnant women. Limited postmarketing reports describe cases of fetal malformations with use of bevacizumab products in pregnancy; however, these reports are insufficient to determine drug associated risks. In animal reproduction studies, intravenous administration of bevacizumab to pregnant rabbits every 3 days during organogenesis at doses approximately 1 to 10 times the clinical dose of 10 mg/kg produced fetal resorptions, decreased maternal and fetal weight gain and multiple congenital malformations including corneal opacities and abnormal ossification of the skull and skeleton including limb and phalangeal defects (see Data ) .
Furthermore, animal models link angiogenesis and VEGF and VEGFR2 to critical aspects of female reproduction, embryo-fetal development, and postnatal development. Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Pregnant rabbits dosed with 10 mg/kg to 100 mg/kg bevacizumab (approximately 1 to 10 times the clinical dose of 10 mg/kg) every three days during the period of organogenesis (gestation day 6–18) exhibited decreases in maternal and fetal body weights and increased number of fetal resorptions. There were dose-related increases in the number of litters containing fetuses with any type of malformation (42% for the 0 mg/kg dose, 76% for the 30 mg/kg dose, and 95% for the 100 mg/kg dose) or fetal alterations (9% for the 0 mg/kg dose, 15% for the 30 mg/kg dose, and 61% for the 100 mg/kg dose).
Skeletal deformities were observed at all dose levels, with some abnormalities including meningocele observed only at the 100 mg/kg dose level. Teratogenic effects included: reduced or irregular ossification in the skull, jaw, spine, ribs, tibia and bones of the paws; fontanel, rib and hindlimb deformities; corneal opacity; and absent hindlimb phalanges.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of bevacizumab products in pediatric patients have not been established. In published literature reports, cases of non-mandibular osteonecrosis have been observed in patients under the age of 18 years who received bevacizumab. Bevacizumab products are not approved for use in patients under the age of 18 years.
Antitumor activity was not observed among eight pediatric patients with relapsed GBM who received bevacizumab and irinotecan. Addition of bevacizumab to standard of care did not result in improved event-free survival in pediatric patients enrolled in two randomized clinical studies, one in high grade glioma (n=121) and one in metastatic rhabdomyosarcoma or non-rhabdomyosarcoma soft tissue sarcoma (n=154). Based on the population pharmacokinetics analysis of data from 152 pediatric and young adult patients with cancer (7 months to 21 years of age), bevacizumab clearance normalized by body weight in pediatrics was comparable to that in adults.
Juvenile Animal Toxicity Data Juvenile cynomolgus monkeys with open growth plates exhibited physeal dysplasia following 4 to 26 weeks exposure at 0.4 to 20 times the recommended human dose (based on mg/kg and exposure). The incidence and severity of physeal dysplasia were dose-related and were partially reversible upon cessation of treatment.
🧓 Geriatric Use ▾
8.5Geriatric Use In an exploratory, pooled analysis of 1745 patients from five randomized, controlled studies, 35% of patients were ≥65 years old. The overall incidence of ATE was increased in all patients receiving bevacizumab with chemotherapy as compared to those receiving chemotherapy alone, regardless of age; however, the increase in the incidence of ATE was greater in patients ≥65 years (8% vs. 3%) as compared to patients <65 years (2% vs.
1%) [see Warnings and Precautions (5.4) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Bevacizumab products bind VEGF and prevent the interaction of VEGF to its receptors (Flt-1 and KDR) on the surface of endothelial cells. The interaction of VEGF with its receptors leads to endothelial cell proliferation and new blood vessel formation in in vitro models of angiogenesis. Administration of bevacizumab to xenotransplant models of colon cancer in nude (athymic) mice caused reduction of microvascular growth and inhibition of metastatic disease progression.
12.3Pharmacokinetics The pharmacokinetic profile of bevacizumab was assessed using an assay that measures total serum bevacizumab concentrations (i.e., the assay did not distinguish between free bevacizumab and bevacizumab bound to VEGF ligand). Based on a population pharmacokinetic analysis of 491 patients who received 1 to 20 mg/kg of bevacizumab every week, every 2 weeks, or every 3 weeks, bevacizumab pharmacokinetics are linear and the predicted time to reach more than 90% of steady state concentration is 84 days.
The accumulation ratio following a dose of 10 mg/kg of bevacizumab once every 2 weeks is 2.8. Population simulations of bevacizumab exposures provide a median trough concentration of 80.3 mcg/mL on Day 84 (10 th , 90 th percentile: 45, 128) following a dose of 5 mg/kg once every two weeks. Distribution The mean (% coefficient of variation [CV%]) central volume of distribution is 2.9 (22%) L.
Elimination The mean (CV%) clearance is 0.23 (33) L/day. The estimated half-life is 20 days (11 to 50 days). Specific Populations The clearance of bevacizumab varied by body weight, sex, and tumor burden.
After correcting for body weight, males had a higher bevacizumab clearance (0.26 L/day vs.
0.21L/day) and a larger central volume of distribution (3.2 L vs.
2.7L) than females. Patients with higher tumor burden (at or above median value of tumor surface area) had a higher bevacizumab clearance (0.25 L/day vs.
0.20L/day) than patients with tumor burdens below the median. In Study AVF2107g, there was no evidence of lesser efficacy (hazard ratio for overall survival) in males or patients with higher tumor burden treated with bevacizumab as compared to females and patients with low tumor burden.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Bevacizumab products bind VEGF and prevent the interaction of VEGF to its receptors (Flt-1 and KDR) on the surface of endothelial cells. The interaction of VEGF with its receptors leads to endothelial cell proliferation and new blood vessel formation in in vitro models of angiogenesis. Administration of bevacizumab to xenotransplant models of colon cancer in nude (athymic) mice caused reduction of microvascular growth and inhibition of metastatic disease progression.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ZIRABEV (bevacizumab-bvzr) injection is a clear to slightly opalescent, colorless to pale brown, sterile solution for intravenous infusion supplied in a carton containing one single-dose vial in the following strengths: • 100 mg/4 mL (25 mg/mL) (NDC 0069-0315-01) • 400 mg/16 mL (25 mg/mL) (NDC 0069-0342-01) Store refrigerated at 2°C to 8°C (36°F to 46°F) in the original carton until time of use to protect from light. Do not freeze or shake the vial or carton.
📦 Storage and Handling ▾
Store refrigerated at 2°C to 8°C (36°F to 46°F) in the original carton until time of use to protect from light. Do not freeze or shake the vial or carton.
📋 Description ▾
11 DESCRIPTION Bevacizumab-bvzr is a vascular endothelial growth factor inhibitor. Bevacizumab-bvzr is a recombinant humanized monoclonal IgG1 antibody that contains human framework regions and murine complementarity-determining regions. Bevacizumab-bvzr has an approximate molecular weight of 149 kDa.
Bevacizumab-bvzr is produced in a mammalian cell (Chinese Hamster Ovary) expression system. ZIRABEV (bevacizumab-bvzr) injection is a sterile, preservative-free, clear to slightly opalescent, colorless to pale brown solution in a single-dose vial for intravenous use. ZIRABEV contains bevacizumab-bvzr at a concentration of 25 mg/mL in either 100 mg/4 mL or 400 mg/16 mL single-dose vials.
Each mL of solution contains 25 mg bevacizumab-bvzr, edetate disodium dihydrate (0.05 mg), polysorbate 80 (0.2 mg), succinic acid (2.36 mg), sucrose (85 mg), and Water for Injection, USP. Sodium hydroxide is added to adjust the pH. The pH is 5.5.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Gastrointestinal Perforations and Fistulae Bevacizumab products may increase the risk of developing gastrointestinal perforations and fistulae. Advise patients to immediately contact their healthcare provider for high fever, rigors, persistent or severe abdominal pain, severe constipation, or vomiting [see Warnings and Precautions (5.1) ]. Surgery and Wound Healing Complications Bevacizumab products can increase the risk of wound healing complications.
Instruct patients not to undergo surgery without first discussing this potential risk with their healthcare provider [see Warnings and Precautions (5.2) ] . Hemorrhage Bevacizumab products can increase the risk of hemorrhage. Advise patients to immediately contact their healthcare provider for signs and symptoms of serious or unusual bleeding including coughing or spitting blood [see Warnings and Precautions (5.3) ] .
Arterial and Venous Thromboembolic Events Bevacizumab products increase the risk of arterial and venous thromboembolic events. Advise patients to immediately contact their healthcare provider for signs and symptoms of arterial or venous thromboembolism [see Warnings and Precautions (5.4 , 5.5) ] . Hypertension Bevacizumab products can increase blood pressure.
Advise patients that they will undergo routine blood pressure monitoring and to contact their healthcare provider if they experience changes in blood pressure [see Warnings and Precautions (5.6) ] . Posterior Reversible Leukoencephalopathy Syndrome Posterior reversible encephalopathy syndrome (PRES) has been associated with bevacizumab products treatment. Advise patients to immediately contact their healthcare provider for new onset or worsening neurological function [see Warnings and Precautions (5.7) ] .
Renal Injury and Proteinuria Bevacizumab products increase the risk of proteinuria and renal injury, including nephrotic syndrome. Advise patients that treatment with ZIRABEV requires regular monitoring of renal function and to contact their healthcare provider for proteinuria or signs and symptoms of nephrotic syndrome [see Warnings and Precautions (5.8) ] . Infusion-Related Reactions Bevacizumab products can cause infusion-related reactions.
Advise patients to contact their healthcare provider immediately for signs or symptoms of infusion-related reactions [see Warnings and Precautions (5.9) ]. Congestive Heart Failure Bevacizumab products can increase the risk of developing congestive heart failure. Advise patients to contact their healthcare provider immediately for signs and symptoms of CHF [see Warnings and Precautions (5.12) ].
Embryo-Fetal Toxicity Advise female patients that bevacizumab products may cause fetal harm and to inform their healthcare provider with a known or suspected pregnancy [see Warnings and Precautions (5.10) , Use in Specific Populations (8.1) ]. Advise females of reproductive potential to use effective contraception during treatment with ZIRABEV and for 6 months after the last dose [see Use in Specific Populations (8.3) ]. Ovarian Failure Bevacizumab products may lead to ovarian failure.
Advise patients of potential options for preservation of ova prior to starting treatment [see Warnings and Precautions (5.11) ]. Lactation Advise women not to breastfeed during treatment with ZIRABEV and for 6 months after the last dose [see Use in Specific Populations (8.2) ] .