
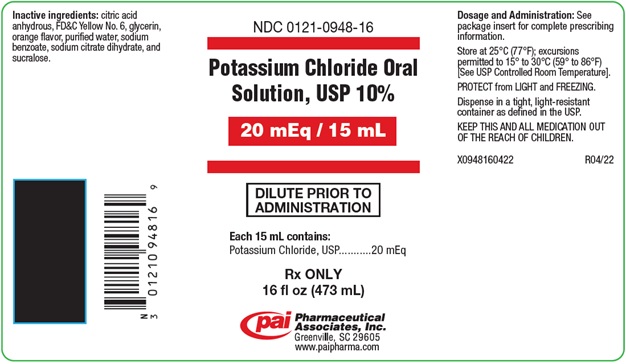
Potassium Chloride 20 meq/15mL Solution, 473 mL — NDC 0121-0948-16 (Billing 00121-0948-16)
This is a package of 473 mL of Potassium Chloride 20 meq/15mL Solution from PAI Holdings, LLC dba PAI Pharma, marketed since Mar 2023 and currently FDA-listed; retail pharmacies pay about $0.0409 per mL (NADAC). It is this product's only package size.
Other active recalls for Potassium Chloride (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 001264
- GCN: 03443
- GPI-14 (Medi-Span): 79700030002085
- HICL (First Databank): 000549
- AHFS class code: 40:12.00.00
- RxCUI (RxNorm): 312515
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Potassium class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats and prevents low potassium. Doctors often use it when you take diuretics or lose fluids through diarrhea or vomiting and food alone isn't enough. The injection is used in...
- Take tablets and capsules with meals, not on an empty stomach, to protect your stomach. Powders and liquids need to be diluted first. Follow your prescriber's directions and keep y...
- The most common issue is stomach upset. Taking it with food helps. Call your doctor if you have severe vomiting, belly pain, swelling or bleeding, since that can mean an ulcer or b...
- Check with me first. Blood pressure medicines such as ACE inhibitors and ARBs, spironolactone, and NSAIDs can raise potassium. Triamterene and amiloride should be avoided with it.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Potassium Chloride (prescription drug) — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.041 | $19.35 / 473 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.0695 | $32.87 / 473 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.0928 | $43.89 / 473 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00121-0948-16 You're viewing this Main listing | 473 mL in 1 BOTTLE | 2023-03-27 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Potassium Chloride 20 meq/15mLthis 00121-0948-16 | PAI | 473 ml | $0.041 | AA | Availability likely | — |
| Potassium Chloride 20 meq/15mL 00603-1542-58 | Endo | 473 ml | $0.041 | AA | Discontinued | — |
| Potassium Chloride 20 meq/15mL 59651-0959-47 | Aurobindo | 473 ml | $0.041 | AA | Availability likely | — |
| Potassium Chloride 1.5 g/15mL 69238-1459-02 | Amneal | 473 ml | $0.041 | AA | Availability likely | — |
| Potassium Chloride 20 meq/15mL 70010-0072-44 | Granules | 473 ml | $0.041 | AA | Availability likely | — |
| Potassium Chloride 20 meq/15mL 72888-0041-13 | Advagen | 473 ml | $0.041 | AA | Availability likely | — |
| Potassium Chloride 20 meq/15mL 43386-0168-01 | Lupin | 473 ml | $0.084 | AA | FDA listed | +105% |
| Potassium Chloride 20 meq/30mL 00121-1896-00 | PAI | 10 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 00121-4948-00 | PAI | 10 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 00904-7461-46 | Major | 30 cups | — | AA | FDA listed | — |
| Potassium Chloride 40 meq/30mL 00904-7462-43 | Major | 50 cups | — | AA | FDA listed | — |
| Potassium Chloride for Oral Solution 1.5 g/1.58g 10135-0819-08 | Marlex | 1.58 g | — | AA | FDA listed | — |
| Potassium Chloride 1.5 g/15mL 17856-0048-01 | ATLANTIC | 72 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 27808-0168-01 | Tris | 473 ml | — | — | FDA listed | — |
| Potassium chloride 20 meq/15mL 31722-0494-47 | Camber | 473 ml | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 33342-0511-73 | Macleods | 473 ml | — | AA | FDA listed | — |
| Potassium Chloride 40 meq/30mL 43598-0160-01 | Dr. | 100 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 43598-0891-10 | Dr. | 100 cups | — | AA | FDA listed | — |
| Potassium Chloride 1.5 g/15mL 50268-0674-15 | AvPAK | 50 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 53041-0681-06 | Guardian | 473 ml | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 54288-0160-47 | BPI | 473 ml | — | AA | FDA listed | — |
| Potassium Chloride 1.5 g/15mL 60687-0628-07 | American | 10 cups | — | AA | Discontinued | — |
| Potassium Chloride 1.5 g/15mL 60687-0884-07 | American | 10 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 63739-0724-50 | McKesson | 10 cups | — | AA | Discontinued | — |
| Potassium Chloride 20 meq/15mL 64950-0320-99 | Genus | 113562 ml | — | AA | Discontinued | — |
| Potassium Chloride 1.5 g/15mL 71656-0021-01 | Saptalis | 10 cups | — | AA | FDA listed | — |
| Potassium Chloride 1.5 g/15mL 81033-0220-51 | Kesin | 10 cups | — | AA | FDA listed | — |
| Potassium Chloride 3 g/30mL 81033-0240-50 | Kesin | 10 cups | — | AA | FDA listed | — |
| Potassium Chloride 20 meq/15mL 82983-0411-47 | Ajenat | 473 ml | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 96K6UQ3ZD4
Sucralose is a synthetic sweetener made from sugar. It's added to medicines to improve taste without adding calories, helping make bitter or unpleasant-tasting drugs easier to take.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Potassium Chloride is indicated for the treatment and prophylaxis of hypokalemia with or without metabolic alkalosis, in patients for whom dietary management with potassium-rich foods or diuretic dose reduction are insufficient. Potassium Chloride is indicated for the treatment and prophylaxis of hypokalemia with or without metabolic alkalosis, in patients for whom dietary management with potassium-rich foods or diuretic dose reduction are insufficient.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Dilute prior to administration ( 2.1 , 5.1 ) Monitor serum potassium and adjust dosage accordingly ( 2.2 , 2.3 ) Treatment of hypokalemia: Adults: Initial doses range from 40-100 mEq/day in 2-5 divided doses: limit doses to 40 mEq per dose. Total daily dose should not exceed 200 mEq (2.2) Pediatric patients aged birth to 16 years old: 2-4 mEq/kg/day in divided doses; not to exceed 1 mEq/kg as a single dose or 40 mEq whichever is lower; if deficits are severe or ongoing losses are great, consider intravenous therapy.
Total daily dose should not exceed 100 mEq (2.3) Maintenance or Prophylaxis of hypokalemia: Adults: Typical dose is 20 mEq per day (2.2) Pediatric patients aged birth to 16 years old: typical dose is 1 mEq/kg/day. Do not exceed 3 mEq/kg/day (2.3)
2.1Administration and Monitoring Monitoring Monitor serum potassium and adjust dosages accordingly. For treatment of hypokalemia, monitor potassium levels daily or more often depending on the severity of hypokalemia until they return to normal. Monitor potassium levels monthly to biannually for maintenance or prophylaxis.
The treatment of potassium depletion, particularly in the presence of cardiac disease, renal disease, or acidosis requires careful attention to acid-base balance, volume status, electrolytes, including magnesium, sodium, chloride, phosphate, and calcium, electrocardiograms and the clinical status of the patient. Correct volume status, acid-base balance and electrolyte deficits as appropriate. Administration Dilute the potassium chloride solution with at least 4 ounces of cold water [see Warnings and Precautions (5.1) ] .
Take with meals or immediately after eating. If serum potassium concentration is ˂2.5 mEq/L, use intravenous potassium instead of oral supplementation.
2.2Adult Dosing Treatment of hypokalemia Daily dose range from 40 to 100 mEq. Give in 2 to 5 divided doses; limit doses to 40 mEq per dose. The total daily dose should not exceed 200 mEq in a 24 hour period.
Maintenance or Prophylaxis Typical dose is 20 mEq per day. Individualize dose based upon serum potassium levels. Studies support the use of potassium replacement in digitalis toxicity.
When alkalosis is present, normokalemia and hyperkalemia may obscure a total potassium deficit. The advisability of use of potassium replacement in the setting of hyperkalemia is uncertain.
2.3Pediatric Dosing Treatment of hypokalemia Pediatric patients aged birth to 16 years old: The initial dose is 2 to 4 mEq/kg/day in divided doses; do not exceed as a single dose 1 mEq/kg or 40 mEq, whichever is lower; maximum daily doses should not exceed 100 mEq. If deficits are severe or ongoing losses are great, consider intravenous therapy. Maintenance or Prophylaxis Pediatric patients aged birth to 16 years old: Typical dose is 1 mEq/kg/day.
Do not exceed 3 mEq/kg/day.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral Solution 10%: 1.3 mEq potassium per mL. Oral Solution 20%: 2.6 mEq potassium per mL. • Oral Solution: 10%; 1.3 mEq potassium per mL • Oral Solution: 20%; 2.6 mEq potassium per mL
⛔ Contraindications ▾
4 CONTRAINDICATIONS Potassium chloride is contraindicated in patients on potassium sparing diuretics. Concomitant use with potassium sparing diuretics. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Gastrointestinal Irritation : Dilute before use, take with meals ( 5.1 )
5.1Gastrointestinal Irritation May cause gastrointestinal irritation if administered undiluted. Increased dilution of the solution and taking with meals may reduce gastrointestinal irritation [see Dosage and Administration (2.1) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions to oral potassium salts are nausea, vomiting, flatulence, abdominal pain/discomfort, and diarrhea. Most common adverse reactions are nausea, vomiting, flatulence, abdominal pain/discomfort, and diarrhea ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Pharmaceutical Associates, Inc. at 1-800-845-8210 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Potassium sparing diuretics: Avoid concomitant use ( 7.1 ) Renin-angiotensin-aldosterone inhibitors: Monitor for hyperkalemia ( 7.2 ) Nonsteroidal Anti-Inflammatory drugs: Monitor for hyperkalemia ( 7.3 )
7.1Potassium-Sparing Diuretics Use with potassium-sparing diuretics can produce severe hyperkalemia. Avoid concomitant use.
7.2Renin-Angiotensin-Aldosterone System Inhibitors Drugs that inhibit the renin-angiotensin-aldosterone system (RAAS) including angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), spironolactone, eplerenone, or aliskiren produce potassium retention by inhibiting aldosterone production. Closely monitor potassium in patients receiving concomitant RAAS therapy.
7.3Nonsteroidal Anti-inflammatory Drugs (NSAIDs) NSAIDS may produce potassium retention by reducing renal synthesis of prostaglandin E and impairing the renin-angiotensin system. Closely monitor potassium in patients on concomitant NSAIDs.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Cirrhosis: Initiate therapy at the low end of the dosing range ( 8.5 ) Renal Impairment: Initiate therapy at the low end of the dosing range ( 8.6 )
8.1Pregnancy There are no human data related to use of Potassium Chloride during pregnancy, and animal studies have not been conducted. Potassium supplementation that does not lead to hyperkalemia is not expected to cause fetal harm. The background risk for major birth defects and miscarriage in the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
8.2Lactation Risk Summary The normal potassium ion content of human milk is about 13 mEq per liter. Since potassium from oral supplements such as Potassium Chloride becomes part of the body potassium pool, as long as body potassium is not excessive, the contribution of potassium chloride supplementation should have little or no effect on the level in human milk.
8.4Pediatric Use The safety and effectiveness of Potassium Chloride have been demonstrated in children with diarrhea and malnutrition from birth to 16 years.
8.5Geriatric Use Clinical studies of Potassium Chloride did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
8.6Cirrhotics Patients with cirrhosis should usually be started at the low end of the dosing range, and the serum potassium level should be monitored frequently. [ see Clinical Pharmacology (12.3 )].
8.7Renal Impairment Patients with renal impairment have reduced urinary excretion of potassium and are at substantially increased risk of hyperkalemia. Patients with impaired renal function, particularly if the patient is on ACE inhibitors, ARBs, or nonsteroidal anti-inflammatory drugs should usually be started at the low end of the dosing range because of the potential for development of hyperkalemia. The serum potassium level should be monitored frequently.
Renal function should be assessed periodically.
🤰 Pregnancy ▾
8.1Pregnancy There are no human data related to use of Potassium Chloride during pregnancy, and animal studies have not been conducted. Potassium supplementation that does not lead to hyperkalemia is not expected to cause fetal harm. The background risk for major birth defects and miscarriage in the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Potassium Chloride have been demonstrated in children with diarrhea and malnutrition from birth to 16 years.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Potassium Chloride did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Symptoms The administration of oral potassium salts to persons with normal excretory mechanisms for potassium rarely causes serious hyperkalemia. However, if excretory mechanisms are impaired or if potassium is administered too rapidly potentially fatal hyperkalemia can result. Hyperkalemia is usually asymptomatic and may be manifested only by an increased serum potassium concentration (6.5-8.0 mEq/L) and characteristic electrocardiographic changes (peaking of T-waves, loss of P-waves, depression of S-T segment, and prolongation of the QT-interval).
Late manifestations include muscle paralysis and cardiovascular collapse from cardiac arrest (9-12 mEq/L).
10.2Treatment Treatment measures for hyperkalemia include the following: Monitor closely for arrhythmias and electrolyte changes. Eliminate foods and medications containing potassium and of any agents with potassium-sparing properties such as potassium-sparing diuretics, ARBS, ACE inhibitors, NSAIDS, certain nutritional supplements and many others. Administer intravenous calcium gluconate if the patient is at no risk or low risk of developing digitalis toxicity.
Administer intravenously 300 to 500 mL/hr of 10% dextrose solution containing 10 to 20 units of crystalline insulin per 1000 mL. Correct acidosis, if present, with intravenous sodium bicarbonate. Use exchange resins, hemodialysis, or peritoneal dialysis.
In patients who have been stabilized on digitalis, too rapid a lowering of the serum potassium concentration can produce digitalis toxicity.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The potassium ion (K+) is the principal intracellular cation of most body tissues. Potassium ions participate in a number of essential physiological processes including the maintenance of intracellular tonicity; the transmission of nerve impulses; the contraction of cardiac, skeletal, and smooth muscle; and the maintenance of normal renal function. The intracellular concentration of potassium is approximately 150 to 160 mEq per liter.
The normal adult plasma concentration is 3.5 to 5 mEq per liter. An active ion transport system maintains this gradient across the plasma membrane. Potassium is a normal dietary constituent, and under steady-state conditions the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine.
The usual dietary intake of potassium is 50 to 100 mEq per day.
12.3Pharmacokinetics Based on published literature, the rate of absorption and urinary excretion of potassium from KCl oral solution were higher during the first few hours after dosing relative to modified release KCl products. The bioavailability of potassium, as measured by the cumulative urinary excretion of K+ over a 24 hour post dose period, is similar for KCl solution and modified release products.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The potassium ion (K+) is the principal intracellular cation of most body tissues. Potassium ions participate in a number of essential physiological processes including the maintenance of intracellular tonicity; the transmission of nerve impulses; the contraction of cardiac, skeletal, and smooth muscle; and the maintenance of normal renal function. The intracellular concentration of potassium is approximately 150 to 160 mEq per liter.
The normal adult plasma concentration is 3.5 to 5 mEq per liter. An active ion transport system maintains this gradient across the plasma membrane. Potassium is a normal dietary constituent, and under steady-state conditions the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine.
The usual dietary intake of potassium is 50 to 100 mEq per day.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Potassium Chloride Oral Solution, USP 10% (20 mEq/15 mL) is an orange flavored, clear orange-colored solution available as follows: NDC 0121-0948-16: 16 fl oz (473 mL) Bottle. NDC 0121-4948-15: 15 mL unit dose cup. Case contains 30 unit-dose cups of 15 mL (NDC 0121-4948-94), packaged in 3 trays of 10 unit-dose cups each, 40 unit-dose cups of 15 mL (NDC 0121-4948-40), packaged in 4 trays of 10 unit-dose cups each, 50 unit-dose cups of 15 mL (NDC 0121-4948-50), packaged in 5 trays of 10 unit-dose cups each, 80 unit-dose cups of 15 mL (NDC 0121-4948-80), packaged in 8 trays of 10 unit-dose cups each and 100 unit-dose cups of 15 mL (NDC 0121-4948-00), packaged in 10 trays of 10 unit-dose cups each.
NDC 0121-1896-30: 30 mL unit dose cup. Case contains 40 unit-dose cups of 30 mL (NDC 0121-1896-40), packaged in 4 trays of 10 unit-dose cups each, 50 unit-dose cups of 30 mL (NDC 0121-1896-50), packaged in 5 trays of 10 unit-dose cups each and 100 unit-dose cups of 30 mL (NDC 0121-1896-00), packaged in 10 trays of 10 unit-dose cups each. Potassium Chloride Oral Solution, USP 20% (40 mEq/15 mL) is an orange flavored, clear orange-colored, solution available as follows: NDC 0121-2847-16: 16 fl oz (473 mL) Bottle.
NDC 0121-2847-15: 15 mL unit dose cup. Case contains 30 unit-dose cups of 15 mL (NDC 0121-2847-94), packaged in 3 trays of 10 unit-dose cups each, 40 unit-dose cups of 15 mL (NDC 0121-2847-40), packaged in 4 trays of 10 unit-dose cups each, 50 unit-dose cups of 15 mL (NDC 0121-2847-50), packaged in 5 trays of 10 unit-dose cups each, 80 unit-dose cups of 15 mL (NDC 0121-2847-80), packaged in 8 trays of 10 unit-dose cups each and 100 unit-dose cups of 15 mL (NDC 0121-2847-00), packaged in 10 trays of 10 unit-dose cups each.
STORAGE Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP. PROTECT from LIGHT and FREEZING.
📦 Storage and Handling ▾
STORAGE Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP. PROTECT from LIGHT and FREEZING.
📋 Description ▾
11 DESCRIPTION Potassium Chloride is a white crystalline or colorless solid. It is soluble in water and slightly soluble in alcohol. Chemically, Potassium Chloride is K-Cl with a molecular mass of 74.55.
Oral Solution 10%: Each 15 mL of solution contains 1.5 g of potassium chloride, USP and the following inactive ingredients: citric acid anhydrous, FD&C Yellow No. 6, glycerin, orange flavor, purified water, sodium benzoate, sodium citrate dihydrate, and sucralose. Oral Solution 20%: Each 15 mL of solution contains 3.0 g of potassium chloride, USP and the following inactive ingredients: citric acid anhydrous, FD&C Yellow No.
6, glycerin, orange flavor, purified water, sodium benzoate, sodium citrate dihydrate and sucralose.
🍼 Nursing Mothers ▾
8.2Lactation Risk Summary The normal potassium ion content of human milk is about 13 mEq per liter. Since potassium from oral supplements such as Potassium Chloride becomes part of the body potassium pool, as long as body potassium is not excessive, the contribution of potassium chloride supplementation should have little or no effect on the level in human milk.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Based on published literature, the rate of absorption and urinary excretion of potassium from KCl oral solution were higher during the first few hours after dosing relative to modified release KCl products. The bioavailability of potassium, as measured by the cumulative urinary excretion of K+ over a 24 hour post dose period, is similar for KCl solution and modified release products.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 16 fl oz (473 mL) NDC 0121-0948-16 Potassium Chloride Oral Solution, USP 10% 20 mEq / 15 mL DILUTE PRIOR TO ADMINISTRATION Rx ONLY 16 fl oz (473 mL) PHARMACEUTICAL ASSOCIATES, INC. GREENVILLE, SC 29605 X0948160422 R04/22 PRINCIPAL DISPLAY PANEL - 16 fl oz (473 mL)
PRINCIPAL DISPLAY PANEL - 15 mL Cup Label Delivers 15 mL NDC 0121-4948-15 Potassium Chloride Oral Solution, USP 10% 20 mEq per 15 mL DILUTE PRIOR TO ADMINISTRATION Package Not Child-Resistant Rx ONLY PHARMACEUTICAL ASSOCIATES, INC. GREENVILLE, SC 29605 PRINCIPAL DISPLAY PANEL - 15 mL Cup Label - 10%
PRINCIPAL DISPLAY PANEL - 30 mL Cup Label Delivers 30 mL NDC 0121-1896-30 Potassium Chloride Oral Solution, USP 10% 40 mEq per 30 mL DILUTE PRIOR TO ADMINISTRATION Package Not Child-Resistant Rx ONLY PHARMACEUTICAL ASSOCIATES, INC. GREENVILLE, SC 29605 PRINCIPAL DISPLAY PANEL - 30 mL Cup Label
PRINCIPAL DISPLAY PANEL - 16 fl oz (473 mL) NDC 0121-2847-16 Potassium Chloride Oral Solution, USP 20% 40 mEq / 15 mL DILUTE PRIOR TO ADMINISTRATION Rx ONLY 16 fl oz (473 mL) PHARMACEUTICAL ASSOCIATES, INC. GREENVILLE, SC 29605 X0948160422 R04/22 PRINCIPAL DISPLAY PANEL - 16 fl oz (473 mL)
PRINCIPAL DISPLAY PANEL - 15 mL Cup Label Delivers 15 mL NDC 0121-2847-15 Potassium Chloride Oral Solution, USP 20% 40 mEq per 15 mL DILUTE PRIOR TO ADMINISTRATION Package Not Child-Resistant Rx ONLY PHARMACEUTICAL ASSOCIATES, INC. GREENVILLE, SC 29605 PRINCIPAL DISPLAY PANEL - 15 mL Cup Label