
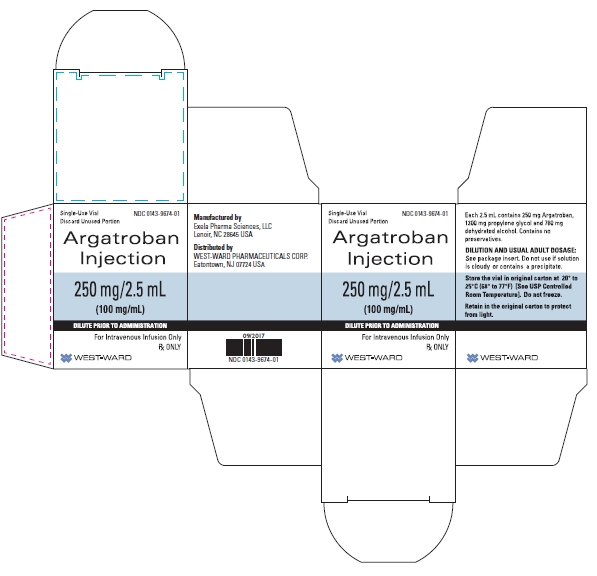
Argatroban 250 mg/2.5mL Injection, 2.5 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Direct Thrombin Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- HIT stands for heparin-induced thrombocytopenia. It's an immune reaction where your body mistakenly attacks your own platelets after being exposed to heparin. This actually makes y...
- What exactly is HIT, and why can't I just keep using heparin?
- Argatroban is given through an IV line directly into your vein as a continuous infusion — you'll receive it in a hospital or clinical setting, not at home. Your care team will run...
- How will I receive this medication, and how long will I be on it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Argatroban — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0883 | $0.864 / J0883 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Argatroban 250 mg/2.5mL 00143-9288-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Argatroban 250 mg/2.5mLthis 00143-9674-01 | Hikma | 2.5 ml | — | AP | FDA listed | — |
| Argatroban 250 mg/2.5mL 42023-0182-01 | Par | 1 vial | — | AP | FDA listed | — |
| Argatroban 250 mg/2.5mL 67457-0212-02 | Mylan | 1 vial | — | AP | FDA listed | — |
| Argatroban 100 mg/mL 70121-1037-01 | Amneal | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00143-9674-01 You're viewing this | 2.5 mL in 1 VIAL (0143-9674-01) | 2012-01-05 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Argatroban is a direct thrombin inhibitor indicated: For prophylaxis or treatment of thrombosis in adult patients with heparin-induced thrombocytopenia (HIT) ( 1.1 ) As an anticoagulant in adult patients with or at risk for HIT undergoing percutaneous coronary intervention (PCI) ( 1.2 )
1.1Heparin-Induced Thrombocytopenia Argatroban Injection is indicated for prophylaxis or treatment of thrombosis in adult patients with heparin-induced thrombocytopenia (HIT).
1.2Percutaneous Coronary Intervention Argatroban Injection is indicated as an anticoagulant in adult patients with or at risk for HIT undergoing percutaneous coronary intervention (PCI).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Argatroban Injection 250 mg/2.5 mL (100 mg/mL) must be diluted 100-fold by mixing with 0.9% Sodium Chloride Injection, 5% Dextrose Injection, or Lactated Ringer’s Injection to a final concentration of 1 mg/mL. ( 2.1 ) Argatroban Injection 50 mg/50 mL (1 mg/mL) is ready for intravenous infusion. Dilution is not required.
( 2.1 ) Heparin-Induced Thrombocytopenia The dose for heparin-induced thrombocytopenia without hepatic impairment is 2 mcg/kg/min administered as a continuous infusion. ( 2.2 ) Percutaneous Coronary Intervention The dose for patients with or at risk for heparin-induced thrombocytopenia undergoing percutaneous coronary intervention is started at 25 mcg/kg/min and a bolus of 350 mcg/kg administered via a large bore intravenous line over 3 to 5 minutes. ( 2.3 )
2.1Preparation for Intravenous Administration Argatroban Injection 250 mg/2.5 mL (100 mg/mL) must be diluted 100-fold prior to infusion. Argatroban should not be mixed with other drugs prior to dilution. Dilution is not required for Argatroban Injection 50 mg/50 mL (1 mg/mL).
Argatroban Injection 250 mg/2.5 mL (100 mg/mL) Argatroban 250 mg/2.5 mL (100 mg/mL) should be diluted in 0.9% Sodium Chloride Injection, 5% Dextrose Injection, or Lactated Ringer’s Injection to a final concentration of 1 mg/mL. The contents of each 2.5-mL vial should be diluted 100-fold by mixing with 250 mL of diluent. Use 250 mg (2.5 mL) per 250 mL of diluent or 500 mg (5 mL) per 500 mL of diluent.
The constituted solution must be mixed by repeated inversion of the diluent bag for 1 minute. Upon preparation, the solution may show slight but brief haziness due to the formation of microprecipitates that rapidly dissolve upon mixing. Use of diluent at room temperature is recommended.
Colder temperatures can slow down the rate of dissolution of precipitates. The final solution must be clear before use. The pH of the intravenous solution prepared as recommended is 3.2 to 7.5.
Solutions prepared as recommended are stable at controlled room temperature, 20º to 25ºC (68º to 77ºF) (see USP) in ambient indoor light for 24 hours; therefore, light-resistant measures such as foil protection for intravenous lines are unnecessary. Solutions are physically and chemically stable for up to 96 hours when protected from light and stored at controlled room temperature, 20º to 25ºC (68º to 77ºF) (see USP) or at refrigerated conditions, 5º±3ºC (41º±5ºF). Prepared solutions should not be exposed to direct sunlight.
No significant potency losses have been noted following simulated delivery of the solution through intravenous tubing. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit. Argatroban Injection 50 mg/50 mL (1 mg/mL) Each 50 mL glass vial contains 50 mg argatroban (1 mg/mL); and, as supplied, is ready for intravenous infusion.
Dilution is not required. Argatroban Injection is a clear, colorless to pale yellow solution. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit.
Do not use if solution is cloudy, contains precipitates, or if the flip top cap is not intact. Vial may be inverted for use with a medical infusion set.
2.2Dosing in Patients with Heparin-Induced Thrombocytopenia Initial Dosage Before administering argatroban, discontinue heparin therapy and obtain a baseline activated partial thromboplastin time (aPTT). The recommended initial dose of argatroban for adult patients without hepatic impairment is 2 mcg/kg/min, administered as a continuous infusion (see Table 1). Table 1 Recommended Doses and Infusion Rates for 2 mcg/kg/min Dose of Argatroban for Patients With HIT* and Without Hepatic Impairment (1 mg/mL Final Concentration) Body Weight (kg) Dose (mcg/min) Infusion Rate (mL/hr) 50 100 6 60 120 7 70 140 8 80 160 10 90 180 11 100 200 12 110 220 13 1…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 250 mg/2.5 mL (100 mg/mL) single-dose vial Injection: 50 mg/50 mL (1 mg/mL) ready for intravenous infusion single-dose vial Injection: 250 mg/2.5 mL (100 mg/mL) single-dose vial. (3) Injection: 50 mg/50 mL (1 mg/mL) ready for intravenous infusion single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Argatroban is contraindicated in: Patients with major bleeding, [see Warnings and Precautions (5.1) ] Patients with a history of hypersensitivity to argatroban. Airway, skin, and generalized hypersensitivity reactions have been reported [see Adverse Reactions (6.1) ] Major bleeding (4) History of hypersensitivity to this product (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hemorrhage can occur. Unexplained fall in hematocrit or blood pressure may indicate hemorrhage. ( 5.1 ) Hepatic impairment: Adjust starting dose and titrate carefully in patients with HIT who have moderate or severe hepatic impairment. Avoid use in PCI in patients with clinically significant hepatic impairment. ( 5.2 )
5.1Risk of Hemorrhage Hemorrhage can occur at any site in the body in patients receiving argatroban. Unexplained fall in hematocrit or blood pressure may indicate hemorrhage. Intracranial and retroperitoneal hemorrhage [ see Adverse Reactions (6.1 )] have been reported.
The risk of hemorrhage with argatroban may be increased in severe hypertension; immediately following lumbar puncture, spinal anesthesia, major surgery (especially involving the brain, spinal cord, or eye), hematologic conditions associated with increased bleeding tendencies such as congenital or acquired bleeding disorders, and gastrointestinal lesions such as ulcerations. Concomitant use of argatroban with antiplatelet agents, thrombolytics, and other anticoagulants may increase the risk of bleeding.
5.2Use in Hepatic Impairment When administering argatroban to patients with hepatic impairment, start with a lower dose and carefully titrate until the desired level of anticoagulation is achieved. Achievement of steady state aPTT levels may take longer and require more argatroban dose adjustments in patients with hepatic impairment compared to patients with normal hepatic function [see Use in Specific Populations (8.6) ] . Also, upon cessation of argatroban infusion in the hepatically impaired patient, full reversal of anticoagulant effects may require longer than 4 hours due to decreased clearance and increased elimination half-life of argatroban [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) ].
Avoid the use of high doses of argatroban in patients undergoing PCI who have clinically significant hepatic disease or AST/ALT levels ≥3 times the upper limit of normal.
5.3Laboratory Tests Anticoagulation effects associated with argatroban infusion at doses up to 40 mcg/kg/min correlate with increases of the aPTT. Although other global clot-based tests including prothrombin time (PT), the International Normalized Ratio (INR), and thrombin time (TT) are affected by argatroban, the therapeutic ranges for these tests have not been identified for argatroban therapy. In clinical trials in PCI, the ACT was used for monitoring argatroban anticoagulant activity during the procedure.
The concomitant use of argatroban and warfarin results in prolongation of the PT and INR beyond that produced by warfarin alone [ see Dosage and Administration (2.5) , Clinical Pharmacology (12.2) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reaction is also discussed in other sections of the labeling: Risk of Hemorrhage [see Warnings and Precautions (5.1) ] . HIT patients: The most common (>5%) adverse reactions were dyspnea, hypotension, fever, diarrhea, sepsis, and cardiac arrest. (6.1) PCI patients: The most common (>5%) adverse reactions were chest pain, hypotension, back pain, nausea, vomiting and headache.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Hikma Pharmaceuticals USA Inc. at 1-877-233-2001 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Adverse Reactions in Patients with HIT (With or Without Thrombosis) Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The following safety information is based on all 568 patients treated with argatroban in Study 1 and Study 2. The safety profile of the patients from these studies is compared with that of 193 historical controls in which the adverse reactions were collected retrospectively.
Adverse reactions are separated into hemorrhagic and non-hemorrhagic reactions. Major bleeding was defined as bleeding that was overt and associated with a hemoglobin decrease ≥ 2 g/dL, that led to a transfusion of ≥ 2 units, or that was intracranial, retroperitoneal, or into a major prosthetic joint. Minor bleeding was overt bleeding that did not meet the criteria for major bleeding.
Table 4 gives an overview of the most frequently observed hemorrhagic reactions, presented separately by major and minor bleeding, sorted by decreasing occurrence among argatroban-treated patients with HIT (with or without thrombosis). Table 4 Major and Minor Hemorrhagic Adverse Reactions in Patients With HIT* Major Hemorrhagic Reactions a Argatroban-treated Patients (Study 1 and Study 2) (n = 568) % Historical Control c (n = 193) % Overall bleeding 5.3
6.7Gastrointestinal 2.3
1.6Genitourinary and hematuria 0.9
0.5Decrease in hemoglobin and hematocrit 0.7 0 Multisystem hemorrhage and DIC 0.5 1 Limb and BKA stump 0.5 0 Intracranial hemorrhage 0 b
0.5Minor Hemorrhagic Reactions a Argatroban-treated Patients (Study 1 and Study 2) (n = 568) % Historical Control c (n = 193) % Gastrointestinal 14.4
18.1Genitourinary and hematuria 11.6
0.8Decrease in hemoglobin and hematocrit 10.4 0 Groin 5.4
3.1Hemoptysis 2.9
0.8Brachial 2.4 0.8 * with or without thrombosis a) Patients may have experienced more than 1 adverse reaction. b) One patient experienced intracranial hemorrhage 4 days after discontinuation of argatroban and following therapy with urokinase and oral anticoagulation. c) The historical control group consisted of patients with a clinical diagnosis of HIT (with or without thrombosis) that were considered eligible by an independent medical panel. DIC = disseminated intravascular coagulation. BKA = below the knee amputation.
Table 5 gives an overview of the most frequently observed non-hemorrhagic reactions sorted by decreasing frequency of occurrence (≥2%) among argatroban-treated HIT/HITTS patients. Table 5 Non-hemorrhagic Adverse Reactions in Patients a With HIT b Argatroban-treated Patients (Study 1 and Study 2) (n = 568) % Historical Control c (n = 193) % Dyspnea 8.1
8.8Hypotension 7.2
2.6Fever 6.9
2.1Diarrhea 6.2
1.6Sepsis 6.0
12.4Cardiac arrest 5.8
3.1Nausea 4.8
0.5Ventricular tachycardia 4.8
3.1Pain 4.6
3.1Urinary tract infection 4.6
5.2Vomiting 4.2 0 Infection 3.7
3.6Pneumonia 3.3
9.3Atrial fibrillation 3.0
11.4Coughing 2.8
1.6Abnormal renal function 2.8
4.7Abdominal pain 2.6
1.6Cerebrovascular disorder 2.3 4.1 a) Patients may have experienced more than 1 adverse reaction. b) With or without thrombosis c) The historical control group consisted of patients with a clinical diagnosis of HIT (with or without thrombosis) that were con…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Heparin: Allow sufficient time for heparin’s effect on activated partial thromboplastin time (aPTT) to decrease before initiating Argatroban Injection therapy. ( 7.1 ) Warfarin: Concomitant use results in increased prolongation of PT and INR. ( 7.2 ) Thrombolytic agents or glycoprotein IIb/IIIa antagonists: Safety and effectiveness of concomitant use with argatroban have not been established. ( 7.4 , 7.5 )
7.1Heparin If argatroban is to be initiated after cessation of heparin therapy, allow sufficient time for heparin’s effect on the aPTT to decrease prior to initiation of argatroban therapy.
7.2Oral Anticoagulant Agents Pharmacokinetic drug-drug interactions between argatroban and warfarin (7.5 mg single oral dose) have not been demonstrated. However, the concomitant use of argatroban and warfarin (5 to 7.5 mg initial oral dose, followed by 2.5 to 6 mg/day orally for 6 to 10 days) results in prolongation of the prothrombin time (PT) and International Normalized Ratio (INR) [see Dosage and Administration (2.5 ) and Clinical Pharmacology (12.2) ].
7.3Aspirin/Acetaminophen No drug-drug interactions have been demonstrated between argatroban and concomitantly administered aspirin or acetaminophen [ see Clinical Pharmacology (12.3) ].
7.4Thrombolytic Agents The safety and effectiveness of argatroban with thrombolytic agents have not been established [ see Adverse Reactions (6.1) ] .
7.5Glycoprotein IIb/IIIa Antagonists The safety and effectiveness of argatroban with glycoprotein IIb/IIIa antagonists have not been established.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Discontinue nursing or drug, taking into account the importance of the drug to the mother. (8.2) Pediatric Use: Safety and effectiveness have not been established. (8.4)
8.1Pregnancy Risk Summary Limited data from published literature and postmarketing reports do not suggest an association between argatroban and adverse fetal developmental outcomes. There are risks to the mother associated with untreated thrombosis in pregnancy and a risk of hemorrhage in the mother and fetus associated with use of anticoagulants (see Clinical Considerations ) . In animal reproduction studies, there was no evidence of adverse developmental outcomes with intravenous administration of argatroban during organogenesis in rats and rabbits at doses up to 0.3- and 0.2-times, respectively, the maximum recommended human dose (MHRD) (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy. Fetal/Neonatal Adverse Reactions Use of anticoagulants, including argatroban, may increase the risk of bleeding in the fetus and neonate.
Monitor neonates for bleeding [see Warnings and Precautions ( 5.1 , 5.3 )] . L abor or Delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Pregnant women receiving argatroban should be carefully monitored for evidence of excessive bleeding or unexpected changes in coagulation parameters [see Warnings and Precautions ( 5.1 , 5.3 )] .
Data Animal Data Developmental studies performed in rats with argatroban at intravenous doses up to 27 mg/kg/day (0.3 times the maximum recommended human dose, based on body surface area) and in rabbits at intravenous doses up to 10.8 mg/kg/day (0.2 times the maximum recommended human dose, based on body surface area) have revealed no evidence of harm to the fetus.
8.2Lactation R isk Summary There are no data on the presence of argatroban in human milk, or its effects on milk production. Argatroban is present in rat milk. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for argatroban and any potential adverse effects on the breastfed infant from argatroban or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients. Argatroban was studied among 18 seriously ill pediatric patients who required an alternative to heparin anticoagulation. Most patients were diagnosed with HIT or suspected HIT.
Age ranges of patients were <6 months, n = 8; six months to <8 years, n = 6; 8 to 16 years, n = 4. All patients had serious underlying conditions and were receiving multiple concomitant medications. Thirteen patients received argatroban solely as a continuous infusion (no bolus dose).
Dosing was initiated in the majority of these 13 patients at 1 mcg/kg/min. Dosing was titrated as needed to achieve and maintain an aPTT of 1.5 to 3 times the baseline value. Most patients required multiple dose adjustments to maintain anticoagulation parameters within the desired range.
During the 30-day study period, thrombotic events occurred during argatroban administration to two patients and following argatroban discontinuation in three other patients. Major bleeding occurred among two patients: one patient experienced…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited data from published literature and postmarketing reports do not suggest an association between argatroban and adverse fetal developmental outcomes. There are risks to the mother associated with untreated thrombosis in pregnancy and a risk of hemorrhage in the mother and fetus associated with use of anticoagulants (see Clinical Considerations ) . In animal reproduction studies, there was no evidence of adverse developmental outcomes with intravenous administration of argatroban during organogenesis in rats and rabbits at doses up to 0.3- and 0.2-times, respectively, the maximum recommended human dose (MHRD) (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%-4% and 15%-20%, respectively.
Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Pregnancy confers an increased risk for thromboembolism that is higher for women with underlying thromboembolic disease and certain high risk pregnancy conditions. Published data describe that women with a previous history of venous thrombosis are at high risk for recurrence during pregnancy. Fetal/Neonatal Adverse Reactions Use of anticoagulants, including argatroban, may increase the risk of bleeding in the fetus and neonate.
Monitor neonates for bleeding [see Warnings and Precautions ( 5.1 , 5.3 )] . L abor or Delivery All patients receiving anticoagulants, including pregnant women, are at risk for bleeding. Pregnant women receiving argatroban should be carefully monitored for evidence of excessive bleeding or unexpected changes in coagulation parameters [see Warnings and Precautions ( 5.1 , 5.3 )] .
Data Animal Data Developmental studies performed in rats with argatroban at intravenous doses up to 27 mg/kg/day (0.3 times the maximum recommended human dose, based on body surface area) and in rabbits at intravenous doses up to 10.8 mg/kg/day (0.2 times the maximum recommended human dose, based on body surface area) have revealed no evidence of harm to the fetus.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients. Argatroban was studied among 18 seriously ill pediatric patients who required an alternative to heparin anticoagulation. Most patients were diagnosed with HIT or suspected HIT.
Age ranges of patients were <6 months, n = 8; six months to <8 years, n = 6; 8 to 16 years, n = 4. All patients had serious underlying conditions and were receiving multiple concomitant medications. Thirteen patients received argatroban solely as a continuous infusion (no bolus dose).
Dosing was initiated in the majority of these 13 patients at 1 mcg/kg/min. Dosing was titrated as needed to achieve and maintain an aPTT of 1.5 to 3 times the baseline value. Most patients required multiple dose adjustments to maintain anticoagulation parameters within the desired range.
During the 30-day study period, thrombotic events occurred during argatroban administration to two patients and following argatroban discontinuation in three other patients. Major bleeding occurred among two patients: one patient experienced an intracranial hemorrhage after 4 days of argatroban therapy in the setting of sepsis and thrombocytopenia and another patient experienced an intracranial hemorrhage after receiving argatroban for greater than 14 days. The study findings did not establish the safe and effective use of argatroban in pediatric patients and the dosing of 1 mcg/kg/min was not supported by the pharmacokinetic data described below.
Pediatric Pharmacokinetics (PK) and Pharmacodynamics (PD) PK parameters of argatroban were characterized in population PK/PD analysis model with sparse data from 15 seriously ill pediatric patients. Argatroban clearance in these seriously ill pediatric patients (0.16 L/hr/kg) was 50% lower compared to argatroban clearance in healthy adults (0.31 L/hr/kg). Four pediatric patients with elevated bilirubin (secondary to cardiac complications or hepatic impairment) had, on average, 80% lower clearance (0.03 L/hr/kg) when compared to pediatric patients with normal bilirubin levels.
These PK/PD analysis models based on a goal of aPTT prolongation of 1.5 to 3 times the baseline value and avoidance of an aPTT >100 seconds for seriously ill pediatric patients with HIT/HITTS who require an alternative to heparin suggested the following: For patients with normal hepatic function , a starting infusion rate of 0.75 mcg/kg/min may have comparable aPTT responses as a starting dose of 2 mcg/kg/min in healthy adults.Additionally, based on an evaluation of aPTT every two hours, increasing the dosage by 0.1 to 0.25 mcg/kg/min could achieve additional aPTT responses.
For patients with hepatic impairment a starting infusion rate of 0.2 mcg/kg/min with increasing dosing by increments of 0.05 mcg/kg/min may have comparable argatroban exposure as expected with adult doses. The safety and effectiveness of argatroban with the above dosing have not been adequately assessed in pediatric patients and the safety and effectiveness of argatroban is not established in pediatric patients. In addition, the described dosage did not take into account multiple factors that could affect the dosage such as current aPTT, target aPTT, and the clinical status of the patient.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects (1340) in clinical studies of argatroban, 35% were 65 and over. In the clinical studies of adult patients with HIT (with or without thrombosis), the effectiveness of argatroban was not affected by age. No trends were observed across age groups for both aPTT and the ACT.
The safety analysis did suggest that older patients had increased underlying conditions, which may predispose them to adverse reactions. The studies were not sized appropriately to detect differences in safety between age groups.
🆘 Overdosage ▾
10 OVERDOSAGE Excessive anticoagulation, with or without bleeding, may be controlled by discontinuing argatroban or by decreasing the argatroban dose. In clinical studies, anticoagulation parameters generally returned from therapeutic levels to baseline within 2 to 4 hours after discontinuation of the drug. Reversal of anticoagulant effect may take longer in patients with hepatic impairment.
No specific antidote to argatroban is available; if life-threatening bleeding occurs and excessive plasma levels of argatroban are suspected, discontinue argatroban immediately and measure aPTT and other coagulation parameters. When argatroban was administered as a continuous infusion (2 mcg/kg/min) prior to and during a 4-hour hemodialysis session, approximately 20% of argatroban was cleared through dialysis. Single intravenous doses of argatroban at 200, 124, 150, and 200 mg/kg were lethal to mice, rats, rabbits, and dogs, respectively.
The symptoms of acute toxicity were loss of righting reflex, tremors, clonic convulsions, paralysis of hind limbs, and coma. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Argatroban is a direct thrombin inhibitor that reversibly binds to the thrombin active site. Argatroban does not require the co-factor antithrombin III for antithrombotic activity. Argatroban exerts its anticoagulant effects by inhibiting thrombin-catalyzed or -induced reactions, including fibrin formation; activation of coagulation factors V, VIII, and XIII; activation of protein C; and platelet aggregation.
Argatroban inhibits thrombin with an inhibition constant (Ki) of 0.04 μM. At therapeutic concentrations, argatroban has little or no effect on related serine proteases (trypsin, factor Xa, plasmin, and kallikrein). Argatroban is capable of inhibiting the action of both free and clot-associated thrombin.
12.2Pharmacodynamics When argatroban is administered by continuous infusion, anticoagulant effects and plasma concentrations of argatroban follow similar, predictable temporal response profiles, with low intersubject variability. Immediately upon initiation of argatroban infusion, anticoagulant effects are produced as plasma argatroban concentrations begin to rise. Steady-state levels of both drug and anticoagulant effect are typically attained within 1 to 3 hours and are maintained until the infusion is discontinued or the dosage adjusted.
Steady-state plasma argatroban concentrations increase proportionally with dose (for infusion doses up to 40 mcg/kg/min in healthy subjects) and are well correlated with steady-state anticoagulant effects. For infusion doses up to 40 mcg/kg/min, argatroban increases in a dose-dependent fashion, the aPTT, ACT, the prothrombin time (PT), the International Normalized Ratio (INR), and the thrombin time (TT) in healthy volunteers and cardiac patients. Representative steady-state plasma argatroban concentrations and anticoagulant effects are shown below for argatroban infusion doses up to 10 mcg/kg/min (see Figure 1).
Figure 1. Relationship at Steady State Between Argatroban Dose, Plasma Argatroban Concentration and Anticoagulant Effect Effect on International Normalized Ratio (INR): Because argatroban is a direct thrombin inhibitor, co-administration of argatroban and warfarin produces a combined effect on the laboratory measurement of the INR. However, concurrent therapy, compared to warfarin monotherapy, exerts no additional effect on vitamin K–dependent factor Xa activity.
The relationship between INR on co-therapy and warfarin alone is dependent on both the dose of argatroban and the thromboplastin reagent used. This relationship is influenced by the International Sensitivity Index (ISI) of the thromboplastin. Data for 2 commonly utilized thromboplastins with ISI values of 0.88 (Innovin, Dade) and 1.78 (Thromboplastin C Plus, Dade) are presented in Figure 2 for an argatroban dose of 2 mcg/kg/min.
Thromboplastins with higher ISI values than shown result in higher INRs on combined therapy of warfarin and argatroban. These data are based on results obtained in normal individuals [see Drug Interactions (7.2) , Dosage and Administration (2.5) , Warnings and Precautions (5.3) ]. Figure 2.
INR Relationship of Argatroban Plus Warfarin Versus Warfarin Alone Figure 2 demonstrates the relationship between INR for warfarin alone and INR for warfarin co-administered with argatroban at a dose of 2 mcg/kg/min. To calculate INR for warfarin alone (INR W ), based on INR for co-therapy of warfarin and argatroban (INR WA ), when the argatroban dose is 2 mcg/kg/min, use the equation next to the appropriate curve. Example: At a dose of 2 mcg/kg/min and an INR performed with Thromboplastin A, the equation 0.19 + 0.57 (INR WA ) = INR W would allow a prediction of the INR on warfarin alone (INR W ).
Thus, using an INR WA value of 4.0 obtained on combined therapy: INR W = 0.19 + 0.57 (4) = 2.47 as the value for INR on warfarin alone. The error (confidence interval) associated with a prediction is ± 0.4 units. Similar linear relationships and prediction errors ex…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Argatroban is a direct thrombin inhibitor that reversibly binds to the thrombin active site. Argatroban does not require the co-factor antithrombin III for antithrombotic activity. Argatroban exerts its anticoagulant effects by inhibiting thrombin-catalyzed or -induced reactions, including fibrin formation; activation of coagulation factors V, VIII, and XIII; activation of protein C; and platelet aggregation.
Argatroban inhibits thrombin with an inhibition constant (Ki) of 0.04 μM. At therapeutic concentrations, argatroban has little or no effect on related serine proteases (trypsin, factor Xa, plasmin, and kallikrein). Argatroban is capable of inhibiting the action of both free and clot-associated thrombin.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Argatroban Injection is available as follows: NDC Strength Packaged 0143-9674-01 250 mg/2.5 mL (100 mg/mL) Single Dose Vial 0143-9559-01 50 mg/50 mL (1 mg/mL) Single Dose Vial Storage and Handling Store the vials in original carton at 20° to 25° C (68° to 77° F) [See USP Controlled Room Temperature]. Do not freeze. Retain in the original carton to protect from light.
If the solution is cloudy, or if an insoluble precipitate is noted, the vial should be discarded.
📋 Description ▾
11 DESCRIPTION Argatroban is a synthetic direct thrombin inhibitor and the chemical name is 1-[5-[(aminoiminomethyl)amino]-1-oxo-2-[[(1,2,3,4-tetrahydro-3-methyl-8- quinolinyl)sulfonyl]amino]pentyl]-4-methyl-2-piperidinecarboxylic acid, monohydrate. Argatroban has 4 asymmetric carbons. One of the asymmetric carbons has an R configuration (stereoisomer Type I) and an S configuration (stereoisomer Type II).
Argatroban consists of a mixture of R and S stereoisomers at a ratio of approximately 65:35. The molecular formula of argatroban is C 23 H 36 N 6 O 5 S•H 2 O. Its molecular weight is 526.66 g/mol.
The structural formula is shown below: Argatroban is a white, odorless crystalline powder that is freely soluble in glacial acetic acid, slightly soluble in ethanol, and insoluble in acetone, ethyl acetate, and ether. Argatroban Injection 250 mg/2.5 mL (100 mg/mL) is a sterile clear, colorless to pale yellow, slightly viscous solution. Argatroban Injection 250 mg/2.5 mL (100 mg/mL) is available in 250-mg (in 2.5-mL) single-dose amber vials, with white flip-top caps.
Each mL of sterile, nonpyrogenic solution contains 100 mg Argatroban. Inert ingredients (per vial): 1300 mg Propylene glycol, 760 mg Dehydrated alcohol. Argatroban Injection 50 mg/50 mL (1 mg/mL) is a sterile clear, colorless to pale yellow, solution.
Argatroban Injection 50 mg/50 mL (1 mg/mL) is available in 50-mg (in 50-mL) single-dose vials, with white flip-top caps. Each mL of sterile, nonpyrogenic solution contains 1 mg Argatroban. Inert ingredients (per vial): 260 mg Propylene glycol, 152 mg Dehydrated alcohol, and 450 mg Sodium Chloride.
Arg chem structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients of the risks associated with Argatroban Injection as well as the plan for regular monitoring during administration of the drug. Specifically, inform patients to report: the use of any other products known to affect bleeding. any medical history that may increase the risk for bleeding, including a history of severe hypertension; recent lumbar puncture or spinal anesthesia; major surgery, especially involving the brain, spinal cord, or eye; hematologic conditions associated with increased bleeding tendencies such as congenital or acquired bleeding disorders and gastrointestinal lesions such as ulcerations. any bleeding signs or symptoms. the occurrence of any signs or symptoms of allergic reactions (e.g., airway reactions, skin reactions and vasodilation reactions).
Manufactured by: Exela Pharma Sciences, LLC Lenoir, NC 28645 Distributed by: Hikma Pharmaceuticals USA Inc. Berkeley Heights, NJ 07922