
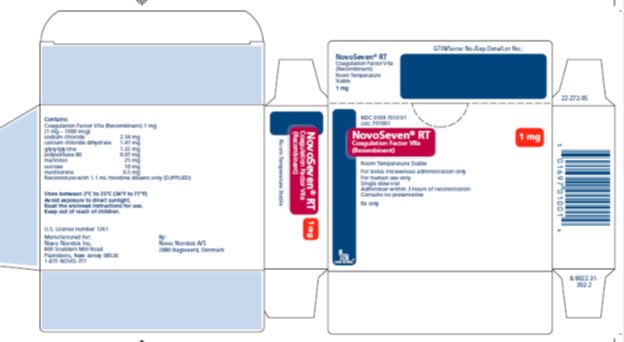
NovoSeven RT Coagulation Factor VIIa (Recombinant) Kit
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| NovoSeven RTthis 00169-7010-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7020-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7040-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7050-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7201-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7202-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7205-01 | Novo | 1 kit | — | — | FDA listed | — |
| NovoSeven RT 00169-7208-01 | Novo | 1 kit | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00169-7010-01 You're viewing this | 1 KIT in 1 KIT (0169-7010-01) * 1 mL in 1 VIAL, GLASS (0169-7017-11) * 1 mL in 1 VIAL, GLASS (0169-7001-98) | 2008-04-30 | Active |
🧭 About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Where does this data come from?
📄 Full FDA label FDA SPL
🚨 Boxed Warning ▾
Warning: Serious thrombotic adverse events are associated with the use of NovoSeven RT outside labeled indications Arterial and venous thrombotic and thromboembolic events following administration of NovoSeven have been reported during postmarketing surveillance. Clinical studies have shown an increased risk of arterial thromboembolic adverse events with NovoSeven RT when administered outside the current approved indications. Fatal and non-fatal thrombotic events have been reported.
Discuss the risks and explain the signs and symptoms of thrombotic and thromboembolic events to patients who will receive NovoSeven RT. Monitor patients for signs or symptoms of activation of the coagulation system and for thrombosis. See WARNINGS AND PRECAUTIONS section of prescribing information.
Safety and efficacy of NovoSeven RT has not been established outside the approved indications. Warning: Serious thrombotic adverse events are associated with the use of NovoSeven RT outside labeled indications Arterial and venous thrombotic and thromboembolic events following administration of NovoSeven have been reported during postmarketing surveillance. Clinical studies have shown an increased risk of arterial thromboembolic adverse events with NovoSeven RT when administered outside the current approved indications.
Fatal and non-fatal thrombotic events have been reported. Discuss the risks and explain the signs and symptoms of thrombotic and thromboembolic events to patients who will receive NovoSeven RT. Monitor patients for signs or symptoms of activation of the coagulation system and for thrombosis.
See WARNINGS AND PRECAUTIONS section of prescribing information. Safety and efficacy of NovoSeven RT has not been established outside the approved indications.
Hemostatic Dosing 90 micrograms/kg given every two hours by bolus infusion until hemostasis is achieved, or until the treatment has been judged to be inadequate. Doses between 35 and 120 micrograms/kg have been used successfully in clinical trials for hemophilia A or B patients with inhibitors, and both the dose and administration interval may be adjusted based on the severity of the bleeding and degree of hemostasis achieved. 1 The minimum effective dose has not been established.
For patients treated for joint or muscle bleeds, a decision on outcome was reached for a majority of patients within eight doses although more doses were required for severe bleeds. A majority of patients who reported adverse experiences received more than twelve doses. Post-hemostatic Dosing The appropriate duration of post-hemostatic dosing has not been studied.
For severe bleeds, dosing should continue at 3-6 hour intervals after hemostasis is achieved, to maintain the hemostatic plug. The biological and clinical effects of prolonged elevated levels of Factor VIIa have not been studied; therefore, the duration of post-hemostatic dosing should be minimized. Patients should be appropriately monitored by a physician experienced in the treatment of hemophilia during this time period.
Minor Surgery An initial dose of 90 micrograms per kg body weight should be given immediately before the intervention and repeated at 2-hour intervals for the duration of the surgery. For minor surgery, post-surgical dosing by bolus injection should occur at 2-hour intervals for the first 48 hours and then at 2- to 6-hour intervals until healing has occurred. Major Surgery An initial dose of 90 micrograms per kg body weight should be given immediately before the intervention and repeated at 2-hour intervals for the duration of the surgery.
For major surgery, post-surgical dosing by bolus injection should occur at 2 hour intervals for 5 days, followed by 4 hour intervals until healing has occurred. Additional bolus doses should be administered if required.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NovoSeven RT Coagulation Factor VIIa (Recombinant) Room Temperature Stable is indicated for: Treatment of bleeding episodes in hemophilia A or B with inhibitors and in acquired hemophilia (1.1) Prevention of bleeding in surgical interventions or invasive procedures in hemophilia A or B with inhibitors and in acquired hemophilia (1.2) Treatment of bleeding episodes in congenital FVII deficiency (1.3) Prevention of bleeding in surgical interventions or invasive procedures in congenital FVII deficiency (1.4)
1.1Treatment of bleeding episodes in hemophilia A or B patients with inhibitors to Factor VIII or Factor IX and in patients with acquired hemophilia
1.2Prevention of bleeding in surgical interventions or invasive procedures in hemophilia A or B patients with inhibitors to Factor VIII or Factor IX and in patients with acquired hemophilia
1.3 Treatment of bleeding episodes in patients with congenital FVII deficiency
1.4Prevention of bleeding in surgical interventions or invasive procedures in patients with congenital FVII deficiency
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For intravenous bolus injection only. After reconstitution, administer within 3 hours; do not freeze or store in syringes (2.6) NovoSeven RT should be administered to patients only under the supervision of a physician experienced in the treatment of bleeding disorders (2.1) Hemophilia A or B with Inhibitors - Bleeding Episodes (2.2) 90 micrograms/kg bolus injection every 2 hours until hemostasis is achieved Post-hemostatic dosing every 3-6 hours for severe bleeds Hemophilia A or B with Inhibitors - Surgery (2.2) 90 micrograms/kg immediately before surgery and every 2 hours during surgery Post-surgical dosing: Minor surgery - 90 micrograms/kg every 2 hours for 48 hours and then every 2-6 hours, until healing has occurred Major sugery - 90 micrograms/kg every 2 hours for the first 5 days and then every 4 hours, until healing has occurred Congenital FVII Deficiency - Bleeding Episodes or Surgery (2.3) 15-30 micrograms/kg every 4-6 hours until hemostasis is achieved Acquired Hemophilia - Bleeding Episodes or Surgery (2.4) 70-90 micrograms/kg every 2-3 hours until hemostasis is achieved
2.1General NovoSeven RT is intended for intravenous bolus administration only. Evaluation of hemostasis should be used to determine the effectiveness of NovoSeven RT and to provide a basis for modification of the NovoSeven RT treatment schedule. Coagulation parameters do not necessarily correlate with or predict the effectiveness of NovoSeven RT.
NovoSeven RT should be administered to patients only under the supervision of a physician experienced in the treatment of bleeding disorders.
2.2Hemophilia A or B with Inhibitors Treatment of Acute Bleeding Episodes Hemostatic Dosing 90 micrograms/kg given every two hours by bolus infusion until hemostasis is achieved, or until the treatment has been judged to be inadequate. Doses between 35 and 120 micrograms/kg have been used successfully in clinical trials for hemophilia A or B patients with inhibitors, and both the dose and administration interval may be adjusted based on the severity of the bleeding and degree of hemostasis achieved. 1 The minimum effective dose has not been established.
For patients treated for joint or muscle bleeds, a decision on outcome was reached for a majority of patients within eight doses although more doses were required for severe bleeds. A majority of patients who reported adverse experiences received more than twelve doses. Post-hemostatic Dosing The appropriate duration of post-hemostatic dosing has not been studied.
For severe bleeds, dosing should continue at 3-6 hour intervals after hemostasis is achieved, to maintain the hemostatic plug. The biological and clinical effects of prolonged elevated levels of Factor VIIa have not been studied; therefore, the duration of post-hemostatic dosing should be minimized. Patients should be appropriately monitored by a physician experienced in the treatment of hemophilia during this time period.
Dosing for Surgical Interventions Minor Surgery An initial dose of 90 micrograms per kg body weight should be given immediately before the intervention and repeated at 2-hour intervals for the duration of the surgery. For minor surgery, post-surgical dosing by bolus injection should occur at 2-hour intervals for the first 48 hours and then at 2- to 6-hour intervals until healing has occurred. Major Surgery An initial dose of 90 micrograms per kg body weight should be given immediately before the intervention and repeated at 2-hour intervals for the duration of the surgery.
For major surgery, post-surgical dosing by bolus injection should occur at 2 hour intervals for 5 days, followed by 4 hour intervals until healing has occurred. Additional bolus doses should be administered if required.
2.3Congenital Factor VII deficiency The recommended dose range for treatment of bleeding episodes or for prevention of bleeding in surgical interventions or invasive procedures in congenital Factor VII deficient patients is 1…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS NovoSeven RT is supplied as a white lyophilized powder in single-use vials containing 1 mg (1000 micrograms), 2 mg (2000 micrograms), or 5 mg (5000 micrograms) rFVIIa per vial. The diluent for reconstitution of NovoSeven RT is a 10 mmol solution of L-histidine in water for injection and is supplied as a clear colorless solution and is referred to as the histidine diluent. After reconstitution with the histidine diluent, each vial contains approximately 1 mg/mL NovoSeven RT (1000 micrograms/mL).
Lyophilized powder in single-use vials: 1, 2, or 5 mg rFVIIa (3) After reconstitution with specified volume of histidine diluent, each vial contains 1 mg/mL (1000 micrograms/mL) of recombinant FVIIa (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Thrombotic events of possible or probable relationship to NovoSeven occurred in 0.28% of bleeding episodes treated in clinical trials within the approved indications. ( 5.1 ) Increased risk of arterial thromboembolic adverse events with use of NovoSeven was demonstrated in 2 meta analyses of placebo-controlled clinical trials in populations outside the approved indications ( 5.2 ) Thrombosis has occurred in women treated with NovoSeven to control post-partum hemorrhage ( 5.2 ) Factor VII deficient patients should be monitored for prothrombin time (PT) and FVII coagulant activity, and for antibody formation to NovoSeven RT ( 5.4 ) Administer with caution in patients with known hypersensitivity ( 5.5 )
5.1Thrombotic Events within the Licensed Indications Clinical trials within the approved indications revealed that thrombotic events of possible or probable relationship to NovoSeven occurred in 0.28% of bleeding episodes treated, with the incidence within hemophilia patients with inhibitors to be 0.20%, and in acquired hemophilia an incidence of 4%. Thrombotic events have been identified through postmarketing surveillance following NovoSeven RT use for each of the approved indications 2 . The incidence of thrombotic events can not be determined from postmarketing data.
Patients with disseminated intravascular coagulation (DIC), advanced atherosclerotic disease, crush injury, septicemia, or concomitant treatment with aPCCs/PCCs (activated or nonactivated prothrombin complex concentrates) have an increased risk of developing thrombotic events due to circulating tissue factor (TF) or predisposing coagulopathy [See Adverse Reactions (6.1) and Drug Interactions (7.1) ]. Caution should be exercised when administering NovoSeven RT to patients with an increased risk of thromboembolic complications.
These include, but are not limited to, patients with a history of coronary heart disease, liver disease, disseminated intravascular coagulation, post-operative immobilization, elderly patients and neonates. In each of these situations, the potential benefit of treatment with NovoSeven RT should be weighed against the risk of these complications . Patients who receive NovoSeven RT should be monitored for development of signs or symptoms of activation of the coagulation system or thrombosis.
When there is laboratory confirmation of intravascular coagulation or presence of clinical thrombosis, the NovoSeven RT dosage should be reduced or the treatment stopped, depending on the patient's symptoms.
5.2Thromboembolic Events outside the Licensed Indications NovoSeven has been studied in placebo controlled trials outside the approved indications to control bleeding in intracerebral hemorrhage, advanced liver disease, trauma, cardiac surgery, spinal surgery, and other therapeutic areas. Safety and effectiveness has not been established in these settings and the use is not approved by FDA. Two meta analyses of these pooled data indicate an increased risk of thrombotic events (10.0% in patients treated with NovoSeven versus 7.5% in placebo-treated patients).
Arterial thromboembolic adverse events including myocardial infarction, myocardial ischemia, cerebral infarction and cerebral ischemia were statistically significantly increased with the use of NovoSeven compared to placebo (5.3 to 5.6% in subjects treated with NovoSeven versus 2.8 to 3.0% in placebo-treated patients). Other arterial thromboembolic events (such as retinal artery embolism, renal artery thrombosis, arterial thrombosis of limb, bowel infarction and intestinal infarction) have also been reported. 3,4,5,6,7 While venous thromboembolic events such as deep venous thrombosis, portal vein thrombosis and pulmonary embolism have been reported in clinical trials, the meta analysis of these pooled data from placebo-controlled trials performed outside the currently approved indications did not suggest an increased risk of venous thromboembolic events in patients treate…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug product cannot be directly compared to rates in clinical trials of another drug, and may not reflect rates observed in practice. In clinical trials, the most common adverse reactions are pyrexia, hemorrhage, injection site reaction, arthralgia, headache, hypertension, hypotension, nausea, vomiting, pain, edema and rash (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Novo Nordisk Inc. at 1-877-668-6777 or FDA at 1-800-FDA-1088, or www.fda.gov/medwatch.
6.1Clinical Trials Experience Thrombotic events following the administration of NovoSeven occurred in 0.28% of bleeding episodes treated, with the incidence in acquired hemophilia of 4% and in hemophilia patients of 0.20% in clinical trials within the approved indications. [ See Warnings and Precautions (5.1) ] . Adverse reactions observed in clinical trials for all labeled indications of NovoSeven included pyrexia, hemorrhage, injection site reaction, arthralgia, headache, hypertension, hypotension, nausea, vomiting, pain, edema, rash (including allergic dermatitis and rash erythematous), pruritus, urticaria, hypersensitivity, cerebral artery occlusion, cerebrovascular accident, pulmonary embolism, deep vein thrombosis, angina pectoris, increased levels of fibrin degradation products, disseminated intravascular coagulation and related laboratory findings including elevated levels of D-dimer and AT-III, thrombosis at i.v. site, non-specified thrombosis, thrombophlebitis, superficial thrombophlebitis.
The following sections describe the adverse event profile observed during clinical studies for each of the labeled indications. Hemophilia A or B Patients with Inhibitors Two studies (Studies 1 and 2) are described for hemophilia A or B patients with inhibitors treated for bleeding episodes [ See Clinical Studies (14.1) ] . The table below lists adverse events that were reported in ≥2% of the 298 patients with hemophilia A or B with inhibitors that were treated with NovoSeven for 1,939 bleeding episodes.
The events listed are considered to be at least possibly related or of unknown relationship to NovoSeven administration. Body System Event # of episodes reported (n=1,939 treatments) # of unique patients (n=298 patients) Body as a whole Fever 16 13 Platelets, Bleeding, and Clotting Hemorrhage NOS Fibrinogen plasma decreased 15 10 8 5 Skin and Musculoskeletal Hemarthrosis 14 8 Cardiovascular Hypertension 9 6 Events which were reported in 1% of patients and were considered to be at least possibly or of unknown relationship to NovoSeven administration were: allergic reaction, arthrosis, bradycardia, coagulation disorder, DIC, edema, fibrinolysis increased, headache, hypotension, injection site reaction, pain, pneumonia, prothrombin decreased, pruritus, purpura, rash, renal function abnormal, therapeutic response decreased, and vomiting.
Serious adverse events that were probably or possibly related, or where the relationship to NovoSeven was not specified, occurred in 14 of the 298 patients (4.7%). Six of the 14 patients died of the following conditions: worsening of chronic renal failure, anesthesia complications during proctoscopy, renal failure complicating a retroperitoneal bleed, ruptured abscess leading to sepsis and DIC, pneumonia, and splenic hematoma and gastrointestinal bleeding. Thrombosis was reported in two of the 298 patients with hemophilia.
Surgery Studies Two clinical trials (Studies 3 and 4) were conducted to evaluate the safety and efficacy of NovoSeven administration during and after surgery in hemophilia A or B patients with inhibitors [See Clinical Studies (14.1) ]. In Study 3, six patients experienced serious adverse events: two of these patients had events which were considered probably or possibly related to study medication (acute post-operative hemarthrosis, internal jugular thrombosis). No deaths occ…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Avoid simultaneous use of NovoSeven RT and PCCs/aPCCs (7.1) NovoSeven RT should not be mixed with infusion solutions (7.2)
7.1Coagulation Factor Concentrates The risk of a potential interaction between NovoSeven RT and coagulation factor concentrates has not been adequately evaluated in preclinical or clinical studies. Simultaneous use of activated prothrombin complex concentrates or prothrombin complex concentrates should be avoided.
7.2Infusion Solutions NovoSeven RT should not be mixed with infusion solutions.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Category C. There are no adequate and well-controlled studies in pregnant women. NovoSeven RT should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Treatment of rats and rabbits with NovoSeven in reproduction studies has been associated with mortality at doses up to 6 mg/kg and 5 mg/kg. At 6 mg/kg in rats, the abortion rate was 0 out of 25 litters; in rabbits at 5 mg/kg, the abortion rate was 2 out of 25 litters. Twenty-three out of 25 female rats given 6 mg/kg of NovoSeven gave birth successfully, however, two of the 23 litters died during the early period of lactation.
No evidence of teratogenicity was observed after dosing with NovoSeven.
8.2Labor and Delivery NovoSeven was administered to a FVII deficient patient (25 years of age, 66 kg) during a vaginal delivery (36 micrograms/kg) and during a tubal ligation (90 micrograms/kg). No adverse reactions were reported during labor, vaginal delivery, or the tubal ligation. There are no adequate and well-controlled studies in labor, delivery, and postpartum periods.
In spontaneous reports of women without a prior diagnosis of bleeding disorders receiving NovoSeven for uncontrolled post-partum hemorrhage, thrombotic events were observed. During this period, patients are at increased risk for thrombotic complications. It is not known to what extent NovoSeven contributed to the occurrence of these events.
8.3Nursing Mothers It is not known whether NovoSeven RT is excreted in human milk. Because many drugs are excreted in human milk, and because of the potential for serious adverse reactions in nursing infants, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
8.4Pediatric Use Clinical trials enrolling pediatric patients were conducted with dosing determined according to body weight and not according to age. The safety and effectiveness of NovoSeven RT has not been studied to determine if there are differences among various age groups, from infants to adolescents (0 to 16 years of age).
8.5Geriatric Use Clinical studies of NovoSeven in congenital factor deficiencies did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C. There are no adequate and well-controlled studies in pregnant women. NovoSeven RT should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Treatment of rats and rabbits with NovoSeven in reproduction studies has been associated with mortality at doses up to 6 mg/kg and 5 mg/kg. At 6 mg/kg in rats, the abortion rate was 0 out of 25 litters; in rabbits at 5 mg/kg, the abortion rate was 2 out of 25 litters. Twenty-three out of 25 female rats given 6 mg/kg of NovoSeven gave birth successfully, however, two of the 23 litters died during the early period of lactation.
No evidence of teratogenicity was observed after dosing with NovoSeven.
🧒 Pediatric Use ▾
8.4Pediatric Use Clinical trials enrolling pediatric patients were conducted with dosing determined according to body weight and not according to age. The safety and effectiveness of NovoSeven RT has not been studied to determine if there are differences among various age groups, from infants to adolescents (0 to 16 years of age).
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of NovoSeven in congenital factor deficiencies did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE There are no adequate and well controlled studies to support the safety or efficacy of using higher than labeled doses in the indicated populations. Dose limiting toxicities of NovoSeven RT have not been investigated in clinical trials. The following are examples of accidental overdose.
Congenital Factor VII Deficiency A newborn female with congenital factor VII deficiency was administered an overdose of NovoSeven (single dose: 800 micrograms/kg). Following additional administration of NovoSeven and various plasma products, antibodies against rFVIIa were detected, but no thrombotic complications were reported. A Factor VII deficient male (83 years of age, 111.1 kg) received two doses of 324 micrograms/kg (10-20 times the recommended dose) and experienced a thrombotic event (occipital stroke).
Hemophilia A or B with Inhibitors One hemophilia B patient (16 years of age, 68 kg) received a single dose of 352 micrograms/kg and one hemophilia A patient (2 years of age, 14.6 kg) received doses ranging from 246 micrograms/kg to 986 micrograms/kg on five consecutive days. There were no reported complications in either case.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action NovoSeven RT is recombinant Factor VIIa and, when complexed with tissue factor can activate coagulation Factor X to Factor Xa, as well as coagulation Factor IX to Factor IXa. Factor Xa, in complex with other factors, then converts prothrombin to thrombin, which leads to the formation of a hemostatic plug by converting fibrinogen to fibrin and thereby inducing local hemostasis. This process may also occur on the surface of activated platelets.
12.2Pharmacodynamics The effect of NovoSeven RT upon coagulation in patients with or without hemophilia has been assessed in different model systems. In an in vitro model of tissue-factor-initiated blood coagulation (Figure A) 10 , the addition of rFVIIa increased both the rate and level of thrombin generation in normal and hemophilia A blood, with an effect shown at rFVIIa concentrations as low as 10 nM. In this model, fresh human blood was treated with corn trypsin inhibitor (CTI) to block the contact pathway of blood coagulation.
Tissue factor (TF) was added to initiate clotting in the presence and absence of rFVIIa for both types of blood. In a separate model, and in line with previous reports 11 , escalating doses of rFVIIa in hemophilia plasma demonstrate a dose-dependent increase in thrombin generation (Figure B). In this model, platelet rich normal and hemophilia plasma was adjusted with autologous plasma to 200,000 platelets/microliter.
Coagulation was initiated by addition of tissue factor and CaCl 2 . Thrombin generation was measured in the presence of a thrombin substrate and various added concentrations of rFVIIa. Figure A Figure B
12.3Pharmacokinetics Healthy Subjects The pharmacokinetics of NovoSeven was investigated in 35 healthy Caucasian and Japanese subjects in a dose-escalation study. Subjects were stratified according to gender and ethnic group and dosed with 40, 80 and 160 micrograms/kg NovoSeven 12 . The pharmacokinetics of rFVII were linear over the dose range of 40 to 180 micrograms/kg.
Pharmacokinetics were similar across gender and ethnic groups. Mean steady state volume of distribution ranged from 130 to 165 mL/kg, mean values of clearance ranged from 33 to 37 mL/h x kg, and mean terminal half-life ranged from 3.9 to 6.0 hours. Hemophilia A or B Single-dose pharmacokinetics of NovoSeven (17.5, 35, and 70 micrograms/kg) exhibited dose-proportional behavior in 15 subjects with hemophilia A or B.
13 Factor VII clotting activities were measured in plasma drawn prior to and during a 24-hour period after NovoSeven administration. The median apparent volume of distribution at steady state was 103 mL/kg (range 78-139). Median clearance was 33 mL/kg/hr (range 27-49).
The median residence time was 3.0 hours (range 2.4-3.3), and the t 1/2 was 2.3 hours (range 1.7-2.7). The median in vivo plasma recovery was 44% (30-71%). The products NovoSeven RT and NovoSeven are pharmacokinetically equivalent.
14 In a bolus single-dose pharmacokinetic study, 5 male adults (90 micrograms/kg) and 10 male pediatric (2-12 years) patients (crossover, 90 and 180 micrograms/kg) with severe hemophilia A (10 of 18 subjects had inhibitors) received NovoSeven 15 . The PK of rFVII following 90 and 180 micrograms/kg IV dose in children indicated dose linearity. Based on the FVII:C assay, the terminal half-life of NovoSeven was 2.6 hrs in pediatric patients and 3.1 hrs in adults.
Based on the 90 microgram/kg dose, the total clearance of NovoSeven in adults and children was 2767 ± 385 mL/hr (37.6 ± 13.1 mL/hr/kg) and 1375 ± 396 mL/hr (57.3 ± 9.5 mL/hr/kg), respectively. The volume of distribution at steady state (V ss ) in adults and children was 121 ± 30 and 153 ± 29 mL/kg, respectively. Congenital Factor VII deficiency Single dose pharmacokinetics of NovoSeven in congenital Factor VII deficiency, at doses of 15 and 30 micrograms per kg body weight, showed no significant difference between the two doses used with regard to dose-independent parameter…
🧬 Mechanism of Action ▾
12.1Mechanism of Action NovoSeven RT is recombinant Factor VIIa and, when complexed with tissue factor can activate coagulation Factor X to Factor Xa, as well as coagulation Factor IX to Factor IXa. Factor Xa, in complex with other factors, then converts prothrombin to thrombin, which leads to the formation of a hemostatic plug by converting fibrinogen to fibrin and thereby inducing local hemostasis. This process may also occur on the surface of activated platelets.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING NovoSeven ® RT Coagulation Factor VIIa (Recombinant) Room Temperature Stable is supplied as a white, lyophilized powder in single-use vials, one vial per carton. The vials are made of glass, closed with a latex-free, chlorobutyl rubber stopper, and sealed with an aluminum cap. The vials are equipped with a snap-off polypropylene cap.
The amount of rFVIIa in milligrams and in micrograms is stated on the label as follows: 1 mg per vial (1000 micrograms/vial) NDC 0169-7010-01 2 mg per vial (2000 micrograms/vial) NDC 0169-7020-01 5 mg per vial (5000 micrograms/vial) NDC 0169-7050-01 The diluent for reconstitution of NovoSeven RT is a 10 mmol solution of L-histidine in water for injection and is supplied as a clear colorless solution, and referred to as the histidine diluent. The vials are made of glass closed with a latex-free, chlorobutyl rubber disc, and covered with an aluminum cap.
The closed vials are equipped with a tamper-evident snap-off cap which is made of polypropylene. Prior to reconstitution, keep refrigerated or store between 2-25°C/36-77°F. Do not freeze.
Store protected from light. Do not use past the expiration date. After reconstitution, NovoSeven RT may be stored either at room temperature or refrigerated for up to 3 hours.
Do not freeze reconstituted NovoSeven RT or store it in syringes.
📋 Description ▾
11 DESCRIPTION NovoSeven RT is recombinant human coagulation Factor VIIa (rFVIIa), intended for promoting hemostasis by activating the extrinsic pathway of the coagulation cascade. 9 NovoSeven RT is a vitamin K-dependent glycoprotein consisting of 406 amino acid residues (MW 50 K Dalton). NovoSeven RT is structurally similar to human plasma-derived Factor VIIa.
The gene for human Factor VII is cloned and expressed in baby hamster kidney cells (BHK cells). Recombinant FVII is secreted into the culture media (containing newborn calf serum) in its single-chain form and then proteolytically converted by autocatalysis to the active two-chain form, rFVIIa, during a chromatographic purification process. The purification process has been demonstrated to remove exogenous viruses (MuLV, SV40, Pox virus, Reovirus, BEV, IBR virus).
No human serum or other proteins are used in the production or formulation of NovoSeven RT. NovoSeven RT is supplied as a sterile, white lyophilized powder of rFVIIa in single-use vials. Each vial of lyophilized drug contains the following: Contents 1 mg Vial 2 mg Vial 5 mg Vial rFVIIa 1000 micrograms 2000 micrograms 5000 micrograms sodium chloride* 2.34 mg 4.68 mg 11.7 mg calcium chloride dihydrate* 1.47 mg 2.94 mg 7.35 mg glycylglycine 1.32 mg 2.64 mg 6.60 mg polysorbate 80 0.07 mg 0.14 mg 0.35 mg mannitol 25 mg 50 mg 125 mg Sucrose 10 mg 20 mg 50 mg Methionine 0.5 mg 1.0 mg 2.5 mg * per mg of rFVIIa: 0.4 mEq sodium, 0.01 mEq calcium The diluent for reconstitution of NovoSeven RT is a 10 mmol solution of histidine in water for injection and is supplied as a clear colorless solution.
After reconstitution with the appropriate volume of histidine diluent, each vial contains approximately 1 mg/mL NovoSeven RT (corresponding to 1000 micrograms/mL). The reconstituted vials have a pH of approximately 6.0 in sodium chloride (2.3 mg/mL), calcium chloride dihydrate (1.5 mg/mL), glycylglycine (1.3 mg/mL), polysorbate 80 (0.1 mg/mL), mannitol (25 mg/mL), sucrose (10 mg/mL), methionine (0.5 mg/mL), and histidine (1.6 mg/mL). The reconstituted product is a clear colorless solution which contains no preservatives.
NovoSeven RT contains trace amounts of proteins derived from the manufacturing and purification processes such as mouse IgG (maximum of 1.2 ng/mg), bovine IgG (maximum of 30 ng/mg), and protein from BHK-cells and media (maximum of 19 ng/mg).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients receiving NovoSeven RT should be informed of the benefits and risks associated with treatment. Patients should be warned about the early signs of hypersensitivity reactions, including hives, urticaria, tightness of the chest, wheezing, hypotension, and anaphylaxis. Patients should also be warned about the signs of thrombosis, including new onset swelling and pain in the limbs or abdomen, new onset chest pain, shortness of breath, loss of sensation or motor power, or altered consciousness or speech.
Patients should be told to immediately seek medical help if any of the above signs or symptoms occur. Date of issue: January 15, 2010 Version: 3 License Number: 1261 Novo Nordisk ® is a registered trademark of Novo Nordisk A/S. NovoSeven ® is a registered trademark of Novo Nordisk Health Care AG. ©1998-2010 Novo Nordisk A/S.
U.S. Patent No. 4,784,950 For information contact: Novo Nordisk Inc.
100 College Road West Princeton, NJ 08540, USA 1-877-NOVO-777 www.NovoSevenRT.com Manufactured by: Novo Nordisk A/S 2880 Bagsvaerd, Denmark