
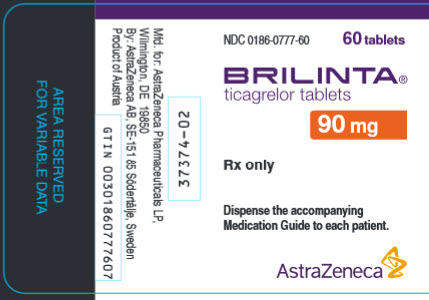
BRILINTA Ticagrelor 90 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the P2Y12 Platelet Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Because of how quickly your body clears ticagrelor — its half-life is only about 7 hours — twice-daily dosing is needed to keep enough of the drug in your system to protect you aro...
- Why do I have to take ticagrelor twice a day — can I just take it once?
- Shortness of breath is actually one of the more common side effects of ticagrelor — roughly 1 in 7 people experience it. The good news is it's usually mild to moderate, it doesn't...
- I've been feeling short of breath since I started ticagrelor. Should I be worried?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ticagrelor — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII O7TSZ97GEP
A mineral compound that serves as a filler and binding agent in tablets and capsules. It adds bulk to the medicine and helps hold ingredients together during manufacturing.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $7.420 | $741.96 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $7.55 | $754.59 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $7.40 | $740.33 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ticagrelor 90 mg 00378-2215-91 | Mylan | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 00480-2695-06 | Teva | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 11788-0158-01 | AiPing | 100 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 33342-0432-09 | Macleods | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 42658-0115-03 | Hisun | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 50268-0826-01 | AvPAK | 100 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 60505-4452-06 | Apotex | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 60687-0928-57 | American | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 67877-0491-05 | Ascend | 500 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 69452-0509-17 | BIONPHARMA | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Ticagrelor 90 mg 72516-0018-06 | Oryza | 60 tablets | $0.263 | AB | Availability likely | save 96% |
| Brilinta 90 mgthis 00186-0777-39 | AstraZeneca | 100 tablets | $7.420 | AB | Availability likely | — |
| Ticagrelor 90 mg 43547-0657-06 | Solco | 60 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 43598-0480-18 | Dr. | 180 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 46708-0241-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| ticagrelor 90 mg 50228-0522-10 | ScieGen | 1000 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 51407-0861-60 | Golden | 60 tablets | — | AB | FDA listed | — |
| Brilinta 90 mg 55154-9618-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 55488-0543-01 | Changzhou | 60 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 62332-0241-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 69097-0991-03 | Cipla | 60 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 70756-0048-60 | Lifestar | 60 tablets | — | AB | FDA listed | — |
| Brilinta 90 mg 71610-0815-41 | Aphena | 5400 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 71610-0914-41 | Aphena | 5400 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 71610-0958-41 | Aphena | 5400 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 72205-0368-11 | Novadoz | 100 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 73190-0008-60 | AvKARE | 60 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 76282-0550-01 | Exelan | 100 tablets | — | AB | FDA listed | — |
| ticagrelor 90 mg 77771-0522-60 | Radha | 60 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 67296-2268-02 | Redpharm | 7 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 72603-0941-01 | NorthStar | 60 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 53401-0028-42 | Aphena | 1800 tablets | — | AB | FDA listed | — |
| Ticagrelor 90 mg 42385-0994-01 | Laurus | 100 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10300065 ↗ | Method of use | U-2541 | Jan 27, 2036 |
| US 10300065 ↗ | Method of use | U-2541 | Jan 27, 2036 |
| US 10300065 ↗ | Method of use | U-2542 | Jan 27, 2036 |
| US 10300065 ↗ | Method of use | U-2542 | Jan 27, 2036 |
| US 8425934 ↗ | Drug product | — | Apr 17, 2030 |
| US 8425934 ↗ | Drug product | — | Apr 17, 2030 |
| US 8425934*PED ↗ | Drug product | — | Oct 17, 2030 |
| US 8425934*PED ↗ | Drug product | — | Oct 17, 2030 |
| US 10300065*PED ↗ | Drug product | — | Jul 27, 2036 |
| US 10300065*PED ↗ | Drug product | — | Jul 27, 2036 |
Is there a generic version of BRILINTA 90 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00186-0777-08 | 8 TABLET in 1 BOTTLE (0186-0777-08) | — | — | 2011-08-05 | Discontinued by firm |
| 00186-0777-39 You're viewing this | 10 BLISTER PACK in 1 BOX, UNIT-DOSE (0186-0777-39) / 10 TABLET in 1 BLISTER PACK | $7.42 / ea | $741.96 | 2011-08-05 | Active |
| 00186-0777-60 | 60 TABLET in 1 BOTTLE (0186-0777-60) | $7.42 / ea | $445.17 | 2011-08-05 | Active |
This pack has the lowest per-ea cost of the 2 priced pack sizes ($7.42 NADAC).
This pack accounts for about 1.6% of this product's recent Medicaid fills; most go to the 60 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 00186-0777-39?
What is the difference between NDC 00186-0777-39 and NDC 00186-0777-08?
What NDC number is used to bill for this package of BRILINTA Ticagrelor 90 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: BLEEDING RISK • BRILINTA, like other antiplatelet agents, can cause significant, sometimes fatal bleeding ( 5.1 , 6.1 ). • Do not use BRILINTA in patients with active pathological bleeding or a history of intracranial hemorrhage • ( 4.1 , 4.2 ). • Do not start BRILINTA in patients undergoing urgent coronary artery bypass graft surgery (CABG) ( 5.1 , • 6.1 ). • If possible, manage bleeding without discontinuing BRILINTA. Stopping BRILINTA increases the risk of • subsequent cardiovascular events ( 5.2 ). WARNING: BLEEDING RISK See full prescribing information for complete boxed warning. • BRILINTA, like other antiplatelet agents, can cause significant, • sometimes fatal bleeding.
( 5.1 , 6.1 ) • Do not use BRILINTA in patients with active pathological • bleeding or a history of intracranial hemorrhage. ( 4.1 , 4.2 ) • Do not start BRILINTA in patients undergoing urgent coronary • artery bypass graft surgery (CABG). ( 5.1 , 6.1 ) • If possible, manage bleeding without discontinuing BRILINTA. • Stopping BRILINTA increases the risk of subsequent • cardiovascular events.
( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BRILINTA is a P2Y 12 platelet inhibitor indicated • to reduce the risk of cardiovascular (CV) death, myocardial infarction (MI), and stroke in patients with acute coronary syndrome (ACS) or a history of MI. For at least the first 12 months following ACS, it is superior to clopidogrel. BRILINTA also reduces the risk of stent thrombosis in patients who have been stented for treatment of ACS.
(1.1) • to reduce the risk of a first MI or stroke in patients with coronary artery disease (CAD) at high risk for such events. While use is not limited to this setting, the efficacy of BRILINTA was established in a population with type 2 diabetes mellitus (T2DM). (1.2) • to reduce the risk of stroke in patients with acute ischemic stroke (NIH Stroke Scale score ≤5) or high-risk transient ischemic attack (TIA).
(1.3)
1.1Acute Coronary Syndrome or a History of Myocardial Infarction BRILINTA is indicated to reduce the risk of cardiovascular (CV) death, myocardial infarction (MI), and stroke in patients with acute coronary syndrome (ACS) or a history of MI. For at least the first 12 months following ACS, it is superior to clopidogrel. BRILINTA also reduces the risk of stent thrombosis in patients who have been stented for treatment of ACS [see Clinical Studies (14.1) ] .
1.2Coronary Artery Disease but No Prior Stroke or Myocardial Infarction BRILINTA is indicated to reduce the risk of a first MI or stroke in patients with coronary artery disease (CAD) at high risk for such events [see Clinical Studies (14.2) ] . While use is not limited to this setting, the efficacy of BRILINTA was established in a population with type 2 diabetes mellitus (T2DM).
1.3Acute Ischemic Stroke or Transient Ischemic Attack (TIA) BRILINTA is indicated to reduce the risk of stroke in patients with acute ischemic stroke (NIH Stroke Scale score ≤5) or high-risk transient ischemic attack (TIA) [see Clinical Studies (14.3) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • ACS or History of MI • Initiate treatment with 180 mg oral loading dose of BRILINTA. Then administer 90 mg twice daily during the first year. After one year, administer 60 mg twice daily.
( 2.2 ) • Patients with CAD and No Prior Stroke or MI • Administer 60 mg BRILINTA twice daily. ( 2.3 ) • Acute Ischemic Stroke • Initiate treatment with a 180 mg loading dose of BRILINTA then continue with 90 mg twice daily for up to 30 days. ( 2.4 ) Use BRILINTA with a daily maintenance dose of aspirin of 75-100 mg.
(2 ) However, in patients who have undergone PCI, consider single antiplatelet therapy with BRILINTA based on the evolving risk for thrombotic versus bleeding events. ( 2.2 )
2.1General Instructions Advise patients who miss a dose of BRILINTA to take their next dose at its scheduled time. For patients who are unable to swallow tablets whole, BRILINTA tablets can be crushed, mixed with water, and drunk. The mixture can also be administered via a nasogastric tube (CH8 or greater) [see Clinical Pharmacology (12.3) ].
Do not administer BRILINTA with another oral P2Y 12 platelet inhibitor. Avoid aspirin at doses higher than recommended [see Clinical Studies (14.1) ].
2.2Acute Coronary Syndrome or a History of Myocardial Infarction Initiate treatment with a 180 mg loading dose of BRILINTA. Administer the first 90 mg maintenance dose of BRILINTA, 6 to 12 hours after the loading dose. Administer 90 mg of BRILINTA twice daily during the first year after an ACS event.
After one year, administer 60 mg of BRILINTA twice daily. Initiate BRILINTA with a daily maintenance dose of aspirin of 75 mg to 100 mg. However, in patients who have undergone percutaneous coronary intervention (PCI), consider single antiplatelet therapy with BRILINTA based on the evolving risk for thrombotic versus bleeding events [see Warnings and Precautions (5.1) and Clinical Studies (14) ].
2.3Coronary Artery Disease but No Prior Stroke or Myocardial Infarction Administer 60 mg of BRILINTA twice daily. Generally, use BRILINTA with a daily maintenance dose of aspirin of 75 mg to 100 mg [see Clinical Studies (14) ].
2.4Acute Ischemic Stroke or Transient Ischemic Attack (TIA) Initiate treatment with a 180 mg loading dose of BRILINTA and then continue with 90 mg twice daily for up to 30 days. Administer the first maintenance dose 6 to 12 hours after the loading dose. Use BRILINTA with a loading dose of aspirin (300 mg to 325 mg) and a daily maintenance dose of aspirin of 75 mg to 100 mg [see Clinical Studies (14) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS BRILINTA (ticagrelor) 90 mg is supplied as a round, biconvex, yellow, film-coated tablet marked with a “90” above “T” on one side. BRILINTA (ticagrelor) 60 mg is supplied as a round, biconvex, pink, film-coated tablet marked with “60” above “T” on one side. • 60 mg and 90 mg tablets (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS • History of intracranial hemorrhage. (4.1) • Active pathological bleeding. (4.2) • Hypersensitivity to ticagrelor or any component of the product. (4.3)
4.1History of Intracranial Hemorrhage BRILINTA is contraindicated in patients with a history of intracranial hemorrhage (ICH) because of a high risk of recurrent ICH in this population [see Clinical Studies (14.1) , (14.2) ].
4.2Active Bleeding BRILINTA is contraindicated in patients with active pathological bleeding such as peptic ulcer or intracranial hemorrhage [see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ] .
4.3Hypersensitivity BRILINTA is contraindicated in patients with hypersensitivity (e.g., angioedema) to ticagrelor or any component of the product.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Dyspnea was reported more frequently with BRILINTA than with control agents in clinical trials. Dyspnea from BRILINTA is self-limiting. (5.3) • Severe Hepatic Impairment: Likely increase in exposure to ticagrelor.
(5.6) • Laboratory Test Interference: False negative platelet functional test results have been reported for Heparin Induced Thrombocytopenia (HIT). BRILINTA is not expected to impact PF4 antibody testing for HIT. (5.8)
5.1Risk of Bleeding Drugs that inhibit platelet function including BRILINTA increase the risk of bleeding [see Warnings and Precautions (5.2) and Adverse Reactions (6.1) ]. Patients treated for acute ischemic stroke or TIA Patients at NIHSS >5 and patients receiving thrombolysis were excluded from THALES and use of BRILINTA in such patients is not recommended.
5.2Discontinuation of BRILINTA in Patients Treated for Coronary Artery Disease Discontinuation of BRILINTA will increase the risk of myocardial infarction, stroke, and death in patients being treated for coronary artery disease. If BRILINTA must be temporarily discontinued (e.g., to treat bleeding or for significant surgery), restart it as soon as possible. When possible, interrupt therapy with BRILINTA for five days prior to surgery that has a major risk of bleeding.
Resume BRILINTA as soon as hemostasis is achieved.
5.3Dyspnea In clinical trials, about 14% (PLATO and PEGASUS) to 21% (THEMIS) of patients treated with BRILINTA developed dyspnea. Dyspnea was usually mild to moderate in intensity and often resolved during continued treatment but led to study drug discontinuation in 0.9% (PLATO), 1.0% (THALES), 4.3% (PEGASUS), and 6.9% (THEMIS) of patients. In a substudy of PLATO, 199 subjects underwent pulmonary function testing irrespective of whether they reported dyspnea.
There was no indication of an adverse effect on pulmonary function assessed after one month or after at least 6 months of chronic treatment. If a patient develops new, prolonged, or worsened dyspnea that is determined to be related to BRILINTA, no specific treatment is required; continue BRILINTA without interruption if possible. In the case of intolerable dyspnea requiring discontinuation of BRILINTA, consider prescribing another antiplatelet agent.
5.4Bradyarrhythmias BRILINTA can cause ventricular pauses [see Adverse Reactions (6.1) ]. Bradyarrhythmias including AV block have been reported in the postmarketing setting. Patients with a history of sick sinus syndrome, 2 nd or 3 rd degree AV block or bradycardia-related syncope not protected by a pacemaker were excluded from clinical studies and may be at increased risk of developing bradyarrhythmias with ticagrelor.
5.5Severe Hepatic Impairment Avoid use of BRILINTA in patients with severe hepatic impairment. Severe hepatic impairment is likely to increase serum concentration of ticagrelor. There are no studies of BRILINTA patients with severe hepatic impairment [see Clinical Pharmacology (12.3)] .
5.6Central Sleep Apnea Central sleep apnea (CSA) including Cheyne-Stokes respiration (CSR) has been reported in the post-marketing setting in patients taking ticagrelor, including recurrence or worsening of CSA/CSR following rechallenge. If central sleep apnea is suspected, consider further clinical assessment.
5.7Laboratory Test Interferences False negative functional tests for Heparin Induced Thrombocytopenia (HIT) BRILINTA has been reported to cause false negative results in platelet functional tests (including the heparin-induced platelet aggregation (HIPA) assay) for patients with Heparin Induced Thrombocytopenia (HIT). This is related to inhibition of the P2Y 12 -receptor on the healthy donor platelets in the test by ticagrelor in the affected patient’s serum/plasma. Information on concomitant treatment with BRILINTA is required for interpretation of HIT functional tests.
Based on the mechanism of BRILINTA interference, BRILINTA is not expected to impact PF4 antibody testing for HIT.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are also discussed elsewhere in the labeling: • Bleeding [see Warnings and Precautions (5.1) ] • Dyspnea [see Warnings and Precautions (5.3) ] Most common adverse reactions (>5%) are bleeding and dyspnea. (5.1 , 5.3 , 6.1) To report SUSPECTED ADVERSE REACTIONS, contact AstraZeneca at 1-800-236-9933 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. BRILINTA has been evaluated for safety in more than 58,000 patients. Bleeding in PLATO (Reduction in risk of thrombotic events in ACS) Figure 1 is a plot of time to the first non-CABG major bleeding event.
Figure 1 - Kaplan-Meier estimate of time to first non-CABG PLATO-defined major bleeding event (PLATO) Frequency of bleeding in PLATO is summarized in Tables 1 and 2. About half of the non-CABG major bleeding events were in the first 30 days. Table 1 - Non-CABG related bleeds (PLATO) BRILINTA 90 mg BID N=9235 Clopidogrel N=9186 n (%) patients with event n (%) patients with event PLATO Major + Minor 713 (7.7) 567 (6.2) Major 362 (3.9) 306 (3.3) Fatal/Life-threatening 171 (1.9) 151 (1.6) Fatal 15 (0.2) 16 (0.2) Intracranial hemorrhage (Fatal/Life-threatening) 26 (0.3) 15 (0.2) PLATO Minor bleed: requires medical intervention to stop or treat bleeding.
PLATO Major bleed: any one of the following: fatal; intracranial; intrapericardial with cardiac tamponade; hypovolemic shock or severe hypotension requiring intervention; significantly disabling (e.g., intraocular with permanent vision loss); associated with a decrease in Hb of at least 3 g/dL (or a fall in hematocrit (Hct) of at least 9%); transfusion of 2 or more units. PLATO Major bleed, fatal/life-threatening: any major bleed as described above and associated with a decrease in Hb of more than 5 g/dL (or a fall in hematocrit (Hct) of at least 15%); transfusion of 4 or more units.
Fatal: A bleeding event that directly led to death within 7 days. No baseline demographic factor altered the relative risk of bleeding with BRILINTA compared to clopidogrel. In PLATO, 1584 patients underwent CABG surgery.
The percentages of those patients who bled are shown in Figure 2 and Table 2. Figure 2 - ‘Major fatal/life-threatening’ CABG-related bleeding by days from last dose of study drug to CABG procedure (PLATO) X-axis is days from last dose of study drug prior to CABG. The PLATO protocol recommended a procedure for withholding study drug prior to CABG or other major surgery without unblinding.
If surgery was elective or non-urgent, study drug was interrupted temporarily, as follows: If local practice was to allow antiplatelet effects to dissipate before surgery, capsules (blinded clopidogrel) were withheld 5 days before surgery and tablets (blinded ticagrelor) were withheld for a minimum of 24 hours and a maximum of 72 hours before surgery. If local practice was to perform surgery without waiting for dissipation of antiplatelet effects capsules and tablets were withheld 24 hours prior to surgery and use of aprotinin or other hemostatic agents was allowed.
If local practice was to use IPA monitoring to determine when surgery could be performed both the capsules and tablets were withheld at the same time and the usual monitoring procedures followed. T Ticagrelor; C Clopidogrel. Table 2 - CABG-related bleeding (PLATO) BRILINTA 90 mg BID N=770 Clopidogrel N=814 n (%) patients with event n (%) patients with event PLATO Total Major 626 (81.3) 666 (81.8) Fatal/Life-threatening 337 (43.8) 350 (43.0) Fatal 6 (0.8) 7 (0.9) PLATO Major bleed : any one of the following: fatal; intracranial; intrapericardial with cardiac tamponade; hypovolemic shock or severe hypotension requiring intervention; significantly disabling…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Avoid use with strong CYP3A inhibitors or CYP3A inducers. (7.1 , 7.2) • Opioids: Decreased exposure to ticagrelor. Consider use of parenteral anti-platelet agent.
( 7.3 ) • Patients receiving more than 40 mg per day of simvastatin or lovastatin may be at increased risk of statin-related adverse effects. ( 7.4 ) • Rosuvastatin plasma concentrations may increase. Monitor for statin-related adverse effects.
( 7.4 ) • Monitor digoxin levels with initiation of or any change in BRILINTA. ( 7.5 )
7.1Strong CYP3A Inhibitors Strong CYP3A inhibitors substantially increase ticagrelor exposure and so increase the risk of dyspnea, bleeding, and other adverse events. Avoid use of strong inhibitors of CYP3A (e.g., ketoconazole, itraconazole, voriconazole, clarithromycin, nefazodone, ritonavir, saquinavir, nelfinavir, indinavir, atazanavir and telithromycin) [see Clinical Pharmacology (12.3) ] .
7.2Strong CYP3A Inducers Strong CYP3A inducers substantially reduce ticagrelor exposure and so decrease the efficacy of ticagrelor. Avoid use with strong inducers of CYP3A (e.g., rifampin, phenytoin, carbamazepine and phenobarbital) [see Clinical Pharmacology (12.3) ] .
7.3Opioids As with other oral P2Y 12 inhibitors, co-administration of opioid agonists delay and reduce the absorption of ticagrelor and its active metabolite presumably because of slowed gastric emptying [see Clinical Pharmacology (12.3) ] . Consider the use of a parenteral anti-platelet agent in acute coronary syndrome patients requiring co-administration of morphine or other opioid agonists.
7.4Simvastatin, Lovastatin, Rosuvastatin BRILINTA increases serum concentrations of simvastatin and lovastatin because these drugs are metabolized by CYP3A4. Avoid simvastatin and lovastatin doses greater than 40 mg [ see Clinical Pharmacology (12.3) ]. Brilinta increases serum concentration of rosuvastatin because rosuvastatin is a BCRP substrate [see Clinical Pharmacology (12.3) ].
7.5Digoxin BRILINTA inhibits the P-glycoprotein transporter; monitor digoxin levels with initiation of or change in BRILINTA therapy [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Breastfeeding not recommended. (8.2)
8.1Pregnancy Risk Summary Available data from case reports with BRILINTA use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Ticagrelor given to pregnant rats and pregnant rabbits during organogenesis caused structural abnormalities in the offspring at maternal doses about 5 to 7 times the maximum recommended human dose (MRHD) based on body surface area. When ticagrelor was given to rats during late gestation and lactation, pup death and effects on pup growth were seen at approximately 10 times the MRHD ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In reproductive toxicology studies, pregnant rats received ticagrelor during organogenesis at doses from 20 to 300 mg/kg/day. 20 mg/kg/day is approximately the same as the MRHD of 90 mg twice daily for a 60 kg human on a mg/m 2 basis. Adverse outcomes in offspring occurred at doses of 300 mg/kg/day (16.5 times the MRHD on a mg/m 2 basis) and included supernumerary liver lobe and ribs, incomplete ossification of sternebrae, displaced articulation of pelvis, and misshapen/misaligned sternebrae.
At the mid-dose of 100 mg/kg/day (5.5 times the MRHD on a mg/m 2 basis), delayed development of liver and skeleton was seen. When pregnant rabbits received ticagrelor during organogenesis at doses from 21 to 63 mg/kg/day, fetuses exposed to the highest maternal dose of 63 mg/kg/day (6.8 times the MRHD on a mg/m 2 basis) had delayed gall bladder development and incomplete ossification of the hyoid, pubis and sternebrae occurred. In a prenatal/postnatal study, pregnant rats received ticagrelor at doses of 10 to 180 mg/kg/day during late gestation and lactation.
Pup death and effects on pup growth were observed at 180 mg/kg/day (approximately 10 times the MRHD on a mg/m 2 basis). Relatively minor effects such as delays in pinna unfolding and eye opening occurred at doses of 10 and 60 mg/kg (approximately one-half and 3.2 times the MRHD on a mg/m 2 basis).
8.2Lactation Risk Summary There are no data on the presence of ticagrelor or its metabolites in human milk, the effects on the breastfed infant, or the effects on milk production. Ticagrelor and its metabolites were present in rat milk at higher concentrations than in maternal plasma. When a drug is present in animal milk, it is likely that the drug will be present in human milk. Breastfeeding is not recommended during treatment with BRILINTA.
8.4Pediatric Use The safety and effectiveness of BRILINTA have not been established in pediatric patients. Effectiveness was not demonstrated in an adequate and well-controlled study conducted in 101 BRILINTA-treated pediatric patients, aged 2 to <18 for reducing the rate of vaso-occlusive crises in sickle cell disease.
8.5Geriatric Use About half of the patients in PLATO, PEGASUS, THEMIS, and THALES were ≥65 years of age and at least 15% were ≥75 years of age. No overall differences in safety or effectiveness were observed between elderly and younger patients.
8.6Hepatic Impairment Ticagrelor is metabolized by the liver and impaired hepatic function can increase risks for bleeding and other adverse events. Avoid use of BRILINTA in patients with severe hepatic impairment. There is limited experience with BRILINTA in patients with moderate hepatic impairment; consider the risks and benefits of treatment, noting the probable increase in exposure to ticagrelor.
No dosage adjustment is needed in patients with mild hepatic impairment [see Warnings and Precautions (5.5) and Clinical Phar…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from case reports with BRILINTA use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Ticagrelor given to pregnant rats and pregnant rabbits during organogenesis caused structural abnormalities in the offspring at maternal doses about 5 to 7 times the maximum recommended human dose (MRHD) based on body surface area. When ticagrelor was given to rats during late gestation and lactation, pup death and effects on pup growth were seen at approximately 10 times the MRHD ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In reproductive toxicology studies, pregnant rats received ticagrelor during organogenesis at doses from 20 to 300 mg/kg/day. 20 mg/kg/day is approximately the same as the MRHD of 90 mg twice daily for a 60 kg human on a mg/m 2 basis. Adverse outcomes in offspring occurred at doses of 300 mg/kg/day (16.5 times the MRHD on a mg/m 2 basis) and included supernumerary liver lobe and ribs, incomplete ossification of sternebrae, displaced articulation of pelvis, and misshapen/misaligned sternebrae.
At the mid-dose of 100 mg/kg/day (5.5 times the MRHD on a mg/m 2 basis), delayed development of liver and skeleton was seen. When pregnant rabbits received ticagrelor during organogenesis at doses from 21 to 63 mg/kg/day, fetuses exposed to the highest maternal dose of 63 mg/kg/day (6.8 times the MRHD on a mg/m 2 basis) had delayed gall bladder development and incomplete ossification of the hyoid, pubis and sternebrae occurred. In a prenatal/postnatal study, pregnant rats received ticagrelor at doses of 10 to 180 mg/kg/day during late gestation and lactation.
Pup death and effects on pup growth were observed at 180 mg/kg/day (approximately 10 times the MRHD on a mg/m 2 basis). Relatively minor effects such as delays in pinna unfolding and eye opening occurred at doses of 10 and 60 mg/kg (approximately one-half and 3.2 times the MRHD on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BRILINTA have not been established in pediatric patients. Effectiveness was not demonstrated in an adequate and well-controlled study conducted in 101 BRILINTA-treated pediatric patients, aged 2 to <18 for reducing the rate of vaso-occlusive crises in sickle cell disease.
🧓 Geriatric Use ▾
8.5Geriatric Use About half of the patients in PLATO, PEGASUS, THEMIS, and THALES were ≥65 years of age and at least 15% were ≥75 years of age. No overall differences in safety or effectiveness were observed between elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE There is currently no known treatment to reverse the effects of BRILINTA, and ticagrelor is not dialyzable. Treatment of overdose should follow local standard medical practice. Bleeding is the expected pharmacologic effect of overdosing.
If bleeding occurs, appropriate supportive measures should be taken. Platelet transfusion did not reverse the antiplatelet effect of BRILINTA in healthy volunteers and is unlikely to be of clinical benefit in patients with bleeding. Other effects of overdose may include gastrointestinal effects (nausea, vomiting, diarrhea) or ventricular pauses.
Monitor the ECG.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ticagrelor and its major metabolite reversibly interact with the platelet P2Y 12 ADP-receptor to prevent signal transduction and platelet activation. Ticagrelor and its active metabolite are approximately equipotent.
12.2Pharmacodynamics The inhibition of platelet aggregation (IPA) by ticagrelor and clopidogrel was compared in a 6-week study examining both acute and chronic platelet inhibition effects in response to 20 μM ADP as the platelet aggregation agonist. The onset of IPA was evaluated on Day 1 of the study following loading doses of 180 mg ticagrelor or 600 mg clopidogrel. As shown in Figure 5, IPA was higher in the ticagrelor group at all time points.
The maximum IPA effect of ticagrelor was reached at around 2 hours, and was maintained for at least 8 hours. The offset of IPA was examined after 6 weeks on ticagrelor 90 mg twice daily or clopidogrel 75 mg daily, again in response to 20 μM ADP. As shown in Figure 6, mean maximum IPA following the last dose of ticagrelor was 88% and 62% for clopidogrel.
The insert in Figure 6 shows that after 24 hours, IPA in the ticagrelor group (58%) was similar to IPA in clopidogrel group (52%), indicating that patients who miss a dose of ticagrelor would still maintain IPA similar to the trough IPA of patients treated with clopidogrel. After 5 days, IPA in the ticagrelor group was similar to IPA in the placebo group. It is not known how either bleeding risk or thrombotic risk track with IPA, for either ticagrelor or clopidogrel.
Figure 5 - Mean inhibition of platelet aggregation (±SE) following single oral doses of placebo, 180 mg ticagrelor or 600 mg clopidogrel Figure 6 - Mean inhibition of platelet aggregation (IPA) following 6 weeks on placebo, ticagrelor 90 mg twice daily, or clopidogrel 75 mg daily Transitioning from clopidogrel to BRILINTA resulted in an absolute IPA increase of 26.4% and from BRILINTA to clopidogrel resulted in an absolute IPA decrease of 24.5%. Patients can be transitioned from clopidogrel to BRILINTA without interruption of antiplatelet effect [see Dosage and Administration (2) ] . figure_5 figure_6
12.3Pharmacokinetics Ticagrelor demonstrates dose proportional pharmacokinetics, which are similar in patients and healthy volunteers. Absorption BRILINTA can be taken with or without food. Absorption of ticagrelor occurs with a median t max of 1.5 h (range 1.0–4.0).
The formation of the major circulating metabolite AR-C124910XX (active) from ticagrelor occurs with a median t max of 2.5 h (range 1.5-5.0). The mean absolute bioavailability of ticagrelor is about 36% (range 30%-42%). Ingestion of a high-fat meal had no effect on ticagrelor C max , but resulted in a 21% increase in AUC.
The C max of its major metabolite was decreased by 22% with no change in AUC. BRILINTA as crushed tablets mixed in water, given orally or administered through a nasogastric tube into the stomach, is bioequivalent to whole tablets (AUC and C max within 80-125% for ticagrelor and AR-C124910XX) with a median t max of 1.0 hour (range 1.0 – 4.0) for ticagrelor and 2.0 hours (range 1.0 –8.0) for AR-C124910XX. Distribution The steady state volume of distribution of ticagrelor is 88 L.
Ticagrelor and the active metabolite are extensively bound to human plasma proteins (>99%). Metabolism CYP3A4 is the major enzyme responsible for ticagrelor metabolism and the formation of its major active metabolite. Ticagrelor and its major active metabolite are weak P-glycoprotein substrates and inhibitors.
The systemic exposure to the active metabolite is approximately 30-40% of the exposure of ticagrelor. Ticagrelor is a BCRP inhibitor. Excretion The primary route of ticagrelor elimination is hepatic metabolism.
When radiolabeled ticagrelor is administered, the mean recovery of radioactivity is approximately 84% (58% in feces, 26% in urine). Recoveries of ticagrelor and the active metabolite in urine were both less than 1% of the dose. The primary route…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ticagrelor and its major metabolite reversibly interact with the platelet P2Y 12 ADP-receptor to prevent signal transduction and platelet activation. Ticagrelor and its active metabolite are approximately equipotent.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BRILINTA (ticagrelor) 90 mg is supplied as a round, biconvex, yellow, film-coated tablet with a “90” above “T” on one side: Bottles of 60 – NDC 0186-0777-60 100 count Hospital Unit Dose – NDC 0186-0777-39 BRILINTA (ticagrelor) 60 mg is supplied as a round, biconvex, pink, film-coated tablet with a “60” above “T” on one side: Bottles of 60 – NDC 0186-0776-60 Storage and Handling Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F) [see USP controlled room temperature].
📋 Description ▾
11 DESCRIPTION BRILINTA contains ticagrelor, a cyclopentyltriazolopyrimidine, inhibitor of platelet activation and aggregation mediated by the P2Y 12 ADP-receptor. Chemically it is (1 S ,2 S ,3 R ,5 S )-3-[7-{[(1 R ,2 S )-2-(3,4-difluorophenyl)cyclopropyl]amino}-5-(propylthio)-3 H -[1,2,3]-triazolo[4,5- d ]pyrimidin-3-yl]-5-(2-hydroxyethoxy)cyclopentane-1,2-diol. The empirical formula of ticagrelor is C 23 H 28 F 2 N 6 O 4 S and its molecular weight is 522.57.
The chemical structure of ticagrelor is: Ticagrelor is a crystalline powder with an aqueous solubility of approximately 10 μg/mL at room temperature. BRILINTA 90 mg tablets for oral administration contain 90 mg of ticagrelor and the following ingredients: mannitol, dibasic calcium phosphate, sodium starch glycolate, hydroxypropyl cellulose, magnesium stearate, hydroxypropyl methylcellulose, titanium dioxide, talc, polyethylene glycol 400, and ferric oxide yellow. BRILINTA 60 mg tablets for oral administration contain 60 mg of ticagrelor and the following ingredients: mannitol, dibasic calcium phosphate, sodium starch glycolate, hydroxypropyl cellulose, magnesium stearate, hydroxypropyl methylcellulose, titanium dioxide, polyethylene glycol 400, ferric oxide black, and ferric oxide red. chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Advise patients daily doses of aspirin should not exceed 100 mg and to avoid taking any other medications that contain aspirin. Advise patients that they: • Will bleed and bruise more easily • Will take longer than usual to stop bleeding • Should report any unanticipated, prolonged or excessive bleeding, or blood in their stool or urine.
Advise patients to contact their doctor if they experience unexpected shortness of breath, especially if severe. Advise patients to inform physicians and dentists that they are taking BRILINTA before any surgery or dental procedure. Advise women that breastfeeding is not recommended during treatment with BRILINTA [see Use in Specific Populations (8.2) ] .
BRILINTA ® is a trademark of the AstraZeneca group of companies. Distributed by: AstraZeneca Pharmaceuticals LP, Wilmington, DE 19850 © AstraZeneca 2024
💬 Medication Guide ▾
MEDICATION GUIDE BRILINTA® (brih-LIN-tah) (ticagrelor) Tablets What is the most important information I should know about BRILINTA? BRILINTA is used to lower your chance of having, or dying from, a heart attack or stroke. BRILINTA (and similar drugs) can cause bleeding that can be serious and sometimes lead to death.
In cases of serious bleeding, such as internal bleeding, the bleeding may result in the need for blood transfusions or surgery. While you take BRILINTA: • you may bruise and bleed more easily • you are more likely to have nose bleeds • it will take longer than usual for any bleeding to stop Call your healthcare provider right away, if you have any of these signs or symptoms of bleeding while taking BRILINTA: • bleeding that is severe or that you cannot control • pink, red or brown urine • vomiting blood or your vomit looks like “coffee grounds” • red or black stools (looks like tar) • coughing up blood or blood clots Do not stop taking BRILINTA without talking to the healthcare provider who prescribes it for you.
People who are treated with a stent, and stop taking BRILINTA too soon, have a higher risk of getting a blood clot in the stent, having a heart attack, or dying. If you stop BRILINTA because of bleeding, or for other reasons, your risk of a heart attack or stroke may increase. Your healthcare provider may instruct you to stop taking BRILINTA 5 days before surgery.
This will help to decrease your risk of bleeding with your surgery or procedure. Your healthcare provider should tell you when to start taking BRILINTA again, as soon as possible after surgery. Taking BRILINTA with aspirin BRILINTA is taken with aspirin, unless your healthcare provider specifically tells you otherwise.
Talk to your healthcare provider about the dose of aspirin that you should take with BRILINTA. In most cases, you should not take a dose of aspirin higher than 100 mg daily. Do not take doses of aspirin higher than what your healthcare provider tells you to take.
Tell your healthcare provider if you take other medicines that contain aspirin, and do not take new over-the-counter medicines with aspirin in them. What is BRILINTA? BRILINTA is a prescription medicine used to: • decrease your risk of death, heart attack, and stroke in people with a blockage of blood flow to the heart (acute coronary syndrome or ACS) or a history of a heart attack.
BRILINTA can also decrease your risk of blood clots in your stent in people who have received stents for the treatment of ACS. • decrease your risk of a first heart attack or stroke in people who have a condition where the blood flow to the heart is decreased (coronary artery disease or CAD) who are at high risk for having a heart attack or stroke. • decrease your risk of stroke in people who are having a stroke (acute ischemic stroke) or mini-stroke (transient ischemic attack or TIA). It is not known if BRILINTA is safe and effective in children.
Do not take BRILINTA if you: • have a history of bleeding in the brain • are bleeding now • are allergic to ticagrelor or any of the ingredients in BRILINTA. See the end of this Medication Guide for a complete list of ingredients in BRILINTA. Before taking BRILINTA, tell your healthcare provider about all of your medical conditions, if you: • have had bleeding problems in the past • have had any recent serious injury or surgery • plan to have surgery or a dental procedure.
See “ What is the most important information I should know about BRILINTA?” • have a history of stomach ulcers or colon polyps • have lung problems, such as COPD or asthma • have liver problems • have a history of stroke • are pregnant or plan to become pregnant. It is not known if BRILINTA will harm your unborn baby. You and your healthcare provider should decide if you will take BRILINTA. • are breastfeeding or plan to breastfeed.
It is not known if BRILINTA passes into your breast milk. You should not breastfeed during treatment with BRILINTA. Talk to your healthcare provider ab…